Clinicians › Wrist
Proximal Row Carpectomy
PRC for SLAC/SNAC II and Kienbock: radiocapitate articulation, capitate/lunate-fossa gatekeeping, PRC vs four-corner fusion, capsular interposition, long-term survivorship.
For patients: a plain-language version of this topic is available. See the patient guide.
Overview
Proximal row carpectomy is a dependable, motion-preserving salvage procedure that provides satisfactory pain relief in the majority of patients while maintaining functional wrist motion and grip strength [5]. It is associated with high patient satisfaction and the ability to return to work [5], demonstrating long-term efficacy with good clinical results maintained out to an average of 15 years postoperatively [12, 29]. As a low-risk alternative to total wrist arthrodesis, it offers a low rate of conversion to fusion [10] and provides pain-free function that compares favorably with total or limited carpal fusions [13]. In patients younger than 45 years, the procedure yields improved motion and fewer complications compared to four-corner arthrodesis [8, 14], resulting in slightly better wrist movement and no need for hardware removal [14]. Patients report better function during activities of daily living compared to those undergoing wrist four-corner fusion [6], and existing evidence suggests advantages of greater range of motion, fewer complications, and lower costs compared to scaphoid excision and four-corner arthrodesis for scapholunate advanced collapse arthritis [21]. Among three procedures for this condition, proximal row carpectomy best preserves wrist mobility with a flexion-extension arc of 71° [11].
The procedure is indicated for various pathologic conditions, including stage II SLAC wrist with a preserved capitolunate joint, where it is preferred because it is technically less demanding and yields durable results [25]. It serves as a dependable, low-risk option for patients wishing to retain radiocarpal motion, achieving satisfactory pain relief in 26 of 27 patients [19]. Long-term follow-up confirms that patients older than thirty-five years at the time of surgery maintain satisfactory range of motion, grip strength, and pain relief [16]. Specific indications include the concurrence of Kienbock's Disease and Scapholunate Dissociation after acute wrist trauma [7], advanced Kienböck's disease [4], and avascular necrosis of the scaphoid [3]. While not recommended for the rheumatoid wrist, the procedure may be useful where other pathologic conditions are involved if the remaining articular surfaces are uninvolved [20].
Arthroscopic proximal row carpectomy appears to be a safe, effective, and reliable procedure for a variety of wrist conditions, allowing for rapid mobilization of the wrist compared with the open procedure [27]. The technique can be extended by allograft scaffold interposition arthroplasty, which covers eroded articular surfaces with a dermal allograft scaffold to preclude bone-to-bone contact [43].
Anatomy & Pathophysiology
Bony Anatomy
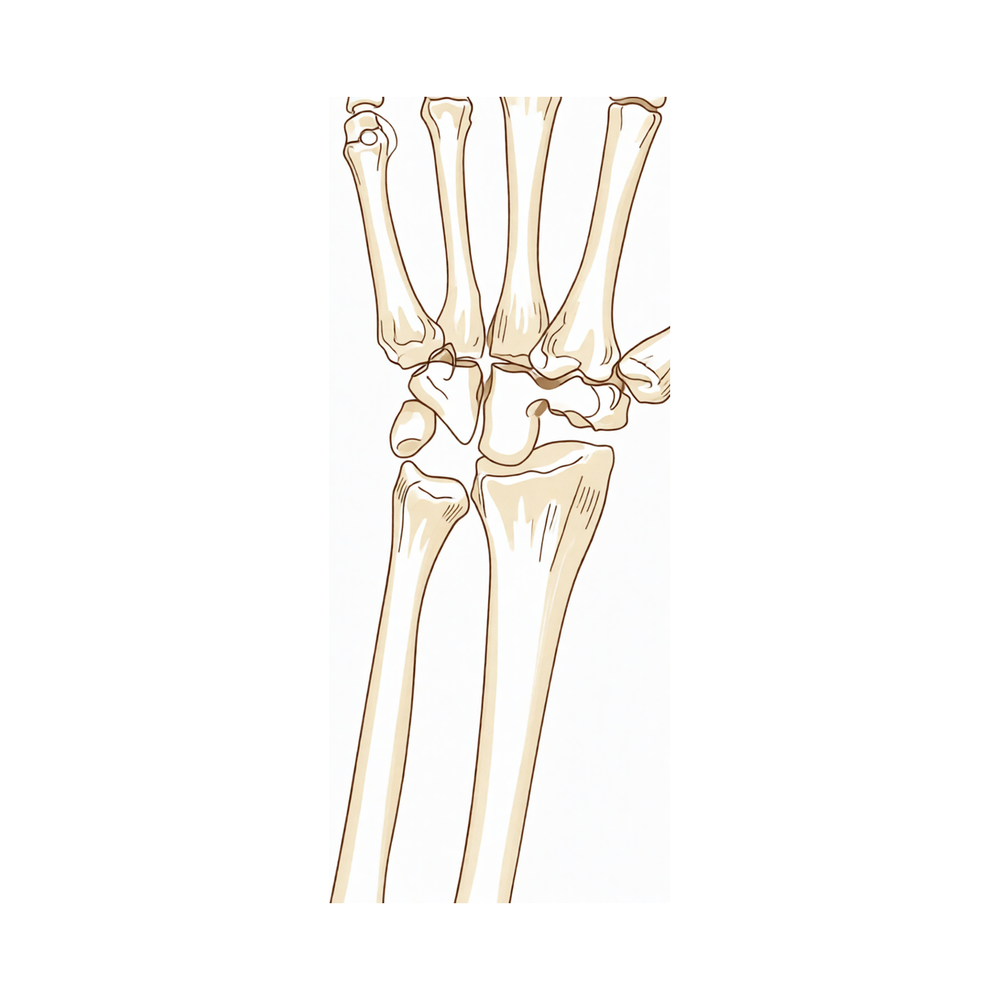
The wrist comprises the distal radioulnar, radiocarpal, and ulnocarpal joints, along with eight carpal bones organized into proximal and distal rows [56]. The proximal row consists of the scaphoid, lunate, triquetrum, and pisiform, while the distal row includes the trapezium, trapezoid, capitate, and hamate [56]. The radiocarpal joints articulate the distal radius with the scaphoid and lunate via concave facets, and with the triquetrum on the triangular fibrocartilage [56]. The distal concave surfaces of the proximal row form midcarpal articulations with the distal row [56]. The distal radius features two concave facets for the scaphoid and lunate, separated by the scapholunate ridge, and a sigmoid notch along the ulnar border for the ulnar head [66]. The distal ulna is covered with hyaline cartilage on its dorsal, lateral, palmar, and distal surfaces, with the ulnar styloid projecting distally from a base containing the fovea for the triangular fibrocartilaginous complex [66]. The distal ulnar convexity articulates at the lesser sigmoid notch of the distal radius, accommodating the ulnar head through two-thirds of its arc with a 20-degree inclination [56]. The ulnar styloid lies dorsal to the ulnar head and extends distally [56].
The scaphoid receives its primary vascular supply from a branch of the radial artery at the dorsal ridge, with smaller vessels entering the palmar tubercle to supply the distal 30% [66]. The lunate is broader palmarly than dorsally and possesses both dorsal and palmar vascular supplies in 80% of wrists, while 20% have only a palmar supply [66]. The triquetrum articulates distally with the hamate, radially with the lunate, and volarly with the pisiform, stabilized to the ulnar fovea by the ulnotriquetral ligament [66]. The hamate consists of a body and a hook (hamulus) that serves as an attachment for the transverse carpal ligament and origins of the flexor digiti minimi and opponens digiti minimi [66]. The capitate head often relies on retrograde vascular supply, and its distal articular surface is divided into three facets by two ridges for articulation with the index, long, and ring finger metacarpals [66]. The trapezoid has two distal facets articulating with the index finger metacarpal [66]. The trapezium features a saddle-shaped articulation with the thumb metacarpal base and a palmar groove for the flexor carpi radialis, bordered laterally by a palmar tuberosity and the transverse carpal ligament attachment [66]. The pisiform is a sesamoid bone within the flexor carpi ulnaris tendon and serves as the origin for the abductor digiti minimi [66].
The concave elliptical distal radius is oriented in the sagittal plane with an average 11-degree volar tilt and a 23-degree radial inclination in the frontal plane [60]. Radial length, measured from the radial styloid tip to the ulnar articular surface, averages 13 mm [60].
Ligaments
Extrinsic carpal ligaments connect the radius or ulna to the carpus, with volar ligaments generally stronger than dorsal ligaments [61]. The radioscaphocapitate (RSC) ligament connects to the scaphoid waist, limiting ulnar carpal translation, while the long radiolunate ligament limits ulnar translocation and the short radiolunate ligament controls lunate position [61]. The radioscapholunate ligament, also known as the ligament of Testut, is a vascular conduit rather than a true ligament [61]. The ulnolunate and ulnotriquetral ligaments attach to the palmar radioulnar ligament and the lunate and triquetrum, respectively [61]. The ulnocapitate ligament attaches to the ulnar head, originates from the volar margin of the ulnar fovea, and is the most superficial or palmar [61]. The dorsal radiocarpal (DRC) or dorsal radiotriquetral ligament has a trapezoidal shape, passing from the dorsal rim of the distal radius to the lunate and triquetrum, with fibers inserting onto the dorsal lunotriquetral interosseous ligament [61]. Damage to the DRC ligament, in conjunction with other intrinsic injuries, confers further carpal instability [61].
Intrinsic carpal ligaments originate and insert within the carpus [61]. The scapholunate interosseous ligament (SLIL) is a major wrist stabilizer and the most commonly injured wrist ligament [61]. It is C-shaped with dorsal, palmar, and interosseous portions, with the dorsal portion being the strongest and thickest [61]. The SLIL provides a flexion force on the lunate due to its attachment to the scaphoid [61]. The lunotriquetral interosseous ligament (LTIL) is also C-shaped, with the volar portion being the thickest and strongest, providing an extension moment on the lunate [61]. The capitohamate ligament is a thick 5 × 5 mm ligament with extensions to the third or fourth metacarpals [61]. The dorsal intercarpal ligament (DIC) passes from the dorsal tubercle of the triquetrum to the distal pole of the scaphoid [61]. Together with the DRC ligament, the DIC reinforces the elastic dorsal wrist capsule and stabilizes the scapholunate articulation via deep fibers contributing to the dorsal SLIL [61]. The space of Poirier is a ligament-free area adjacent to the proximal capitate, situated ulnar to the RSC ligament and radial to the long radiolunate in the carpal tunnel floor [61]. This weak area is vulnerable to instability, allowing the distal carpal row to separate from the lunate during perilunate dislocation [61].
The triangular fibrocartilage complex (TFCC) attaches to the base of the ulnar styloid, separating the hyaline cartilage-covered ulnar head from the styloid [56]. It includes the ulnar collateral ligament, dorsal and volar radioulnar ligaments, articular disc, meniscal homologue, extensor carpi ulnaris sheath, and ulnolunate and ulnotriquetral ligaments [56]. The TFCC is formed by the central meniscus homolog, dorsal and volar radioulnar ligaments, the floor of the extensor carpi ulnaris tendon sheath, and volar ulnocarpal ligaments [66]. It arises from the radial border of the distal radius and inserts into the base of the ulnar styloid and distal ulna through the ligamentum subcruentum [66]. The dorsal and volar radioulnar ligaments are the primary stabilizers of the distal radioulnar joint [66]. Only the peripheral 10% to 40% of the volar, ulnar, and dorsal TFCC has a vascular supply [66].
Specific extrinsic ligament origins and insertions include: Radial collateral ligament: Originates from the radius 0 mm from the radial styloid and inserts on the scaphoid waist and distal palmar trapezium [66]. Radioscaphocapitate ligament: Originates from the radius 4 mm from the radial styloid and inserts on the scaphoid waist and midpalmar capitate [66]. Radiolunatotriquetral ligament: Originates from the radius 10 mm from the radial styloid and inserts on the lunate ± triquetrum [66]. Radioscapholunate ligament: Originates from the mesocapsule at the termination of the anterior interosseous nerve and artery and inserts on the ligament of Testut and Kuenz [66]. Short radiolunate ligament: Originates from the volar-ulnar margin of the radius and inserts on the lunate [66]. Ulnotriquetral ligament: Originates from the volar radioulnar ligament and inserts on the triquetrum [66]. Ulnolunate ligament: Originates from the volar radioulnar ligament and inserts on the lunate [66]. Ulnocapitate ligament: Originates from the volar margin of the ulnar head and inserts on the capitate [66]. Dorsal radiocarpal ligament: Originates from the dorsal radius at the Lister tubercle and inserts on the lunate and triquetrum [66]. It originates at the dorsal lip of the distal radius, adjacent to the dorsal radial tubercle, and traverses the radiocarpal joint obliquely to insert into the lunate and triquetrum [66]. Dorsal intercarpal ligament: Originates from the triquetrum and inserts on the scaphoid, trapezoid, and capitate [66]. It arises from the distal, dorsal surface of the triquetrum and passes across the midcarpal joint to attach to the dorsal surfaces of the scaphoid waist and the trapezoid [56].
There are four types of dorsal radiocarpal ligaments, and dorsal intercarpal ligaments have variable anatomy [56].
Vascular Anatomy
The terminal branches of the radial, ulnar, and anterior interosseous arteries provide extraosseous blood supply to the carpus through three dorsal and three palmar transverse arterial arches with longitudinal connections [69]. Dorsal radiocarpal arch: Located at the radiocarpal joint, supplying the lunate and triquetrum [69]. Dorsal intercarpal arch: The largest arch, located between the proximal and distal carpal rows, supplying the distal carpal row and, through anastomoses with the radiocarpal arch, the lunate and triquetrum [69]. Basal metacarpal arch: Located at the base of the metacarpals, most variable, and supplying the distal carpal row [69]. Palmar radiocarpal arch: Located at the level of the radiocarpal joint on the palmar surfaces of the lunate and triquetrum [69]. Intercarpal arch: Located between the proximal and distal carpal rows, most variable, and does not contribute to nutrient vessels in the carpus [69]. Deep palmar arch: Located at the level of the metacarpal bases, consistent, and communicates with the dorsal basal metacarpal arch and the palmar metacarpal arteries [69].
Kinematics and Biomechanics
The wrist functions as a two-joint system linking the hand (distal carpal row and metacarpals) to the forearm (radius and ulna) around the highly mobile proximal carpal row [67]. The two principal articulations are the radiocarpal and midcarpal joints, situated proximal and distal to the mobile proximal row [67]. The wrist includes multiple articulations: radiocarpal, midcarpal, pisotriquetral, trapeziometacarpal, and carpometacarpal joints [61]. Motion planes include flexion, extension, radial deviation, ulnar deviation, and circumduction, with minimal carpal motion during pronosupination [61].
Approximately 62° of wrist extension occurs through the radiocarpal joint [61]. 62% of wrist flexion occurs through the midcarpal joint [61]. The midcarpal joint is mostly responsible for 20° and 40° of radial and ulnar deviation, respectively [61]. It is also responsible for the “dart thrower’s motion,” involving movement from radial extension into ulnar flexion [61]. In neutral ulnar variance, the radius bears 80% of the axial load transmitted through the radiocarpal joint, while the ulna bears 20% [61]. With axial loading through the neutral wrist, approximately 80% of forces are transmitted through the distal radius (60% scaphoid facet, 40% lunate facet) and 20% through the distal ulna [66].
The proximal row forms an intercalated segment between the distal row and distal radius, bound into a functional unit by the SLIL and LTIL [61]. The distal row is rigid due to stout intercarpal ligaments, acting as a functional unit with the scaphoid bridging both rows [61]. The proximal carpal row has no muscular or tendinous attachments and is an intercalary segment [66]. During wrist flexion from neutral, the distal row flexes and ulnarly deviates slightly while the scaphoid pronates [61]. The proximal row flexes differentially, with more rotation through the scaphoid, followed by the triquetrum and lunate, and translates dorsally [61]. During wrist extension from neutral, the distal row extends and radially deviates slightly while the scaphoid supinates [61]. The proximal row extends differentially, with more motion in the scaphoid, followed by the triquetrum and lunate, and translates palmarly [61]. With ulnar deviation, the proximal row extends relative to the forearm/distal row, while with radial deviation, it flexes [66].
With wrist flexion, 60% of the motion is midcarpal and 40% is radiocarpal [66]. With wrist extension, 33% of the motion is midcarpal and 66% is radiocarpal [66]. Relative contributions to wrist motion were: wrist flexion: RC joint 63%, MC joint 36%; wrist extension: RC joint 53%, MC joint 46% [101]. More than half the motion of the carpus when the wrist was loaded in extension occurred at the midcarpal joint [89]. The dart-thrower’s path of radial extension to ulnar flexion defines the transition between flexion and extension of the scaphoid and lunate, and a path of motion during which proximal row motion approaches zero [67]. The dart-thrower’s motion occurs almost exclusively through the midcarpal joint, with rotation occurring along the mechanical axis of the wrist [67]. All bones of each row rotate in the same plane during any direction of global wrist motion [67]. In all but pure flexion/extension of the uninjured wrist, the proximal and distal rows move in divergent directions [67]. Division of either of the proximal row’s interosseous ligaments in isolation does not result in a postural deformity of the lunate [67]. Similar “collapse” deformities of proximal row alignment (VISI or DISI) can occur with or without disruption of an interosseous ligament (“dissociative” or “nondissociative”) [67].
Classification
SLAC Wrist: Proximal row carpectomy is indicated for stage II SLAC wrist where the capitolunate joint is intact [25, 42]. It serves as a reliable motion-preserving procedure for SLAC wrist [11]. In patients younger than age 45 years, it offers improved motion and fewer complications compared to four-corner arthrodesis [8]. For SLAC/SNAC wrist, the procedure provides advantages of greater range of motion, fewer complications, and lower costs compared to scaphoid excision and four-corner arthrodesis [21]. It yields slightly better wrist movement with fewer surgical complications and no need for hardware removal compared to four-corner arthrodesis [14]. Function during activities of daily living is better compared to wrist four-corner fusion [6]. The procedure achieves a flexion-extension arc of 71°, best preserving wrist mobility among three procedures [11]. Significant changes in radiocarpal loading occur after the procedure [36]. Postoperative immobilisation is not necessary [23]. Long-term efficacy and results have been demonstrated [2, 9]. In rare cases of flexor pollicis longus rupture due to scaphoid nonunion advanced collapse, excellent functional results are achieved when combined with primary flexor pollicis longus tenorrhaphy [28].
SNAC Wrist: Proximal row carpectomy is a reliable motion-preserving procedure for scaphoid nonunion advanced collapse (SNAC) wrist [13]. It provides pain-free function that compares favorably with total or limited carpal fusions for scaphoid nonunion [13].
Kienböck’s Disease: The procedure is a reliable and durable option for patients with Lichtman stage IIIA or IIIB Kienböck's disease [24]. It is a reliable motion-preserving procedure for advanced-stage Kienböck's disease, with good clinical results maintained out to an average of 15 years postoperatively [12]. It is also a reliable motion-preserving procedure for Kienböck’s disease in elderly patients [1] and for advanced Kienböck's disease with satisfactory results [4]. It is selected as the most reliable procedure for the concurrence of Kienbock's Disease and Scapholunate Dissociation after Acute Wrist Trauma [7].
Other Indications: Proximal row carpectomy is a reliable and durable procedure for chronic perilunate dislocations [9, 9]. It is a reliable motion-preserving procedure for avascular necrosis of the scaphoid with satisfactory results [3]. It is a reliable motion-preserving procedure for wrist arthritis, with long-term durability confirmed by systematic review [29]. It is a useful procedure to preserve joint motion of the wrist in selected cases of complete amputation at the wrist joint, achieving good functional results in young individuals [44]. It is a motion-preserving salvage procedure with a low rate of conversion to wrist arthrodesis [10].
Contraindications and General Outcomes: Proximal row carpectomy is not recommended for the rheumatoid wrist [20]. It may be useful for non-rheumatoid pathologic conditions if the remaining articular surfaces are uninvolved [20]. The procedure is a dependable and durable procedure that results in satisfactory pain relief in the majority of patients, maintenance of functional wrist motion and grip strength, high patient satisfaction, and ability to return to work [5].
Clinical Presentation
Proximal row carpectomy serves as a reliable motion-preserving salvage procedure that provides pain-free function comparable to total or limited carpal fusions [13]. It is an acceptable salvage option for the posttraumatic stiff and painful wrist [105] and a reliable treatment for relieving pain and improving function in Kienböck disease [31]. For radiocarpal osteoarthritis, the procedure yields stable outcomes over time, except in young adults and manual laborers who experience a notable early revision rate [103]. In cases of static scapholunate dissociation, however, the procedure results in a stiffened, weakened wrist [30]. The therapeutic approach must meet the patient’s expectations, requiring an in-depth consultation to evaluate needs [106]. It is crucial to establish the patient’s particular needs regarding mobility and/or strength before considering the procedure [106]. The surgical strategy must consider local conditions for arthritis development as well as the patient’s functional requirements [106].
Comparative Outcomes and Functional Preservation
Proximal row carpectomy best preserves wrist mobility, with a flexion-extension arc of 71° among three procedures for scapholunate advanced collapse [11]. Grip strength averaged 94% of the opposite wrist in the proximal row carpectomy group compared to 74% in the four-corner arthrodesis group [35]. Patients report better function during activities of daily living compared to wrist four-corner fusion [6]. Compared to four-corner arthrodesis in patients younger than 45 years, proximal row carpectomy offers improved motion and fewer complications [8]. It also results in slightly better wrist movement with fewer surgical complications and no need for hardware removal [14]. Compared to scaphoid excision and four-corner arthrodesis for scapholunate advanced collapse arthritis, proximal row carpectomy offers greater range of motion, fewer complications, and lower costs [21].
Long-Term Stability and Failure Rates
Post-operative motion and grip strength values appear to remain stable over time [41]. At long-term follow-up, all patients older than thirty-five years at the time of surgery maintained satisfactory range of motion, grip strength, and pain relief [16, 18]. Reported results at a minimum 10-year follow-up consistently show maintenance of strength, motion, and satisfaction with an average conversion rate to radiocarpal arthrodesis of 12% [104]. At a minimum 20-year follow-up, eleven wrists (65%) underwent no further surgery [104]. Ten of eleven patients who did not undergo radiocarpal arthrodesis continued to be satisfied, with minimal decrease in motion and grip strength compared with the uninvolved side [104]. The average time to failure, defined as the time from proximal row carpectomy to radiocarpal arthrodesis, was 11 years (range, 8 mo to 20 y) [104]. All patients returned to their original employment after the procedure [104]. There was no correlation between degenerative radiographic changes and satisfaction level [104]. The predicted probability of failure revealed a higher risk in patients who underwent the procedure for specific indications [104].
Complications and Patient Dissatisfaction
Surgical failure rates with conversion to wrist fusion following proximal row carpectomy occurred early within the post-operative follow-up [41]. Many patients continued to complain of pain requiring daily medication and were unable to return to manual labor [41]. Forty-six patients (74%) were not satisfied with the results due to persistent pain or inability to return to previous occupational activities [41]. Fifty-two patients required daily pain medication for wrist pain [41]. Twelve patients had undergone a wrist arthrodesis following proximal row carpectomy [41]. In a study with a mean follow-up of 97.9 months, seven patients (22%) required revision surgery for wrist fusion after a mean of 18.6 months [103]. Fifteen patients had radiocapitate osteoarthritis in that same cohort [103]. The long-term clinical outcomes of proximal row carpectomy are not well characterized [41].
Radiological Adaptation and Biomechanics
Significant changes in radiocarpal loading occur after proximal row carpectomy [36]. Radiological adaptation in the radiocapitate joint was found in a retrospective study with 3 years’ minimum follow-up [103]. The radiocapitate index went from 0.68 immediately postoperative to 0.74 at the final assessment [103]. In a study with a mean follow-up of 97.9 months, the mean flexion/extension arc was 93° and the mean grip strength was 25 kg [103]. The mean QuickDASH was 29 and the mean Mayo Wrist score was 69 in that cohort [103]. At a minimum 20-year follow-up, the average QuickDASH score was 16 and the Patient-Related Wrist Evaluation score was 26 [104]. The flexion-extension arc was 68°, and grip strength was 72% of the contralateral side at that long-term interval [104].
Indications and Surgical Considerations
Proximal row carpectomy is a motion-sparing procedure for degenerative disorders of the proximal carpal row [104]. It allows patients to have early motion, avoids the risk of complications such as nonunion, and enables potentially improved overall wrist motion for young and high-demand patients [48]. The procedure has gained recent support and its incidence has increased, even in patients under 45 years old [26]. Proximal row carpectomy is a popular procedure for the treatment of wrist arthritis [41]. It can be performed to treat both scaphotrapeziotrapezoid osteoarthritis and Scapho-Lunate Advanced Collapse [113]. Several authors have reported doing proximal row carpectomy or four-corner fusion with scaphoid excision to treat both conditions and achieving good results [113]. Once disease extends outside of the lunate, reconstruction with proximal row carpectomy or partial or total wrist arthrodesis should be considered on the basis of which articular surfaces are affected [47]. Four corner arthrodesis and proximal row carpectomy should not always be standard management for advanced radiocarpal arthritis [33]. Proximal row carpectomy is a useful procedure to preserve joint motion of the wrist in selected cases of complete amputation at the wrist joint [44]. Surgeons should remain vigilant for Kienbock's Disease and Scapholunate Dissociation after wrist trauma [7].
Surgical Technique and Rehabilitation
Proximal row carpectomy by palmar approach allows early rehabilitation with better recovery of wrist motility [46]. Arthroscopic proximal row carpectomy appears to be a safe, effective, and reliable procedure for a variety of wrist conditions, and it allows for rapid mobilization of the wrist compared with the open procedure [27]. Postoperative immobilisation is not necessary after proximal row carpectomy [23]. Simultaneous proximal row carpectomy and radius to distal carpal row arthrodesis did not decrease the postoperative grip strength [34]. Proximal row carpectomy with primary flexor pollicis longus tenorrhaphy yielded excellent functional results for a rare case of flexor pollicis longus rupture due to scaphoid nonunion advanced collapse [28].
Investigations
MRI: Magnetic resonance imaging is the modality of choice for imaging radiographically occult fractures of the hand and wrist [64]. It has an expanding role in evaluating pathologic conditions of the elbow and wrist, requiring high-resolution images best obtained with surface coil technique and a high-field system [81]. A static magnetic field strength of at least 1.5 T using a dedicated wrist coil is recommended for analyzing interosseous, intrinsic, and extrinsic ligament insertions [78]. The volar extrinsic, SL interosseous, dorsal intercarpal, and LT ligaments are best visualized using 1 mm slices (with no interslice gap) in the coronal plane [78]. The DRC and intercarpal ligaments are best viewed on both coronal and sagittal images [78]. Oblique axial views along the longitudinal axes of these ligaments allow further analysis, especially when an injury is suspected [78]. Concomitant cartilage-sensitive imaging is integrative to influence assessment and surgical management, as cartilage integrity influences clinical and surgical management, especially in the setting of SLAC wrist [78].
CT: CT scanning enables the 3D analysis of carpal dysfunction [78]. CT or MR imaging is recommended as the presence or absence of carpal collapse is important for surgical decision-making [128]. CT is more useful than plain X-rays for evaluating partial carpal arthrodesis [136].
Dynamic Imaging: Dynamic fluoroscopy shows abnormal motion between the scaphoid and lunate and changes in the kinematics of the midcarpal joint [78]. Live imaging shows whether the DISI is reducible, giving the physician valuable information as the treatment is planned [78].
Arthroscopy: Arthroscopy is considered by many to be the diagnostic intervention of choice for determining the degree of injury to the wrist and can assess the condition of the cartilage (normal or degenerative), ability to reduce the carpus, and any other associated injuries [78]. The degree of intrinsic and extrinsic ligament injury can be identified from the arthroscopic evaluation [78]. Geissler grade II SLIL injuries tend to be isolated, whereas grade IV injuries often involve complete dorsal extrinsic ligament disruption [78].
Other Considerations: In the wrist, a common indication for MRI is evaluation of the intrinsic carpal ligaments [81]. With proper technique, injuries to the triangular fibrocartilage complex (TFCC) can be demonstrated with MRI [81]. The TFCC is composed of signal-poor fibrocartilage, and perforations in the TFCC appear as linear defects or gaps filled with hyperintense fluid on coronal gradient-echo or T2-weighted pulse sequences [81]. Although evaluation of the scapholunate and lunotriquetral ligaments is more challenging, with optimal technique and equipment the integrity of these structures can be consistently assessed [81]. The addition of arthrographic contrast improves the visualization of these ligaments on MR images [81]. The extrinsic carpal ligaments can be identified with three-dimensional volumetric scanning and subsequent reconstruction [81]. MRI is useful in detecting additional marrow abnormalities in osteonecrosis, as seen in the lunate in Kienböck disease or in the scaphoid after fracture [81]. Asymmetry of marrow signal in proximal and distal fragments of a fractured scaphoid is suggestive of proximal pole ischemia [81]. MRI provides earlier detection of synovitis and erosive bone changes associated with rheumatoid arthritis than do radiographs [81]. The inconsequent use of available modern magnetic resonance imaging (MRI) techniques and the lack of reliable preoperative diagnoses necessitated pure diagnostic arthroscopies for ulnar-sided wrist pain [122]. Preoperative MRI may facilitate the selection of patients with more favorable capitate morphology based on observed variations in capitate morphology and the potential for associated alterations in joint contact forces after proximal row carpectomy [120]. The classification allows surgeons to tailor surgical reconstruction to anatomical findings, such as performing a proximal row carpectomy or radio-scapholunate fusion [32].
Treatment
Non-Operative
The provided evidence does not detail specific conservative management protocols such as weight loss, physical therapy, NSAIDs, or injections.
Operative
Indications: Proximal row carpectomy is indicated primarily in patients with scapholunate advanced collapse wrist or advanced Kienböck disease [132]. It serves as a dependable, low-risk procedure for patients who wish to retain radiocarpal motion [19] and has earned a respected place in the hand surgeon's armamentarium [132]. Although surgical management of wrist arthritis remains controversial, proximal row carpectomy has gained recent support, with increasing incidence even in patients under 45 years old [26]. Prerequisites for the standard procedure include good cartilage on the proximal pole of the capitate and in the lunate fossa of the radius [132]. Articular incongruity in the lunate fossa of the radius is a contraindication [132]. However, X-ray findings of degenerative changes at the lunocapitate and radiolunate joint need not contraindicate the procedure [50]. If there is cartilage damage on the proximal pole of the capitate, the modification of Salomon and Eaton is a reasonable alternative to the standard proximal row carpectomy [132].
Surgical Approach / Technique: The most important surgical step in proximal row carpectomy is preservation of the radioscaphocapitate ligament [132]. For a proximal row carpectomy with a dorsal capsule interposition flap, a 6 to 8 cm dorsal longitudinal incision is placed just ulnar to Lister’s tubercle, centered over the radiocarpal joint and in line with the third ray [141]. The posterior interosseous nerve is identified 1 to 2 cm proximal to the joint and sharply transected with the excision of a short segment [141]. An upside-down U-shaped flap is raised as the joint is arthrotomized, hinging on a 2 to 3 cm wide segment of the dorsal capsule on the distal radius extending from the level of the distal radio-ulnar joint to the base of the radial styloid [141]. A technique combining proximal row carpectomy and rigid internal fixation has proved to be a highly predictable operation with much less morbidity and fewer complications than older techniques using distant bone graft [116].
Adjuncts: The wrist arthroscope can be used as an adjunct to proximal row carpectomy as a preoperative staging procedure to assess the condition of the proximal capitate and the distal radius, to identify supplemental techniques, or to aid the selection of an alternative wrist salvage procedure [45]. Arthroscopy makes it possible to assist with proximal row carpectomy [138]. In situations where residual pain persists after the procedure, arthroscopy can be used to evaluate the status of the proximal capitate, the distal radial articular surface, and the condition of any interposition material introduced during the index procedure [45].
Other Considerations: Proximal row carpectomy best preserves wrist mobility, with a flexion-extension arc of 71° [11]. Compared to 4-Corner Arthrodesis in patients younger than 45 years, proximal row carpectomy offers improved motion and fewer complications [8]. Existing evidence suggests proximal row carpectomy has advantages of greater range of motion, fewer complications, and lower costs compared to scaphoid excision and four-corner arthrodesis for treatment of scapholunate advanced collapse arthritis [21]. Direct surgical costs were 430% greater for 4-corner arthrodesis than proximal row carpectomy, driven primarily by implant costs, despite similar clinical outcomes reported in the literature [51]. Grip strength averaged 74% of the opposite wrist in the four-corner arthrodesis group and 94% in the proximal row carpectomy group [35]. At long-term followup, all patients older than thirty-five years of age at the time of proximal row carpectomy had maintained a satisfactory range of motion, grip strength, and pain relief and were satisfied with the result [18]. Biomechanically, after proximal row carpectomy, contact pressure increases, contact area decreases, and translational motion increases [133]. A technique covering eroded articular surfaces with a dermal allograft scaffold extends traditional indications by precluding bone-to-bone contact [43].
Complications
Comparison with Four-Corner Arthrodesis: Proximal row carpectomy is associated with fewer surgical complications than four-corner arthrodesis [8]. Specifically, proximal row carpectomy results in fewer surgical complications and no need for hardware removal compared to four-corner arthrodesis [14]. The overall complication incidence in the four-corner arthrodesis group was double that of the proximal row carpectomy group [49]. Proximal row carpectomy has a lower rate of complications than four-corner arthrodesis [21]. However, proximal row carpectomy and four-corner arthrodesis have equal rates of postoperative sepsis and reflex sympathetic dystrophy [137]. The FCA patient group had a significantly higher rate of secondary operations, including those for nonunion, symptomatic hardware, and other implant-related issues, when combined with wrist arthrodesis conversion [165].
Specific Complications and Risks: Proximal row carpectomy carries a significantly higher risk of developing further osteoarthritis than four-corner fusion [49]. Consequently, proximal row carpectomy is not an alternative for longstanding scapholunate dissociation (SLAC-Wrist) due to the high incidence of degenerative changes in the midcarpal joint [52]. Functionally, proximal row carpectomy decreases grip strength to 60-80% of normal [108]. Despite these functional limitations, proximal row carpectomy is a low-risk procedure [19]. The procedure avoids the risk of complications such as nonunion [48].
Conversion to Arthrodesis: Proximal row carpectomy has a low rate of conversion to wrist arthrodesis [10]. Conversion to total wrist arthrodesis was significantly more frequent after partial arthrodesis (19%) than after proximal row carpectomy (5%) [49]. In a long-term follow-up study of proximal row carpectomy, twelve patients had undergone a wrist arthrodesis [41].
Recovery
Light activity (weeks): The evidence provided does not specify a typical week range for the resumption of desk work, driving, or light activities of daily living.
Full activity (months): The evidence provided does not specify a month range for the return to manual work, sport, or full range of motion and strength.
Complete recovery / outcome plateau (months): The evidence provided does not specify a month range for the stabilization of pain, strength, and final functional outcomes.
Rehabilitation protocol: The proximal row carpectomy performed via a palmar approach allows for early rehabilitation, which is associated with better recovery of wrist motility [46].
Functional milestones: Proximal row carpectomy best preserves wrist mobility among the three procedures compared, with a flexion-extension arc of 71° [11]. The mean expected motion is about 60% of normal wrist mobility in the relevant age group (40–55 years) [49]. Wrist mobility is generally reported slightly better after proximal row carpectomy than after four-corner arthrodesis [49]. The mean expected grip strength is roughly 70%–75% of the contralateral side [49]. Saltzman et al. (2015) reported mean DASH scores of 21 in patients aged 40–48 years [49]. Patients reported better function during activities of daily living [6].
Other Considerations: At an average follow-up of 10 years, the procedure is reliable and durable for patients with Lichtman stage IIIA or IIIB Kienböck's disease [24]. Proximal row carpectomy results in slightly better movement of the wrist with fewer surgical complications and no need for hardware removal [14]. The procedure has improved motion and fewer complications [8]. Mulford et al. (2009) found good results in terms of pain relief in 84% of patients [49]. However, Mulford et al. (2009) found a significantly higher risk of developing further osteoarthritis after proximal row carpectomy than after four-corner fusion [49]. Saltzman et al. (2015) found that the overall complication incidence in the four-corner arthrodesis group was double that of the proximal row carpectomy group [49]. Mulford et al. (2009) found no significantly higher rate of conversion to total wrist arthrodesis after proximal row carpectomy compared to four-corner fusion [49]. Rahgozar et al. (2017) found that conversion to total wrist arthrodesis was significantly more frequent after partial arthrodesis (19%) than after a proximal row carpectomy (5%) [49]. The mean pivot point shifted proximally 6.8-9.1 mm after proximal row carpectomy for all motions tested [121].
Key Evidence
- [L5] The patient was managed successfully by proximal row carpectomy. [1] (10.1016/j.jhsa.2004.02.013)
- [L4] Our study shows a long-term efficacy of proximal row carpectomy. [2] (10.1016/j.main.2009.10.003)
- [L4] All three patients were treated with proximal row carpectomy with satisfactory results. [3] (10.1016/0363-5023(92)90466-3)
- [L4] Proximal row carpectomy in this group of patients provided satisfactory results. [4] (10.1016/0363-5023(94)90108-2)
- [L4] Proximal row carpectomy is a dependable and durable procedure that results in satisfactory pain relief in the majority of patients, maintenance of functional wrist motion and grip strength, high patient satisfaction, and ability to return to work. [5] (10.1016/s0363-5023(03)00248-x)
- [L3] The patients after proximal row carpectomy reported better function during activities of daily living. [6] (10.1177/1753193416638812)
- [L4] Proximal row carpectomy was selected as the most reliable procedure for this concurrence, and surgeons should remain vigilant for these conditions after wrist trauma. [7] (10.1007/s11552-012-9477-2)
- [L4] Proximal row carpectomy has improved motion and fewer complications. [8] (10.1016/j.jhsa.2017.03.015)
- [L4] [9] (10.1053/jhsu.1999.1231)
- [L3] Proximal row carpectomy is a motion-preserving salvage procedure with a low rate of conversion to wrist arthrodesis. [10] (10.1016/j.jhsa.2021.09.031)
- [L4] Of the three procedures, proximal row carpectomy best preserves wrist mobility, with a flexion-extension arc of 71°. [11] (10.1016/0363-5023(94)90178-3)
- [L4] This study demonstrates proximal row carpectomy to be a reliable motion-preserving procedure with good clinical results maintained out to an average of 15 years postoperatively. [12] (10.1016/j.jhsa.2007.12.010)
- [L4] Proximal row carpectomy has proven to be a reliable motion-preserving salvage procedure that can provide pain-free function that compares favorably with total or limited carpal fusions. [13] (10.1016/s0749-0712(21)01450-5)
- [L3] Proximal row carpectomy seems to result in slightly better movement of the wrist with fewer surgical complications and no need for hardware removal. [14] (10.1016/j.jhsa.2014.12.035)
- [L4] The majority of patients experienced satisfactory pain relief, functional wrist motion, and effective grip strength following proximal row carpectomy. [15] (10.1016/0363-5023(94)90284-4)
- [L4] At the time of long-term follow-up, all patients older than thirty-five years of age at the time of a proximal row carpectomy had maintained a satisfactory range of motion, grip strength, and pain relief and were satisfied with the result. [16] (10.2106/00004623-200411000-00001)
- [L4] Proximal row carpectomy is an effective procedure with regard to pain relief and subjective patient satisfaction. [17] (10.1016/0363-5023(93)90239-y)
- [L4] At the time of long-term followup, all patients older than thirty-five years of age at the time of a proximal row carpectomy had maintained a satisfactory range of motion, grip strength, and pain relief and were satisfied with the result. [18] (10.2106/jbjs.e.00261)
- [L4] Proximal row carpectomy is a dependable, low-risk procedure for patients who wish to retain radiocarpal motion, achieving satisfactory pain relief in 26 of 27 patients. [19] (10.1016/0363-5023(90)90054-u)
- [L4] Proximal row carpectomy is not recommended for the rheumatoid wrist but may be useful where other pathologic conditions are involved if the remaining articular surfaces are uninvolved. [20] (10.1016/0363-5023(91)90007-x)
- [L4] Existing evidence suggests proximal row carpectomy has advantages of greater range of motion, fewer complications and lower costs. [21] (10.1177/17531934241265838)
- [L3] The authors conclude that postoperative immobilisation is not necessary after proximal row carpectomy. [23] (10.1177/1753193408092490)
- [L4] At an average follow-up of 10 years, proximal row carpectomy is a reliable and durable procedure for patients with Lichtman stage IIIA or IIIB Kienböck's disease. [24] (10.1016/j.jhsa.2008.02.031)
- [L4] For stage II SLAC wrist with a preserved capitolunate joint, proximal row carpectomy is preferred because it is technically less demanding and yields durable results. [25] (10.5435/00124635-200307000-00007)
- [L2] Surgical management of wrist arthritis remains a controversial issue, but proximal row carpectomy has gained recent support and its incidence has increased, even in patients under 45 years old. [26] (10.1016/j.jhsa.2023.11.009)
- [L4] Arthroscopic proximal row carpectomy appears to be a safe, effective, and reliable procedure for a variety of wrist conditions, and it allows for rapid mobilization of the wrist compared with the open procedure. [27] (10.1016/j.jhsa.2011.01.009)
- [L5] Proximal row carpectomy with primary FPL tenorrhaphy yielded excellent functional results. [28] (10.1016/j.hansur.2020.10.018)
- [L4] This systematic review confirms the long-term durability of proximal row carpectomy when used for the treatment of wrist arthritis. [29] (10.1055/s-0032-1329547)
- [L4] Proximal row carpectomy, when performed for static scapholunate dissociation, results in a stiffened, weakened wrist. [30] (10.1177/1753193410382719)
- [L5] Traditional surgical procedures such as radial shortening osteotomy and proximal row carpectomy have been shown to be reliable treatment options for relieving pain and improving function. [31] (10.1016/j.jhsa.2012.06.029)
- [L4] The classification allows surgeons to tailor surgical reconstruction to anatomical findings, such as performing a proximal row carpectomy or radio-scapholunate fusion. [32] (10.1097/00130911-200603000-00003)
- [L4] Four corner arthrodesis and proximal row carpectomy should not always be standard management for advanced radiocarpal arthritis. [33] (10.1177/1753193420973322)
- [L4] Simultaneous proximal row carpectomy and radius to distal carpal row arthrodesis did not decrease the postoperative grip strength. [34] (10.1016/0363-5023(94)90175-9)
- [L4] Grip strength averaged 74% of the opposite wrist in the four-corner arthrodesis group and 94% in the proximal row carpectomy group. [35] (10.1016/s0363-5023(05)80144-3)
- [L5] Significant changes in radiocarpal loading occur after proximal row carpectomy. [36] (10.1016/j.jhsa.2004.07.006)
- [L3] [41] (10.1007/s11552-011-9368-y)
- [L4] The procedure is the choice for stage III SLAC wrist, whereas proximal row carpectomy is indicated in stage II SLAC where the capitolunate joint is intact. [42] (10.1053/otor.2003.36321)
- [L5] This technique extends the traditional indications for proximal row carpectomy by covering eroded articular surfaces with a dermal allograft scaffold, thereby precluding bone-to-bone contact. [43] (10.1097/bth.0b013e318220e0b6)
- [L4] Proximal row carpectomy is a useful procedure to preserve joint motion of the wrist in selected cases of complete amputation at the wrist joint, achieving good functional results in young individuals. [44] (10.1007/s11552-008-9141-z)
- [L4] [45] (10.1016/j.hcl.2005.08.006)
- [L4] The proximal row carpectomy by palmar approach allows early rehabilitation with better recovery of wrist motility, while the midcarpal tenodesis shows progressive carpal collapse over time even in the absence of symptoms. [46] (10.1177/1753193418775067)
- [L4] Once disease extends outside of the lunate, reconstruction with proximal row carpectomy or partial or total wrist arthrodesis should be considered on the basis of which articular surfaces are affected. [47] (10.2106/jbjs.24.01090)
- [L5] Proximal row carpectomy allows patients to have early motion, avoids the risk of complications such as nonunion, and enables potentially improved overall wrist motion for young and high-demand patients. [48] (10.2106/jbjs.st.19.00054)
- [L4] [49] (10.1177/1753193419876063)
- [L4] X-ray findings of degenerative changes at the lunocapitate and radiolunate joint need not contraindicate a proximal row carpectomy. [50] (10.1016/s0363-5023(96)80147-x)
- [L3] Direct surgical costs were 430% greater for 4-corner arthrodesis than proximal row carpectomy, driven primarily by implant costs, despite similar clinical outcomes reported in the literature. [51] (10.1016/j.jhsa.2018.06.101)
- [L4] Proximal row carpectomy seems to be no alternative after longstanding scapholunate dissociation (SLAC-Wrist) because of the high incidence of degenerative changes in the midcarpal joint. [52] (10.1016/0266-7681(94)90353-0)
- [L4] More than half the motion of the carpus when the wrist was loaded in extension occurred at the midcarpal joint. [89] (10.1016/j.jhsa.2012.10.035)
- [L5] Relative contributions to wrist motion were: wrist flexion: RC joint 63%, MC joint 36%; wrist extension: RC joint 53%, MC joint 46%. [101] (10.1016/s0363-5023(88)80013-3)
- [Paper] [103] (10.1016/j.otsr.2020.03.038)
- [L4] [104] (10.1016/j.jhsa.2013.04.028)
- [L4] The results of this series demonstrate that proximal row carpectomy is an acceptable salvage procedure in the posttraumatic stiff and painful wrist. [105] (10.1016/s0363-5023(83)80165-8)
- [L5] [106] (10.1016/j.hansur.2020.08.013)
- [L4] [108] (10.1016/0363-5023(93)90043-3)
- [Paper] [113] (10.1016/j.hansur.2020.12.007)
- [L4] This technique of wrist arthrodesis combining proximal row carpectomy and rigid internal fixation has proved to be a highly predictable operation with much less morbidity and fewer complications than with older techniques using distant bone graft. [116] (10.1016/j.jhsa.2012.11.010)
- [L4] Based on observed variations in capitate morphology and the potential for associated alterations in joint contact forces after proximal row carpectomy, preoperative MRI may facilitate the selection of patients with more favorable capitate morphology. [120] (10.1016/j.jhsa.2008.02.021)
- [Paper] The mean pivot point shifted proximally (6.8-9.1 mm) after proximal row carpectomy for all motions tested. [121] (10.1016/j.clinbiomech.2011.03.002)
- [L4] The inconsequent use of available modern magnetic resonance imaging (MRI) techniques and the lack of reliable preoperative diagnoses necessitated pure diagnostic arthroscopies for ulnar-sided wrist pain. [122] (10.1177/1558944716660555hs)
- [L3] CT or MR imaging is recommended as the presence or absence of carpal collapse is important for surgical decision-making. [128] (10.1177/17531934231153966)
- [L4] [132] (10.1016/j.jhsa.2015.04.033)
- [Paper] [133] (10.1007/s11552-008-9086-2)
- [L4] We conclude that CT is more useful than plain X-rays for evaluating partial carpal arthrodesis. [136] (10.1016/s0266-7681(97)80367-1)
- [L4] [137] (10.1016/j.jhsa.2009.06.020)
- [L4] [138] (10.1016/j.otsr.2021.103161)
- [Paper] [141] (10.1097/bth.0b013e3181d44526)
- [L4] In contrast, the FCA patient group had a significantly higher rate of secondary operations, including those for nonunion, symptomatic hardware, and other implant-related issues, when combined with wrist arthrodesis conversion. [165] (10.1055/s-0037-1604395)
See Also
- Kienböck's Disease
References
[1] Kienböck’s disease in an elderly patient treated with proximal row carpectomy. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.02.013
[2] Proximal row carpectomy: Long-term results. Chirurgie de la Main. 2010. DOI: 10.1016/j.main.2009.10.003
[3] Avascular necrosis of the scaphoid: Report of three cases treated with a proximal row carpectomy. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90466-3
[4] Proximal row carpectomy in advanced Kienböck's disease. The Journal of Hand Surgery. 1994. DOI: 10.1016/0363-5023(94)90108-2
[5] Proximal row carpectomy: a minimum 10-year follow-up study. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)00248-x
[6] Comparison of activities of daily living after proximal row carpectomy or wrist four-corner fusion. Journal of Hand Surgery (European Volume). 2016. DOI: 10.1177/1753193416638812
[7] Kienbock's Disease and Scapholunate Dissociation after Acute Wrist Trauma. HAND. 2012. DOI: 10.1007/s11552-012-9477-2
[8] Proximal Row Carpectomy and 4-Corner Arthrodesis in Patients Younger Than Age 45 Years. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.03.015
[9] Long-term assessment of proximal row carpectomy for chronic perilunate dislocations. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.1231
[10] Risk of Total Wrist Arthrodesis Following Proximal Row Carpectomy: An Analysis of 1,070 Patients. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2021.09.031
[11] Surgical treatment of scapholunate advanced collapse. The Journal of Hand Surgery. 1994. DOI: 10.1016/0363-5023(94)90178-3
[12] Treatment of Advanced-Stage Kienböck's Disease With Proximal Row Carpectomy: An Average 15-Year Follow-Up. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2007.12.010
[13] PROXIMAL ROW CARPECTOMY FOR THE TREATMENT OF SCAPHOID NONUNION. Hand Clinics. 2001. DOI: 10.1016/s0749-0712(21)01450-5
[14] Four-Corner Arthrodesis Versus Proximal Row Carpectomy: A Retrospective Study With a Mean Follow-Up of 17 Years. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.12.035
[15] Long-term results following proximal row carpectomy. The Journal of Hand Surgery. 1994. DOI: 10.1016/0363-5023(94)90284-4
[16] Proximal Row Carpectomy: Study with a Minimum of Ten Years of Follow-up. The Journal of Bone and Joint Surgery-American Volume. 2004. DOI: 10.2106/00004623-200411000-00001
[17] Proximal row carpectomy: A multicenter study. The Journal of Hand Surgery. 1993. DOI: 10.1016/0363-5023(93)90239-y
[18] Proximal Row Carpectomy. Journal of Bone and Joint Surgery. 2005. DOI: 10.2106/jbjs.e.00261
[19] Proximal row carpectomy: Clinical evaluation. The Journal of Hand Surgery. 1990. DOI: 10.1016/0363-5023(90)90054-u
[20] Proximal row carpectomy: Review of rheumatoid and nonrheumatoid wrists. The Journal of Hand Surgery. 1991. DOI: 10.1016/0363-5023(91)90007-x
[21] Proximal row carpectomy or scaphoid excision and four-corner arthrodesis for treatment of scapholunate advanced collapse arthritis. Journal of Hand Surgery (European Volume). 2024. DOI: 10.1177/17531934241265838
[23] Proximal Row Carpectomy With or Without Postoperative Immobilisation. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193408092490
[24] Proximal Row Carpectomy for Advanced Kienböck's Disease: Average 10-Year Follow-Up. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2008.02.031
[25] Proximal Row Carpectomy and Intercarpal Arthrodesis for the Management of Wrist Arthritis. Journal of the American Academy of Orthopaedic Surgeons. 2003. DOI: 10.5435/00124635-200307000-00007
[26] A Changing Landscape in the Surgical Management of Wrist Arthritis: An Analysis of National Trends From 2009 to 2019. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2023.11.009
[27] Arthroscopic Proximal Row Carpectomy. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2011.01.009
[28] Proximal row carpectomy combined with primary flexor pollicis longus tenorrhaphy: An effective treatment alternative for a rare case of flexor pollicis longus rupture due to scaphoid nonunion advanced collapse. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.10.018
[29] Long-Term Outcomes of Proximal Row Carpectomy: A Systematic Review of the Literature. Journal of Wrist Surgery. 2012. DOI: 10.1055/s-0032-1329547
[30] Proximal row carpectomy for scapholunate dissociation. Journal of Hand Surgery (European Volume). 2010. DOI: 10.1177/1753193410382719
[31] Kienböck Disease. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.06.029
[32] Arthroscopic Assessment and Classification of Kienbock's Disease. Techniques in Hand & Upper Extremity Surgery. 2006. DOI: 10.1097/00130911-200603000-00003
[33] Management of scapholunate advanced collapse and scaphoid nonunion advanced collapse without proximal row carpectomy or four corner fusion. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420973322
[34] Simultaneous proximal row carpectomy and radius to distal carpal row arthrodesis. The Journal of Hand Surgery. 1994. DOI: 10.1016/0363-5023(94)90175-9
[35] Motion-preserving procedures in the treatment of scapholunate advanced collapse wrist: Proximal row carpectomy versus four-corner arthrodesis. The Journal of Hand Surgery. 1995. DOI: 10.1016/s0363-5023(05)80144-3
[36] Changes in radiocarpal loading characteristics after proximal row carpectomy. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.07.006
[41] Long-Term Outcomes of Proximal Row Carpectomy: A Minimum of 15-Year Follow-up. HAND. 2011. DOI: 10.1007/s11552-011-9368-y
[42] Scaphoid excision and four-corner fusion in the SLAC/SNAC wrist. Operative Techniques in Orthopaedics. 2003. DOI: 10.1053/otor.2003.36321
[43] Proximal Row Carpectomy With Allograft Scaffold Interposition Arthroplasty. Techniques in Hand & Upper Extremity Surgery. 2011. DOI: 10.1097/bth.0b013e318220e0b6
[44] Hand Replantation with Proximal Row Carpectomy. HAND. 2008. DOI: 10.1007/s11552-008-9141-z
[45] Proximal Row Carpectomy. Hand Clinics. 2005. DOI: 10.1016/j.hcl.2005.08.006
[46] Proximal row carpectomy, scaphoidectomy with midcarpal arthrodesis or midcarpal tenodesis: when and how to use. Journal of Hand Surgery (European Volume). 2018. DOI: 10.1177/1753193418775067
[47] Kienböck Disease: Recent Advances in Understanding and Management. Journal of Bone and Joint Surgery. 2025. DOI: 10.2106/jbjs.24.01090
[48] Proximal Row Carpectomy in Young Patients. JBJS Essential Surgical Techniques. 2021. DOI: 10.2106/jbjs.st.19.00054
[49] Functional outcomes after salvage procedures for the destroyed wrist: an overview. Journal of Hand Surgery (European Volume). 2019. DOI: 10.1177/1753193419876063
[50] Proximal row carpectomy with partial capitate resection. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80147-x
[51] Comparison of Direct Surgical Costs for Proximal Row Carpectomy and 4-Corner Arthrodesis. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.06.101
[52] Advanced Carpal Collapse after Longstanding Scaphoid Nonunion (SNAC-Wrist) and Longstanding Scapho-Lunate Dissociation (SLAC-Wrist)—Where are the Differences?. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90353-0
[56] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > ANATOMY.
[60] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > FRACTURES AND DISLOCATIONS OF THE DISTAL AND MID-FOREARM.
[61] Aaos Comprehensive Orthopaedic Review 3. Carpal Instability* > II. Anatomy and Biomechanics (See Chapter 92).
[64] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Imaging: Advances in Imaging of the Hand and Upper Extremity > Magnetic Resonance Imaging.
[66] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Hand and Wrist > VII. The Wrist.
[67] Green S Operative Hand Surgery. WRIST BIOMECHANICS > Carpal Kinematics.
[69] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > CIRCULATION.
[78] Green S Operative Hand Surgery. Advanced Imaging.
[81] Campbell S Operative Orthopaedics 4 Volume Set. WRIST AND ELBOW.
[89] In Vivo Kinematics of the Scaphoid, Lunate, Capitate, and Third Metacarpal in Extreme Wrist Flexion and Extension. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2012.10.035
[101] An in vitro analysis of wrist motion: The effect of limited intercarpal arthrodesis and the contributions of the radiocarpal and midcarpal joints. The Journal of Hand Surgery. 1988. DOI: 10.1016/s0363-5023(88)80013-3
[103] Long-term radiological changes and functional outcomes after proximal row carpectomy: Retrospective study with 3 years’ minimum follow-up. Orthopaedics & Traumatology: Surgery & Research. 2020. DOI: 10.1016/j.otsr.2020.03.038
[104] Proximal Row Carpectomy: Minimum 20-Year Follow-Up. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2013.04.028
[105] Proximal row carpectomy for posttraumatic disorders of the carpus. The Journal of Hand Surgery. 1983. DOI: 10.1016/s0363-5023(83)80165-8
[106] Trapeziometacarpal osteoarthritis and arthritis of the wrist. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.08.013
[108] Wrist arthrodesis in post-traumatic arthritis: A comparison of two methods. The Journal of Hand Surgery. 1993. DOI: 10.1016/0363-5023(93)90043-3
[113] Scaphotrapeziotrapezoid osteoarthritis: From the joint to the patient. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.12.007
[116] Modified AO Arthrodesis of the Wrist (With Proximal Row Carpectomy). The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2012.11.010
[120] MRI Study of the Capitate, Lunate, and Lunate Fossa With Relevance to Proximal Row Carpectomy. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2008.02.021
[121] Effects of proximal row carpectomy on wrist biomechanics: A cadaveric study. Clinical Biomechanics. 2011. DOI: 10.1016/j.clinbiomech.2011.03.002
[122] Preventable Repeat Wrist Arthroscopies. HAND. 2016. DOI: 10.1177/1558944716660555hs
[128] Diagnostic performance of traditional radiographic indices in detection of carpal collapse in Kienböck’s disease. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231153966
[132] Proximal Row Carpectomy. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.04.033
[133] AAHS Abstracts. HAND. 2008. DOI: 10.1007/s11552-008-9086-2
[136] Computed Tomography in Partial Carpal Arthrodesis. Journal of Hand Surgery. 1997. DOI: 10.1016/s0266-7681(97)80367-1
[137] Management of Scapholunate Advanced Collapse Pattern of Degenerative Arthritis of the Wrist. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2009.06.020
[138] Kienböck's disease in 2021. Orthopaedics & Traumatology: Surgery & Research. 2022. DOI: 10.1016/j.otsr.2021.103161
[141] Proximal Row Carpectomy With a Dorsal Capsule Interposition Flap. Techniques in Hand & Upper Extremity Surgery. 2010. DOI: 10.1097/bth.0b013e3181d44526
[165] Long-Term Outcome and Secondary Operations after Proximal Row Carpectomy or Four-Corner Arthrodesis. 2017. DOI: 10.1055/s-0037-1604395