Clinicians › General-Health
Nerve Conduction Studies: Interpretation
A clinician teaching reference: how to read NCS/EMG, representative normal values, and condition patterns.
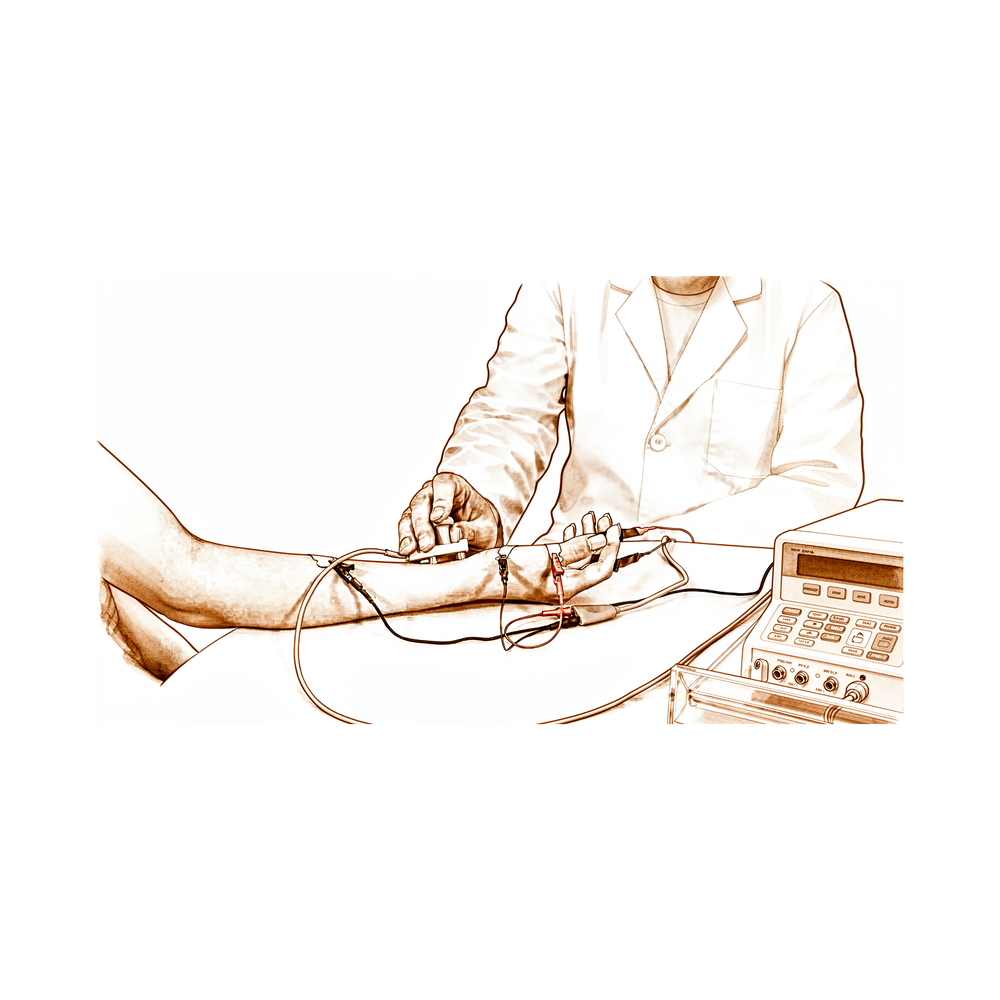
Overview
Nerve conduction studies quantify impaired nerve function and serve as the best available indicator of overall disease severity, offering some prognostic value for surgical outcome [1]. Early detection through these studies facilitates more timely treatment and increases the incidence of recovery [2]. While there is no universally agreed-upon reference standard for diagnosing carpal tunnel syndrome, clinicians rely on symptoms and signs alone, electrodiagnostic testing, or both [58]. The primary value of preoperative nerve conduction studies lies in obtaining the correct diagnosis and determining the severity of median nerve disease, rather than predicting postoperative outcome [6]. This diagnostic utility remains valid even when electrodiagnostic results do not correlate with final symptomatic outcomes after carpal tunnel release [10, 62].
Electrodiagnostic tests provide significantly more information regarding nerve condition and function than ultrasonography [15]. Although ultrasound and nerve conduction studies yield a similar number of patients within 10% of their diagnostic threshold values [5], median nerve ultrasonography measurements distinguish between normal and abnormal electrodiagnostic studies and correlate with electrodiagnostic severity categories [55]. Comparison of sensory nerve responses is more effective than using absolute median nerve latency for documenting median nerve abnormalities [8]. However, the definition of abnormal median sensory nerve conduction distinguishes a subset of patients who appear to benefit from surgical treatment [4]. In the absence of other objective evidence of median nerve dysfunction, referring working-age patients with suspected carpal tunnel syndrome for nerve conduction studies offers little value if they are negative on both Tinel's and Phalen's tests [3].
Diagnosis of mild or moderate idiopathic median neuropathy at the carpal tunnel is less accurate and reliable than severe cases due to the subjective nature of symptoms and the imprecision of objective tests near normal margins [66]. Consequently, highly sensitive tests are required to assess or exclude the diagnosis in one quarter of carpal tunnel syndrome cases [65]. Clinical, electrodiagnostic, and physical examination criteria require better definition to avoid inaccurate diagnoses and unnecessary surgeries [21]. When signs and symptoms suggest mild-to-moderate median neuropathy and surgery is being considered, patients and clinicians might consider additional testing, such as electrodiagnostic studies or ultrasound, to increase the probability of actual median neuropathy that can benefit from surgery [23]. The selection of an appropriate electrical screening test depends on the prevalence and seriousness of the target disease and the relative consequences of over- and underdiagnosis [19].
How It Works
Electrodiagnostic studies comprise nerve conduction studies and needle electromyography, which are used to characterize, localize, and monitor nerve pathology and healing [11]. Nerve conduction studies measure local electrical gradients [12], while needle electromyography evaluates muscle activity at rest and during contraction to detect denervation [12]. These modalities are useful in confirming and localizing suspected entrapment neuropathy, radiculopathy, and polyneuropathy [36], as well as defining the severity and distribution of injury in nerve trauma [36]. When combined with clinical findings, electrodiagnostic studies significantly improve diagnostic reliability for compressive neuropathies [14].
Clinicians must understand nerve conduction studies as a measure of impaired nerve function rather than a test that determines the diagnosis [1]. They serve as the best available indicator of overall disease severity and possess some prognostic value for surgical outcome [1]. In ulnar neuropathy at the elbow, absolute slowing of conduction velocity in the across-elbow segment is a better method for identification than relative slowing compared with the forearm segment [44].
Reporting and Methodology: There is variability regarding the thoroughness of electrodiagnostic studies and the quality of information in reports [17]. EDX reports should specifically indicate abnormalities of latency and conduction and present a clear description of the probable pathophysiologic processes rather than just compiling slight abnormalities [42]. Traditional methods of electrodiagnosis currently produce results that are more accurate and informative than newer techniques [31]. Ultrasound may be a feasible alternative as the first-line confirmatory test, although it may not replace electrodiagnostic testing as the most sensitive and specific test [20]. Ultrasound helps detect the relationship of the nerve with neighbouring tissues, especially in patients still symptomatic after surgery, and can help explain surgical failures [38].
Clinical Application in Carpal Tunnel Syndrome: In the absence of other objective evidence of median nerve dysfunction, there is little value in referring patients of working age with suspected CTS for nerve conduction studies if they are negative on both Tinel's and Phalen's tests [3]. Neurophysiological studies contribute little to the diagnosis in typical cases of carpal tunnel syndrome and are more often confounding than of assistance [18]. The results of carpal tunnel release in patients with typical symptoms are no better after nerve conduction studies, and therefore nerve conduction studies can be omitted in these cases [41]. However, the authors argue that the electrodiagnostic criteria used in the referenced study were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in CTS [7]. This does not negate the value of electrodiagnostic testing [10]. The author continues to use electrodiagnostic studies as part of a clinical evaluation process and considers this a reasonable way to practice medicine [16]. The author proposes that the clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries [21].
Prognostic and Intraoperative Utility: Amplitudes of compound muscle action potential and sensory nerve action potential before surgery induced by palmar stimulation can predict improvements in nerve conduction study scores and clinical findings after surgical treatment [28]. Although both clinical outcome and electrophysiological findings improved significantly after surgery, there was no correlation between improvements in nerve conduction and Boston Questionnaire scores [29]. While patients with normal studies showed significant improvement in QuickDASH scores after carpal tunnel release, the improvement was not as great as in those with abnormal studies [39]. Electrodiagnostic studies performed preoperatively and during surgery complement one another and clinical/imaging studies to better define the number, location, and severity of plexus lesions [40].
What the Evidence Shows
Diagnostic Role and Interpretation
Nerve conduction studies (NCS) function as a measure of impaired nerve function and serve as the best available indicator of overall disease severity, rather than a test that determines the diagnosis [1]. Electrodiagnostic studies objectively examine the physiologic status of a nerve, utilizing NCS and electromyography to characterize, localize, and monitor nerve pathology and healing [11]. While NCS measure local electrical gradients, needle EMG evaluates muscle activity at rest and during contraction to detect denervation [12]. In-office NCS detect median neuropathy with clinically relevant accuracy, demonstrating performance similar to interexaminer agreement in traditional electrodiagnostic laboratories [47]. However, using the clinical diagnosis of carpal tunnel syndrome (CTS) as the criterion standard, NCS demonstrated moderate sensitivity and specificity and a low positive predictive value in population-based CTS [34]. Evidence remains inconclusive regarding which sensory or motor test for CTS diagnosis offers the highest diagnostic accuracy [68]. Furthermore, some authors argue that electrodiagnostic criteria used in referenced studies were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in CTS [7].
Clinical Utility and Limitations
In the absence of other objective evidence of median nerve dysfunction, there is little value in referring patients of working age with suspected CTS for NCS if they are negative on both Tinel's and Phalen's tests [3]. NCS are considered an unnecessary luxury in patients with a firm clinical diagnosis of CTS, as they do not improve outcomes and their lack of standardization and reproducibility cannot be justified in the age of evidence-based medicine [25]. While peripheral nerve injuries can be managed without electromyography, the diagnostic aid has gained additional confidence in both diagnosis and prognosis [33]. The diagnostic value of provocative tests in ulnar neuropathy at the elbow is poor and should not be recommended for clinical decision making [69].
Prognostic Value and Outcomes
NCS possess some prognostic value for surgical outcome [1]. Early detection via NCS allows for more timely treatment and increased incidence of recovery in thoracic outlet syndrome [2]. A significant correlation exists between improvement in sensory nerve conduction velocity and clinical improvement at follow-up [49]. Conversely, no relationship was found between pre-operative symptoms or nerve conduction impairment and the outcome of surgery or time to resolution of symptoms [48]. The incidence of acquisition of postoperative electrodiagnostic studies after carpal tunnel release is substantial when the prevalence of preoperative studies is high, supporting the utility of baseline electrodiagnostic studies for future comparison [59].
Impact on Management and Treatment
Electrodiagnostic study severity had a direct relationship to the probability of receiving surgery but did not correlate with use of nonsurgical treatment [60]. Treatment plans changed in 19% of patients based on electrodiagnostic test results [61]. Clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries [21]. Patients with clinical features of CTS but normal NCS reported significant improvements in patient-reported outcomes at 1 year after decompression, although the improvement was significantly less than that observed in patients with abnormal NCS [46]. Patients who clinically have ulnar nerve compression still benefit from ulnar nerve decompression despite normal nerve conduction tests [50]. The absence of any real difference in nerve conduction time between the working group with symptoms and the group with diagnosed CTS indicates a high probability that many of the participants with symptoms would have had abnormal findings on standard electrodiagnostic tests [26].
Comparison with Ultrasound
Although ultrasound may not replace electrodiagnostic testing as the most sensitive and specific test, it may be a feasible alternative as the first-line confirmatory test [20]. Ultrasound is a valid alternative confirmatory test compared with electrodiagnostic studies in detecting ulnar neuropathy at the elbow [53]. A large-scale, randomized controlled trial is required to determine the effects of sonography on clinical outcomes, the number of nerve conduction studies performed, and the total cost [13].
Practical Considerations
Nerve conduction studies function as a measure of impaired nerve function and the best available indicator of overall disease severity, rather than a test that determines the diagnosis [1]. When performed appropriately alongside clinical assessment, neurophysiologic evaluation contributes significantly to the evaluation of patients with peripheral nervous system complaints [54]. Although newer techniques hold potential, traditional methods of electrodiagnosis currently produce results that are more accurate and informative [31]. It is important to review data and continue to critically evaluate outcomes to determine the best practices in restoring function in patients with atraumatic nerve palsy [30].
Diagnostic Utility and Limitations: Electrodiagnostic criteria used in some referenced studies were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in carpal tunnel syndrome [7]. The absence of any real difference in nerve conduction time between the working group with symptoms and the group with diagnosed CTS indicates a high probability that many of the participants with symptoms would have had abnormal findings on standard electrodiagnostic tests [26]. When signs and symptoms suggest mild-to-moderate median neuropathy and surgery is being considered, patients and clinicians might consider additional testing, such as EDS or US, to increase the probability of actual median neuropathy that can benefit from surgery [23].
Prognostic Value and Treatment Implications: Nerve conduction studies have some prognostic value for surgical outcome in carpal tunnel syndrome [1]. The value of electrodiagnostic testing is not negated by the lack of predictive value for postoperative outcome [10]. Early detection via nerve conduction studies allows for more timely treatment and an increased incidence of recovery in thoracic outlet syndrome [2]. The best current evidence suggests that corticosteroid injections provide minimal transient improvement in nerve conduction and symptomatology compared with placebo or wrist splints [22].
Procedural and Systemic Factors: Once clinical experience in the placement of microelectroneurography electrodes has been obtained, the incidence of paresthesia will remain at 10% or less [51]. Revision procedures for persistent and recurrent cubital tunnel syndrome result in pain relief and paresthesia reduction in approximately 75% of patients, but results are inferior compared with primary procedures [32]. Similar variation exists in the use of electrodiagnostic testing based on insurance type [56].
Key Evidence
- [L5] Nerve conduction studies should be understood not as a test that determines the diagnosis but as a measure of impaired nerve function, serving as the best available indicator of overall disease severity with some prognostic value for surgical outcome. [1] (10.1177/17531934231191685)
- [L5] It emphasizes that early detection via nerve conduction studies allows for more timely treatment and increased incidence of recovery. [2] (10.1016/s0749-0712(03)00089-1)
- [L3] In the absence of other objective evidence of median nerve dysfunction, there is little value in referring patients of working age with suspected CTS for nerve conduction studies if they are negative on both Tinel's and Phalen's tests. [3] (10.1186/1471-2474-14-242)
- [L2] The definition of abnormal median sensory nerve conduction distinguished a subset of patients who appeared to benefit from surgical treatment. [4] (10.1186/1471-2474-14-241)
- [L3] Ultrasound and nerve conduction studies yielded a similar number of patients within 10% of their diagnostic threshold values. [5] (10.1177/1558944720964963)
- [L5] The value of preoperative nerve conduction studies lies in obtaining the correct diagnosis and determining the severity of the median nerve disease, not in predicting postoperative outcome. [6] (10.1016/s0363-5023(96)80384-4)
- [L5] The authors argue that the electrodiagnostic criteria used in the referenced study were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in CTS. [7] (10.1067/jhsu.2000.jjhsu00025a1le01)
- [L5] Comparison of sensory nerve responses is more effective than the use of an absolute median nerve latency in documenting median nerve abnormalities. [8] (10.1002/mus.22208)
- [L3] The questionnaire demonstrated a sensitivity of 82% and specificity of 67% when compared to nerve conduction studies. [9] (10.1177/1753193409105566)
- [L5] This does not negate the value of electrodiagnostic testing. [10] (10.1016/s0363-5023(96)80222-x)
- [L5] Electrodiagnostic studies (EDS) are powerful tools used to objectively examine the physiologic status of a nerve, consisting of nerve conduction studies and electromyography to characterize, localize, and monitor nerve pathology and healing. [11] (10.1016/j.hcl.2013.04.005)
- [L5] The text outlines that nerve conduction studies measure local electrical gradients and that needle EMG evaluates muscle activity at rest and during contraction to detect denervation. [12] (10.1016/s0749-0712(01)00009-9)
- [L2] A large-scale, randomized controlled trial is required to determine the effects of sonography on clinical outcomes, the number of nerve conduction studies performed, and the total cost. [13] (10.1002/art.20723)
- [L5] Electrodiagnostic studies, when used in combination with clinical findings, can improve diagnostic reliability significantly for compressive neuropathies. [14] (10.1016/s0749-0712(21)00305-x)
- [L2] Electrodiagnostic tests provide significantly more information than ultrasonography regarding the condition and function of the nerve. [15] (10.1177/1753193413489046)
- [L5] The author continues to use electrodiagnostic studies as part of a clinical evaluation process and considers this a reasonable way to practice medicine. [16] (10.1016/s0363-5023(96)80380-7)
- [L4] There is variability with respect to the thoroughness of electrodiagnostic studies and in the quality of information in the reports. [17] (10.1016/s0363-5023(98)80089-0)
- [L3] Neurophysiological studies contribute little to the diagnosis in typical cases of carpal tunnel syndrome and are more often confounding than of assistance. [18] (10.1054/jhsb.2000.0496)
- [L3] The selection of an appropriate electrical screening test for peripheral nerve injury, such as entrapment neuropathy, depends on the prevalence and seriousness of the target disease and the relative consequences of over- and underdiagnosis. [19] (10.1016/s0363-5023(96)80165-1)
- [L1] Although ultrasound may not replace electrodiagnostic testing as the most sensitive and specific test, it may be a feasible alternative as the first-line confirmatory test. [20] (10.1007/s11999-010-1637-5)
- [L5] The author proposes that the clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries. [21] (10.1016/s0363-5023(05)80209-6)
- [L1] The best current evidence suggests that corticosteroid injections provide minimal transient improvement in nerve conduction and symptomatology compared with placebo or wrist splints. [22] (10.1177/17531934241240380)
- [L3] When signs and symptoms suggest mild-to-moderate median neuropathy and surgery is being considered, patients and clinicians might consider additional testing, such as EDS or US, to increase the probability of actual median neuropathy that can benefit from surgery. [23] (10.1097/corr.0000000000002751)
- [L5] Nerve conduction studies are an unnecessary luxury in patients with a firm clinical diagnosis of carpal tunnel syndrome, as they do not improve outcomes and their lack of standardization and reproducibility cannot be justified in the age of evidence-based medicine. [25] (10.1054/jhsb.2001.0669)
- [L3] The absence of any real difference in nerve conduction time between the working group with symptoms and the group with diagnosed CTS indicates a high probability that many of the participants with symptoms would have had abnormal findings on standard electrodiagnostic tests. [26] (10.1016/0363-5023(92)90116-7)
- [L3] Amplitudes of compound muscle action potential and sensory nerve action potential before surgery induced by palmar stimulation can predict improvements in nerve conduction study scores and clinical findings after surgical treatment. [28] (10.1186/s12891-020-03750-z)
- [L3] Although both clinical outcome and electrophysiological findings improved significantly after surgery, there was no correlation between improvements in nerve conduction and Boston Questionnaire scores. [29] (10.1054/jhsb.2002.0762)
- [Commentary] It is important to review our data and continue to critically evaluate our outcomes to determine the best practices in restoring function in our patients with atraumatic nerve palsy. [30] (10.1016/j.jhsa.2017.07.027)
- [L5] Although newer techniques hold potential, traditional methods of electrodiagnosis currently produce results that are more accurate and informative. [31] (10.1016/j.jhsa.2007.07.021)
- [L4] Revision procedures result in pain relief and paresthesia reduction in approximately 75% of patients, but results are inferior compared with primary procedures. [32] (10.1016/j.jhsa.2018.03.057)
- [L4] The authors state that while peripheral nerve injuries can be managed without electromyography, the diagnostic aid has gained them additional confidence in both diagnosis and prognosis. [33] (10.2106/00004623-196244060-00001)
- [L3] Using the clinical diagnosis of CTS as the criterion standard, nerve conduction tests had moderate sensitivity and specificity and a low positive predictive value in population-based CTS. [34] (10.1186/1471-2474-4-9)
- [L5] Nerve conduction studies and needle electromyography are extremely useful in confirming and localizing suspected entrapment neuropathy, radiculopathy, and polyneuropathy, and in defining the severity and distribution of injury in nerve trauma. [36] (10.5435/00124635-200407000-00008)
- [Commentary] US helps detect the relationship of the nerve with neighbouring tissues, especially in patients still symptomatic after surgery, and can help explain surgical failures. [38] (10.1177/1753193413513524)
- [L5] The letter discusses the interpretation of nerve conduction studies and notes that while patients with normal studies showed significant improvement in QuickDASH scores after carpal tunnel release, the improvement was not as great as in those with abnormal studies. [39] (10.1177/1753193420967839)
- [L5] Electrodiagnostic studies performed preoperatively and during surgery complement one another and clinical/imaging studies to better define the number, location, and severity of plexus lesions. [40] (10.1016/j.hcl.2004.09.003)
- [L1] The results of carpal tunnel release in patients with typical symptoms are no better after nerve conduction studies, and therefore nerve conduction studies can be omitted in these cases. [41] (10.1177/1753193412445162)
- [L5] EDX reports should specifically indicate abnormalities of latency and conduction and present a clear description of the probable pathophysiologic processes rather than just compiling slight abnormalities. [42] (10.1016/s0363-5023(96)80298-x)
- [L4] The study concludes that absolute slowing of conduction velocity in the across-elbow segment is a better method for identification of ulnar neuropathy at the elbow than relative slowing compared with the forearm segment. [44] (10.1002/mus.10513)
- [L3] Patients with clinical features of carpal tunnel syndrome but normal nerve conduction studies reported significant improvements in patient-reported outcomes at 1 year after decompression, although the improvement was significantly less than that observed in patients with abnormal nerve conduction studies. [46] (10.1177/1753193419866646)
- [L1] This meta-analysis showed that in-office NCS detects median neuropathy with clinically relevant accuracy, with performance similar to interexaminer agreement in traditional electrodiagnostic laboratories. [47] (10.1016/j.jhsa.2010.09.012)
- [L3] No relationship was found between pre-operative symptoms or nerve conduction impairment and the outcome of surgery or time to resolution of symptoms. [48] (10.1054/jhsb.2001.0616)
- [L3] There was a significant correlation between improvement in sensory nerve conduction velocity and clinical improvement at follow-up. [49] (10.1054/jhsb.2000.0376)
- [L2] We conclude that patients who clinically have ulna nerve compression still benefit from ulna nerve decompression despite normal nerve conduction tests. [50] (10.1142/s0218810415500215)
- [L5] Once clinical experience in the placement of these electrodes has been obtained, the incidence of paresthesia will remain at 10% or less. [51] (10.1016/s0363-5023(79)80166-5)
- [L4] Ultrasound is a valid alternative confirmatory test compared with electrodiagnostic studies in detecting ulnar neuropathy at the elbow. [53] (10.1016/j.jhsa.2023.08.014)
- [L5] When performed appropriately with a clinical assessment, it contributes significantly to the evaluation of patients with peripheral nervous system complaints. [54] (10.5435/00124635-200005000-00006)
- [L3] Median nerve ultrasonography measurements not only distinguished between normal and abnormal electrodiagnostic studies but also correlated with the category of electrodiagnostic severity. [55] (10.5435/jaaos-d-17-00557)
- [L3] Similar variation exists in the use of electrodiagnostic testing based on insurance type. [56] (10.1016/j.jhsa.2018.11.001)
- [L2] There is no universally agreed-upon reference standard test for diagnosing carpal tunnel syndrome, and clinicians use symptoms and signs alone, electrodiagnostic testing, or both. [58] (10.1016/j.jhsa.2014.03.039)
- [L4] The incidence of acquisition of postoperative electrodiagnostic studies after carpal tunnel release is substantial when the prevalence of preoperative studies is high, supporting the utility of baseline electrodiagnostic studies for future comparison. [59] (10.1177/1753193418815546)
- [L2] Electrodiagnostic study severity had a direct relationship to the probability of receiving surgery but did not correlate with use of nonsurgical treatment. [60] (10.1016/j.jhsa.2020.08.020)
- [L3] Treatment plan changed in 19% of patients based on electrodiagnostic test results. [61] (10.1177/1753193413497903)
- [L3] Given specific clinical criteria for establishing the diagnosis of carpal tunnel syndrome, electrodiagnostic testing does not appear to correlate with improved final symptomatic outcome after carpal tunnel release. [62] (10.1016/s0363-5023(96)80164-x)
- [L2] The best sensitivity for a case definition of carpal tunnel syndrome was a history of nocturnal awakenings with paresthesias in median nerve–served digits, while the specificity of continuous tingling/numbness was high at 97.5%. [64] (10.5435/jaaos-d-17-00034)
- [L3] Highly sensitive tests are required to assess or exclude the diagnosis in one quarter of cases of carpal tunnel syndrome. [65] (10.1016/0266-7681(94)90245-3)
- [L5] Diagnosis of mild or moderate idiopathic median neuropathy at the carpal tunnel is less accurate and reliable than severe cases due to the subjective nature of symptoms and the imprecision of objective tests near normal margins. [66] (10.1016/j.jhsa.2023.06.003)
- [L1] The evidence was inconclusive on which sensory or motor test for CTS diagnosis had the highest diagnostic accuracy. [68] (10.1186/s12891-021-04202-y)
- [L2] The diagnostic value of provocative tests in ulnar neuropathy at the elbow is poor and should not be recommended for clinical decision making. [69] (10.1136/jnnp.2009.180844)
References
[1] Use of nerve conduction studies in carpal tunnel syndrome. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231191685
[2] “EMG” for thoracic outlet syndrome. Hand Clinics. 2004. DOI: 10.1016/s0749-0712(03)00089-1
[3] Symptoms, signs and nerve conduction velocities in patients with suspected carpal tunnel syndrome. BMC Musculoskeletal Disorders. 2013. DOI: 10.1186/1471-2474-14-242
[4] Impact of carpal tunnel surgery according to pre-operative abnormality of sensory conduction in median nerve: a longitudinal study. BMC Musculoskeletal Disorders. 2013. DOI: 10.1186/1471-2474-14-241
[5] Comparison of Borderline Ultrasound and Nerve Conduction Studies for Carpal Tunnel Syndrome. HAND. 2020. DOI: 10.1177/1558944720964963
[6] Electrical studies as a prognostic factor in the surgical treatment of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80384-4
[7] Diagnostic testing in carpal tunnel syndrome. The Journal of Hand Surgery. 2000. DOI: 10.1067/jhsu.2000.jjhsu00025a1le01
[8] Electrodiagnostic evaluation of carpal tunnel syndrome. Muscle & Nerve. 2011. DOI: 10.1002/mus.22208
[9] Assessment of a diagnostic questionnaire and protocol for management of carpal tunnel syndrome. Journal of Hand Surgery (European Volume). 2009. DOI: 10.1177/1753193409105566
[10] Electrical studies as a prognostic factor in carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80222-x
[11] Timing and Appropriate Use of Electrodiagnostic Studies. Hand Clinics. 2013. DOI: 10.1016/j.hcl.2013.04.005
[12] Electrodiagnosis in carpal tunnel syndrome. Hand Clinics. 2002. DOI: 10.1016/s0749-0712(01)00009-9
[13] Diagnostic value of sonography in patients with suspected carpal tunnel syndrome: A prospective study. Arthritis & Rheumatism. 2005. DOI: 10.1002/art.20723
[14] GENERAL PRINCIPLES AND USE OF ELECTRODIAGNOSTIC STUDIES IN CARPAL AND CUBITAL TUNNEL SYNDROMES. Hand Clinics. 1996. DOI: 10.1016/s0749-0712(21)00305-x
[15] No correlation between sonographic and electrophysiological parameters in carpal tunnel syndrome. Journal of Hand Surgery (European Volume). 2013. DOI: 10.1177/1753193413489046
[16] Electrical studies as a prognostic factor in the surgical treatment of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80380-7
[17] Electrodiagnostic reports of median neuropathy at the wrist. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80089-0
[18] Neurophysiology not Required Before Surgery for Typical Carpal Tunnel Syndrome. Journal of Hand Surgery. 2001. DOI: 10.1054/jhsb.2000.0496
[19] A comparison of traditional electrodiagnostic studies, electroneurometry, and vibrometry in the diagnosis of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80165-1
[20] The Sensitivity and Specificity of Ultrasound for the Diagnosis of Carpal Tunnel Syndrome: A Meta-analysis. Clinical Orthopaedics & Related Research. 2011. DOI: 10.1007/s11999-010-1637-5
[21] Electrodiagnostic testing and carpal tunnel release outcome. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(05)80209-6
[22] Steroid versus placebo injections and wrist splints in patients with carpal tunnel syndrome: a systematic review and network meta-analysis. Journal of Hand Surgery (European Volume). 2024. DOI: 10.1177/17531934241240380
[23] Diagnosis of Mild-to-moderate Idiopathic Median Neuropathy at the Carpal Tunnel Based on Signs and Symptoms is Discordant From Diagnosis Based on Electrodiagnostic Studies and Ultrasound. Clinical Orthopaedics & Related Research. 2023. DOI: 10.1097/corr.0000000000002751
[25] Nerve Conduction Studies for Carpal Tunnel Syndrome: Essential Prelude to Surgery or Unnecessary Luxury?. Journal of Hand Surgery. 2002. DOI: 10.1054/jhsb.2001.0669
[26] Use of motor nerve conduction testing and vibration sensitivity testing as screening tools for carpal tunnel syndrome in industry. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90116-7
[28] Clinical predictors of surgical outcomes of severe carpal tunnel syndrome patients: utility of palmar stimulation in a nerve conduction study. BMC Musculoskeletal Disorders. 2020. DOI: 10.1186/s12891-020-03750-z
[29] Assessment of Outcome of Carpal Tunnel Syndrome: A Comparison of Electrophysiological Findings and a Self-Administered Boston Questionnaire. Journal of Hand Surgery. 2002. DOI: 10.1054/jhsb.2002.0762
[30] Commentary on Management of Atraumatic Posterior Interosseous Nerve Palsy. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.07.027
[31] The Role of Neurodiagnostic Studies in Nerve Injuries and Other Orthopedic Disorders. The Journal of Hand Surgery. 2007. DOI: 10.1016/j.jhsa.2007.07.021
[32] The Management of Persistent and Recurrent Cubital Tunnel Syndrome. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.03.057
[33] Use of the Electromyogram in Evaluating Upper-Extremity Peripheral Nerve Lesions. The Journal of Bone & Joint Surgery. 1962. DOI: 10.2106/00004623-196244060-00001
[34] Diagnostic properties of nerve conduction tests in population-based carpal tunnel syndrome. BMC Musculoskeletal Disorders. 2003. DOI: 10.1186/1471-2474-4-9
[36] Clinical Nerve Conduction and Needle Electromyography Studies. Journal of the American Academy of Orthopaedic Surgeons. 2004. DOI: 10.5435/00124635-200407000-00008
[38] Commentary on Zyluk et al. No correlation between sonographic and electrophysiological parameters in carpal tunnel syndrome; and Yalçın et al. Ultrasound diagnosis of ulnar neuropathy: Comparison of symptomatic and asymtomatic nerve thickness. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193413513524
[39] Re: Mackenzie et al. Carpal tunnel decompression in patients with normal nerve conduction studies. J Hand Surg Eur. 2020, 45: 260–4. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420967839
[40] Preoperative and intraoperative electrophysiologic assessment of brachial plexus injuries. Hand Clinics. 2005. DOI: 10.1016/j.hcl.2004.09.003
[41] The results of carpal tunnel release for carpal tunnel syndrome diagnosed on clinical grounds, with or without electrophysiological investigations: a randomized study. Journal of Hand Surgery (European Volume). 2012. DOI: 10.1177/1753193412445162
[42] Electrodiagnostic testing in hand surgery. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80298-x
[44] Which motor nerve conduction study is best in ulnar neuropathy at the elbow?. Muscle & Nerve. 2003. DOI: 10.1002/mus.10513
[46] Carpal tunnel decompression in patients with normal nerve conduction studies. Journal of Hand Surgery (European Volume). 2019. DOI: 10.1177/1753193419866646
[47] Accuracy of In-Office Nerve Conduction Studies for Median Neuropathy: A Meta-Analysis. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2010.09.012
[48] Carpal Tunnel Syndrome: The Correlation between Outcome, Symptoms and Nerve Conduction Study Findings. Journal of Hand Surgery. 2001. DOI: 10.1054/jhsb.2001.0616
[49] Value of Electrodiagnostic Tests in Carpal Tunnel Syndrome. Journal of Hand Surgery. 2000. DOI: 10.1054/jhsb.2000.0376
[50] Ulna Nerve Decompression at the Elbow in Patients with Normal Nerve Conduction Tests. Hand Surgery. 2015. DOI: 10.1142/s0218810415500215
[51] Microelectroneurography for the inexperienced?. The Journal of Hand Surgery. 1979. DOI: 10.1016/s0363-5023(79)80166-5
[53] Diagnosis of Ulnar Neuropathy at the Elbow Using Ultrasound — A Comparison to Electrophysiologic Studies. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.08.014
[54] Role of Neurophysiologic Evaluation in Diagnosis. Journal of the American Academy of Orthopaedic Surgeons. 2000. DOI: 10.5435/00124635-200005000-00006
[55] Median Nerve Ultrasonography Measurements Correlate With Electrodiagnostic Carpal Tunnel Syndrome Severity. Journal of the American Academy of Orthopaedic Surgeons. 2019. DOI: 10.5435/jaaos-d-17-00557
[56] Variations in Utilization of Carpal Tunnel Release Among Medicaid Beneficiaries. The Journal of Hand Surgery. 2019. DOI: 10.1016/j.jhsa.2018.11.001
[58] Diagnosing Carpal Tunnel Syndrome. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.03.039
[59] Utility of ‘baseline’ electrodiagnostic studies for carpal tunnel release. Journal of Hand Surgery (European Volume). 2018. DOI: 10.1177/1753193418815546
[60] The Association Between Electrodiagnostic Severity and Treatment Recommendations for Carpal Tunnel Syndrome. The Journal of Hand Surgery. 2021. DOI: 10.1016/j.jhsa.2020.08.020
[61] Changes in treatment plan for carpal tunnel syndrome based on electrodiagnostic test results. Journal of Hand Surgery (European Volume). 2013. DOI: 10.1177/1753193413497903
[62] Electrodiagnostic testing and carpal tunnel release outcome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80164-x
[64] Median Nerve Symptoms, Signs, and Electrodiagnostic Abnormalities Among Working Adults. Journal of the American Academy of Orthopaedic Surgeons. 2018. DOI: 10.5435/jaaos-d-17-00034
[65] Sensitivity of the Various Tests for the Diagnosis of Carpal Tunnel Syndrome. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90245-3
[66] Diagnosing Mild to Moderate Idiopathic Median Neuropathy at the Carpal Tunnel. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.06.003
[68] Diagnostic accuracy of sensory and motor tests for the diagnosis of carpal tunnel syndrome: a systematic review. BMC Musculoskeletal Disorders. 2021. DOI: 10.1186/s12891-021-04202-y
[69] The diagnostic value of provocative clinical tests in ulnar neuropathy at the elbow is marginal. Journal of Neurology, Neurosurgery & Psychiatry. 2009. DOI: 10.1136/jnnp.2009.180844