Patients › Wrist
Wrist Arthroscopy
Diagnostic and therapeutic wrist arthroscopy — what it is, when it's used, and recovery.
Why this operation has been suggested
Dr Kieran Hirpara, an upper-limb surgeon at Mater Private Hospital Rockhampton, starts with the least invasive options that suit your condition. Patients are generally referred to our clinic by their GP; if a physiotherapist has suggested you see us, you will still need a referral from your GP in order to be eligible for the Medicare rebate. At your appointment we take a careful history, examine your wrist, and arrange imaging where it is needed to work out what is causing your pain.
Wrist arthroscopy is an operation that uses a small camera inside the wrist joint to look closely at the joint surfaces and soft tissues. We usually suggest it when wrist pain has lasted more than 3 months, has not settled with non-operative care such as activity change, hand therapy, splinting or injections, and when scans and examination have not given a clear enough answer. It may also be recommended after a fracture or a ligament injury, to check the joint surfaces and soft tissues and to treat some problems in the same sitting. The operation can also help with stiffness, some types of arthritis, and long-standing ligament trouble. People who had the operation for persistent wrist pain improved on average by about 50% at one year, though most continued to have some pain and disability. The main aim is less pain, better movement and a steadier wrist, decided together with you.
Before the operation
Your surgeon will give you clear instructions before the day, and we cover the practical points here. You will need to stop eating and drinking from seven hours before your operation. We ask for seven hours rather than the usual six so your operation can be brought forward if the theatre list runs early. Bring a list of your current medications, and your surgeon will tell you if any need to be paused beforehand. Arrange for someone to drive you home afterwards, and wear loose, comfortable clothing. Imaging such as an X-ray, MRI or ultrasound helps plan the operation, and this is usually arranged at your appointment. If you have other medical conditions, you may need blood tests or a review with the anaesthetist.
On the day
On the day of your operation, you present to the hospital's surgical admissions unit. You are checked in there and prepared for theatre. You will then meet the anaesthetist, the doctor who looks after your anaesthetic and pain relief. This operation is done under general anaesthetic. You will be fully asleep for the operation. Some patients may also have a regional nerve block for post-operative pain relief; the anaesthetist decides on the day based on your individual circumstances.
You are then taken into the operating theatre, where the operation is performed. When it is finished, you wake up in the recovery area. Nurses monitor you there while the anaesthetic wears off. Once you are stable, you either go to the ward or go home, depending on the procedure and your recovery.
What the operation involves
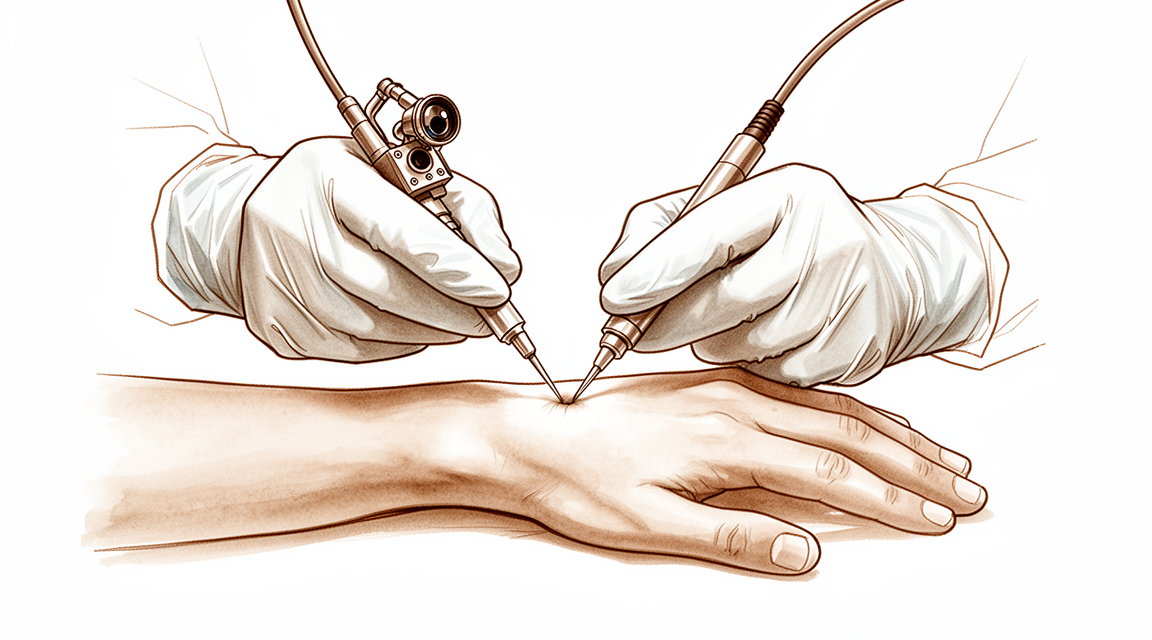
Wrist arthroscopy is a keyhole operation. Your surgeon makes a few small cuts around the wrist, and a small camera goes through one of them so the inside of the joint can be seen on a screen. During the operation your arm is held steady and your fingers are gently suspended in soft finger traps, with a steady pull on the wrist that opens up the joint and creates room to work. Salt water flows through the joint to keep the view clear.
Once the camera is inside, your surgeon can look closely at the joint surfaces and the soft tissues, including the cartilage lining the bones and the ligaments that hold the small wrist bones together. What happens next depends on what is found. Loose pieces of cartilage or bone can be removed. Inflamed tissue lining the joint can be trimmed away. A cyst or a thickened band of tissue can be dealt with. Torn ligaments, including the triangular cartilage on the little-finger side of the wrist, can be trimmed or repaired. If a bone is broken, the pieces can be lined up precisely under the camera and held with screws or pins while they heal. If the wrist has become stiff after an injury or a previous operation, tight tissue can be released to free it up.
At the end, the small cuts are closed with stitches. A dressing goes over the wrist, and your hand is usually supported in a bandage or splint. The dressing stays on for about 10 days, and we will tell you how to care for the wounds in the meantime.
After the operation
You will wake up in the recovery area, where nurses watch you as the anaesthetic wears off. This is usually a day case, so you can expect to go home the same day, although occasionally patients stay overnight. Your wrist will be in a dressing, and your hand may be supported in a bandage or splint. We leave the dressing on for about 10 days; please do not take it off before then unless we tell you to. We change or remove it when we see you. Pain relief is planned for you before you go home; take it as directed. If you had a nerve block, numbness and weakness in the first 24 hours are expected. Once it wears off, at about 24 hours, call the clinic if your fingers stay numb or you cannot move them. Ask someone to stay with you for the first 24 hours. Call the clinic the same day if you have a fever, spreading redness around the wound, fluid or pus leaking from it, or pain that keeps getting worse despite your pain medicines. Go to the emergency department if your fingers or hand turn pale, cold, white, blue or dark, as this can be a circulation problem. Keep your hand raised when resting to help swelling settle. Most people move around the house normally from the day of surgery; you do not need bed rest.
Recovery
For the first few days your wrist will be sore and swollen, and your fingers may feel stiff. Keeping your hand raised when resting helps the swelling settle. Take your pain relief as directed, and expect the discomfort to ease steadily as the days pass.
Most people move around the house normally from the day of surgery. You will need someone to handle heavy lifting and driving at first. Once any splint comes off and you can hold the wheel comfortably, you can drive again; our page on driving after upper-limb surgery explains this in more detail. The dressing stays on for about 10 days, and we will check the wounds when we see you.
Hand therapy is a big part of getting your wrist moving again. Your rehabilitation is with Ruby Doolan at Extend Rehabilitation. Ruby is a hand therapist: she will guide your exercises and make any splint you need along the way. Early on, the focus is gentle movement and controlling swelling. As the wrist settles, the exercises build up to gripping, lifting and using your hand for everyday tasks. Recovery follows a step-by-step pattern, and coordinated movement between the wrist and fingers keeps improving as the weeks go by.
How quickly you return to work, sport or the gym depends on what was found and repaired inside your wrist, and on your job and hobbies. Your timeline may differ from someone else's; we and your therapist will guide you at each stage.
What can go wrong
Most patients do well, but problems can occasionally happen. Your surgeon and the team monitor you closely to spot any issue early.
Infection is uncommon after this operation, but it matters when it happens. Call the clinic the same day if you have a fever, spreading redness around the wound, or fluid or pus leaking from it. Call the clinic the same day too if pain keeps getting worse despite your pain medicines. In a severe infection deep in the wrist, further surgery is sometimes needed, and this is very rare.
The finger traps that hold your fingers during the operation can leave your finger joints sore afterwards, or bruise the soft tissue or small nerves in a finger. This settles on its own in most cases. Bring it up at your next review if a finger is still sore or feels odd.
Fluid used to fill the joint during the operation can occasionally leak into the tissues of the forearm. Watch for swelling in the forearm that builds up quickly, along with tightness and pain that keeps growing. Call the clinic straight away if you notice this.
Nerves near the wrist can be irritated or injured during the operation. You might notice numbness, tingling or a patch of skin that feels different once the nerve block has worn off, at about 24 hours. Numbness and weakness in the first 24 hours after a nerve block are expected. Call the clinic if numbness lasts beyond that, or if you cannot move your fingers or hand once the block has worn off. If you cannot reach the clinic, go to your nearest emergency department.
The complications table on this page lists typical rates if you want the specifics.
When to call us
Most people recover without problems, but it helps to know what to watch for. Call the clinic the same day if you have a fever, spreading redness around the wound, fluid or pus leaking from it, or pain that keeps getting worse despite your pain medicines. Call the clinic if your fingers stay numb or you cannot move them once the nerve block has worn off, at about 24 hours. Go to the emergency department if your calf swells or is painful, if you become short of breath or get chest pain, or if your fingers or hand turn pale, cold, white, blue or dark. These can be signs of a blood clot or a circulation problem. If you cannot reach the clinic, go to your nearest emergency department.
Where to read more about the condition
This page is about the operation itself. The condition it treats, including what the evidence shows about when surgery helps and when it does not, is covered in more detail on the Wrist Ligament Injuries page.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Wrist arthroscopy is a valuable means of diagnosis and treatment of wrist disorders [2].
- Wrist arthroscopy is a safe procedure with a low rate of major and minor complications [3].
- Wrist arthroscopy provides views of and access to the intraarticular spaces of the wrist that are otherwise difficult to achieve without widely open approaches [4].
- The indications for wrist arthroscopy are growing with the description of volar portals for the radiocarpal and scaphotrapezial trapezoid joint [1].
- Volar portals for wrist arthroscopy have certain advantages over the standard dorsal portals for visualizing dorsal capsular structures as well as the palmar aspects of the carpal ligaments [15].
- The routine use of wrist arthroscopy as a replacement or supplement to arthrography cannot be justified [5].
- Wrist arthroscopy may be recommended in cases of chronic wrist pain where the clinical suspicion is strong and the operating team is well-versed with the technique [6].
- Postoperative infection after wrist arthroscopy is uncommon but clinically relevant, particularly in elderly, male patients with systemic comorbidities or undergoing synovectomy [7].
- Arthroscopic arthrolysis is a suitable and promising surgical option for the treatment of wrist stiffness after trauma or surgery [8].
- In a prospective comparative study, the arthroscopically guided procedure for intra-articular distal radius fracture was superior to the conventional open procedure [12].
- Arthroscopic exploration of the extensor carpi ulnaris and its subsheath using standard wrist arthroscopy is relatively simple to perform without the need of a further portal [11].
- Complete avulsion of the distal posterior interosseous nerve during wrist arthroscopy is a possible cause of persistent pain after arthroscopy [10].
- It is questioned whether distal posterior interosseous nerve avulsion could be responsible for symptomatic improvement in certain patients after arthroscopy due to partial wrist denervation [10].
- A simple, effective, and cost-efficient solution exists to overcome oversized finger traps for wrist arthroscopy distraction [9].
- The concept to use a physical model for wrist arthroscopy training is well perceived and indicates the potential for continued development [14].
Anatomy & Pathophysiology
Bony Anatomy
- The wrist includes the distal radioulnar, radiocarpal, and ulnocarpal joints and the eight carpal bones and their proximal and distal articulations and attached ligaments [38].
- The carpus comprises eight ossicles traditionally separated into two rows: the proximal row (scaphoid, lunate, triquetrum, pisiform) and the distal row (trapezium, trapezoid, capitate, hamate) [39].
- The distal radius articular surface has two concave facets for the scaphoid and lunate, separated by the scapholunate ridge [39].
- The sigmoid notch along the ulnar border of the distal radius is a shallow concavity for the articulating ulnar head at the distal radioulnar joint [39].
- The distal ulna is covered with hyaline cartilage on its dorsal, lateral, palmar, and distal surfaces [39].
- The ulnar styloid projects distally, and at its base, the fovea is the insertion for the triangular fibrocartilaginous complex (TFCC) [39].
- The scaphoid's primary vascular supply is a branch of the radial artery at the dorsal ridge, with smaller vessels entering the palmar tubercle to supply the distal 30% [39].
- The lunate has a dorsal and palmar vascular supply in 80% of wrists, while 20% have only a palmar supply [39].
- The capitate head often relies on a retrograde vascular supply [39].
- The pisiform is a sesamoid bone within the flexor carpi ulnaris tendon and serves as the origin for the abductor digiti minimi [39].
- The distal radial articular surface has a double obliquity of 12–15 degrees in the lateral view and 15–20 degrees in the anteroposterior view [43].
- The carpal articular surface has a smaller diameter of curvature than the radius, with stability in the medial and palmar aspects dependent on ligamentous and capsular resistance [43].
- The scaphoid presents a long axis inclined by 45 degrees to the long axis of the radius [43].
- The triquetrum is not in contact with the ulnar head; a fibro-cartilage disc, the triangular ligament, separates the two bones [43].
Ligaments and Soft Tissue Anatomy
- The triangular fibrocartilage complex (TFCC) consists of the central meniscus homolog, dorsal and volar radioulnar ligaments, the floor of the extensor carpi ulnaris tendon sheath, and volar ulnocarpal ligaments [39].
- The TFCC arises from the radial border of the distal radius and inserts into the base of the ulnar styloid and distal ulna through the ligamentum subcruentum [39].
- The dorsal and volar radioulnar ligaments are the primary stabilizers of the distal radioulnar joint [39].
- Only the peripheral 10% to 40% of the volar, ulnar, and dorsal TFCC has a vascular supply [39].
- The scapholunate interosseous ligament is C-shaped in the sagittal plane, with the dorsal third being the thickest and strongest portion [39].
- The volar portion of the lunotriquetral ligament is the thickest [39].
- The extrinsic wrist ligaments include the dorsal intercarpal ligament and the dorsal radiocarpal ligament [39].
- The dorsal radiocarpal ligament originates at the dorsal lip of the distal radius adjacent to Lister's tubercle and inserts into the lunate and triquetrum [39].
- The dorsal intercarpal ligament arises from the triquetrum and attaches to the scaphoid, trapezoid, and capitate [39].
- The terminal branches of the radial, ulnar, and anterior interosseous arteries provide extraosseous blood supply to the carpus through three dorsal and three palmar transverse arterial arches [41].
- The dorsal intercarpal arch is the largest of the dorsal arches and supplies the distal carpal row and, through anastomoses, the lunate and triquetrum [41].
- The deep palmar arch at the level of the metacarpal bases is consistent and communicates with the dorsal basal metacarpal arch and palmar metacarpal arteries [41].
- The extensor carpi ulnaris tendon rotates around the ulnar head, situated on the ulnar side of the styloid in pronation and on the radial side in supination [44].
- The extensor carpi radialis brevis is the primary wrist extensor with a moment arm of 16.30 mm, compared to 12.50 mm for the extensor carpi radialis longus [44].
Kinematics and Biomechanics
- The wrist functions as a two-joint system linking the hand to the forearm around the highly mobile bones of the proximal carpal row [40].
- With axial loading through the neutral wrist, approximately 80% of forces are transmitted through the distal radius (60% scaphoid facet, 40% lunate facet) and 20% through the distal ulna [39].
- With wrist flexion, 60% of the motion is midcarpal and 40% is radiocarpal [39].
- With wrist extension, 33% of the motion is midcarpal and 66% is radiocarpal [39].
- The proximal carpal row has no muscular or tendinous attachments and is an intercalary segment [39].
- With ulnar deviation, the proximal row extends relative to the forearm/distal row, while with radial deviation, the proximal row flexes [39].
- The dart-thrower's path of radial extension to ulnar flexion defines the transition between flexion and extension of the scaphoid and lunate [40].
- Dart-thrower's motion occurs almost exclusively through the midcarpal joint [40].
Pathophysiology of Wrist Disorders
- Scapholunate advanced collapse (SLAC) wrist pathophysiology involves scapholunate interosseous ligament injury leading to palmar flexion of the scaphoid and extension of the lunate (DISI) [36].
- In SLAC wrist, the radioscaphoid joint becomes incongruous, leading to altered contact forces and arthrosis at the radioscaphoid and capitolunate joints [36].
- The radiolunate joint is typically spared in SLAC wrist due to its spheroid shape [36].
- Ulnocarpal impingement is a degenerative condition resulting from a discrepancy in the relative length of the distal articular surfaces of the radius and ulna (positive ulnar variance) [36].
- Posttraumatic causes of ulnocarpal impingement include distal radius fracture with shortening, Galeazzi or Essex-Lopresti fracture, and childhood epiphyseal plate injuries [36].
- Congenital causes of ulnocarpal impingement include dyschondroplasia (Madelung deformity) and naturally occurring positive ulnar variance [36].
- In rheumatoid arthritis, the classic pattern of wrist deformity involves destabilization of the carpus caused by attenuation of extrinsic wrist ligaments, resulting in ulnar-palmar translocation and wrist supination [49].
- Three main pathophysiological factors drive rheumatoid wrist deformation: cartilage destruction, synovial expansion, and ligamentous laxity [49].
- In juvenile arthritis, uncontrolled joint synovitis stretches essential ligaments and erodes cartilage and bone, resulting in a progressive shift of the carpus ulnarward and volarward [50].
- The dorsal wrist ganglion is the prototype of hand and wrist ganglions, accounting for 60% to 70% of all hand and wrist ganglions [23].
- The main cyst of a dorsal wrist ganglion is usually located directly over the scapholunate ligament [23].
- A small, mucin-filled duct invariably pierces the transverse fibers of the scapholunate ligament, connecting the underlying scapholunate joint with the main ganglion cyst [23].
TFCC Tear Classification
- The Palmer classification categorizes triangular fibrocartilage complex (TFCC) tears into traumatic (class 1) or degenerative (class 2) [24].
- Subtypes within the Palmer classification are based on the specific location within the TFCC [24].
- The class and location of a TFCC tear have important implications for treatment [24].
- Class 1A traumatic TFCC injuries are characterized by central perforation or tear [24].
- Class 1B traumatic TFCC injuries are characterized by ulnar avulsion with or without ulnar styloid fracture [24].
- Class 1C traumatic TFCC injuries are characterized by distal avulsion involving the origins of the ulnolunate and ulnotriquetral ligaments [24].
- Class 1D traumatic TFCC injuries are characterized by radial avulsion involving the dorsal and/or volar radioulnar ligaments [24].
- Class 2A degenerative TFCC tears are characterized by TFCC wear or thinning [24].
- Class 2B degenerative TFCC tears are characterized by Class 2A findings plus lunate and/or ulnar chondromalacia [24].
- Class 2C degenerative TFCC tears are characterized by TFCC perforation plus lunate and/or ulnar chondromalacia [24].
- Class 2D degenerative TFCC tears are characterized by Class 2C findings plus lunotriquetral ligament disruption [24].
- Class 2E degenerative TFCC tears are characterized by Class 2D findings plus ulnocarpal and distal radioulnar joint arthritis [24].
- Arthroscopy is the gold standard for the detection of TFCC tears [24].
- The arthroscopic trampoline test is performed to assess TFCC resiliency by balloting the central portion with a small probe [24].
- The arthroscopic hook test can be used to demonstrate peripheral detachment of the TFCC [24].
- The arthroscopic suction test can show laxity of the TFCC when peripherally scarred in or foveal detachment when the distal radioulnar joint is clinically unstable [24].
Clinical Presentation
Diagnostic Indications
- Indications for diagnostic wrist arthroscopy include chronic wrist pain of uncertain etiology with more than 3 months interval, unresponsive to conservative treatment [21, 37].
- Indications for diagnostic wrist arthroscopy include assessment of acute ligamentous injuries, including scapholunate, lunotriquetral, and triangular fibrocartilage complex (TFCC) injuries [21].
- Indications for diagnostic wrist arthroscopy include evaluation of carpal instability [21].
- Indications for diagnostic wrist arthroscopy include assessment of chondral lesions [21].
- Indications for diagnostic wrist arthroscopy include evaluation of associated soft tissue injury in fracture conditions, including distal radius, scaphoid, ulnar styloid, and other carpal bone fractures [21].
- Indications for diagnostic wrist arthroscopy include assessment of scaphoid healing in delayed union and nonunion [21].
- Indications for diagnostic wrist arthroscopy include staging of posttraumatic arthritis, including scapholunate advanced collapse (SLAC), scaphoid nonunion advanced collapse (SNAC), and distal radius fractures [21].
- Indications for diagnostic wrist arthroscopy include evaluation of monoarticular arthritis and synovial biopsy [21].
- Indications for diagnostic wrist arthroscopy include evaluation of Kienböck disease [21, 37].
- Patients without positive provocative sign on examination seldom yield positive findings at wrist arthroscopy [37].
- Arthroscopic findings need to correlate with clinical examination [37].
Clinical Examination Principles
- The natural inclination to study radiographs or special imaging studies and reports prior to a thorough history and physical examination should be avoided, as this introduces cognitive bias which can affect thinking and decision making [34].
- Physical examination always needs to be preceded by a thorough investigation of the patient’s medical history, with special emphasis on the mechanism of injury and acuity [34].
- The patient should be asked details about the location, duration, and characteristics of any pain, including aggravating and relieving factors and previous treatments [34].
- With chronic problems, it is important to inquire about the patient’s jobs and hobbies, and whether there has been exposure to repetitive stress, vibrating tools, or potentially dangerous instruments [34].
- Elucidating a history of ligamentous laxity or multiple joint instabilities, especially in younger patients presenting with chronic wrist pain, is important [34].
- Such an evaluation should also include an assessment of the patient's stress coping skills [34].
- Swelling is generally moderate in wrist dislocations, and bone displacements may be evident only if the patient is seen immediately after experiencing trauma [34].
- If there has been a delay since the accident, swelling may have increased substantially, making visualization of the displaced bones more difficult [34].
- Skin abrasions, contusions, or ecchymosed areas may be helpful in determining the mechanism of injury and the potential areas of damage [34].
- Range of motion is usually limited by pain in acute injuries, whereas it may be reduced or normal in more chronic cases [34].
- In chronic cases, passive assessment of mobility is valuable not only in determining the presence of abnormal motion or crepitus but also in reproducing the patient’s pain [34].
- The physician should record the motion in the contralateral, uninjured wrist for comparative purposes [34].
- Palpation for areas of maximal tenderness is one of the most useful tools in the diagnosis of wrist pathology, especially in patients with chronic dysfunctions [34].
- In acute dislocations, tenderness is seldom elicited at specific points but rather in a diffuse manner due to extensive soft tissue damage [34].
- Palpation should always be performed in a methodical way, starting from the basal joint of the thumb and proceeding across the proximal carpal row from the scaphoid to the triquetrum and continuing from the hamate back across the distal row and CMC joints [34].
- A careful assessment of neural and vascular status is imperative, with particular attention being paid to the median and ulnar nerves [34].
- The median and ulnar nerves may be injured by direct contusion at the moment of impact, by compression from displaced bones or by swelling within the carpal canal [34].
- A thorough set of provocative maneuvers should be performed to rule out alternative or even concurrent diagnoses [34].
- The examination should begin in a nontender area and proceed rotationally around the carpus, ending at the most symptomatic area [34].
- Bilateral grip and pinch strength are useful to uncover underlying pathology in chronic cases [34].
- Strength may be diminished due to muscle atrophy, pain inhibition, or learned behaviors [34].
- Rapid alternating grip assessment may be helpful in determining voluntary effort [34].
- A local injection of anesthetic to a painful joint or selected tendon sheath may help normalize the dynamometer readings and narrow the diagnostic spectrum [34].
- Sensory testing should always accompany an examination of suspected nerve compression, using threshold or density testing [34].
Specific Provocative Maneuvers
- The ligamentous habitus of a given individual must be assessed using information from the normal wrist because of the wide variation in mobility and laxity [54].
- The Watson test, or scaphoid shift test, is designed to show scaphoid instability [54].
- In the Watson test, the examiner puts one hand on the radial border of the distal forearm with the thumb on the palmar aspect of the scaphoid while moving the patient’s hand to bring about ulnar then radial deviation of the wrist [54].
- The Watson test causes a dorsal subluxation of the scaphoid, accompanied by a painful click [54].
- A positive Watson shift test results when the scaphoid subluxates dorsally out of the scaphoid fossa and relocates when pressure is released [36].
- The ballotment tests, or shear tests, consist of demonstrating abnormal movements between adjacent bones by exerting pressure in opposite directions [54].
- The scapholunate ballotment test involves stressing of the scapholunate joint by volar pressure on the tubercle of the scaphoid and dorsal pressure on the lunate [54].
- If there is any ligament damage, pressure on these two bones causes a painful shearing of the scapholunate joint [54].
- Instability of the lunotriquetral joint can be demonstrated by Reagan’s test, which involves dorsal pressure on the lunate and volar pressure on the triquetrum [54].
- The midcarpal joint "pivot shift" test consists of supinating and volar subluxing the distal row of the carpus [54].
- The pivot shift test is performed by placing the patient elbow upon a firm surface, holding the elbow at 90 degrees, putting the hand into a fully supine position and holding the distal forearm firmly [54].
- The hand is moved into full radial deviation and then the ulnar side of the carpus is forced into further supination and a volar subluxed position [54].
- The wrist must not be flexed during the pivot shift test [54].
- The hand, still with the displacing force applied, is gently moved from radial to full ulnar deviation [54].
- The normal wrist will notch into a less supinated position as the head of the capitate engages the lunate, because of the restraint of the anterior capsule and triquetrolunate interosseous ligaments [54].
- Rupture, attenuation or excess laxity allow the capitate to drift out of the lunate [54].
- Triquetral hamate instability is demonstrated with the wrist straight with ulnar deviation [54].
- After a range of about 20 degrees, triquetral hamate instability produces a firm block [54].
- If one forces a sharp click accompanied by discrete posterior movement of the wrist, the proximal row of the carpus has moved from the VISI position to that of DISI, thus allowing a complete ulnar deviation of the wrist joint [54].
- The radio-carpal and midcarpal joint anteroposterior drawer test involves one hand holding the patient’s hand by the metacarpals to apply axial traction while the other hand stabilizes the patient’s forearm [54].
- While holding this traction, anteroposterior force is applied and a drawer is elicited at the radio-carpal, then the midcarpal joint [54].
- The ability to push the midcarpal joint volarward is present to a varying degree in most normal asymptomatic patients [54].
- A marked drawer test is a sign of congenital laxity [54].
- An exaggeration of the normal ulna head prominence is seen in dorsal subluxation or articular effusion [54].
- The prominence of the ulna head may be temporarily reduced by direct pressure over the ulna head [54].
- In the rheumatoid wrist, the ulna head prominence is further exaggerated by a supination deformity of the carpus [54].
- If the hand is held in full ulnar deviation and the ulna head is held forward by the examiner’s thumb, significant pain may be precipitated by this movement alone, suggesting DRUJ pathology [54].
- Pain precipitated by pronosupination while the ulna head is pressed volarward and the pisiform pressed dorsally is usually indicative of some form of ulnar impingement or abutment syndrome [54].
- The diagnosis of DRUJ arthrosis is confirmed by improvement in rotation and grip strength with injection of a local anesthetic into the DRUJ [36].
- Clinical findings for DRUJ arthrosis include pain that increases with proximal rotation of the forearm and compression of the ulna against the radius [36].
- Symptoms of ulnocarpal impingement include pain on the dorsal side of the DRUJ and an intermittent clicking sensation [36].
- Pain in ulnocarpal impingement is exacerbated by forearm rotation and ulnar deviation [36].
- Pain in ulnocarpal impingement occurs with axial loading of the ulnar side of the wrist [36].
- Pain in ulnocarpal impingement occurs with dorsal and palmar displacement of the distal ulna, with the wrist in ulnar deviation (positive ballottement test) [36].
- Symptoms of SLAC wrist include reduced grip and pinch strength [36].
- Symptoms of SLAC wrist include stiffness with extension and radial deviation [36].
- Symptoms of SLAC wrist include localized tenderness at the radioscaphoid articulation [36].
- Symptoms of SLAC wrist include decreased wrist motion on extension and radial deviation [36].
Imaging and Preoperative Evaluation
- After the history and physical examination, radiographic evaluation is helpful in determining the diagnosis, prognosis, and management of wrist problems [32].
- MRI should be added for evaluation of the triangular fibrocartilage; the distal radioulnar joint (DRUJ); and vascularity of the various carpal bones, extrinsic ligaments, joint surfaces, and surrounding soft tissues to confirm clinical suspicion and correlate with physical examination findings [32].
- A high rate of false-positive findings on MR images of normal subjects has been reported [32].
- A dedicated wrist coil provides enhanced resolution of wrist structures [32].
- Routine radiographic series for the wrist consist of four views: posteroanterior, lateral, oblique, and ulnar-deviated posteroanterior scaphoid view [32].
- Spot views of the carpal bones for detail (carpal tunnel view) are a useful radiographic technique [32].
- Fluoroscopic spot views of the wrist are a useful radiographic technique [32].
- A series of views for instability includes anteroposterior clenched fist, posteroanterior in neutral, radial, and ulnar deviation, lateral in neutral and full flexion and extension, semipronated oblique 30 degrees from the posteroanterior, and semisupinated oblique 30 degrees from the lateral [32].
- Diagnostic ultrasound is a useful radiographic technique for evaluating a painful wrist [32].
- Cine or video fluoroscopy is a useful radiographic technique for evaluating a painful wrist [32].
- Bone scanning is a useful radiographic technique for evaluating a painful wrist [32].
- Arthrography of the wrist (triple injection when indicated) is a useful radiographic technique [32].
- CT is a useful radiographic technique for evaluating a painful wrist [32].
- MRI is a useful radiographic technique for evaluating a painful wrist [32].
- The authors do not feel that the routine use of wrist arthroscopy as a replacement or supplement to arthrography can be justified [5].
- Perform repeated clinical examinations for chronic wrist pain as part of preoperative evaluation [37].
Investigations
Diagnostic Role and Indications
- Arthroscopic assessment of intercarpal ligament injuries and instability is considered by many the “gold standard” for evaluation of these conditions [31].
- Arthroscopy is the gold standard for detection of triangular fibrocartilage complex (TFCC) tears [24].
- Arthroscopy has been found to be more accurate than arthrography in identifying the location and size of triangular fibrocartilage and interosseous ligament injuries [31].
- Arthroscopy is more accurate than triple-injection cinearthrography in detecting tears of the dorsal sensory branch of the ulnar nerve during arthroscopic repair of the triangular fibrocartilage [31].
- Indications for wrist arthroscopy include the evaluation of ligamentous injuries, examination of joint articular surfaces, removal of loose bodies, biopsy of synovium, irrigation and debridement of joints, and confirmation and supplementation of wrist arthrography [31].
Arthroscopic Tests
Imaging Modalities
- MRI should be added for evaluation of the triangular fibrocartilage, the distal radioulnar joint, and vascularity of the various carpal bones, extrinsic ligaments, joint surfaces, and surrounding soft tissues to confirm clinical suspicion and correlate with physical examination findings [32].
- With proper technique, injuries to the triangular fibrocartilage complex can be demonstrated with MRI [46].
- Perforations in the triangular fibrocartilage complex appear as linear defects or gaps filled with hyperintense fluid on coronal gradient-echo or T2-weighted pulse sequences [46].
- The addition of arthrographic contrast improves the visualization of carpal ligaments on MR images [46].
- MRI is useful in detecting additional marrow abnormalities in osteonecrosis, as seen in the lunate in Kienböck disease or in the scaphoid after fracture [46].
- Asymmetry of marrow signal in proximal and distal fragments of a fractured scaphoid is suggestive of proximal pole ischemia [46].
- MRI has a limited role in the evaluation of carpal tunnel syndrome, which remains a clinical diagnosis [46].
- Axial imaging with T2 weighting can clearly display masses within the confines of the carpal tunnel, as well as edema and swelling of the median nerve [46].
- MRI provides earlier detection of synovitis and erosive bone changes associated with rheumatoid arthritis than do radiographs [46].
- MRI has an expanding role in the evaluation of inflammatory arthritis [46].
- MRI has gained a greater role in the evaluation of acute wrist trauma, where bone marrow edema may reveal fractures of the carpal bones or distal radius that are radiographically occult [46].
- MRI is controversial for TFCC pathology, but newer innovations suggest value in detection and localization of TFCC pathology [24].
Radiographic Techniques
- Spot views of the carpal bones are used for detail, including the carpal tunnel view [32].
- Arthrography of the wrist, including triple injection when indicated, is a useful radiographic technique [32].
Preoperative Assessment
- The natural inclination to study radiographs or special imaging studies and reports prior to a thorough history and physical examination should be avoided, as this introduces cognitive bias [34].
Treatment
Indications and Diagnostic Role
Operative Technique and Setup
- The patient is positioned supine on the operating table with a traction device applied to distract the wrist joint [21].
- Traction force of 10 to 12 lb is applied through plastic finger traps over the index and middle fingers, or more preferably, the middle three fingers [21].
- Overdistraction or use of wire finger traps may cause postoperative finger joint pain or localized contusion to soft tissue or digital nerves [21].
- Nylon finger traps are more comfortable and atraumatic to the patient, especially in awake cases [21].
- For arthroscopy over the scaphotrapeziotrapezoid joint, an additional trap and traction can be put on the thumb [21].
- When an overhead traction boom is employed, countertraction is provided by securing the arm to the hand table, and the operated limb is draped free up to the elbow level [21].
- When a dedicated wrist traction device is being used, the limb is draped up to the axilla level and the lower arm is wrapped to the basal plate of the device close to the elbow level [21].
- A traction device should be sterilizable and allow flexible positioning of the wrist intraoperatively in varying degrees of extension, flexion, and radial and ulnar deviation [21].
- Tourniquet use is optional and is often unnecessary, especially for diagnostic and uncomplicated therapeutic procedures performed under local anesthesia without sedation [21].
- Joint visibility is maintained by saline inflow, as the small volume of the wrist makes fluid distention rather impractical compared to the knee or shoulder joint [21].
- The main maneuver in creating the working space is controlled traction, while saline maintains a clear view by removing intraarticular debris through the outflow portal [21].
- The hydrostatic pressure generated by saline irrigation serves a hemostatic role when arthroscopy is performed without a tourniquet [21].
- Continuous irrigation is achieved with a 3 L bag of normal saline suspended 1.5 m above the patient and instilled under gravity [21].
- Caution should be used to avoid extravasation of fluid that may lead to compartment syndrome [21].
Therapeutic Procedures
- In the treatment of central triangular fibrocartilage complex tears, partial excision using the holmium:Yttrium-aluminum-garnet laser has been performed over a five-year experience [13].
- Arthroscopically guided procedure for intra-articular distal radius fracture was found to be superior to the conventional open procedure based on a prospective comparative study [12].
- Ablative procedures in wrist arthroscopy include TFCC debridement, debridement of ligament tears, synovectomy, wrist ganglionectomy, removal of loose body, capsulotomy/capsulectomy, lavage, and arthrolysis [21].
- Ablative bony procedures in wrist arthroscopy include scaphoidectomy, radial styloidectomy, wafer procedure, proximal row carpectomy, and proximal hamate excision [21].
- Ablative cartilage procedures in wrist arthroscopy include debridement of chondral and osteochondral lesions [21].
- Reparative soft tissue procedures in wrist arthroscopy include peripheral TFCC tear repair, TFCC foveal avulsion repair, scapholunate ligament injury repair, and lunotriquetral ligament injury repair [21].
- Reparative bony tissue procedures in wrist arthroscopy include arthroscopic-assisted reduction and internal fixation (ARIF) for distal radius fracture and scaphoid fracture [21].
- Reparative cartilage procedures in wrist arthroscopy include drill/abrasion chondroplasty [21].
- Reconstructive soft tissue procedures in wrist arthroscopy include arthroscopic TFCC reconstruction with tendon graft and arthroscopic-assisted scapholunate ligament reconstruction with tendon graft [21].
- Reconstructive bony procedures in wrist arthroscopy include arthroscopic bone grafting for scaphoid nonunion, limited carpal fusion, intraosseous bone cyst, and intraosseous ganglion [21].
- Reconstructive cartilage tissue procedures in wrist arthroscopy include osteochondral grafting [21].
Complications and Safety
- DPIN avulsion could be responsible for symptomatic improvement in certain patients after arthroscopy due to partial wrist denervation [10].
Complications
- Overdistraction during wrist arthroscopy distraction can cause postoperative finger joint pain [21].
- Use of wire finger traps for wrist arthroscopy distraction may cause localized contusion to soft tissue or digital nerves [21].
- Nylon finger traps are more comfortable and atraumatic to the patient than other traction methods, especially in awake cases [21].
- Extravasation of fluid during wrist arthroscopy may lead to compartment syndrome [21].
- Postoperative infection after wrist arthroscopy is uncommon but clinically relevant [7].
- Postoperative infection risk after wrist arthroscopy is particularly elevated in elderly, male patients with systemic comorbidities or those undergoing synovectomy [7].
- Complete avulsion of the distal posterior interosseous nerve can occur during wrist arthroscopy [10].
- Distal posterior interosseous nerve avulsion is a possible cause of persistent pain after wrist arthroscopy [10].
- Inadvertent damage to the dorsal branch of the ulnar nerve can be avoided by placing the 6R portal in the proximal fifth (19%) of a line drawn from the ulnar styloid to the fourth dorsal web space [22].
Recovery
- Postoperative infection risk is particularly relevant in elderly, male patients with systemic comorbidities or undergoing synovectomy [7].
Key Evidence
- [Paper] The indications for wrist arthroscopy are growing with the description of volar portals for the radiocarpal and scaphotrapezial trapezoid joint. [1] (10.1097/00130911-200603000-00007)
- [L4] From these data it appears that wrist arthroscopy is a valuable means of diagnosis and treatment of wrist disorders. [2] (10.1016/s0266-7681(96)80100-8)
- [L4] Wrist arthroscopy is a safe procedure with a low rate of major and minor complications. [3] (10.1016/j.jhsa.2003.12.020)
- [L5] Wrist arthroscopy can be a useful tool in one’s armamentarium in the diagnosis and treatment of wrist pathology, providing views of and access to the intraarticular spaces of the wrist that are otherwise difficult to achieve without widely open approaches. [4] (10.1016/j.eats.2024.103223)
- [L4] The authors do not feel that the routine use of wrist arthroscopy as a replacement or supplement to arthrography can be justified. [5] (10.1016/0266-7681(94)90256-9)
- [L4] It may be recommended in cases of chronic wrist pain where the clinical suspicion is strong and the operating team is well-versed with the technique. [6] (10.1177/1558944716660555ig)
- [L3] Postoperative infection after wrist arthroscopy is uncommon but clinically relevant, particularly in elderly, male patients with systemic comorbidities or undergoing synovectomy. [7] (10.1016/j.otsr.2026.104771)
- [L4] Arthroscopic arthrolysis is a suitable and promising surgical option for the treatment of wrist stiffness after trauma or surgery. [8] (10.1016/s0363-5023(03)80309-x)
- [L5] We present a simple, effective, and cost-efficient solution to overcome oversized finger traps for wrist arthroscopy distraction. [9] (10.1016/j.eats.2025.103662)
- [L5] An alternate question is whether DPIN avulsion could be responsible for symptomatic improvement in certain patients after arthroscopy due to partial wrist denervation. [10] (10.1053/jhsu.1999.0240)
- [L5] They found this arthroscopic exploration relatively simple to perform without the need of a further portal. [11] (10.1177/1753193420948404)
- [L3] On the basis of our prospective comparative study, we found that the arthroscopically guided procedure was superior to the conventional open procedure. [12] (10.1016/j.jhsb.2006.03.177)
- [L4] [13] (10.1053/jhsu.2001.20157)
- [Paper] The concept to use a physical model for wrist arthroscopy training is well perceived, and indicates the potential for continued development. [14] (10.1016/j.main.2015.10.087)
- [L5] Volar portals for wrist arthroscopy have certain advantages over the standard dorsal portals for visualizing dorsal capsular structures as well as the palmar aspects of the carpal ligaments. [15] (10.1097/00130911-200412000-00006)
- [L5] Inadvertent damage to the dorsal branch of the ulnar nerve can be avoided if care is taken to place the 6R portal in the ‘‘safe area’’ found within the proximal fifth (19%) of a line drawn from the ulnar styloid to the fourth dorsal web space. [22] (10.1016/j.jhsb.2005.10.005)
References
[1] Uses and Abuses of Wrist Arthroscopy. Techniques in Hand & Upper Extremity Surgery. 2006. DOI: 10.1097/00130911-200603000-00007
[2] The Value of Wrist Arthroscopy. Journal of Hand Surgery. 1996. DOI: 10.1016/s0266-7681(96)80100-8
[3] Complications of wrist arthroscopy. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2003.12.020
[4] Wrist Arthroscopy: Positioning, Portal Placement, and Diagnostic Evaluation. Arthroscopy Techniques. 2024. DOI: 10.1016/j.eats.2024.103223
[5] Wrist Arthroscopy. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90256-9
[6] Wrist Arthroscopy as a Diagnostic Tool in Chronic Wrist Pain. HAND. 2016. DOI: 10.1177/1558944716660555ig
[7] Incidence and risk factors of postoperative infection after wrist arthroscopy: an 11-year nationwide population-based cohort study in South Korea. Orthopaedics & Traumatology: Surgery & Research. 2026. DOI: 10.1016/j.otsr.2026.104771
[8] Arthroscopic wrist arthrolysis. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)80309-x
[9] Tip to Overcome Oversized Finger Traps in Wrist Arthroscopy Distraction. Arthroscopy Techniques. 2025. DOI: 10.1016/j.eats.2025.103662
[10] Complete avulsion of the distal posterior interosseous nerve during wrist arthroscopy: A possible cause of persistent pain after arthroscopy. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.0240
[11] Visualization of the extensor carpi ulnaris and its subsheath using standard wrist arthroscopy. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420948404
[12] 2.3 Wrist arthroscopy in intra-articular distal radius fracture. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 2006. DOI: 10.1016/j.jhsb.2006.03.177
[13] The holmium:Yttrium-aluminum-garnet laser in wrist arthroscopy: A five-year experience in the treatment of central triangular fibrocartilage complex tears by partial excision. The Journal of Hand Surgery. 2001. DOI: 10.1053/jhsu.2001.20157
[14] Development of a wrist arthroscopy simulator. Chirurgie de la Main. 2015. DOI: 10.1016/j.main.2015.10.087
[15] Clinical Applications of Volar Portals in Wrist Arthroscopy. Techniques in Hand & Upper Extremity Surgery. 2004. DOI: 10.1097/00130911-200412000-00006
[21] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > SURGICAL TECHNIQUE FOR DIAGNOSTIC ARTHROSCOPY > Setup.
[22] The Anatomy of the Dorsal Cutaneous Branch of the Ulnar Nerve – a Safe Zone for Positioning of the 6r Portal in Wrist Arthroscopy. Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsb.2005.10.005
[23] Green S Operative Hand Surgery. BOX 59.1 Ganglions of the Hand and Wrist > Operative Treatment > Dorsal Wrist Ganglion.
[24] Miller S Review Of Orthopaedics. DISTAL RADIOULNAR JOINT, TRIANGULAR FIBROCARTILAGE COMPLEX, AND WRIST ARTHROSCOPY > 2. TFCC tears.
[31] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > ARTHROSCOPY OF THE WRIST.
[32] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > RADIOGRAPHIC TECHNIQUES.
[34] Green S Operative Hand Surgery. Diagnosis and Treatment > Assessment of the Symptomatic Wrist.
[36] Aaos Comprehensive Orthopaedic Review 3. Arthritides of the Hand and Wrist* > IV. Posttraumatic Arthritis.
[37] Green S Operative Hand Surgery. AUTHOR'S PREFERRED METHOD OF TREATMENT: ARTHROSCOPIC PARTIAL WRIST FUSION > Diagnostic Wrist Arthroscopy.
[38] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > ANATOMY.
[39] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Hand and Wrist > VII. The Wrist.
[40] Green S Operative Hand Surgery. WRIST BIOMECHANICS > Carpal Kinematics.
[41] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > CIRCULATION.
[43] Exam Of The Hand Wrist 2Ed. 1.2 SKELETON OF THE WRIST.
[44] Exam Of The Hand Wrist 2Ed. Extension of the wrist > Muscles of wrist extension.
[46] Campbell S Operative Orthopaedics 4 Volume Set. WRIST AND ELBOW.
[49] Green S Operative Hand Surgery. WRIST INVOLVEMENT IN RA.
[50] Tachdjian S Pediatric Orthopaedics From The Texas Scottish Rite Hospital For Children E Book. Wrist Involvement.
[54] Exam Of The Hand Wrist 2Ed. Examination.