Clinicians › Hand
Metacarpophalangeal joint arthroplasty
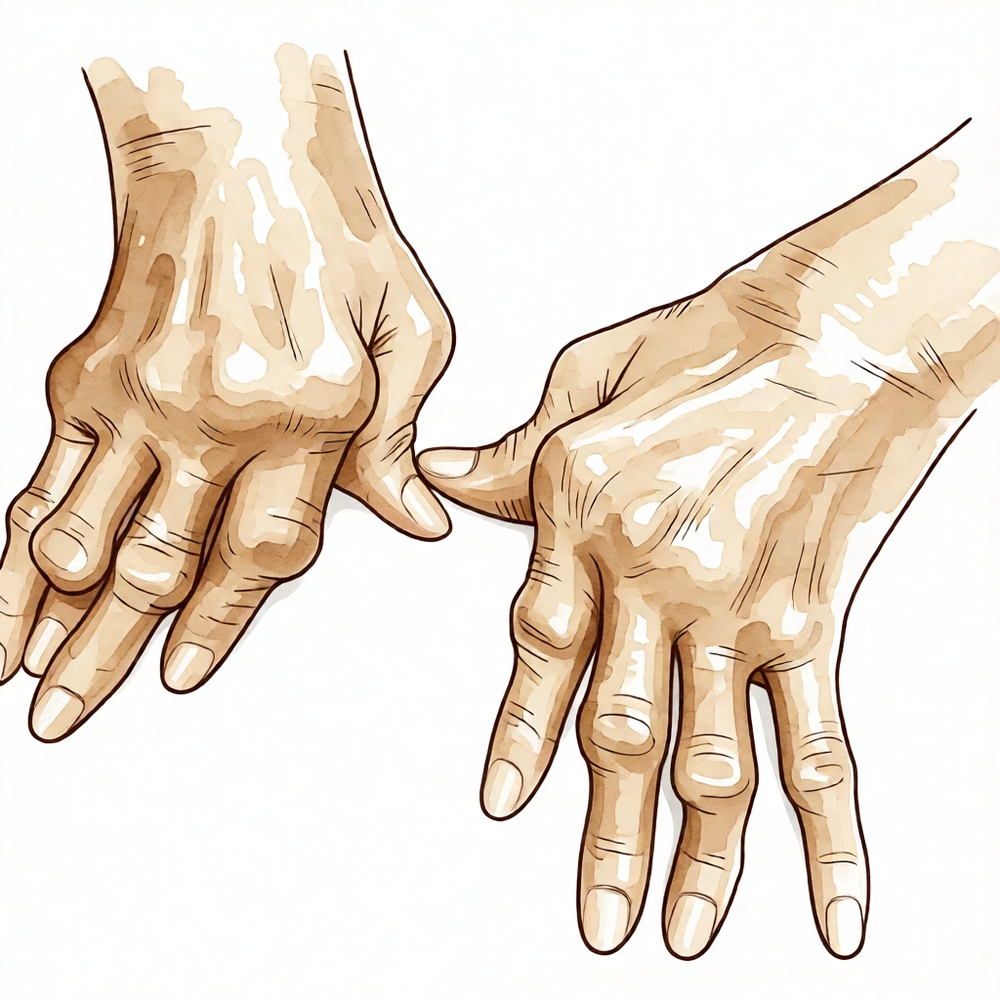
For patients: a plain-language version of this topic is available. See the patient guide.
Overview
Metacarpophalangeal joint arthroplasty remains a central intervention for managing the rheumatoid hand, where outcomes for therapeutic surgeries such as arthroplasty and arthrodesis are generally favorable [1, 41]. The procedure is indicated for arthritic disease provided there is competent ligamentous and capsular support to prevent dislocation and recurrent deformity [4]. It also serves as a viable alternative to joint transfer or fusion in major hand injuries involving destroyed metacarpophalangeal joints [5]. For the advanced thumb, specifically boutonniere rheumatoid deformity, the procedure of choice is MP joint arthroplasty combined with IP joint fusion [35]. Functional improvement in the fingers can be achieved through the combination of interphalangeal joint arthrodesis and metacarpophalangeal prosthetic arthroplasty [3].
Postoperative results demonstrate that the overall average metacarpophalangeal range of motion is 42 degrees, representing an 8-degree increase over preoperative values [2]. While pain relief is generally good for hand joint arthroplasties, high rates of deformity recurrence and complications persist depending on the implant type and joint involved [19]. Specific implant data indicates that pyrocarbon implants for osteoarthritis carry a 7% revision rate at 5 years [11]. A modified suture suspension arthroplasty technique has shown very good stability and improved strength in all operated joints at a mean follow-up of 24 months [16].
The long-term expectations and indications for silicone metacarpophalangeal arthroplasty require careful examination in light of improvements in the medical management of rheumatoid disease [6]. Current evidence notes an apparent lack of appropriate, independent testing for metacarpophalangeal prostheses [8]. The 5-year results of a new total replacement prosthesis are sufficiently encouraging to present the device as a treatment method for arthritic disease with adequate soft-tissue support [4].
Anatomy & Pathophysiology
Bony Anatomy and Kinematics
The hand skeleton comprises 27 bones organized into five rays, each forming a polyarticulated chain of metacarpals and phalanges [45]. The thumb metacarpal is the shortest of the metacarpals, whereas the index metacarpal is the longest [45]. In the sagittal plane, the first metacarpal forms an angle of approximately 45 degrees with the second metacarpal [45]. The transverse axis of the palm, corresponding to the metacarpophalangeal articulations, is oblique and creates an acute angle of approximately 75 degrees with the longitudinal axis [45]. These metacarpophalangeal joints function as the keystones of the hand’s longitudinal arches [91]. The thumb provides approximately 40% of hand function and nearly one-fourth of overall bodily function [29]. The position of the metacarpophalangeal joint influences basal joint loading in the thumb [47].
The thumb metacarpophalangeal joint exhibits a wide range in the magnitude of range of motion and in the normal shape of the metacarpal head, which can be round or flat [53]. Altered thumb rotation patterns during pinch may contribute to joint misalignment and the development of osteoarthritis [116]. Proximal migration of the thumb metacarpal does not appear to influence the functional outcome [25].
Soft Tissue Anatomy
Metacarpophalangeal joint extension is driven by extrinsic extensor force transmitted through the sagittal bands [44]. These bands form a sling that allows proximal extrinsic extensor tension to be transmitted to the proximal phalanx, permitting metacarpophalangeal joint extension without a direct tendinous insertion onto the proximal phalanx [44]. The sagittal band fibers insert onto the volar proximal phalanx and onto the lateral borders of the volar plate [44]. Rupture or attenuation of the sagittal band fibers allows the extrinsic extensor tendon to sublux to the ulnar side of the metacarpal head, causing ulnar deviation of the finger [44].
The metacarpophalangeal joints are stabilized by collateral ligaments and a thick volar articular capsule known as the volar plate [91]. The volar plates of the metacarpophalangeal articulations are interconnected by the deep transverse intermetacarpal ligament, also referred to as the interglenoid ligament [91]. In the thumb, the abductor pollicis brevis, flexor brevis, and adductor pollicis contribute fibers to the extensor mechanism, which includes a transverse hood and oblique fibers [75]. The combined action of these muscles on the distal thumb joints is to flex the metacarpophalangeal joint and extend the interphalangeal joint [75].
The extensor pollicis brevis inserts on the dorsum of the proximal aspect of the proximal phalanx of the thumb and actively extends the metacarpophalangeal joint [44]. The extensor pollicis longus inserts on the distal phalanx and provides forceful extension of the thumb interphalangeal joint [44]. The flexor pollicis longus inserts into the proximal base of the thumb distal phalanx and flexes both the interphalangeal and metacarpophalangeal joints of the thumb [95]. Anatomical studies have identified two annular and one oblique pulley in the thumb flexor tendon sheath [126].
Specific measurements of the thumb volar plate include a radial border of 8.5 ± 1.3 mm, an ulnar border of 8.8 ± 1.0 mm, a proximal border of 7.5 ± 1.0 mm, and a distal border of 7.8 ± 0.6 mm [140]. The distance between the ulnar sesamoid bone and the oblique pulley measures 12.1 ± 1.1 mm, and from the radial sesamoid to the oblique pulley measures 16.6 ± 0.2 mm [140]. The distance between the sesamoids and the base of the proximal phalanx measures 2.2 ± 0.2 mm [140].
The dorsal skin of the hand is thin and has loose connections with deeper planes, allowing free gliding during finger flexion [97]. Flexion at the metacarpophalangeal joint alone requires an average skin lengthening of 1.25 cm, with a range of 1 to 2 cm [97].
Pathophysiology
Thumb metacarpophalangeal instability is commonly found in conjunction with trapeziometacarpal osteoarthritis [18]. Metacarpophalangeal deformities associated with trapeziometacarpal osteoarthritis include hyperextension and valgus types [18]. Primary osteoarthritis of the thumb joints is most commonly encountered in the trapeziometacarpal joint and less commonly in the interphalangeal and metacarpophalangeal joints [29]. The prevalence of primary osteoarthritis in the trapeziometacarpal joint is reported to be as high as 15% in adults over age 30 [29]. As many as one-third of postmenopausal women are affected by trapeziometacarpal joint osteoarthritis [29]. Carpometacarpal and metacarpophalangeal joint collapse is associated with increased pain but not functional impairment in persons with thumb carpometacarpal osteoarthritis [120]. Thumb carpometacarpal joint osteoarthritis reflects the joint's teleology, where pathomechanics drive inflammatory markers and injury to soft tissue structures rather than simple wear and tear [135].
Rheumatoid arthritis is a chronic, progressive, systemic inflammatory disease that affects the musculoskeletal system [64]. The inflammatory process in rheumatoid arthritis results in synovial proliferation, collagenous destruction of cartilage and soft tissues, and bone resorption [64]. The metacarpophalangeal joint is the most common site of involvement in the rheumatoid hand [64].
Palmar metacarpophalangeal dislocation is an infrequent injury with a controversial pathogenic mechanism [28]. One theory suggests that hyperextension results in interposition of the palmar plate between the metacarpal and proximal phalanx, preventing closed reduction [28]. Another theory suggests that hyperflexion associated with proximal translation of the proximal phalanx is followed by inturning of the dorsal aspect of the joint capsule, preventing reduction [28].
Classification
Modified Type 1 Thumb Deformity Classification: A modified classification for Type 1 thumb deformity in rheumatoid arthritis was developed to detect advanced deformity earlier. This system demonstrated a stronger correlation with hand function compared to previous methods [46].
Eaton-Littler Classification: The Eaton-Littler classification system for radiological osteoarthritis of the first carpometacarpal joint demonstrated moderate interobserver agreement among radiologists and hand surgeons [193].
Anatomical Radiological Classification: An anatomically based radiological classification for thumb basal joint arthritis was proposed to differentiate between different forms of the disease to allow for prospective study assessment [174].
Carpometacarpal Arthroplasty Implant Classification: A systematic review classified carpometacarpal arthroplasty implants into four design types: total joint replacement, hemiarthroplasty, interposition arthroplasty, and miscellaneous designs [176].
Silastic Osteolysis Grading System: A grading system for radiographic osteolytic changes after silastic metacarpophalangeal arthroplasty was proposed to classify osteolysis in bones adjacent to prostheses [165].
Palmar Dislocation Classification: A classification for palmar dislocation of the metacarpophalangeal joint distinguishes between acute and chronic dislocations. Acute dislocations are further categorized as reducible or irreducible [54].
Carpometacarpal Osteoarthritic Degeneration Staging: A system for staging carpometacarpal osteoarthritic degeneration grades cartilage lesions on a five-point scale based on location and degree of damage across six anatomical areas [198].
Other Considerations: Ulnar instability is suggested to be included in the classification of thumb carpometacarpal joint osteoarthritis stages and considered in treatment options [180].
Clinical Presentation
Chronic Arthropathy
Rheumatoid arthritis typically involves the metacarpophalangeal and proximal interphalangeal joints of the hand early in the disease course [64]. In the thumb, the metacarpophalangeal joint is usually the most affected by rheumatoid arthritis [60]. Metacarpophalangeal joint disease is common in rheumatoid patients, who have inherent instability at the metacarpophalangeal joint [39]. Compensatory hypermobility and degeneration at the adjacent metacarpophalangeal joint make carpometacarpal joint arthrodesis a second line of treatment in patients who have rheumatoid arthritis [60].
Primary osteoarthritis of the metacarpophalangeal joint is infrequent, even for experienced hand surgeons at busy referral centers [39]. As many as one-third of postmenopausal women are affected by primary osteoarthritis of the trapeziometacarpal joint [29]. Little information is available regarding the prevalence of primary osteoarthritis occurring in the interphalangeal and metacarpophalangeal joints of the thumb [29]. Reports have suggested that chronic repetitive trauma in patients with heavy manual labor may contribute to thumb joint osteoarthritis [29]. Primary osteoarthritis of the metacarpophalangeal joint is considered the best indication for nonconstrained implant design due to good ligamentous support and additional maintenance of stability by border digits [39].
Two types of metacarpophalangeal deformities associated with trapeziometacarpal osteoarthritis are hyperextension and valgus [18]. If not corrected, thumb metacarpophalangeal instability can have detrimental effects on the outcome of trapeziometacarpal osteoarthritis treatment [18]. The main reason for revision of thumb carpometacarpal resection arthroplasty is symptomatic impingement of the thumb metacarpal [40]. The most common pathologies encountered during revision basal joint arthroplasty include trapeziometacarpal instability, unrecognized scaphotrapezoid arthritis, and untreated metacarpophalangeal joint hyperextension [34].
Acute Injury
Palmar metacarpophalangeal dislocation is an infrequent injury [28]. Delay in diagnosis of palmar metacarpophalangeal dislocation is a common feature because of its rarity and the lack of obvious X-ray changes [28]. The mechanism of injury for palmar metacarpophalangeal dislocation was reported as hyperflexion in three cases, hyperextension in one case, and was not described in four cases [28].
The pathogenic mechanism of palmar metacarpophalangeal dislocation is controversial, with two opposing theories proposed by Renshaw and Louis (1973) and Wood and Dobyns (1981) [28]. According to Renshaw and Louis (1973), hyperextension of the metacarpophalangeal joint results in interposition of the palmar plate between the metacarpal and proximal phalanx, preventing closed reduction [28]. Wood and Dobyns (1981) suggest that hyperflexion of the metacarpophalangeal joint associated with proximal translation of the proximal phalanx occurs first, followed by inturning of the dorsal aspect of the joint capsule, preventing reduction [28]. From the literature and a specific case, the mechanism proposed by Wood and Dobyns (1981) seems to be more common for palmar metacarpophalangeal dislocation [28].
Investigations
Clinical Evaluation: A careful physical examination is essential to direct care and future testing if indicated [43]. Clinical evaluation of the hand and wrist requires combining patient history with a careful physical examination to pinpoint or narrow the scope of possible pathologic processes [43]. Diagnostic tests such as imaging and serum laboratory studies are useful in determining hand pathology but can be expensive, time-consuming, and often nonspecific [43].
Plain Radiography: Plain radiographs were 47% sensitive and 94% specific in their ability to detect end-stage scaphotrapezoid joint arthritis in patients with end-stage carpometacarpal arthritis of the thumb base [81]. No radiographic or demographic variables were found to be risk factors for scaphotrapezoid joint arthritis in patients with end-stage carpometacarpal arthritis of the thumb base [81]. Palmar metacarpophalangeal dislocation is an infrequent injury where delay in diagnosis is a common feature because of its rarity and the lack of obvious X-ray changes [28]. Radiographic development of trapeziometacarpal arthrosis is an expected part of human aging, although clinically significant, functionally limiting trapeziometacarpal arthrosis is less common [207]. The development of clinically significant trapeziometacarpal arthrosis may be unrelated to hand use [207].
MRI: MRI demonstrated erosive chondropathy of the metacarpal head in a case of a locked metacarpophalangeal joint, which was confirmed at surgical exploration [157].
Bone Scan: Bone scan uptake after trapeziometacarpal joint arthroplasty progressively decreases over time, with normalization of tracer uptake expected between 14 and 25.5 months after surgery [186].
Other Considerations: Subjects presenting with early thumb carpometacarpal joint osteoarthritis had significantly lower bone density as assessed with Hounsfield units at the thumb carpometacarpal joint [200]. Surgical treatment for congenital stiffness associated with symphalangism at the metacarpophalangeal joint is feasible if the patient has an incompletely restricted joint, a well-segmented joint space, and a relatively round metacarpal head on imaging studies [204].
Treatment
Non-Operative
Surgical management of the arthritic thumb metacarpophalangeal joint is reserved for patients who have failed appropriate nonsurgical measures [188]. Non-operative treatment for thumb base osteoarthritis has not been thoroughly explored, and because surgery may have a strong placebo effect, further evaluation through pragmatic trials comparing surgery versus no surgery or placebo arms is required [151].
Operative
Indications: The goals of surgical intervention for the arthritic thumb metacarpophalangeal joint are pain relief, restoration of function, and prevention of additional insult to neighboring joints [188]. Surgery for arthritis of the hand relieves pain and improves activities of daily living [197]. While pain relief is generally good, high rates of deformity recurrence and complications exist depending on the implant type and joint involved [19]. Implant arthroplasty should be considered as an alternative to arthrodesis in the small subgroup of patients with metacarpophalangeal joint idiopathic osteoarthritis that has been refractory to nonsurgical treatment measures [38].
Surgical Approach / Technique: The volar plate arthroplasty creates a thick interposition substance that blocks bone-to-bone contact, elevates the proximal phalanx, and reestablishes the strong anchorage of the volar plate to the metacarpal [153]. Composite metacarpophalangeal joint reconstruction should be considered in free toe-to-hand procedures when metacarpal head articular cartilage is preserved [36]. The authors have used a described dorsal approach with safety and convenience over a several-year period for repair and reconstruction of both the ulnar and radial collateral ligaments at the thumb metacarpophalangeal joint [150]. Simple traction under local or regional anesthesia allows the locking of the metacarpophalangeal joint to be released in a number of cases [199]. In a case series of locking of the metacarpophalangeal joint of the thumb, 1 chronic case and 4 of 10 cases with a nonround shape of metacarpal heads required open reduction [173]. Recent advances in small joint arthroscopy have allowed for intervention earlier in the disease course for thumb metacarpophalangeal arthritis, although few cases involving the thumb metacarpophalangeal joint have been reported [188].
Implant Selection: The 5-year results of a new total replacement prosthesis are sufficiently encouraging to present this device as a method of treatment in arthritic disease of the metacarpophalangeal joints where there is competent ligamentous and capsular support to prevent dislocation and recurrent deformity [4]. Metacarpophalangeal arthroplasty with a pyrocarbon implant demonstrated reliable improvement in pain and arc of motion in patients with rheumatoid arthritis [37]. Metacarpophalangeal surface replacement arthroplasty for noninflammatory arthritis can improve arc of motion and pain, though 1 in 3 joints requires reoperation [51]. Thumb metacarpophalangeal surface replacement arthroplasty is a viable option for end-stage arthritis with unanimous pain relief in this series [182]. The larger extension and flexion moment arms of the newer implants compared with the Swanson is an advantage to obtaining better clinical motion after metacarpophalangeal implant arthroplasty [69]. Metacarpal phalangeal arthroplasty with silicone Dacron prostheses was shown to be a good operation for pain relief [181].
Other Considerations: Implant arthroplasty provides an alternative to arthrodesis of the metacarpophalangeal joint of the thumb that is most useful when arthrodesis of the interphalangeal joint is considered [33]. In the advanced thumb, metacarpophalangeal joint arthroplasty and interphalangeal joint fusion is the procedure of choice [35]. The most commonly performed procedure for end-stage thumb metacarpophalangeal arthritis in the past half century has been fusion [188]. Concerns regarding loss of range of motion, progression of adjacent joint disease, and implant complications have made arthroplasty a viable alternative to fusion for end-stage thumb metacarpophalangeal arthritis [188]. A fixed hyperextension deformity of the metacarpophalangeal joint constitutes a contraindication to the placement of a constrained trapeziometacarpal prosthesis such as the ARPE prosthesis [160]. Late infection, occurring greater than 6 months after operation, of metacarpophalangeal silicone implants is an unusual complication of arthroplasty [32]. In one case of metacarpophalangeal joint prosthesis malrotation seen on roentgenograms, the finger clinically tracked in line with the other fingers and its range of motion was comparable to the other three metacarpophalangeal joints [17].
Adjuncts: Arthrodesis of the thumb metacarpophalangeal joint using a cannulated screw and threaded washer is effective, reliable, and accomplished easily, with a low incidence of complications [7]. Thumb metacarpophalangeal capsulodesis enhances the result of a basal joint arthroplasty by improving the transmission of force along the thumb ray and by correcting the metacarpal collapse, which produces dorsal subluxation stress on the metacarpotrapezial joint [62]. Preoperative planning for ligament reconstruction and tendon interposition or suspension arthroplasty of the trapeziometacarpal joint must include understanding salvage options to preserve thumb metacarpal stability if the flexor carpi radialis is deficient intraoperatively [67].
Complications
Infection (PJI): Periprosthetic joint infection is uncommon after metacarpophalangeal or proximal interphalangeal arthroplasties [209]. In a series of 325 silicone metacarpophalangeal arthroplasties, infection occurred in seven patients (2%) [136]. A series of 441 silicone-Dacron arthroplasties reported an infection rate of 0.3%, with one deep wound infection requiring prosthesis removal without replacement and one superficial infection cleared with wound care and oral antibiotics [148]. In 54 cemented Steffee arthroplasties of the thumb metacarpophalangeal joint, no early postoperative infections occurred within the first year; however, two implants succumbed to infection at 3 and 5 years postoperatively, attributed to retained K-wires from interphalangeal fusion that protruded through the skin [164]. No superficial or deep infections were reported in 84 second-generation Guepar total arthroplasties of the thumb basal joint [169], 10 revision thumb-base surgeries with Swanson silastic interposition arthroplasty [159], or 10 pyrocarbon metacarpophalangeal joint arthroplasties performed after acute open trauma [162]. In 13 patients treated with the Rubis II prosthesis for trapeziometacarpal osteoarthritis, one infection occurred [223]. Patients receiving intra-articular corticosteroid injection within 3 months before surgery for CMC joint arthritis may face increased risk of repeat surgery for wound complication or infection in the 90-day postoperative period [224]. The incidence of periprosthetic joint infection in patients with rheumatoid arthritis is 1.6 times greater than in those undergoing the same procedure for osteoarthritis [217].
Implant Failure and Fracture: Seventeen percent of combined 4-, 5-, and 6-year follow-up prostheses fractured in a series of silicone-Dacron arthroplasties, with 30 percent of 6-year prostheses fractured; function was not affected by prosthesis fracture, and prostheses were not replaced [26]. Eleven fractures occurred in 41 implanted Sutter metacarpophalangeal prostheses (27% fracture rate), with all ten total fractures of retrieved prostheses occurring at the junction of the distal stem and the hinge [132]. Fourteen prostheses fractured in a series of metacarpophalangeal joint arthroplasties, with all joints demonstrating recurrent deformity [148]. In 54 cemented Steffee arthroplasties of the thumb metacarpophalangeal joint, four arthroplasties were considered failures, including two instances of gross loosening and two implant failures secondary to infection; one grossly loose implant progressed to periprosthetic fracture, treated with implant removal and arthrodesis of the MCP [164]. In 84 second-generation Guepar total arthroplasties of the thumb basal joint, no intraoperative metacarpal or trapezial fractures, dislocations, subluxation between implant components, secondary ossification, allergies to prosthetic materials, or sensory problems of the dorsal side of the thumb were observed; a single surgical revision was necessary at 15 months due to persistent pain secondary to cup loosening [169]. In 13 patients treated with the Rubis II prosthesis for trapeziometacarpal osteoarthritis, complications included six dislocations and nine reoperations [223].
Dislocation and Instability: Dislocation occurred in 27 patients (8%) in a series of 325 cases of silicone metacarpophalangeal arthroplasty [136]. Revision MCP arthroplasty is associated with a relatively high rate of postoperative dislocations [72]. Ulnar drift recurred in forty-nine fingers after Silastic spacer arthroplasty, but was less than 30 degrees in all but one [124]. Recurrence of deformity, specifically ulnar drift, developed in twelve additional patients in a series of metacarpophalangeal joint arthroplasties; in only two patients was the recurrence significant and associated with any loss of function [148]. Recurrent volar subluxation occurred in only one patient in a series of metacarpophalangeal joint arthroplasties, who also fractured her prosthesis twice; one patient developed marked radial deviation associated with prosthesis fracture, and recurrent radial drift was a problem post-operatively in one patient despite dynamic splinting, but did not impair function or require additional surgery [148]. In 84 second-generation Guepar total arthroplasties of the thumb basal joint, three cases of type 1 complex pain syndrome (algodystrophy) appeared [169]. In 89 Weilby tendon interposition arthroplasties, complications included loss of first metacarpal abduction in 4 patients, carpal tunnel compression in 3, trigger thumb in 1, transient oedema of the hand in 2, and reflex sympathetic dystrophy in 5 [127].
Bony Complications and Subsidence: Intraoperative phalanx or metacarpal fracture occurred in six patients (2%) in a series of 325 cases of silicone metacarpophalangeal arthroplasty, with no noted postoperative fractures [136]. No bony fractures were noted in a series of metacarpophalangeal joint arthroplasties [148]. A relationship of any significance between postoperative first metacarpal subsidence and functional outcomes does not appear in a modified suture suspension arthroplasty technique [9]. Ligament reconstruction with tendon interposition and suture-only suspension arthroplasty exhibit equivalent thumb metacarpal subsidence over a greater than 6-month postoperative time frame [84]. Proximal migration of the thumb metacarpal does not appear to influence the functional outcome in ligament reconstruction with or without tendon interposition [25]. In 89 Weilby tendon interposition arthroplasties, the distance between the distal pole of the scaphoid and the base of the first metacarpal averaged 1 cm immediately after operation, was maintained two months later, but decreased to a few millimetres at examination after two years [127]. The main cause of revision for trapeziectomy failures in thumb base osteoarthritis was collapse of the thumb column resulting in arthrogenic contact of the first metacarpal with the scaphoid [77]. The main reason for revision of thumb carpometacarpal resection arthroplasty is symptomatic impingement of the thumb metacarpal, which should be treated with resection of the metacarpal base and scaphotrapezoidal joint [40].
Nerve and Tendon Injury: No nerve or tendon injuries were known to have occurred in a series of metacarpophalangeal joint arthroplasties, and adherence of extensor tendons to skin and underlying tissue was not noted to be a problem [148]. There were no cases of nerve or vascular injuries in a series of 54 cemented Steffee arthroplasties of the thumb metacarpophalangeal joint [164]. In a series of 84 second-generation Guepar total arthroplasties of the thumb basal joint, a secondary rupture of the extensor pollicis longus tendon occurred in one patient six weeks postoperatively, leading to a transfer of the index's extensor tendon [169].
Stiffness and Functional Outcomes: The most common postoperative complication in the hand was joint stiffness, which was most common at the PIP joint, in a series of osteochondral autograft transfers for metacarpophalangeal and interphalangeal cartilage defects [220]. Revision surgery after failed silicone proximal interphalangeal joint arthroplasty was most successful in patients with severe postoperative stiffness [213]. In a series of 10 patients undergoing revision thumb-base surgery with Swanson silastic interposition arthroplasty, persistent post-operative pain can be due to incomplete trapezial resection, neuroma formation due to injury of sensory branches of radial nerve, unrecognized concomitant arthritis in the scaphotrapezoid joint, metacarpophalangeal arthritis, metacarpal base spurs, instability in the metacarpophalangeal joint, and complex regional pain syndrome [159]. Potential concomitant pain sources sought included De Quervain’s tenosynovitis, carpal tunnel syndrome, scaphotrapezoid arthritis, and metacarpal collapse due to thumb metacarpophalangeal joint instability; seven of 17 patients reported to have undergone revision surgery were found to have one of these alternative treatable causes for persistent pain without the need for the revision interpositional arthroplasty technique [159]. One patient required first web space deepening for web space contracture 14 years after arthroplasty [164]. All 10 patients reported that they were satisfied with the results of revision and glad to have had revision surgery; nine patients reported improvement in general ADLs, and one reported no change in these, even though there was improvement in specific tasks [159]. All patients reported an improvement in pinch and ability to open jars after revision; three patients reported improvement in use of keys after revision, and two patients reported improved writing after revision [159]. In a series of 10 pyrocarbon metacarpophalangeal joint arthroplasties performed after acute open trauma, all patients except one reported no or mild pain at the last follow-up, with no cases of revision [162]. Mean total arc of motions for the MCP, proximal interphalangeal, and distal interphalangeal joints were 56 degrees (30° to 70°), 76 degrees (40° to 100°), and 50 degrees (21° to 70°), respectively; postoperative mean grip, oppositional pinch, and appositional pinch strengths were 28, 9, and 11 kg, respectively [162]. The mean follow-up was 4 years; all injuries were the result of a direct laceration over the MCP joint, with six hemi- and four total arthroplasties performed within 24 hours of the initial injury [162]. MCP arthroplasty was performed safely in the setting of acute complex open MCP joint trauma, with patients having preservation of adequate MCP joint motion and experiencing little pain; MCP arthroplasty should be a consideration in cases of open MCP joint trauma to preserve motion, prevent pain, and avoid fusion [162]. The study type was Therapeutic IV, with key words Acute arthroplasty, MCP, metacarpophalangeal joint arthroplasty, pyrocarbon [162].
Other Considerations: In a series of 479 thumb carpometacarpal joint replacements from the Norwegian Arthroplasty Register, current evidence does not support widespread implementation of thumb CMC replacements despite relatively satisfactory implant survivorship [79]. In a series of 89 Weilby tendon interposition arthroplasties, complications included reflex sympathetic dystrophy in 5 patients, transient oedema of the hand in 2, trigger thumb in 1, carpal tunnel compression in 3, and loss of first metacarpal abduction in 4 [127]. The authors were Matthew T. Hou [162].
Recovery
Rehabilitation protocol: Postoperative therapy regimens contribute to an increase in MCP motion and hand function [171]. However, hand therapists remain unaware of the most effective postoperative protocol for MCP arthroplasty or the suitability of each regimen for specific implants and soft-tissue procedures [171]. Rehabilitation following thumb CMC arthroplasty predominantly utilizes clinical expertise, with multiple therapy programs existing [146].
Other Considerations: Joint goal-setting is essential for understanding patients' unique reasons for undergoing MCP arthroplasty and facilitating realistic expectations [177]. Patient expectations of MCP joint arthroplasty were uniformly high, with functional improvement being the greatest motivation for surgery [154]. Patients were satisfied with only modest gains in grip and pinch strength after silicone metacarpophalangeal arthroplasty [225].
Key Evidence
- [L5] Metacarpophalangeal joint arthroplasty continues to play a central role in the management of the rheumatoid hand. [1] (10.1177/17531934261430139)
- [L4] After implant arthroplasty, the overall average metacarpophalangeal range of motion was 42 degrees, which represented an increase of 8 degrees over the preoperative value. [2] (10.1016/0363-5023(93)90100-h)
- [L4] Functional improvement can be obtained in the fingers by interphalangeal joint arthrodesis and metacarpophalangeal prosthetic arthroplasty and in the thumb with metacarpophalangeal and/or interphalangeal arthrodesis. [3] (10.1016/s0363-5023(76)80040-8)
- [L4] The 5 year results of this arthroplasty are sufficiently encouraging to present this device as a method of treatment in arthritic disease of the metacarpophalangeal joints where there is competent ligamentous and capsular support to prevent dislocation and recurrent deformity. [4] (10.1016/s0266-7681(03)00147-5)
- [L4] In major hand injuries with destroyed metacarpophalangeal joints, immediate Swanson arthroplasty is a viable alternative to joint transfer or fusion. [5] (10.1016/j.main.2004.09.008)
- [L4] Given these findings, the indications for and long-term expectations of silicone metacarpophalangeal arthroplasty must be carefully examined in light of the improvements in the medical management of rheumatoid disease. [6] (10.2106/00004623-200310000-00001)
- [L4] This technique for arthrodesis of the thumb metacarpophalangeal joint is effective, reliable, and accomplished easily, with a low incidence of complications. [7] (10.1016/j.jhsa.2004.06.013)
- [L3] The aim of this article is to highlight the apparent lack of appropriate, independent testing of metacarpophalangeal prostheses. [8] (10.1016/j.jhsb.2003.08.008)
- [L4] A relationship of any significance between postoperative first metacarpal subsidence and functional outcomes does not appear. [9] (10.1177/1558944719886669)
- [L4] Metacarpophalangeal arthroplasty using a pyrocarbon implant for osteoarthritis demonstrates a 7% revision rate at 5 years after surgery. [11] (10.1016/j.jhsa.2022.08.013)
- [L4] All operated metacarpophalangeal joints showed very good stability and improved strength with a mean follow-up of 24 months. [16] (10.1016/s1297-3203(01)00061-0)
- [L4] In one case malrotation of a prosthesis for the metacarpophalangeal joint was seen on roentgenograms, but clinically this finger tracked in line with the other fingers and its range of motion was comparable to the other three metacarpophalangeal joints. [17] (10.1016/s0363-5023(79)80109-4)
- [L4] [18] (10.1016/j.hansur.2020.05.013)
- [L4] The review describes various arthroplasty possibilities, indications, and surgical techniques for hand joints, noting that while pain relief is generally good, there are high rates of deformity recurrence and complications depending on the implant type and joint involved. [19] (10.1177/17531934211017703)
- [L1] Furthermore, proximal migration of the thumb metacarpal does not appear to influence the functional outcome. [25] (10.2106/jbjs.d.02630)
- [L4] [26] (10.1016/s0363-5023(77)80070-1)
- [L5] [28] (10.1016/s0266-7681(98)80146-0)
- [L4] [29] (10.1016/j.jhsa.2014.11.026)
- [L5] Late infection, occurring greater than 6 months after operation, of metacarpophalangeal silicone implants is an unusual complication of arthroplasty. [32] (10.1016/0363-5023(92)90131-8)
- [L5] Implant arthroplasty provides an alternative to arthrodesis of the MCP joint of the thumb that is most useful when arthrodesis of the IP joint is considered. [33] (10.1016/s0749-0712(21)00247-x)
- [L4] The most common pathologies encountered during revision basal joint arthroplasty include trapeziometacarpal instability, unrecognized scaphotrapezoid arthritis, and untreated metacarpophalangeal joint hyperextension. [34] (10.1016/j.jhsg.2024.12.004)
- [L4] In the advanced thumb, MP joint arthroplasty and IP joint fusion is the procedure of choice. [35] (10.1016/0363-5023(90)90032-m)
- [L4] Composite metacarpophalangeal joint reconstruction should be considered in free toe-to-hand procedures when metacarpal head articular cartilage is preserved. [36] (10.1016/0363-5023(93)90385-g)
- [L4] Metacarpophalangeal arthroplasty with a pyrocarbon implant demonstrated reliable improvement in pain and arc of motion in patients with RA. [37] (10.1177/15589447211063577)
- [L4] Implant arthroplasty should be considered as an alternative to arthrodesis in the small subgroup of patients who present with MCP joint idiopathic osteoarthritis that has been refractory to nonsurgical treatment measures. [38] (10.1016/j.jhsa.2005.02.011)
- [L5] [39] (10.1016/j.jhsa.2012.11.025)
- [L4] The main reason for revision, symptomatic impingement of the thumb metacarpal, should be treated with resection of the metacarpal base and scaphotrapezoidal joint. [40] (10.1177/17531934211050559)
- [L5] While outcomes are generally favorable for therapeutic surgeries like arthrodesis and arthroplasty, further study is required to determine the best indications for ulnar head arthroplasty. [41] (10.1016/j.jht.2013.12.002)
- [L3] The modified classification could detect advanced deformity earlier and was more strongly correlated with hand function. [46] (10.1177/1753193419886719)
- [L5] [47] (10.2106/00004623-200105000-00009)
- [L4] Metacarpophalangeal SRA for noninflammatory arthritis can improve arc of motion and pain, though 1 in 3 joints requires reoperation. [51] (10.1177/15589447211028917)
- [L4] There is a wide range in the magnitude of the thumb MCP joint ROM and in the normal shape (round vs flat) of the thumb metacarpal head. [53] (10.1016/s0363-5023(03)00303-4)
- [L5] [54] (10.1053/jhsu.2000.jhsu025a0166)
- [L5] [60] (10.1016/j.hcl.2008.03.005)
- [L4] This procedure enhances the result of a basal point arthroplasty by improving the transmission of force along the thumb ray and by correcting the metacarpal collapse, which produces dorsal subluxation stress on the metacarpotrapezial joint. [62] (10.1016/s0363-5023(88)80029-7)
- [L5] [64] (10.5435/00124635-200305000-00005)
- [L4] Preoperative planning must include understanding salvage options to preserve thumb metacarpal stability if the FCR is deficient intraoperatively. [67] (10.1016/j.jhsa.2013.06.014)
- [L3] The authors state that the larger extension and flexion moment arms of the newer implants compared with the Swanson is an advantage to obtaining better clinical motion after metacarpophalangeal implant arthroplasty. [69] (10.1016/j.jhsa.2005.01.014)
- [L4] Revision MCP arthroplasty is a challenging procedure with one in five patients requiring a revision procedure at 5 years and a relatively high rate of postoperative dislocations. [72] (10.5435/jaaos-d-17-00042)
- [L4] [75] (10.2106/00004623-196244070-00010)
- [L4] The main cause of revision was collapse of the thumb column resulting in arthrogenic contact of the first metacarpal with the scaphoid. [77] (10.1016/j.hansur.2021.03.014)
- [L3] Despite relatively satisfactory implant survivorship in our register study, current evidence does not support widespread implementation of thumb CMC replacements. [79] (10.1177/1753193413513988)
- [L3] [81] (10.1177/1558944718765246)
- [L3] LRTI and SSA exhibit equivalent thumb metacarpal subsidence over a greater than 6-month postoperative time frame. [84] (10.1177/15589447221084014)
- [L3] Altered thumb rotation patterns during pinch may contribute to joint misalignment and the development of osteoarthritis. [116] (10.1177/17531934251383073)
- [L3] Future studies should determine the relationship between thumb hypermobility and joint collapse and how to manage these conditions effectively. [120] (10.1016/j.jht.2020.07.003)
- [L3] [124] (10.2106/00004623-198466030-00008)
- [L5] Anatomical studies have identified two annular and one oblique pulley in the thumb. [126] (10.1016/s0363-5023(77)80101-9)
- [L4] [127] (10.1016/0266-7681(87)90062-3)
- [L4] [132] (10.1054/jhsb.2002.0862)
- [L5] The article reviews current evidence suggesting that thumb carpometacarpal joint osteoarthritis reflects the joint's teleology, where pathomechanics drive inflammatory markers and injury to soft tissue structures rather than simple wear and tear. [135] (10.1016/j.jhsa.2018.01.002)
- [L4] [136] (10.1177/1753193418778461)
- [L5] [140] (10.1097/bth.0b013e3182019f92)
- [L4] This study demonstrates that multiple therapy programs exist and rehabilitation following thumb CMC arthroplasty predominantly utilizes clinical expertise. [146] (10.1016/j.jht.2020.10.016)
- [L4] [148] (10.1016/0266-7681(84)90047-0)
- [L5] The authors have used the described dorsal approach with safety and convenience over a several year period for repair and reconstruction of both the ulnar and radial collateral ligaments at the thumb metacarpophalangeal joint. [150] (10.1097/00130911-200403000-00003)
- [Letter] Non-operative treatment for thumb base osteoarthritis has not been thoroughly explored and surgery may have a strong placebo effect, requiring further evaluation through pragmatic trials comparing surgery versus no surgery or placebo arms. [151] (10.1177/17531934211008365)
- [Paper] The volar plate arthroplasty creates a thick interposition substance that blocks bone-to-bone contact, elevates the proximal phalanx, and reestablishes the strong anchorage of the volar plate to the metacarpal. [153] (10.1016/0363-5023(89)90115-9)
- [L1] Patient expectations of MCP joint arthroplasty were uniformly high, with functional improvement being the greatest motivation for surgery. [154] (10.1016/j.jhsa.2011.02.002)
- [L5] In this case, MRI demonstrated erosive chondropathy of the metacarpal head, which was confirmed at surgical exploration. [157] (10.1016/0266-7681(93)90025-b)
- [L4] [159] (10.1177/1753193412447496)
- [L5] Conversely, a fixed hyperextension deformity of the metacarpophalangeal joint constitutes a contraindication to the placement of a constrained trapeziometacarpal prosthesis such as the ARPE prosthesis. [160] (10.1016/s1297-3203(01)00016-6)
- [L4] [162] (10.1016/j.jhsa.2015.09.012)
- [L4] [164] (10.1053/jhsu.2001.21533)
- [L1] [165] (10.1016/j.jhsb.2004.03.019)
- [L4] [169] (10.1016/j.otsr.2008.06.001)
- [L5] This review suggests that all regimens contribute toward an increase in MCP motion and an increase in hand function, but despite the efforts of patients and clinicians, hand therapists remain unaware of the most effective postoperative protocol for MCP arthroplasty or the suitability of each regimen for specific implants and soft-tissue procedures. [171] (10.1197/s0894-1130(03)00156-x)
- [Paper] This case series showed that 1 chronic case and 4 of 10 cases with a nonround shape of metacarpal heads required open reduction. [173] (10.1055/s-0039-3400441)
- [L5] The anatomically based radiological classification that is proposed here aims to differentiate between the different forms of thumb basal joint arthritis so as to allow a prospective study to assess the results. [174] (10.1016/j.hansur.2020.04.013)
- [L4] This systematic review classifies CMC arthroplasty implants into four design types: total joint replacement, hemiarthroplasty, interposition arthroplasty, and miscellaneous designs, providing an overview of strategies, design changes, and biomechanical characteristics of currently available implants for treating osteoarthritis of the thumb. [176] (10.1016/j.jhsa.2019.11.015)
- [L4] Joint goal-setting is essential for understanding patients' unique reasons for undergoing MCP arthroplasty and facilitating realistic expectations. [177] (10.1002/msc.1061)
- [L3] The authors suggest that ulnar instability should be included in the classification of thumb CMCj osteoarthritis stages and considered in treatment options. [180] (10.1055/s-0039-1697650)
- [L4] MP replacement arthroplasty was shown to be a good operation for pain relief. [181] (10.1016/s0363-5023(86)80197-6)
- [L4] Thumb SMPA is a viable option for end-stage arthritis with unanimous pain relief in this series. [182] (10.1177/1558944719878841)
- [L4] Bone scan uptake after trapeziometacarpal joint arthroplasty progressively decreases over time, with normalization of tracer uptake expected between 14 and 25.5 months after surgery. [186] (10.1177/17531934251345359)
- [L5] [188] (10.5435/jaaos-d-18-00683)
- [L3] [193] (10.1016/j.jhsa.2011.06.017)
- [L3] Surgery for arthritis of the hand relieves pain and improves activities of daily living (ADL). [197] (10.1054/jhsb.1998.0211)
- [Paper] [198] (10.1016/s0894-1130(04)00179-6)
- [L4] Simple traction under local or regional anesthesia allows the locking to be released in a number of cases. [199] (10.1016/j.main.2011.01.004)
- [L2] Subjects presenting with early CMC OA had significantly lower bone density as assessed with HU at the thumb CMC joint (trapezium and first metacarpal base). [200] (10.1016/j.jhsa.2017.09.004)
- [L4] Surgical treatment for congenital stiffness associated with symphalangism at the MCP joint is feasible if the patient has an incompletely restricted joint, a well-segmented joint space, and a relatively round metacarpal head on imaging studies. [204] (10.1016/j.jhsa.2006.04.008)
- [L5] Radiographic development of trapeziometacarpal arthrosis is an expected part of human aging, although clinically significant, functionally limiting trapeziometacarpal arthrosis is less common, and its development may be unrelated to hand use. [207] (10.1016/j.jhsa.2015.04.038)
- [L4] PJI is uncommon after MCP or PIP arthroplasties. [209] (10.1016/j.jhsa.2024.12.008)
- [L4] Revision surgery after failed silicone proximal interphalangeal joint arthroplasty was most successful in patients with severe postoperative stiffness. [213] (10.1016/j.jhsa.2013.11.035)
- [L4] The incidence of periprosthetic joint infection among patients with rheumatoid arthritis is 1.6 times greater than in patients undergoing the same procedure for osteoarthritis, potentially due to immunosuppressive therapies. [217] (10.1016/j.arth.2017.11.031)
- [L4] In their experience, the most common postoperative complication in the hand was joint stiffness, which was most common at the PIP joint. [220] (10.1097/bth.0000000000000128)
- [L4] Complications occurred in 13 patients, including 9 reoperations, 6 dislocations, and 1 infection. [223] (10.1016/j.main.2013.10.080)
- [L2] Patients who receive an intra-articular corticosteroid injection within the 3 months before surgery for CMC joint arthritis may be at increased risk of repeat surgery to treat a wound complication/infection in the 90-day postoperative period. [224] (10.1016/j.jhsa.2021.04.010)
- [L2] Patients were satisfied with only modest gains in grip and pinch strength after silicone metacarpophalangeal arthroplasty. [225] (10.1016/j.jhsa.2011.09.042)
See Also
References
[1] Balancing metacarpophalangeal joint arthroplasty in rheumatoid arthritis. Journal of Hand Surgery (European Volume). 2026. DOI: 10.1177/17531934261430139
[2] Motion after metacarpophalangeal joint reconstruction in rheumatoid disease. The Journal of Hand Surgery. 1993. DOI: 10.1016/0363-5023(93)90100-h
[3] Opera-glass hand in rheumatoid arthritis. The Journal of Hand Surgery. 1976. DOI: 10.1016/s0363-5023(76)80040-8
[4] Five-Year Results of a New Total Replacement Prosthesis for the Finger Metacarpo-phalangeal Joints. Journal of Hand Surgery. 2003. DOI: 10.1016/s0266-7681(03)00147-5
[5] Arthroplasties métacarpophalangiennes en urgence par implant de Swanson dans les traumatismes pluritissulaires complexes de la main. À propos de deux cas revus à 14 ans. Chirurgie de la Main. 2004. DOI: 10.1016/j.main.2004.09.008
[6] METACARPOPHALANGEAL JOINT ARTHROPLASTY IN RHEUMATOID ARTHRITIS. The Journal of Bone and Joint Surgery-American Volume. 2003. DOI: 10.2106/00004623-200310000-00001
[7] Arthrodesis of the thumb metacarpophalangeal joint using a cannulated screw and threaded washer. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.06.013
[8] Snapping the Fingers. Journal of Hand Surgery. 2003. DOI: 10.1016/j.jhsb.2003.08.008
[9] A Modified Suture Suspension Arthroplasty Technique for the Treatment of Basal Joint Arthritis: Short- to Intermediate-Term Outcomes. HAND. 2020. DOI: 10.1177/1558944719886669
[11] Metacarpophalangeal Joint Pyrocarbon Arthroplasty for Osteoarthritis: An Analysis of 44 Arthroplasties. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2022.08.013
[16] Une technique originale de stabilisation des métacarpophalangiennes des mains cubitales : «La capsuloplastie transosseuse à forage antéropostérieur ». Chirurgie de la Main. 2001. DOI: 10.1016/s1297-3203(01)00061-0
[17] A cone-shaped reamer for use with Swanson-design hand joint implants. The Journal of Hand Surgery. 1979. DOI: 10.1016/s0363-5023(79)80109-4
[18] Metacarpophalangeal joint instability in trapeziometacarpal osteoarthritis: A systematic review. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.05.013
[19] Arthroplasty in the hand: what works and what doesn’t?. Journal of Hand Surgery (European Volume). 2021. DOI: 10.1177/17531934211017703
[25] Ligament Reconstruction with or without Tendon Interposition to Treat Primary Thumb Carpometacarpal Osteoarthritis. Journal of Bone and Joint Surgery. 2005. DOI: 10.2106/jbjs.d.02630
[26] Metacarpophalangeal joint arthroplasty with silicone-Dacron prostheses (Niebauer type): Six and a half years' experience. The Journal of Hand Surgery. 1977. DOI: 10.1016/s0363-5023(77)80070-1
[28] Palmar Metacarpophalangeal Joint Dislocation. Journal of Hand Surgery. 1998. DOI: 10.1016/s0266-7681(98)80146-0
[29] Management of Osteoarthrosis of the Thumb Joints. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.11.026
[32] Sequential infection of silicone metacarpophalangeal joint arthroplasties resulting from skin breakdown. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90131-8
[33] IMPLANT ARTHROPLASTY OF THE METACARPOPHALANGEAL JOINT OF THE THUMB. Hand Clinics. 2001. DOI: 10.1016/s0749-0712(21)00247-x
[34] Failed Thumb Basal Joint Arthroplasty: An Analysis of Common Etiologies Leading to Reoperation. Journal of Hand Surgery Global Online. 2025. DOI: 10.1016/j.jhsg.2024.12.004
[35] Boutonniere rheumatoid thumb deformity. The Journal of Hand Surgery. 1990. DOI: 10.1016/0363-5023(90)90032-m
[36] Composite finger metacarpophalangeal joint reconstruction in combined second and third free toe-to-hand transfers. The Journal of Hand Surgery. 1993. DOI: 10.1016/0363-5023(93)90385-g
[37] Outcomes of Pyrocarbon Arthroplasty in Metacarpophalangeal Joints Affected by Rheumatoid Arthritis. HAND. 2022. DOI: 10.1177/15589447211063577
[38] Silicone Implant Arthroplasty in Patients With Idiopathic Osteoarthritis of the Metacarpophalangeal Joint. The Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsa.2005.02.011
[39] Clinical and Radiographic Outcomes of Metacarpophalangeal Joint Pyrolytic Carbon Arthroplasty for Osteoarthritis. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2012.11.025
[40] Outcomes and recommendations for revision of thumb carpometacarpal resection arthroplasty. Journal of Hand Surgery (European Volume). 2021. DOI: 10.1177/17531934211050559
[41] Update on the surgical treatment for rheumatoid arthritis of the wrist and hand. Journal of Hand Therapy. 2014. DOI: 10.1016/j.jht.2013.12.002
[43] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[44] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > Image DISORDERS OF THE MUSCULATURE OF THE HAND.
[45] Exam Of The Hand Wrist 2Ed. 1.1 SKELETON OF THE HAND > The osseous skeleton.
[46] A modified Terrono classification for Type 1 thumb deformity in rheumatoid arthritis: a cross-sectional analysis. Journal of Hand Surgery (European Volume). 2019. DOI: 10.1177/1753193419886719
[47] Influence of Metacarpophalangeal Joint Position on Basal Joint-Loading in the Thumb. The Journal of Bone and Joint Surgery-American Volume. 2001. DOI: 10.2106/00004623-200105000-00009
[51] Outcomes of Surface Replacement Arthroplasty in Metacarpophalangeal Joints Affected by Noninflammatory Arthritis. HAND. 2021. DOI: 10.1177/15589447211028917
[53] Motion and morphology of the thumb metacarpophalangeal joint. The Journal of Hand Surgery. 2003. DOI: 10.1016/s0363-5023(03)00303-4
[54] Irreducible palmar metacarpophalangeal joint dislocation due to junctura tendinum interposition: A case report and review of the literature. The Journal of Hand Surgery. 2000. DOI: 10.1053/jhsu.2000.jhsu025a0166
[60] The Rheumatoid Thumb. Hand Clinics. 2008. DOI: 10.1016/j.hcl.2008.03.005
[62] Thumb metacarpophalangeal capsulodesis: An adjunct procedure to basal joint arthroplasty for collapse deformity of the first ray. The Journal of Hand Surgery. 1988. DOI: 10.1016/s0363-5023(88)80029-7
[64] Metacarpophalangeal Joint Arthroplasty in Rheumatoid Arthritis. Journal of the American Academy of Orthopaedic Surgeons. 2003. DOI: 10.5435/00124635-200305000-00005
[67] Salvage Options for Flexor Carpi Radialis Tendon Disruption During Ligament Reconstruction and Tendon Interposition or Suspension Arthroplasty of the Trapeziometacarpal Joint. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2013.06.014
[69] Metacarpophalangeal Joint Mechanics After 3 Different Silicone Arthroplasties. The Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsa.2005.01.014
[72] Revision Metacarpophalangeal Arthroplasty: A Longitudinal Study of 128 Cases. Journal of the American Academy of Orthopaedic Surgeons. 2019. DOI: 10.5435/jaaos-d-17-00042
[75] Surgery of the Thumb in Rheumatoid Arthritis. The Journal of Bone & Joint Surgery. 1962. DOI: 10.2106/00004623-196244070-00010
[77] Revision of trapeziectomy failures in thumb base osteoarthritis: retrospective analysis of ten cases and review of the literature. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2021.03.014
[79] The results of 479 thumb carpometacarpal joint replacements reported in the Norwegian Arthroplasty Register. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193413513988
[81] Comparison of Radiographic and Intraoperative Visual Assessment of Scaphotrapezoid Joint Arthritis in Patients With End-Stage Carpometacarpal Arthritis of the Thumb Base. HAND. 2018. DOI: 10.1177/1558944718765246
[84] Radiographic Thumb Metacarpal Subsidence Following Ligament Reconstruction With Tendon Interposition and Suture-Only Suspension Arthroplasty in the Treatment of Basal Joint Arthritis. HAND. 2022. DOI: 10.1177/15589447221084014
[91] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[95] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > FLEXOR TENDON INJURY.
[97] Exam Of The Hand Wrist 2Ed. The dorsal skin.
[116] Thumb rotation patterns during pinch in patients with trapeziometacarpal osteoarthritis. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934251383073
[120] Carpometacarpal and metacarpophalangeal joint collapse is associated with increased pain but not functional impairment in persons with thumb carpometacarpal osteoarthritis. Journal of Hand Therapy. 2021. DOI: 10.1016/j.jht.2020.07.003
[124] Metacarpophalangeal joint implant arthroplasty with a Silastic spacer.. The Journal of Bone & Joint Surgery. 1984. DOI: 10.2106/00004623-198466030-00008
[126] Anatomy of the flexor tendon sheath and pulleys of the thumb. The Journal of Hand Surgery. 1977. DOI: 10.1016/s0363-5023(77)80101-9
[127] Weilby tendon interposition arthroplasty for osteoarthritis of the trapezial joints. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90062-3
[132] A Comparison of ex vivo and in vitro Sutter Metacarpophalangeal Prostheses. Journal of Hand Surgery. 2003. DOI: 10.1054/jhsb.2002.0862
[135] The Teleology of the Thumb: On Purpose and Design. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.01.002
[136] Long-term outcomes of silicone metacarpophalangeal arthroplasty: a longitudinal analysis of 325 cases. Journal of Hand Surgery (European Volume). 2018. DOI: 10.1177/1753193418778461
[140] Treatment of Hyperextension Deformity of the Thumb Metacarpophalangeal Joint in Basal Joint Arthritis. Techniques in Hand & Upper Extremity Surgery. 2011. DOI: 10.1097/bth.0b013e3182019f92
[146] Practice patterns following carpometacarpal (CMC) arthroplasty. Journal of Hand Therapy. 2022. DOI: 10.1016/j.jht.2020.10.016
[148] Metacarpophalangeal Joint Arthroplasty Eleven Year Follow-up Study. Journal of Hand Surgery. 1984. DOI: 10.1016/0266-7681(84)90047-0
[150] Surgical Approaches to the Metacarpophalangeal Joint of the Thumb for Repair and Reconstruction of the Collateral Ligaments and Capsule. Techniques in Hand and Upper Extremity Surgery. 2004. DOI: 10.1097/00130911-200403000-00003
[151] Letter about a Published Paper. Journal of Hand Surgery (European Volume). 2021. DOI: 10.1177/17531934211008365
[153] The metacarpophalangeal volar plate arthroplasty. The Journal of Hand Surgery. 1989. DOI: 10.1016/0363-5023(89)90115-9
[154] Hand Appearance as a Patient Motivation for Surgery and a Determinant of Satisfaction with Metacarpophalangeal Joint Arthroplasty for Rheumatoid Arthritis. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2011.02.002
[157] Diagnosis of the Aetiology of a Locked Metacarpophalangeal Joint Using MRI. Journal of Hand Surgery. 1993. DOI: 10.1016/0266-7681(93)90025-b
[159] The use of Swanson silastic interposition arthroplasty in revision thumb-base surgery for failed trapeziectomy; a case series of 10 patients. Journal of Hand Surgery (European Volume). 2012. DOI: 10.1177/1753193412447496
[160] Les problèmes de l'articulation métacarpophalangienne dans le traitement chirurgical de la rhizarthrose par prothèse contrainte type ARPE. Chirurgie de la Main. 2001. DOI: 10.1016/s1297-3203(01)00016-6
[162] Metacarpophalangeal Joint Arthroplasty in the Setting of Trauma. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.09.012
[164] Long-term results of cemented Steffee arthroplasty of the thumb metacarpophalangeal joint. The Journal of Hand Surgery. 2001. DOI: 10.1053/jhsu.2001.21533
[165] Grading of Radiographic Osteolytic Changes after Silastic Metacarpophalangeal Arthroplasty and a Prospective Trial of Osteolysis Following Use of Swanson and Sutter Prostheses. Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsb.2004.03.019
[169] Second generation Guepar total arthroplasty of the thumb basal joint: 50 months follow-up in 84 cases. Orthopaedics & Traumatology: Surgery & Research. 2009. DOI: 10.1016/j.otsr.2008.06.001
[171] Postoperative therapy after metacarpophalangeal arthroplasty. Journal of Hand Therapy. 2003. DOI: 10.1197/s0894-1130(03)00156-x
[173] Treatment of Locking of the Metacarpophalangeal Joint of the Thumb. Journal of Hand and Microsurgery. 2020. DOI: 10.1055/s-0039-3400441
[174] Anatomically based radiological classification of thumb basal joint arthritis. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.04.013
[176] Trends in Trapeziometacarpal Implant Design: A Systematic Survey Based on Patents and Administrative Databases. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2019.11.015
[177] Patients' Expectations, Experiences and the Determinants of Satisfaction related to Metacarpophalangeal Arthroplasty. Musculoskeletal Care. 2013. DOI: 10.1002/msc.1061
[180] Treatment of Severe Ulnar Instability of the MCP Joint Improves Function in LRTI Arthroplasty for Osteoarthritis of the Thumb CMC Joint. Journal of Wrist Surgery. 2019. DOI: 10.1055/s-0039-1697650
[181] Long-term follow-up of metacarpal phalangeal arthroplasty with silicone Dacron prostheses. The Journal of Hand Surgery. 1986. DOI: 10.1016/s0363-5023(86)80197-6
[182] Long-term Outcomes of Silastic Arthroplasty of the Thumb Metacarpophalangeal Joint. HAND. 2019. DOI: 10.1177/1558944719878841
[186] Bone scintigraphy in trapeziometacarpal joint replacement. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934251345359
[188] Thumb Metacarpophalangeal Joint Arthritis. Journal of the American Academy of Orthopaedic Surgeons. 2019. DOI: 10.5435/jaaos-d-18-00683
[193] Interobserver Agreement of the Eaton-Littler Classification System and Treatment Strategy of Thumb Carpometacarpal Joint Osteoarthritis. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2011.06.017
[197] Hand Surgery and Quality of Life. Journal of Hand Surgery. 1999. DOI: 10.1054/jhsb.1998.0211
[198] The human first carpometacarpal joint: Osteoarthritic degeneration and 3-dimensional modeling. Journal of Hand Therapy. 2004. DOI: 10.1016/s0894-1130(04)00179-6
[199] Blocage de l’articulation métacarpophalangienne : à propos de quatre cas. Chirurgie de la Main. 2011. DOI: 10.1016/j.main.2011.01.004
[200] Changes in Local Bone Density in Early Thumb Carpometacarpal Joint Osteoarthritis. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2017.09.004
[204] Surgical Treatment for a Congenitally Stiff Metacarpophalangeal Joint of the Small Finger: Report of Four Cases. The Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsa.2006.04.008
[207] Epidemiology of Trapeziometacarpal Arthrosis. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.04.038
[209] Incidence and Presentation of Periprosthetic Joint Infection After Primary Metacarpophalangeal and Proximal Interphalangeal Arthroplasty. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2024.12.008
[213] Revision Arthroplasty for Failed Silicone Proximal Interphalangeal Joint Arthroplasty: Indications and 8-Year Results. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2013.11.035
[217] Rheumatoid Arthritis, Disease Modifying Agents, and Periprosthetic Joint Infection: What Does a Joint Surgeon Need to Know?. The Journal of Arthroplasty. 2018. DOI: 10.1016/j.arth.2017.11.031
[220] Osteochondral Autograft Transfer for Treatment of Metacarpophalangeal and Interphalangeal Cartilage Defects. Techniques in Hand & Upper Extremity Surgery. 2016. DOI: 10.1097/bth.0000000000000128
[223] Prise en charge de l’arthrose trapézo-métacarpienne par prothèse Rubis II. Bilan à 5ans. Chirurgie de la Main. 2013. DOI: 10.1016/j.main.2013.10.080
[224] Risk of Infection in Thumb Carpometacarpal Surgery After Corticosteroid Injection. The Journal of Hand Surgery. 2021. DOI: 10.1016/j.jhsa.2021.04.010
[225] Objective Functional Outcomes and Patient Satisfaction After Silicone Metacarpophalangeal Arthroplasty for Rheumatoid Arthritis. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2011.09.042