Clinicians › General-Health
Bone Healing and Remodelling
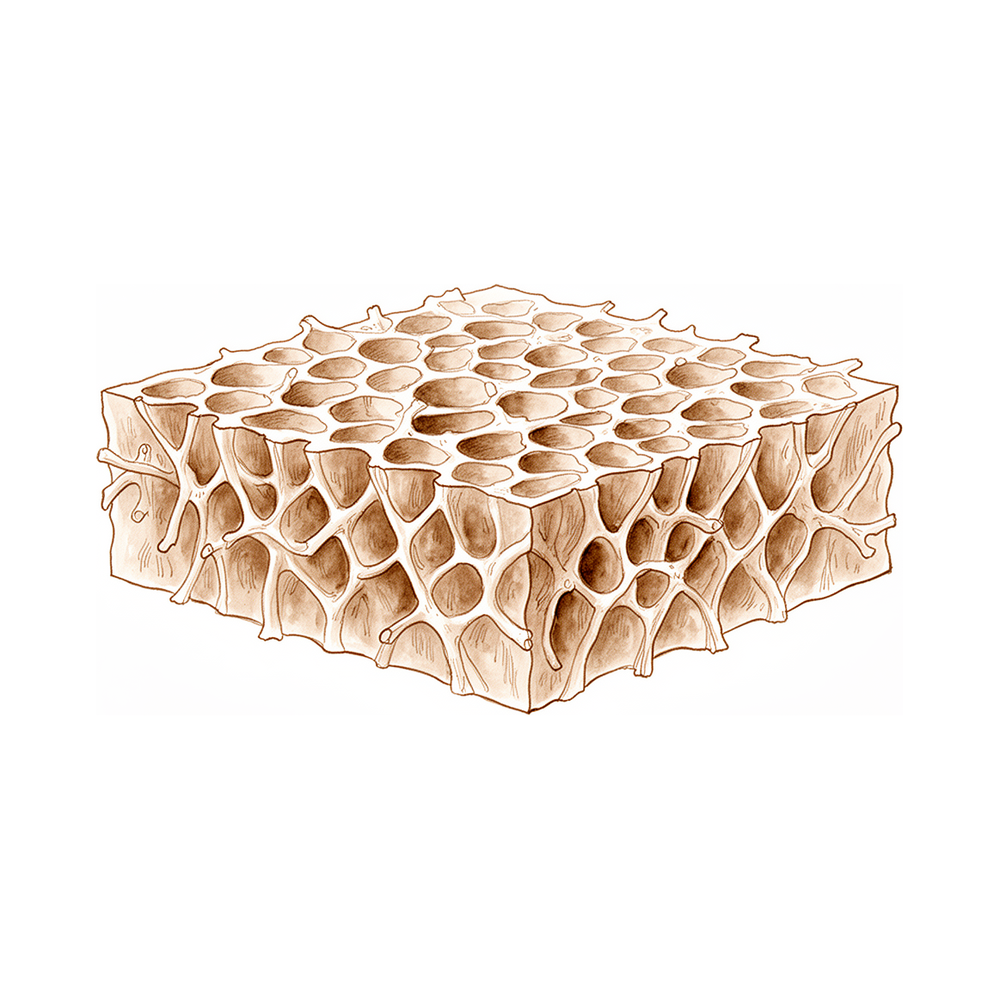
Overview
Bone repair proceeds through regeneration rather than simple healing, a complex physiological process involving recruitment, modulation, and osteoconduction that occurs during normal fracture healing and continuous adult remodelling [1, 2]. The primary objective is to regenerate mineralized tissue in the fracture area and restore mechanical strength [16]. Successful healing requires the uninterrupted progression of biological events within a favourable mechanical environment [22]; consequently, accurate reduction is a requisite, as adverse mechanical conditions associated with various immobilization techniques can significantly compromise normal fracture healing [72].
The biological landscape is dynamic, with M2 macrophages clearly prevalent during the ossification phase [28]. Immunomodulation is emerging as a potential therapeutic target to improve healing [3], although identification and targeted interventions for inflammation-induced bone resorption remain limited, necessitating further research for early detection and treatment [8]. In the context of bacterial infection, bone loss and new bone formation coincide as part of the local tissue response, representing related processes [38]. While current evidence regarding growth factors accelerating fracture healing is promising, results must be interpreted with caution until phase III, level I studies become available [4].
Clinical management requires careful consideration of adjuncts and comorbidities. There is no clinical evidence to support the use of PRP for long-bone defects and nonunions [19], whereas the use of PRF/BMSC during standard procedures is effective in shortening nonunion healing time [68]. Tissue engineering offers a developing option to reduce bone graft limitations and improve healing of fractures and defects [18]. Physicians should consider only short-term administration of COX-2 inhibitors or other drugs for pain management during the fracture healing phase [14]. Proper recognition of osteoporosis etiology is essential for improving bone health and preventing further loss [71]. The manner of skeletal reconstruction depends on defect location and size, anticipated growth and functional needs, and weighed procedural risks [31]. Developing additional measures to assess biological healing will improve reliability and permit assessment of healing stages [6]. Despite numerous studies over the last three decades, there is still no hard proof whether traumatic brain injury results in accelerated fracture healing, and the pathophysiological background remains unclarified [37].
How It Works
Fundamental Processes and Goals
Bone regeneration is a complex, well-orchestrated physiological process of bone formation that occurs during normal fracture healing and continuous remodelling throughout adult life [2]. Fracture healing is a complex physiologic process involving a combination of intramembranous and enchondral ossification, driven by the interplay of host biology (progenitor cells, growth factors, ECM) and the mechanical environment [49]. The biology of fracture healing is a complex biological process that follows specific regenerative patterns and involves changes in the expression of several thousand genes [47].
Molecular and Cellular Mechanisms
The balance between signalling molecules involved in bone formation with their inhibitors, particularly between BMPs and their antagonists, is a critical determinant of osteogenesis, skeletal development, fracture repair, and bone remodelling [7]. Alterations of the BMP signaling pathway, either by direct targeting of the BMPs or by their inhibitors, interfere with embryologic skeletal development and postnatal regenerative repair following skeletal trauma [45]. Insights into TGFβ/BMP signaling open new prospects for generating novel therapies against clinical disorders [41]. Understanding cellular and molecular pathways is critical for advancing fracture treatment and understanding skeletal growth, repair, and aging [42]. Knowledge of key pathways in bone biology can improve surgeon understanding, clinical recognition, and treatment of bone homeostasis–related diseases [9]. Periostin plays an important role in fracture healing, and therapeutically targeting the age-related decrease in periostin may improve healing outcomes in older populations [15]. Therapeutic suppression of osteoclast Notch signaling presents a balanced paradigm for increasing bone formation, regeneration, and healing [40].
Immune and Inflammatory Modulation
Understanding the effects of standard orthopaedic interventions on the local and systemic inflammatory responses and early fracture healing is important for optimizing fracture union [23].
Biological Influences and Pathologies
Type 2 diabetes impacts bone fracture healing through mechanisms such as impaired vascularity, enhanced inflammation, altered bone turnover, and the generation of advanced glycation end products (AGEs) that reduce bone quality [25]. Hypoxia can modify bone remodeling, although clinical studies have shown contradictory results [24]. Stress fractures arise when bone stresses exceed the capacity of bone to withstand and heal from those stresses, resulting from either excessive bone strain with microdamage accumulation or depressed bony remodeling in response to normal strain [48]. Increased bone resorption occurs at an early stage in the development of osteoarthritis, and blocking bone-resorbing cytokines prevents cartilage damage [46].
Remodelling and Regeneration
Bone remodeling is a process whose current understanding and regulation are outlined in scientific literature [17]. Site-specific remodeling appears to be responsible for corticalization and marrow regeneration [43]. Bone grafting enhances bone regeneration and fracture healing through osteoconductive, osteoinductive, and osteogenic capacities [29].
Assessment and Modelling
Computational modeling findings quantified the effects of the initial healing phase on healing outcome to better understand the biological and mechanobiological mechanisms and their utilization in the design and optimization of treatment strategies [21]. Drilled hole defects in mouse femur enable experimental genetics studies to investigate the cellular and molecular mechanisms of spontaneous cortical and cancellous bone repair and may be useful for pharmacological studies [39].
Therapeutic Interventions
Prospective, randomised, double-blind, placebo-controlled trials demonstrate the clinical efficacy of ultrasound in accelerating fracture healing [11]. The combined action of low-dose FGF-2 and BMP-2 increases the speed and extent of bone healing and may be a solution to the current problems with high-dose BMP-2 [12]. In direct percutaneous gene delivery for segmental bone defects, the repair tissue is predominantly trabecular bone, has normal bone mineral content, and has gained mechanical strength [5]. Further understanding of the biology of fracture repair may lead to improved treatment modalities [44].
What the Evidence Shows
Fundamental Mechanisms and Physiology
Bone loss and new bone formation coincide as part of the local tissue response to a bacterial infection [38]. Type 2 diabetes impacts bone fracture healing through mechanisms including impaired vascularity, enhanced inflammation, altered bone turnover, and the generation of advanced glycation end products (AGEs) that reduce bone quality [25]. An age-related decrease in periostin expression may be associated with attenuated fracture healing in old mice [15]. Therapeutically targeting this age-related decrease in periostin may improve healing outcomes in older populations [15].
Inflammation and Immune Response
Identification and targeted interventions for inflammatory induced bone resorption remain limited, requiring further research to advance early detection and treatments [8].
Biological Adjuncts and Growth Factors
PRP use for bone healing appears only beneficial when used in combination with osteoconductive scaffolds, though neither allograft nor autograft appear to be appropriate carriers [65]. Combinatory use of PRP and hyperbaric oxygen (HBO) resulted in increased bone regeneration and neovascularization compared to all other groups [66]. The evidence for bone healing shows promising results, particularly for mesenchymal stem cells (MSCs) and BMP in the treatment of non-unions [62]. Available literature for the use of biologic therapies in stress fractures is restricted, with most reports using biologics as a supplement to surgical fixation in studies lacking control groups [74]. Local and regional gene therapy has improved healing in preclinical trials of articular and other musculoskeletal conditions [60]. In a rabbit ulnar osteotomy model, osteotomy sites treated with rhBMP-2 healed approximately 33% faster than sites treated with buffer or left untreated, with mechanical properties as much as twofold greater at three and four weeks [59]. In a study of direct percutaneous gene delivery for segmental bone defects, the repair tissue was predominantly trabecular bone, had normal bone mineral content, and had gained mechanical strength [5].
Bone Grafting and Biomaterials
The success of bone grafting depends on the active participation of the graft in reparative osteogenesis, with conditions for successful grafting being early vascularization and a vital graft [61]. Cell therapy holds promise as an alternative to autologous bone grafting for promoting bone repair, avoiding drawbacks such as donor-site morbidity and loss of bone stock [26]. The advantages of delayed primary bone grafting include primary bone healing, a shorter rehabilitation period, fewer operations, avoidance of wound contracture, and bone grafting in a well-vascularized scar-free bed [34]. The use of xenogeneic demineralized bone implants promotes induced osteogenesis and rapid healing, avoids harvesting procedures, and offers a potentially unlimited supply of banked material [35]. A study of demineralized bone powder demonstrated a 100% success rate in bone healing as interpreted by an independent observer, with no evidence of secondary graft resorption or recurrence of the lesion [20]. Correct formulation and design of the graft to ensure adequate osteo-activity and resorption appears intrinsic to a successful outcome for coral bone substitutes [69].
Physical Modalities and Adjuncts
In the surgical treatment of stable knee osteochondral defect (OCD) lesions, bone stimulator use did not appear to improve radiographic or clinical healing [63].
Pharmacological Considerations
Animal data and limited scientifically robust clinical evidence in humans indicate that physicians should consider only short-term administration of COX-2 inhibitors or other drugs in the pain management of patients in the phase of fracture or other bone defect healing [14]. The balance of evidence suggests that a short-duration NSAID regimen is a safe and effective supplement to other modes of post-fracture pain control, without a significantly increased risk of sequelae related to disrupted healing [30].
Distraction Osteogenesis
In cases of distraction osteogenesis through high energy fractures, bone formation at the distracted fracture site was satisfactory and times for regenerate consolidation were similar to those seen in standard corticotomies [70]. Well-designed clinical studies are needed to establish safe and effective guidelines for various modalities to enhance new bone formation during distraction osteogenesis in children [32]. Current techniques for evaluating bone healing during distraction osteogenesis provide novel and significant information for evaluating bone healing in the future [73].
Specific Clinical Scenarios and Outcomes
In a study of bilateral hand transplantation under immunosuppression with tacrolimus, mycophenolate mofetil, and prednisolone, ingrowth of small vessels at the bone junction was observed at week 3, calcified callus became visible at month 4, and bone union was completed at month 11 [55]. All nonunions and fractures healed after an average of 5 months in a study using cement spacers with antibiotics for posttraumatic infected nonunions and bone defects of the upper extremity [67]. A breakthrough is envisaged to allow treatment of bone loss and non-union in a more efficient, reliable, and accelerated manner [33].
Practical Considerations
Biological Mechanisms and Regulation
The balance between signalling molecules involved in bone formation and their inhibitors, particularly between BMPs and their antagonists, is a critical determinant of osteogenesis, skeletal development, fracture repair, and bone remodelling [7]. During the ossification phase of bone fracture healing, M2 macrophages are clearly prevalent [28]. Additionally, an age-related decrease in periostin expression may be associated with attenuated fracture healing in old mice [15].
Pharmacological and Medical Management
Increasing physician awareness of medication side effects allows for the monitoring of bone health and the implementation of therapeutic interventions to prevent or treat drug-induced osteoporosis [53].
Surgical Techniques and Grafting
Autologous bone graft remains the gold standard for enhancing fracture healing, though limitations include low graft volume and donor site morbidity [58]. The advantages of delayed primary bone grafting include primary bone healing, a shorter rehabilitation period, fewer operations, avoidance of wound contracture, and bone grafting in a well-vascularized scar-free bed [34]. The application of rhBMP-7 as a bone-stimulating agent is safe and serves as a powerful adjunct for the treatment of persistent upper and lower limb non-unions [57].
Bone grafting alternatives offer osteoconductive, osteoinductive, and osteogenic properties with limited morbidity compared to traditional iliac crest harvesting [56]. The ideal bone-graft substitute is biocompatible, bioresorbable, osteoconductive, osteoinductive, structurally similar to bone, easy to use, and cost-effective [54]. Currently marketed bone-graft substitute products vary in composition and mechanism [54].
Adjunctive Therapies and Emerging Strategies
The major constraints for routine use of BMP are inadequate clinical trials in humans and the need to comprehensively assess the cost-effectiveness and budget impact of BMP [52].
Clinical Assessment and Outcomes
In the context of direct percutaneous gene delivery for segmental bone defects, the repair tissue is predominantly trabecular bone, has normal bone mineral content, and has gained mechanical strength [5]. One study demonstrated a 100% success rate in bone healing as interpreted by an independent observer, with no evidence of secondary graft resorption or recurrence of the lesion [20].
Bone lengthening in the pediatric upper extremity is associated with a high complication rate [36]. Success in this context is commonly defined by radiographic lengthening, joint motion, and patient satisfaction rather than validated outcome measures [36]. Management of osteolysis after total knee arthroplasty requires a global assessment of the character and progression of the osteolysis weighed against patient-specific risk factors to determine if surgery or continued radiographic surveillance is indicated [51]. Clinical results for alternative bearing surfaces in total joint arthroplasty are currently only short- to mid-term [50]. Factors such as brittle fracture and high cost must be considered when using alternative bearing surfaces for total joint arthroplasty [50].
Key Evidence
- [L5] Bone repair occurs by regeneration rather than healing, involving recruitment, modulation, and osteoconduction. [1] (10.1016/s0894-1130(98)80008-2)
- [L4] Bone regeneration is a complex, well-orchestrated physiological process of bone formation, which can be seen during normal fracture healing, and is involved in continuous remodelling throughout adult life. [2] (10.1186/1741-7015-9-66)
- [L5] Owing to these efforts, immunomodulation is emerging as a potential therapeutic target to improve bone fracture healing. [3] (10.1007/s11914-018-0423-2)
- [L5] Current evidence of growth factors accelerating fracture healing is promising, but results should be interpreted with caution until phase III, level I studies become available. [4] (10.1016/j.injury.2007.02.013)
- [L5] At this time, the repair tissue is predominantly trabecular bone, has normal bone mineral content, and has gained mechanical strength. [5] (10.2106/jbjs.e.00464)
- [L5] In the future, developing additional measures to assess biological healing will improve the reliability and permit us to assess stages of fracture healing. [6] (10.1016/j.injury.2014.04.003)
- [Paper] The balance between signalling molecules involved in bone formation with their inhibitors, particularly between BMPs and their antagonists, is a critical determinant of osteogenesis, skeletal development, fracture repair, and bone remodelling. [7] (10.1016/j.injury.2006.02.039)
- [L5] Identification and targeted interventions for inflammatory induced bone resorption remain limited, and further research is required to advance early detection and treatments. [8] (10.3389/fphys.2020.511799)
- [L5] Knowledge of key pathways in bone biology can improve surgeon understanding, clinical recognition, and treatment of bone homeostasis–related diseases. [9] (10.5435/jaaos-d-23-00164)
- [L1] Prospective, randomised, double-blind, placebo-controlled trials demonstrate its clinical efficacy in accelerating fracture healing. [11] (10.1016/j.injury.2008.01.015)
- [L5] The combined action of low-dose FGF-2 and BMP-2 increases the speed and extent of bone healing and may be a solution to the current problems with high-dose BMP-2. [12] (10.5435/jaaos-22-10-677)
- [L4] These animal data, together with the view of limited scientifically robust clinical evidence in humans, indicate that physicians consider only short-term administration of COX-2 inhibitors or other drugs in the pain management of patients who are in the phase of fracture or other bone defect healing. [14] (10.1097/bor.0b013e32836200b8)
- [Paper] This study supports an important role of periostin in fracture healing, and therapeutically targeting the age-related decrease in periostin may improve healing outcomes in older populations. [15] (10.1002/jor.25439)
- [Paper] The goal of fracture healing is to regenerate mineralized tissue in the fracture area and restore mechanical strength to the bone. [16] (10.1016/s0894-1130(03)80003-0)
- [Paper] This review outlines the current understanding of bone remodeling and its regulation. [17] (10.1196/annals.1365.035)
- [L4] Tissue engineering is a new and developing option introduced to reduce limitations of bone grafts and improve the healing processes of bone fractures and defects. [18] (10.1186/1749-799X-9-18)
- [L3] There is no clinical evidence to support the use of PRP in the treatment of long-bone defects and nonunions. [19] (10.1016/j.injury.2007.02.009)
- [L4] The study demonstrated a 100% success rate in bone healing as interpreted by an independent observer, with no evidence of secondary graft resorption or recurrence of the lesion. [20] (10.1016/0266-7681(93)90154-8)
- [L5] Findings quantified the effects of the initial healing phase on healing outcome to better understand the biological and mechanobiological mechanisms and their utilization in the design and optimization of treatment strategies. [21] (10.1186/s12891-019-2854-z)
- [Paper] The uninterrupted progression of biological events in conjunction with a favourable mechanical environment remains the hallmark of successful fracture healing. [22] (10.1016/j.injury.2016.10.008)
- [L5] Understanding the effects of standard orthopaedic interventions on the local and systemic inflammatory responses and early fracture healing is important for optimizing fracture union. [23] (10.5435/jaaos-d-16-00646)
- [L4] Clinical studies, although with contradictory results, have shown that hypoxia can modify bone remodeling. [24] (10.3390/ijms23063233)
- [L4] It discusses mechanisms such as impaired vascularity, enhanced inflammation, altered bone turnover, and the generation of advanced glycation end products (AGEs) that reduce bone quality. [25] (10.3389/fendo.2018.00006)
- [L4] Cell therapy holds promise as an alternative to autologous bone grafting for promoting bone repair, avoiding drawbacks such as donor-site morbidity and loss of bone stock. [26] (10.1016/j.otsr.2013.11.010)
- [L5] M2 macrophages were clearly prevalent during the ossification phase. [28] (10.1016/j.bone.2015.10.019)
- [L5] Bone grafting enhances bone regeneration and fracture healing through osteoconductive, osteoinductive, and osteogenic capacities. [29] (10.1530/eor-24-0032)
- [L4] The balance of evidence suggests that a short-duration NSAID regimen is a safe and effective supplement to other modes of post-fracture pain control, without a significantly increased risk of sequelae related to disrupted healing. [30] (10.2106/jbjs.j.01743)
- [L5] The manner of skeletal reconstruction depends on the location and size of the defect, the anticipated growth and functional needs of the patient, and the weighed risks of each procedure as tolerated by the patient. [31] (10.5435/jaaos-d-25-00228)
- [L5] Well-designed clinical studies are needed to establish safe and effective guidelines for various modalities to enhance new bone formation during distraction osteogenesis in children. [32] (10.5435/00124635-201102000-00005)
- [L5] A breakthrough is envisaged to allow treatment of bone loss and non-union in a more efficient, reliable, and accelerated manner. [33] (10.1016/s0020-1383(13)70002-0)
- [L4] The advantages of delayed primary bone grafting are: primary bone healing, a shorter rehabilitation period, fewer operations, avoidance of wound contracture, and bone grafting in a well-vascularized scar-free bed. [34] (10.1016/s0363-5023(84)80179-3)
- [L5] The use of xenogeneic demineralized bone implants promotes induced osteogenesis and rapid healing, avoids harvesting procedures, and offers a potentially unlimited supply of banked material. [35] (10.1016/s0363-5023(84)80229-4)
- [L5] The procedure is associated with a high complication rate, and success is commonly defined by radiographic lengthening, joint motion, and patient satisfaction rather than validated outcome measures. [36] (10.2106/jbjs.16.00007)
- [L4] Despite numerous studies over the last 3 decades, there is still no hard proof whether traumatic brain injury results in accelerated fracture healing, and the pathophysiological background remains unclarified. [37] (10.1155/2015/204842)
- [L4] It discusses how bone loss and new bone formation coincide as part of the local tissue response to a bacterial infection, and how these seemingly opposite processes are related to each other. [38] (10.1002/jor.24422)
- [L5] These models enable experimental genetics studies to investigate the cellular and molecular mechanisms of spontaneous cortical and cancellous bone repair and may be useful for pharmacological studies. [39] (10.1007/s00223-009-9314-y)
- [L5] These new insights into TGFβ/BMP signaling on bone will open new prospects for generating novel therapies against clinical disorders. [41] (10.7150/ijbs.2929)
- [Paper] Understanding these cellular and molecular pathways is critical for advancing fracture treatment and understanding skeletal growth, repair, and aging. [42] (10.1016/j.injury.2005.07.019)
- [L5] Site-specific remodeling appears to be responsible for corticalization and marrow regeneration. [43] (10.2106/jbjs.e.01006)
- [L5] Further understanding of the biology of fracture repair may lead to improved treatment modalities. [44] (10.5435/00124635-200811000-00001)
- [Paper] Alterations of the BMP signaling pathway, either by direct targeting of the BMPs or by their inhibitors has been shown to interfere with embryologic skeletal development and a post natal regenerative repair following skeletal trauma. [45] (10.1016/s0020-1383(09)70003-8)
- [L4] Accumulative in vivo evidence shows that increased bone resorption occurs at an early stage in the development of osteoarthritis and that blocking bone-resorbing cytokines prevents cartilage damage. [46] (10.1016/j.cytogfr.2011.04.003)
- [L5] The biology of fracture healing is a complex biological process that follows specific regenerative patterns and involves changes in the expression of several thousand genes. [47] (10.1016/j.injury.2011.03.031)
- [Paper] Stress fractures arise when bone stresses exceed the capacity of bone to withstand and heal from those stresses, resulting from either excessive bone strain with microdamage accumulation or depressed bony remodeling in response to normal strain. [48] (10.1016/j.csm.2005.08.010)
- [L5] Fracture healing is a complex physiologic process involving a combination of intramembranous and enchondral ossification, driven by the interplay of host biology (progenitor cells, growth factors, ECM) and the mechanical environment. [49] (10.1016/j.hcl.2013.08.002)
- [L4] However, clinical results are currently only short- to mid-term, and factors such as brittle fracture and high cost must be considered. [50] (10.5435/00124635-199807000-00001)
- [L5] Management requires a global assessment of the character and progression of the osteolysis weighed against patient-specific risk factors to determine if surgery or continued radiographic surveillance is indicated. [51] (10.5435/jaaos-d-13-00189)
- [L5] The major constraints for routine use of BMP are inadequate clinical trials in humans and the need to comprehensively assess the cost-effectiveness and budget impact of BMP. [52] (10.1016/j.injury.2006.12.012)
- [L5] Increasing physician awareness of these side effects will allow for monitoring of bone health and therapeutic interventions to prevent or treat drug-induced osteoporosis. [53] (10.1177/1759720x14546350)
- [L5] The ideal bone-graft substitute is biocompatible, bioresorbable, osteoconductive, osteoinductive, structurally similar to bone, easy to use, and cost-effective, but currently marketed products vary in composition and mechanism. [54] (10.2106/00004623-200100022-00007)
- [L4] In this study, ingrowth of small vessels at the bone junction was observed at week 3, calcified callus became visible at month 4, and bone union was completed at month 11. [55] (10.1016/j.jhsa.2004.05.007)
- [L5] These alternatives offer osteoconductive, osteoinductive, and osteogenic properties with limited morbidity compared to traditional iliac crest harvesting. [56] (10.5435/00124635-201102000-00006)
- [L4] The study supports the view that the application of rhBMP-7 as a bone-stimulating agent is safe and a powerful adjunct to be considered in the surgeon's armamentarium for the treatment of these challenging clinical conditions. [57] (10.1016/j.injury.2005.10.010)
- [L5] Autologous bone graft remains the gold standard for enhancing fracture healing, though limitations include low graft volume and donor site morbidity. [58] (10.1530/eor-23-0047)
- [L5] Osteotomy sites treated with rhBMP-2 healed approximately 33% faster than did osteotomy sites either treated with buffer or left untreated, with mechanical properties as much as twofold greater at three and four weeks. [59] (10.2106/00004623-200108000-00012)
- [L5] Local and regional gene therapy has improved healing in preclinical trials of articular and other musculoskeletal conditions. [60] (10.1196/annals.1402.065)
- [Paper] The success of bone grafting depends on the active participation of the graft in reparative osteogenesis, with conditions for successful grafting being early vascularization and a vital graft. [61] (10.1016/0020-1383(94)90256-9)
- [L4] The evidence for bone healing shows promising results, particularly for MSCs and BMP in the treatment of non-unions. [62] (10.1177/17531934251327034)
- [L3] In the surgical treatment of stable knee OCD lesions, bone stimulator use did not appear to improve radiographic or clinical healing. [63] (10.1177/2325967120s00178)
- [L4] PRP use for bone healing appears only beneficial when used in combination with osteoconductive scaffolds; however, neither allograft nor autograft appear to be appropriate carriers. [65] (10.1007/s00402-012-1641-1)
- [L5] Combinatory use of PRP and HBO resulted in increased bone regeneration and neovascularization compared to all other groups. [66] (10.1016/j.injury.2016.09.039)
- [L4] All nonunions and fractures healed after an average of 5 months. [67] (10.1097/bth.0b013e3181f42bd3)
- [L3] This study supports the concept that the use of PRF/BMSC, during the standard procedure, is effective in shortening nonunion healing time. [68] (10.1016/j.injury.2016.09.021)
- [L4] Correct formulation and design of the graft to ensure adequate osteo-activity and resorption appears intrinsic to a successful outcome. [69] (10.1016/j.injury.2016.10.025)
- [L4] In each case, bone formation at the distracted fracture site was satisfactory and times for regenerate consolidation were similar to those seen in standard corticotomies. [70] (10.1016/s0020-1383(98)00128-4)
- [L4] Proper recognition of the etiology of osteoporosis is an essential step in improving bone health and preventing further bone loss. [71] (10.3390/jcm11092382)
- [L5] An accurate reduction is a requisite for bone healing, and adverse mechanical conditions associated with different bone immobilization techniques can compromise normal bone fracture healing significantly. [72] (10.1097/01.blo.0000132263.14046.0c)
- [L4] This review comprehensively summarizes the latest techniques for evaluating bone healing during distraction osteogenesis, providing novel and significant information for evaluating bone healing in the future. [73] (10.1186/s12891-022-05458-8)
- [L5] Available literature for the use of biologic therapies in stress fractures is restricted, with most reports using biologics as a supplement to surgical fixation in studies lacking control groups. [74] (10.1016/j.jisako.2024.04.008)
See Also
- Osteoarthritis
References
[1] Bony tissue repair. Journal of Hand Therapy. 1998. DOI: 10.1016/s0894-1130(98)80008-2
[2] Bone regeneration: current concepts and future directions. BMC Medicine. 2011. DOI: 10.1186/1741-7015-9-66
[3] The Role of the Immune Cells in Fracture Healing. Current Osteoporosis Reports. 2018. DOI: 10.1007/s11914-018-0423-2
[4] Can we accelerate fracture healing?. Injury. 2007. DOI: 10.1016/j.injury.2007.02.013
[5] Direct Percutaneous Gene Delivery to Enhance Healing of Segmental Bone Defects. The Journal of Bone & Joint Surgery. 2006. DOI: 10.2106/jbjs.e.00464
[6] Biological perspectives of delayed fracture healing. Injury. 2014. DOI: 10.1016/j.injury.2014.04.003
[7] The role of inhibitory molecules in fracture healing. Injury. 2006. DOI: 10.1016/j.injury.2006.02.039
[8] The Effect of Inflammation on Bone. Frontiers in Physiology. 2021. DOI: 10.3389/fphys.2020.511799
[9] Bone Homeostasis and Physiology in Normal and Orthopaedic Disease Conditions. Journal of the American Academy of Orthopaedic Surgeons. 2023. DOI: 10.5435/jaaos-d-23-00164
[11] External adjuncts to enhance fracture healing: What is the role of ultrasound?. Injury. 2008. DOI: 10.1016/j.injury.2008.01.015
[12] Optimizing BMP-2-induced bone repair with FGF-2. Journal of the American Academy of Orthopaedic Surgeons. 2014. DOI: 10.5435/jaaos-22-10-677
[14] NSAIDs and fracture healing. Current Opinion in Rheumatology. 2013. DOI: 10.1097/bor.0b013e32836200b8
[15] Age‐related decrease in periostin expression may be associated with attenuated fracture healing in old mice. Journal of Orthopaedic Research. 2022. DOI: 10.1002/jor.25439
[16] Fracture healing: Bone healing, fracture management, and current concepts related to the hand. Journal of Hand Therapy. 2003. DOI: 10.1016/s0894-1130(03)80003-0
[17] Bone Remodeling. Annals of the New York Academy of Sciences. 2006. DOI: 10.1196/annals.1365.035
[18] Bone regenerative medicine: classic options, novel strategies, and future directions. Journal of Orthopaedic Surgery and Research. 2014. DOI: 10.1186/1749-799X-9-18
[19] Growth factors — BMPs, DBMs, and buffy coat products: are there any proven differences amongst them?. Injury. 2007. DOI: 10.1016/j.injury.2007.02.009
[20] Demineralized Bone Powder. Journal of Hand Surgery. 1993. DOI: 10.1016/0266-7681(93)90154-8
[21] Computational modeling of human bone fracture healing affected by different conditions of initial healing stage. BMC Musculoskeletal Disorders. 2019. DOI: 10.1186/s12891-019-2854-z
[22] The roles of immune cells in bone healing; what we know, do not know and future perspectives. Injury. 2016. DOI: 10.1016/j.injury.2016.10.008
[23] Osteoimmunology: Effects of Standard Orthopaedic Interventions on Inflammatory Response and Early Fracture Healing. Journal of the American Academy of Orthopaedic Surgeons. 2018. DOI: 10.5435/jaaos-d-16-00646
[24] Molecular Mechanisms Involved in Hypoxia-Induced Alterations in Bone Remodeling. International Journal of Molecular Sciences. 2022. DOI: 10.3390/ijms23063233
[25] The Impact of Type 2 Diabetes on Bone Fracture Healing. Frontiers in Endocrinology. 2018. DOI: 10.3389/fendo.2018.00006
[26] Cell therapy for bone repair. Orthopaedics & Traumatology: Surgery & Research. 2014. DOI: 10.1016/j.otsr.2013.11.010
[28] Macrophages in bone fracture healing: Their essential role in endochondral ossification. Bone. 2018. DOI: 10.1016/j.bone.2015.10.019
[29] Long bone uninfected non-union: grafting techniques. EFORT Open Reviews. 2024. DOI: 10.1530/eor-24-0032
[30] The Effect of Nonsteroidal Anti-Inflammatory Drug Administration on Acute Phase Fracture-Healing: A Review. Journal of Bone and Joint Surgery. 2012. DOI: 10.2106/jbjs.j.01743
[31] Autograft and Biologic Living Bone Reconstructions in Orthopaedic Oncology. Journal of the American Academy of Orthopaedic Surgeons. 2025. DOI: 10.5435/jaaos-d-25-00228
[32] Enhancement of Bone Formation During Distraction Osteogenesis: Pediatric Applications. Journal of the American Academy of Orthopaedic Surgeons. 2011. DOI: 10.5435/00124635-201102000-00005
[33] Bone regeneration strategies: Current trends but what the future holds?. Injury. 2013. DOI: 10.1016/s0020-1383(13)70002-0
[34] Delayed primary bone grafting in the hand and wrist after traumatic bone loss. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80179-3
[35] The use of demineralized xenogeneic bone implants to correct phalangeal defects: A case report. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80229-4
[36] Bone Lengthening in the Pediatric Upper Extremity. Journal of Bone and Joint Surgery. 2016. DOI: 10.2106/jbjs.16.00007
[37] Improved Fracture Healing in Patients with Concomitant Traumatic Brain Injury: Proven or Not?. Mediators of Inflammation. 2015. DOI: 10.1155/2015/204842
[38] Impact of Bacterial Infections on Osteogenesis: Evidence From In Vivo Studies. Journal of Orthopaedic Research. 2019. DOI: 10.1002/jor.24422
[39] Drilled Hole Defects in Mouse Femur as Models of Intramembranous Cortical and Cancellous Bone Regeneration. Calcified Tissue International. 2009. DOI: 10.1007/s00223-009-9314-y
[40] 10.1002-jor.24384. n.d..
[41] TGF-β and BMP Signaling in Osteoblast Differentiation and Bone Formation. International Journal of Biological Sciences. 2012. DOI: 10.7150/ijbs.2929
[42] Current concepts of molecular aspects of bone healing. Injury. 2005. DOI: 10.1016/j.injury.2005.07.019
[43] rhBMP-2 Delivered in a Calcium Phosphate Cement Accelerates Bridging of Critical-Sized Defects in Rabbit Radii. The Journal of Bone & Joint Surgery. 2006. DOI: 10.2106/jbjs.e.01006
[44] Recent Developments in the Biology of Fracture Repair. Journal of the American Academy of Orthopaedic Surgeons. 2008. DOI: 10.5435/00124635-200811000-00001
[45] The role of endogenous bone morphogenetic proteins in normal skeletal repair. Injury. 2009. DOI: 10.1016/s0020-1383(09)70003-8
[46] Crosstalk between cartilage and bone: When bone cytokines matter. Cytokine & Growth Factor Reviews. 2011. DOI: 10.1016/j.cytogfr.2011.04.003
[47] The biology of fracture healing. Injury. 2011. DOI: 10.1016/j.injury.2011.03.031
[48] The Pathophysiology of Stress Fractures. Clinics in Sports Medicine. 2006. DOI: 10.1016/j.csm.2005.08.010
[49] Basic Science of Bone Healing. Hand Clinics. 2013. DOI: 10.1016/j.hcl.2013.08.002
[50] Alternative Bearing Surfaces for Total Joint Arthroplasty. Journal of the American Academy of Orthopaedic Surgeons. 1998. DOI: 10.5435/00124635-199807000-00001
[51] Evaluating the Progression of Osteolysis After Total Knee Arthroplasty. Journal of the American Academy of Orthopaedic Surgeons. 2015. DOI: 10.5435/jaaos-d-13-00189
[52] Bone morphogenic protein and its application in trauma cases: A current concept update. Injury. 2007. DOI: 10.1016/j.injury.2006.12.012
[53] Medication-induced osteoporosis: screening and treatment strategies. Therapeutic Advances in Musculoskeletal Disease. 2014. DOI: 10.1177/1759720x14546350
[54] Bone-Graft Substitutes: Facts, Fictions, and Applications. The Journal of Bone and Joint Surgery-American Volume. 2001. DOI: 10.2106/00004623-200100022-00007
[55] Bilateral hand transplantation: Bone healing under immunosuppression with tacrolimus, mycophenolate mofetil, and prednisolone. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.05.007
[56] Bone Grafting in Surgery About the Foot and Ankle: Indications and Techniques. American Academy of Orthopaedic Surgeon. 2011. DOI: 10.5435/00124635-201102000-00006
[57] Application of recombinant BMP-7 on persistent upper and lower limb non-unions. Injury. 2005. DOI: 10.1016/j.injury.2005.10.010
[58] Biological aspects to enhance fracture healing. EFORT Open Reviews. 2023. DOI: 10.1530/eor-23-0047
[59] Recombinant Human Bone Morphogenetic Protein-2 Accelerates Healing in a Rabbit Ulnar Osteotomy Model. The Journal of Bone and Joint Surgery-American Volume. 2001. DOI: 10.2106/00004623-200108000-00012
[60] Gene Therapy in Musculoskeletal Repair. Annals of the New York Academy of Sciences. 2007. DOI: 10.1196/annals.1402.065
[61] 3. Biological principles of autogenous bone grafting. Injury. 1994. DOI: 10.1016/0020-1383(94)90256-9
[62] The role of orthobiologics in bone healing and joint and tendon degeneration in the upper limb. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934251327034
[63] ADJUVANT TREATMENT OF OCD LESIONS OF THE KNEE WITH BONE STIMULATORS. Orthopaedic Journal of Sports Medicine. 2020. DOI: 10.1177/2325967120s00178
[65] Can platelet-rich plasma (PRP) improve bone healing? A comparison between the theory and experimental outcomes. Archives of Orthopaedic and Trauma Surgery. 2012. DOI: 10.1007/s00402-012-1641-1
[66] Synergistic effects of HBO and PRP improve bone regeneration with autologous bone grafting. Injury. 2016. DOI: 10.1016/j.injury.2016.09.039
[67] Cement Spacers With Antibiotics for the Treatment of Posttraumatic Infected Nonunions and Bone Defects of the Upper Extremity. Techniques in Hand & Upper Extremity Surgery. 2010. DOI: 10.1097/bth.0b013e3181f42bd3
[68] Radiological assessment of the PRF/BMSC efficacy in the treatment of aseptic nonunions: A retrospective study on 90 subjects. Injury. 2016. DOI: 10.1016/j.injury.2016.09.021
[69] Is there a role of coral bone substitutes in bone repair?. Injury. 2016. DOI: 10.1016/j.injury.2016.10.025
[70] Distraction osteogenesis through high energy fractures. Injury. 1998. DOI: 10.1016/s0020-1383(98)00128-4
[71] Secondary Osteoporosis and Metabolic Bone Diseases. Journal of Clinical Medicine. 2022. DOI: 10.3390/jcm11092382
[72] Biomechanical Considerations of Fracture Treatment and Bone Quality Maintenance in Elderly Patients and Patients with Osteoporosis. Clinical Orthopaedics and Related Research. 2004. DOI: 10.1097/01.blo.0000132263.14046.0c
[73] The progress in quantitative evaluation of callus during distraction osteogenesis. BMC Musculoskeletal Disorders. 2022. DOI: 10.1186/s12891-022-05458-8
[74] Biologic therapies in stress fractures: Current concepts. Journal of ISAKOS. 2024. DOI: 10.1016/j.jisako.2024.04.008