Clinicians › Hand
Soft Tissue Trauma
Hand soft tissue trauma: assessment, infection risk, and management principles for crush, injection, and compartment syndrome injuries.
Overview
Severe soft-tissue injuries associated with closed and open fractures require treatment based on correct fracture classification and corresponding soft tissue assessment [1]. Management must be individualized to the patient’s general health, secondary diagnoses, and available treatment options [1]. Appropriate management of the soft-tissue envelope is essential for good outcomes in high-energy extremity trauma, demanding strict adherence to soft-tissue principles for accurate decision-making and outcome prediction [2]. Major and extensive injuries necessitate a planned approach grounded in broad training and knowledge rather than isolated past experiences [3]. For low-energy civilian gunshot wounds, initial assessment prioritizes life-threatening blood loss, early antibiotics, soft tissue injury, and associated vascular or neurological damage [4]. Iatrogenic extravasation injuries are best prevented, but when they occur, prompt diagnosis and treatment are mandatory to minimize soft tissue damage [5].
Open fractures constitute serious injuries requiring prompt antibiotic administration, timely surgical débridement, skeletal stabilization, and soft-tissue coverage [7]. Soft tissue coverage is required to salvage traumatized limbs and restore adequate function and form [8]. Free flap reconstruction should be selected early in the treatment algorithm if a better end result is anticipated, as it allows for early coverage, composite reconstruction of damaged tissues, and early mobilization [10]. In standardized closed soft tissue injuries, infection rates are significantly higher and the ID50 for infection is lower compared to scenarios without soft tissue trauma [11]. The decision on soft tissue coverage for severe infections is complex, requiring consideration of wound character, patient factors, and anticipated functional results [14]. Degloving injuries require individualized management based on specific injury characteristics [16].
Upper extremity defects require durable coverage to allow early postoperative mobilization and rehabilitation [22]. The posterior interosseous artery flap provides reliable coverage and favorable functional outcomes in severe hand injuries [34]. Firework-related hand injuries often require reconstruction rather than repair, with many patients needing secondary procedures; prevention remains the best treatment [63]. Local and regional flaps protect against contractures and facilitate mobility [140]. Fasciocutaneous flaps are optimal for initial reconstruction when secondary procedures are foreseen due to pliability and ease of re-elevation [146]. Two simultaneous pedicled flaps offer a simple alternative to free tissue transfer for complex hand and forearm defects, particularly in critically ill, multi-extremity injured patients [148]. Individualized thoracodorsal artery perforator chimeric flaps provide flexible design for customized coverage with limited donor site morbidity [150]. Delayed wound closure is the rule in major trauma centres due to practical constraints, while emergency free tissue transfer is the exception [55]. Further research is required to define optimal indications for vacuum-assisted wound closure compared with traditional methods [51].
Anatomy & Pathophysiology
Osseous Anatomy
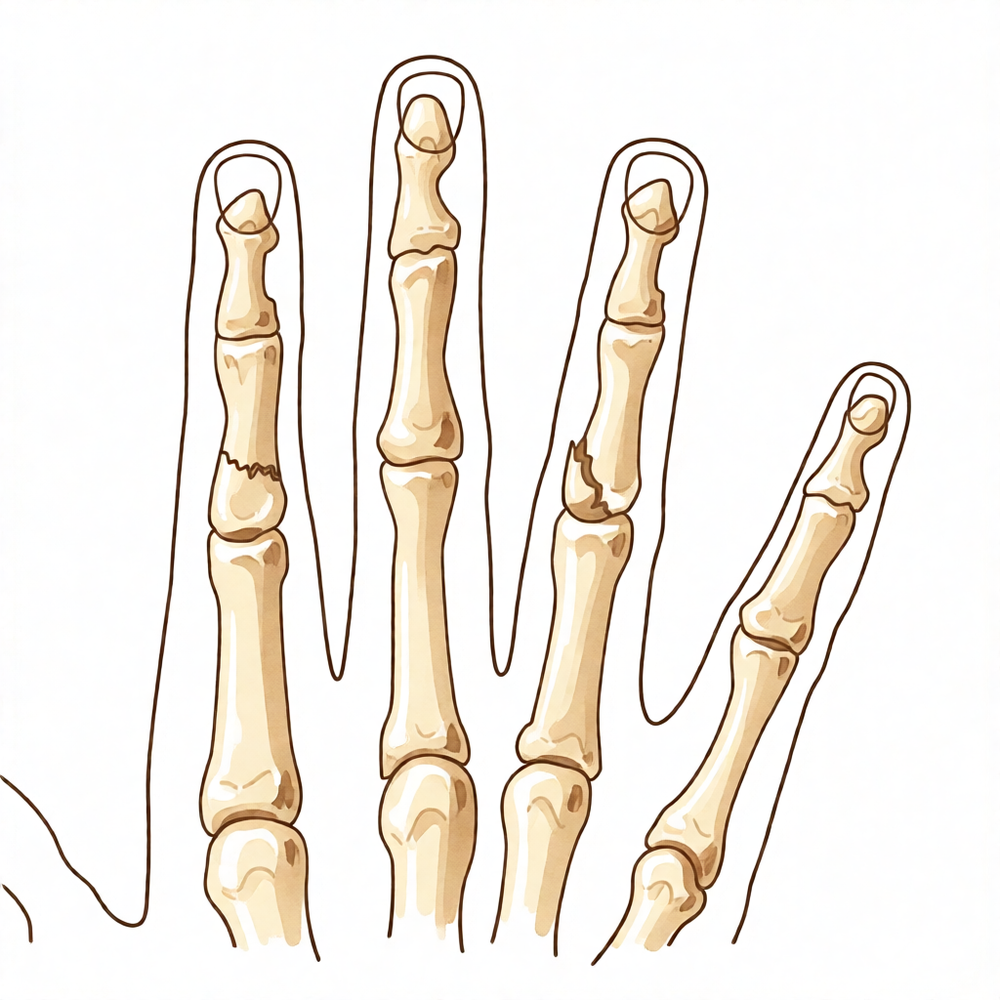
The skeleton of the hand and wrist comprises 27 bones, 19 of which are long bones [38]. The hand skeleton is organized into five rays, each forming a polyarticulated chain of metacarpals and phalanges [38]. The base of each metacarpal articulates with the distal carpal row, while the carpus connects to the forearm via its proximal row [38]. This configuration grants the wrist three axes of movement, allowing the hand to assume any spatial configuration [38]. The radial ray is the shortest, consisting of a metacarpal and two phalanges, and continues the external carpal column formed by the scaphoid and trapezium [38]. The trapezium is angled anteriorly relative to the carpal plane, creating an approximately 45-degree angle between the first and second metacarpals in the sagittal plane [38]. The thumb metacarpal is the shortest, whereas the index metacarpal is the longest [38]. The proximal and middle phalanges of the middle and ring fingers are longer than those of the index finger [38].
The hand skeleton presents longitudinal and transverse concavities, forming a cup shape with palmar concavity when the thumb opposes the index finger [38]. The transverse palmar axis is oblique, positioned more distally at the index metacarpophalangeal joint and more proximally at the fifth metacarpophalangeal joint [38]. This transverse axis forms an acute angle of approximately 75 degrees with the longitudinal axis [38]. Epiphyseal plates are located at the proximal ends of the phalanges and the first metacarpal, and at the distal ends of the other metacarpals [38]. The index metacarpal is the most firmly fixed [70]. The ring metacarpal exhibits approximately 10 degrees of mobility in flexion and extension, while the fifth metacarpal has a range of approximately 20 degrees [70]. The second through fifth metacarpals are bound together by the deep transverse intermetacarpal ligament, also known as the interglenoid ligament [70]. The metacarpophalangeal joints serve as the keystones of the hand’s longitudinal arches, with volar plates preventing hyperextension [70].
Musculotendinous Anatomy
Digital posture control requires a complex balance of extrinsic and intrinsic muscle forces [37]. Extrinsic muscles originate outside the hand and insert on the hand or carpus, while intrinsic muscles have both origin and insertion within the hand [37]. Extrinsic extensors traverse six fibroosseous retinacular compartments at the wrist [37]. The first compartment contains the abductor pollicis longus and extensor pollicis brevis [37]. The second compartment contains the extensor carpi radialis longus and brevis [37]. The third compartment contains the extensor pollicis longus, which turns abruptly radialward around Lister tubercle [37]. The fourth compartment contains the extensor indicis proprius, lying deep to the four tendons of the extensor digitorum communis [37]. The fifth compartment contains the extensor digiti quinti, and the sixth contains the extensor carpi ulnaris tendon [37].
The extensor digitorum communis tendons of the middle, ring, and little fingers are tethered by juncturae tendinum over the dorsum of the hand proximal to the metacarpophalangeal joint [37]. Digital extensor tendons are stabilized over the midline of the metacarpophalangeal joint by attachment to sagittal band fibers, which insert onto the volar proximal phalanx and lateral borders of the volar plate [37]. Rupture or attenuation of these fibers allows the extrinsic extensor tendon to sublux ulnarly, causing ulnar deviation of the finger [37]. The extrinsic finger flexors are the flexor digitorum profundus and superficialis [37]. The flexor digitorum profundus inserts on the proximal volar aspect of the distal phalanx, while the flexor digitorum superficialis flexes the proximal interphalangeal and metacarpophalangeal joints [37].
There are seven interosseous muscles: four dorsal and three volar [67]. The dorsal interossei are abductors, and the volar interossei are adductors [67]. The middle finger possesses two dorsal interossei and no volar interossei because the central axis of the hand lies within it [67]. Each dorsal interosseous muscle, except the third, has two heads [67]. The superficial head abducts and weakly flexes the proximal phalanx, while the deep head flexes and weakly abducts the proximal phalanx while extending the middle and distal phalanges [67]. The volar interossei have a single head and none insert onto the proximal phalanx [67].
The flexor digitorum profundus originates from the proximal ulna and interosseous membrane [74]. The flexor digitorum superficialis has a radial head from the proximal radius shaft and a humeral ulnar head from the medial humeral epicondyle and coronoid process of the ulna [74]. The flexor digitorum superficialis tendon bifurcates around the flexor digitorum profundus at the beginning of the A2 pulley, with slips reuniting distally at the Camper chiasm [74]. The flexor pollicis longus originates from a radial head (proximal radius and interosseous membrane) and an accessory head (coronoid process of the ulna and medial humeral epicondyle) [74]. The fibroosseous tunnel, or digital flexor sheath, consists of annular pulleys providing mechanical stability and cruciate pulleys providing flexibility [74]. The A2 and A4 pulleys are most essential for maintaining flexor tendon mechanical advantage [74]. The tenosynovium lining the sheath supplies nutrition and lubrication to poorly vascularized flexor tendons, with vascularity within the sheath supplied via the vinculum longus and brevis [74].
Cutaneous Anatomy
Dorsal skin features a thin epidermis with a horny layer only 0.02 mm thick, and a dermis that is thinner and less resistant than the palmar dermis [76]. Unlike the palm, dorsal skin possesses a normal pilosebaceous system [76]. Dorsal skin becomes fragile in old age and is vulnerable to cutaneous atrophy from factors such as steroid therapy [76]. Finger flexion significantly lengthens dorsal skin; in the middle finger, the distance between the wrist and ungual fold increases by an average of 3 cm from extension to full flexion [76]. Flexion at the metacarpophalangeal joint alone requires an average skin lengthening of 1.25 cm [76]. Dorsal and palmar skin areas are independent due to adhesions anchoring their common boundary to the underlying plane [76].
The superficial palmar fascia lies in a coronal plane beneath the palmar subcutaneous tissue, covering a triangular area of the central palm with the proximal corner facing directly proximal [77]. The palmaris longus tendon, when present, terminates in continuity with the fibers of the proximal corner of this fascia [77]. Four central bands of fascia extend distally from the common point toward each finger, with no central band for the thumb [77]. Digital neurovascular structures are surrounded by a diffuse network of thin transverse oblique fibers [77]. Fibers dorsal to the neurovascular bundle are collectively called Cleland ligament, while those palmar to the bundle are called Grayson ligament [77]. A subdermal fascial layer borders the periphery of the web spaces from roughly the radial thumb sesamoid to the ulnar side of the small finger’s proximal flexion crease [77].
Skin coverage dimensions are critical for reconstruction planning. The skin required to cover the thumb distal to the metacarpophalangeal joint is approximately 9 cm wide and 8 cm long [69]. Skin loss of the thumb and first metacarpal measures 13 cm wide and 12 cm long [69]. The skin cover of both palmar and dorsal surfaces of the hand is 12 cm by 10 cm [69]. The skin covering each finger is 7 cm by 10 cm on both palmar and dorsal aspects [69].
Vascular Anatomy
The "princeps pollicis" artery, the terminal branch of the radial artery, crosses the first intermetacarpal space and runs along the ulnar side of the first metacarpal bone [71]. It emerges onto the subcutaneous palmar tissue at the level of the cutaneous flexion crease of the metacarpophalangeal joint [71]. The princeps pollicis divides into two terminal rami, the collateral palmar arteries of the thumb, which run symmetrically along the digital tunnel [71]. An arcade located deep in the flexor tendon joins these two arteries at the level of the distal metaphysis of the first phalanx [71]. Only 15% of anatomical dissections fall into the classical category of palmar artery layout in the thumb [71]. In the second segment of the thumb, the main artery is the ulnar collateral artery [71]. The subtendinous anastomosis at the neck of the first phalanx acts as a "moderator" between the two collateral arteries [71]. Dorsal arteries of the thumb originate from palmar arteries (princeps, commissural, or anastomoses of the superficial arcade) at the level of the first metacarpal [71].
Pathophysiology & Injury Mechanisms
The infection rate after a standardized closed soft tissue injury was significantly higher, and the ID50 lower, than without soft tissue trauma [11]. Hand finger trauma involving loss of skin or soft tissue injuries, even when correctly repaired acutely, often presents skin troubles that can lead to functional loss and patient dissatisfaction [15]. Projectile composition and shape determine a bullet's tendency to deform, fragment, or spin [35]. Low-velocity bullets usually travel at 1000 ft/sec or less, whereas high-velocity bullets travel at 2000 ft/sec or more [35]. Most military weapons range from 2400 ft/sec to 2900 ft/sec [35]. The severity and character of the wound are directly dependent on the kinetic energy imparted to the tissue [35]. Tissue damage is determined by missile velocity and mass, as well as bullet shape, type, and interactions within tissues [35]. Bullet fragmentation, deformation, and production of secondary missiles contribute significantly to wounding potential [35]. Laceration or crushing of tissues are the predominant mechanisms of injury from low-velocity missiles, while shock waves are not considered a significant determinant of tissue injury [35].
Closed degloving of the thumb is a rare condition caused by crushing and elongation forces that detach soft tissues without skin disruption [121]. Hand trauma, particularly surgical trauma and repetitive mechanical stress, is associated with the onset of Dupuytren's disease [112]. The first metacarpal is the most vulnerable bone in rugby union football injuries [103]. Flexor pulley lesions are the most common hand lesions related to rock climbing, followed by fractures and strains [104].
Classification
Gustilo–Anderson: This system classifies open fractures based on soft tissue injury severity. Type 3B injuries are defined by significant soft tissue insult and loss, resulting in large defects [26]. These injuries are uncommon in the femur but represent the most challenging clinical scenario in the tibia, where they carry very high infection risks and frequently require further operative intervention for union, particularly when bone loss is present [26]. Management of Gustilo type 3B injuries typically requires flap coverage and plastic surgery expertise [26].
SATT: The SATT classification system directs management by first identifying the severity of the initial injury and determining part viability [110]. It incorporates anatomical localisation (isolated vs. extended) and topography (volar vs. dorsal) to guide treatment [110]. Additionally, the system accounts for the type of injury, distinguishing between sharp and crush-avulsed mechanisms [110].
Burns: Burns are categorized according to the degree of damage to epithelium, dermis, subcutaneous tissue, and other underlying structures [139]. First-degree injuries involve epidermal damage only, presenting without open wounds or blistering; they heal without scarring and do not require surgical treatment [139]. Second-degree burns are partial-thickness injuries encompassing the epidermis and varying degrees of dermis, subcategorized as superficial or deep [139]. Superficial second-degree burns exhibit blister formation and pain due to dermal nerve ending involvement, often healing via re-epithelialization with local wound care over 10 to 14 days [139].
Ring and Bangle Avulsion: A new classification, class IIC, has been proposed for ring avulsion injuries with venous compromise only, which should be treated with micro-venous reconstruction [144]. Bangle avulsion injuries of the forearm range in severity from relatively minor soft tissue injury to complete amputation [153].
Other Considerations: Treatment for severe soft-tissue injuries must be adapted to the individual patient, considering general health status, secondary diagnoses, and available options [1]. The decision on soft tissue coverage is complex, requiring consideration of wound character, patient factors, and anticipated functional results [14]. A treatment strategy based on the location of the soft tissue defect and perforator anatomy allows for expedient one-stage upper limb wound coverage [52].
In experimental models, the ID50 for infection after a standardized closed soft tissue injury was lower than without soft tissue trauma [11]. A grade 2 closed soft tissue trauma damaged the periosteum and muscle, with both injuries healing rapidly; its effects on fracture healing were limited to the early phase [6].
Clinical infection rates correlate with injury severity, though the trend did not reach statistical significance [57]. At 6 months, infection rates were 2 for type 1, 14 for type 2, and 24 for type 3 injuries [57]. In type 1 injuries, both subsequent infections were superficial soft tissue infections developing within 1 month [57]. In type 2 injuries, 9 infections were superficial, 4 were deep soft tissue infections, and 1 was osteomyelitis [57]. In type 3 wounds, 6 infections were superficial, 12 were deep soft tissue infections, and 6 were osteomyelitis [57]. Infections diagnosed after 1 month included 3 deep tissue infections and 2 cases of osteomyelitis [57].
Specific injury mechanisms require tailored approaches. Conservative treatment of high-pressure water jet injury of the hand makes admission and close follow-up mandatory, with immediate surgical intervention considered if the clinical course deteriorates [9]. The initial clinical presentation of Freon gas burns is often reassuring and does not reflect actual depth or severity [12]. Open fractures of the upper limb occur in bones with good blood supply and adequate soft tissue cover, making them less challenging to treat than lower limb counterparts [26]. Emergent reduction, early soft tissue cover, and orderly surgical fixation are essential for managing complex open carpal dissociations [21].
Clinical Presentation
History and Initial Assessment
Initial assessment of soft-tissue injuries prioritizes life-threatening blood loss, early antibiotics, and the identification of associated vascular and neurological injuries [4]. For hand injuries, the history must establish hand dominance and the nature of the patient’s job [23]. In high-pressure injection injuries, the history is critical and must document the pressure of the injection gun, the exact material injected, the estimated volume, and the distance from the gun to the extremity [94]. Patients with these injuries often underestimate their severity because pain is frequently absent initially and the entry site is small [94]. Conversely, injuries from blunt-edged items may appear severe but are often harmless because they follow weak anatomic spaces with minimal tissue damage [28]. Patients presenting late with mutilating hand injuries typically report chronic pain, stiffness, malpositioning, scissoring, and severe deformities [23]. Even when acute repairs are correct, finger trauma involving skin or soft tissue loss often leads to functional loss and dissatisfaction due to subsequent skin troubles [15].
Physical Examination and Imaging
The neurovascular status of the limb must be carefully evaluated and documented before surgical intervention for severe upper limb injuries [29]. A thorough physical examination for high-pressure injection injuries includes documenting entry and exit wounds, assessing neurovascular status, evaluating tendon involvement, and checking for crepitus [94]. The entry wound in these cases is often a small puncture, and injected material may exude or be expressible [94]. Radiographs are helpful to assess the extent of spread and deep tissue injury when air or radiodense materials are involved [94]. For delayed presentation of hand injuries, basic investigations include wound swabs for culture and antibiotic sensitivity, along with radiographs [23]. If necessary, soft tissue ultrasound imaging, computed tomography, MRI, and vascular assessment via Doppler ultrasonography and angiography are performed [23].
Specific Injury Patterns and Complications
Acute compartment syndrome: This is a clinical emergency requiring vigilance, prompt diagnosis, and treatment [40]. Risk factors include high-energy injuries, specific fracture patterns, and younger age [40]. In the hand, the most common causes are crush injury, prolonged decubitus, and infection [96]. A soft-tissue sarcoma can cause necrosis and edema leading to acute compartment syndrome; therefore, a neoplasm must be considered in the differential diagnosis for cases without clear trauma [93, 18].
Infection and specific mechanisms: Clinical findings suggestive of the need for hospitalization for cat bite infections include location over a joint or tendon sheath, erythema, pain, and swelling [92]. When signs of rapidly progressive soft-tissue infection develop, Aeromonas hydrophila should be considered as a causative pathogen [25]. Individuals presenting with self-inflicted gunshot wounds to the hand are more likely to present with acute carpal tunnel syndrome requiring urgent surgical decompression [90]. In modern warfare, blast and fragment injuries are the most common wounds, with most involving secondary blast injuries from flying debris [20]. The extent and severity of hand injuries caused by sword assaults can result in devastating loss of function [89].
Investigations
General Assessment: Initial assessment of low-energy civilian gunshot wounds prioritizes life-threatening blood loss, early antibiotics, soft tissue injury, and possible associated vascular and neurological injuries [4]. A careful physical examination is essential to direct care and future testing for injured or dysfunctional hands and wrists [36]. While diagnostic tests such as imaging and serum laboratory studies are useful in determining hand pathology, they can be expensive, time-consuming, and often nonspecific [36].
MRI: MRI is the imaging modality of choice for the majority of soft-tissue tumors [127]. A thorough evaluation including quality imaging is essential to identify sarcomas before unplanned resection [127]. In Dupuytren's disease, MRI is probably most useful in identifying additional pathology such as flexor tendon bowstringing [80]. It may also provide a quantitative noninvasive measure of cellularity in affected areas, which serves as an index of biologic activity [80].
Ultrasound: Augmenting plain radiographs with ultrasound may aid in the diagnosis of septic arthritis following a rattlesnake bite [138]. In a series of 19 cases, all radiolucent foreign bodies were visible on perioperative ultrasound before extraction and invisible after extraction [164]. An 8-MHz Doppler tone assessment may be used to identify superficially displaced neurovascular bundles when Dupuytren cords lie beneath soft fleshy prominences, though false-negatives are possible [80].
CT: Complementary imaging such as CT scans is often useful for diagnosing metacarpohamarian luxations with frontal hamatum fracture [169].
Arthrography: Arthrography is recommended to assist in deciding whether to proceed with surgical or conservative treatment for soft tissue injuries to the dorsum of the metacarpophalangeal joint [162].
Other Considerations: Complementary imaging such as pronation oblique views is often useful for diagnosing metacarpohamarian luxations with frontal hamatum fracture [169]. The diagnosis of Bizarre Parosteal Osteochondromatous Proliferation in pediatric cases can be challenging due to presenting symptoms and radiographic findings [158].
Treatment
General Principles and Initial Management
Treatment of severe soft-tissue injuries in closed and open fractures must be based on correct fracture and soft tissue injury classification, adapted to the individual patient's general health status, secondary diagnoses, and available treatment options [1]. Management of major and extensive soft-tissue injuries associated with skeletal fractures requires a planned approach based on broad training and knowledge rather than limited past experiences [3]. Open fractures require prompt antibiotic administration, timely surgical débridement, skeletal stabilization, and soft-tissue coverage [7]. The management of degloving soft tissue injuries should be individualized based on the specific characteristics of each injury [16]. Soft tissue defects of the upper extremity require durable coverage that allows early postoperative mobilization and rehabilitation to maximize functional outcomes [22]. In delayed presentation of mutilating hand injuries, the assessment of loss in various tissue components can only be made at the time of debridement [23]. Open fractures of the upper limb are less challenging to treat than lower limb counterparts due to good blood supply and adequate soft tissue cover [26]. Conversely, Gustilo type 3B open tibial fractures are associated with very high risks of infection and frequently require further operative intervention to achieve union, particularly if there has been bone loss [26].
On presentation with a severe upper limb injury, the patient should be managed according to advanced trauma life support principles [29]. The wound in severe upper limb injuries should be handled only for removal of gross contaminants, photographic documentation, and sealing from the environment [29]. Mangled extremity injuries require routine trauma protocols that address the patient as a whole, as 10% to 17% of these patients will have an associated life-threatening injury [82]. Prophylactic antibiotics and tetanus prophylaxis should be administered as soon as possible for mangled extremity injuries [82]. The injured extremity should be evaluated for adequate vascular perfusion, and vascular surgery consultation obtained if a vascular injury is suspected [82]. A determination of the time of injury is of great importance in ischemic limbs [82]. The soft tissue wound should be inspected to note the pattern of soft tissue injury and contamination [82]. A cursory removal of gross contamination via irrigation should be performed before dressing wounds and immobilizing the extremity if fracture or joint reduction is necessary before transport to the operating room [82]. A detailed motor and sensory examination should be performed and documented before and after any manipulation of the extremity [82]. The presence of an acute compartment syndrome, which occurs at a rate of 1% to 10% in open fractures, should be sought out [82]. Radiographic evaluation for mangled extremity injuries should include two orthogonal views of any involved joints or long bones, as well as the joint above and below any confirmed fractures [82]. Photographs of the extremity should be obtained whenever possible to provide documentation of the initial injury and a visual record of progress [82]. A comprehensive musculoskeletal examination should be performed to rule out any concomitant musculoskeletal injuries in polytrauma patients [82]. A sterile dressing should be applied to open wounds and the limb immobilized as soon as possible to minimize ongoing soft tissue damage until the patient is in the operating room [82].
Goals in treating upper extremity mangling injuries include preserving life, preserving tissue, preserving function, and reconstructing and restoring function of both the extremity and the patient [81]. General principles for managing mangling injuries include complete debridement of devitalized tissue, restoration of good vascularity, rigid skeletal fixation while minimizing additional soft tissue injury, stable vascularized soft tissue coverage, timely intervention for repair and reconstruction, comprehensive rehabilitation, and secondary procedures as needed [81]. Factors necessary to optimize ultimate function in mangling injuries include careful evaluation of all functional systems, formulation of a comprehensive reconstructive plan, thorough but careful wound debridement, meticulous operative reconstruction, restoration of good vascularity, rigid skeletal fixation, stable vascularized soft tissue coverage, comprehensive rehabilitation, and secondary procedures as needed [81]. The multisystem nature of mangling injuries demands knowledge and expertise in trauma surgery, orthopedic surgery, vascular surgery, and plastic surgery, often benefiting from a multispecialty team approach [81]. Treatment goals for hand fractures include restoration of length, alignment, and articular congruity, along with stabilization and soft tissue repair [48].
Debridement and Wound Management
Prevention remains the ideal treatment for iatrogenic extravasation injuries, and when they occur, they must be diagnosed and treated promptly to minimize the amount of soft tissue injury [5]. Conservative treatment of high-pressure water jet injury of the hand makes admission and close follow-up mandatory, and immediate surgical intervention must be considered in cases of deterioration of the clinical course [9]. Secondary free flap reconstruction delays rehabilitation, prolongs hospital stay, and increases overall costs and number of operations [29]. Granulation tissue develops in response to wound colonization, is poorly penetrated by antibiotics, and is a precursor to fibrosis [29]. Tissue edema peaks within 3 days of injury and contributes to joint stiffness, fibrosis, inadequate mobilization, and extension of the physiologic zone of injury [29]. Serial debridement may result in overall greater tissue loss caused by desiccation, extension of the zone of injury, and edema and granulation tissue compromising delineation between viable and nonviable tissue [29]. Larger wounds resulting from serial debridement compared with primary debridement and reconstruction make free tissue transfer more likely and longer pedicles necessary [29]. A serial approach to debridement may be indicated when conversion of a contaminated wound to a cleaner wound is impossible, such as after severe crush injuries, severe multiplanar degloving, massive wound contamination, electrical burn injuries, or in patients with other life-threatening injuries that preclude a surgical procedure of required duration [29].
The strategy of wide debridement of all injected material and devitalized tissue through extensile incisions, thorough irrigation, open packing, repeat wound debridements as necessary, delayed closure, and aggressive therapy to restore motion has proven successful in patients who present acutely or subacutely and is the preferred approach for the management of high-pressure injection injuries of the hand [137]. The technique of concomitant use of antibiotic-loaded calcium sulphate and bone marrow aspirate after debridement proved safety and efficacy in eradicating infection and bony healing of defects in adult chronic osteomyelitis [105]. The use of Integra in managing soft tissue defects in patients with chemotherapy extravasation injuries can provide coverage that results in both a functional and aesthetically pleasing outcome [118]. Negative pressure wound therapy (NPWT) maintains wound homeostasis and reduces wound exudate and soft tissue edema [145]. Studies have shown that NPWT with instillation further enhances wound healing and expedites the debridement of acute and chronic wounds [145]. Use of NPWT on the amputation stump may shorten the delay from initial ectopic banking to subsequent delayed replantation [145].
Soft Tissue Coverage and Reconstruction
Free flap soft tissue reconstruction should be selected early in the treatment algorithm if a better end result can be anticipated, as it allows for early coverage with composite reconstruction of all damaged or missing tissues and early mobilization to restore function [10]. Delayed wound closure is the rule and emergency free tissue transfer is the exception in major trauma centres due to practical constraints like team availability and patient condition [55]. The outcome of the open fracture is largely dependent on the quality of the soft-tissue envelope [83]. The timing of soft-tissue coverage should occur as quickly as the wound allows and within the 7- to 10-day period for optimal wound coverage [83]. The tissue type (muscle versus fasciocutaneous), the type of transfer (free versus pedicled), and the need for secondary surgeries are imperative considerations to optimize the functional and aesthetic outcome of severe injuries [83]. Orthoplastic teams have demonstrated improved adherence to fracture treatment guidelines and have demonstrated improved patient outcomes [83]. The aesthetic appearance is often improved with the use of a fasciocutaneous flap [83]. Soft-tissue surgeons and orthopaedic trauma surgeons should collaborate for optimal patient outcomes [83].
Orthoplastic teams comprise orthopaedic surgeons trained in microsurgery, orthopaedic trauma surgeons, and plastic surgeons with microsurgical expertise dedicated to limb salvage [147]. Fully integrated orthoplastic teams work together throughout the patient’s hospital course to optimize the efficiency and efficacy of débridement, skeletal fixation, and soft-tissue reconstruction [147]. Débridement and temporary fixation can be achieved in a single surgical procedure, with the promise of early soft-tissue coverage enabling a comprehensive, excisional approach to débridement that removes all nonviable tissues and prepares the defect for rapid definitive management [147]. The goal of soft-tissue coverage should be to facilitate the use of the optimal skeletal reconstruction strategy [147]. A treatment strategy based on the location of soft tissue defect and the perforator anatomy allows for expedient upper limb wound coverage in one stage using perforator-based propeller flaps [52]. The posterior interosseous artery (PIA) flap, either alone or in combination with local flaps, provides reliable soft-tissue coverage and favorable functional outcomes in patients with severe hand injuries [34]. Pelnac® artificial dermis assisted by vacuum sealing drainage can be considered as a viable alternative for addressing severe injuries or complex wound conditions in severe avulsion injuries of the fingers [59]. Free flap reconstruction has been used simultaneously with delayed replantation to deliver uninjured tissue to provide coverage of vital structures such that the replantation need not be performed as a subsequent staged procedure [145]. We do not recommend routine use of the first dorsal interosseous muscle as a flap; however, its use in cases in which the muscle has been denervated would seem justified [136].
Specific Injury Management
A grade 2 closed soft tissue trauma damaged the periosteum and the muscle, but both injuries healed rapidly and the effects of the soft tissue trauma on the fracture healing process were limited to the early phase of the healing process [6]. Treatment of Morel-Lavallée lesions is predominantly conservative or minimally invasive with good functional outcomes [32]. There is insufficient evidence to determine the best splint type or specific indications for surgery in mallet finger injuries [49]. Twelve evidence-based recommendations were developed for the use of NPWT in traumatic wounds and reconstructive surgery, with the strongest evidence base for skin grafts and the weakest for primary treatment of burns [50]. Further experience is required, as well as clinical and basic research, to define optimal indications and benefits of vacuum-assisted wound closure compared with traditional methods of wound management [51]. Locally applied VEGF stimulates fracture healing after acute soft tissue trauma and might be an option for fracture treatment in cases with severe soft tissue damage [45]. Conservative management of tendinous mallet finger injuries that have been neglected for 2 to 4 weeks can be treated as well as those injuries in patients presenting within the first 2 weeks of injury with low long-term complication rates [113]. Early treatment with debridement and stabilization is recommended for ballistic fractures of the hand and wrist, with primary bone grafting considered due to lack of follow-up and patient noncompliance [142].
Splinting for postoperative hand burn care should continue until re-epithelialization is complete, if possible, for maintained prevention of edema, contracture, scarring, and functional impediment [143]. Early and aggressive hand physical therapy and rehabilitation are critical to the success of most surgical interventions for hand burns [143]. Contracture of the skin, fascia, and/or muscles is the most common postburn hand deformity and can severely impede recovery [143]. Hand contracture often occurs at the first webspace (dorsal interosseous and adductor pollicis muscles) and can further involve the volar wrist and interphalangeal joint [143]. The hand surgeon should always be prepared to skin graft or perform a flap after contracture release, since the “lack of skin” is almost always the underlying cause [143]. Flexion contractures should be released before extension contractures to prevent the burying of fingers into the palm and to improve hygiene [143]. After contracture release, split-thickness skin graft (STSG) alone provides reliable coverage and significant range of motion improvement, especially dorsally, whereas chronic volar contractures are more likely to require flap closure to cover critical structures [143]. In the first webspace, local flap management has been shown to require fewer revision procedures than skin grafting [143]. Chronic boutonniere deformity can often retain basic functionality and is passively correctable with splinting; furthermore, invasive procedures often yield unpredictable results [143]. Despite nonsurgical management and late fasciotomy (> 24 hours) being the most described treatments for neonatal limb compartment syndrome, the lowest rate of sequelae was observed when decompression was performed within the first 24 hours [111]. Improved survival rates on the battlefield have resulted in new and ongoing challenges in the care of U.S. military personnel, necessitating the application of new technology and treatment alternatives to provide the best care to those wounded in war [108].
Complications
Infection and Wound Healing: Standardized closed soft tissue injuries result in significantly higher infection rates and lower ID50 values compared to injuries without soft tissue trauma [11]. In agricultural upper extremity injuries, clinical infection rates at 6 months correlate with injury severity: 2 patients for type 1, 14 for type 2, and 24 for type 3 [57]. Osteomyelitis was diagnosed in 6 patients with type 3 wounds and 1 patient with type 2 wounds [57]. Delayed presentation of mutilating hand injuries leads to infection and secondary problems that cause certain sequelae, including chronic pain, stiffness, malpositioning, scissoring, and severe deformities [23]. Even when correctly repaired acutely, hand finger trauma involving skin or soft tissue loss often presents with skin troubles that lead to functional loss and patient dissatisfaction [15]. The relationship between infection and nonunion is confirmed in phalangeal fractures within severely injured hands [135].
Fracture Healing and Bone Complications: Moderate soft tissue trauma (grade 2 closed) damages the periosteum and muscle, but its effects on fracture healing are limited to the early phase [6]. Associated soft tissue injury is a risk factor for nonunion in phalangeal fractures, with (neuro)vascular injury appearing responsible for this effect [135]. Segmental bone loss predisposes to nonunion; in a study of severely injured hands, nonunion occurred in ten fractures with segmental bone loss, where cancellous bone graft was used in only one of these fractures [135]. Inadequate fixation results in malunion and nonunion, secondarily affecting other joints and movement in patients with delayed presentation of hand injuries [23].
Vascular and Neurological Complications: Initial assessment of low-energy civilian gunshot wounds must focus on life-threatening blood loss and possible associated vascular and neurological injuries [4]. Complications following vascular injury can be severe; one patient undergoing treatment for gunshot-related upper extremity nerve injuries underwent transradial amputation [13].
Iatrogenic and Chemical Injuries: Rapid management of iatrogenic cytotoxic product extravasation, as soon as the accident is recognized and before signs of skin suffering appear, is a preponderant factor for therapeutic success [30]. Extensive extravasation injuries are defined as loss of 300 cm² of tissue in the upper arm or forearm, or significant soft tissue loss over the hand or palmar wrist with major tendon, nerve, or vascular exposure [129].
Functional and Long-Term Outcomes: Upper extremity injuries seem to have limited effect on long-term outcome in polytrauma patients, provided no injury was caused to the brachial plexus [47]. Postoperative courses for peritendinous fibrosis of the dorsum of the hand are characterized by prolonged rehabilitation and recurrent swelling [130]. Permanent disability was substantial in 15 patients treated for this condition between 1958 and 1980 [130]. Twelve of these 15 patients returned to work 3 to 30 months postoperatively [130].
Recovery
Light activity (weeks): The evidence provided does not specify a typical week range for the resumption of desk work, driving, or light activities of daily living.
Full activity (months): The evidence provided does not specify a typical month range for the return to manual work, sport, or full range of motion and strength.
Complete recovery / outcome plateau (months): Most patients achieve maximal recovery by 2 to 3 years following surgical resection for soft-tissue sarcoma of the extremities [163].
Rehabilitation protocol: Outcomes for Zone 2 flexor tendon injuries depend on proper surgical methods, the surgeon's experience, and early mobilization [54]. The time elapsed between injury and surgery is not an important risk factor for a good outcome in these injuries [54]. Treatment of Morel-Lavallée lesions in the pediatric population is predominantly conservative or minimally invasive [32].
Functional milestones: At long-term follow-up, patient-reported outcome measures and objective outcomes for the homodigital unipedicle neurovascular island flap for fingertip coverage are satisfactory [53]. At 6-month follow-up, patients with dorsum of the finger coverage using the homodigital subcutaneous flap retained robust soft tissue coverage with no functional restrictions or cold intolerance [61]. Clinical outcomes postoperative for suture anchor repair of avulsed adductor pollicis injury are good, with intact range of motion and no surgical complication at the 6-month follow-up visit [156].
Other Considerations: Moderate soft tissue trauma delays new bone formation only in the early phase of fracture healing [6]. A grade 2 closed soft tissue trauma damaged the periosteum and the muscle, but both injuries healed rapidly [6]. The homodigital unipedicle neurovascular island flap for fingertip coverage is a safe and reliable flap at long-term follow-up [53]. Minor degrees of A2 pulley injury do not appear to have a longterm deleterious affect on climbing ability [60]. Treatment of Morel-Lavallée lesions in the pediatric population yields good functional outcomes [32]. The PIA flap, either alone or in combination with local flaps, provides reliable soft-tissue coverage and favorable functional outcomes in patients with severe hand injuries [34]. Donor-site morbidity for the parascapular free flap is limited to widened incisional scar and no detectable impairment of the musculoskeletal function [58]. Although associated with a relatively high rate of complications, vascularised fibular grafts for reconstruction of extremity bone defects after resection of bone and soft-tissue tumours have a high rate of successful limb salvage and a good long-term functional outcome [154].
Key Evidence
- [Paper] Treatment should always be based on the correct classification of the fracture and the corresponding soft tissue injury, but needs to be adapted to the individual patient considering general health status, secondary diagnoses and currently available treatment options. [1] (10.1016/j.injury.2024.111935)
- [L5] Appropriate management of the soft-tissue envelope is essential to a good outcome, and orthopaedic surgeons must adhere to strict principles of soft-tissue management to ensure appropriate decision making and accurate prediction of outcome. [2] (10.5435/00124635-199701000-00005)
- [L5] Management of major and extensive soft-tissue injuries associated with skeletal fractures requires a planned approach and action based on broad training and knowledge, and not one or two past experiences. [3] (10.2106/00004623-196244040-00018)
- [Paper] Initial assessment should focus on assessment of life-threatening blood loss, early antibiotics, soft tissue injury and possible associated injuries (vascular and neurological). [4] (10.1016/j.injury.2025.112787)
- [L5] Prevention remains the ideal treatment for these iatrogenic injuries, and when they do occur, they must be diagnosed and treated promptly to minimize the amount of soft tissue injury. [5] (10.1016/j.jhsa.2011.10.001)
- [Paper] A grade 2 closed soft tissue trauma damaged the periosteum and the muscle, but both injuries healed rapidly and the effects of the soft tissue trauma on the fracture healing process were limited to the early phase of the healing process. [6] (10.1002/jor.20173)
- [L5] Soft tissue coverage is required to salvage traumatized limbs and restore adequate function and form. [8] (10.1016/j.hcl.2017.09.007)
- [L5] Conservative treatment of a patient with this type of injury makes admission and close follow-up mandatory, and immediate surgical intervention must be considered in cases of deterioration of the clinical course. [9] (10.1016/s0363-5023(85)80047-2)
- [L5] Free flap soft tissue reconstruction should be selected early in the treatment algorithm if a better end result can be anticipated, as it allows for early coverage with composite reconstruction of all damaged or missing tissues and early mobilization to restore function. [10] (10.1016/j.hcl.2007.02.007)
- [Paper] The infection rate after a standardized closed soft tissue injury was significantly higher and the ID50 lower than without soft tissue trauma. [11] (10.1016/s0736-0266(02)00149-3)
- [L4] The initial clinical presentation is often reassuring and does not reflect the actual depth or severity of the injury. [12] (10.1016/j.main.2012.04.004)
- [L4] [13] (10.1016/j.jhsa.2021.03.020)
- [L5] The decision on how to approach soft tissue coverage is complex and requires consideration of the wound character, patient factors, and anticipated functional results. [14] (10.1016/j.hcl.2020.03.011)
- [L4] Hand fingers trauma with loss of skin or soft tissue injuries, even if correctly repaired in acute, often present skin troubles that can lead to functional loss and patient’s unsatisfaction. [15] (10.1016/j.main.2012.10.104)
- [L4] The management of degloving soft tissue injuries (DSTIs) should be individualized, taking into account the specific characteristics of each injury. [16] (10.1016/j.injury.2024.111939)
- [L4] This case highlights the importance of considering rare causes, like soft tissue sarcoma, in cases of compartment syndrome without clear trauma. [18] (10.1016/j.jhsg.2025.01.003)
- [L4] Blast and fragment injuries are the most common wounds in modern warfare, with most involving secondary blast injuries from flying debris. [20] (10.2106/00004623-200207000-00022)
- [Case_report] The authors emphasize that emergent reduction, early soft tissue cover, and orderly surgical fixation are essential for managing complex open carpal dissociations. [21] (10.1016/j.jhsa.2007.07.025)
- [L5] Soft tissue defects of the upper extremity require durable coverage that will allow early postoperative mobilization and rehabilitation to maximize functional outcomes. [22] (10.1016/j.hcl.2014.08.002)
- [L5] [23] (10.1016/j.hcl.2016.07.008)
- [L5] When signs of rapidly progressive soft-tissue infection develop in such a patient, Aeromonas hydrophila should be considered as a causative pathogen. [25] (10.2106/jbjs.c.00923)
- [Paper] [26] (10.1016/j.injury.2024.111604)
- [L4] Despite their initial horrible appearance, injuries caused by “blunt-edged items” are quite harmless to the affected limb because they follow weak anatomic spaces of the extremity and cause minimal tissue damage leaving all vascular and nervous structures intact. [28] (10.1142/s0218810417500101)
- [L5] [29] (10.1016/j.hcl.2014.01.001)
- [L4] Rapid management, as soon as the accident is recognized and before the appearance of signs of skin suffering, is a preponderant factor for therapeutic success. [30] (10.1016/j.main.2013.10.124)
- [L4] Treatment is predominantly conservative or minimally invasive with good functional outcomes. [32] (10.1177/2325967121s00025)
- [L4] The PIA flap, either alone or in combination with local flaps, provides reliable soft-tissue coverage and favorable functional outcomes in patients with severe hand injuries. [34] (10.1016/j.injury.2026.113151)
- [L5] [35] (10.1016/s0749-0712(21)00457-1)
- [Paper] The results showed that locally applied VEGF stimulates fracture healing after acute soft tissue trauma and might be an option for fracture treatment in cases with severe soft tissue damage. [45] (10.1002/jor.21340)
- [L3] Injuries to the upper extremities seem to have limited effect on long-term outcome in patients with polytrauma, as long as no injury was caused to the brachial plexus. [47] (10.1302/0301-620x.99b2.37999)
- [L4] There is insufficient evidence to determine the best splint type or specific indications for surgery. [49] (10.1016/j.jhsa.2009.06.018)
- [L1] Twelve evidence-based recommendations were developed for the use of NPWT in traumatic wounds and reconstructive surgery, with the strongest evidence base for skin grafts and the weakest for primary treatment of burns. [50] (10.1016/s0020-1383(11)00041-6)
- [L5] Further experience is required, as well as clinical and basic research, to define optimal indications and benefits compared with traditional methods of wound management. [51] (10.5435/00124635-200209000-00002)
- [L4] A treatment strategy based on the location of soft tissue defect and the perforator anatomy allows for expedient upper limb wound coverage in one stage. [52] (10.1016/s0363-5023(11)60028-2)
- [L4] At a long-term follow-up, the patient-reported outcome measures and objective outcomes of this flap are satisfactory and it is a safe and reliable flap. [53] (10.1177/17531934231172081)
- [L4] The time elapsed between injury and surgery is not an important risk factor for a good outcome; rather, outcomes depend on proper surgical methods, the surgeon's experience, and early mobilization. [54] (10.1177/17531934211024435)
- [L5] Delayed wound closure is the rule and emergency free tissue transfer is the exception in major trauma centres due to practical constraints like team availability and patient condition. [55] (10.1016/j.injury.2007.03.011)
- [L2] [57] (10.1016/j.jhsa.2007.09.003)
- [L4] Donor-site morbidity is limited to widened incisional scar and no detectable impairment of the musculoskeletal function. [58] (10.1016/s0266-7681(96)80280-4)
- [L4] This approach can be considered as a viable alternative for addressing severe injuries or complex wound conditions. [59] (10.1186/s13018-025-05547-z)
- [L5] Minor degrees of this injury do not appear to have a longterm deleterious affect on climbing ability. [60] (10.1016/0266-7681_90_90135-q)
- [L4] At 6-month follow-up, all three patients retained robust soft tissue coverage with no functional restrictions or cold intolerance. [61] (10.1007/s11552-010-9279-3)
- [L4] Patients often require reconstruction rather than repair, and many will require secondary procedures, making prevention the best treatment. [63] (10.1016/j.jhsa.2014.08.041)
- [L4] This case series demonstrates the extent and severity of hand injuries that can be caused by sword assaults with devastating loss of function for the victims. [89] (10.1177/1753193410381576)
- [L4] Individuals presenting with SI GSWs are more likely to be older, to require multiple operations, to develop infections, and to present with acute carpal tunnel syndrome requiring urgent surgical decompression. [90] (10.1177/15589447211014603)
- [L3] Clinical findings suggestive of the need for hospitalization include location of the bite over a joint or tendon sheath, erythema, pain, and swelling. [92] (10.1016/j.jhsa.2013.11.003)
- [L4] A neoplasm should be considered in the differential diagnosis of the cause of a compartment syndrome, as a soft-tissue sarcoma can cause necrosis and edema leading to acute compartment syndrome. [93] (10.2106/00004623-199508000-00017)
- [L4] [94] (10.1016/j.jhsa.2012.07.005)
- [L4] Treating providers should recognize crush injury, prolonged decubitus, and infection as the most common causes of acute hand compartment syndrome. [96] (10.1177/15589447221084012)
- [L3] The first metacarpal is the most vulnerable bone, and the tackle is the most dangerous phase of play. [103] (10.1016/0266-7681(93)90210-7)
- [L5] Flexor pulley lesions, followed by fractures and strains are the most common lesions affecting the hand that are related to this practice. [104] (10.1142/s2424835516400038)
- [L4] The technique proved safety and efficacy in eradicating the infection and bony healing of the defects after debridement. [105] (10.1007/s00264-018-4063-z)
- [L5] Improved survival rates on the battlefield have resulted in new and ongoing challenges in the care of U.S. military personnel, necessitating the application of new technology and treatment alternatives to provide the best care to those wounded in war. [108] (10.1016/j.jhsa.2007.07.007)
- [L4] [110] (10.1016/j.injury.2008.06.007)
- [L4] Despite nonsurgical management and late fasciotomy (> 24 hours) being the most described treatments, the lowest rate of sequelae was observed when decompression was performed within the first 24 hours. [111] (10.1016/j.jhsa.2023.08.013)
- [L1] Hand trauma, particularly surgical trauma and repetitive mechanical stress, is associated with the onset of Dupuytren's disease. [112] (10.1177/17531934251360545)
- [L3] Conservative management of tendinous mallet finger injuries that have been neglected for 2 to 4 weeks can be treated as well as those injuries in patients presenting within the first 2 weeks of injury with low long-term complication rates. [113] (10.1016/j.jhsa.2014.06.140)
- [L4] Closed degloving of the thumb is a rare condition caused by crushing and elongation forces that detaches soft tissues without skin disruption. [121] (10.1016/j.jhsa.2007.06.016)
- [L4] [129] (10.1016/s0363-5023(83)80048-3)
- [L4] [130] (10.1016/s0363-5023(82)80148-2)
- [L4] [135] (10.1054/jhsb.2000.0486)
- [L5] We do not recommend routine use of the first dorsal interosseous muscle as a flap; however, its use in cases in which the muscle has been denervated would seem justified. [136] (10.1016/s0363-5023(85)80208-2)
- [L5] The strategy of wide debridement of all injected material and devitalized tissue through extensile incisions, thorough irrigation, open packing, repeat wound debridements as necessary, delayed closure, and aggressive therapy to restore motion has proven successful in patients who present acutely or subacutely and is the preferred approach for the management of high-pressure injection injuries of the hand. [137] (10.1097/00130911-199906000-00002)
- [L5] Augmenting plain radiographs with additional imaging modalities like ultrasound or dark-field imaging may aid in diagnosis. [138] (10.1016/j.jhsa.2021.04.004)
- [L5] [139] (10.1016/j.jhsa.2010.03.019)
- [L4] The purpose of this review was to present an overview of local and regional flaps commonly used for soft tissue reconstruction within the hand, focusing on a systematic approach to treating challenging conditions with optimal soft tissue reconstruction that protects against contractures and facilitates mobility. [140] (10.1016/j.jhsa.2013.09.027)
- [L4] Early treatment with debridement and stabilization is recommended, with primary bone grafting considered due to lack of follow-up and patient noncompliance. [142] (10.1177/1558944717697432)
- [L5] [143] (10.1016/j.jhsa.2025.02.020)
- [L4] The authors propose a new classification, class IIC, for ring avulsion injuries with venous compromise only, which should be treated with micro-venous reconstruction. [144] (10.1016/0363-5023(89)90187-1)
- [L4] [145] (10.1016/j.hcl.2019.01.002)
- [L5] Fasciocutaneous flaps are the optimal choice for initial soft tissue reconstruction when secondary procedures are foreseen due to their pliable nature and ease of re-elevation. [146] (10.1016/j.hcl.2014.01.004)
- [L4] The technique of two simultaneous pedicled flaps is a simple and successful alternative to free tissue transfer for coverage of complex soft tissue defects in the hand and forearm, particularly in critically ill, multi-extremity injured patients where free tissue transfer is not indicated. [148] (10.1177/1753193409347428)
- [L4] It provided a flexible design for customized coverage of complex soft tissue defects with limited donor site morbidity. [150] (10.1186/s13018-023-03852-z)
- [L4] Bangle avulsion injuries of the forearm can range in severity from a relatively minor soft tissue injury to complete amputation. [153] (10.1177/1753193413519537)
- [L4] Although associated with a relatively high rate of complications, each reconstruction method is useful, with a high rate of successful limb salvage and a good long-term functional outcome. [154] (10.1302/0301-620x.99b9.bjj-2017-0219.r1)
- [L5] We report good clinical outcomes postoperative, with intact ROM and no surgical complication at the 6-month follow-up visit. [156] (10.1097/bth.0000000000000225)
- [L4] The diagnosis in pediatric cases can be challenging due to presenting symptoms and radiographic findings. [158] (10.1016/j.jhsa.2020.05.002)
- [L4] The authors recommend arthrography to assist in deciding whether to proceed with surgical or conservative treatment. [162] (10.1054/jhsb.2001.0656)
- [L4] Most patients will achieve maximal recovery by 2 to 3 years following surgical resection for soft-tissue sarcoma of the extremities. [163] (10.2106/jbjs.23.01007)
- [L4] All radiolucent foreign bodies in the series were visible on perioperative ultrasound before extraction and invisible after extraction. [164] (10.1016/j.hansur.2018.10.056)
- [L4] Metacarpohamarian luxations with frontal hamatum fracture are often underdiagnosed, and complementary imaging such as pronation oblique views or CT scans is often useful. [169] (10.1016/s1297-3203(00)73607-9)
See Also
- Dupuytren's Disease
- Tumors
- Mallet Finger
- Reconstructive Surgery
References
[1] Initial treatment of severe soft-tissue injuries in closed and open fractures to prevent fracture-related infection. Injury. 2024. DOI: 10.1016/j.injury.2024.111935
[2] Soft-Tissue Injuries Associated With High-Energy Extremity Trauma: Principles of Management. Journal of the American Academy of Orthopaedic Surgeons. 1997. DOI: 10.5435/00124635-199701000-00005
[3] Major and Extensive Soft-Tissue Injuries Complicating Skeletal Fractures. The Journal of Bone & Joint Surgery. 1962. DOI: 10.2106/00004623-196244040-00018
[4] Acute management of low energy civilian gunshot wounds. Injury. 2025. DOI: 10.1016/j.injury.2025.112787
[5] Extravasation Injuries. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2011.10.001
[6] Moderate soft tissue trauma delays new bone formation only in the early phase of fracture healing. Journal of Orthopaedic Research. 2006. DOI: 10.1002/jor.20173
[7] Chapter 14 Evaluation and Management of Soft-Tissue Injury and Open Fractures. 2021.
[8] Traumatic Wounds of the Upper Extremity. Hand Clinics. 2018. DOI: 10.1016/j.hcl.2017.09.007
[9] High-pressure water jet injury of the hand. The Journal of Hand Surgery. 1985. DOI: 10.1016/s0363-5023(85)80047-2
[10] Indications and Selection of Free Flaps for Soft Tissue Coverage of the Upper Extremity. Hand Clinics. 2007. DOI: 10.1016/j.hcl.2007.02.007
[11] Influence of a standardized closed soft tissue trauma on resistance to local infection. An experimental study in rats. Journal of Orthopaedic Research. 2003. DOI: 10.1016/s0736-0266(02)00149-3
[12] Gelure au gaz fréon : une brulure atypique évoluant en deux temps. Chirurgie de la Main. 2012. DOI: 10.1016/j.main.2012.04.004
[13] Gunshot-Related Upper Extremity Nerve Injuries at a Level 1 Trauma Center. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2021.03.020
[14] Soft Tissue Coverage for Severe Infections. Hand Clinics. 2020. DOI: 10.1016/j.hcl.2020.03.011
[15] Traitement post-traumatique des lésions cutanées de la main par lipofilling. Chirurgie de la Main. 2012. DOI: 10.1016/j.main.2012.10.104
[16] Comprehensive management of degloving soft tissue injuries of the extremity: A 12-year retrospective study. Injury. 2024. DOI: 10.1016/j.injury.2024.111939
[18] Forearm Compartment Release with Incidental Soft Tissue Sarcoma. Journal of Hand Surgery Global Online. 2025. DOI: 10.1016/j.jhsg.2025.01.003
[20] Blast and Fragment Injuries of the Musculoskeletal System. The Journal of Bone & Joint Surgery. 2002. DOI: 10.2106/00004623-200207000-00022
[21] Complex Carpal Dissociation With Open, Complete, and Divergent Trapezium, Capitate, and Hamate Dislocation: A Case Report. The Journal of Hand Surgery. 2007. DOI: 10.1016/j.jhsa.2007.07.025
[22] Soft Tissue Coverage of the Upper Extremity. Hand Clinics. 2014. DOI: 10.1016/j.hcl.2014.08.002
[23] Challenges Posed by Delayed Presentation of Mutilating Hand Injuries. Hand Clinics. 2016. DOI: 10.1016/j.hcl.2016.07.008
[25] Aeromonas Hydrophila Necrotizing Fasciitis. The Journal of Bone & Joint Surgery. 2006. DOI: 10.2106/jbjs.c.00923
[26] Timing of debridement: When to do it, and who should perform it?. Injury. 2024. DOI: 10.1016/j.injury.2024.111604
[28] A Rare Type of Upper Extremity Injury: Penetrating Injuries Caused by Blunt-edged Items. The Journal of Hand Surgery (Asian-Pacific Volume). 2017. DOI: 10.1142/s0218810417500101
[29] Free Muscle Flaps for Reconstruction of Upper Limb Defects. Hand Clinics. 2014. DOI: 10.1016/j.hcl.2014.01.001
[30] Les extravasations iatrogènes des produits cytotoxiques : à propos de 19 cas. Chirurgie de la Main. 2013. DOI: 10.1016/j.main.2013.10.124
[32] ARE SPORTS INJURIES THE MOST COMMON CAUSE OF MOREL-LAVALLEE LESIONS IN THE PEDIATRIC POPULATION?. Orthopaedic Journal of Sports Medicine. 2021. DOI: 10.1177/2325967121s00025
[34] Posterior interosseous artery flap for severe hand injuries: Outcomes of reconstruction combined with local and regional flaps. Injury. 2026. DOI: 10.1016/j.injury.2026.113151
[35] THE MANAGEMENT OF PENETRATING TRAUMA TO THE HAND. Hand Clinics. 1999. DOI: 10.1016/s0749-0712(21)00457-1
[36] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[37] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > Image DISORDERS OF THE MUSCULATURE OF THE HAND.
[38] Exam Of The Hand Wrist 2Ed. 1.1 SKELETON OF THE HAND > The osseous skeleton.
[40] Chapter 8 Acute Compartment Syndrome. 2021.
[45] Local application of VEGF compensates callus deficiency after acute soft tissue trauma—results using a limb‐shortening distraction procedure in rabbit tibia. Journal of Orthopaedic Research. 2011. DOI: 10.1002/jor.21340
[47] Injuries to the upper extremities in polytrauma. The Bone & Joint Journal. 2017. DOI: 10.1302/0301-620x.99b2.37999
[48] Chapter 95 Hand Trauma. 2019.
[49] Mallet Finger Injuries. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2009.06.018
[50] Evidence-based recommendations for the use of Negative Pressure Wound Therapy in traumatic wounds and reconstructive surgery: Steps towards an international consensus. Injury. 2011. DOI: 10.1016/s0020-1383(11)00041-6
[51] New Techniques in Wound Management: Vacuum-Assisted Wound Closure. Journal of the American Academy of Orthopaedic Surgeons. 2002. DOI: 10.5435/00124635-200209000-00002
[52] Clinical Application of Perforator Based Propeller Flaps in Upper Limb Soft Tissue Reconstruction. The Journal of Hand Surgery. 2011. DOI: 10.1016/s0363-5023(11)60028-2
[53] Long-term patient-reported outcome measures of fingertip coverage with a homodigital unipedicle neurovascular island flap. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231172081
[54] Up to five-week delay in primary repair of Zone 2 flexor tendon injuries: outcomes and complications. Journal of Hand Surgery (European Volume). 2021. DOI: 10.1177/17531934211024435
[55] Early versus delayed closure of open fractures. Injury. 2007. DOI: 10.1016/j.injury.2007.03.011
[57] The Microbiology and Risk of Infection Following Open, Agricultural Upper Extremity Injuries. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2007.09.003
[58] The parascapular free flap for reconstruction of post-traumatic defects of the extremities. Journal of Hand Surgery. 1996. DOI: 10.1016/s0266-7681(96)80280-4
[59] Pelnac® artificial dermis assisted by vacuum sealing drainage for treatment of severe avulsion injuries of the fingers. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05547-z
[60] Injury to the A2 Pulley in Rock Climbers. Journal of Hand Surgery. 1990. DOI: 10.1016/0266-7681_90_90135-q
[61] The Homodigital Subcutaneous Flap for Soft Tissue Coverage of the Dorsum of the Finger: A Case Series. HAND. 2010. DOI: 10.1007/s11552-010-9279-3
[63] Firework-Related Injuries of the Hand. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.08.041
[67] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[69] Exam Of The Hand Wrist 2Ed. Planning skin cover of the hand and forearm.
[70] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[71] Exam Of The Hand Wrist 2Ed. Techniques of investigation of the arterial supply by J P Melki > Vascularization of the thumb > Palmar aspect.
[74] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > FLEXOR TENDON INJURY.
[76] Exam Of The Hand Wrist 2Ed. The dorsal skin.
[77] Green S Operative Hand Surgery. PERTINENT ANATOMY.
[80] Dupuytren S Disease And Related Hyperproliferative Disorders. 54. The Future of Dupuytren’s Research and Treatment > 54.4 Mechanical Measurements and Procedures > 54.4.4 Imaging.
[81] Green S Operative Hand Surgery. EVOLUTION IN THE TREATMENT OF MANGLING INJURIES > PRINCIPLES.
[82] Rockwood And Green S Fractures In Adults. Effect of Blast on the Musculoskeletal System > Principles of Management.
[83] Orthopaedic Knowledge Update Trauma. Extremity Soft-Tissue Reconstruction Associated With Fracture > Summary.
[89] Severe hand injuries resulting from Samurai sword assaults: a Dublin case series. Journal of Hand Surgery (European Volume). 2010. DOI: 10.1177/1753193410381576
[90] Point Blank: A Retrospective Review of Self-inflicted Gunshot Wounds to the Hand. HAND. 2021. DOI: 10.1177/15589447211014603
[92] Cat Bite Infections of the Hand: Assessment of Morbidity and Predictors of Severe Infection. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2013.11.003
[93] Synovial sarcoma presenting as an acute compartment syndrome.. The Journal of Bone & Joint Surgery. 1995. DOI: 10.2106/00004623-199508000-00017
[94] High-Pressure Injection Injuries. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.07.005
[96] Surgical Demographics of Acute Hand Compartment Syndrome. HAND. 2022. DOI: 10.1177/15589447221084012
[103] Injuries to the Hand in Rugby Union Football. Journal of Hand Surgery. 1993. DOI: 10.1016/0266-7681(93)90210-7
[104] Hand Injury in Rock Climbing: Literature Review. The Journal of Hand Surgery (Asian-Pacific Volume). 2016. DOI: 10.1142/s2424835516400038
[105] One-stage surgery for adult chronic osteomyelitis: concomitant use of antibiotic-loaded calcium sulphate and bone marrow aspirate. International Orthopaedics. 2018. DOI: 10.1007/s00264-018-4063-z
[108] Injuries Sustained to the Upper Extremity Due to Modern Warfare and the Evolution of Care. The Journal of Hand Surgery. 2007. DOI: 10.1016/j.jhsa.2007.07.007
[110] Versatility of the island forearm flap in the management of extensive skin defects of the hand. Injury. 2008. DOI: 10.1016/j.injury.2008.06.007
[111] Neonatal Limb Compartment Syndrome: A Comprehensive Review. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2023.08.013
[112] Incidence of Dupuytren’s disease following hand trauma: a systematic review. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934251360545
[113] Soft-Tissue Mallet Injuries: A Comparison of Early and Delayed Treatment. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.06.140
[118] In_Reply_S036350231200826X. 2008.
[121] Closed Degloving of the Thumb. The Journal of Hand Surgery. 2007. DOI: 10.1016/j.jhsa.2007.06.016
[127] Chapter 68 Soft-Tissue Tumors: Evaluation and Diagnosis. 2020.
[129] Management of extensive doxorubicin hydrochloride extravasation injuries. The Journal of Hand Surgery. 1983. DOI: 10.1016/s0363-5023(83)80048-3
[130] Experience with peritendinous fibrosis of the dorsum of the hand. The Journal of Hand Surgery. 1982. DOI: 10.1016/s0363-5023(82)80148-2
[135] Treatment of Phalangeal Fractures in Severely Injured Hands. Journal of Hand Surgery. 2001. DOI: 10.1054/jhsb.2000.0486
[136] The denervated first dorsal interosseous muscle flap: A case report. The Journal of Hand Surgery. 1985. DOI: 10.1016/s0363-5023(85)80208-2
[137] Open Wound Technique for High-pressure Injection Injuries of the Hand. Techniques in Hand & Upper Extremity Surgery. 1999. DOI: 10.1097/00130911-199906000-00002
[138] Septic Arthritis of the Proximal Interphalangeal Joint After Rattlesnake Bite. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2021.04.004
[139] Acute Management of Burn Injuries to the Hand and Upper Extremity. The Journal of Hand Surgery. 2010. DOI: 10.1016/j.jhsa.2010.03.019
[140] Local and Regional Flaps for Hand Coverage. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2013.09.027
[142] Current Trends in the Management of Ballistic Fractures of the Hand and Wrist: Experiences of a High-Volume Level I Trauma Center. HAND. 2017. DOI: 10.1177/1558944717697432
[143] The Acute Burned Upper Extremity: Evolution of Practices and Management. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2025.02.020
[144] A new class of ring avulsion injuries. The Journal of Hand Surgery. 1989. DOI: 10.1016/0363-5023(89)90187-1
[145] Revascularization and Replantation in the Hand. Hand Clinics. 2019. DOI: 10.1016/j.hcl.2019.01.002
[146] Refinements and Secondary Surgery After Flap Reconstruction of the Traumatized Hand. Hand Clinics. 2014. DOI: 10.1016/j.hcl.2014.01.004
[147] Chapter 16 Extremity Soft-Tissue Reconstruction Associated With Fracture. 2021.
[148] Simultaneous pedicled flaps for coverage of complex blast injuries to the forearm and hand (with supplemental external fixation to the iliac crest for immobilization). Journal of Hand Surgery (European Volume). 2009. DOI: 10.1177/1753193409347428
[150] Individualized design of thoracodorsal artery perforator chimeric flap for customized reconstruction of complex three-dimensional defects in the extremities. Journal of Orthopaedic Surgery and Research. 2023. DOI: 10.1186/s13018-023-03852-z
[153] Bangle avulsion injuries of the forearm. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193413519537
[154] Vascularised fibular grafts for reconstruction of extremity bone defects after resection of bone and soft-tissue tumours. The Bone & Joint Journal. 2017. DOI: 10.1302/0301-620x.99b9.bjj-2017-0219.r1
[156] Suture Anchor Repair of Avulsed Adductor Pollicis Injury, Secondary to Motor Vehicle Collision: Case Report and Technique. Techniques in Hand & Upper Extremity Surgery. 2019. DOI: 10.1097/bth.0000000000000225
[158] Bizarre Parosteal Osteochondromatous Proliferation (Nora Lesion) in Pediatric Phalanges. The Journal of Hand Surgery. 2021. DOI: 10.1016/j.jhsa.2020.05.002
[162] Treatment of Soft Tissue Injuries to the Dorsum of the Metacarpophalangeal Joint (Boxer’s Knuckle). Journal of Hand Surgery. 2002. DOI: 10.1054/jhsb.2001.0656
[163] Mapping the Course of Recovery Following Limb-Salvage Surgery for Soft-Tissue Sarcoma of the Extremities. Journal of Bone and Joint Surgery. 2024. DOI: 10.2106/jbjs.23.01007
[164] Intérêt de l’échographie peropératoire dans la recherche de corps étrangers à la main — à propos d’une série de 19 cas. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.056
[169] 13 Une forme rare de luxation carpométacarpiennne : la luxation métacarpohamulienne avec fracture frontale de l’hamatum. À propos de 4 cas. Chirurgie de la Main. 2000. DOI: 10.1016/s1297-3203(00)73607-9