Clinicians › Hand
Dislocations
Hand/upper extremity dislocations: diagnosis, reduction techniques, and open management for irreducible variants (perilunate, IP joint).
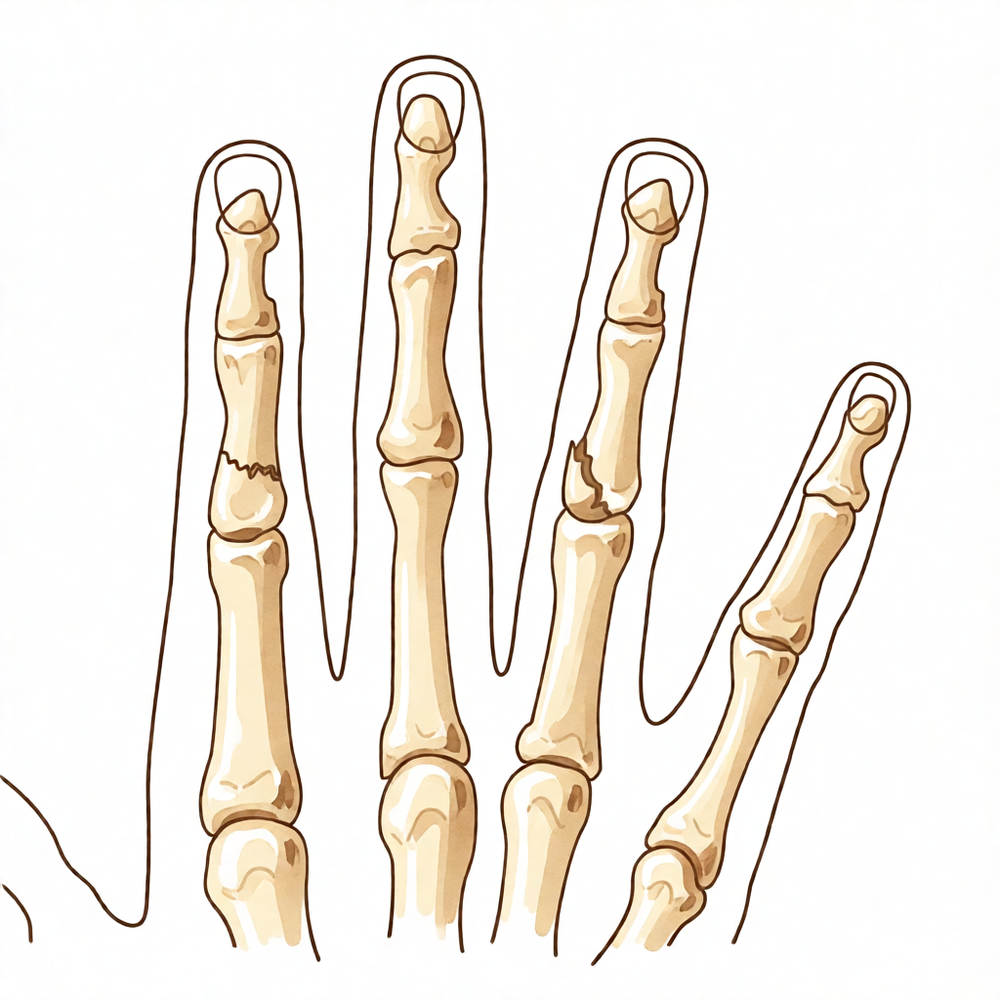
Overview
Shoulder dislocations present distinct epidemiological and prognostic profiles that guide initial management. The 15-to-19-year age group carries the highest risk of recurrent dislocation and instability following glenohumeral dislocation [1]. In patients requiring stabilization surgery, there is no significant difference between the side of dislocation and hand dominance [72]. Recurrent instability necessitating capsular reconstruction appears more prevalent in patients with a prior history of shoulder dislocation, particularly in the context of luxatio erecta [17]. Prognostic factors vary by injury type; for locked posterior shoulder dislocations, the duration of the dislocation is the primary factor influencing clinical outcomes, rather than humeral head defect size or patient age [12]. Associated injuries constitute an adverse prognostic factor for subtalar dislocations [48], while delayed treatment of proximal interphalangeal joint injuries risks persistent subluxation or dislocation [2].
General management principles prioritize closed reduction for simultaneous small finger dislocations without associated lesions [3]. Most pediatric metacarpal fractures and dislocations evolve favorably, with only 20% requiring reduction and surgical stabilization being rare [4]. For acute Kaplan dislocation, a proposed closed reduction manoeuvre is effective and can be performed under local anaesthesia in most cases, reducing the need for surgery [64]. Following surgery for irreducible open metacarpophalangeal joint dislocation, immobilization is recommended for 2 weeks [11].
Operative intervention is supported for patients under 25 to reduce re-dislocation after first-time traumatic anterior shoulder dislocation [7], particularly in young, active individuals involved in highly demanding sports [71]. When acute irreducible shoulder dislocations are treated with open or arthroscopic procedures, recurrence rates are low, with no recurrent dislocation reported in limited follow-up [5]. However, the choice of open reduction and stabilization technique for chronic anterior dislocation is highly variable, leading to wide variation in outcomes and a high number of complications such as resubluxation and early arthrosis [14]. Specific indications include the modified McLaughlin procedure for acute locked posterior dislocations with a head defect of 25–45% [68] and surgical treatment for Rockwood type IV dislocations, whereas Rockwood type III dislocations benefit from conservative treatment [58]. Operative management of carpometacarpal fracture dislocations yields good-to-excellent functional outcomes despite relatively high surgical complication rates [34], with open reduction and internal fixation recommended for delayed presentations [55]. Suture-button stabilisation offers a less-invasive alternative for thumb carpometacarpal joint instability [15]. In hamatometacarpal joint fracture-dislocations, a large dislocated fragment or suspicion of ligamental interposition indicates open reduction and internal fixation [62]. Outcomes following surgical treatment of volar fracture subluxation/dislocation of the proximal interphalangeal joint are poor, with most patients developing arthritis and some requiring salvage procedures [61]. Dynamic distraction external fixation for unstable proximal interphalangeal joint fracture-dislocations produces results comparable with other techniques [70]. Operative intervention is necessary for most complex cases of elbow dislocations and complex instability [60].
Anatomy & Pathophysiology
Glenohumeral Joint
Glenohumeral instability is defined as the inability of the humeral head to remain centered in the glenoid fossa [8]. This condition is distinct from laxity, a physical finding often unassociated with clinical instability [8]. Instability is most commonly a functional disability and rarely a cause of pain in the absence of obvious functional difficulties [8]. Etiologies include congenital factors such as glenoid dysplasia or systemic conditions like Ehlers-Danlos syndrome [8]. Traumatic instability arises from injury to the bone, rotator cuff, labrum, capsule, or a combination of ligaments [8], while atraumatic instability results from decompensation of stabilizing mechanisms [8]. Patients with a traumatic etiology for recurrent instability usually have unidirectional instability and obvious pathology such as a Bankart lesion [8]. Recurrent traumatic instability typically produces symptoms when the arm is placed in a position near that of the original injury [8]. Recurrent instability can consist of repeated glenohumeral dislocations, subluxations, or both [8]. A dislocation is classified as locked or fixed if the humeral head has been impaled on the edge of the glenoid, making reduction difficult [8]. The group aged 15 to 19 years is at the highest risk of recurrent dislocation and instability following glenohumeral dislocation [1].
Posterior dislocations of the shoulder are often overlooked because standard antero-posterior roentgenograms fail to demonstrate the posterior displacement [56]. Anatomicopathological findings in posterior shoulder dislocation can include a pouchlike posterior distension of the capsule and a frayed posterior labrum [56]. A congenitally redundant posterior capsule may predispose a patient to posterior glenohumeral dislocation following trivial trauma [56].
Hip Joint
Posterior hip dislocations outnumber anterior dislocations by approximately nine to one [77] and represent 90% of all hip dislocations [78]. The typical mechanism for a posterior hip dislocation is a deceleration accident in which the occupant's knee strikes the dashboard with both the knee and hip flexed [77]. The position of the hip, the force vector applied, and the individual's anatomy affect the direction of the dislocation and whether a fracture–dislocation or pure dislocation occurs [77].
The anterior iliofemoral and posterior ischiofemoral ligaments run from the acetabulum to the femoral neck [78]. The ligamentum teres runs from the acetabulum (cotyloid fossa) to the femoral head (fovea centralis) [78]. The main arterial blood supply to the hip comes from the superior and posterior cervical arteries, which are primarily derived from the medial circumflex artery [78]. A lesser contribution of 10% to 15% to the hip's arterial blood supply is made via the artery of the ligamentum teres [78].
Hand and Wrist
The skeleton of the hand and wrist consists of 27 bones, of which 19 are long bones [39]. The hand consists of 19 bones, 17 articulations, and 19 muscles situated entirely within the hand [79]. The skeleton of the hand is divided into five rays, each making up a polyarticulated chain comprising the metacarpals and phalanges [39]. The base of each metacarpal articulates with the distal row of the carpus [39]. The wrist has three axes of movement, permitting the hand to be positioned in any spatial configuration [39]. The thumb metacarpal makes an angle of about 45 degrees with the second metacarpal in the sagittal plane [39]. The transverse axis of the palm forms an acute angle of approximately 75 degrees with the longitudinal axis [39]. The epiphyseal plates are located at the proximal ends of the phalanges and the first metacarpal, whereas they are located at the distal ends of the other metacarpals [39].
The extrinsic extensors run through six different fibroosseous retinacular compartments at the wrist level [38]. * First compartment: Contains the abductor pollicis longus and the extensor pollicis brevis [38]. * Second compartment: Contains the extensor carpi radialis longus and the extensor carpi radialis brevis [38]. * Third compartment: Contains the extensor pollicis longus, which turns abruptly radialward about Lister tubercle [38]. * Fourth compartment: Contains the extensor indicis proprius lying deep to the four tendons of the extensor digitorum communis [38]. * Fifth compartment: Contains the extensor digiti quinti [38]. * Sixth compartment: Contains the extensor carpi ulnaris tendon, which inserts at the base of the little finger metacarpal [38].
The sagittal band fibers insert onto the volar proximal phalanx and onto the lateral borders of the volar plate [38]. Rupture or attenuation of the sagittal band fibers allows the extrinsic extensor tendon to sublux to the ulnar side of the metacarpal head, causing ulnar deviation of the finger [38]. The flexor digitorum profundus inserts on the proximal volar aspect of the distal phalanx [38]. The flexor digitorum superficialis acts as a flexor of the proximal interphalangeal and metacarpophalangeal joints [38].
There are seven interosseous muscles in the hand, consisting of four dorsal and three volar muscles [81]. The dorsal interossei are abductors, while the volar interossei are adductors [81]. The middle finger has two dorsal interossei and no volar interossei because the central axis of the hand lies within it [81]. The deep head of each dorsal interosseous muscle forms a lateral tendon, or lateral band, at the level of the MP joint [81]. The volar interossei form the ulnar lateral band of the index finger and the radial lateral band of the ring and little fingers [81]. The abductor digiti quinti inserts onto the ulnar lateral tubercle at the base of the proximal phalanx of the little finger [81]. The opponens digiti quinti arises from the pisohamate ligament and the hook of the hamate and inserts onto the ulnar side of the diaphysis of the fifth metacarpal [81].
The metacarpal arch is endowed with adaptability due to the mobility of the peripheral metacarpals [84]. The index metacarpal is the most firmly fixed, while the fifth metacarpal is semi-independent with a range of flexion–extension of approximately 20 degrees [84]. The second to fifth metacarpals are bound together by the deep transverse intermetacarpal ligament, also known as the interglenoid ligament [84]. The metacarpophalangeal articulations are the keystones of the longitudinal arches of the hand [84]. The volar plates prevent hyperextension at the metacarpophalangeal joints [84].
The superficial palmar fascia covers a triangular area of the central palm, with the proximal corner facing directly proximal [91]. The palmaris longus tendon terminates in continuity with the fibers of the proximal corner of the superficial palmar fascia when present [91]. Fibers dorsal to the digital neurovascular bundle are collectively called Cleland ligament, and those palmar to the bundle are called Grayson ligament [91]. The dorsal skin of the hand is thin, possesses a normal pilosebaceous system, and has loose connections with deeper planes allowing free gliding [90]. Flexion of the fingers produces a significant lengthening of the dorsal skin, with an average increase of 3 cm in the middle finger from extension to full flexion [90]. The dorsal and palmar areas of skin are independent due to a system of adhesions that anchors their common boundary to the underlying plane [90].
The "princeps pollicis" artery is the terminal branch of the radial artery that crosses the first intermetacarpal space and runs along the ulnar side of the first metacarpal bone [85]. The princeps pollicis divides into two terminal rami, the collateral palmar arteries of the thumb, at the level of the cutaneous flexion crease of the metacarpophalangeal joint [85]. An arcade located deep in the flexor tendon joins together the two palmar arteries of the thumb at the level of the distal metaphysis of the first phalanx [85]. The dorsal arteries of the thumb originate from palmar arteries at the level of the first metacarpal and head distally on the side of the two distal phalanges [85].
The patterns of peri-articular finger injuries differ greatly between the three finger joints due to the mechanism of falling and local biomechanical forces [94]. The dorsoradial ligament is the primary restraining force with respect to acute dorsal dislocation of the thumb carpometacarpal joint [124]. The anatomic basis for complete, irreducible dislocation of the MP joint involves the volar plate, the A1 pulley, the flexor tendons, the lumbricals, and, in the small finger, the abductor and flexor digiti quinti [148]. In a complete dorsal MP dislocation, a tendon noose forms around the metacarpal head as periarticular tendons are drawn dorsally past the metacarpal head [148]. In the index finger, the entrapping structures for a complete dorsal MP dislocation include the lumbrical muscle radially and the flexor tendons ulnarly [148]. In the small finger, the entrapping structures for a complete dorsal MP dislocation include the common tendon of the abductor digiti quinti and the flexor digiti minimi ulnarly and the lumbrical muscle and flexor tendons radially [148]. Subluxation (simple) dislocations are reducible by closed means, whereas complete (complex) dislocations are not [148]. An incomplete or simple dislocation can be converted into a complete or complex dislocation by an inappropriate attempt to reduce the finger by exaggerating the hyperextension deformity [148].
The salient pathologic feature precluding successful closed reduction of a chronic, complex volar MP dislocation may be interposition of the dorsal capsule within the joint [132]. The mechanism of injury for a chronic, complex volar MP dislocation is a hyperflexion, proximal translational force applied to the proximal phalanx [132]. Palmar dislocation of the metacarpophalangeal joint is a rare injury with uncertain pathogenesis [187]. Wood and Dobyns concluded that avulsion of the dorsal capsule from the metacarpal neck and its interposition into the metacarpophalangeal joint are essential pathologic processes in palmar dislocation [187]. Renshaw and Louis stated that the mechanism of injury for palmar dislocation is forceful hyperextension of the metacarpophalangeal joint, followed by distal attachment avulsion of the palmar plate which is subsequently entrapped in the joint [187]. Betz et al. suggested that a combination of active flexion and forceful hyperextension is important in producing a palmar dislocation [187]. Rotatory force is thought to be responsible for the ruptures of the collateral ligaments that occur in palmar dislocations [187].
In palmar dislocation of the proximal interphalangeal joint, the opposite collateral ligament remains intact and acts as a pin axis about which the joint rotates as it subluxates anteriorly [192]. In palmar dislocation of the proximal interphalangeal joint, collateral ligament tears are complete in all but patients with intraarticular fractures where a few palmar fibers remain intact [192]. The ends of the torn collateral ligament in palmar PIP dislocation are always found deep to the subluxated lateral band and thickened transverse retinacular ligament [192].
Classification
Glenohumeral Joint
Clinical cases of glenohumeral instability are characterized according to the circumstances under which they occur, the degree of instability, and the direction of instability [8]. Instability is classified as acute if seen within the first days after its onset, and chronic otherwise [8]. Instability is classified as recurrent if a glenohumeral joint has been dislocated on many occasions [8]. Instability arising from a traumatic episode involves injury to the bone, rotator cuff, labrum, capsule, or a combination of ligaments [8]. Patients with a traumatic etiology usually have unidirectional instability and often have obvious pathology such as a Bankart lesion [8]. Posterior dislocations represent 90% of all hip dislocations [78].
Acromioclavicular Joint
Rockwood type VI acromioclavicular joint dislocations are exceedingly rare, with only 24 cases reported to date [24].
Sternoclavicular Joint
The Allman clinical classification for sternoclavicular dislocation is a tool for treatment choice in addition to the direction of dislocation [54]. Allman Stage 1: corresponds to a contusion or minor distortion with a stable joint and no radiological signs of lesions [54]. Allman Stage 2: is a subluxation of the joint due to partial rupture of the sternoclavicular ligaments, whereas the costoclavicular ligament remains intact [54]. Allman Stage 3: is a dislocation of the joint with a complete rupture of all ligaments and the articular disk [54].
Metacarpophalangeal Joint
Traumatic dislocation of the metacarpophalangeal joint may be simple (easily reducible) or complex (requiring surgical intervention) [22]. Palmar dislocation of the thumb metacarpophalangeal joint is classified into Type A (stable joint), Type B (tendon block), and Type C (joint instability) [105].
Proximal Interphalangeal Joint
Fracture-dislocations of the proximal interphalangeal joint encompass a spectrum of injury severity, ranging from injuries that require little intervention to those that require advanced reconstructive surgery for optimal outcome [119]. Understanding the fracture within the context of a stability-based classification system helps to guide the selection of the most appropriate treatment for proximal interphalangeal joint fracture-dislocations [99]. The use of injury classification on the basis of deforming forces helps in directing rational rehabilitation therapy for proximal interphalangeal joint fractures and dislocations [107].
Tarsometatarsal Joint
The Quénu and Küss classification describes three types of Lisfranc injury patterns: homolateral, isolated, and divergent [180]. The Hardcastle classification distinguishes three main groups of Lisfranc fracture-dislocations: complete, partial, and divergent dislocation patterns [180]. Type A (complete): characterized by the involvement of all parts of the Lisfranc joint complex with dislocation within one plane [180]. Type B (partial): identified by partial incongruity of the joint complex [180]. In Type B Lisfranc fracture-dislocations, a medial dislocation pattern involves the first metatarsal or a variable number of metatarsals excluding the fifth [180]. In Type B Lisfranc fracture-dislocations, a lateral dislocation pattern involves one or more of the lateral metatarsals while the first ray remains stable and intact [180]. Type C (divergent): shows medialization of the first metatarsal in conjunction with lateral translation of a variable number of the lateral four metatarsal bones [180].
Clinical Presentation
General Principles and Diagnostic Challenges
Accurate diagnosis and management of hand and carpal fractures and dislocations are predicated on a thorough physical examination and appropriate imaging to limit joint stiffness while preserving mobility and function [27]. Foot fractures and dislocations are common traumatic injuries associated with high rates of morbidity and dysfunction, requiring an understanding of classifications and management to ensure anatomic alignment and functional recovery [52]. Clinicians and radiologists agreed on the presence or absence of fracture or dislocation in 897 of 1011 cases (89 per cent) [6].
Carpometacarpal joint dislocations and fracture dislocations are uncommon injuries that can be very disabling if not recognized early [43]. The diagnosis of carpometacarpal dislocations must be considered even though they are rare, and standard radiographs should be supplemented with three-quarter and strict profile views [45]. Palmar metacarpophalangeal dislocation is an infrequent injury where delay in diagnosis is a common feature because of its rarity and the lack of obvious X-ray changes [47]. Palmar dislocation of the 5th CMCJ is a rare injury and should be recognised early [50]. Anterior dislocations of the second and third carpometacarpal joints are extremely rare [51]. Perilunate dislocation is a rare and often underdiagnosed wrist lesion, typically occurring in young males after violent trauma [42].
Clinical results for PIP joint dislocations and fracture-dislocations vary and are often difficult to predict due to the complexity of fracture patterns and potential for sub-acute or chronic presentation [18]. Early recognition and treatment are important for good outcomes, with reduction of the joint without subluxation being more important than anatomic reduction of fracture fragments [49]. Timely treatment of complex fracture-dislocations ensures optimal outcome in range of motion and overall hand function [25]. Early diagnosis and treatment provide satisfactory functional results for volar dislocation of the ring finger MCP joint [53]. If the diagnosis of an ulnar CMC joint dislocation or fracture–dislocation is early accomplished and a concentric and stable reduction is initially achieved, the nonoperative treatment may be a successful option to take into account but requiring a close follow-up for the first week [32]. In patients with delayed presentation of CMC fracture dislocations, we recommend ORIF [55]. There is a risk of persistent subluxation or dislocation, particularly if treatment is delayed [2].
Shoulder Dislocations
Glenohumeral instability is an inability of the humeral head to remain centered in the glenoid fossa [8]. Glenohumeral instability is not the same as laxity, which is a physical finding often unassociated with clinical instability [8]. Clinical cases of glenohumeral instability can be characterized according to the circumstances under which they occur, the degree of instability, and the direction of instability [8]. Congenital instability may result from local anomalies such as glenoid dysplasia or from systemic conditions such as Ehlers-Danlos syndrome [8]. Instability is acute if seen within the first days after its onset; otherwise it is chronic [8]. A dislocation is locked (or fixed) if the humeral head has been impaled on the edge of the glenoid, thus making reduction of the dislocation difficult [8]. If a glenohumeral joint has been dislocated on many occasions, the instability is recurrent [8]. Instability can arise from a traumatic episode in which an injury occurs to the bone, rotator cuff, labrum, capsule, or a combination of ligaments [8]. Patients with a traumatic etiology usually have unidirectional instability, often have obvious pathology such as a Bankart lesion [8].
The group aged 15 to 19 years was at the highest risk of recurrent dislocation and instability [1]. Almost half of all first-time dislocations at the age of <25 years will have stabilising surgery and two-thirds will develop different stages of arthropathy within 25 years [13]. The systematic review found that the available literature supports surgical intervention in patients under the age of 25 to reduce re-dislocation [7]. Early intervention and low pain levels at presentation were the two most important factors that significantly favor successful reduction of a shoulder dislocation [20]. When patients were treated with an open or arthroscopic procedure, recurrence was low, with none reporting recurrent dislocation in limited follow-up [5].
Locked shoulder dislocations, either anterior or posterior, are very rare [33]. Locked shoulder dislocations are always the source of classification, diagnosis and treatment challenges [33]. The diagnosis of locked shoulder dislocations can be missed, even for anterior dislocations, despite notable clinical and radiographic evidence [33]. The initial dislocation is missed in 60% of cases for locked posterior dislocations, despite injury circumstances that are often highly suggestive [33]. Posterior dislocations and fracture-dislocations are difficult to diagnose with a standard AP radiograph and are frequently missed or misdiagnosed during initial treatment [40]. Bilateral posterior dislocation of the shoulder is exceedingly rare [44]. Posterior shoulder dislocations are rare in the pediatric population and require a high level of suspicion for diagnosis [46]. Positioning the shoulder in abduction and external rotation helps maintain reduction, and serial radiographs may be beneficial to monitor for sequelae in pediatric posterior shoulder dislocation [46]. The most common treatment for a shoulder dislocation in paediatric patients is a closed shoulder reduction [30]. Females and children were significantly more likely to present with a dislocation by sustaining player contact [95].
In specific situations, additional diagnostic studies may be indicated when clinical findings suggest a neurologic injury [29]. Electrodiagnostic studies and nerve conduction velocity studies should be obtained when clinical findings suggest a neurologic injury [29]. Electrodiagnostic studies and nerve conduction velocity studies will be positive within 3 to 4 weeks following the injury [29]. Although the presence of a neurologic deficit likely will not alter the approach to management, it is important to document the deficit before surgical intervention so that the deficit cannot be construed as a result of the procedure performed [29]. Vascular compromise associated with shoulder dislocation is very uncommon, but when it is suspected, evaluation by a vascular specialist is important to determine whether additional angiographic imaging studies are indicated [29].
Chronic glenohumeral dislocations are challenging problems for orthopedic surgeons [59]. In most situations, pain and limited shoulder range of motion (ROM) lead patients to seek medical evaluation for chronic glenohumeral dislocations [59]. Even with a presentation of pain and limited ROM, the injury can be overlooked by the treating physician unless a careful and systematic history, physical examination, and radiographic evaluation are performed [59]. The strongest patient-related factors associated with dislocation after reverse shoulder arthroplasty were a history of postoperative subluxations and having a primary diagnosis of fracture nonunion [23].
Other Joint Dislocations
Complete anterior dislocation of the sacro-iliac joint is a very unusual injury that can occur in skeletally mature individuals following severe trauma [21]. Traumatic dislocation of the metacarpophalangeal joint is a relatively uncommon injury that may be simple (easily reducible) or complex (requiring surgical intervention) [22]. RW type VI AC dislocations remain exceedingly rare, with only 24 cases reported to date [24]. Congenital patellar dislocation is a condition that requires surgical intervention [97].
Different classifications can be used to describe a sternoclavicular dislocation, one based on the anatomic position of the dislocation and the other on the etiology of the lesion [54]. A clinical classification was published by Allman and seems to be a good tool for the treatment choice in addition to the direction of dislocation [54]. Stage 1 sternoclavicular dislocation corresponds to a contusion or minor distortion with a stable joint and no radiological signs of lesions [54]. Stage 2 sternoclavicular dislocation is a subluxation of the joint due to partial rupture of the sternoclavicular ligaments, whereas the costoclavicular ligament remains intact [54]. Stage 3 sternoclavicular dislocation is a dislocation of the joint with a complete rupture of all ligaments and the articular disk [54]. There has been no re-dislocation on the right elbow, five years postsurgery, in a patient with bilateral elbow dislocation and Rubinstein-Taybi syndrome [28].
Investigations
General Principles: A careful physical examination is essential to direct care and future testing if indicated, as diagnostic tests such as imaging and serum laboratory studies can be expensive, time consuming, and often nonspecific [37]. Machine learning–aided diagnosis may help to decrease misdiagnosis of perilunate dislocations, particularly when subspecialist evaluation is delayed [191].
Plain Radiography: Standard radiographs for carpometacarpal dislocations should be supplemented with three-quarter and strict profile views [45]. In pediatric posterior shoulder dislocation, serial radiographs may be beneficial to monitor for sequelae [46]. After healing of acute trapeziometacarpal joint dislocation, joint stability is confirmed by obtaining stress radiographs to identify whether joint subluxation is present before degenerative changes occur [190]. CMC joint fracture dislocation of all fingers requires thorough clinical examination and radiological assessment [181]. The importance of recognizing the injury mechanism is highlighted to guide radiographic assessment for volar dislocation of the second and third carpometacarpal joints [174].
MRI: An increased glenoid index on MRI may help identify patients at risk for primary or recurrent anterior glenohumeral instability events [175].
Other Considerations: Perilunate dislocation is a rare and often underdiagnosed wrist lesion [42]. Knowledge of the injury and correct imaging evaluation could avoid late diagnosis of palmar trapezoid dislocation [189]. The CMC joint dislocation was missed in the initial limited radiological investigation of the thumb when attention was directed to an obvious open IP joint dislocation [186]. Diagnosing the cause of ulnar collateral ligament locking may be complicated by the lack of evidence in imaging studies [185].
Treatment
Non-Operative
Historic physicians established the foundation for modern conservative management of shoulder dislocations [9]. For acute initial anterior shoulder dislocations, nonoperative treatment involves a supervised rehabilitation program using a sling for comfort for three weeks, followed by restrengthening exercises emphasizing internal rotation and adduction muscles [116]. All conservatively treated patients with primary traumatic anterior shoulder dislocations received a sling for a few days and instructions for muscular rehabilitation [170]. In pediatric patients, the absence of Hill-Sachs and Bankart lesions suggests conservative treatment is a viable option [152]. Most simple elbow dislocations are managed nonoperatively with closed manipulative reduction and early rehabilitation, yielding good functional outcomes, though residual stiffness, pain, or instability may persist [142]. For hand and wrist injuries, closed reduction is the treatment of choice for simultaneous dislocations without associated lesions [3]. Most metacarpal fractures and dislocations in children have a favorable evolution, with only 20% requiring reduction and surgical stabilization being rare [4]. Closed reduction has successfully managed divergent double dislocations involving dorsal distal interphalangeal joint dislocation and volar metacarpophalangeal joint dislocation [10]. When a trans-scaphoid perilunate dislocation is diagnosed late, enduring functional results may be achieved with nonoperative treatment [26]. Superior dislocation of the sternoclavicular joint can be treated nonoperatively [63]. While closed management and immobilization can be considered if recognized early, surgical reduction and stabilization are more commonly warranted for lesser digit carpometacarpal joint fracture-dislocations [149]. Conservative treatment through immediate reduction and splint immobilization can be sufficient for acute, uncomplicated ulnar carpometacarpal dislocations, although instability may persist after three weeks in some cases [163]. Management of habitual thumb metacarpophalangeal joint dislocation in children should be conservative, resisting surgical tightening and encouraging the child to unlearn the habit [164]. Many acute hand and wrist injuries can be managed nonsurgically with extension splints, while optimal management of subacute or chronic injuries remains undefined [136].
Operative
Indications: Surgical treatment is more effective than conservative options in preventing recurrent instability in adolescents and young adults under 40 years of age with first-time anterior shoulder dislocation [101]. For chronic glenohumeral dislocations, optimal management is not clearly defined, but consensus exists on general guidelines [59]. Surgery is indicated in the acute setting for physically active patients with knee dislocations and in the chronic setting for instability without significant arthrosis [117]. Restoring the anatomy and biomechanics of the trapeziometacarpal joint is essential, making surgical treatment usually indicated for these injuries [16]. Current evidence suggests operative treatment of Rockwood grade III dislocations results in better cosmetic and radiological results, similar functional outcomes, and longer time off work compared to non-operative treatment [131].
Surgical Approach / Technique: A wide variety of management options are available for chronic glenohumeral dislocations, including closed reduction, open reduction with tendon and bone transfers, allograft procedures, and prosthetic arthroplasty [59]. Supervised self-reduction and physician-assisted techniques serve as effective first-line treatments for anterior shoulder dislocation, potentially reducing the need for analgesics and emergency room visits [130]. The modified McLaughlin procedure is a reliable option for treating acute locked posterior shoulder dislocation with a head defect of 25–45% [68]. Open reduction and internal fixation is indicated for fracture-dislocations of the hamatometacarpal joint when a large dislocated fragment is present or ligamental interposition is suspected [62]. Open reduction is necessary when closed reduction fails to reduce dorsal dislocation of the distal interphalangeal joint with fracture of the volar base [69]. Suture-button stabilisation offers a less-invasive alternative to traditional methods for thumb carpometacarpal joint instability and dislocation, with favourable outcomes in both chronic instability and acute traumatic dislocation [15]. Surgical treatment using a suture button implant for delayed ulnar carpometacarpal fracture–dislocations allows early motion from two weeks post-surgery, resulting in good motion and increased hand grip [74]. Delayed treatment of unstable proximal interphalangeal joint fracture-dislocations with a DDEF is effective in restoring function [111]. Despite relatively high surgical complication rates, operative management of carpometacarpal fracture dislocations results in good-to-excellent functional outcomes [34].
Pain Management: Surgeons and patients should try to avoid opioids if possible after nonoperatively treated fractures and dislocations [137].
Other Considerations: In specific situations, additional diagnostic studies such as electrodiagnostic studies and nerve conduction velocity studies should be obtained when clinical findings suggest neurologic injury [29]. The position of external rotation immobilization does not offer any obvious clinical advantage over internal rotation in a traditional sling for younger patients with first-time shoulder dislocation and cannot be recommended [118, 122]. The current best evidence does not support the relative effectiveness of immobilization in external rotation compared with internal rotation to avoid recurrent shoulder dislocations [118]. In a practical context, using any sling for three to four weeks is challenging for younger patients, who often feel better after one week [122]. External rotation braces are bulky, difficult to manage in daily life, and associated with poor compliance in younger age groups [122]. Evaluation of the entire patient is essential when managing hip dislocations due to the high incidence of associated injuries; clinicians must consider the mechanism, anatomic predispositions to instability, and associated injuries that affect the treatment plan [77]. Orthopaedic trauma management of knee dislocations is a complex, multifactorial treatment dilemma [161]. A stable although limited arc of motion is present after reduction of most articular and many nonarticular fractures and dislocations [147]. This review underscores the need for additional research and education to establish standardized protocols and evidence-based practices for perilunate dislocations [19]. A retrospective evaluation of 21 patients treated between January 2012 and January 2018 for chronic acromioclavicular joint dislocation included patients with chronic injury (more than 6 weeks from injury), primary treatment failure (pain and/or instability 6 weeks after injury, or initial surgery), closed physis, unilateral injury, written consent, and minimum 1 year of follow-up [177].
Complications
Shoulder Dislocations
Instability and Recurrence: Patients aged 15 to 19 years face the highest risk of recurrent dislocation and instability following glenohumeral dislocation [1]. Surgical intervention in patients under 25 is supported by literature to reduce re-dislocation after first-time traumatic anterior shoulder dislocation [7], with almost half of all first-time dislocations in this age group undergoing stabilising surgery [13]. Recurrent instability requiring capsular reconstruction appears more prevalent in patients with a history of shoulder dislocation following luxatio erecta [17]. For reverse shoulder arthroplasty, the strongest patient-related factors associated with dislocation are a history of postoperative subluxations and a primary diagnosis of fracture nonunion [23].
Arthropathy: Two-thirds of patients with first-time dislocations at age <25 years develop different stages of arthropathy within 25 years [13]. Age at primary dislocation, recurrence, high-energy sports, and alcohol abuse are factors associated with the development of arthropathy after primary anterior shoulder dislocation [176]. The choice of open reduction and stabilization technique for chronic anterior dislocation is highly variable, leading to wide variation in reported outcomes and a high number of complications such as resubluxation and early arthrosis [14].
Neurologic and Vascular Injury: Vascular compromise associated with shoulder dislocation is very uncommon [29]. When clinical findings suggest a neurologic injury, electrodiagnostic studies and nerve conduction velocity studies should be obtained [29]; these studies will be positive within 3 to 4 weeks following the injury [29]. It is important to document a neurologic deficit before surgical intervention so that the deficit cannot be construed as a result of the procedure performed [29].
Other Considerations: In patients with locked posterior shoulder dislocation, the duration of the dislocation is the primary factor influencing clinical outcomes, rather than humeral head defect size or patient age [12]. Locked posterior shoulder dislocations are missed in 60% of cases in the acute phase [33]. Non-operated patients with primary anterior shoulder dislocation and self-reported shoulder trouble three-six weeks after initial injury do not have less shoulder impairment than non-operated patients with recurrent anterior shoulder dislocation and self-reported shoulder trouble three-six weeks after their latest shoulder dislocation event [150].
Hand and Wrist Dislocations
Posttraumatic Arthritis: Perilunate dislocations and transscaphoid perilunate fracture dislocations are associated with a high incidence of posttraumatic arthritis [36]. Posttraumatic degenerative changes were observed in 12 of 18 cases of perilunate dislocations and transscaphoid perilunate fracture dislocations at a minimum 10-year follow-up [36]. Signs of posttraumatic arthritis after these injuries increase progressively but are well tolerated at an average follow-up of 13 years [36]. The presence of radiological arthritis and static carpal instability did not cause reduced function at a minimum follow-up of 10 years in patients with perilunate dislocations and transscaphoid perilunate fracture dislocations [36].
Functional Outcomes: Despite relatively high surgical complication rates, operative management of non-thumb carpometacarpal joint fracture dislocations results in good-to-excellent functional outcomes [34].
Other Considerations: Secondary dislocation or pseudarthrosis could not be observed in patients treated with osteosynthesis of traumatic manubriosternal dislocations and sternal fractures using a 3.5/4.0 mm fixed-angle plate [182].
Other Joint Dislocations
Chronic Pain: Long-term outcomes for pelvic ring injuries are complicated by posterior pelvic pain and are largely multifactorial [73].
Recovery
Shoulder Dislocations
Other Considerations: Long-term functional stability varies by injury type and treatment modality. Shoulders treated for bilateral luxatio erecta were stable with no recurrent instability at 3-year follow-up [66]. In young, active patients, acute arthroscopic Bankart repair for first-time traumatic anterior glenohumeral dislocations resulted in excellent subjective function and return to athletics, with an acceptable rate of recurrence and reoperation at long-term follow-up [171]. Conversely, Type I and II acromioclavicular joint disruptions impair long-term shoulder function in about half of patients 10 years after injury [153].
Hand and Wrist Dislocations
Other Considerations: Recovery outcomes for hand and wrist dislocations are generally favorable, though presentation timing and specific joint involvement influence the clinical course. In a series of 80 patients with 81 involved hands, 17.5% (14/80) of patients with carpometacarpal dislocations or fracture-dislocations presented more than 10 days out from injury [35]. Despite the presence of radiological arthritis and static carpal instability, function was not reduced at a minimum follow-up of 10 years after perilunate dislocations and transscaphoid perilunate fracture dislocations [36]. Early diagnosis and treatment provide satisfactory functional results for volar dislocation of the ring finger metacarpophalangeal joint [53].
For extensor tendon dislocations, recurrence is rare. All 16 cases of traumatic and spontaneous dislocation of the extensor tendon of the long finger were followed-up more than 1 year, with no recurrence observed [67]. Similarly, both patients treated nonoperatively for traumatic dislocations of the extensor digitorum tendons achieved normal pain-free function of the involved digit and experienced no episodes of recurrent dislocation [75].
Fracture-dislocations of the proximal interphalangeal joint treated with extension block pinning yield satisfactory long-term outcomes, similar to mid-term follow-up results reported 11 years earlier [76]. This technique produces excellent functional outcomes with minimal long-term disability for unstable dorsal proximal interphalangeal joint fracture-dislocations [173]. Isolated open metacarpophalangeal dislocations, such as of the little finger, can achieve full recovery with painless range of motion and no residual instability, as seen at a 26-month follow-up visit [144].
Complex wrist dislocations also demonstrate good recovery potential. A patient with a combined reverse perilunate and axial–ulnar dislocation of the wrist achieved excellent functional results with no major complications at 1 year follow-up [168]. Follow-up at 32 months for a multidirectional radiocarpal dislocation without fracture showed excellent clinical and radiographic results [169]. Open reduction of simultaneous dislocations of the carpometacarpal and metacarpophalangeal joints of the thumb, with repair of the relevant ligaments and the dorsal capsule of the CMC joint, gives good results even after considerable delay in treatment [193].
Elbow Dislocations
No evidence provided.
Key Evidence
- [L3] The group aged 15 to 19 years was at the highest risk of recurrent dislocation and instability. [1] (10.1016/j.jse.2017.09.006)
- [L4] There is a risk of persistent subluxation or dislocation, particularly if treatment is delayed. [2] (10.1016/j.jhsb.2005.05.006)
- [L4] Closed reduction is the treatment of choice for simultaneous dislocations without associated lesions. [3] (10.1016/j.jhsa.2012.10.043)
- [L5] Most of these fractures and dislocations have a favorable evolution, with only 20% requiring reduction and surgical stabilization being rare. [4] (10.1016/j.main.2013.02.018)
- [L4] When patients were treated with an open or arthroscopic procedure, recurrence was low, with none reporting recurrent dislocation in limited follow-up. [5] (10.1177/23259671221121633)
- [L4] Clinicians and radiologists agreed on the presence or absence of fracture or dislocation in 897 of 1011 cases (89 per cent). [6] (10.1016/s0020-1383(80)80048-9)
- [L1] The systematic review found that the available literature supports surgical intervention in patients under the age of 25 to reduce re-dislocation. [7] (10.1177/17585732241254693)
- [L5] This review demonstrates that historic physicians paved the way for the modern conservative treatment of shoulder dislocations. [9] (10.1177/17585732211058407)
- [Case_report] Closed reduction of this divergent double dislocation was successful. [10] (10.1007/s11552-009-9218-3)
- [L5] We recommend that after surgery immobilization be maintained for 2 weeks, as recommended for other types of MP joint dislocation. [11] (10.1016/s0363-5023(09)91082-6)
- [L4] In patients with locked posterior shoulder dislocation, the primary factor influencing clinical outcomes is the duration of the dislocation, rather than humeral head defect size or patient age. [12] (10.1186/s12891-025-08886-4)
- [L2] Almost half of all first-time dislocations at the age of <25 years will have stabilising surgery and two-thirds will develop different stages of arthropathy within 25 years. [13] (10.1007/s00167-015-3980-2)
- [L4] The choice of open reduction and stabilization technique for chronic anterior dislocation was highly variable and led to a wide variation in reported outcomes with a high number of complications such as resubluxation and early arthrosis. [14] (10.1016/j.jse.2020.10.010)
- [L4] The technique offers a less-invasive alternative to traditional stabilisation methods with favourable outcomes in both chronic instability and acute traumatic dislocation. [15] (10.1177/15589447261469607)
- [L5] Restoring the anatomy and biomechanics of the trapeziometacarpal joint is essential when treating these injuries; for this reason, surgical treatment is usually indicated. [16] (10.1016/j.hansur.2015.12.009)
- [L4] Recurrent instability requiring capsular reconstruction seems to be more prevalent in patients with a previous history of shoulder dislocation. [17] (10.1016/j.jse.2009.07.062)
- [L5] Clinical results for PIP joint dislocations and fracture-dislocations vary and are often difficult to predict due to the complexity of fracture patterns and potential for sub-acute or chronic presentation. [18] (10.1177/17531934231183259)
- [L4] This review outlines the current approaches to the diagnosis and treatment of perilunate dislocations while underscoring the need for additional research and education to establish standardized protocols and evidence-based practices. [19] (10.1016/j.jhsg.2025.100803)
- [L1] Early intervention and low pain levels at presentation were the two most important factors that significantly favor successful reduction of a shoulder dislocation. [20] (10.1016/j.jse.2012.01.004)
- [Case_report] Complete anterior dislocation of the sacro-iliac joint is a very unusual injury that can occur in skeletally mature individuals following severe trauma. [21] (10.2106/00004623-197658010-00028)
- [L5] Traumatic dislocation of the metacarpophalangeal joint is a relatively uncommon injury that may be simple (easily reducible) or complex (requiring surgical intervention). [22] (10.5435/00124635-200905000-00006)
- [L3] The strongest patient-related factors associated with dislocation were a history of postoperative subluxations and having a primary diagnosis of fracture nonunion. [23] (10.1016/j.jse.2023.05.028)
- [L5] RW type VI AC dislocations remain exceedingly rare, with only 24 cases reported to date. [24] (10.1016/j.jisako.2025.101042)
- [L5] Timely treatment of complex fracture-dislocations ensures optimal outcome in range of motion and overall hand function. [25] (10.1016/j.csm.2019.10.006)
- [L4] The authors conclude that when this injury is diagnosed late, an enduring functional result may be achieved by nonoperative treatment. [26] (10.1016/j.jhsa.2007.05.003)
- [Case_report] There has been no re-dislocation on the right elbow, five years postsurgery, and we hope that our experience will help clinicians in the future when treating patients with similar conditions. [28] (10.1016/j.jseint.2023.03.021)
- [L5] [29] (10.5435/00124635-200807000-00004)
- [L3] The most common treatment for a shoulder dislocation in paediatric patients is a closed shoulder reduction. [30] (10.3390/ijerph17082834)
- [L4] If the diagnosis of an ulnar CMC joint dislocation or fracture–dislocation is early accomplished and a concentric and stable reduction is initially achieved, the nonoperative treatment may be a successful option to take into account but requiring a close follow-up for the first week. [32] (10.1055/s-0039-1688468)
- [L4] [33] (10.1016/j.main.2014.12.006)
- [L4] Despite relatively high surgical complication rates, operative management of CMC fracture dislocations results in good-to-excellent functional outcomes. [34] (10.1016/j.jhsg.2024.11.003)
- [L4] [35] (10.1177/1558944719852743)
- [L4] [36] (10.1016/j.jhsa.2009.09.003)
- [L4] Posterior dislocations and fracture-dislocations are difficult to diagnose with a standard AP radiograph and are frequently missed or misdiagnosed during initial treatment. [40] (10.1016/s1058-2746(95)80036-0)
- [L4] Perilunate dislocation is a rare and often underdiagnosed wrist lesion, typically occurring in young males after violent trauma. [42] (10.1016/j.hansur.2017.10.201)
- [L5] Carpometacarpal joint dislocations and fracture dislocations are uncommon injuries that can be very disabling if not recognized early. [43] (10.5435/jaaos-d-25-00583)
- [L5] Bilateral posterior dislocation of the shoulder is exceedingly rare. [44] (10.1016/j.main.2012.01.002)
- [L5] The diagnosis of carpometacarpal dislocations must be considered even though they are rare, and standard radiographs should be supplemented with three-quarter and strict profile views. [45] (10.1016/s1297-3203(01)00065-8)
- [Case_report] Posterior shoulder dislocations are rare in the pediatric population and require a high level of suspicion for diagnosis; positioning the shoulder in abduction and external rotation helps maintain reduction, and serial radiographs may be beneficial to monitor for sequelae. [46] (10.1016/j.xrrt.2020.12.003)
- [L5] Palmar metacarpophalangeal dislocation is an infrequent injury where delay in diagnosis is a common feature because of its rarity and the lack of obvious X-ray changes. [47] (10.1016/s0266-7681(98)80146-0)
- [L4] Associated injuries represent an adverse prognostic factor for subtalar dislocations. [48] (10.1016/j.injury.2024.111474)
- [L4] Early recognition and treatment are important for good outcomes, with reduction of the joint without subluxation being more important than anatomic reduction of fracture fragments. [49] (10.2106/jbjs.rvw.o.00019)
- [L5] Palmar dislocation of the 5th CMCJ is a rare injury and should be recognised early. [50] (10.1142/s242483552072011x)
- [L5] Anterior dislocations of the second and third carpometacarpal joints are extremely rare. [51] (10.1016/j.main.2007.07.005)
- [L5] Early diagnosis and treatment provide satisfactory functional results for volar dislocation of the ring finger MCP joint. [53] (10.1016/j.hansur.2018.05.001)
- [Case_report] [54] (10.1007/s00167-004-0504-x)
- [L4] In patients with delayed presentation of CMC fracture dislocations, we recommend ORIF. [55] (10.1016/j.jhsa.2015.07.017)
- [L4] [56] (10.2106/00004623-195840020-00022)
- [L4] Surgery improves the clinical and radiological outcome in Rockwood type IV dislocations, whereas Rockwood type III dislocations benefit from conservative treatment. [58] (10.1007/s00167-020-06423-5)
- [L4] Outcomes following surgical treatment of the volar fracture subluxation/dislocation are poor, with most patients developing arthritis and some requiring salvage procedures. [61] (10.1016/j.jhsa.2017.03.030)
- [L5] The presence of a large dislocated fragment and the suspicion of ligamental interposition were the indications for an open reduction and internal fixation in this patient. [62] (10.1016/s0363-5023(86)80119-8)
- [L4] Superior dislocation of the SCJ can be treated nonoperatively. [63] (10.1016/j.jse.2007.02.126)
- [L4] The proposed closed reduction manoeuvre is effective for acute Kaplan dislocation and can be performed under local anaesthesia in most cases, reducing the need for surgery. [64] (10.1177/17531934261473762)
- [L5] At 3-year follow-up, the shoulders were stable and revealed no recurrent instability. [66] (10.1067/mse.2001.115987)
- [L4] All 16 cases were followed-up more than 1 year, and no recurrence of the extensor dislocation was observed. [67] (10.1016/0363-5023(90)90025-m)
- [L4] With respect to functional outcome, modified McLaughlin procedure is a reliable option for the treatment of acute locked posterior shoulder dislocation with a head defect of 25–45%. [68] (10.1007/s00167-012-2217-x)
- [L5] In this patient closed reduction had failed to reduce the dislocation and open reduction was necessary. [69] (10.1016/s0020-1383(97)00121-6)
- [L4] Our results are comparable with other techniques used in the management of unstable PIP joint fracture-dislocations. [70] (10.1016/j.jhsa.2007.07.018)
- [L5] Recent studies suggest an operative approach to the first-time anterior dislocation of the shoulder, especially if the patient is young, active, and involved in highly demanding sports. [71] (10.1007/s00167-009-0950-6)
- [L4] This retrospective study suggests that there is no significant difference between the side of shoulder dislocation and hand dominance of patients who sustain shoulder dislocations requiring shoulder stabilization surgery. [72] (10.1016/j.jses.2018.04.001)
- [L4] The surgical treatment using a suture button implant allowed early motion from 2 weeks after surgery, which resulted in good motion of the ulnar CMC joints and increased hand grip. [74] (10.1055/s-0039-1693051)
- [L4] Both patients achieved normal pain-free function of the involved digit and experienced no episodes of recurrent dislocation. [75] (10.1016/s0363-5023(85)80215-x)
- [L4] The long-term outcomes were satisfactory and similar to the mid-term follow-up results of the same patient cohort reported 11 years earlier. [76] (10.1177/17531934221102251)
- [L4] The patterns of peri-articular finger injuries differ greatly between the three finger joints, explained by the mechanism of falling and local biomechanical forces. [94] (10.1177/17531934251381203)
- [L4] Females and children were significantly more likely to present with a dislocation by sustaining player contact. [95] (10.1016/j.jse.2024.07.040)
- [L5] Understanding the fracture within the context of a stability-based classification system helps to guide in the selection of the most appropriate treatment. [99] (10.1053/jssh.2002.33317)
- [L1] Surgical treatments are more effective than conservative options in preventing recurrent instability in adolescents and young adults under 40 years of age with first-time anterior shoulder dislocation. [101] (10.1016/j.arthro.2025.07.044)
- [L4] Palmar dislocation of the thumb metacarpophalangeal joint is classified into three types: Type A (stable joint), Type B (tendon block), and Type C (joint instability). [105] (10.1177/1753193413499291)
- [L5] The use of injury classification on the basis of the deforming forces helps in directing rational rehabilitation therapy. [107] (10.1016/s0894-1130(03)80007-8)
- [Paper] Delayed treatment of unstable PIPJ fracture-dislocations with a DDEF is effective in restoring function to the PIPJ. [111] (10.1016/j.injury.2015.06.027)
- [L3] [116] (10.1177/03635465010290051101)
- [L2] The current best evidence does not support a relative effectiveness of immobilization in external rotation compared with internal rotation to avoid recurrent shoulder dislocations in patients with traumatic anterior shoulder dislocations. [118] (10.1016/j.jse.2013.07.037)
- [L5] Fracture-dislocations of the proximal interphalangeal joint encompass a spectrum of injury severity, ranging from injuries that require little intervention to those that require advanced reconstructive surgery for optimal outcome. [119] (10.5435/jaaos-21-02-88)
- [L1] [122] (10.2106/jbjs.9616.ebo209)
- [L5] The dorsoradial ligament is the primary restraining force with respect to acute dorsal dislocation of the thumb carpometacarpal joint. [124] (10.1016/0363-5023(94)90229-1)
- [L1] These techniques could be used as an effective first-line treatment for anterior shoulder dislocation, potentially reducing the need for analgesics and emergency room visits. [130] (10.1186/s12891-024-07379-0)
- [L2] Current evidence suggests that operative rather than non-operative treatment of Rockwood grade III dislocations results in better cosmetic and radiological results, similar functional outcomes and longer time off work. [131] (10.1302/0301-620x.95b12.31802)
- [L4] [132] (10.1016/s0363-5023(81)80015-9)
- [L5] Many acute injuries can be managed nonsurgically with extension splints, while optimal management of subacute or chronic injuries remains undefined. [136] (10.5435/jaaos-d-13-00203)
- [L4] Surgeons and patients should try to avoid opioids if possible after nonoperatively treated fractures and dislocations. [137] (10.2106/jbjs.17.01475)
- [L5] At a 26-month follow-up visit, the patient had fully recovered, with painless range of motion and no residual instability. [144] (10.1016/j.hansur.2018.06.001)
- [Paper] A stable although limited arc of motion was present after reduction of most articular fractures and dislocations and many nonarticular fractures and dislocations. [147] (10.1016/s0363-5023(83)80247-0)
- [L5] While closed management and immobilization can be considered if the injury is recognized early, surgical reduction and stabilization are more commonly warranted. [149] (10.1016/j.jhsa.2026.02.016)
- [L4] Non-operated patients with primary anterior shoulder dislocation and self-reported shoulder trouble three-six weeks after initial injury do not have less shoulder impairment (self-reportedly or objectively measured) than non-operated patients with recurrent anterior shoulder dislocation and self-reported shoulder trouble three-six weeks after their latest shoulder dislocation event. [150] (10.1186/s12891-019-2444-0)
- [L4] The case reported here was initially treated conservatively, but instability was still present after 3 weeks. [151] (10.1054/jhsb.1999.0334)
- [Case_report] The absence of Hill-Sachs and Bankart lesions in this pediatric patient suggests that conservative treatment is a viable option for managing shoulder dislocation in children. [152] (10.1016/j.xrrt.2024.01.012)
- [L4] Type I and II acromioclavicular joint disruptions impair long-term shoulder function in about half of patients 10 years after injury. [153] (10.1177/0363546508319047)
- [L4] Although operative treatment is recommended in the literature, these cases show that conservative treatment through immediate reduction and splint immobilization can be sufficient for acute, uncomplicated ulnar CMC dislocations. [163] (10.1007/s11552-011-9347-3)
- [L4] Management should be conservative, resisting surgical attempts to tighten the joint, and encouraging children to unlearn the habit. [164] (10.1177/1753193416687915)
- [Case_report] The patient achieved excellent functional results with no major complications at 1 year follow-up. [168] (10.1177/1753193408091348)
- [L5] Follow-up at 32 months showed excellent clinical and radiographic results. [169] (10.1016/0363-5023(92)90328-m)
- [L3] [170] (10.1007/s00167-009-0998-3)
- [L4] At long-term follow-up, acute arthroscopic Bankart repair for first-time traumatic anterior glenohumeral dislocations resulted in excellent subjective function and return to athletics in young, active patients with an acceptable rate of recurrence and reoperation. [171] (10.1177/0363546508328416)
- [L4] It is technically straightforward and cheap, and produces excellent functional outcomes with minimal long-term disability. [173] (10.1177/15589447211066352)
- [L5] The authors present a method of fixation to clarify early assessment and management, highlighting the importance of recognizing the injury mechanism to guide radiographic assessment. [174] (10.1016/j.hansur.2018.06.004)
- [L3] This useful MRI measurement may help identify patients at risk for primary or recurrent anterior glenohumeral instability events and may therefore help with guiding treatment and prevention. [175] (10.1177/2325967120986139)
- [L2] Age at primary dislocation, recurrence, high-energy sports, and alcohol abuse were factors associated with the development of arthropathy. [176] (10.1016/j.jse.2008.11.004)
- [L4] [177] (10.1016/j.jseint.2020.04.014)
- [L5] CMC joint fracture dislocation of all fingers is an extremely rare injury that needs thorough clinical examination and radiological assessment. [181] (10.1142/s0218810417720261)
- [L4] They note that secondary dislocation or pseudarthrosis could not be observed in their patients. [182] (10.1007/s00402-011-1297-2)
- [L4] Although diagnosing the cause of UCL locking may be complicated by the lack of evidence in imaging studies, open surgical treatment has traditionally been the most often used with a high success rate. [185] (10.1016/j.jhsg.2022.08.003)
- [L5] The CMC joint dislocation was missed in the initial limited radiological investigation of the thumb, because attention was directed to the obvious open IP joint dislocation. [186] (10.1016/0266-7681(88)90146-5)
- [L5] [187] (10.1016/j.jhsb.2003.09.009)
- [L5] Knowledge of the injury and the correct imaging evaluation could avoid late diagnosis and allow proper handling and treatment of the patient, which could improve the prognosis. [189] (10.1177/1558944716660555dk)
- [L5] After healing, joint stability is confirmed by obtaining stress radiographs to identify whether joint subluxation is present before degenerative changes occur. [190] (10.1016/s0363-5023(98)80022-1)
- [Paper] This may help to decrease misdiagnosis of perilunate dislocations, particularly when subspecialist evaluation is delayed. [191] (10.1177/15589447241308603)
- [L4] [192] (10.1016/s0363-5023(84)80182-3)
- [L5] This case illustrates that open reduction of these dislocations with repair of the relevant ligaments and the dorsal capsule of the CMC joint gives good results even after considerable delay in treatment. [193] (10.1016/0020-1383(93)90062-b)
See Also
References
[1] Epidemiology of glenohumeral dislocation and subsequent instability in an urban population. Journal of Shoulder and Elbow Surgery. 2018. DOI: 10.1016/j.jse.2017.09.006
[2] Internal Fixation of Unstable Fracture Dislocations of the Proximal Interphalangeal Joint. Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsb.2005.05.006
[3] Simultaneou Triple Dislocation of the Small Finger. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2012.10.043
[4] Traumatismes ostéoarticulaires des métacarpiens chez l’enfant. Chirurgie de la Main. 2013. DOI: 10.1016/j.main.2013.02.018
[5] A Systematic Review of Acute Irreducible Shoulder Dislocations in the 21st Century. Orthopaedic Journal of Sports Medicine. 2022. DOI: 10.1177/23259671221121633
[6] Correlation between clinical and radiological diagnosis for fractures and dislocations in an accident department. Injury. 1980. DOI: 10.1016/s0020-1383(80)80048-9
[7] A systematic review and meta-analysis of operative versus non-operative management for first time traumatic anterior shoulder dislocation in young adults. Shoulder & Elbow. 2024. DOI: 10.1177/17585732241254693
[8] Fractures, Dislocations, and Acquired Problems of the Shoulder in Children. 2016.
[9] History of closed reduction techniques and initial management for shoulder dislocations: From classical antiquity to modern times. Shoulder & Elbow. 2021. DOI: 10.1177/17585732211058407
[10] Dorsal Dislocation of the Distal Interphalangeal Joint and Volar Dislocation of the Metacarpophalangeal Joint in the Same Finger: A Case Report. HAND. 2009. DOI: 10.1007/s11552-009-9218-3
[11] Irreducible open dislocation of the metacarpophalangeal joint of the small finger. The Journal of Hand Surgery. 1992. DOI: 10.1016/s0363-5023(09)91082-6
[12] The duration of dislocation is the most important prognostic factor in chronic locked posterior shoulder dislocations treated with the modified McLaughlin surgical procedure: a multicentre study. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-08886-4
[13] Primary anterior dislocation of the shoulder: long-term prognosis at the age of 40 years or younger. Knee Surgery, Sports Traumatology, Arthroscopy. 2016. DOI: 10.1007/s00167-015-3980-2
[14] Results and complications of head-preserving techniques in chronic neglected shoulder dislocation: a systematic review. Journal of Shoulder and Elbow Surgery. 2021. DOI: 10.1016/j.jse.2020.10.010
[15] Suture-Button Stabilisation for Thumb Carpometacarpal Joint Instability and Dislocation: A Retrospective Case Series. HAND. 2026. DOI: 10.1177/15589447261469607
[16] Recurrent posttraumatic trapeziometacarpal joint dislocation in a child: A case report. Hand Surgery and Rehabilitation. 2016. DOI: 10.1016/j.hansur.2015.12.009
[17] Results of treatment of luxatio erecta (inferior shoulder dislocation). Journal of Shoulder and Elbow Surgery. 2010. DOI: 10.1016/j.jse.2009.07.062
[18] Proximal interphalangeal joint dislocations and fracture-dislocations. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231183259
[19] A Review of Perilunate Wrist Dislocations. Journal of Hand Surgery Global Online. 2025. DOI: 10.1016/j.jhsg.2025.100803
[20] Milch versus Stimson technique for nonsedated reduction of anterior shoulder dislocation: a prospective randomized trial and analysis of factors affecting success. Journal of Shoulder and Elbow Surgery. 2012. DOI: 10.1016/j.jse.2012.01.004
[21] Complete anterior dislocation of the sacro-iliac joint. A case report. The Journal of Bone & Joint Surgery. 1976. DOI: 10.2106/00004623-197658010-00028
[22] Metacarpophalangeal Joint Dislocation. Journal of the American Academy of Orthopaedic Surgeons. 2009. DOI: 10.5435/00124635-200905000-00006
[23] Predictors of dislocations after reverse shoulder arthroplasty: a study by the ASES complications of RSA multicenter research group. Journal of Shoulder and Elbow Surgery. 2024. DOI: 10.1016/j.jse.2023.05.028
[24] Rockwood type VI acromioclavicular joint dislocations: A systematic review. Journal of ISAKOS. 2026. DOI: 10.1016/j.jisako.2025.101042
[25] Management of Finger Joint Dislocation and Fracture-Dislocations in Athletes. Clinics in Sports Medicine. 2020. DOI: 10.1016/j.csm.2019.10.006
[26] Long-Term Follow-Up of an Undiagnosed Trans-Scaphoid Perilunate Dislocation Demonstrating Articular Remodeling and Functional Adaptation. The Journal of Hand Surgery. 2007. DOI: 10.1016/j.jhsa.2007.05.003
[27] Chapter 29 Hand/Carpal Fractures and Dislocations. 2021.
[28] A case of bilateral elbow dislocation in a patient with Rubinstein-Taybi syndrome. JSES International. 2023. DOI: 10.1016/j.jseint.2023.03.021
[29] Chronic Glenohumeral Dislocation. Journal of the American Academy of Orthopaedic Surgeons. 2008. DOI: 10.5435/00124635-200807000-00004
[30] Epidemiology of Paediatric Shoulder Dislocation: A Nationwide Study in Italy from 2001 to 2014. International Journal of Environmental Research and Public Health. 2020. DOI: 10.3390/ijerph17082834
[32] Nonoperative Treatment of Ulnar Carpometacarpal Fracture–Dislocations. Journal of Wrist Surgery. 2019. DOI: 10.1055/s-0039-1688468
[33] Locked posterior dislocation of the shoulder: A report of three cases. Chirurgie de la Main. 2015. DOI: 10.1016/j.main.2014.12.006
[34] Operative Treatment of Non-Thumb Carpometacarpal Joint Fracture Dislocations. Journal of Hand Surgery Global Online. 2025. DOI: 10.1016/j.jhsg.2024.11.003
[35] Carpometacarpal Fracture-Dislocations: A Retrospective Review of Injury Characteristics and Radiographic Outcomes. HAND. 2019. DOI: 10.1177/1558944719852743
[36] Perilunate Dislocations and Transscaphoid Perilunate Fracture–Dislocations: A Retrospective Study With Minimum Ten-Year Follow-Up. The Journal of Hand Surgery. 2010. DOI: 10.1016/j.jhsa.2009.09.003
[37] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[38] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > Image DISORDERS OF THE MUSCULATURE OF THE HAND.
[39] Exam Of The Hand Wrist 2Ed. 1.1 SKELETON OF THE HAND > The osseous skeleton.
[40] Surgical treatment of chronic posterior dislocations and fracture-dislocations. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80036-0
[42] La luxation péri-lunaire du carpe – à propos de 32 cas. Hand Surgery and Rehabilitation. 2017. DOI: 10.1016/j.hansur.2017.10.201
[43] Carpometacarpal Joint Dislocations and Fracture Dislocations of the Index Through Small Digits. Journal of the American Academy of Orthopaedic Surgeons. 2025. DOI: 10.5435/jaaos-d-25-00583
[44] Acute bilateral posterior dislocation of the shoulder: One-stage reconstruction of both humeral heads with cancellous autograft and cartilage preservation. Chirurgie de la Main. 2012. DOI: 10.1016/j.main.2012.01.002
[45] Fracture-luxation carpométacarpienne du deuxième rayon à propos d'un cas et revue de la littérature. Chirurgie de la Main. 2001. DOI: 10.1016/s1297-3203(01)00065-8
[46] Case report: pediatric posterior shoulder dislocation. JSES Reviews, Reports, and Techniques. 2021. DOI: 10.1016/j.xrrt.2020.12.003
[47] Palmar Metacarpophalangeal Joint Dislocation. Journal of Hand Surgery. 1998. DOI: 10.1016/s0266-7681(98)80146-0
[48] Treatment and rehabilitation of subtalar dislocations: A case series and a review of the literature. Injury. 2024. DOI: 10.1016/j.injury.2024.111474
[49] Treatment of Proximal Interphalangeal Joint Fracture-Dislocations. JBJS Reviews. 2015. DOI: 10.2106/jbjs.rvw.o.00019
[50] Palmar Dislocations of the 5th Carpometacarpal Joint: Case Report of a Rare Injury and Review of Published Cases. The Journal of Hand Surgery (Asian-Pacific Volume). 2020. DOI: 10.1142/s242483552072011x
[51] Luxation carpométacarpienne antérieure des deuxième et troisième rayons. Chirurgie de la Main. 2007. DOI: 10.1016/j.main.2007.07.005
[52] Chapter 46 Foot Fractures and Dislocations. 2021.
[53] Volar metacarpophalangeal joint dislocation: A case report. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.05.001
[54] Anterior subluxation after reduction of a posterior traumatic sterno‐clavicular dislocation: a case report and a review of the literature. Knee Surgery, Sports Traumatology, Arthroscopy. 2004. DOI: 10.1007/s00167-004-0504-x
[55] The Effect of Timing on the Treatment and Outcome of Combined Fourth and Fifth Carpometacarpal Fracture Dislocations. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.07.017
[56] Bilateral Recurrent Posterior Dislocation of the Shoulder. The Journal of Bone & Joint Surgery. 1958. DOI: 10.2106/00004623-195840020-00022
[58] Surgery improves the clinical and radiological outcome in Rockwood type IV dislocations, whereas Rockwood type III dislocations benefit from conservative treatment. Knee Surgery, Sports Traumatology, Arthroscopy. 2021. DOI: 10.1007/s00167-020-06423-5
[59] 5. Chronic Glenohumeral Dislocations and Impression Fractures: Evaluation, Imaging, Treatment, and Outcomes. 2003.
[60] Elbow Dislocations and Complex Instability. 2021.
[61] The Central Slip Fracture: Results of Operative Treatment of Volar Fracture Subluxations/Dislocations of the Proximal Interphalangeal Joint. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.03.030
[62] Fracture-dislocation of the hamatometacarpal joint: A case report. The Journal of Hand Surgery. 1986. DOI: 10.1016/s0363-5023(86)80119-8
[63] Superior dislocation of the sternoclavicular joint. Journal of Shoulder and Elbow Surgery. 2008. DOI: 10.1016/j.jse.2007.02.126
[64] Closed reduction technique for complex dorsal metacarpophalangeal dislocation in children. Journal of Hand Surgery (European Volume). 2026. DOI: 10.1177/17531934261473762
[66] Luxatio erecta of bilateral shoulders. Journal of Shoulder and Elbow Surgery. 2001. DOI: 10.1067/mse.2001.115987
[67] Traumatic and spontaneous dislocation of extensor tendon of the long finger. The Journal of Hand Surgery. 1990. DOI: 10.1016/0363-5023(90)90025-m
[68] Excellent results of lesser tuberosity transfer in acute locked posterior shoulder dislocation. Knee Surgery, Sports Traumatology, Arthroscopy. 2012. DOI: 10.1007/s00167-012-2217-x
[69] Dorsal dislocation of the distal interphalangeal joint with fracture of the volar base: an unusual type. Injury. 1997. DOI: 10.1016/s0020-1383(97)00121-6
[70] Use of Dynamic Distraction External Fixation for Unstable Fracture-Dislocations of the Proximal Interphalangeal Joint. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2007.07.018
[71] Primary anterior shoulder dislocation in young athletes: fix them!. Knee Surgery, Sports Traumatology, Arthroscopy. 2009. DOI: 10.1007/s00167-009-0950-6
[72] Hand dominance in traumatic shoulder dislocations. JSES Open Access. 2018. DOI: 10.1016/j.jses.2018.04.001
[73] Chapter 32 Pelvic Fractures: Definitive Treatment and Outcomes. 2021.
[74] Surgical Treatment for Delayed Ulnar Carpometacarpal Fracture–Dislocations. Journal of Wrist Surgery. 2019. DOI: 10.1055/s-0039-1693051
[75] Nonoperative treatment of traumatic dislocations of the extensor digitorum tendons in patients without rheumatoid disorders. The Journal of Hand Surgery. 1985. DOI: 10.1016/s0363-5023(85)80215-x
[76] Long-term outcomes after extension block pinning for fracture-dislocations of the proximal interphalangeal joint. Journal of Hand Surgery (European Volume). 2022. DOI: 10.1177/17531934221102251
[77] Hip Dislocations and Femoral Head Fractures. 2019.
[78] Chapter 98 Hip Dislocations and Femoral Head Fractures. 2019.
[79] Exam Of The Hand Wrist 2Ed. INTRODUCTION.
[81] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[84] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[85] Exam Of The Hand Wrist 2Ed. Techniques of investigation of the arterial supply by J P Melki > Vascularization of the thumb > Palmar aspect.
[90] Exam Of The Hand Wrist 2Ed. The dorsal skin.
[91] Green S Operative Hand Surgery. PERTINENT ANATOMY.
[94] Is there a difference in the types of injuries occurring around each finger joint after a fall?. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934251381203
[95] Sex and age-specific analysis of basketball-related shoulder dislocations in the United States: a national injury data review. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2024.07.040
[97] Chapter 26 Congenital Dislocation of the Knee and Congenital Patellar Dislocations. 2020.
[99] Fracture dislocations of the proximal interphalangeal joint. Journal of the American Society for Surgery of the Hand. 2002. DOI: 10.1053/jssh.2002.33317
[101] Surgical Treatment Is Superior to Conservative Options in Preventing Recurrence of First-Time Anterior Shoulder Dislocation in Adolescents and Adults Under 40 Years of Age: A Systematic Review and Network Meta-analysis. Arthroscopy: The Journal of Arthroscopic & Related Surgery. 2025. DOI: 10.1016/j.arthro.2025.07.044
[105] Palmar dislocation of the thumb metacarpophalangeal joint: report of four cases and a review of the literature. Journal of Hand Surgery (European Volume). 2013. DOI: 10.1177/1753193413499291
[107] Management of proximal interphalangeal joint fractures and dislocations. Journal of Hand Therapy. 2003. DOI: 10.1016/s0894-1130(03)80007-8
[111] Delayed treatment of unstable proximal interphalangeal joint fracture-dislocations with a dynamic external fixator. Injury. 2015. DOI: 10.1016/j.injury.2015.06.027
[116] Prospective Evaluation of Arthroscopic Stabilization of Acute, Initial Anterior Shoulder Dislocations in Young Athletes. The American Journal of Sports Medicine. 2001. DOI: 10.1177/03635465010290051101
[117] Chapter 101 Knee Dislocations and Patellar Fractures. 2019.
[118] Immobilization in internal or external rotation does not change recurrence rates after traumatic anterior shoulder dislocation. Journal of Shoulder and Elbow Surgery. 2014. DOI: 10.1016/j.jse.2013.07.037
[119] Fracture-dislocations of the Proximal Interphalangeal Joint. Journal of the American Academy of Orthopaedic Surgeons. 2013. DOI: 10.5435/jaaos-21-02-88
[122] Immobilization with an External Rotation Brace Was Similar to an Internal Rotation Sling for Shoulder Dislocation. Journal of Bone and Joint Surgery. 2014. DOI: 10.2106/jbjs.9616.ebo209
[124] Acute dislocation of the carpometacarpal joint of the thumb: An anatomic and cadaver study. The Journal of Hand Surgery. 1994. DOI: 10.1016/0363-5023(94)90229-1
[130] Efficacy of supervised self-reduction vs. physician-assisted techniques for anterior shoulder dislocations: a systematic review and meta-analysis. BMC Musculoskeletal Disorders. 2024. DOI: 10.1186/s12891-024-07379-0
[131] Controversies relating to the management of acromioclavicular joint dislocations. The Bone & Joint Journal. 2013. DOI: 10.1302/0301-620x.95b12.31802
[132] Chronic, complex volar dislocation of the metacarpophalangeal joint. The Journal of Hand Surgery. 1981. DOI: 10.1016/s0363-5023(81)80015-9
[136] Closed Sagittal Band Injury of the Metacarpophalangeal Joint. Journal of the American Academy of Orthopaedic Surgeons. 2015. DOI: 10.5435/jaaos-d-13-00203
[137] A Prospective Evaluation of Patient-Reported Opioid Utilization After Nonoperative Treatment of Fractures and Dislocations. Journal of Bone and Joint Surgery. 2018. DOI: 10.2106/jbjs.17.01475
[142] Elbow Dislocations and Terrible Triad Injuries. 2019.
[144] Isolated open metacarpophalangeal dislocation of the little finger. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.06.001
[147] Fractures and dislocations of the wrist and hand, then and now. The Journal of Hand Surgery. 1983. DOI: 10.1016/s0363-5023(83)80247-0
[148] Dislocations and Ligament Injuries of the Digits. 2021.
[149] Current Concepts: Lesser Digit Carpometacarpal Joint Fracture-Dislocations. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2026.02.016
[150] Patients with non-operated traumatic primary or recurrent anterior shoulder dislocation have equally poor self-reported and measured shoulder function: a cross-sectional study. BMC Musculoskeletal Disorders. 2019. DOI: 10.1186/s12891-019-2444-0
[151] Rupture of the Ulnar Collateral Ligament of the Metacarpophalangeal Joint of the Index Finger. Journal of Hand Surgery. 2000. DOI: 10.1054/jhsb.1999.0334
[152] Anterior shoulder dislocation and clavicle fracture in a 6-year-old boy: a case report and literature review. JSES Reviews, Reports, and Techniques. 2024. DOI: 10.1016/j.xrrt.2024.01.012
[153] Long-Term Shoulder Function after Type I and II Acromioclavicular Joint Disruption. The American Journal of Sports Medicine. 2008. DOI: 10.1177/0363546508319047
[161] Chapter 40 Knee Dislocations. 2021.
[163] Acute Ulnar Carpometacarpal Dislocations. Can it be Treated Conservatively? A Review of Four Cases. HAND. 2011. DOI: 10.1007/s11552-011-9347-3
[164] Habitual dislocation of the thumb metacarpophalangeal joint in children. Journal of Hand Surgery (European Volume). 2017. DOI: 10.1177/1753193416687915
[168] Combined Reverse Perilunate and Axial–Ulnar Dislocation of the Wrist: A Case Report. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193408091348
[169] Multidirectional radiocarpal dislocation without fracture: A case report. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90328-m
[170] Bony Bankart is a positive predictive factor after primary shoulder dislocation. Knee Surgery, Sports Traumatology, Arthroscopy. 2009. DOI: 10.1007/s00167-009-0998-3
[171] Long-term Follow-up of Acute Arthroscopic Bankart Repair for Initial Anterior Shoulder Dislocations in Young Athletes. The American Journal of Sports Medicine. 2009. DOI: 10.1177/0363546508328416
[173] Extension-Block Pinning for Unstable Dorsal Proximal Interphalangeal Joint Fracture-Dislocations: A Simple, Percutaneous Technique With Reproducible Outcomes. HAND. 2022. DOI: 10.1177/15589447211066352
[174] Volar dislocation of the second and third carpometacarpal joints – the Lisfranc injury of the hand?. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.06.004
[175] Increased Glenoid Index as a Risk Factor for Pediatric and Adolescent Anterior Glenohumeral Dislocation: An MRI-Based, Case-Control Study. Orthopaedic Journal of Sports Medicine. 2021. DOI: 10.1177/2325967120986139
[176] Neer Award 2008: Arthropathy after primary anterior shoulder dislocation–223 shoulders prospectively followed up for twenty-five years. Journal of Shoulder and Elbow Surgery. 2009. DOI: 10.1016/j.jse.2008.11.004
[177] Chronic acromioclavicular dislocations: multidirectional stabilization without grafting. JSES International. 2020. DOI: 10.1016/j.jseint.2020.04.014
[180] Fractures and Dislocations of the Midfoot and Forefoot. 2019.
[181] Multiple Carpometacarpal Dislocations of the Hand – An Uncommon Variant: A Rare Case. The Journal of Hand Surgery (Asian-Pacific Volume). 2017. DOI: 10.1142/s0218810417720261
[182] Osteosynthesis of traumatic manubriosternal dislocations and sternal fractures with a 3.5/4.0 mm fixed-angle plate (LCP). Archives of Orthopaedic and Trauma Surgery. 2011. DOI: 10.1007/s00402-011-1297-2
[185] Middle Finger Metacarpophalangeal Joint Locked in Flexion Caused by Entrapped Ulnar Collateral Ligament. Journal of Hand Surgery Global Online. 2022. DOI: 10.1016/j.jhsg.2022.08.003
[186] Simultaneous dislocations of the, interphalangeal and carpometacarpal joints of the thumb : A case report. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90146-5
[187] Palmar Dislocation of the Metacarpophalangeal Joint of the Finger. Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsb.2003.09.009
[189] Palmar Dislocation of the Trapezoid. HAND. 2016. DOI: 10.1177/1558944716660555dk
[190] Acute dislocation of the trapeziometacarpal joint in a child. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80022-1
[191] Machine Learning–Aided Diagnosis Enhances Human Detection of Perilunate Dislocations. HAND. 2025. DOI: 10.1177/15589447241308603
[192] Palmar dislocation of the proximal interphalangeal joint. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80182-3
[193] Simultaneous dislocations of the carpometacarpal and metacarpophalangeal joints of the thumb. Injury. 1993. DOI: 10.1016/0020-1383(93)90062-b