Clinicians › General-Health
Braces, Splints and Supports
When braces, splints and supports help upper-limb conditions, the main types, how to use them, and what the evidence shows for sprains, tendon problems, arthritis and after surgery.
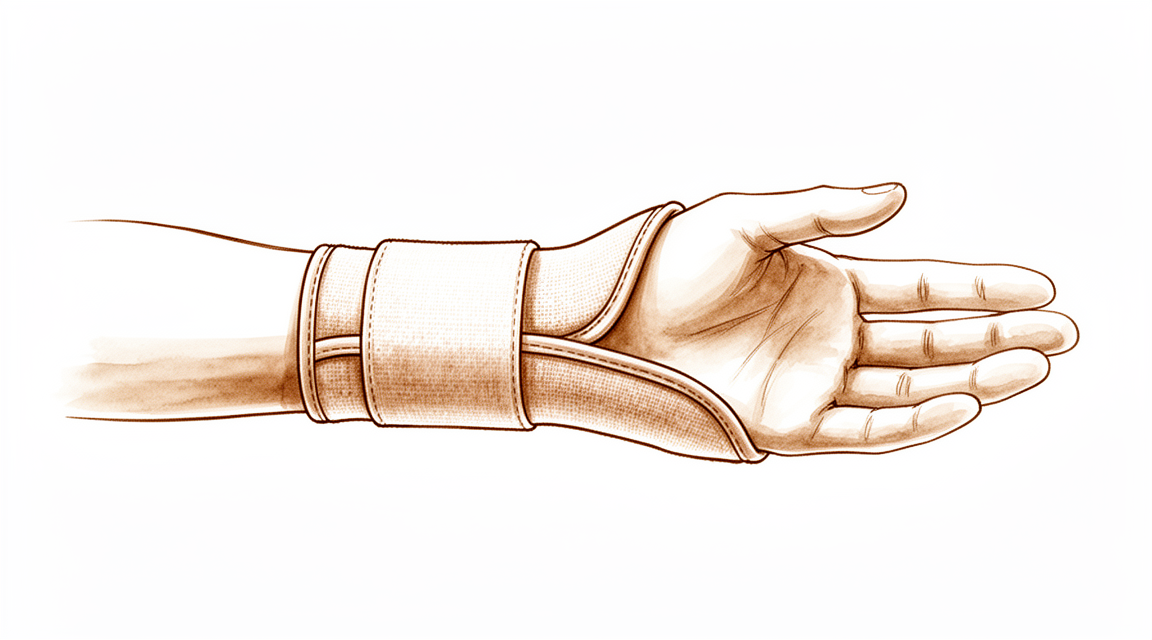
For patients: a plain-language version of this topic is available. See the patient guide.
Overview
Splinting for hand and upper extremity pathology is established as definitive standard practice in rehabilitation [4]. While the selection of appropriate splints for managing joint stiffness has historically been empirical [42], the field is actively advancing toward an evidence-based approach [3]. Design considerations play a more significant role in dynamic extensor splinting than previously expected [1], and force analysis clearly indicates the theoretical advantages and disadvantages of dynamic versus static designs [22]. Many splints can be constructed with inexpensive, available, and often discarded materials [10], though Plaster of Paris splints have the specific drawback that any required changes necessitate the fabrication of a whole new splint [40].
Clinical outcomes vary by device and indication. The Swing Design Dynamic Traction Splint offers similar benefits to previously reported splints while remaining simple and compact [2]. The clamshell splint with otoform lining has proven equally effective for other conditions requiring immobilization [5]. In metacarpal fracture management, a prospective study found that only 41% of patients in the metacarpal-brace group completed treatment compared to 81% in the plaster-cast group, with 60% of exclusions in the brace group due to complications [25]. Conversely, a modified Kleinert splint for digital flexor tendon mobilisation is easy to make, requires virtually no maintenance, and appears to be producing improved results with gaining widespread acceptance [9, 11].
Specific orthotic applications address distinct mechanical needs. A straight spring orthosis for proximal interphalangeal joint extension mobilization is effective for tissue deformation, cost-effective, low profile, and easy for patients to handle [35]. An ulnar boost splint for midcarpal instability follows recommendations to support the pisotriquetral area [64]. However, a volar splint has clear limitations regarding immobilization [63], and dynamic flexion splinting for the distal interphalangeal joint is contraindicated when the proximal interphalangeal joint must be held in full extension [34]. For nerve injuries, the optimal orthosis for complete median and radial nerve-injured war casualties has not been previously described [7], and in a single-subject experiment on radial nerve palsy, only splint 3 met criteria for improving function and patient compliance [6]. The conclusion that sling immobilization is 'not inferior' to brace immobilization after arthroscopic rotator cuff repair cannot be attributed solely to the type of immobilization [8].
How It Works
Biomechanics and Design Principles
The application of splints for treating hand and upper extremity problems is accepted as definitive standard practice in rehabilitation [4]. Splint design must be based on mechanical fact rather than on mode-of-the-day bias [23]. Force analysis clearly indicates the theoretical advantages and disadvantages of dynamic and static splint designs [22]. The sustained positioning of joints and soft tissue with plaster of Paris provides a gentler and more precise means of tissue remodeling than does dynamic or static progressive splinting [27]. During the early phase, braces provide support to inflamed tissues without complete immobilization, facilitating healing [21].
Specific Splint Mechanisms and Outcomes
Radial Nerve Palsy: In a single-subject experiment, only splint 3 met the criteria of improving function and being worn by the patient [6]. Kleinert Splints: A modified Kleinert splint is easy to make and requires virtually no maintenance due to its simplicity [9]. This modified design appears to be producing improved results and is gaining more widespread acceptance [11]. The modified Kleinert controlled mobilization splint has theoretical advantages over the usual Kleinert splint [43]. Buddy Splints: A newly developed buddy splint corrects the mechanical and kinesiologic disadvantages of current buddy strapping systems [26]. Static Splinting: A static gutter splint may be worn at night to maintain gains achieved in the day for distal interphalangeal joint flexion contractures [20]. The objective of providing reduction and stability to the thumb metacarpophalangeal joint and improving function was achieved with a three-point static splint [28]. Similarly, the objective of providing reduction and stability to the MP joint and improving function was achieved with an ambulatory arm elevator sling [29]. Protective and Deformity Management: A silicone splint has value as both a protective splint following injury and prophylactically for diving injuries of the thumb [14]. A molded polythene splint for mallet finger deformities suggests that slight flexion is a better position for splintage, as hyperextension is likely to cause subluxation to appear [44]. ACL Injuries: The Cross Brace Protocol provides an additional non-operative option for ACL injuries and may be associated with satisfactory anatomical and functional healing for certain patient groups [46].
Limitations and Complications
Three patients initially managed with extension block splintage for dorsal fracture subluxation of the PIP joints proceeded to surgery because the splint failed to hold the joint in reduction, resulting in a less favourable outcome [18]. In a prospective study of metacarpal fractures, only 41% of patients in the metacarpal-brace group completed treatment compared to 81% in the plaster-cast group, with 60% of exclusions in the brace group due to complications [25]. Limited results from an underpowered study suggest splinting may not be required postoperatively for isolated digital nerve injuries in the hand [15].
Fabrication and Materials
Surgery and a postoperative regimen of rigid night splints and web-retaining gloves for day wear has allowed arrest or minimal progression of contractures in compliant patients with recessive dystrophic epidermolysis bullosa [33].
What the Evidence Shows
General Principles and Design
Studies involving smaller numbers of subjects can contribute to evidence-based practice if performed with high-level study design and standardized outcome measures [16]. The lack of high-quality evidence regarding splints with or without wrist immobilization following flexor tendon repair necessitates randomized clinical trials to guide rehabilitation choices [65].
Materials and Fabrication
Plaster of Paris provides a gentler and more precise means of tissue remodeling than dynamic or static progressive splinting for sustained positioning of joints and soft tissue [27]. Woodcast splints are used in clinical practice with good results and high patient acceptability [39]. A comparison study suggests further research is needed to compare the time and cost effectiveness of quickcast versus traditional thermoplastic materials [32].
Fractures and Dislocations
Functional bracing of fractures of the second through fifth metacarpals resulted in a final angulation averaging 15° compared to 31° in the splint group [49]. Three patients with dorsal fracture subluxation of the proximal interphalangeal joints managed with extension block splintage proceeded to surgery because the splint failed to hold the joint in reduction, resulting in a less favourable outcome [18]. Swing Design Dynamic Traction Splinting for intra-articular fractures of the digits offers similar benefits to previously reported splints and is simple and compact in design [2]. James traction splinting has been used for PIP fractures, with outcomes highlighted in two case studies at military treatment facilities [17].
Tendon Injuries
A modification of the Kleinert splint for mobilization of digital flexor tendons is easy to make and requires virtually no maintenance [9]. The modified Kleinert splint appears to be producing improved results and gaining more widespread acceptance [11]. A new dynamic splint for postoperative treatment of flexor tendon injury produced results significantly better than treatment in the traditional splint [52]. Patients with acute zone III extensor tendon injuries treated with dynamic extension splinting returned to full activities with good-to-excellent results 8 weeks earlier than those treated with static splinting [60].
Nerve Injuries and Palsy
In a single-subject experiment for radial nerve palsy, only one specific splint met the criteria of improving function and being worn by the patient [6]. The optimal orthosis for the complete median and radial nerve-injured war casualty has not been previously described to the authors' knowledge [7]. A supination splint worn distal to the elbow is clinically effective in increasing supination passive range of motion [53].
Contractures and Stiffness
Patient-adjusted static elbow splints achieved a functional arc of motion or very close to it after failure of conservative treatment for elbow contractures [62]. In Dupuytren's contracture, the types of splint and programmes for using them varied widely [19]. It remains unknown whether patients treated with static splintage for several months after Dupuytren's contracture surgery achieve better extension at 12 to 18 months or if there is any loss of flexion in this group [30, 31]. A three-point static splint achieved the objective of providing reduction and stability to the thumb metacarpophalangeal joint and improving function for chronic volar subluxation [28]. An ambulatory arm elevator sling achieved the objective of providing reduction and stability to the MP joint and improving function [29].
Arthritis and Overuse
Braces during the early phase of overuse injuries provide support to inflamed tissues without complete immobilization, facilitating healing [21]. All patients with arthritis of the first carpometacarpal joint who had initial improvement in symptoms with splinting had between 54% and 61% average improvement in symptom severity 6 months after splinting [55].
Trigger Finger
Splinting offers an alternative for patients who have a strong objection to cortisone injection for trigger fingers and thumb [38]. A low-profile ring splint for trigger finger is easily fabricated, functional, and requires minimal therapy visits [58]. A prospective case series of proximal interphalangeal joint orthosis and therapeutic exercise for trigger finger demonstrates feasibility and short-term clinical improvement but cannot establish superiority over other conservative treatments due to the absence of a control group [50].
Specific Conditions and Pediatric Applications
Surgery and a postoperative regimen of rigid night splints and web-retaining gloves for day wear allowed arrest or minimal progression of contractures in compliant patients with recessive dystrophic epidermolysis bullosa in short-term follow-up averaging 17 months [33]. A modification to a pediatric thumb splint has aided in preventing children from removing their splints [36]. The double-T palmar splint provides significantly superior results for maintaining the safe position, justifying its additional 50 g weight [59]. The PIPflex splint for treatment of mallet finger produced results superior to those resulting from other methods of splintage in 25 patients [61]. A clamshell splint with otoform lining has proven equally effective for other conditions requiring immobilization [5].
Practical Considerations
Design and Biomechanics
Splint design exerts a more significant influence on the electrophysiologic basis of dynamic extensor splinting than previously anticipated [1]. While "Therapeutic Hand Splints: A Rational Approach" addresses mechanics, physics, and biological considerations rather than specific fabrication patterns [13], practical designs prioritize patient compliance and ease of use. A straight spring orthosis for extension mobilization of proximal interphalangeal (PIP) joint flexion contractures effectively deforms tissue while remaining easy to fabricate, cost-effective, low-profile, and manageable by the patient [35]. Similarly, low-profile dynamic splints assist therapists in prescribing devices and monitoring progress [24], and a low-profile extension splint for active extensor lag of the PIP joint promotes functional hand use, thereby increasing compliance [57].
Specific Device Applications: * Reston Foam Splint: Described as comfortable, safe, versatile, and simple, this option is significantly cheaper and more readily available than conventional manufactured splints [56]. * Thumb CMC Immobilization: A small splint allows unrestricted use of adjacent joints and serves as a cost-effective, efficient treatment for patients postponing or excluding surgical reconstruction for thumb carpometacarpal joint pain [54]. * Wrist Extension: A static progressive wrist extension splint is easy to fabricate, cost-effective, and relatively comfortable based on clinical experience [48]. * Protective and Pediatric Use: A silicone splint provides value as a protective device post-injury and prophylactically for preventing diving injuries of the thumb [14]. A modification to a pediatric thumb splint has aided in preventing children from removing their splints in a clinic setting [36]. * Webspace Recovery: An adjustable first webspace splint was utilized in a patient who achieved a very satisfying webspace recovery [12].
Materials and Fabrication
Woodcast splints are employed in clinical practice with good results and high patient acceptability as an eco-conscious alternative material [39]. For digital flexor tendon mobilization, a modified Kleinert splint is easy to make and requires virtually no maintenance due to its simplicity [9]. A swing design dynamic traction splint for intra-articular fractures of the digits is noted for its simple and compact design [2]. Further studies are suggested to compare the time and cost effectiveness of commercially available splinting materials, specifically quickcast versus traditional thermoplastic, in the fabrication of a resting hand splint [32].
Clinical Application and Efficacy
In a single-subject experiment regarding splinting for radial nerve palsy, only splint 3 met the criteria of improving function and being worn by the patient [6]. For distal interphalangeal (DIP) joint flexion contractures, a static gutter splint may be worn at night to maintain gains achieved during the day [20]. However, a dynamic flexion splint for the DIP joint is contraindicated in situations requiring the PIP joint to be held in full extension [34]. An alternative flexion splinting protocol requires only the flexion splint, as opposed to the traditional sequence of extension followed by flexion splinting, which reduces fabrication costs and simplifies patient instructions [51]. A new method of extension-block splinting for the PIP joint was found to be much more comfortable than an extension-block cast, although the authors noted the splint was annoying [47].
Fracture Management and Outcomes: * PIP Fractures: James traction splinting interventions for PIP fractures have been highlighted in two case studies at military treatment facilities [17]. Conversely, three patients initially managed with splintage for dorsal fracture subluxation of the PIP joints proceeded to surgery because the splint failed to hold the joint in reduction; these patients experienced a less favourable outcome [18]. * Distal Radial Fractures: If patients with minimally displaced distal radial fractures can be treated safely using a removable splint, this saves them time and inconvenience regarding additional hospital visits and reduces healthcare system costs [45]. * Dynamic Splinting Power Sources: A new power source in dynamic splinting with lower force-extension ratios has helped improve range of motion within the splint, although further controlled trials are needed to confirm this [41].
Research and Practice Context
Topics selected for inclusion in a special issue on splinting are intended to advance the artistry of splinting toward an evidence-based practice approach [3]. While studies including large numbers of subjects are needed to substantiate the effectiveness of splinting, studies involving smaller numbers of subjects can contribute greatly, provided they are performed with the highest level of study design and use standardized outcome measures valid for answering the designated research questions [16]. Although a study on postoperative splinting for isolated digital nerve injuries in the hand is underpowered, these limited results suggest splinting may not be required postoperatively [15]. The purpose of a historical review of splinting was to identify, using an intensive literature review, the primary historical factors and events that shaped the evolution of current splinting technique and practice [37].
Key Evidence
- [Paper] This shows that splint design plays a more significant role than previously expected. [1] (10.1016/0363-5023(92)90404-d)
- [L4] It offers similar benefits to splints reported previously in the literature, and is simple and compact in design. [2] (10.1197/j.jht.2005.11.001)
- [L5] The topics selected for inclusion in this special issue are intended to advance the artistry of splinting toward an evidence-based practice approach. [3] (10.1053/hanthe.2002.v15.015009)
- [L5] Currently, the application of splints for treating hand and upper extremity problems is accepted as definitive standard practice in this rehabilitation arena. [4] (10.1016/s0894-1130(98)80014-8)
- [L5] The splint has proven equally effective for other conditions requiring immobilization. [5] (10.1016/s0894-1130(97)80046-4)
- [L5] Only splint 3 met the criteria of improving function and being worn by the patient. [6] (10.1016/s0894-1130(01)80053-3)
- [L5] To the authors' knowledge the optimal orthosis for this situation has not been previously described. [7] (10.1016/s0894-1130(12)80275-4)
- [L5] They argue that the conclusion that sling immobilization is 'not inferior' to brace immobilization cannot be attributed solely to the type of immobilization. [8] (10.1002/arj.70326)
- [L4] The splint is easy to make and, because of its simplicity, requires virtually no maintenance. [9] (10.1016/0266-7681(87)90007-6)
- [L5] The examples given show that many splints can be constructed with material that is inexpensive, available, and often discarded. [10] (10.1016/s0363-5023(81)80008-1)
- [L5] The modified splint appears to be producing improved results and to be gaining more widespread acceptance. [11] (10.1016/s0363-5023(88)80070-4)
- [L5] The patient for whom the splint was initially developed has recovered a very satisfying webspace thanks to the splint. [12] (10.1016/s0894-1130(96)80091-3)
- [Paper] The text focuses on mechanics, physics, and biological considerations rather than providing specific splint patterns or fabrication instructions. [13] (10.1016/s0894-1130(02)70027-6)
- [L5] Our clinical opinion is that it has value as both a protective splint following injury and as well as prophylacticly. [14] (10.1197/j.jht.2006.07.029)
- [L1] Although this study is underpowered, these limited results suggest splinting may not be required postoperatively. [15] (10.1197/j.jht.2007.04.010)
- [Paper] While studies that include large numbers of subjects are needed to substantiate the effectiveness of splinting, studies involving smaller numbers of subjects can contribute greatly as well, so long as they are performed with the highest level of study design and use standardized outcome measures that are valid for answering the designated research questions. [16] (10.1053/hanthe.2002.v15.0150131)
- [L4] The authors present two case studies highlighting James traction splinting interventions and corresponding outcomes at military treatment facilities. [17] (10.1197/j.jht.2007.08.019)
- [L3] Three patients initially managed with splintage proceeded to surgery because the splint failed to hold the joint in reduction, and these patients had a less favourable outcome. [18] (10.1016/s0266-7681(05)80249-9)
- [L5] The types of splint and programmes for using them varied widely. [19] (10.1016/0266-7681(92)90208-j)
- [L5] A static gutter splint may be worn at night to maintain gains achieved in the day. [20] (10.1016/s0894-1130(01)80009-0)
- [L5] Braces during the early phase provide support to inflamed tissues without complete immobilization, facilitating healing. [21] (10.1016/s0278-5919(05)70273-8)
- [L3] It clearly indicates theoretical advantages and disadvantages of the dynamic and static splint designs. [22] (10.1016/s0894-1130(99)80074-x)
- [Paper] Creation of splint designs should be based on mechanical fact rather than on mode-of-the-day bias. [23] (10.1016/s0894-1130(12)80309-7)
- [Paper] This will assist therapists in the prescription of splints for certain patients and enable them to monitor their progress closely. [24] (10.1016/s0894-1130(12)80332-2)
- [L1] Only 41% of the patients from the metacarpal-brace group completed the treatment, compared to 81% in the plaster-cast group, with 60% of exclusions in the brace group due to complications. [25] (10.1016/s0894-1130(12)80327-9)
- [Paper] This newly developed buddy splint corrects the mechanical and kinesiologic disadvantages of current buddy strapping systems. [26] (10.1016/s0894-1130(12)80041-x)
- [L5] The sustained positioning of joints and soft tissue with plaster of Paris provides a gentler and more precise means of tissue remodeling than does dynamic or static progressive splinting. [27] (10.1053/hanthe.2002.v15.015014)
- [L5] The objective of providing reduction and stability to the MP joint and improving function was achieved with this splint. [28] (10.1016/s0894-1130(12)80062-7)
- [Paper] The objective of providing reduction and stability to the MP joint and improving function was achieved with this splint. [29] (10.1016/s0894-1130(12)80064-0)
- [L5] In particular, we need to know whether patients treated with static splintage for several months after operation achieve better extension at 12 to 18 months and, if so, is there any loss of flexion in this group? [30] (10.1016/0266-7681(87)90182-3)
- [L5] In particular, we need to know whether patients treated with static splintage for several months after operation achieve better extension at 12 to 18 months and, if so, is there any loss of flexion in this group? [31] (10.1016/0266-7681_87_90182-3)
- [L4] Further studies are suggested for comparing time and cost effectiveness between commercially available splinting materials. [32] (10.1016/s0894-1130(98)80060-4)
- [L4] Surgery and the postoperative regimen of rigid night splints and web-retaining gloves for day wear has allowed arrest or minimal progression of contractures in compliant patients in short-term follow-up study of an average of 17 months. [33] (10.1016/s0363-5023(96)80210-3)
- [L5] This splinting tack is contraindicated in situations that require the PIP to be held in full extension. [34] (10.1016/s0894-1130(03)00041-3)
- [Paper] The concept of a straight spring for this orthosis was effective for tissue deformation, easy to make and finish, cost-effective, low profile, and easy to handle by the patient. [35] (10.1016/j.jht.2020.01.005)
- [L5] This splint modification has aided in preventing children in our clinic from removing their splints. [36] (10.1197/j.jht.2004.04.014)
- [Paper] The purpose of this study was to identify, using an intensive literature review, the primary historical factors and events that shaped the evolution of current splinting technique and practice. [37] (10.1053/hanthe.2002.v15.0150091)
- [L4] Splinting offers an alternative for patients who have a strong objection to cortisone injection. [38] (10.1016/0363-5023(92)90124-8)
- [L5] Woodcast splints are used in clinical practice with good results and high patient acceptability. [39] (10.1097/bth.0000000000000210)
- [Paper] The only drawback to these splints was that if changes were needed, a whole new splint had to be fabricated. [40] (10.1016/s0894-1130(12)80157-8)
- [L4] It is their initial impression that the lower force-extension ratios have helped to improve range of motion within the splint, although further controlled trials are needed to confirm this. [41] (10.1016/s0894-1130(89)80022-5)
- [L5] To date, selection of the proper splint for managing joint stiffness has been empirical. [42] (10.1053/hanthe.2002.v15.015015)
- [L5] The modified splint has theoretical advantages over the usual Kleinert splint and it may be of clinical use—further trials are in progress. [43] (10.1016/s0266-7681(84)80039-x)
- [L5] The author suggests that a better position for splintage is slight flexion, as hyperextension provided by a splint is likely to cause the subluxation to appear. [44] (10.1016/s0363-5023(85)80277-x)
- [L2] If patients can be treated safely using a removable splint, this will save them time and inconvenience in terms of additional visits to the hospital, and save the healthcare system money. [45] (10.1302/0301-620x.107b1.bjj-2024-0634.r1)
- [L2] The Cross Brace Protocol provides an additional non-operative option for ACL injuries and may be associated with satisfactory anatomical and functional healing for certain patient groups. [46] (10.1177/2325967126s00013)
- [L4] Although the authors found the splint annoying, it was much more comfortable than an extension-block cast. [47] (10.1016/s0363-5023(80)80118-3)
- [L5] Based on clinical experience, the authors have found this splint is easy to fabricate, cost-effective, and relatively comfortable. [48] (10.1016/s0894-1130(02)80009-6)
- [L2] Final angulation averaged 15° in the brace group compared to 31° in the splint group. [49] (10.1016/s0363-5023(87)80179-x)
- [L4] Because of the absence of a control group, these findings demonstrate feasibility and short-term clinical improvement but cannot establish superiority over other conservative treatments. [50] (10.1016/j.jhsg.2026.101038)
- [L4] This protocol requires only the flexion splint as opposed to the traditional extension splint followed by flexion splinting; therefore, the cost of splint fabrication is reduced and the instructions to patients for following their splinting programs are simplified. [51] (10.1016/s0894-1130(96)80022-6)
- [L4] Results were significantly better than after treatment in the traditional splint. [52] (10.1016/s0363-5023(89)80025-5)
- [L4] Results indicate the supination splint is clinically effective in increasing supination PROM. [53] (10.1016/s0894-1130(03)00034-6)
- [L5] This small splint allows unrestricted use of adjacent joints and is a cost-effective, efficient treatment option for those patients who elect to postpone or exclude surgical reconstruction for thumb CMC joint pain. [54] (10.1016/s0894-1130(00)80006-x)
- [L4] All patients who had initial improvement in their symptoms with splinting had between 54% and 61% average improvement in symptom severity 6 months after splinting. [55] (10.1053/jhsu.1999.jhsu24a0086)
- [L5] The Reston foam splint is a very comfortable, safe, versatile, and simple splint that is much cheaper and more readily available than conventional manufactured splints. [56] (10.1016/s0363-5023(89)80029-2)
- [L5] The advantages of this splint are that it is low profile, leading to more functional use of the hand and thus increasing patient compliance. [57] (10.1197/j.jht.2007.04.008)
- [L4] This low-profile ring splint is easily fabricated and functional and the treatment protocol requires minimal therapy visits. [58] (10.1197/j.jht.2008.05.001)
- [L2] The significantly superior results of the double-T splint are worth this additional 50 g. [59] (10.1016/s0266-7681(05)80214-1)
- [L2] When results were compared with the results of our method of static splinting used prior to this prospective study, patients returned to full activities with good-to-excellent results 8 weeks earlier instead of at 16 to 18 weeks. [60] (10.1016/s0363-5023(10)80082-6)
- [L4] The results of treatment in 25 patients are superior in our hands to those resulting from other methods of splintage. [61] (10.1016/0266-7681(88)90126-x)
- [L4] The functional arc of motion or very close to it was achieved using patient-adjusted static splints after failure of conservative treatment. [62] (10.1016/s1058-2746(95)80215-0)
- [L4] A volar splint has clear limitations regarding immobilization, which is of relevance in clinical practice. [63] (10.1177/1753193416686039)
- [L5] The splint follows recommendations to support the pisotriquetral area. [64] (10.1197/j.jht.2004.04.013)
- [L5] The lack of high-quality evidence means that randomized clinical trials need to be performed to guide rehabilitation choices. [65] (10.1016/j.hansur.2019.05.004)
References
[1] Electrophysiologic basis of dynamic extensor splinting. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90404-d
[2] Swing Design Dynamic Traction Splinting for the Treatment of Intra-articular Fractures of the Digits. Journal of Hand Therapy. 2006. DOI: 10.1197/j.jht.2005.11.001
[3] The splinting issue. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.015009
[4] The influence of splinting on healing tissues. Journal of Hand Therapy. 1998. DOI: 10.1016/s0894-1130(98)80014-8
[5] The clamshell splint with otoform lining. Journal of Hand Therapy. 1997. DOI: 10.1016/s0894-1130(97)80046-4
[6] Splinting and radial nerve palsy: A single-subject experiment. Journal of Hand Therapy. 2001. DOI: 10.1016/s0894-1130(01)80053-3
[7] Orthosis for the Complete Median and Radial Nerve-injured War Casualty. Journal of Hand Therapy. 1992. DOI: 10.1016/s0894-1130(12)80275-4
[8] Regarding “Sling Is Not Inferior to Brace Immobilization After Arthroscopic Rotator Cuff Repair: A Randomized Controlled Trial”. Arthroscopy. 2026. DOI: 10.1002/arj.70326
[9] A modification of the kleinert splint for mobilisation of digital flexor tendons. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90007-6
[10] Examples of simply fabricated, custom-made splints for the hand. The Journal of Hand Surgery. 1981. DOI: 10.1016/s0363-5023(81)80008-1
[11] Kleinert splint. The Journal of Hand Surgery. 1988. DOI: 10.1016/s0363-5023(88)80070-4
[12] Adjustable First Webspace Splint. Journal of Hand Therapy. 1996. DOI: 10.1016/s0894-1130(96)80091-3
[13] Therapeutic Hand Splints: A Rational Approach. Volume 1: Mechanical and Biomechanical Considerations. Journal of Hand Therapy. 2002. DOI: 10.1016/s0894-1130(02)70027-6
[14] A Silicone Splint to Prevent Diving Injuries of the Thumb. Journal of Hand Therapy. 2006. DOI: 10.1197/j.jht.2006.07.029
[15] Postoperative Splinting for Isolated Digital Nerve Injuries in the Hand. Journal of Hand Therapy. 2007. DOI: 10.1197/j.jht.2007.04.010
[16] Outcomes, treatment effectiveness, efficacy, and evidence-based practice: Examples from the world of splinting. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.0150131
[17] James Traction Splinting for PIP Fractures. Journal of Hand Therapy. 2008. DOI: 10.1197/j.jht.2007.08.019
[18] Dorsal Fracture Subluxation of the Proximal Interphalangeal Joints Treated by Extension Block Splintage. Journal of Hand Surgery. 1992. DOI: 10.1016/s0266-7681(05)80249-9
[19] A Review of Attitudes to Splintage in Dupuytren's Contracture. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90208-j
[20] A flexion contracture splint for the distal interphalangeal joint. Journal of Hand Therapy. 2001. DOI: 10.1016/s0894-1130(01)80009-0
[21] REHABILITATION CONCEPTS AND SUPPORTIVE DEVICES FOR OVERUSE INJURIES OF THE UPPER EXTREMITIES. Clinics in Sports Medicine. 2001. DOI: 10.1016/s0278-5919(05)70273-8
[22] Force analysis of the belly gutter and capener splints. Journal of Hand Therapy. 1999. DOI: 10.1016/s0894-1130(99)80074-x
[23] Splints: Mechanics versus Convention. Journal of Hand Therapy. 1995. DOI: 10.1016/s0894-1130(12)80309-7
[24] Low-profile Dynamic Splints: A Solution to the Friction Problem. Journal of Hand Therapy. 1993. DOI: 10.1016/s0894-1130(12)80332-2
[25] Functional Fracture Bracing in Metacarpal Fractures: The Galveston Metacarpal Brace versus a Plaster-of-Paris Bandage in a Prospective Study. Journal of Hand Therapy. 1993. DOI: 10.1016/s0894-1130(12)80327-9
[26] Buddy Splint. Journal of Hand Therapy. 1994. DOI: 10.1016/s0894-1130(12)80041-x
[27] Plaster of Paris: The forgotten hand splinting material. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.015014
[28] Three-Point Static Splint for Chronic Volar Subluxation of the Thumb Metacarpophalangeal Joint. Journal of Hand Therapy. 1994. DOI: 10.1016/s0894-1130(12)80062-7
[29] Ambulatory Arm Elevator Sling (Hands Up). Journal of Hand Therapy. 1994. DOI: 10.1016/s0894-1130(12)80064-0
[30] A review of attitudes to splintage in Dupuytren's contracture. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90182-3
[31] A Review of Attitudes to Splintage in Dupuytren’s Contracture. Journal of Hand Surgery. 1987. DOI: 10.1016/0266-7681_87_90182-3
[32] Comparison study of quickcast versus a traditional thermoplastic in the fabrication of a resting hand splint. Journal of Hand Therapy. 1998. DOI: 10.1016/s0894-1130(98)80060-4
[33] Surgical treatment and postoperative splinting of recessive dystrophic epidermolysis bullosa. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80210-3
[34] Dynamic flexion splint for the distal interphalangeal joint. Journal of Hand Therapy. 2003. DOI: 10.1016/s0894-1130(03)00041-3
[35] Design of an orthosis with straight spring for extension mobilization of flexion contracture of the proximal interphalangeal joint. Journal of Hand Therapy. 2021. DOI: 10.1016/j.jht.2020.01.005
[36] Modification to a pediatric thumb splint. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2004.04.014
[37] A History of splinting: To understand the present, view the past. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.0150091
[38] Trigger fingers and thumb: When to splint, inject, or operate. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90124-8
[39] An Eco-conscious Alternative Material for Splinting in Hand Surgery. Techniques in Hand & Upper Extremity Surgery. 2018. DOI: 10.1097/bth.0000000000000210
[40] Plaster of Paris Splints. Journal of Hand Therapy. 1995. DOI: 10.1016/s0894-1130(12)80157-8
[41] A new power source in dynamic splinting: Clinical experience and results. Journal of Hand Therapy. 1989. DOI: 10.1016/s0894-1130(89)80022-5
[42] A proposed decision hierarchy for splinting the stiff joint, with an emphasis on force application parameters. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.015015
[43] A Modified Kleinert Controlled Mobilization Splint Following Flexor Tendon Repair. Journal of Hand Surgery. 1984. DOI: 10.1016/s0266-7681(84)80039-x
[44] Molded polythene splint for mallet finger deformities. The Journal of Hand Surgery. 1985. DOI: 10.1016/s0363-5023(85)80277-x
[45] Do patients with minimally displaced distal radial fractures need a plaster cast?. The Bone & Joint Journal. 2025. DOI: 10.1302/0301-620x.107b1.bjj-2024-0634.r1
[46] Short-term Outcomes of the Cross Brace Protocol for ACL Rupture Management: A Prospective Cohort Study. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/2325967126s00013
[47] A new method of extension-block splinting for the proximal interphalangeal joint—Preliminary report. The Journal of Hand Surgery. 1980. DOI: 10.1016/s0363-5023(80)80118-3
[48] Static progressive wrist extension splint. Journal of Hand Therapy. 2002. DOI: 10.1016/s0894-1130(02)80009-6
[49] Functional bracing of fractures of the second through fifth metacarpals. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80179-x
[50] Effectiveness of Proximal Interphalangeal Joint Orthosis and Therapeutic Exercise in the Management of Trigger Finger: A Prospective Case Series. Journal of Hand Surgery Global Online. 2026. DOI: 10.1016/j.jhsg.2026.101038
[51] Effect of an alternative flexion splinting protocol on mid-joint rom. Journal of Hand Therapy. 1996. DOI: 10.1016/s0894-1130(96)80022-6
[52] A new dynamic splint for postoperative treatment of flexor tendon injury. The Journal of Hand Surgery. 1989. DOI: 10.1016/s0363-5023(89)80025-5
[53] A Supination Splint Worn Distal to the Elbow:. Journal of Hand Therapy. 2003. DOI: 10.1016/s0894-1130(03)00034-6
[54] The biomechanics of a thumb carpometacarpal immobilization splint: Design and fitting. Journal of Hand Therapy. 2000. DOI: 10.1016/s0894-1130(00)80006-x
[55] Splinting in the treatment of arthritis of the first carpometacarpal joint. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.jhsu24a0086
[56] A simple, comfortable, conforming, and adaptable splint. The Journal of Hand Surgery. 1989. DOI: 10.1016/s0363-5023(89)80029-2
[57] Low Profile Extension Splint for Active Extensor Lag of the Proximal Interphalangeal Joint. Journal of Hand Therapy. 2007. DOI: 10.1197/j.jht.2007.04.008
[58] Effectiveness of Splinting for the Treatment of Trigger Finger. Journal of Hand Therapy. 2008. DOI: 10.1197/j.jht.2008.05.001
[59] Maintaining the Safe Position in a Palmar Splint. Journal of Hand Surgery. 1996. DOI: 10.1016/s0266-7681(05)80214-1
[60] Results of acute zone III extensor tendon injuries treated with dynamic extension splinting. The Journal of Hand Surgery. 1991. DOI: 10.1016/s0363-5023(10)80082-6
[61] The pipflex splint for treatment of mallet finger. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90126-x
[62] Patient-adjusted static elbow splints for elbow contractures: A preliminary report. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80215-0
[63] Helicoidal splinting after wrist surgery: a laboratory study. Journal of Hand Surgery (European Volume). 2017. DOI: 10.1177/1753193416686039
[64] An ulnar boost splint for midcarpal instability. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2004.04.013
[65] Splints, with or without wrist immobilization, following surgical repair of flexor tendon lesions of the hand: A systematic review. Hand Surgery and Rehabilitation. 2019. DOI: 10.1016/j.hansur.2019.05.004