Patients › Shoulder
اوس ایکرومیالی (Os Acromiale)
Patient-facing topic on os acromiale — failed fusion of an acromial ossification centre that may cause shoulder pain and contribute to subacromial impingement.
آپ کو کیا محسوس ہوتا ہے
اوس ایکرومیالی (os acromiale) میں درد عموماً آپ کے کندھے کے سامنے اور پہلو میں، جوڑ کی ہڈی والی چھت کے اوپر محسوس ہوتا ہے۔ سر سے اوپر کے کاموں سے یہ بڑھ جاتا ہے۔ اونچے شیلف تک ہاتھ بڑھانا، دھلے کپڑے لٹکانا، یا کوئی چیز کندھے کی اونچائی سے اوپر اٹھانا، یہ سب درد شروع کر سکتے ہیں۔ بہت سے لوگوں کو رات کو بھی درد محسوس ہوتا ہے، اور جب آپ اس طرف لیٹیں تو یہ آپ کو جگا سکتا ہے۔
یہ درد کندھے کے اوپر ہڈی کے ایک چھوٹے ٹکڑے سے آتا ہے جو بڑھنے کی عمر کے دوران باقی ہڈی سے کبھی نہیں جڑا۔ جب آپ بازو اٹھاتے ہیں تو ایک پٹھا اس ڈھیلے ٹکڑے کو کھینچتا ہے اور یہ تھوڑا سا ہلتا ہے، جس سے اس کے نیچے موجود ٹینڈن (tendon)، یعنی وہ مضبوط ڈوری جو پٹھے کو ہڈی سے جوڑتی ہے، پر دباؤ پڑتا ہے۔ ہڈی کے دونوں ٹکڑوں کے درمیان کے ملاپ کو چھونے پر بھی درد ہو سکتا ہے، اور اسے براہِ راست دبانے سے درد شروع ہو سکتا ہے۔
روزمرہ زندگی میں ہو سکتا ہے آپ کو محسوس ہو کہ بازو کو پہلو کی طرف باہر اٹھاتے وقت یا اسے باہر کی طرف گھماتے وقت یہ کمزور ہے۔ دردناک قوس (painful arc) عام ہے: بازو اٹھاتے ہوئے راستے کے درمیان میں کندھے میں درد ہوتا ہے، پھر بازو مزید اوپر جانے پر درد کم ہو جاتا ہے۔ چونکہ اس کی علامات کندھے کی چھت کے نیچے والے ٹینڈن کے گھساؤ سے بہت ملتی جلتی ہیں، اس لیے اس مسئلے کو آسانی سے روٹیٹر کف (rotator cuff)، یعنی ٹینڈنوں کا وہ گروپ جو کندھے کو تھامتا اور گھماتا ہے، کا مسئلہ سمجھ لیا جاتا ہے، اور اُس کے علاج کے بعد بھی یہ درد دیتا رہ سکتا ہے۔
اس طرح کی ہڈی کی بناوٹ والے زیادہ تر لوگوں کو کبھی کچھ محسوس نہیں ہوتا۔ اکثر اس کا پتا کسی اور وجہ سے کیے گئے اسکین پر اتفاقاً چلتا ہے۔ جب یہ درد کا سبب بنتا ہے تو عموماً کم عمر بالغوں میں ظاہر ہوتا ہے، اکثر کسی چوٹ کے بغیر، اور اگر آپ کے کندھے کا درد فزیوتھراپی، کھیل سے آرام، یا انجکشن سے ٹھیک نہیں ہوا تو اس پر شک کرنا مناسب ہے۔
اگر آپ کی علامات ٹھیک نہیں ہو رہیں، ہفتوں کے دوران بدتر ہو رہی ہیں، رات کو آپ کو جگاتی ہیں، یا آپ کو کام کرنے یا بازو استعمال کرنے سے روکتی ہیں، تو اپنے فیملی ڈاکٹر (GP) کو دکھائیں یا کسی ماہر سے معائنے کی درخواست کریں۔
دراصل کیا ہو رہا ہے
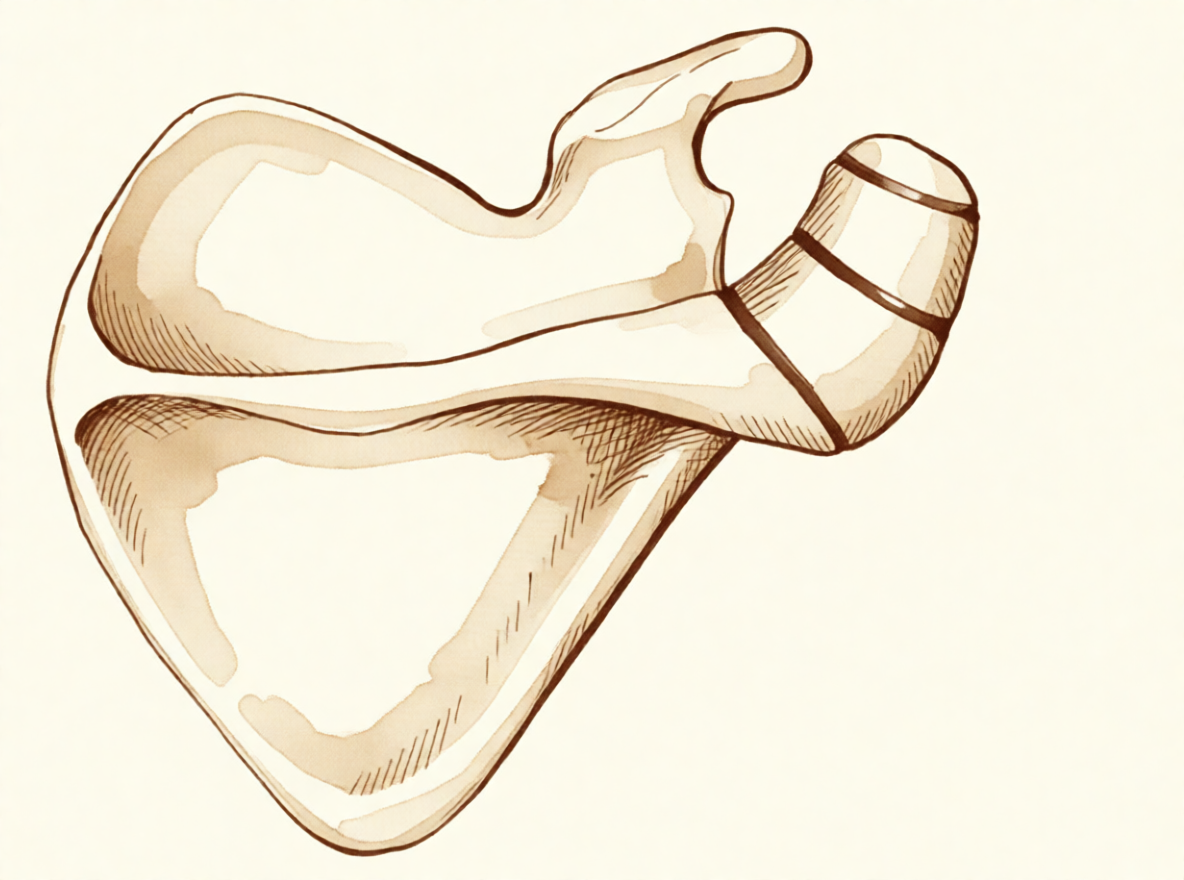
آپ کے کندھے کی ہڈی والی چھت ہڈی کے ایک ہی ٹکڑے کے طور پر نہیں بنتی۔ یہ تین الگ الگ مراکز سے شروع ہوتی ہے جو آہستہ آہستہ آپس میں جڑتے ہیں؛ یہ عمل تقریباً 15 سال کی عمر میں شروع ہوتا ہے اور عموماً 25 سال کی عمر تک مکمل ہو جاتا ہے۔ تقریباً 8 فیصد لوگوں میں ان میں سے ایک ملاپ کبھی بند نہیں ہوتا۔ یہ خلا ہڈی کے بجائے سخت ریشے دار بافت سے بھر جاتا ہے، جس سے چھت کا ایک چھوٹا ٹکڑا ٹھوس ہڈی کے بجائے ایک لچکدار کڑی کے ذریعے جڑا رہ جاتا ہے۔
اسے ایک ایسے تختے کی طرح سمجھیں جو دیوار پر ایک ڈھیلے پیچ سے لگا ہو۔ یہ ٹکا رہتا ہے، لیکن جب آپ اس پر ٹیک لگاتے ہیں تو تھوڑا سا ہلتا ہے۔ جو پٹھا آپ کے بازو کو پہلو کی طرف باہر اٹھاتا ہے وہ اسی چھت سے جڑا ہوتا ہے، اس لیے جب بھی آپ بازو اٹھاتے ہیں، وہ پٹھا ڈھیلے ٹکڑے کو کھینچتا ہے اور یہ تھوڑا سا لچکتا ہے۔ یہ حرکت چھت کے نیچے سے گزرنے والے ٹینڈن کو نیچے دباتی ہے، اور یہ رگڑ اس میں جلن (irritation) پیدا کرتی ہے۔ یہی وجہ ہے کہ سر سے اوپر کے کاموں میں درد ہوتا ہے اور درد کندھے کے سامنے اور پہلو میں محسوس ہوتا ہے۔
لچکدار کڑی خود بھی مسئلہ بن سکتی ہے۔ یہ بذاتِ خود چھونے پر درد کرنے لگ سکتی ہے، بالکل کسی گھسے ہوئے جوڑ کی طرح، اور اسے دبانے سے درد شروع ہو جاتا ہے۔ اس طرح کی ہڈی کی بناوٹ والے زیادہ تر لوگوں کو کبھی کچھ محسوس نہیں ہوتا، اور بظاہر یہ نہ تو بذاتِ خود کندھے میں درد پیدا کرتا ہے اور نہ ٹینڈن کے پھٹنے کا امکان بڑھاتا ہے۔ لیکن جب ڈھیلا ٹکڑا معمول سے زیادہ ہلنے لگے، چاہے اپنی بناوٹ کی وجہ سے یا اس جگہ چوٹ لگنے کے بعد، تو یہ ہر بار بازو اٹھانے پر ٹینڈن پر دباؤ ڈال سکتا ہے۔ یہی اوپر بیان کیا گیا دردناک قوس اور رات کا درد پیدا کرتا ہے۔
چونکہ ڈھیلا ٹکڑا عین اس جگہ ہوتا ہے جہاں ٹینڈن ہوتا ہے، اس لیے یہ دونوں مسائل اکثر ایک ساتھ سامنے آتے ہیں۔ اگر آپ کے کندھے کا ٹینڈن کے کسی مسئلے کے لیے پہلے ہی علاج ہو چکا ہے اور درد ٹھیک نہیں ہوا، تو اس نہ جڑے ہوئے ٹکڑے کی جانچ کروانا فائدہ مند ہے، کیونکہ صرف ٹینڈن کا آپریشن کرنے سے اس کے اوپر ہلنے والا ہڈی کا ٹکڑا پرسکون نہیں ہوگا۔
ہم اس کے لیے کیا کر سکتے ہیں
ڈاکٹر کیرن ہِرپرا، جو Mater Private Hospital Rockhampton میں بازو اور ہاتھ کے سرجن (upper-limb surgeon) ہیں، علاج کا آغاز ان سب سے کم چیر پھاڑ والے طریقوں سے کرتے ہیں جو آپ کے مسئلے کے لیے موزوں ہوں۔ مریض عام طور پر اپنے فیملی ڈاکٹر (GP) کے ریفرل (referral) پر ہمارے کلینک آتے ہیں؛ اگر کسی فزیوتھراپسٹ نے آپ کو ہمیں دکھانے کا مشورہ دیا ہے، تب بھی میڈیکیئر (Medicare) کی رقم کی واپسی (rebate) کا اہل ہونے کے لیے آپ کو اپنے فیملی ڈاکٹر سے ریفرل لینا ہوگا۔ پہلی ملاقات پر ہم آپ سے آپ کی تکلیف اور صحت کی تفصیل پوچھتے ہیں، آپ کے کندھے کا معائنہ کرتے ہیں، اور جہاں ضرورت ہو ایکسرے یا اسکین کا انتظام کرتے ہیں۔
پہلا قدم عموماً یہ ہوتا ہے کہ آپ اپنے کندھے کو استعمال کرنے کا طریقہ بدلیں اور فزیوتھراپی کو پوری طرح آزمائیں۔ فزیوتھراپی کا مقصد ہڈی والی چھت کے نیچے کی جلن کو کم کرنا اور آپ کے کندھے کے اردگرد کے پٹھوں کو مضبوط کرنا ہے تاکہ وہ سر سے اوپر کے کاموں کو بہتر طور پر سہہ سکیں۔ کسی اور چیز کے بارے میں سوچنے سے پہلے اسے مناسب وقت تک آزمائیں۔
درد کی دوا اس دوران آپ کو حرکت جاری رکھنے میں مدد دے سکتی ہے۔ سوزش کم کرنے والی سادہ دوائیں، جو آپ کے فیملی ڈاکٹر کے مشورے کے مطابق لی جائیں، دکھن کو کم کرتی ہیں تاکہ آپ آرام سے اپنی ورزشیں کر سکیں۔ اگر درد ٹھیک نہیں ہو رہا، ہفتوں کے دوران بڑھ رہا ہے، رات کو آپ کو جگاتا ہے، یا آپ کو کام کرنے یا بازو استعمال کرنے سے روکتا ہے، تو اپنے فیملی ڈاکٹر کو دکھائیں یا کسی ماہر سے معائنے کی درخواست کریں۔
جب سرجری کے بغیر علاج سے کافی بہتری نہ آئی ہو تو ہم سرجری پر غور کرتے ہیں۔ اس سے پہلے ہم سادہ ایکسرے سے تشخیص کی تصدیق کرتے ہیں، جو نہ جڑے ہوئے ٹکڑے کو دکھانے کے لیے تقریباً ہمیشہ کافی ہوتے ہیں۔ بغل کے نیچے سے لیا گیا ایکسرے کا زاویہ جوڑ کی شکل اور چھت کا اگلا حصہ صاف دکھاتا ہے، اور یہ اس لیے اہم ہے کہ چوٹ ہڈی کے دونوں ٹکڑوں کے درمیان کے ملاپ کو نقصان پہنچا سکتی ہے۔ الٹراساؤنڈ چھت کے نیچے سے گزرنے والے ٹینڈن کو جانچنے کا ایک آسان اور درست طریقہ ہے، اور ایم آر آئی اسکین اس ٹینڈن اور اردگرد کی نرم بافتوں کی زیادہ مکمل تصویر دیتا ہے۔
ہم جو آپریشن سب سے زیادہ تجویز کرتے ہیں وہ دوربین کے ذریعے (keyhole، arthroscopic) جوڑ کا معائنہ اور برسا ہٹانے کا عمل (bursectomy) ہے، یعنی چھت کے نیچے کی جگہ سے سوزش والی بافت صاف کرنا، اور پھر ایک چھوٹے کھلے چیرے کے ذریعے ہڈی کی پیوندکاری (bone grafting) اور فکسیشن (fixation)، یعنی ڈھیلے ٹکڑے کو ساکن تھامے رکھنا تاکہ یہ ہڈی کے باقی حصے سے جڑ سکے۔ اسے ساکن رکھنے سے دونوں ٹکڑے آپس میں جڑ سکتے ہیں۔ اگر ڈھیلا ٹکڑا چھوٹا ہو تو ہم اسے جمانے کے بجائے نکال سکتے ہیں۔ بڑے ٹکڑے کو جمانے میں احتیاط کی ضرورت ہوتی ہے، کیونکہ بازو اٹھانے والا پٹھا اسے مسلسل کھینچتا رہتا ہے اور ٹکڑا پتلا ہوتا ہے۔ کبھی کبھی فکسیشن کے بعد ٹکڑا نہیں جڑتا، جسے ہڈی کا نہ جڑنا (non-union) کہتے ہیں۔ ہم آپ سے تفصیل سے بات کریں گے کہ کون سا طریقہ آپ کے کندھے کے لیے مناسب ہے، اور آپ کے ساتھ مل کر فیصلہ کریں گے۔
کیا توقع رکھیں
اس طرح کی ہڈی کی بناوٹ والے زیادہ تر لوگوں کو کبھی کوئی تکلیف نہیں ہوتی، اور اس کے لیے کسی علاج کی ضرورت نہیں ہوتی۔ جب یہ درد کا سبب بنتا ہے تو آگے کی صورتِ حال اس پر منحصر ہے کہ ڈھیلا ٹکڑا ٹکا ہوا ہے یا نہیں، اور آیا یہی واقعی آپ کے درد کی وجہ ہے۔
درد دینے والے ٹکڑے کا علاج عموماً سرجری کے بغیر شروع ہوتا ہے۔ کندھے کو استعمال کرنے کا طریقہ بدلنے، فزیوتھراپی اور درد کی سادہ دوا سے بہت سے لوگوں کو آرام آ جاتا ہے۔ اگر مناسب وقت تک آزمانے کے بعد بھی اس سے فائدہ نہ ہوا ہو تو سرجری سے درد میں واضح کمی اور کندھے کی بہتر کارکردگی حاصل ہو سکتی ہے۔ جب ڈھیلے ٹکڑے کو ساکن رکھا جائے اور یہ ہڈی کے باقی حصے سے جڑ جائے تو کندھے کی کارکردگی کے پیمانوں پر لوگوں کے نتائج اس صورت سے بہتر ہوتے ہیں جب دونوں ٹکڑے الگ رہیں۔ تاہم سرجری ہمیشہ حل نہیں ہوتی۔ اس مسئلے کے ساتھ ساتھ ٹینڈن کے پھٹاؤ والے کچھ لوگوں میں سرجری کے بعد نتائج ملے جلے رہے ہیں، اور مجموعی طور پر 53 فیصد لوگوں کو اطمینان بخش نتائج ملے۔
اگر اسے ایسے ہی چھوڑ دیا جائے اور یہ آپ کو تکلیف دیتا رہے تو درد عموماً خود سے ختم نہیں ہوتا۔ اسے نظر انداز کر جانا بھی آسان ہے: جب علاج کے بعد بھی کندھے کا درد ٹھیک نہ ہوا ہو، بشمول ٹینڈن کے کسی مسئلے کی سرجری کے بعد، تو اس مسئلے پر شک کرنا چاہیے، کیونکہ صرف ٹینڈن کا آپریشن کرنے سے اس کے اوپر ہلنے والا ہڈی کا ٹکڑا پرسکون نہیں ہوگا۔
سرجری کے بعد صحت یابی آہستہ آہستہ ہوتی ہے۔ آپ اپنے فزیوتھراپسٹ کے ساتھ کام کریں گے، پہلے حرکت بحال کریں گے اور پھر طاقت، اور سر سے اوپر وزن اٹھانے کی صلاحیت ہفتوں سے مہینوں میں آہستہ آہستہ واپس آئے گی۔ مقصد ایک ایسا کندھا ہے جو روزمرہ زندگی کا ساتھ دے سکے، اور بازو اٹھاتے وقت وہ تیز درد نہ ہو جس کی وجہ سے آپ ہمارے پاس آئے تھے۔
اگر آپ کی کوئی انگلی، ہاتھ یا بازو گرم، سرخ، سوجا ہوا اور دردناک ہو جائے، خاص طور پر بخار کے ساتھ، تو اسی دن ہسپتال کی ایمرجنسی جائیں۔ اس کے لیے فیملی ڈاکٹر کے ریفرل کی ضرورت نہیں۔
ڈاکٹر کو کب دکھائیں
اس طرح کی ہڈی کی بناوٹ والے زیادہ تر لوگوں کو کبھی علاج کی ضرورت نہیں پڑتی، لیکن اگر آپ کے کندھے کا درد ٹھیک نہیں ہو رہا، ہفتوں کے دوران بدتر ہو رہا ہے، رات کو آپ کو جگاتا ہے، یا آپ کو کام کرنے یا بازو استعمال کرنے سے روکتا ہے، تو اپنے فیملی ڈاکٹر کو دکھائیں یا کسی ماہر سے معائنے کی درخواست کریں۔ اگر درد کندھے کے سامنے اور پہلو میں ہو، سر سے اوپر کے کاموں سے بڑھ جائے، یا اس طرف لیٹنے پر بار بار آپ کو جگاتا ہو، تو جلد معائنہ کروائیں۔ معائنہ کروانا اس صورت میں بھی فائدہ مند ہے اگر کندھے کے اوپر دکھنے والی جگہ کو دبانے پر درد ہو، اگر بازو کو پہلو کی طرف باہر اٹھاتے یا باہر کی طرف گھماتے وقت یہ کمزور محسوس ہو، یا اگر بازو اٹھاتے ہوئے راستے کے درمیان میں کندھے میں درد ہو۔ ان علامات والے کم عمر بالغوں کا، جنہیں کوئی چوٹ نہ لگی ہو، اس مسئلے کے لیے معائنہ ہونا چاہیے، خاص طور پر اگر فزیوتھراپی، کھیل سے آرام یا انجکشن سے فائدہ نہ ہوا ہو۔ اگر کوئی انگلی، ہاتھ یا بازو گرم، سرخ، سوجا ہوا اور دردناک ہو جائے، خاص طور پر بخار کے ساتھ، تو اسی دن ہسپتال کی ایمرجنسی جائیں؛ اس کے لیے فیملی ڈاکٹر کے ریفرل کی ضرورت نہیں۔
مزید تفصیل
Advanced reading: the deeper science (optional)
یہ حصہ اس سے آگے جاتا ہے جتنا آپ کو اپنے علاج کے فیصلوں کے لیے جاننے کی ضرورت ہے۔ اوس ایکرومیالی کے بارے میں یہ اضافی مطالعہ اس لیے فائدہ مند ہے کہ یہ لوگوں کی ایک قابل ذکر اقلیت میں جسم کی بناوٹ کا ایک عام فرق (anatomical variant) ہے، عام طور پر کوئی تکلیف نہیں دیتا، اور اکثر کندھے کے ایسے درد کا ذمہ دار ٹھہرایا جاتا ہے جس کا یہ ذمہ دار نہیں ہوتا۔
یہ کیا ہے، اور کتنا عام ہے
ایکرومیون، یعنی کندھے کے اوپر ہڈی کی چھت، ہڈی بننے کے کئی الگ الگ مراکز سے بنتا ہے جو عام طور پر نوعمری کے آخری برسوں یا بیس کی دہائی کے شروع میں آپس میں جڑ جاتے ہیں۔ کچھ لوگوں میں ان میں سے ایک نہیں جڑتا، اور ایک مستقل ریشے دار جوڑ باقی رہ جاتا ہے۔ یہی اوس ایکرومیالی ہے، اور یہ بعد میں پیدا نہیں ہوتا بلکہ نوجوانی سے موجود ہوتا ہے۔
یہ کتنا عام ہے، یہ مختلف آبادیوں میں مختلف ہوتا ہے۔ 6,842 مریضوں پر کئی مراکز کی ایک تحقیق میں پایا گیا کہ اوس ایکرومیالی کا تعلق روٹیٹر کف کی چوٹوں سے ہے، کہ جس جاپانی آبادی کا مطالعہ کیا گیا اس میں یہ غیر ایشیائی آبادیوں کی نسبت کم عام تھا، اور یہ کہ ٹکڑے کا سائز عموماً چھوٹا تھا [1]۔
روٹیٹر کف کی چوٹ سے اس تعلق کو غور سے پڑھنا چاہیے۔ اس سے یہ ثابت ہوتا ہے کہ یہ دونوں اتفاق سے زیادہ کثرت سے ایک ساتھ پائے جاتے ہیں، یہ نہیں کہ اوس ایکرومیالی ٹینڈن کے پھٹنے کا سبب بنتا ہے۔ قابل فہم طریقۂ کار دونوں طرف جا سکتا ہے: نہ جڑا ہوا ٹکڑا ڈیلٹائیڈ (deltoid) پٹھے کے کھنچاؤ سے تھوڑا سا ہلتا ہے، جس سے اس کے نیچے کے ٹینڈن میں جلن (irritation) پیدا ہو سکتی ہے — یا کندھے کی وہی حرکیات جو روٹیٹر کف کی بیماری کا امکان بڑھاتی ہیں، ایک غیر مستحکم ٹکڑے کو بھی تکلیف دہ بنا دیتی ہیں۔
کیا درد اسی سے ہے، یہی اصل سوال ہے
چونکہ یہ ایکسرے اور اسکین پر نظر آتا ہے، مستقل ہوتا ہے اور غیر معمولی دکھائی دیتا ہے، اس لیے اوس ایکرومیالی آسانی سے کندھے کے درد کی بتائی جانے والی وجہ بن جاتا ہے۔ زیادہ تر خاموش ہوتے ہیں، اور جن لوگوں میں یہ ہوتا ہے ان میں سے زیادہ تر کو کبھی پتا بھی نہیں چلتا۔
تکلیف دینے والے اوس ایکرومیالی کی پہچان یہ ہے کہ دبانے پر درد عین ٹکڑے کے اوپر ہوتا ہے، اسے دبانے سے درد دوبارہ پیدا ہوتا ہے، اور جہاں تشخیص کے لیے انجکشن استعمال کیا جائے، وہاں آرام خاص طور پر اسی جوڑ میں انجکشن لگانے سے ملتا ہے، نہ کہ اس کے نیچے ایکرومیون کے نیچے کی جگہ (subacromial space) میں انجکشن سے۔ ان علامات کی غیر موجودگی میں، اس دریافت کو اتفاقی سمجھنا ہی بہتر ہے۔
اس کی ذیلی اقسام روایتی طور پر اس بنیاد پر درجہ بند کی جاتی ہیں کہ جڑنے کی کون سی جگہ متاثر ہے [2]، جو سرجری کے لحاظ سے اہم ہے کیونکہ ہلنے والے ٹکڑے کا سائز طے کرتا ہے کہ اسے نکالا جا سکتا ہے یا اسے جمانا ضروری ہے۔
یہ کندھے کی دوسری سرجری کو کیوں پیچیدہ بناتا ہے
اوس ایکرومیالی کی عملی اہمیت اکثر اس کی اپنی علامات سے کم، اور اس بات سے زیادہ ہوتی ہے کہ یہ کسی اور مسئلے کے لیے منصوبہ بند آپریشنوں پر کیا اثر ڈالتا ہے۔
ڈیلٹائیڈ پٹھا ایکرومیون سے جڑا ہوتا ہے، اس لیے نہ جڑا ہوا ٹکڑا اس کھنچاؤ کو ایک ہلنے والے جوڑ کے پار منتقل کرتا ہے۔ نچلی سطح سے ہڈی نکالنا، جیسا کہ ایکرومیوپلاسٹی (acromioplasty، ایکرومیون کی نچلی سطح سے ہڈی چھیلنا) میں ہوتا ہے، ایک پہلے سے غیر مستحکم ٹکڑے کو پتلا کر دیتا ہے، اور ایک بے علامت فرق کو تکلیف دہ بنا سکتا ہے یا ہڈی کے نہ جڑنے (nonunion) کا سبب بن سکتا ہے۔ یہی سب سے مضبوط وجہ ہے کہ آپریشن سے پہلے کے ایکسرے اور اسکین پر اسے پہچانا جائے: اس کا علاج کرنے کے لیے نہیں، بلکہ اسے غیر مستحکم ہونے سے بچانے کے لیے۔
جہاں اس کا علاج ضروری ہو، وہاں انتخاب چھوٹے ٹکڑے کو نکال دینے اور بڑے ٹکڑے کو جمانے کے درمیان ہوتا ہے، اور اس جوڑ کے پار ٹکڑے کو جمانا مشکل سمجھا جاتا ہے، ٹکڑا پتلا ہوتا ہے، ڈیلٹائیڈ اسے مسلسل کھینچتا رہتا ہے، اور ہڈی کے نہ جڑنے کی شرح قابل ذکر ہوتی ہے۔ یہ مشکل خود اس بات کی ایک وجہ ہے کہ آپریشن کرنے سے پہلے یہ یقین کر لیا جائے کہ درد واقعی اوس ایکرومیالی سے ہی آ رہا ہے۔
حوالہ جات
[1] Kozono N, Nishii A, Ishitani E, Mizuki Y, Kimura T, Yamamoto S, et al. Prevalence and factors associated with os acromiale: a multicenter study. JSES Int. 2025;9(5):1541-5. https://doi.org/10.1016/j.jseint.2025.05.015
[2] Boehm TD, Matzer M, Brazda D, Gohlke FE. Os acromiale associated with tear of the rotator cuff treated operatively. Review of 33 patients. J Bone Joint Surg Br. 2003;85(4):545-9. https://doi.org/10.1302/0301-620X.85B4.13634
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- A symptomatic, unstable os acromiale is relatively rare despite the radiographic appearance of an os acromiale being not uncommon in patients presenting with shoulder pain [1].
- An os acromiale should always be suspected in cases of failed rotator cuff surgery or ongoing shoulder pain after failed treatment [2].
- The prevalence of os acromiale was 2.13% in Thai patients with shoulder problems who required MRI evaluation [3].
- Os acromiale is associated with rotator cuff injuries [7].
- The greater the distance of the acromioclavicular joint from the anterior edge of the acromion, the higher the likelihood of an os acromiale [15].
- The authors recommend that the acromion be carefully examined roentgenographically prior to operation in any patient with a rotator cuff tear [10].
- Surgical treatment is usually not indicated for os acromiale in the professional tennis player [9].
- Operative management of a symptomatic os acromiale that has failed initial nonoperative treatment leads to decreased symptoms and improvement in clinical outcomes [4].
- Surgical options for symptomatic os acromiale include arthroscopic sub-total excision, arthroscopic subacromial decompression of stable fragments, and open reduction and internal fixation of unstable fragments [13].
- Patients with a united os acromiale had a significantly better functional outcome as measured by the Constant score (P = .0169) [12].
- The advantages of arthroscopic internal fixation include improved visualization of the undersurface of the acromion, allowing excellent reduction, the possibility of treating concomitant shoulder pathologies, and to avoid increased morbidity of the open approach [14].
- Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients but resolves spontaneously over time in the majority of patients [5].
- The presence of os acromiale does not appear to have a negative impact on the clinical outcomes after surgery and rTSA remains a safe and effective treatment option [6].
- The outcome of RTSA does not seem to be negatively affected by the presence of an os acromiale [11].
- Ipsilateral os acromiale may be a relative contraindication to the clavicle hook plate [16].
Anatomy & Pathophysiology
Bony Anatomy
- The acromion has three ossification centers: the metacromion (base), the mesoacromion (middle), and the preacromion (tip) [38].
- Failure of fusion of the acromial ossification centers results in os acromiale [38].
- Os acromiale is defined as incomplete fusion of secondary ossification centers, most commonly between the mesoacromion and meta-acromion [49].
- The unfused segment in os acromiale is most commonly the meso-acromion, a configuration often termed a meso-type os acromiale [22].
- The acromion, coracoacromial ligament, and coracoid process form the coracoacromial arch, a rigid bony-ligamentous structure that imparts stability to the shoulder girdle [35].
- The rotator cuff, subacromial bursa, and subdeltoid bursa pass underneath the coracoacromial arch [35].
- The scapula is attached to the axial skeleton by the acromioclavicular and sternoclavicular joints [37].
- The acromion is a flattened bony process that curves forwards from the scapular spine [37].
Prevalence and Associations
- In Thai patients with shoulder problems who required MRI evaluation, the prevalence of os acromiale was 2.13% [3].
- The radiographic appearance of an os acromiale is not uncommon in patients presenting with shoulder pain [1].
- A symptomatic, unstable os acromiale is relatively rare [1].
Pathophysiology
- Most diagnoses of os acromiale are made incidentally on axillary view radiographs of the shoulder [22].
- Primary shoulder pain is usually unrelated to the unfused os acromiale [22].
- When an os acromiale drives symptoms, the two principal causes are motion at the non-union site or an impingement-type syndrome resulting from flexion of the os fragment during deltoid contraction and arm elevation [22].
- Pain from an os acromiale due to these mechanisms has been reported in a variety of sports, particularly among throwing athletes and swimmers [22].
- Previously stable non-unions can become unstable following an episode of blunt trauma to the region [22].
- The synchondrosis of an os acromiale can be injured following trauma [24].
- Extrinsic impingement occurs when the space available for the rotator cuff is diminished, with examples including acromial fracture or pathologic os acromiale [62].
Epidemiology and Prevalence
- Liberson reviewed 1800 shoulder girdles and identified an incidence of os acromiale of 1.4% [21].
- The lesion was bilateral in 62% of patients in Liberson's review of 1800 shoulder girdles [21].
Associated Pathology and Risk Factors
- The greater the distance of the AC joint from the anterior edge of the acromion, the higher the likelihood of an os acromiale [15].
Diagnostic Considerations
- Awareness of the os acromiale in the young athlete, appropriate clinical examination, and image studies are crucial to confirm diagnosis [19].
- Appropriate radiographic investigation including axillary views is emphasized for the diagnosis of os acromiale injuries [24].
Clinical Presentation
- An os acromiale should always be suspected in cases of failed rotator cuff surgery [2].
- An os acromiale should always be suspected in cases of ongoing shoulder pain after failed treatment [2].
- Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients [5].
- Postoperative local tenderness at the os acromiale resolves spontaneously over time in the majority of patients [5].
- The lesion was bilateral in 62% of patients in Liberson's review [21].
- The unfused segment is most commonly the meso-acromion [22].
- Any primary shoulder pain is usually unrelated to the unfused os [22].
- If the os acromiale is driving symptoms, one principle cause is motion at the non-union site [22].
- If the os acromiale is driving symptoms, another principle cause is an impingement-type syndrome resulting from flexion of the os fragment during deltoid contraction and arm elevation [22].
- Pain from an os acromiale by the mechanism of impingement has been reported in a variety of sports [22].
- Pain from an os acromiale by the mechanism of impingement has been reported in particular among throwing athletes and swimmers [22].
- Meta–os acromiale is the rarest subtype of os acromiale [23].
Investigations
Prevalence and Demographics
- Liberson reviewed 1800 shoulder girdles and identified an incidence of os acromiale of 1.4%, with the lesion being bilateral in 62% of patients [21].
- A multicenter study aimed to determine the prevalence of and factors associated with os acromiale in the Japanese population [8].
- The radiographic appearance of an os acromiale is not uncommon in patients presenting with shoulder pain, but a symptomatic, unstable os acromiale is relatively rare [1].
Radiographic Evaluation
- The acromion should be carefully examined roentgenographically prior to operation in any patient with a rotator cuff tear [10].
- Appropriate radiographic investigation for os acromiale includes axillary views [24].
- Awareness of the os acromiale in the young athlete requires appropriate clinical examination and image studies to confirm diagnosis [19].
- The standard shoulder series should include orthogonal views of the shoulder, including a true AP view in the scapular plane, an AP view, an axillary view, and a scapular Y view [60].
- The scapular Y view provides visualization of the coracoacromial arch and can reveal coracoacromial spurs, which have been closely associated with the presence of rotator cuff pathology [60].
- The scapular Y view can also show acromial shape [60].
- At least two X-ray views should be obtained for shoulder imaging: an anteroposterior in the plane of the glenoid and an axillary projection with the arm in abduction to show the relationship of the humeral head to the glenoid [52].
- The purpose of imaging of the shoulder is to help establish the diagnosis, determine the severity of the pathoanatomy, assist in surgical planning, and enable the surgeon to illustrate the condition of the shoulder to the patient [30].
- Standardized plain films are almost always sufficient to garner the information needed for shoulder evaluation [30].
- The first key view for shoulder imaging is the anteroposterior (AP) in the plane of the scapula taken so that the x-ray beam passes through the glenohumeral joint [30].
- The second key view for shoulder imaging is the axillary view taken with the arm in the functional position of elevation in the plane of the scapula and oriented so that both the spinoglenoid notch and the scapular neck are visible [30].
- The axillary view is referred to as the "truth view" because it demonstrates the glenohumeral relationships in the functional position of elevation [30].
- CT scans have the disadvantage of being taken with the arm in the adducted position, unlike the axillary truth view [30].
- The temptation to "overimage" should be resisted, obtaining only the scans or reconstructions that are necessary for the care of the patient [30].
Magnetic Resonance Imaging
- In Thai patients with shoulder problems, os acromiale was identified via Magnetic Resonance Imaging evaluation [3].
- MRI is useful to identify labral tears and rotator cuff tears, although the accuracy for these is enhanced by combining the scan with arthrography [52].
- MRI is the modality of choice for evaluating the rotator cuff, biceps, and subacromial/subdeltoid bursa [59].
- T2-weighted MRI provides better visualization of full thickness rotator cuff tears [59].
- MR arthrography is considered the benchmark for evaluation for labral tears and rarely is indicated for evaluation of rotator cuff pathology [59].
- When MRI or MR arthrography is contraindicated, CT arthrography is indicated [59].
Ultrasonography
- Ultrasonography is a simple and accurate test for identifying rotator cuff tears and calcific tendinitis [52].
- Ultrasonography is a low-cost alternative to MRI and arthrography for evaluating both skeletal and soft-tissue structures of the shoulder [59].
- Ultrasonography can provide immediate, real-time visualization of the rotator cuff, biceps tendon, and calcific deposits [59].
- Ultrasonography can be used to measure the subacromial space and detect atrophy of rotator cuff muscles [59].
- Ultrasonography is highly operator dependent and is not as useful for evaluating labral tears or rotator cuff tears that are very small or larger than 3 cm [59].
- The most commonly performed joint examination using ultrasonography is the shoulder examination, and accuracy depends on the skill of the scanner operator and an awareness of pitfalls that are encountered [50].
Clinical Associations and Diagnostic Implications
- The synchondrosis of an os acromiale can be injured following trauma, though rarely [24].
Treatment
Non-Operative
- A symptomatic os acromiale in a competitive female fastball pitcher was treated successfully with open reduction and internal fixation [27].
Operative
- Symptomatic unstable os acromiale can be effectively treated with autogenous bone-grafting and internal fixation using a rigid tension-band construct and cannulated screws, which results in a high rate of union [65].
- This new arthroscopic technique of fixation of os acromiale with absorbable screws provides promising clinical, cosmetic, and radiologic results with high patient satisfaction [28].
- After 3 to 6 years of follow-up, all 6 shoulders were rated as excellent according to criteria similar to that of the American Shoulder and Elbow Surgeons [18].
- Modified arthroscopic subacromial decompression can provide results similar to standard arthroscopic subacromial decompression for routine impingement [25].
- Meta–os acromiale is the rarest subtype of os acromiale, and special consideration must be given to the type of tension-band construct used to achieve adequate compression and fixation [23].
Complications
Post-operative and Surgical Complications
- Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients following reverse total shoulder arthroplasty [5].
Diagnostic and Clinical Implications
Pathophysiology and Mechanisms of Symptom
- Pain from an os acromiale by the mechanism of impingement has been reported in a variety of sports, in particular among throwing athletes and swimmers [22].
Recovery
- After 3 to 6 years of follow-up, all 6 shoulders treated with osteosynthesis of an unstable mesoacromion were rated as excellent according to criteria similar to that of the American Shoulder and Elbow Surgeons [18].
- At a two to five year follow-up, all patients treated for fusion of the unstable mesoacromion had fused [69].
Key Evidence
- [L4] While the radiographic appearance of an os acromiale is not uncommon in patients presenting with shoulder pain, a symptomatic, unstable os acromiale is relatively rare. [1] (10.1097/00132589-200412000-00006)
- [L4] An os acromiale should always be suspected in cases of failed rotator cuff surgery or ongoing shoulder pain after failed treatment. [2] (10.1097/00132589-200609000-00006)
- [L3] In Thai patients with shoulder problems who required MRI evaluation, the prevalence of os acromiale was 2.13%. [3] (10.1177/23259671221078806)
- [L4] Operative management of a symptomatic os acromiale that has failed initial nonoperative treatment leads to decreased symptoms and improvement in clinical outcomes. [4] (10.1016/j.jse.2019.05.047)
- [L3] Postoperative local tenderness at the os acromiale can be expected in 1 out of 4 patients but resolves spontaneously over time in the majority of patients. [5] (10.1177/2325967120965131)
- [L4] The presence of os acromiale does not appear to have a negative impact on the clinical outcomes after surgery and rTSA remains a safe and effective treatment option. [6] (10.1016/j.xrrt.2025.01.002)
- [L3] The study supports previous findings that os acromiale is associated with rotator cuff injuries. [7] (10.1016/j.jseint.2025.05.015)
- [L3] This multicenter study aimed to determine the prevalence of and factors associated with os acromiale in the Japanese population. [8] (10.1016/j.jse.2025.01.008)
- [L4] Surgical treatment is usually not indicated for os acromiale in the professional tennis player. [9] (10.1177/2325967118773723)
- [L4] The authors recommend that the acromion be carefully examined roentgenographically prior to operation in any patient with a rotator cuff tear. [10] (10.2106/00004623-198466080-00029)
- [L4] The outcome of RTSA does not seem to be negatively affected by the presence of an os acromiale. [11] (10.1016/j.jse.2017.02.012)
- [L4] Patients with a united os acromiale had a significantly better functional outcome as measured by the Constant score (P = .0169). [12] (10.1016/s1058-2746(98)90008-8)
- [L5] Surgical options for symptomatic os acromiale include arthroscopic sub-total excision, arthroscopic subacromial decompression of stable fragments, and open reduction and internal fixation of unstable fragments. [13] (10.5435/jaaos-d-17-00011)
- [L5] The advantages of this technique are improved visualization of the undersurface of the acromion, allowing excellent reduction, the possibility of treating concomitant shoulder pathologies, and to avoid increased morbidity of the open approach. [14] (10.1097/bte.0000000000000191)
- [L4] Our data suggest that the greater the distance of the AC joint from the anterior edge of the acromion, the higher the likelihood of an os acromiale. [15] (10.1067/mse.2003.128136)
- [L4] Ipsilateral os acromiale may be a relative contraindication to the clavicle hook plate. [16] (10.1186/s12891-021-04841-1)
- [L4] After 3 to 6 years of follow-up, all 6 shoulders were rated as excellent according to criteria similar to that of the American Shoulder and Elbow Surgeons. [18] (10.1016/s1058-2746(99)90004-6)
- [L4] Awareness of the os acromiale in the young athlete, appropriate clinical examination, and image studies are crucial to confirm diagnosis. [19] (10.1016/j.jseint.2020.02.008)
- [L4] [22] (10.1302/2058-5241.4.180100)
- [L4] Meta–os acromiale is the rarest subtype of os acromiale, and special consideration must be given to the type of tension-band construct used to achieve adequate compression and fixation. [23] (10.1177/03635465211028238)
- [L4] This case highlights that the synchondrosis of an os acromiale can be injured following trauma, though rarely, and emphasizes the need for appropriate radiographic investigation including axillary views and a flexible surgical approach. [24] (10.1016/j.jse.2008.02.012)
- [L5] Increased awareness of the diagnosis and improved techniques have shown that modified arthroscopic subacromial decompression can provide results similar to standard arthroscopic subacromial decompression for routine impingement. [25] (10.1097/00132589-200206000-00003)
- [L4] A symptomatic os acromiale in a competitive female fastball pitcher was treated successfully with open reduction and internal fixation. [27] (10.1177/0363546506288305)
- [L4] This new arthroscopic technique of fixation of os acromiale with absorbable screws provides promising clinical, cosmetic, and radiologic results with high patient satisfaction. [28] (10.1016/j.jse.2011.12.011)
- [L4] Symptomatic unstable os acromiale can be effectively treated with autogenous bone-grafting and internal fixation using a rigid tension-band construct and cannulated screws, which results in a high rate of union. [65] (10.2106/00004623-199809000-00011)
- [L4] At a two to five year followup all had fused. [69] (10.1016/s1058-2746(95)80192-8)
References
[1] Treatment of the Symptomatic Os Acromiale. Techniques in Shoulder and Elbow Surgery. 2004. DOI: 10.1097/00132589-200412000-00006
[2] Management of Os Acromiale. Techniques in Shoulder and Elbow Surgery. 2006. DOI: 10.1097/00132589-200609000-00006
[3] Prevalence of Os Acromiale in Thai Patients With Shoulder Problems: A Magnetic Resonance Imaging Study. Orthopaedic Journal of Sports Medicine. 2022. DOI: 10.1177/23259671221078806
[4] Os acromiale: systematic review of surgical outcomes. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2019.05.047
[5] Os Acromiale in Reverse Total Shoulder Arthroplasty: A Cohort Study. Orthopaedic Journal of Sports Medicine. 2020. DOI: 10.1177/2325967120965131
[6] Clinical implications of reverse total shoulder arthroplasty with an os acromiale: a systematic review. JSES Reviews, Reports, and Techniques. 2025. DOI: 10.1016/j.xrrt.2025.01.002
[7] Prevalence and factors associated with os acromiale: a multicenter study. JSES International. 2025. DOI: 10.1016/j.jseint.2025.05.015
[8] The prevalence and associated factors of os acromiale: a multicenter study. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2025.01.008
[9] Os Acromiale in Professional Tennis Players. Orthopaedic Journal of Sports Medicine. 2018. DOI: 10.1177/2325967118773723
[10] Rotator cuff tears associated with os acromiale.. The Journal of Bone & Joint Surgery. 1984. DOI: 10.2106/00004623-198466080-00029
[11] Reverse shoulder arthroplasty in patients with os acromiale. Journal of Shoulder and Elbow Surgery. 2017. DOI: 10.1016/j.jse.2017.02.012
[12] Transacromial approach to obtain fusion of unstable os acromiale. Journal of Shoulder and Elbow Surgery. 1998. DOI: 10.1016/s1058-2746(98)90008-8
[13] Symptomatic, Unstable Os Acromiale. Journal of the American Academy of Orthopaedic Surgeons. 2018. DOI: 10.5435/jaaos-d-17-00011
[14] Arthroscopic Internal Fixation of Symptomatic Os Acromiale. Techniques in Shoulder & Elbow Surgery. 2020. DOI: 10.1097/bte.0000000000000191
[15] Relationship between os acromiale and acromioclavicular joint anatomic position. Journal of Shoulder and Elbow Surgery. 2003. DOI: 10.1067/mse.2003.128136
[16] Os acromiale may be a contraindication of the clavicle hook plate: case reports and literature review. BMC Musculoskeletal Disorders. 2021. DOI: 10.1186/s12891-021-04841-1
[18] Successful osteosynthesis of an unstable mesoacromion in 6 shoulders: A new technique. Journal of Shoulder and Elbow Surgery. 1999. DOI: 10.1016/s1058-2746(99)90004-6
[19] The unstable os acromiale: a cause of pain in the young athlete. JSES International. 2020. DOI: 10.1016/j.jseint.2020.02.008
[21] Types of os acromiale according to Liberson. 2006.
[22] Os acromiale: a review of its incidence, pathophysiology, and clinical management. EFORT Open Reviews. 2019. DOI: 10.1302/2058-5241.4.180100
[23] Rare Symptomatic Meta–Os Acromiale in an Athlete. The American Journal of Sports Medicine. 2021. DOI: 10.1177/03635465211028238
[24] Fracture of an os acromiale with associated rupture of the coracoclavicular ligaments. Journal of Shoulder and Elbow Surgery. 2008. DOI: 10.1016/j.jse.2008.02.012
[25] Arthroscopic Management of the Mesoacromion. Techniques in Shoulder and Elbow Surgery. 2002. DOI: 10.1097/00132589-200206000-00003
[27] Surgical Stabilization of Os Acromiale in a Fast-Pitch Softball Pitcher. The American Journal of Sports Medicine. 2006. DOI: 10.1177/0363546506288305
[28] Arthroscopically assisted internal fixation of the symptomatic unstable os acromiale with absorbable screws. Journal of Shoulder and Elbow Surgery. 2012. DOI: 10.1016/j.jse.2011.12.011
[30] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Radiographic Evaluation.
[35] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > ANATOMY.
[37] Rockwood And Green S Fractures In Adults. 29: Principles of Nonunion and Bone Defect Treatment > Applied Anatomy Related to Scapular Fractures.
[38] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Shoulder, Arm, and Elbow > I. Shoulder.
[49] Miller S Review Of Orthopaedics. Genetics of musculoskeletal conditions and abnormalities are summarized in Table 1.27 > UPPER EXTREMITY > SHOULDER.
[50] Orthopaedic Knowledge Update Sports Medicine 6. Diagnostic Ultrasonography and Ultrasonography-Guided Procedures > Annotated References.
[52] Apley And Solomon S Concise System Of Orthopaedics And Trauma. INVESTIGATION.
[59] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Shoulder Anatomy and Biomechanics, Clinical Evaluation, Imaging > Clinical Evaluation > Imaging.
[60] Aaos Comprehensive Orthopaedic Review 3. Imaging of the Shoulder and Elbow > I. Shoulder.
[62] Campbell S Operative Orthopaedics 4 Volume Set. ANTERIOR CRUCIATE LIGAMENT RECONSTRUCTION WITH BONE-PATELLAR TENDON-BONE GRAFT > Developmental Stages of Impingement Syndrome.
[65] The Treatment of Symptomatic Os Acromiale. The Journal of Bone & Joint Surgery*. 1998. DOI: 10.2106/00004623-199809000-00011
[69] Successful fusion of the unstable mesoacromion: Technique and report of five cases. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80192-8