Patients › General-Health
اعصاب کے ٹیسٹ اور نرو کنڈکشن اسٹڈیز
What nerve conduction studies and EMG are, why they are done for carpal tunnel and other nerve problems, what to expect, and how accurate they are.
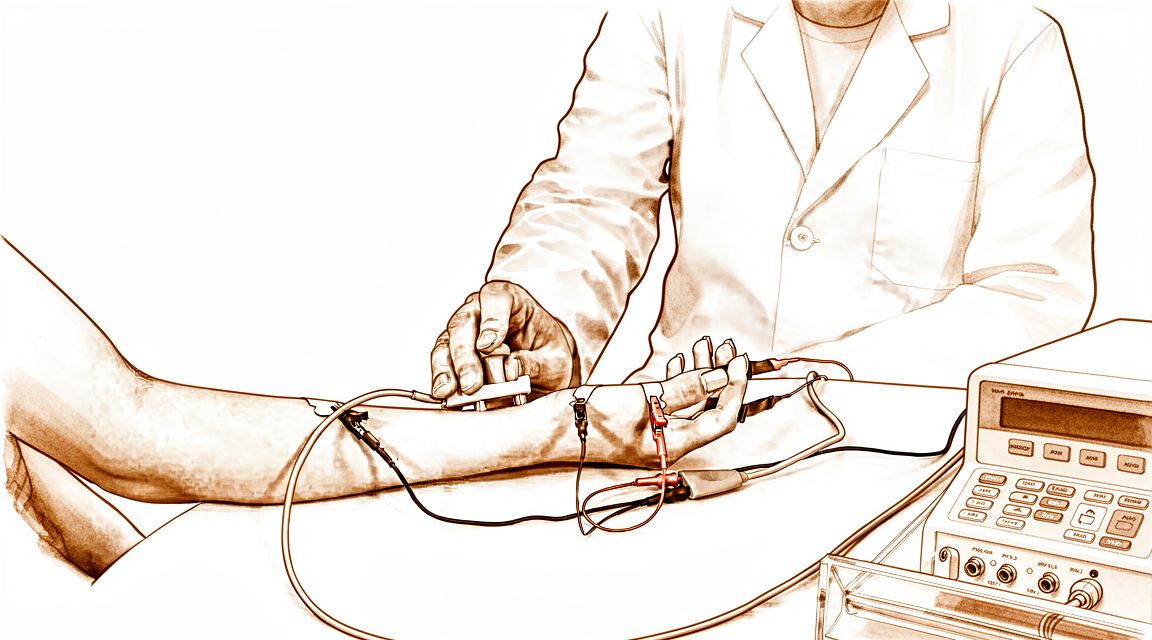
یہ کیا ہے
اعصاب کے ٹیسٹ ناپتے ہیں کہ آپ کے اعصاب (nerves) برقی سگنل کتنی اچھی طرح لے جاتے ہیں۔ اعصاب کے کام کو جانچنے کے دو برقی طریقے ہیں، اور دونوں عملی طور پر مفید ثابت ہوئے ہیں [1]۔ بنیادی ٹیسٹ کو نرو کنڈکشن اسٹڈی (nerve conduction study) کہا جاتا ہے۔ ایک چھوٹا آلہ آپ کے عصب میں ایک ننھی سی برقی لہر (pulse) بھیجتا ہے اور ریکارڈ کرتا ہے کہ سگنل کتنی تیزی سے سفر کرتا ہے۔ اگر کوئی عصب دبا ہوا ہو یا اسے نقصان پہنچا ہو تو سگنل سست یا کمزور ہو جاتا ہے۔
یہ ٹیسٹ سب سے زیادہ کارپل ٹنل سنڈروم (کلائی میں عصب کا دبنا) کے لیے کیے جاتے ہیں، جس میں آپ کی کلائی کے اگلے حصے میں موجود عصب دباؤ میں ہوتا ہے۔ اس بیماری کی سرجری سے پہلے کے جائزے میں انہیں ایک لازمی حصہ سمجھا جاتا ہے [2]۔ زیادہ تر ڈاکٹر اس تصدیق کے بغیر آپریشن نہیں کرتے [3]۔ یہ ٹیسٹ اعصاب کے دوسرے مسائل میں بھی مدد دے سکتے ہیں، جیسے کہنی کے مقام پر عصب پر دباؤ (کیوبیٹل ٹنل سنڈروم، cubital tunnel syndrome) [4]۔
عموماً اسی ملاقات میں آپ کا ایک دوسرا ٹیسٹ بھی ہوتا ہے۔ اس کے لیے چند پٹھوں میں ایک باریک سوئی لگائی جاتی ہے۔ یہ جانچتا ہے کہ پٹھے ان تک پہنچنے والے اعصاب کا کتنی اچھی طرح جواب دیتے ہیں۔ ان دونوں ٹیسٹوں کو مل کر الیکٹروڈائیگنوسٹک اسٹڈیز (electrodiagnostic studies) کہا جاتا ہے، جس کا سیدھا سا مطلب ہے ایسے ٹیسٹ جو اعصاب اور پٹھوں کو جانچنے کے لیے بجلی استعمال کرتے ہیں۔
یہ ٹیسٹ اس لیے کام کرتے ہیں کہ اعصاب اسی طرح سگنل لے جاتے ہیں جیسے تاریں بجلی کا کرنٹ لے جاتی ہیں۔ دبا ہوا عصب ایک دبی ہوئی کیبل کی طرح برتاؤ کرتا ہے، اس لیے اس میں سے گزرنے والا سگنل دیر سے پہنچتا ہے یا کمزور ہو جاتا ہے۔ نتائج سے یہ پیمائش ملتی ہے کہ عصب کتنا متاثر ہے، اور یہ بیماری کی مجموعی شدت کا بہترین دستیاب اشارہ ہے [5]۔ ان ٹیسٹوں کی اہمیت درست تشخیص کرنے اور یہ اندازہ لگانے میں ہے کہ بیماری کتنی شدید ہے، نہ کہ یہ پیش گوئی کرنے میں کہ سرجری کے بعد آپ کیسا محسوس کریں گے [6]۔
ایک بات جاننے کے قابل ہے: ٹیسٹ کا نارمل آنا کارپل ٹنل سنڈروم کو خارج نہیں کرتا، کیونکہ عصب پر دباؤ آتا جاتا رہ سکتا ہے۔
کیا یہ مؤثر ہے؟
سچا جواب یہ ہے کہ یہ ٹیسٹ کچھ کاموں میں اچھے ہیں اور کچھ میں محدود ہیں۔ کارپل ٹنل سنڈروم کی جانچ میں یہ ایک مفید اضافہ ہیں، خاص طور پر جب معیاری ٹیسٹ نارمل آئیں [7]۔ ایک خاص اعصابی ٹیسٹ پر ہونے والی ایک تحقیق میں پایا گیا کہ اس نے 69 فیصد کیسز میں بیماری پکڑ لی، اور ہر مثبت نتیجہ درست تھا۔ جب اس ٹیسٹ کو احساس ناپنے کے ایک اور طریقے کے ساتھ ملایا گیا تو اس نے 84 فیصد کیسز پکڑ لیے [8]۔
یہ ٹیسٹ سرجری سے پہلے تشخیص کی تصدیق میں بھی مدد دیتے ہیں۔ جب آپ کی علامات اور معائنے میں ملنے والی نشانیاں عصب پر ہلکے سے درمیانے دباؤ کی طرف اشارہ کریں اور سرجری پر غور کیا جا رہا ہو، تو اضافی ٹیسٹ اس امکان کو بڑھا سکتا ہے کہ سرجری کسی حقیقی، قابلِ علاج مسئلے پر کی جائے [9]۔ ایک تحقیق میں ان لوگوں کی تعداد جن کی تشخیص صرف علامات کی بنیاد پر ہوئی (73 فیصد) اور ان لوگوں کی تعداد جن کی تصدیق ان ٹیسٹوں اور الٹراساؤنڈ سے ہوئی (51 فیصد) کے درمیان بڑا فرق پایا گیا [10]۔ یہی فرق اس بات کی وجہ ہے کہ ٹیسٹ کیوں اہم ہے: اس سے یہ الگ ہو جاتا ہے کہ کس کو واقعی ایسا اعصابی مسئلہ ہے جس میں سرجری مدد کر سکتی ہے۔
ان کی کچھ حدود بھی ہیں۔ ان ٹیسٹوں کا معیار ٹیسٹ کرنے والوں کے درمیان مختلف ہوتا ہے، اور کچھ رپورٹیں دوسروں سے زیادہ تفصیل دیتی ہیں [11]۔ انہیں پڑھنے کے معیارات (criteria) کو بھی زیادہ واضح طور پر طے کرنے کی ضرورت ہے، تاکہ تشخیص درست ہو اور جب سرجری کی ضرورت نہ ہو تو سرجری نہ کی جائے [12]۔ اور یہ ٹیسٹ آپ کو سب کچھ نہیں بتا سکتے۔ یہ عصب کو ناپتے ہیں، آپ کی علامات کو نہیں۔
کچھ نتائج ملے جلے ہیں۔ اسٹیرائیڈ انجکشن کے بعد ٹیسٹ کے نتائج میں ہونے والی تبدیلیاں دو سال پر نمایاں نہیں تھیں [13]۔ دوسری طرف، انجکشن سے اچھا فائدہ ہونا اس بات کا ایک مددگار اشارہ ہے کہ سرجری کیسی رہ سکتی ہے [14]۔ ٹیسٹوں کی ایک پیمائش، جسے ڈسٹل موٹر لیٹنسی (distal motor latency) کہتے ہیں اور جس کا سیدھا سا مطلب ہے کہ سگنل کو پٹھے تک پہنچنے میں کتنا وقت لگتا ہے، سرجری کے بعد آپ کی حالت کی پیش گوئی میں کچھ اہمیت رکھتی ہے [15]۔
لہٰذا یہ ٹیسٹ تشخیص کے ذریعے کے طور پر اچھا کام کرتے ہیں۔ آپ کی صحت یابی کا مستقبل بتانے میں یہ کم قابلِ اعتماد ہیں۔
اس کے خطرات کیا ہیں؟
اعصاب کے ٹیسٹ محفوظ ہیں، لیکن آپ کو معلوم ہونا چاہیے کہ کیا توقع رکھیں۔ سب سے عام اثر خود ٹیسٹ کے دوران ہونے والی تکلیف ہے۔ برقی لہریں چھوٹی چھوٹی تھپکیوں یا ہلکے جھٹکوں جیسی محسوس ہوتی ہیں۔ اگر کسی پٹھے میں باریک سوئی لگائی جائے تو آپ کو ایک مختصر سی چبھن محسوس ہوگی، اور بعد میں ایک دو دن تک پٹھے میں دکھن ہو سکتی ہے۔ ٹیسٹ کا انگوٹھی والی انگلی (ring finger) والا طریقہ جلدی ہو جاتا ہے اور آپ پر بہت کم بوجھ ڈالتا ہے [16]۔
برقی لہروں سے آپ کی جلد یا جسم کے ٹشوز پر کوئی دیرپا اثر نہیں ہوتا۔ یہ لہریں چھوٹی ہوتی ہیں، اور جلد کو نقصان پہنچائے بغیر اس میں سے گزر جاتی ہیں۔ اگر آپ کا سوئی والا ٹیسٹ ہو تو سوئی لگنے کی جگہوں پر ہلکا سا چھونے پر درد ہو سکتا ہے، اور ایک چھوٹا سا نیل پڑ سکتا ہے۔ یہ خود ہی ٹھیک ہو جاتے ہیں۔
شواہد میں نہ آپ کے باقی جسم پر اثرات بیان کیے گئے ہیں، اور نہ ہی ان ٹیسٹوں سے ہونے والی نایاب لیکن سنگین پیچیدگیاں۔ یہ بات صاف صاف کہنا ضروری ہے: اس صفحے کی بنیاد بننے والی تحقیقات یہ بتاتی ہیں کہ ٹیسٹ کتنی اچھی طرح تشخیص اور پیش گوئی کرتے ہیں، نقصانات کے بارے میں نہیں، اس لیے یہاں سنگین خطرات کے بارے میں معلومات محدود ہیں۔
ایک خطرہ جسمانی نہیں ہے۔ مختلف ٹیسٹ کرنے والے ان ٹیسٹوں کو مختلف طریقے سے پڑھ سکتے ہیں، اور کچھ رپورٹیں دوسروں سے زیادہ تفصیل دیتی ہیں [11]۔ جو رپورٹ چھوٹی چھوٹی خرابیوں کی فہرست تو دے لیکن ان کی وضاحت نہ کرے، وہ غلط نتیجے تک لے جا سکتی ہے [17]۔ ٹیسٹوں کو پڑھنے کے معیارات کو بھی زیادہ واضح طور پر طے کرنے کی ضرورت ہے، تاکہ تشخیص درست ہو اور جب سرجری کی ضرورت نہ ہو تو سرجری نہ کی جائے [12]۔ یہی سب سے اہم چیز ہے جو غلط ہو سکتی ہے: خود ٹیسٹ نہیں، بلکہ کسی نامکمل یا غیر واضح رپورٹ پر بنائی گئی تشخیص۔
اگر آپ کو کارپل ٹنل سنڈروم کے لیے اسٹیرائیڈ انجکشن لگ چکا ہے، تو اس انجکشن کے بعد ٹیسٹ کے نتائج میں ہونے والی تبدیلیاں دو سال پر نمایاں نہیں تھیں [13]۔ اس کا مطلب ہے کہ انجکشن لمبے عرصے میں ٹیسٹوں کے نتائج کو بدلتا ہوا نظر نہیں آتا، اس لیے انجکشن کے بعد دوبارہ کیے گئے ٹیسٹ سے بھی آپ کے عصب کی مناسب تصویر ملنی چاہیے۔
اپنے ڈاکٹر یا ٹیسٹ کرنے والے شخص سے کہیں کہ وہ آپ کو رپورٹ سمجھائیں۔ ٹیسٹ میں کیا ملا اور اس کا کیا مطلب ہے، اس کی واضح وضاحت ایک اچھے نتیجے کا حصہ ہے۔
کیا یہ آپ کے لیے مناسب ہے؟
اگر آپ کی علامات کارپل ٹنل سنڈروم کی طرف اشارہ کرتی ہیں اور سرجری زیرِ غور ہے، تو یہ ٹیسٹ عموماً منصوبے کا حصہ ہوتے ہیں۔ زیادہ تر ڈاکٹر اس تصدیق کے بغیر آپریشن نہیں کرتے [3]۔ اضافی ٹیسٹ اس امکان کو بڑھا سکتا ہے کہ سرجری کسی حقیقی، قابلِ علاج اعصابی مسئلے پر کی جائے [9]۔ یہ اہم ہے، کیونکہ یہ ٹیسٹ درست تشخیص کرتے ہیں اور دکھاتے ہیں کہ آپ کے عصب پر دباؤ کتنا شدید ہے [6]۔
اگر آپ کی علامات مبہم ہوں یا آتی جاتی رہیں تو یہ ٹیسٹ کم مفید ہو سکتے ہیں۔ ہو سکتا ہے ٹیسٹ کے دن عصب پر دباؤ پکڑا نہ جائے۔ نارمل نتیجہ کارپل ٹنل سنڈروم کو خارج نہیں کرتا۔ یہ ٹیسٹ یہ پیش گوئی بھی نہیں کر سکتے کہ سرجری کے بعد آپ کیسا محسوس کریں گے، اس لیے یہ تشخیص کا ذریعہ ہیں، آپ کی صحت یابی کا کوئی وعدہ نہیں [6]۔
بنیادی متبادل الٹراساؤنڈ ہے، جس سے بھی عصب پر دباؤ کی جانچ ہو سکتی ہے [9]۔ آپ کے ڈاکٹر ان میں سے ایک یا دونوں تجویز کر سکتے ہیں۔ ہر ایک کی اپنی خوبیاں ہیں، اور صحیح انتخاب آپ کی علامات اور معائنے پر منحصر ہے۔
یہ فیصلہ آپ اپنے ڈاکٹر کے ساتھ مل کر کریں۔ پوچھیں کہ ٹیسٹ سے کیا ظاہر ہونے کی توقع ہے، اور اگر نتیجہ نارمل آیا تو کیا ہوگا۔ اگر خود ٹیسٹ کے خطرات کے بارے میں آپ کے سوالات ہیں تو اوپر خطرات والا حصہ پڑھیں۔
خلاصہ
اگر کارپل ٹنل سنڈروم کی سرجری پر غور کیا جا رہا ہے تو یہ ٹیسٹ کروانا فائدہ مند ہے۔ یہ تصدیق کرتے ہیں کہ آیا آپ کے عصب پر دباؤ حقیقی ہے، اور دکھاتے ہیں کہ یہ کتنا شدید ہے [6]۔ اضافی ٹیسٹ اس امکان کو بڑھا سکتا ہے کہ سرجری کسی حقیقی، قابلِ علاج مسئلے پر کی جائے [9]۔ حقیقت پسندانہ توقع کے ساتھ ٹیسٹ کروائیں: یہ ٹیسٹ تشخیص میں اچھے ہیں، لیکن یہ پیش گوئی نہیں کر سکتے کہ سرجری کے بعد آپ کیسا محسوس کریں گے [6]۔ سب سے اہم احتیاطی بات یہ ہے کہ نارمل نتیجہ کارپل ٹنل سنڈروم کو خارج نہیں کرتا، کیونکہ عصب پر دباؤ آتا جاتا رہ سکتا ہے۔ کوئی بھی فیصلہ کرنے سے پہلے اپنی رپورٹ کی واضح وضاحت مانگیں۔
حوالہ جات
[1] Sensory threshold and conductance testing in nerve injuries. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1986. DOI: 10.1016/0266-7681(86)90252-4
[2] Correlation of Clinical Signs with Nerve Conduction Tests in the Diagnosis of Carpal Tunnel Syndrome. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90244-5
[3] Current Practice in the Use of Nerve Conduction Studies in Carpal Tunnel Syndrome by Surgeons in the Netherlands. Journal of Hand Surgery (European Volume). 2007. DOI: 10.1016/j.jhse.2007.09.007
[4] Diagnosis of Ulnar Neuropathy at the Elbow Using Ultrasound — A Comparison to Electrophysiologic Studies. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.08.014
[5] Use of nerve conduction studies in carpal tunnel syndrome. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231191685
[6] Electrical studies as a prognostic factor in the surgical treatment of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80384-4
[7] Provocative motor nerve conduction testing in presumptive carpal tunnel syndrome unconfirmed by traditional electrodiagnostic testing. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(97)80045-7
[8] The utility of portable nerve conduction testing for patients with carpal tunnel syndrome: A prospective clinical study. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90117-8
[9] Diagnosis of Mild-to-moderate Idiopathic Median Neuropathy at the Carpal Tunnel Based on Signs and Symptoms is Discordant From Diagnosis Based on Electrodiagnostic Studies and Ultrasound. Clinical Orthopaedics & Related Research. 2023. DOI: 10.1097/corr.0000000000002751
[10] CORR Insights®: Diagnosis of Mild-to-moderate Idiopathic Median Neuropathy at the Carpal Tunnel Based on Signs and Symptoms is Discordant From Diagnosis Based on Electrodiagnostic Studies and Ultrasound. Clinical Orthopaedics & Related Research. 2023. DOI: 10.1097/corr.0000000000002822
[11] Electrodiagnostic reports of median neuropathy at the wrist. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80089-0
[12] Electrodiagnostic testing and carpal tunnel release outcome. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(05)80209-6
[13] Nerve Conduction Studies after Treatment for Carpal Tunnel Syndrome. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90191-4
[14] Diagnostic and therapeutic value of carpal tunnel injection. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80065-9
[15] Carpal Tunnel Syndrome: Neurophysiological Results of Surgery Based on Preoperative Electrodiagnostic Testing. Journal of Hand Surgery. 1997. DOI: 10.1016/s0266-7681(97)80355-5
[16] Relative slowing of the median antidromic sensory nerve conduction velocity to the ring finger in screening for carpal tunnel syndrome. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.04.026
[17] Electrodiagnostic testing in hand surgery. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80298-x
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Nerve conduction studies serve as a measure of impaired nerve function and are the best available indicator of overall disease severity with some prognostic value for surgical outcome [1].
- Nerve conduction studies are considered an indispensable part of the pre-operative evaluation for carpal tunnel syndrome [2].
- Provocative nerve conduction testing is a useful and simple addition to the overall evaluation of patients with carpal tunnel syndrome, particularly those with otherwise normal findings on traditional electrodiagnostic studies [3].
- The selection of an appropriate electrical screening test for peripheral nerve injury depends on the prevalence and seriousness of the target disease and the relative consequences of over- and underdiagnosis [4].
- The absence of any real difference in nerve conduction time between a working group with symptoms and a group with diagnosed carpal tunnel syndrome indicates a high probability that many participants with symptoms would have had abnormal findings on standard electrodiagnostic tests [5].
- The value of preoperative nerve conduction studies lies in obtaining the correct diagnosis and determining the severity of the median nerve disease, not in predicting postoperative outcome [6].
- Electrodiagnostic criteria used in some referenced studies were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in carpal tunnel syndrome [7].
- The value of electrodiagnostic testing is not negated by findings that it does not predict postoperative outcome [8].
- When signs and symptoms suggest mild-to-moderate median neuropathy and surgery is being considered, patients and clinicians might consider additional testing, such as electrodiagnostic studies or ultrasound, to increase the probability of actual median neuropathy that can benefit from surgery [9].
- Clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries [10].
- Highly sensitive tests are required to assess or exclude the diagnosis in one quarter of cases of carpal tunnel syndrome [11].
- Nerve conduction studies were more sensitive than sensibility testing in confirming the diagnosis of carpal tunnel syndrome [13].
- The combination of nerve conduction studies and sensibility testing is more sensitive than either test alone in confirming the diagnosis of carpal tunnel syndrome [13].
- Given specific clinical criteria for establishing the diagnosis of carpal tunnel syndrome, electrodiagnostic testing does not appear to correlate with improved final symptomatic outcome after carpal tunnel release [20].
- Surgical intervention is advocated for patients with symptoms only, even when electrodiagnostic studies are normal, in the context of cubital tunnel syndrome [21].
- The majority of neurosurgeons and orthopaedic surgeons seldom operate without electrodiagnostic confirmation in line with the Dutch consensus guideline on this subject [29].
- When used together, Semmes-Weinstein monofilament mappings and sensory nerve conduction parameters present a clearer picture of the patient's sensory status than either test used alone [31].
- Receiver operating characteristic curves showed distal sensory latency measurement to be a superior diagnostic test for carpal tunnel syndrome, with 3.3 ms as optimal upper limit of normal, giving a sensitivity of 74% and a specificity of 87% [45].
How It Works
Diagnostic Utility and Role
- The clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries [10].
- Electrodiagnostic studies are used as part of a clinical evaluation process and are considered a reasonable way to practice medicine [12].
Sensitivity and Specificity
- Nerve conduction studies were more sensitive than sensibility testing in confirming the diagnosis of carpal tunnel syndrome, but the combination of the two studies is more sensitive than either test alone [13].
- The sensitivity of the neurometer test alone was 69% and specificity was 100%, increasing to 84% sensitivity when combined with quantitative sensibility testing [28].
- The relative slowing of the antidromic sensory conduction velocity of the median nerve to the ring finger is determined easily and efficiently and imposes minimal strain on the patient [34].
Prognostic Value and Outcomes
- Compound muscle action potential amplitude, but not other conventional electrodiagnostic parameters, was predictive of functional outcomes after in situ decompression of the ulnar nerve [22].
- Suprascapular nerve dysfunction, evidenced by reduced nerve amplitudes and supraspinatus muscle atrophy, significantly predicts poor functional outcomes following shoulder hemiarthroplasty, even when tuberosities are well healed [19].
- This strength recovers gradually as the median nerve heals, but never returns to normal, indicating that this test can be extrapolated to the reinnervation of the abductor pollicies brevis [23].
Technical Considerations and Reporting
- There is variability with respect to the thoroughness of electrodiagnostic studies and in the quality of information in the reports [16].
- Electrodiagnostic reports should specifically indicate abnormalities of latency and conduction and present a clear description of the probable pathophysiologic processes rather than just compiling slight abnormalities [26].
- The conduction velocity of the ulnar nerve after an anterior transposition is determined by both the position of the elbow and the location for the measurement of the skin distance [37].
Physiological Mechanisms and Intraoperative Findings
- When in situ nerve strain reached 8.1 ± 0.5%, the compound muscle action potential was not evoked [33].
- Intraoperative conduction latencies indicated a dramatic and immediate reduction in the conduction latency across the carpal canal in all but seven patients, two of whom had diabetes [36].
- Electrodiagnostic studies revealed an acute median nerve lesion at the wrist with motor and/or sensory conduction blocks in 20/30 women with pregnancy-related carpal tunnel syndrome [18].
Comparative Modalities
- Ultrasound is a valid alternative confirmatory test compared with electrodiagnostic studies in detecting ulnar neuropathy at the elbow [14].
- The study confirms the high diagnostic value of the pre-operative antidromic sensory conduction velocity findings [25].
What the Evidence Shows
Diagnostic Role and Sensitivity
- The absence of any real difference in nerve conduction time between the working group with symptoms and the group with diagnosed carpal tunnel syndrome indicates a high probability that many participants with symptoms would have had abnormal findings on standard electrodiagnostic tests [5].
- There is a severe discordance between the estimated prevalence of mild-to-moderate carpal tunnel syndrome based on clinical signs and symptoms (73%) versus electrodiagnostic studies and ultrasound (51%) [27].
- The authors argue that the electrodiagnostic criteria used in the referenced study were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in carpal tunnel syndrome [7].
- Carpal tunnel injection is a reasonably accurate diagnostic test, as a good response to injection is an excellent diagnostic and prognostic sign for surgical treatment [42].
Prognostic Value and Outcomes
- Upper arm motor nerve conduction velocity might be a useful predictor of poor surgical outcome in cubital tunnel syndrome [32].
- Distal motor latency is a simple test with a predictive value of the postoperative neurophysiological and clinical outcome of carpal tunnel syndrome [39].
- The changes in electrophysiological findings occurring spontaneously in carpal tunnel syndrome and after treatment by injection are not statistically significant at two years [38].
Clinical Application and Reporting
- The author continues to use electrodiagnostic studies as part of a clinical evaluation process and considers this a reasonable way to practice medicine [12].
- The author proposes that the clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries [10].
- The study confirms the high diagnostic value of the pre-operative antidromic sensory conduction velocity findings in carpal tunnel syndrome [25].
- Surgical intervention is advocated for patients with symptoms only, even when electrodiagnostic studies are normal, in cases of cubital tunnel syndrome [21].
- The incidence of abnormal conduction times was not reliably correlated with either age or duration of paralysis in the paraplegic hand [24].
- In primates, there is no significant difference in the conduction velocity of peripheral nerves repaired in adults and those repaired in early life [15].
- Although there are essential differences between Semmes-Weinstein monofilament mappings and sensory nerve conduction parameters, when used together they present a clearer picture of the patient's sensory status than either test used alone [31].
- The strength of the abductor pollicis brevis recovers gradually as the median nerve heals but never returns to normal, indicating that this test can be extrapolated to the reinnervation of the abductor pollicis brevis [23].
- Chitosan phonophoresis demonstrated significant improvements in nerve conduction, pain reduction, and enhancement of hand function for mild to moderate cubital tunnel syndrome [17].
- All patients had good clinical and electrophysiological recovery at 6 months following single-stage opponensplasty added at the time of release for severe carpal tunnel syndrome [41].
- Three weeks after the operation, 77% of the patients in the tourniquet group had denervation in other than thenar muscles [46].
Practical Considerations
Diagnostic Interpretation and Utility
- Nerve conduction studies serve as a measure of impaired nerve function and the best available indicator of overall disease severity, rather than a test that determines the diagnosis [1].
- The value of preoperative nerve conduction studies lies in obtaining the correct diagnosis and determining the severity of median nerve disease, not in predicting postoperative outcome [6].
- Electrodiagnostic testing does not appear to correlate with improved final symptomatic outcome after carpal tunnel release given specific clinical criteria for establishing the diagnosis [20].
- When signs and symptoms suggest mild-to-moderate median neuropathy and surgery is being considered, patients and clinicians might consider additional testing, such as EDS or US, to increase the probability of actual median neuropathy that can benefit from surgery [9].
- The authors argue that the electrodiagnostic criteria used in the referenced study were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in CTS [7].
- This does not negate the value of electrodiagnostic testing [8].
Testing Variations and Screening
- Provocative nerve conduction testing is a useful and simple addition to the overall evaluation of patients with CTS, particularly those with otherwise normal findings on traditional electrodiagnostic studies [3].
- The absence of any real difference in nerve conduction time between the working group with symptoms and the group with diagnosed CTS indicates a high probability that many of the participants with symptoms would have had abnormal findings on standard electrodiagnostic tests [5].
- There is a significant discrepancy between the practice recommended by the Danish Society of Neurophysiology of performing neurophysiological investigations in all cases of suspected CTS and what is actually done in most surgical departments [35].
Specific Clinical Scenarios
- Upper arm motor nerve conduction velocity (MNCV) might be a useful predictor of poor surgical outcome in cubital tunnel syndrome [32].
- Surgical intervention is advocated for patients with symptoms only, even when electrodiagnostic studies are normal, in cases of electrodiagnostic-negative cubital tunnel syndrome [21].
- SSN dysfunction, evidenced by reduced nerve amplitudes and supraspinatus muscle atrophy, significantly predicts poor functional outcomes following shoulder hemiarthroplasty, even when tuberosities are well healed [19].
- The incidence of abnormal conduction times in the paraplegic hand was not reliably correlated with either age or duration of paralysis [24].
- Intraoperative electrodiagnosis may offer limited value in neonatal brachial plexus palsy surgery, but there is insufficient evidence to reach robust conclusions [44].
- This underscores the need for surgeons to carefully evaluate suprascapular nerve integrity in cases of rotator cuff tear [40].
Methodological and Prognostic Notes
- Only studies with randomization, blinding, and sham injection or sham surgery can address subjective symptoms and satisfaction reliably and accurately [30].
Key Evidence
- [L5] Nerve conduction studies should be understood not as a test that determines the diagnosis but as a measure of impaired nerve function, serving as the best available indicator of overall disease severity with some prognostic value for surgical outcome. [1] (10.1177/17531934231191685)
- [L3] We consider nerve conduction studies to be an indispensable part of the pre-operative evaluation. [2] (10.1016/0266-7681(94)90244-5)
- [L2] Provocative nerve conduction testing is a useful and simple addition to the overall evaluation of patients with CTS, particularly those with otherwise normal findings on traditional electrodiagnostic studies. [3] (10.1016/s0363-5023(97)80045-7)
- [L3] The selection of an appropriate electrical screening test for peripheral nerve injury, such as entrapment neuropathy, depends on the prevalence and seriousness of the target disease and the relative consequences of over- and underdiagnosis. [4] (10.1016/s0363-5023(96)80165-1)
- [L3] The absence of any real difference in nerve conduction time between the working group with symptoms and the group with diagnosed CTS indicates a high probability that many of the participants with symptoms would have had abnormal findings on standard electrodiagnostic tests. [5] (10.1016/0363-5023(92)90116-7)
- [L5] The value of preoperative nerve conduction studies lies in obtaining the correct diagnosis and determining the severity of the median nerve disease, not in predicting postoperative outcome. [6] (10.1016/s0363-5023(96)80384-4)
- [L5] The authors argue that the electrodiagnostic criteria used in the referenced study were inadequate and not the most sensitive available, potentially leading to the erroneous conclusion that electrodiagnostic studies offer no additional diagnostic power in CTS. [7] (10.1067/jhsu.2000.jjhsu00025a1le01)
- [L5] This does not negate the value of electrodiagnostic testing. [8] (10.1016/s0363-5023(96)80222-x)
- [L3] When signs and symptoms suggest mild-to-moderate median neuropathy and surgery is being considered, patients and clinicians might consider additional testing, such as EDS or US, to increase the probability of actual median neuropathy that can benefit from surgery. [9] (10.1097/corr.0000000000002751)
- [L5] The author proposes that the clinical, electrodiagnostic, and physical examination criteria need better definition to avoid inaccurate diagnoses and unnecessary surgeries. [10] (10.1016/s0363-5023(05)80209-6)
- [L3] Highly sensitive tests are required to assess or exclude the diagnosis in one quarter of cases of carpal tunnel syndrome. [11] (10.1016/0266-7681(94)90245-3)
- [L5] The author continues to use electrodiagnostic studies as part of a clinical evaluation process and considers this a reasonable way to practice medicine. [12] (10.1016/s0363-5023(96)80380-7)
- [L4] The results indicate that nerve conduction studies were more sensitive than sensibility testing in confirming the diagnosis of carpal tunnel syndrome, but the combination of the two studies is more sensitive than either test alone. [13] (10.1016/s0363-5023(82)80176-7)
- [L4] Ultrasound is a valid alternative confirmatory test compared with electrodiagnostic studies in detecting ulnar neuropathy at the elbow. [14] (10.1016/j.jhsa.2023.08.014)
- [L3] The study demonstrates that in primates there is no significant difference in the conduction velocity of peripheral nerves repaired in adults and those repaired in early life. [15] (10.1016/s0363-5023(83)80199-3)
- [L4] There is variability with respect to the thoroughness of electrodiagnostic studies and in the quality of information in the reports. [16] (10.1016/s0363-5023(98)80089-0)
- [L1] This approach demonstrated significant improvements in nerve conduction, pain reduction, and enhancement of hand function. [17] (10.1016/j.jht.2024.02.006)
- [L4] Electrodiagnostic studies revealed an acute median nerve lesion at the wrist with motor and/or sensory conduction blocks in 20/30 women. [18] (10.1016/s0266-7681(98)80232-5)
- [L3] SSN dysfunction, evidenced by reduced nerve amplitudes and supraspinatus muscle atrophy, significantly predicts poor functional outcomes following SHA, even when tuberosities are well healed. [19] (10.1016/j.jse.2025.07.001)
- [L3] Given specific clinical criteria for establishing the diagnosis of carpal tunnel syndrome, electrodiagnostic testing does not appear to correlate with improved final symptomatic outcome after carpal tunnel release. [20] (10.1016/s0363-5023(96)80164-x)
- [L2] We advocate surgical intervention for patients with symptoms only, even when electrodiagnostic studies are normal. [21] (10.1053/jhsu.2001.26327)
- [L2] Compound muscle action potential amplitude, but not other conventional electrodiagnostic parameters, was predictive of functional outcomes after in situ decompression of the ulnar nerve. [22] (10.1016/j.jhsa.2022.10.008)
- [L5] This strength recovers gradually as the median nerve heals, but never returns to normal, indicating that this test can be extrapolated to the reinnervation of the abductor pollicies brevis. [23] (10.1016/s0266-7681(03)00022-6)
- [L4] The incidence of abnormal conduction times was not reliably correlated with either age or duration of paralysis. [24] (10.1016/s0363-5023(88)80132-1)
- [L4] The study confirms the high diagnostic value of the pre-operative antidromic sensory conduction velocity findings. [25] (10.1016/0266-7681(88)90161-1)
- [L5] EDX reports should specifically indicate abnormalities of latency and conduction and present a clear description of the probable pathophysiologic processes rather than just compiling slight abnormalities. [26] (10.1016/s0363-5023(96)80298-x)
- [L5] There is a severe discordance between the estimated prevalence of mild-to-moderate carpal tunnel syndrome based on clinical signs and symptoms (73%) versus electrodiagnostic studies and ultrasound (51%), calling into question whether clinicians can confidently diagnose patients with mild-to-moderate CTS. [27] (10.1097/corr.0000000000002822)
- [L3] The sensitivity of the neurometer test alone was 69% and specificity was 100%, increasing to 84% sensitivity when combined with quantitative sensibility testing. [28] (10.1016/0363-5023(92)90117-8)
- [L4] The majority of neurosurgeons and orthopaedic surgeons seldom operate without electrodiagnostic confirmation in line with the Dutch consensus guideline on this subject. [29] (10.1016/j.jhse.2007.09.007)
- [L4] Although there are essential differences in these two tests, when used together they present a clearer picture of the patient's sensory status than either test used alone. [31] (10.1016/s0894-1130(87)80010-8)
- [L3] Upper arm motor nerve conduction velocity (MNCV) might be a useful predictor of poor surgical outcome. [32] (10.1177/17585732241293360)
- [Paper] The results showed that when the in situ nerve strain reached 8.1 ± 0.5%, the compound muscle action potential was not evoked. [33] (10.1016/s0736-0266(02)00080-3)
- [L3] The relative slowing of the antidromic sensory conduction velocity of the median nerve to the ring finger is determined easily and efficiently and imposes minimal strain on the patient. [34] (10.1016/j.jhsa.2004.04.026)
- [L4] There is a significant discrepancy between the practice recommended by the Danish Society of Neurophysiology of performing neurophysiological investigations (NI) in all cases of suspected CTS and what is actually done in most surgical departments. [35] (10.1016/s0266-7681(97)80443-3)
- [L4] The results of intraoperative conduction latencies indicated a dramatic and immediate reduction in the conduction latency across the carpal canal in all but seven patients, two of whom had diabetes. [36] (10.1016/s0363-5023(78)80119-1)
- [L4] The conduction velocity of the ulnar nerve after an anterior transposition is determined by both the position of the elbow and the location for the measurement of the skin distance. [37] (10.1016/s0363-5023(87)80051-5)
- [L3] The changes in electrophysiological findings occurring spontaneously in carpal tunnel syndrome and after treatment by injection are not statistically significant at two years. [38] (10.1016/0266-7681(92)90191-4)
- [L3] DML is a simple test with a predictive value of the postoperative neurophysiological and clinical outcome of carpal tunnel syndrome. [39] (10.1016/s0266-7681(97)80355-5)
- [L5] This underscores the need for surgeons to carefully evaluate suprascapular nerve integrity in such cases. [40] (10.1186/s12891-025-09195-6)
- [L3] All patients had good clinical and electrophysiological recovery at 6 months. [41] (10.1177/1558944716660555fx)
- [L4] Results suggest that carpal tunnel injection is also a reasonably accurate diagnostic test, as a good response to injection is an excellent diagnostic and prognostic sign for surgical treatment. [42] (10.1016/s0363-5023(84)80065-9)
- [L4] Intraoperative electrodiagnosis may offer limited value in neonatal brachial plexus palsy surgery, but there is insufficient evidence to reach robust conclusions. [44] (10.1177/17531934261478357)
- [L3] Receiver operating characteristic curves showed distal sensory latency measurement to be a superior diagnostic test, with 3.3 ms as optimal upper limit of normal, giving a sensitivity of 74% and a specificity of 87%. [45] (10.1016/s0363-5023(96)80020-7)
- [L1] Three weeks after the operation 77% of the patients in the tourniquet group had denervation in other than thenar muscles. [46] (10.1016/s0363-5023(89)80011-5)
References
[1] Use of nerve conduction studies in carpal tunnel syndrome. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231191685
[2] Correlation of Clinical Signs with Nerve Conduction Tests in the Diagnosis of Carpal Tunnel Syndrome. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90244-5
[3] Provocative motor nerve conduction testing in presumptive carpal tunnel syndrome unconfirmed by traditional electrodiagnostic testing. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(97)80045-7
[4] A comparison of traditional electrodiagnostic studies, electroneurometry, and vibrometry in the diagnosis of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80165-1
[5] Use of motor nerve conduction testing and vibration sensitivity testing as screening tools for carpal tunnel syndrome in industry. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90116-7
[6] Electrical studies as a prognostic factor in the surgical treatment of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80384-4
[7] Diagnostic testing in carpal tunnel syndrome. The Journal of Hand Surgery. 2000. DOI: 10.1067/jhsu.2000.jjhsu00025a1le01
[8] Electrical studies as a prognostic factor in carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80222-x
[9] Diagnosis of Mild-to-moderate Idiopathic Median Neuropathy at the Carpal Tunnel Based on Signs and Symptoms is Discordant From Diagnosis Based on Electrodiagnostic Studies and Ultrasound. Clinical Orthopaedics & Related Research. 2023. DOI: 10.1097/corr.0000000000002751
[10] Electrodiagnostic testing and carpal tunnel release outcome. The Journal of Hand Surgery. 1997. DOI: 10.1016/s0363-5023(05)80209-6
[11] Sensitivity of the Various Tests for the Diagnosis of Carpal Tunnel Syndrome. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90245-3
[12] Electrical studies as a prognostic factor in the surgical treatment of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80380-7
[13] Nerve conduction studies and sensibility testing in carpal tunnel syndrome. The Journal of Hand Surgery. 1982. DOI: 10.1016/s0363-5023(82)80176-7
[14] Diagnosis of Ulnar Neuropathy at the Elbow Using Ultrasound — A Comparison to Electrophysiologic Studies. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.08.014
[15] Nerve conduction velocity, microscopic, and electron microscopy studies comparing repaired adult and baby monkey median nerves. The Journal of Hand Surgery. 1983. DOI: 10.1016/s0363-5023(83)80199-3
[16] Electrodiagnostic reports of median neuropathy at the wrist. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80089-0
[17] Effectiveness of chitosan phonophoresis on ulnar nerve conduction velocity, pain relief, and functional outcomes for mild to moderate cubital tunnel syndrome: A double-blind randomized controlled trial. Journal of Hand Therapy. 2024. DOI: 10.1016/j.jht.2024.02.006
[18] Pregnancy-Related Carpal Tunnel Syndrome. Journal of Hand Surgery. 1998. DOI: 10.1016/s0266-7681(98)80232-5
[19] Radiological and electrodiagnostic insights into suprascapular nerve dysfunction: a key predictor of poor functional outcomes in shoulder hemiarthroplasty. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2025.07.001
[20] Electrodiagnostic testing and carpal tunnel release outcome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80164-x
[21] The rationale for and efficacy of surgical intervention for electrodiagnostic-negative cubital tunnel syndrome. The Journal of Hand Surgery. 2001. DOI: 10.1053/jhsu.2001.26327
[22] Electrodiagnostic Predictors of Outcomes After In Situ Decompression of the Ulnar Nerve. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2022.10.008
[23] Re. Clinical value of electrodiagnostic testing following repair of peripheral nerve lesions: a prospective study. Th. H.J. Van de Kar, J.B. Jaquet, J. Meulstee, C.B.H. Molenaar, R.J. Schimsheimer, S.E.R. Hovius. Journal of Hand Surgery 2002: 27B(4): 345–349.. Journal of Hand Surgery. 2003. DOI: 10.1016/s0266-7681(03)00022-6
[24] The paraplegic hand: Electrodiagnostic studies and clinical findings. The Journal of Hand Surgery. 1988. DOI: 10.1016/s0363-5023(88)80132-1
[25] Assessment of sensory nerve conduction in carpal tunnel syndrome before, during and after operation. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90161-1
[26] Electrodiagnostic testing in hand surgery. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80298-x
[27] CORR Insights®: Diagnosis of Mild-to-moderate Idiopathic Median Neuropathy at the Carpal Tunnel Based on Signs and Symptoms is Discordant From Diagnosis Based on Electrodiagnostic Studies and Ultrasound. Clinical Orthopaedics & Related Research. 2023. DOI: 10.1097/corr.0000000000002822
[28] The utility of portable nerve conduction testing for patients with carpal tunnel syndrome: A prospective clinical study. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90117-8
[29] Current Practice in the Use of Nerve Conduction Studies in Carpal Tunnel Syndrome by Surgeons in the Netherlands. Journal of Hand Surgery (European Volume). 2007. DOI: 10.1016/j.jhse.2007.09.007
[30] Probability_and_Pathophysiology_S0363502312002821. 2002.
[31] Correlating Semmes-Weinstein monofilament mappings with sensory nerve conduction parameters in Hansen's disease patients: An update. Journal of Hand Therapy. 1987. DOI: 10.1016/s0894-1130(87)80010-8
[32] Clinical significance of upper arm motor nerve conduction velocity in cubital tunnel syndrome. Shoulder & Elbow. 2024. DOI: 10.1177/17585732241293360
[33] In situ strain and stress of nerve conduction blocking in the brachial plexus. Journal of Orthopaedic Research. 2002. DOI: 10.1016/s0736-0266(02)00080-3
[34] Relative slowing of the median antidromic sensory nerve conduction velocity to the ring finger in screening for carpal tunnel syndrome. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2004.04.026
[35] Operative Treatment of Carpal Tunnel Syndrome in Denmark. Journal of Hand Surgery. 1997. DOI: 10.1016/s0266-7681(97)80443-3
[36] Intraoperative changes in motor nerve conduction latency in carpal tunnel syndrome. The Journal of Hand Surgery. 1978. DOI: 10.1016/s0363-5023(78)80119-1
[37] Validity of nerve conduction velocity studies after anterior transposition of the ulnar nerve. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80051-5
[38] Nerve Conduction Studies after Treatment for Carpal Tunnel Syndrome. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90191-4
[39] Carpal Tunnel Syndrome: Neurophysiological Results of Surgery Based on Preoperative Electrodiagnostic Testing. Journal of Hand Surgery. 1997. DOI: 10.1016/s0266-7681(97)80355-5
[40] Electromyography does not show adequate effectiveness in diagnosis of suprascapular nerve lesions caused by rotator cuff tear in rat model. BMC Musculoskeletal Disorders. 2025. DOI: 10.1186/s12891-025-09195-6
[41] Should Single-Stage Opponensplasty Be Added at the Time of Release for Severe Carpal Tunnel Syndrome?. HAND. 2016. DOI: 10.1177/1558944716660555fx
[42] Diagnostic and therapeutic value of carpal tunnel injection. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80065-9
[44] Intraoperative electrodiagnostic testing as a decision-making tool for neonatal brachial plexus palsy: a scoping review. Journal of Hand Surgery (European Volume). 2026. DOI: 10.1177/17531934261478357
[45] Evaluation of portable nerve conduction testing in the diagnosis of carpal tunnel syndrome. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80020-7
[46] Upper extremity tourniquet effects in carpal tunnel release. The Journal of Hand Surgery. 1989. DOI: 10.1016/s0363-5023(89)80011-5