Patients › Hand
بوٹونیئر ڈیفارمیٹی (Boutonnière Deformity)
Extensor central-slip injury at the middle finger joint; early splinting prevents the zigzag deformity, established cases need surgery.
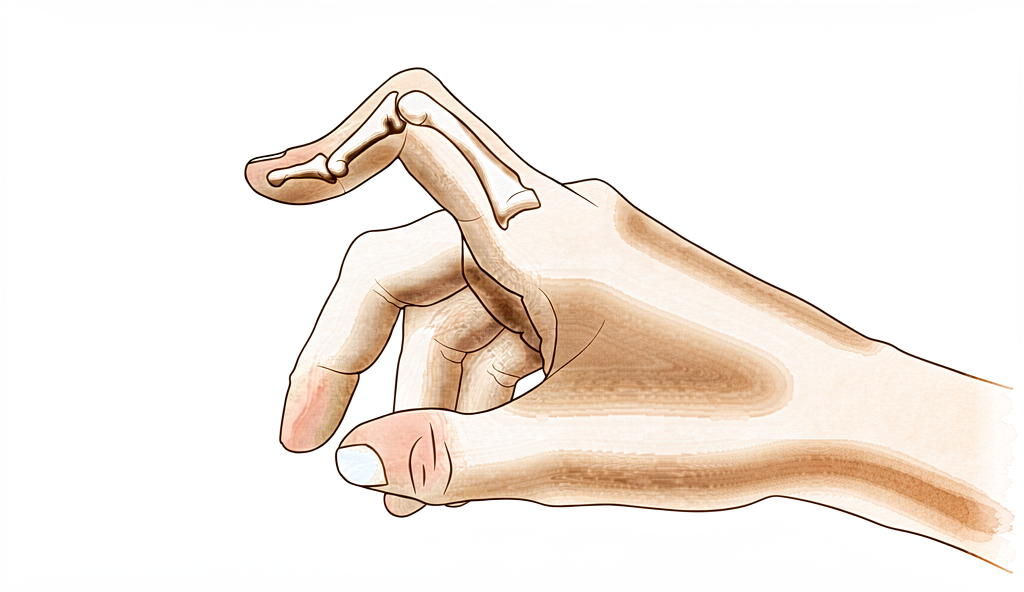
آپ کو کیا محسوس ہوتا ہے
بوٹونیئر ڈیفارمیٹی (boutonnière deformity) میں آپ کی انگلی کا درمیانی جوڑ نیچے ہتھیلی کی طرف مڑ جاتا ہے اور انگلی کا سرا دوسری طرف، یعنی پیچھے کی طرف، مڑ جاتا ہے۔ درمیانی جوڑ کے اوپر انگلی سوجی ہوئی نظر آ سکتی ہے، اور وہاں درد بھی ہو سکتا ہے۔ درمیانی جوڑ کو سیدھا کرنا مشکل ہو جاتا ہے، اور آپ جتنی زیادہ کوشش کرتے ہیں، انگلی اتنی ہی زیادہ مزاحمت کرتی محسوس ہوتی ہے۔
یہ مشکل سب سے زیادہ ان کاموں میں سامنے آتی ہے جن میں انگلی کو سیدھا کر کے پھر سے موڑنا پڑتا ہے۔ سکہ اٹھانا، کپ کو دستے سے پکڑنا، ٹائپ کرنا، قمیض کے بٹن لگانا یا چابی گھمانا، یہ سب مشکل ہو سکتے ہیں۔ خود گرفت اکثر کام کرتی رہتی ہے، اسی لیے بہت سے لوگ مدد لینے سے پہلے کئی ہفتوں تک انگلی کی اس حالت کو برداشت کرتے رہتے ہیں۔
اگر یہ خرابی کسی چوٹ سے ہوئی ہو تو ہاتھ استعمال کرنے کے بعد درمیانی جوڑ میں دکھن ہو سکتی ہے، اور صبح کے وقت، انگلی کے کھلنے سے پہلے، اکڑاؤ زیادہ ہو سکتا ہے۔ ریومیٹائیڈ آرتھرائٹس (rheumatoid arthritis) میں یہی مڑی ہوئی حالت آہستہ آہستہ بنتی ہے، کیونکہ جوڑ کی اندرونی جھلی مہینوں تک سوزش زدہ اور سوجی ہوئی رہتی ہے۔
چند علامات پر فوری توجہ ضروری ہے۔ اگر آپ کی انگلی یا ہاتھ گرم، سرخ، سوجا ہوا اور دردناک ہو جائے، خاص طور پر بخار کے ساتھ، تو اسی دن ہسپتال کی ایمرجنسی جائیں۔ یہی ہدایت اس صورت میں بھی ہے اگر کوئی انگلی سفید پڑنے لگے، ٹھنڈی ہو جائے، بالکل سفید یا نیلی ہو جائے، یا اگر کسی چوٹ کے بعد اچانک اس میں احساس یا حرکت ختم ہو جائے۔ اور اگر اس کے بجائے علامات کم نہ ہو رہی ہوں، ہفتوں کے دوران بڑھ رہی ہوں، آپ کو رات کو جگا دیتی ہوں، یا آپ کو کام کرنے یا اپنا ہاتھ استعمال کرنے سے روکتی ہوں، تو اپنے فیملی ڈاکٹر (GP) سے ملیں یا ماہر سے معائنہ کروانے کا کہیں۔
دراصل کیا ہو رہا ہے
ہر انگلی کی پشت پر ٹینڈنوں (tendons، یعنی وہ مضبوط ڈوریاں جو پٹھوں کو ہڈی سے جوڑتی ہیں) کا ایک مجموعہ چلتا ہے جو جوڑوں کو سیدھا کرتا ہے۔ انہیں ایسی رسیاں سمجھیں جو انگلی کی پشت پر ایک غلاف (hood) کے نیچے چلتی ہیں۔ جو رسی درمیانی جوڑ کو سیدھا کرتی ہے اسے سینٹرل سلپ (central slip) کہتے ہیں، اور یہ درمیانی ہڈی کی جڑ سے جڑی ہوتی ہے۔ دو اور ڈوریاں، جنہیں اطراف کی پٹیاں (lateral bands) کہتے ہیں، اس کے ساتھ ساتھ چلتی ہیں اور درمیانی جوڑ اور انگلی کے سرے دونوں کو سیدھا کرنے میں مدد دیتی ہیں۔
بوٹونیئر ڈیفارمیٹی میں سینٹرل سلپ پھٹ کر یا کھنچ کر درمیانی ہڈی سے الگ ہو جاتی ہے۔ درمیانی جوڑ کو اب کھینچ کر سیدھا نہیں کیا جا سکتا، اس لیے وہ مڑی ہوئی حالت میں گر جاتا ہے۔ پھر اطراف کی دونوں پٹیاں جوڑ کے اوپر سے پھسل کر نیچے ہتھیلی کی طرف کھسک جاتی ہیں۔ جب وہ جوڑ کے محور سے نیچے آ جاتی ہیں تو یہی ڈوریاں درمیانی جوڑ کو سیدھا کرنے کے بجائے موڑنے لگتی ہیں، اور انگلی کے سرے کو دوسری طرف، یعنی پیچھے کی طرف، کھینچتی ہیں۔ اسی لیے انگلی اوپر بیان کی گئی حالت میں جم جاتی ہے، یعنی درمیانی جوڑ مڑا ہوا اور سرا پیچھے کی طرف خم کھایا ہوا، اور اسی لیے اسے سیدھا کرنے کی ہر کوشش پر یوں لگتا ہے کہ ڈوریاں آپ کے خلاف اور زور سے کھینچ رہی ہیں۔
یہ حالت پیدا ہونے کے لیے ایک سے زیادہ حصے کا خراب ہونا ضروری ہے۔ خرابی بننے سے پہلے سینٹرل سلپ، وہ لیگامنٹ (ligament)، یعنی ریشوں کا مضبوط بندھن، جو انگلی کی پشت پر دونوں ڈوریوں کو آپس میں باندھتا ہے، اور غلاف کے وہ ریشے جو ہر چیز کو اپنی جگہ پر رکھتے ہیں، ان سب کو چوٹ لگنا ضروری ہے۔ اکیلی سینٹرل سلپ کا پھٹاؤ پوری خرابی پیدا کیے بغیر درمیانی جوڑ کو کمزور چھوڑ سکتا ہے، اور یہ ایک وجہ ہے کہ جلد علاج اہم ہے: یہ خرابی کو بننے سے بالکل روک سکتا ہے۔
ایک ہی انجام مختلف شروعاتی وجوہات سے ہو سکتا ہے۔ کوئی چوٹ، جیسے انگلی پر ضرب یا جوڑ کی پشت پر کٹ، ایسا کر سکتی ہے، اور ریومیٹائیڈ آرتھرائٹس کی مسلسل سوزش بھی، جو آہستہ آہستہ انہی ساختوں کو گھسا کر ختم کر دیتی ہے۔ کوئی انگلی ٹینڈن کی کسی چوٹ کے بغیر بھی ایسی نظر آ سکتی ہے، جب مسئلہ اس کے بجائے جوڑ کی ہتھیلی والی طرف ہو، اور اس قسم کا علاج مختلف طریقے سے ہوتا ہے، اسی لیے پہلے یہ معلوم کرنا ضروری ہے کہ آپ کو کون سی قسم ہے۔
ہم اس کے لیے کیا کر سکتے ہیں
ڈاکٹر کیرن ہِرپرا، جو Mater Private Hospital Rockhampton میں بازو اور ہاتھ کے سرجن (upper-limb surgeon) ہیں، علاج کا آغاز ان کم سے کم مداخلت والے طریقوں سے کرتے ہیں جو آپ کی حالت کے لیے موزوں ہوں۔ مریضوں کو عام طور پر ان کا فیملی ڈاکٹر (GP) ہمارے کلینک میں بھیجتا ہے؛ اگر کسی فزیوتھراپسٹ نے آپ کو ہمیں دکھانے کا مشورہ دیا ہے، تب بھی میڈیکیئر (Medicare) کی طرف سے رقم کی واپسی کا حقدار بننے کے لیے آپ کو اپنے فیملی ڈاکٹر سے ریفرل (referral) لینا ہو گا۔ کلینک میں ہم آپ کی طبی تاریخ لیتے ہیں، آپ کے ہاتھ کا معائنہ کرتے ہیں، اور ضرورت ہو تو اسکین کا انتظام کرتے ہیں تاکہ معلوم ہو سکے کہ مسئلہ کیا ہے۔ چونکہ یہ خرابی کئی مختلف شروعاتی وجوہات سے پیدا ہو سکتی ہے، اس لیے کسی بھی علاج سے پہلے یہ طے کیا جاتا ہے کہ آپ کو کون سی قسم ہے۔
پہلا قدم عموماً اسپلنٹ اور ہینڈ تھراپی (ہاتھ کی بحالی کا علاج) ہوتا ہے۔ حالیہ چوٹ میں درمیانی جوڑ کو اسپلنٹ میں سیدھا رکھنا اس خرابی کو بننے سے بالکل روک سکتا ہے، اور یہ جتنی جلدی شروع ہو اتنا بہتر ہے: جن لوگوں کا علاج چوٹ کے چھ ہفتوں کے اندر ہو جائے ان کا نتیجہ ان سے بہتر رہتا ہے جن کا علاج بعد میں ہو۔ اسپلنٹ صرف درمیانی جوڑ کو سیدھا رکھتا ہے۔ آپ کی انگلی کا سرا، انگلی کی جڑ کا جوڑ (knuckle) اور آپ کی دوسری انگلیاں حرکت کرتی رہتی ہیں، کیونکہ پوری انگلی کو ساکت رکھنے سے انگلی کا سرا اکڑ جاتا ہے۔ جو خرابی کچھ عرصے سے موجود ہو، اس میں ہم درمیانی جوڑ کو جتنا ممکن ہو سیدھا کرنے کے لیے پلستر استعمال کر سکتے ہیں، جس کے بعد تین ماہ تک ایک ایسا اسپلنٹ لگایا جاتا ہے جو کام کرتے وقت آپ کو انگلی موڑنے دیتا ہے۔ سرجری پر غور کرنے سے پہلے یہ طریقہ آزمانے کے قابل ہے۔
جب اسپلنٹ اور تھراپی سے کافی بہتری نہ آئی ہو تو سرجری پر غور کیا جا سکتا ہے۔ آپریشن میں اس ٹینڈن کو دوبارہ بنایا جاتا ہے جو درمیانی جوڑ کو سیدھا کرتا ہے، بعض اوقات آپ کے اپنے بازو کے نچلے حصے (forearm) سے ٹینڈن کا ایک چھوٹا ٹکڑا گرافٹ (graft)، یعنی لگایا جانے والا نیا ٹکڑا، کے طور پر لے کر۔ کچھ صورتوں میں جو ٹینڈن ہتھیلی کی طرف کھسک گئے ہوں انہیں واپس جوڑ کے اوپر ان کی اصل جگہ پر لایا جاتا ہے۔ ہر صورت میں مقصد ایک ہی ہے: آپ درمیانی جوڑ کو دوبارہ سیدھا کر سکیں اور انگلی کو اس کے اٹکے یا نیچے مڑے بغیر استعمال کر سکیں۔ اس آپریشن کا اپنا الگ صفحہ ہے، اور کوئی بھی فیصلہ کرنے سے پہلے ہم آپ سے بات کریں گے کہ آپ کی انگلی کے لیے اس میں کیا کچھ شامل ہوگا۔
کیا توقع رکھیں
نتیجہ بہت حد تک وقت پر منحصر ہے۔ اگر بوٹونیئر ڈیفارمیٹی جلد پکڑ لی جائے تو اکثر اسے جمنے سے پہلے روکا جا سکتا ہے۔ چوٹ کے جلد بعد درمیانی جوڑ کو اسپلنٹ میں سیدھا رکھنا اس خرابی کو بننے سے بالکل روک سکتا ہے، اور جن لوگوں کا علاج چھ ہفتوں کے اندر ہو جائے ان کا نتیجہ ان سے بہتر رہتا ہے جن کا علاج بعد میں ہو۔ اگر ایسے ہی چھوڑ دیا جائے تو یہ خرابی ایک جیسی رہنے کے بجائے بڑھتی جاتی ہے، کیونکہ اپنی جگہ سے کھسکے ہوئے ٹینڈن انگلی کو اس کی مڑی ہوئی حالت میں مزید کھینچتے رہتے ہیں۔ جو چوٹ معمولی لگ رہی تھی وہ ہفتوں بعد ایک اکڑی ہوئی، جمی ہوئی انگلی کا باعث بن سکتی ہے۔
جو خرابی کچھ عرصے سے موجود ہو، اس میں بھی آپریشن کے بغیر علاج کا واقعی کردار ہے۔ درمیانی جوڑ کو جتنا ممکن ہو سیدھا کرنے کے لیے پلستر، اور اس کے بعد تین ماہ تک ایک ایسا اسپلنٹ جو استعمال کے دوران آپ کو انگلی موڑنے دیتا ہے، اچھا کام کر سکتا ہے۔ انگلی اس طریقے سے تب فائدہ اٹھاتی ہے جب پلستر درمیانی جوڑ کو تقریباً سیدھا کر سکے اور آپ ان تین مہینوں کے دوران اسپلنٹ میں اپنا ہاتھ فعال طور پر استعمال کریں، اور اس دوران انگلی کا مڑنا بھی بحال ہوتا جائے۔ انگوٹھے کی چوٹوں میں انگوٹھے کے جوڑ (knuckle) کو اسپلنٹ میں سیدھا رکھنا مدد دے سکتا ہے، اگر یہ خرابی بننے سے پہلے شروع کیا جائے۔
سرجری کا مقصد یہ ہے کہ آپ درمیانی جوڑ کو دوبارہ سیدھا کر سکیں۔ رپورٹ کیے گئے 18 افراد کے ایک گروپ میں، جن کی پرانی خرابی کو درست کرنے کے لیے ٹینڈن گرافٹ کا آپریشن کیا گیا، 16 کے نتائج اچھے یا بہت اچھے رہے۔ ایک نئی تکنیک، جس میں انگلی کو جلد حرکت دی جاتی ہے، 11 کیسوں میں کامیاب بتائی گئی۔ سرجری اس خرابی کی پیدائشی قسم میں بھی مدد دے سکتی ہے، جس میں یہ پیدائش سے موجود ہوتی ہے۔
یہ ایمانداری سے کہنا چاہیے کہ ہر اصلاح دیرپا نہیں ہوتی۔ ریومیٹائیڈ آرتھرائٹس سے متاثرہ انگلیوں میں، بیماری کے بعد کے مرحلوں میں صرف نرم ٹشو (soft tissue) کی سرجری شاید قائم نہ رہے، اور طویل مدتی نتائج کا اندازہ لگانا زیادہ مشکل ہوتا ہے۔ جب خرابی واپس آ جائے یا برقرار رہے تو کوئی دوسرا آپریشن بہتر حل ہو سکتا ہے۔ وجہ کچھ بھی ہو، حقیقت پسندانہ مقصد ایک ایسی انگلی ہے جسے آپ سیدھا کر سکیں اور استعمال کر سکیں، بالکل نارمل انگلی کا وعدہ نہیں۔
ڈاکٹر کو کب دکھائیں
بوٹونیئر ڈیفارمیٹی میں جلد توجہ کا فائدہ ہوتا ہے، اس لیے یہ جاننا مفید ہے کہ کب قدم اٹھانا ہے۔ اگر آپ کی انگلی کو چوٹ لگی ہو اور درمیانی جوڑ سیدھا نہ ہو رہا ہو، یا چوٹ کے کئی دن بعد بھی انگلی مڑی ہوئی اور سوجی ہوئی ہو، تو اپنے فیملی ڈاکٹر سے ملیں اور ماہر سے معائنہ کروانے کا کہیں۔ اسپلنٹ جتنی جلدی شروع ہو، خرابی کو جمنے سے پہلے روکنے کا امکان اتنا ہی بہتر ہوتا ہے۔
چند علامات پر زیادہ جلدی دیکھ بھال ضروری ہے۔ اگر آپ کی انگلی یا ہاتھ گرم، سرخ، سوجا ہوا اور دردناک ہو جائے، خاص طور پر بخار کے ساتھ، تو اسی دن ہسپتال کی ایمرجنسی جائیں۔ یہی ہدایت اس صورت میں بھی ہے اگر کوئی انگلی سفید پڑنے لگے، ٹھنڈی ہو جائے، بالکل سفید یا نیلی ہو جائے، یا اگر کسی چوٹ کے بعد اچانک اس میں احساس یا حرکت ختم ہو جائے۔ اگر زخمی جوڑ کے اوپر جلد پھٹی ہوئی ہو، یا انگلی کی شکل واضح طور پر بگڑی ہوئی نظر آئے، تو بھی ہسپتال کی ایمرجنسی جائیں۔
اگر اس کے بجائے علامات کم نہ ہو رہی ہوں، ہفتوں کے دوران بڑھ رہی ہوں، آپ کو رات کو جگا دیتی ہوں، یا آپ کو کام کرنے یا اپنا ہاتھ استعمال کرنے سے روکتی ہوں، تو اپنے فیملی ڈاکٹر سے ملیں یا ماہر سے معائنہ کروانے کا کہیں۔ اگر آپ کلینک کے اوقات کے بعد یا ہفتے کے آخر میں کلینک سے رابطہ نہ کر سکیں، تو اپنے قریب ترین ہسپتال کی ایمرجنسی جائیں۔
مزید تفصیل
Advanced reading: the deeper science (optional)
یہ حصہ اس سے آگے جاتا ہے جس کی آپ کو اپنے علاج کے فیصلوں کے لیے ضرورت ہے۔ بوٹونیئر ڈیفارمیٹی اضافی مطالعے کے قابل ہے، کیونکہ ایک دردناک، سوجی ہوئی، مڑی ہوئی انگلی کا فطری علاج، یعنی اسے آرام دینا اور ساکت رکھنا، وہی ایک چیز ہے جس کی شواہد خاص طور پر تائید نہیں کرتے۔
جلد حرکت، طویل عرصے تک ساکت رکھنا نہیں
سینٹرل سلپ کی چوٹ کے علاج پر ایک منظم جائزہ (systematic review) میں شواہد کی بنیاد محدود پائی گئی، اور کھلی اور بند دونوں قسم کی چوٹوں کے لیے مختلف طریقوں کے کردار کی اچھی طرح تائید نہیں ہوتی [1]۔ اس حد کے اندر، انفرادی تحقیقات کے شواہد جلد حرکت شروع کرنے کی محتاط طور پر تائید کرتے ہیں اور طویل عرصے تک ساکت رکھنے کی تائید نہیں کرتے [1]۔
یہ بات صاف صاف کہنا ضروری ہے کیونکہ یہ فطری ردعمل کے خلاف ہے۔ فرق بھرتی ہوئی سینٹرل سلپ کی حفاظت کرنے میں ہے، جس کے لیے درمیانی جوڑ کو سیدھا رکھنا ضروری ہے، اور پوری انگلی کو ساکت کر دینے میں، جس سے انگلی کے سرے کا جوڑ سیدھی حالت میں اکڑ جاتا ہے اور پوری انگلی سخت ہو جاتی ہے۔ اسپلنٹ کا مقصد ایک جوڑ کو تھامے رکھنا ہے جبکہ باقی جوڑ حرکت کرتے رہیں۔
یہ خرابی ایک جگہ رکنے کے بجائے بڑھتی کیوں ہے
بوٹونیئر ایک بڑھنے والی خرابی ہے، جو غیر معمولی بات ہے اور سمجھنے کے قابل ہے۔ سینٹرل سلپ درمیانی ہڈی کی جڑ سے جڑی ہوتی ہے اور درمیانی جوڑ کو سیدھا کرتی ہے۔ جب یہ ناکام ہو جاتی ہے تو وہ جوڑ مڑی ہوئی حالت میں گر جاتا ہے، اور دونوں اطراف کی پٹیاں (lateral bands)، جو عام طور پر جوڑ کے محور کے اوپر سے گزرتی ہیں، اس کے نیچے کھسک جاتی ہیں۔
محور کے نیچے آ جانے کے بعد، وہی ٹینڈن جو پہلے درمیانی جوڑ کو سیدھا کرنے میں مدد دیتے تھے، اسے موڑنا شروع کر دیتے ہیں، اور ساتھ ہی انگلی کے سرے کو حد سے زیادہ پیچھے کی طرف (hyperextension) کھینچ لیتے ہیں۔ اس طرح خرابی خود کو مضبوط کرتی جاتی ہے: انگلی کو سیدھا کرنے کی ہر کوشش ان ساختوں کو اور کس دیتی ہے جو اب اسے مڑا ہوا رکھے ہوئے ہیں۔ اسی لیے ایک چوٹ جو معمولی لگ رہی تھی، ہفتوں بعد ایک جمی ہوئی خرابی پیدا کر سکتی ہے، اور اسی لیے سادہ اسپلنٹ سے علاج کا موقع شروع ہی میں ہوتا ہے۔
وہ خرابی جو بوٹونیئر نہیں ہے
ایک انگلی سینٹرل سلپ کی کسی چوٹ کے بغیر بھی یہی شکل اختیار کر سکتی ہے، اور اس کا علاج بالکل مختلف ہے۔ بوٹونیئر اور سوڈو بوٹونیئر (pseudoboutonnière) خرابیاں اپنی اندرونی بناوٹ کی خرابی، تشخیص اور علاج میں مختلف ہیں [2]؛ سوڈو قسم درمیانی جوڑ پر والر پلیٹ (volar plate)، یعنی جوڑ کی ہتھیلی والی طرف کی سخت گدی، کی چوٹ سے پیدا ہوتی ہے، جس میں انگلی کے سرے کا جوڑ حد سے زیادہ پیچھے کی طرف کھنچنے کے بجائے دوسرے کے موڑنے پر معمول کے مطابق مڑ جاتا ہے۔
مریض کے معائنے کے وقت ان دونوں میں فرق انگلی کے سرے سے کیا جاتا ہے۔ اصل بوٹونیئر میں سرا حد سے زیادہ پیچھے کی طرف مڑا رہتا ہے اور موڑنے کی مزاحمت کرتا ہے، خاص طور پر جب درمیانی جوڑ کو سیدھا رکھا جائے؛ سوڈو بوٹونیئر میں یہ آسانی سے مڑ جاتا ہے۔ سوڈو بوٹونیئر پر اسپلنٹ ایسے لگانا جیسے وہ اصل بوٹونیئر ہو، غلط جوڑ کا علاج ہے۔
یہ ان چوٹوں کے ایک خاندان سے تعلق رکھتی ہے جن کی پہچان اس سے ہوتی ہے کہ ٹینڈن کہاں ناکام ہوتا ہے
بوٹونیئر، میلٹ فنگر (انگلی کا سرا نیچے لٹک جانا) اور سیجیٹل بینڈ (sagittal band) کی چوٹ کے ساتھ، سیدھا کرنے والے نظام کی تین بند (جلد کٹے بغیر ہونے والی) چوٹوں میں سے ایک ہے، جنہیں اس حصے کے لحاظ سے درجہ بند کیا جاتا ہے جہاں یہ نظام ناکام ہوتا ہے [3]۔ تینوں چوٹ کے چند دنوں کے اندر ایک سوجی ہوئی انگلی کی صورت میں سامنے آ سکتی ہیں جو غیر معمولی حالت میں رکھی ہو، اور ہر ایک کے لیے اسپلنٹ کی الگ پوزیشن درکار ہوتی ہے، اور یہی عملی وجہ ہے کہ ہفتوں کے اسپلنٹ کا فیصلہ کرنے سے پہلے واضح تشخیص تک پہنچنا ضروری ہے۔
حوالہ جات
[1] Geoghegan L, Wormald JCR, Adami RZ, Rodrigues JN. Central slip extensor tendon injuries: a systematic review of treatments. J Hand Surg Eur Vol. 2019;44(8):825-32. https://doi.org/10.1177/1753193419845311
[2] Hanson ZC, Thompson RG, Andrews JR, Lourie GM. Boutonniere versus pseudoboutonniere deformities: pathoanatomy, diagnosis, and treatment. J Hand Surg Am. 2023;48(5):489-97. https://doi.org/10.1016/j.jhsa.2022.10.019
[3] Lin JD, Strauch RJ. Closed soft tissue extensor mechanism injuries (mallet, boutonniere, and sagittal band). J Hand Surg Am. 2014;39(5):1005-11. https://doi.org/10.1016/j.jhsa.2013.11.018
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- A staged technique for the repair of traumatic boutonniere deformity allows the surgeon to divide the deformity into various categories and use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery [1].
- Differentiating a true boutonniere deformity from a pseudoboutonniere injury is critical in determining clinical management [2].
- A retrospective study of fifty-four longstanding post-burn boutonnière deformities was carried out to evaluate the problems associated with the surgical procedures [3].
- An understanding of the anatomy, clinical presentation, treatment options, and expected outcomes is crucial for optimal treatment of posttraumatic boutonnière and swan neck deformities [4].
- Early treatment of central slip injuries can prevent the deformity [5].
- Transection of the terminal extensor tendon is a useful procedure for salvage of the boutonniere deformity [6].
- No boutonniere deformities were produced in a series of 20 patients who had chronic mallet finger deformity treated with central slip tenotomy [7].
- Reconstruction of the central slip by the transverse retinacular ligament is not indicated for boutonnière deformities with severe contracture of the lateral band [8].
- The best indication for reconstruction of the central slip by the transverse retinacular ligament is in cases in which the central slip is defective and conservative treatment is not effective [8].
- Similar results occurred for chronic boutonniere deformity using serial casting for adequate extension followed by 3 months of relative motion flexion (RMF) orthotic use, which should be attempted prior to surgical intervention [9].
- A new surgical technique with early mobilization is an effective and simplified treatment of Boutonniere deformity [10].
- The natural history of the boutonnière deformity in rheumatoid arthritis is outlined, and a simple method of repair is described [11].
- Chronic boutonniere deformity will respond to relative motion flexion splinting if serial casting can place the proximal interphalangeal joint in less than -20° extension, and the patient actively uses the hand in a relative motion flexion orthosis for 3 months, recovering flexion [12].
- The Y-shaped tendon graft can be a useful procedure for the correction of chronic boutonniere deformity [13].
- In a patient series of 18 patients, the Y-shaped tendon graft provided good or excellent results in 16 patients [13].
- Extension splinting of the metacarpophalangeal (MP) joint may be effective if traumatic thumb injuries are treated before development of a boutonnière deformity [14].
- Congenital boutonniere deformity is understood as various embryonic developmental failures [15].
- A reliable surgical option for congenital boutonniere deformity involves central slip reconstruction [15].
- Extensor tenotomy to correct a boutonnière deformity of long standing markedly lessened disability with restoration of flexion of the distal joint [16].
- In chronic boutonniere deformity, when the lateral bands are deficient or damaged, the cross-lateral band reconstruction technique using palmaris longus autograft is a treatment option with satisfactory results [17].
- Extension splinting may be effective if traumatic thumb injuries are treated before deformity development [18].
- Surgical treatment with advancement of the extensor pollicis brevis tendon and imbrication of the dorsoradial capsule is necessary once a traumatic thumb boutonnière deformity is established [18].
- The prevalence of boutonnière deformity without rheumatoid arthritis or trauma is approximately 13% [19].
- Current concepts relating to the presentation and treatment of closed soft tissue injuries of the extensor mechanism in zones I, III, and V, commonly known as mallet finger, boutonniere deformities, and sagittal band injuries, are summarized [20].
- Long-term results following soft tissue reconstruction for boutonniere finger deformity in rheumatoid arthritis are unreliable [24].
- Recurrent or persistent deformity in rheumatoid arthritis is best treated with a salvage procedure [24].
Anatomy & Pathophysiology
Extensor Mechanism Anatomy
- The extensor mechanism of the finger at the level of the proximal interphalangeal (PIP) joint consists of both intrinsic and extrinsic contributions [28].
- The extensor tendon entering the digit is the continuation of the extensor digitorum communis (EDC), with contributions from the extensor indicis proprius in the index finger and the extensor digiti quinti in the small finger [28].
- In 30% of cases, the EDC has a separate insertion into the base of the proximal phalanx, but extension of the metacarpophalangeal (MP) joint typically occurs through the pull of the sagittal bands [28].
- The principal bony insertion of the extrinsic digital extensors is on the dorsal proximal aspect of the middle phalanx [32].
- Metacarpophalangeal joint extension is provided by extrinsic extensor force transmitted through the sagittal bands [32].
- Distal interphalangeal joint extension is achieved through conjoined lateral bands composed of tendinous slips from both extrinsic and intrinsic tendons [32].
- The deep head of each dorsal interosseous muscle forms a lateral tendon, or lateral band, at the level of the MP joint [41].
- At the level of the middle of the proximal phalanx, transverse fibers arch dorsally from each lateral band to join over the dorsum of the finger, flexing the proximal phalanx [41].
- Oblique fibers (spiral fibers) from the lateral bands sweep over the distal third of the proximal phalanx to insert onto the lateral tubercles at the base of the middle phalanx, extending the middle phalanx [41].
- The lateral bands are joined by the lateral slips of the extensor tendon to form the conjoined lateral band [41].
- The two conjoined lateral bands to each finger unite at the distal third of the middle phalanx to form the terminal tendon, which inserts at the base of the distal phalanx to extend it [41].
- The volar interossei form the ulnar lateral band of the index finger and the radial lateral band of the ring and little fingers [41].
- The flexor digiti quinti brevis is structurally and functionally similar to the deep head of the dorsal interossei, forming the ulnar lateral band of the little finger [41].
Pathophysiology & Biomechanics
- A boutonniere deformity requires subluxation of the lateral bands volar to the axis of rotation of the PIP joint [22].
- Damage to the central slip alone does not cause a boutonniere deformity [22].
- A boutonniere deformity occurs only when the central slip, triangular ligament, and transverse and oblique fibers of the interosseous hood are all damaged [22].
- Detachment of the central slip from the middle phalanx produces a decrease in extension of the PIP joint [22].
- When the transverse and oblique fibers of the interosseous hood are divided in addition to the central slip, extension at the PIP joint is further decreased [22].
- Early treatment of central slip injuries can prevent the development of the deformity [5].
- The extensor mechanism is a complex structure that demands a delicate balance from intrinsic and extrinsic tendons of the hand [28].
- Injury to the extensor mechanism can disrupt this delicate balance, leading to significant sequelae [28].
- Understanding the anatomy, clinical presentation, treatment options, and expected outcomes is crucial for optimal treatment of posttraumatic boutonnière and swan neck deformities [4].
Classification
- A staged management plan allows the surgeon to divide traumatic boutonniere deformity into various categories and use the operative procedure indicated for each particular problem [1].
- The choice of surgical procedure for rheumatoid boutonniere deformity is dependent on accurate staging of the deformity, which is based on the flexibility of the proximal interphalangeal joint and the state of the articular cartilage [23].
- In a cadaveric model, damage to the central slip alone does not cause a boutonniere deformity [22].
- The boutonniere deformity requires subluxation of the lateral bands volar to the axis of rotation of the PIP joint [22].
- In a cadaveric model, the central slip, triangular ligament, and oblique fibers need to all be damaged to cause subluxation of the lateral bands which leads to an acute boutonniere deformity [29].
- Anterior dislocation of the proximal interphalangeal joint is associated with ruptures of the central slip of the extensor mechanism and results in boutonnière deformity unless repaired [27].
- The incidence of uncorrectable swan-neck and boutonniere deformities is estimated to be between 8% and 16% during the first 2 years after the onset of systemic disease in rheumatoid arthritis [23].
- The prevalence of boutonniere deformities in patients with established rheumatoid arthritis is approximately 36% [23].
Clinical Presentation
Diagnostic Differentiation and Classification
- The surgeon can divide the boutonniere deformity into various categories to use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery [1].
Etiology and Pathomechanics
- The cause of boutonniere deformity in rheumatoid arthritis is chronic synovitis of the proximal interphalangeal joint [23].
- Combined injury of the central slip, triangular ligament, and transverse and oblique fibers of the interosseous hood causes a boutonniere deformity [22].
Prevalence and Natural History
- A swan-neck or boutonniere deformity occurs in approximately half of patients with rheumatoid arthritis [23].
- The incidence of uncorrectable swan-neck and boutonniere deformities is estimated to be between 8% and 16% during the first 2 years after the onset of systemic disease [23].
- The prevalence of finger deformities in patients with established rheumatoid arthritis is approximately 36% for boutonniere deformities [23].
- The natural history of the boutonnière deformity in rheumatoid arthritis is outlined in the literature [11].
Clinical Assessment and Testing
- The central slip tenodesis test detects disruption of the central slip before the boutonniere deformity becomes established [34].
- The central slip tenodesis test is applicable in uncooperative children and unconscious patients [34].
- Treating swan neck and boutonniere deformities of the PIP joint requires understanding the cause, biomechanical changes, and articular status [26].
Investigations
Clinical Examination and Diagnostic Tests
- A careful physical examination is essential to direct care and future testing if indicated [31].
- Diagnostic tests such as imaging and serum laboratory studies are useful in the determination of pathology but can be expensive, time consuming, and often nonspecific [31].
Biomechanical and Pathomechanical Assessment
Imaging and Advanced Modalities
- A computational 3D model validation reassures the reliability of research in understanding the pathomechanics of boutonniere deformity [21].
Treatment
Non-Operative
- Early treatment of central slip injuries can prevent the development of boutonniere deformity [5].
- Extension splinting of the metacarpophalangeal joint may be effective for traumatic thumb boutonniere deformity if treated before the deformity develops [14].
- Extension splinting may be effective for traumatic thumb boutonniere deformity if treated before deformity development [18].
- Chronic boutonniere deformity responds to relative motion flexion splinting if serial casting places the proximal interphalangeal joint in less than -20° extension and the patient actively uses a relative motion flexion orthosis for 3 months [12].
- Serial casting for adequate extension followed by 3 months of relative motion flexion orthotic use should be attempted prior to surgical intervention for chronic boutonniere deformity [9].
- The use of relative motion flexion orthoses is effective in increasing active distal interphalangeal joint flexion and improving proximal interphalangeal joint extension in patients with Burton stage 1 chronic boutonniere deformity [30].
- Conservative treatment of closed central slip injuries involves immobilization of the proximal interphalangeal, distal interphalangeal, and metacarpophalangeal joints in full extension for four weeks followed by a Capener spring splint for two further weeks [92].
- In a review of 115 central slip injuries, 17 of 24 patients treated conservatively achieved an outcome of less than a 20° extension deficit at the proximal interphalangeal joint and more than 80% return of proximal interphalangeal joint flexion [92].
- Patients treated for central slip injuries within six weeks of injury had better outcomes than those treated later [92].
Operative
- A staged technique allows the surgeon to divide traumatic boutonniere deformity into various categories and use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery [1].
- Reconstruction of the central slip by the transverse retinacular ligament is best indicated in cases in which the central slip is defective and conservative treatment is not effective [8].
- A simple method of repair for the rheumatoid boutonnière deformity is described in the literature [11].
- In a patient series, the Y-shaped tendon graft provided good or excellent results in 16 of 18 patients with chronic boutonniere deformity [13].
- Surgical treatment with advancement of the extensor pollicis brevis tendon and imbrication of the dorsoradial capsule is necessary once a traumatic boutonnière deformity of the thumb is established [18].
- The cross-lateral band reconstruction technique using palmaris longus autograft is a treatment option with satisfactory results for chronic boutonniere deformity when the lateral bands are deficient or damaged [17].
- A reliable surgical option involving central slip reconstruction is suggested for the congenital form of boutonniere deformity [15].
- A simple staged procedure using a central slip facilitation device is a valid alternative in the management of severe Dupuytren's proximal interphalangeal joint contracture, demonstrating reliable, reproducible correction of the deformity and acceptable patient outcomes [38].
Complications
- In a patient series of 18 patients, the Y-shaped tendon graft provided good or excellent results in 16 of 18 patients for the correction of chronic boutonniere deformity [13].
- Extension splinting of the MP joint may be effective if traumatic thumb injuries are treated before development of a boutonnière deformity [14].
- The case extends understanding of congenital boutonniere deformity as various embryonic developmental failures and suggests a reliable surgical option involving central slip reconstruction [15].
- Surgical treatment with advancement of the extensor pollicis brevis tendon and imbrication of the dorsoradial capsule is necessary once a boutonnière deformity is established in the thumb [18].
- This article summarizes current concepts relating to the presentation and treatment of closed soft tissue injuries of the extensor mechanism in zones I, III, and V, commonly known as mallet finger, boutonniere deformities, and sagittal band injuries [20].
- This validation reassures the reliability of the research in understanding the pathomechanics of boutonniere deformity [21].
- In a cadaver model, detachment of the central slip from the middle phalanx produced a decrease in extension of the PIP joint [22].
- When the transverse and oblique fibers of the interosseous hood were also divided after central slip detachment, extension at the PIP joint was further decreased [22].
- A boutonniere deformity occurred only when all 3 structures (central slip, transverse and oblique fibers of the interosseous hood, and triangular ligament) were damaged [22].
- Division of the central slip leads to loss of extension at the PIP joint [22].
- The prevalence of finger deformities in patients with established rheumatoid arthritis is approximately 14% for swan-neck deformities and 36% for boutonniere deformities [23].
- In the later stages of both swan-neck and boutonniere deformities, soft-tissue procedures alone may not result in lasting operative correction [23].
- Long-term results following soft tissue reconstruction are unreliable [24].
- Recurrent or persistent deformity is best treated with a salvage procedure [24].
- Treating swan neck and boutonniere deformities of the PIP joint is a difficult challenge that requires understanding the cause, biomechanical changes, and articular status [26].
- Anterior dislocation of the proximal interphalangeal joint is associated with ruptures of the central slip of the extensor mechanism [27].
- Anterior dislocation of the proximal interphalangeal joint results in boutonnière deformity unless repaired [27].
Recovery
Non-Operative Management
- Serial casting for adequate extension followed by 3 months of relative motion flexion (RMF) orthotic use should be attempted prior to surgical intervention for chronic boutonniere deformity [9].
- Chronic boutonniere deformity responds to relative motion flexion splinting if serial casting places the proximal interphalangeal joint in less than -20° extension and the patient actively uses the hand in a relative motion flexion orthosis for 3 months, recovering flexion [12].
- Extension splinting of the metacarpophalangeal joint may be effective for traumatic thumb boutonniere injuries if treated before the development of a boutonnière deformity [14].
Operative Management
- A staged technique allows the surgeon to divide the traumatic boutonniere deformity into various categories and use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery [1].
- The Y-shaped tendon graft provided good or excellent results in 16 of 18 patients for the correction of chronic boutonniere deformity [13].
- Reconstruction of the central slip by the transverse retinacular ligament is indicated in cases in which the central slip is defective and conservative treatment is not effective, but is not indicated for boutonnière deformities with severe contracture of the lateral band [8].
- A simple method of repair for the correction of the rheumatoid boutonnière deformity has been described [11].
- A new surgical technique with early mobilization for chronic boutonniere deformity was reported to be an effective and simplified treatment in 11 cases [10].
- Central slip reconstruction is a reliable surgical option for the congenital form of boutonniere deformity [15].
Outcomes and Prognosis
- Early treatment of central slip injuries can prevent the boutonniere deformity [5].
- Long-term results following soft tissue reconstruction for boutonniere finger deformity in rheumatoid arthritis are unreliable, and recurrent or persistent deformity is best treated with a salvage procedure [24].
- In the later stages of rheumatoid boutonniere deformities, soft-tissue procedures alone may not result in lasting operative correction [23].
- A patient with boutonniere deformity of the second toe after planter dislocation of the proximal interphalangeal joint reported neither deformity nor difficulty when last seen 22 months after the operation [95].
Key Evidence
- [L4] With this plan of management, the surgeon is able to divide the boutonniere deformity into various categories and then use the operative procedure indicated for each particular problem, often avoiding unnecessary surgery. [1] (10.1016/s0363-5023(83)80009-4)
- [L5] Differentiating a true boutonniere deformity from a pseudoboutonniere injury is critical in determining clinical management. [2] (10.1016/j.jhsa.2022.10.019)
- [L4] A retrospective study of fifty-four longstanding post-burn boutonnière deformities was carried out to evaluate the problems associated with the surgical procedures. [3] (10.1016/0266-7681(86)90006-9)
- [L5] An understanding of the anatomy, clinical presentation, treatment options, and expected outcomes is crucial for optimal treatment of posttraumatic boutonnière and swan neck deformities. [4] (10.5435/jaaos-d-14-00272)
- [L5] The paper outlines the anatomy, pathoanatomy, and treatment concepts for boutonniere deformity, emphasizing that early treatment of central slip injuries can prevent the deformity. [5] (10.1016/s0749-0712(21)00060-3)
- [L4] Transection of the terminal extensor tendon is a useful procedure for salvage of the boutonniere deformity. [6] (10.1016/s0749-0712(21)00065-2)
- [L4] No boutonniere deformities were produced in this series of 20 patients who had chronic mallet finger deformity. [7] (10.1016/s0363-5023(87)80205-8)
- [L4] This procedure is not indicated for boutonnière deformities with severe contracture of the lateral band; its best indication is in cases in which the central slip is defective and conservative treatment is not effective. [8] (10.1016/0266-7681(90)90080-n)
- [L4] Similar results occurred for chronic boutonniere deformity using serial casting for adequate extension followed by 3 months of RMF orthotic use, which should be attempted prior to surgical intervention. [9] (10.1016/j.jht.2023.02.005)
- [L4] Our technique is an effective and simplified treatment of Boutonniere deformity. [10] (10.1097/bth.0000000000000152)
- [L4] The natural history of the boutonnière deformity in rheumatoid arthritis is outlined, and a simple method of repair is described. [11] (10.2106/00004623-196951070-00009)
- [L4] Chronic boutonniere deformity will respond to relative motion flexion splinting if serial casting can place the proximal interphalangeal joint in less than -20° extension, and the patient actively uses the hand in a relative motion flexion orthosis for 3 months, recovering flexion. [12] (10.1097/sap.0000000000002307)
- [L4] The Y-shaped tendon graft can be a useful procedure for the correction of chronic boutonniere deformity; in our patient series, this provided good or excellent results in 16 of 18 patients. [13] (10.1016/j.jhsa.2021.01.003)
- [L4] Extension splinting of the MP joint may be effective if these injuries are treated before development of a boutonnière deformity. [14] (10.1016/s0266-7681(00)80024-8)
- [Case_report] The case extends understanding of congenital boutonniere deformity as various embryonic developmental failures and suggests a reliable surgical option involving central slip reconstruction. [15] (10.1016/j.jhsa.2014.05.030)
- [L4] In chronic boutonniere deformity, when the lateral bands are deficient or damaged, the cross-lateral band reconstruction technique using palmaris longus autograft is a treatment option with satisfactory results. [17] (10.1016/j.jhsa.2017.04.010)
- [L4] Extension splinting may be effective if treated before deformity development, but surgical treatment with advancement of the extensor pollicis brevis tendon and imbrication of the dorsoradial capsule is necessary once a boutonnière deformity is established. [18] (10.1054/jhsb.1999.0303)
- [L3] The prevalence of boutonnière deformity without rheumatoid arthritis or trauma is approximately 13%. [19] (10.1177/1753193417704610)
- [L5] This article summarizes current concepts relating to the presentation and treatment of closed soft tissue injuries of the extensor mechanism in zones I, III, and V, commonly known as mallet finger, boutonniere deformities, and sagittal band injuries. [20] (10.1016/j.jhsa.2013.11.018)
- [L5] This validation reassures the reliability of the research in understanding the pathomechanics of boutonniere deformity. [21] (10.1186/s13018-025-06329-3)
- [L5] [22] (10.1016/j.jhsa.2017.07.011)
- [L5] [23] (10.5435/00124635-199903000-00002)
- [L5] Long-term results following soft tissue reconstruction are unreliable, and recurrent or persistent deformity is best treated with a salvage procedure. [24] (10.1016/j.jhsa.2011.05.029)
- [L4] Treating swan neck and boutonniere deformities of the PIP joint is a difficult challenge that requires understanding the cause, biomechanical changes, and articular status. [26] (10.1016/j.hcl.2017.12.006)
- [Paper] [28] (10.1016/j.hcl.2012.05.044)
- [Paper] In a cadaveric model, the central slip, triangular ligament, and oblique fibers need to all be damaged to cause subluxation of the lateral bands which leads to an acute boutonniere deformity. [29] (10.1016/s0363-5023(12)60014-8)
- [L4] The use of RMFO is effective in increasing active distal interphalangeal joint flexion and improving PIP extension in patients with Burton stage 1 chronic boutonniere deformity. [30] (10.1016/j.jhsa.2022.08.007)
- [Paper] The test detects disruption of the central slip before the boutonniere deformity becomes established and is applicable in uncooperative children and unconscious patients. [34] (10.1016/0266-7681(94)90057-4)
- [L4] The simple staged procedure is a valid alternative in the management of severe Dupuytren's PIPJ contracture, demonstrating reliable, reproducible correction of the deformity and acceptable patient outcomes. [38] (10.1177/1753193412439673)
- [L4] [92] (10.1177/1758998318822663)
- [Case_report] The patient reported neither deformity nor difficulty when last seen 22 months after the operation. [95] (10.1007/s00402-009-0816-x)
References
[1] A staged technique for the repair of the traumatic boutonniere deformity. The Journal of Hand Surgery. 1983. DOI: 10.1016/s0363-5023(83)80009-4
[2] Boutonniere Versus Pseudoboutonniere Deformities: Pathoanatomy, Diagnosis, and Treatment. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2022.10.019
[3] Reconstructive surgery of the post-burn boutonnière deformity. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1986. DOI: 10.1016/0266-7681(86)90006-9
[4] Posttraumatic Boutonnière and Swan Neck Deformities. Journal of the American Academy of Orthopaedic Surgeons. 2015. DOI: 10.5435/jaaos-d-14-00272
[5] BOUTONNIERE DEFORMITY. Hand Clinics. 1995. DOI: 10.1016/s0749-0712(21)00060-3
[6] TREATMENT OF THE CHRONIC BOUTONNIERE DEFORMITY BY EXTENSOR TENOTOMY. Hand Clinics. 1995. DOI: 10.1016/s0749-0712(21)00065-2
[7] Central slip tenotomy for chronic mallet finger deformity. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80205-8
[8] Reconstruction of the Central Slip by the Transverse Retinacular Ligament for Boutonnière Deformity. Journal of Hand Surgery. 1990. DOI: 10.1016/0266-7681(90)90080-n
[9] The relative motion concept in acute and chronic boutonniere deformity: Invited commentary. Journal of Hand Therapy. 2023. DOI: 10.1016/j.jht.2023.02.005
[10] Chronic Boutonniere Deformities, Supple, or Stiff: A New Surgical Technique With Early Mobilization in 11 Cases. Techniques in Hand & Upper Extremity Surgery. 2017. DOI: 10.1097/bth.0000000000000152
[11] Correction of the Rheumatoid Boutonnière Deformity. The Journal of Bone & Joint Surgery. 1969. DOI: 10.2106/00004623-196951070-00009
[12] A Paradigm Shift in Managing Acute and Chronic Boutonniere Deformity. Annals of Plastic Surgery. 2020. DOI: 10.1097/sap.0000000000002307
[13] Y-Shaped Tendon Graft—A Technique in the Reconstruction of Posttraumatic Chronic Boutonniere Deformity. The Journal of Hand Surgery. 2021. DOI: 10.1016/j.jhsa.2021.01.003
[14] Traumatic Boutonnière Deformity of the Thumb. Journal of Hand Surgery. 2000. DOI: 10.1016/s0266-7681(00)80024-8
[15] Restoration of the Central Slip in Congenital Form of Boutonniere Deformity: Case Report. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.05.030
[16] Extensor Tenotomy for Chronic Boutonniere Deformity of the Finger: REPORT OF TWO CASES.. The Journal of Bone and Joint Surgery. American Volume. 1965.
[17] Chronic Boutonniere Deformity: Cross-Lateral Band Technique Using Palmaris Longus Autograft. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.04.010
[18] TRAUMATIC BOUTONNIÈRE DEFORMITY OF THE THUMB. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 2000. DOI: 10.1054/jhsb.1999.0303
[19] Thumb boutonnière deformity without rheumatoid arthritis or trauma. Journal of Hand Surgery (European Volume). 2017. DOI: 10.1177/1753193417704610
[20] Closed Soft Tissue Extensor Mechanism Injuries (Mallet, Boutonniere, and Sagittal Band). The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2013.11.018
[21] Assessment of the ligamentous stress distribution in the pathomechanics of the boutonniere deformity through a computational 3D model. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-06329-3
[22] Biomechanics of the Acute Boutonniere Deformity. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2017.07.011
[23] Operative Correction of Swan-Neck and Boutonniere Deformities in the Rheumatoid Hand. Journal of the American Academy of Orthopaedic Surgeons. 1999. DOI: 10.5435/00124635-199903000-00002
[24] Treatment of Boutonniere Finger Deformity in Rheumatoid Arthritis. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2011.05.029
[26] Treating the Proximal Interphalangeal Joint in Swan Neck and Boutonniere Deformities. Hand Clinics. 2018. DOI: 10.1016/j.hcl.2017.12.006
[27] Anterior dislocation of the proximal interphalangeal joint. A cause of rupture of the central slip of the extensor mechanism.. The Journal of bone and joint surgery. American volume. 1970.
[28] Boutonnière and Pulley Rupture in Elite Athletes. Hand Clinics. 2012. DOI: 10.1016/j.hcl.2012.05.044
[29] Biomechanics of the Acute Boutonniere Deformity. The Journal of Hand Surgery. 2012. DOI: 10.1016/s0363-5023(12)60014-8
[30] The Use of Relative Motion Flexion Orthoses for Chronic Boutonniere Deformity. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2022.08.007
[31] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[32] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > Image DISORDERS OF THE MUSCULATURE OF THE HAND.
[34] The Central Slip Tenodesis Test for Early Diagnosis of Potential Boutonnière Deformities. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90057-4
[38] Management of severe Dupuytren’s contracture of the proximal interphalangeal joint with use of a central slip facilitation device. Journal of Hand Surgery (European Volume). 2012. DOI: 10.1177/1753193412439673
[41] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[92] Therapeutic management of closed central slip injuries: Outcome of a service evaluation. Hand Therapy. 2019. DOI: 10.1177/1758998318822663
[95] Boutonniere deformity of the second toe after planter dislocation of proximal interphalangeal joint: a case report. Archives of Orthopaedic and Trauma Surgery. 2009. DOI: 10.1007/s00402-009-0816-x