Patients › Rehabilitation
انگلی کے درمیانی (PIP) جوڑ کی تبدیلی
انگلی کے گھسے ہوئے درمیانی جوڑ (PIP جوڑ) کی سلیکون سے تبدیلی کے بعد صحت یابی کا ایک محفوظ منصوبہ، جس میں حرکت شروع کرنے کی رفتار اس بات پر منحصر ہے کہ سرجن نے انگلی کے سامنے (ہتھیلی کی طرف) سے رسائی حاصل کی یا پشت کی طرف سے۔
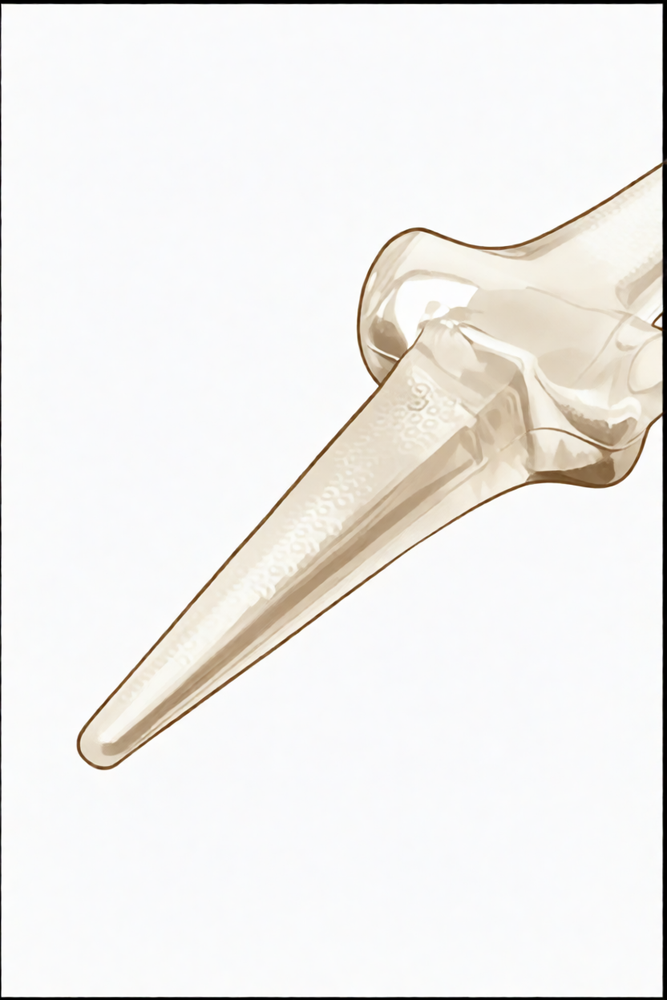
یہ پروٹوکول انگلی کے گھسے ہوئے درمیانی جوڑ کی تبدیلی (proximal interphalangeal (PIP) joint، یعنی انگلی کا درمیانی جوڑ) کے بعد آپ کی صحت یابی میں رہنمائی کرتا ہے، جس میں اس جوڑ کی جگہ ایک لچکدار سلیکون اسپیسر (spacer) لگایا جاتا ہے، اور یہ آپریشن ڈاکٹر کیرن ہِرپرا Mater Private Hospital Rockhampton میں کرتے ہیں۔ یہ صفحہ گھر پر کی جانے والی آپ کی ورزشوں کے پروگرام سے شروع ہوتا ہے، اور اس کے بعد وہ منظم طبی پروٹوکول آتا ہے جو آپ کے ہینڈ تھراپسٹ (ہاتھ کی بحالی کے ماہر) کے لیے لکھا گیا ہے۔ تھراپی کے پہلے دورے پر یہ صفحہ یا اس کی پی ڈی ایف ساتھ لے کر جائیں تاکہ آپ کی بحالی کا علاج مربوط رہے۔ آپ کی صحت یابی کس طرح آگے بڑھتی ہے، اس کے مطابق آپ کا تھراپسٹ اس منصوبے میں تبدیلی کر سکتا ہے۔
اگر سرجری کے بعد آپ کو اپنے زخم کے بارے میں کوئی تشویش ہو تو کلینک سے رابطہ کریں۔ اکثر یہ مددگار ہوتا ہے کہ زخم کی تصویر لے کر جائزے کے لیے ای میل کر دیں۔
کیا توقع رکھیں
آپ کی انگلی کا درمیانی جوڑ آرتھرائٹس (جوڑ کی خرابی اور سوزش) کی وجہ سے گھس چکا تھا، جس سے اس میں درد اور اکڑاؤ رہتا ہے۔ اس آپریشن میں جوڑ کی گھسی ہوئی سطحیں نکال دی جاتی ہیں اور دونوں ہڈیوں کے درمیان ایک لچکدار سلیکون اسپیسر (سوانسن طرز کا امپلانٹ، یعنی جسم میں لگایا گیا مصنوعی پرزہ؛ Swanson-type implant) رکھ دیا جاتا ہے۔ یہ اسپیسر کوئی سخت مشینی قبضہ (hinge) نہیں ہے؛ یہ ایک لچکدار اسپیسر ہے جو ہڈیوں کو ایک دوسرے سے الگ رکھتا ہے، انگلی کو مڑنے دیتا ہے، اور آپ کے اپنے زخم بھرنے سے بننے والے سخت ریشے (scar tissue) کو اپنے گرد ایک نیا سہارا دینے والا غلاف بنانے دیتا ہے۔ اس کا سب سے بڑا اور سب سے قابلِ اعتماد فائدہ درد سے نجات ہے۔ آپ کو پوری، نارمل حد کے بجائے مڑنے کی ایک کارآمد مگر محدود قوس (عام طور پر تقریباً 40 سے 60 ڈگری) کی توقع بھی رکھنی چاہیے۔ زیادہ تر لوگ بہت مطمئن ہوتے ہیں کیونکہ درد ختم ہو جاتا ہے اور انگلی کو استعمال کرنا آرام دہ ہو جاتا ہے۔
آپ کی صحت یابی کے بارے میں سب سے اہم بات یہ ہے کہ سرجن نے کس طرف سے جوڑ تک رسائی حاصل کی، کیونکہ اسی سے طے ہوتا ہے کہ آپ کتنی جلدی انگلی کو حرکت دے سکتے ہیں:
- سامنے سے (ہتھیلی کی طرف سے، volar approach): انگلی کی پشت پر موجود سیدھا کرنے والا ٹینڈن (tendon)، یعنی وہ مضبوط ڈوری جو پٹھے کو ہڈی سے جوڑتی ہے، پوری طرح محفوظ رہتا ہے۔ چونکہ پشت پر کسی چیز کو ٹھیک ہونا نہیں ہوتا، اس لیے عام طور پر آپ چند دنوں کے اندر انگلی کو حرکت دینا شروع کر سکتے ہیں۔
- پشت کی طرف سے (dorsal approach): جوڑ تک پہنچنے کے لیے سیدھا کرنے والے ٹینڈن (سینٹرل سلپ، central slip) کو چیرنا یا اٹھانا پڑتا ہے، اور پھر اس کی مرمت کی جاتی ہے۔ پہلے اس مرمت کی حفاظت ضروری ہے، اس لیے شروع میں انگلی کو اسپلنٹ میں سیدھا رکھا جاتا ہے اور موڑنا زیادہ آہستہ آہستہ، آپ کے ہینڈ تھراپسٹ کی رہنمائی میں، شروع کیا جاتا ہے۔
آپ کا ہینڈ تھراپسٹ آپ کی سرجری کے راستے کے مطابق منصوبے پر عمل کرے گا۔ ڈاکٹر ہِرپرا انہیں بتائیں گے کہ کون سا راستہ استعمال کیا گیا، اور نیچے دیے گئے اوقات اسی کے مطابق ترتیب دیے گئے ہیں۔ آپ کا آپریشن جس طرف سے بھی ہوا ہو، نیا جوڑ ایک قبضے کی طرح ہے: یہ سیدھی لکیر میں مڑنا اور سیدھا ہونا پسند کرتا ہے، لیکن پہلو کی طرف دھکیلا جانا یا مروڑا جانا پسند نہیں کرتا۔ اسے پہلو کی طرف کے دباؤ سے بچانا ہی اسے طویل مدت تک مستحکم رکھتا ہے۔
احتیاطیں اور پابندیاں
- انگلی کو صرف سیدھی لکیر میں حرکت دیں (موڑنا اور سیدھا کرنا) اور آپریشن والی انگلی پر پہلو کی طرف یا مروڑنے والے کسی بھی زور سے بچیں۔ نیا جوڑ ایک قبضے کی طرح ہے اور پہلو کا دباؤ اسے ڈھیلا یا ٹیڑھا کر سکتا ہے۔
- اپنا اسپلنٹ ہدایت کے مطابق پہنیں، اور سرگرمی کے دوران انگلی کو سیدھی سمت میں چلانے کے لیے بڈی اسٹریپنگ (buddy strapping، یعنی انگلی کو ساتھ والی انگلی کے ساتھ ٹیپ سے باندھنا) استعمال کریں۔
- اگر آپ کی سرجری انگلی کی پشت کی طرف سے ہوئی ہے تو شروع میں دی گئی حد سے آگے اپنی انگلی کو خود سیدھا کرنے کی کوشش ہرگز نہ کریں: سیدھا کرنے والا ٹینڈن ابھی ٹھیک ہو رہا ہے۔
- جب تک آپ کا ہینڈ تھراپسٹ طاقت بڑھانے کی ورزشوں کی اجازت نہ دے (عام طور پر تقریباً چھ ہفتوں سے)، تب تک نہ مضبوطی سے گرفت کریں، نہ زور سے چٹکی کی گرفت کریں، اور نہ کوئی بھاری یا مروڑنے والا کام کریں۔
- شروع ہی سے انگلی کے باقی جوڑوں، اپنی کلائی اور اپنے کندھے کو حرکت میں رکھیں، اور ہلکے روزمرہ کاموں کے لیے ہاتھ کو اتنا استعمال کریں جتنا آرام سے ہو سکے۔
زخم، سوجن اور زخم کے نشان کی دیکھ بھال کے لیے پریکٹس کی زخم کی دیکھ بھال والی رہنمائی دیکھیں۔
آپ کی ورزشیں
Kieran Hirpara 4.0
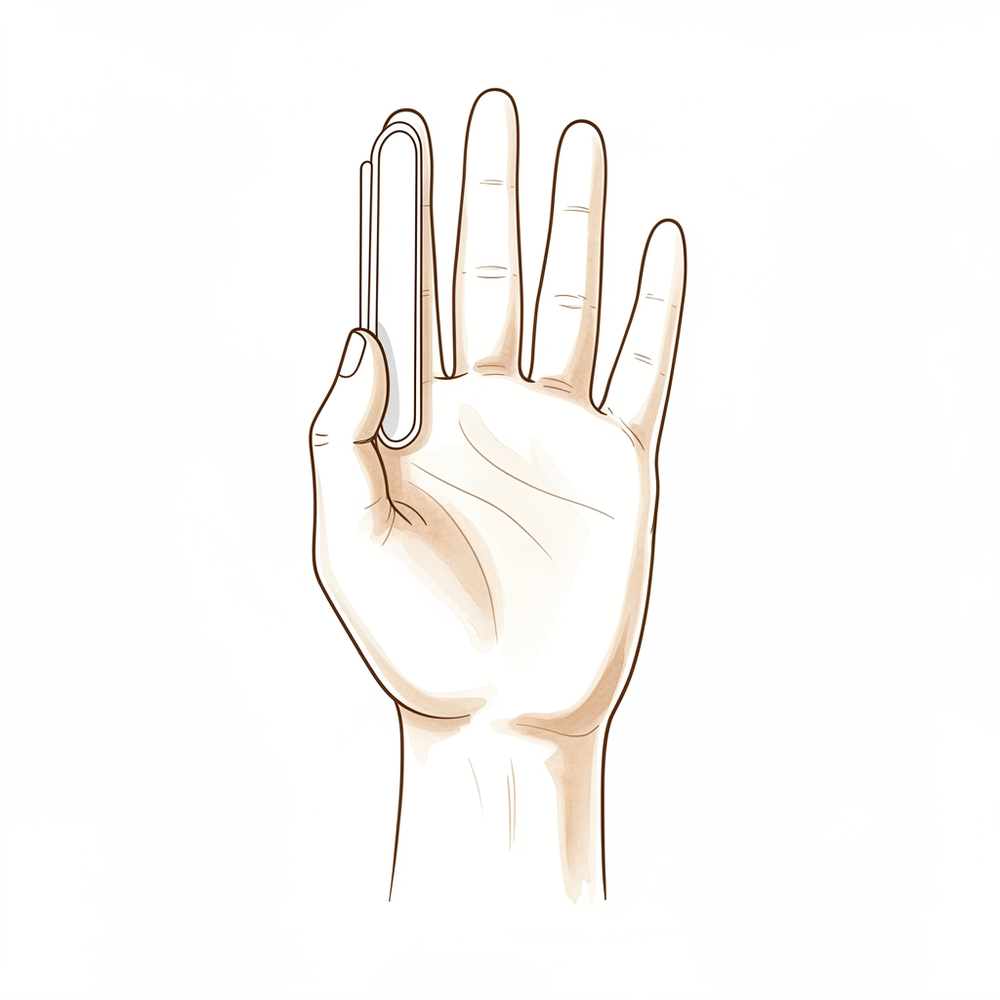
محفوظ طریقے سے اپنی طاقت سے موڑنا (پی آئی پی جوڑ)
باقی انگلیوں اور اسپلنٹ سے ہاتھ کے باقی حصے کو سہارا دیتے ہوئے، آپریشن والی انگلی کے درمیانی جوڑ کو اس حد کے اندر آہستگی سے موڑیں اور سیدھا کریں جو آپ کے ہینڈ تھراپسٹ نے طے کی ہے۔ حرکت آہستہ اور سیدھی رکھیں: انگلی کو ایک طرف ہٹنے دیے بغیر صاف سیدھی لکیر میں موڑیں اور سیدھا کریں۔ اس سے نیا جوڑ حرکت میں رہتا ہے تاکہ وہ اکڑ نہ جائے۔
10 بار، دن میں کئی بار، اپنی طے شدہ حد کے اندر
Kieran Hirpara 4.0
اپنی طاقت سے سیدھا کرنا (extension)
آپریشن والی انگلی کو جتنا ممکن ہو پورا اور سیدھا آہستگی سے سیدھا کریں، پھر ڈھیلا چھوڑ دیں۔ اگر آپ کی سرجری انگلی کی پشت کی طرف سے ہوئی ہے تو یہی وہ حرکت ہے جس کی شروع میں حفاظت کرنی ہے: آپ کا ہینڈ تھراپسٹ ٹھیک ٹھیک بتائے گا کہ کتنا اور کب کرنا ہے، کیونکہ سیدھا کرنے والے ٹینڈن کو پہلے ٹھیک ہونا ضروری ہے۔ اس میں کبھی زبردستی نہ کریں۔
10 بار، دن میں کئی بار، رہنمائی کے مطابق
Kieran Hirpara 4.0
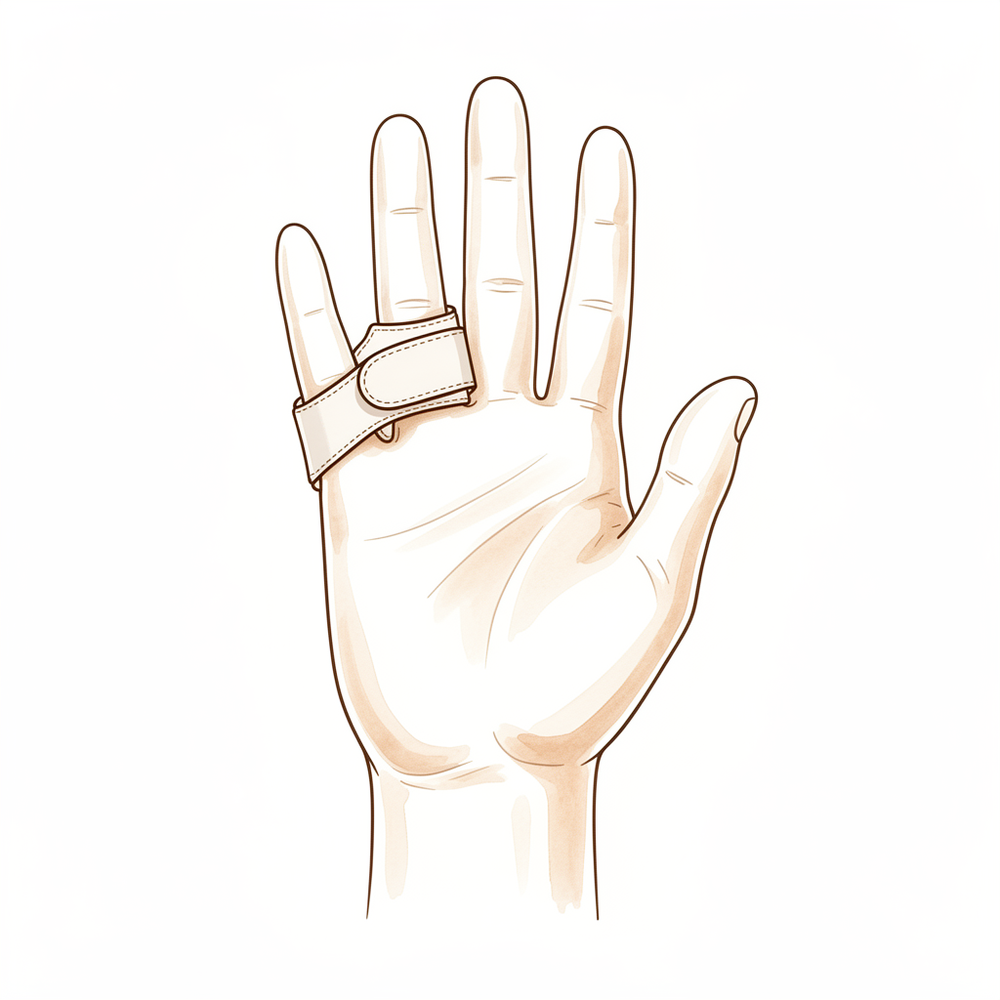
بڈی اسٹریپنگ (ساتھ والی انگلی سے باندھنا)
آپریشن والی انگلی کو ساتھ والی انگلی کے ساتھ آہستگی سے ٹیپ کریں (درمیانی جوڑ کے اوپر اور نیچے، جوڑ کے عین اوپر نہیں)۔ ساتھ والی انگلی ایک اسپلنٹ کا کام کرتی ہے جو آپ کی انگلی کو سیدھی لکیر میں مڑنے اور سیدھا ہونے میں رہنمائی دیتی ہے اور اسے نئے جوڑ پر پہلو کی طرف جھکنے سے روکتی ہے۔ مشورے کے مطابق اسے سرگرمی کے دوران پہنیں۔
ہلکی سرگرمی کے دوران پہنیں، اپنے ہینڈ تھراپسٹ کی رہنمائی کے مطابق
Kieran Hirpara 4.0
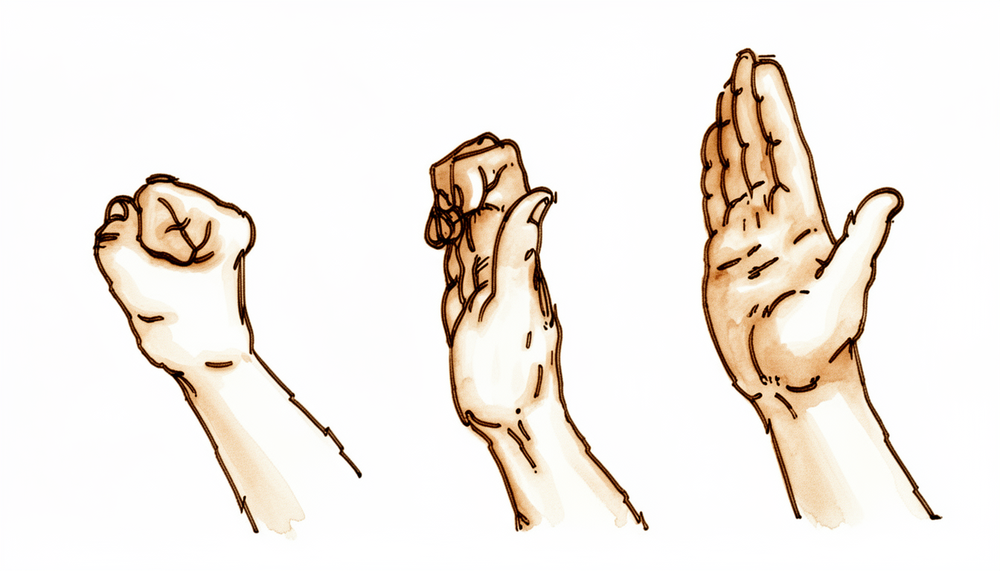
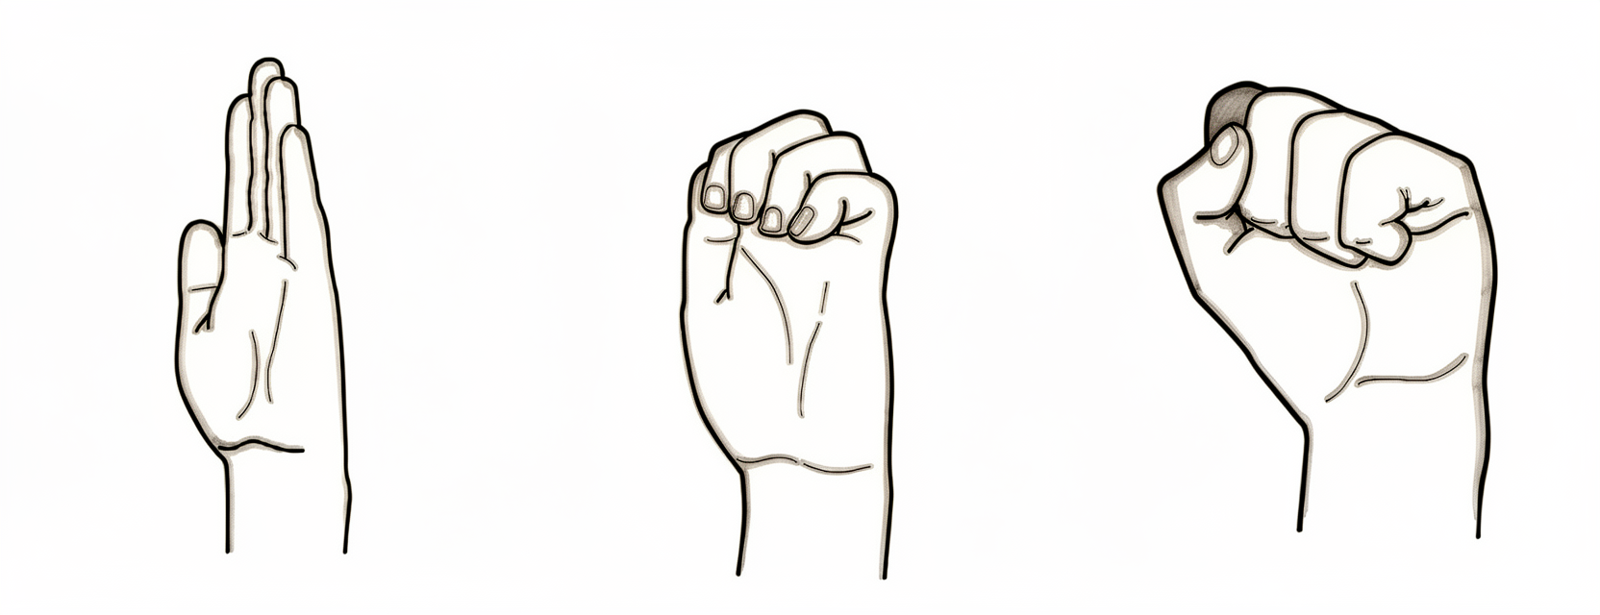
ٹینڈن گلائیڈ ورزشیں (tendon glides)
اپنے ہاتھ کو تین شکلوں سے گزاریں: انگلیاں سیدھی (ہاتھ چپٹا)، پھر صرف آخری دو جوڑوں کو موڑ کر کنڈی (hook) بنائیں، پھر ہلکی سی پوری مٹھی بنائیں، پھر دوبارہ سیدھا کر لیں۔ اس سے ٹینڈن پھسلتے رہتے ہیں تاکہ انگلی کے ٹھیک ہوتے ہوئے وہ نیچے چپک نہ جائیں۔ آپ کو موڑنے کی جو بھی حد دی گئی ہے اس کے اندر رہیں۔
پورا سلسلہ 5 سے 10 بار، دن میں کئی بار
Kieran Hirpara 4.0
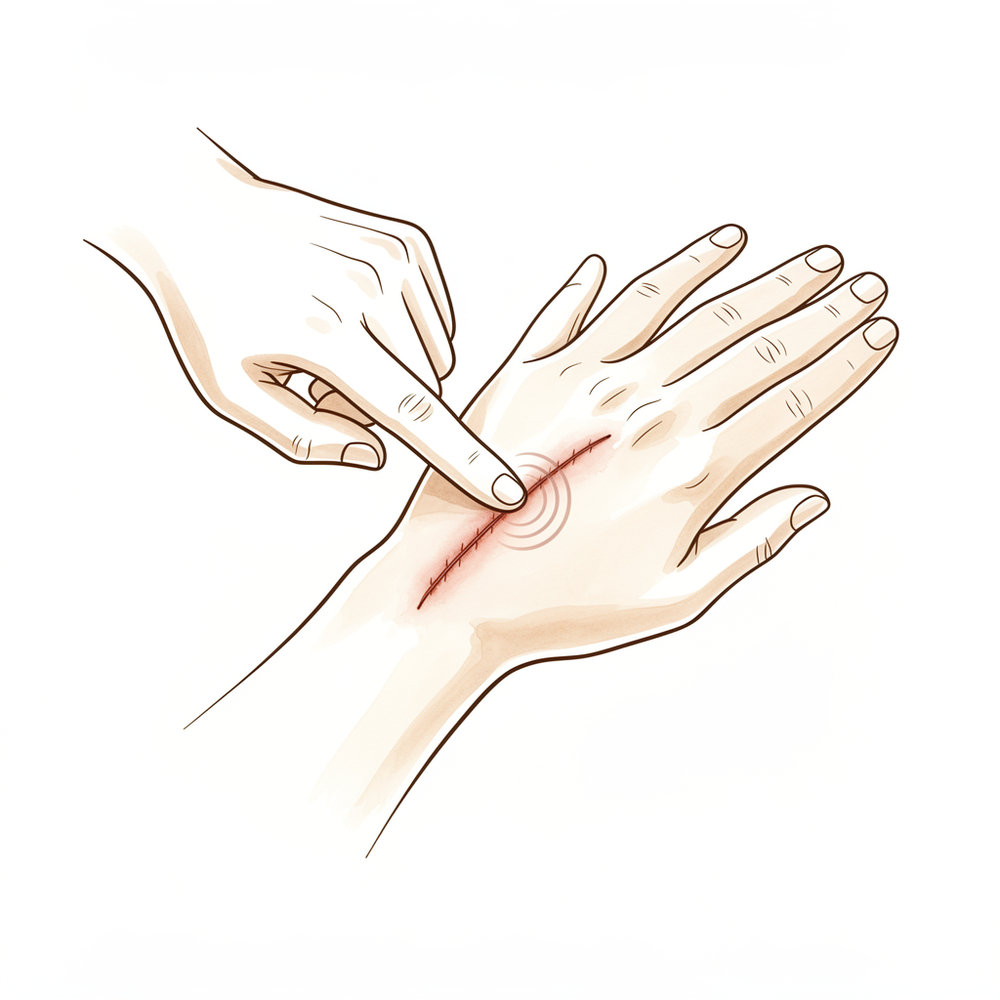
زخم کے نشان کی مالش
جب زخم پوری طرح بھر جائے تو تھوڑی سی سادہ کریم لگا کر چند منٹ تک چھوٹے، مضبوط دائروں میں زخم کے نشان کی مالش کریں۔ اس سے زخم کا نشان نرم رہتا ہے اور نیچے موجود ٹینڈن اور جوڑ سے نہیں چپکتا۔ جب تک آپ کا ہینڈ تھراپسٹ تصدیق نہ کر دے کہ زخم بھر گیا ہے، مالش شروع نہ کریں۔
چند منٹ، دن میں 2 سے 3 بار، زخم بھر جانے کے بعد
Kieran Hirpara 4.0
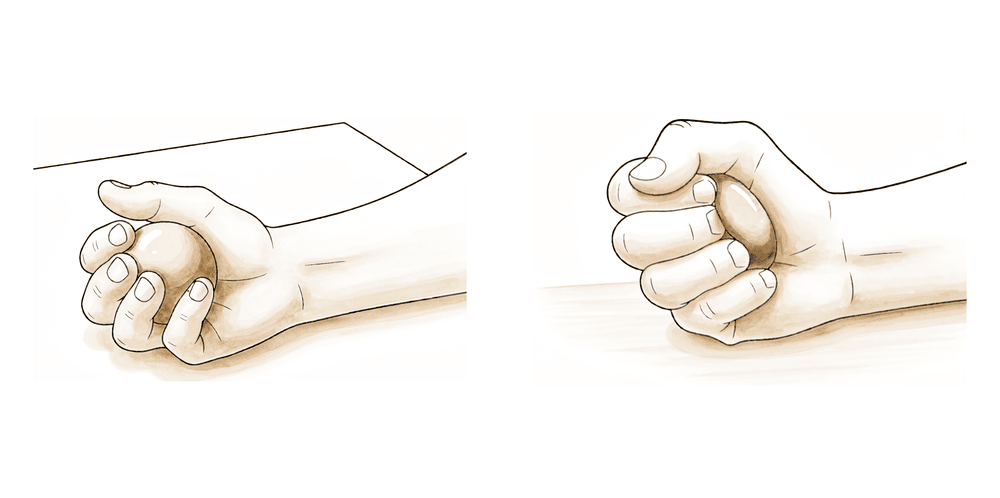
گرفت مضبوط کرنے کی ورزش
یہ بعد کی ورزش ہے — صرف اس وقت جب آپ کا ہینڈ تھراپسٹ طاقت بڑھانے کی اجازت دے (عام طور پر تقریباً چھ ہفتے سے)۔ ایک نرم گیند یا پُٹی (putty) کو نرمی سے دبائیں اور آہستہ آہستہ بڑھائیں۔ جب تک آپ کو بتایا نہ جائے کہ یہ محفوظ ہے، زور سے چٹکی نہ بھریں اور کوئی ایسی مروڑنے والی حرکت نہ کریں جو نئے جوڑ پر پہلو کی طرف زور ڈالے۔
اپنے ہینڈ تھراپسٹ کی رہنمائی کے مطابق (صرف بعد کے مرحلے میں)
یہ آپ کے ہینڈ آؤٹ (ورزشوں کے پرچے) والی ورزشیں ہیں۔ انہیں صرف ڈاکٹر ہِرپرا اور اپنے ہینڈ تھراپسٹ کی رہنمائی کے مطابق شروع کریں، اور آپ کو جو بھی حد اور پابندیاں دی گئی ہیں ان کے اندر رہیں۔ ابتدائی ورزشیں انگلی کو پہلو کے دباؤ کے بغیر سیدھی لکیر میں حرکت میں رکھتی ہیں: محفوظ طریقے سے موڑنا، آہستگی سے سیدھا کرنا، بڈی اسٹریپنگ اور ٹینڈن گلائیڈ ورزشیں (tendon glides)۔ اگر آپ کی سرجری انگلی کی پشت کی طرف سے ہوئی ہے تو اپنی طاقت سے سیدھا کرنے والی ورزش وہ ہے جس کی شروع میں حفاظت کرنی ہے اور جسے آہستہ آہستہ بڑھانا ہے۔ گرفت مضبوط کرنے کی ورزش بعد کے مرحلے کی ہے اور جب تک آپ کو خاص طور پر اجازت نہ دی جائے اسے شروع نہیں کرنا چاہیے۔ جو بھی ورزش تیز درد پیدا کرے یا انگلی کو غیر مستحکم محسوس کروائے، اسے روک دیں۔
آپ کا طبی پروٹوکول
اس صفحے کا باقی حصہ سلیکون پی آئی پی جوڑ کی آرتھروپلاسٹی (silicone PIP joint arthroplasty، یعنی جوڑ کی تبدیلی) کے بعد بحالی کا مرحلہ وار طبی پروٹوکول ہے۔ یہ حصہ آپ کے ہینڈ تھراپسٹ کو دیا جانا ہے، اور ہر مرحلہ سادہ زبان میں اس وضاحت سے شروع ہوتا ہے کہ اس وقت کیا ہو رہا ہے۔ یہ پروٹوکول سرجری کے راستے پر منحصر ہے، اور یہی بنیادی موڑ ہے: سامنے (ہتھیلی) کی طرف سے راستہ (volar approach) انگلی کو سیدھا کرنے والے نظام (extensor mechanism) کو محفوظ چھوڑ دیتا ہے اور چند دنوں کے اندر اپنی طاقت سے ابتدائی حرکت کی اجازت دیتا ہے؛ پشت کی طرف سے راستہ (dorsal approach) سینٹرل سلپ کو کاٹتا یا چیرتا ہے، اس لیے پہلے سیدھا کرنے والے ٹینڈن کے بھرنے کی حفاظت سیدھا رکھنے والے اسپلنٹوں (extension orthoses) اور درجہ بدرجہ موڑنے کے ذریعے کرنی ضروری ہے۔ پورے عرصے میں سلیکون امپلانٹ ایک لچکدار اسپیسر ہے جس کا طویل مدتی استحکام امپلانٹ کے گرد بننے والی جوڑ کی جھلی (capsule) پر منحصر ہے، اس لیے پہلو کی طرف کے دباؤ (coronal / lateral stress) سے بچا جاتا ہے اور حرکت کو خالص آگے پیچھے کی قوس (sagittal arc) میں رکھا جاتا ہے۔
علاج شروع کرنے سے پہلے علاج کرنے والے سرجن سے تصدیق کریں کہ سرجری کا راستہ کون سا تھا (سامنے کی طرف سے یا پشت کی طرف سے: volar vs dorsal)، سینٹرل سلپ اور کولیٹرل لیگامنٹوں (collateral ligaments، یعنی جوڑ کے دونوں پہلوؤں پر وہ مضبوط بندھن جو ایک ہڈی کو دوسری ہڈی سے جوڑتے ہیں) کی حالت یا مرمت کیا ہے، اور آپریشن کے دوران حرکت کی قوس کیا تھی۔ ڈاکٹر ہِرپرا راستہ بتائیں گے؛ اسی کے مطابق سامنے والا (ابتدائی فعال حرکت والا) یا پشت والا (سیدھا رکھ کر حفاظت والا) لائحہ عمل منتخب کریں۔ متوقع عملی ہدف تقریباً 40 سے 60 ڈگری کی بغیر درد کی قوس ہے، پوری حد نہیں۔
مرحلہ I — حفاظت اور حرکت کی شروعات (ہفتے 0 سے 3)
پہلے ہفتوں میں نرم بافتوں (soft tissues) کی حفاظت کی جاتی ہے اور ساتھ ہی اکڑاؤ کو روکا جاتا ہے، اور رفتار مکمل طور پر سرجری کے راستے سے طے ہوتی ہے۔ امپلانٹ موڑنے اور سیدھا کرنے کی حرکت میں مستحکم ہے لیکن پہلو کی طرف کے بوجھ کے سامنے کمزور ہے، اس لیے ساری حرکت ایک صاف آگے پیچھے کی سطح (sagittal plane) میں رکھی جاتی ہے اور انگلی کو بڈی اسٹریپنگ اور اسپلنٹ کا سہارا دیا جاتا ہے۔
آپ کے ہینڈ تھراپسٹ کے لیے:
آگاہی اور احتیاطیں - سرجری کا راستہ معلوم کریں اور اسی کے مطابق لائحہ عمل پر چلیں: - سامنے کی طرف سے راستہ (volar approach): سیدھا کرنے والا نظام محفوظ ہے، اس لیے 3 سے 5 دن پر پی آئی پی اور ڈی آئی پی (PIP/DIP) جوڑوں کی فعال حرکت شروع کریں۔ سامنے کی طرف ایسا ایکسٹینشن بلاک / ٹیمپلیٹ اسپلنٹ (extension-block / template splint) لگائیں جو موڑنے کی چھوٹی قوس (عام طور پر شروع میں تقریباً 30 ڈگری) کی اجازت دے، اور اسے بتدریج بڑھائیں۔ - پشت کی طرف سے راستہ (dorsal approach؛ سینٹرل سلپ چیرا گیا / مرمت کیا گیا): سیدھے ہونے کی حفاظت کریں۔ پی آئی پی جوڑ کو ہر وقت تقریباً پوری طرح سیدھی حالت میں اسپلنٹ میں رکھیں؛ نگرانی میں محدود چھوٹی قوس میں فعال موڑنا شروع کریں، اور سینٹرل سلپ کی مرمت کا خیال رکھیں۔ (سرجن کی ترجیح کے مطابق ریلیٹو موشن / ڈائنامک ایکسٹینشن (relative-motion / dynamic-extension) طریقہ استعمال کیا جا سکتا ہے۔) - آپریشن والے جوڑ پر پہلو کی طرف (coronal: lateral / radial–ulnar) کے دباؤ سے سختی سے بچیں: خالص آگے پیچھے کی حرکت کی رہنمائی کے لیے اسے ساتھ والی انگلی کے ساتھ بڈی اسٹریپ کریں۔ - نہ گرفت، نہ چٹکی کی گرفت، اور نہ مزاحمت کے خلاف یا بوجھ کے ساتھ استعمال۔
علاج - زخم: ہدایت کے مطابق سرجری کی پٹیاں؛ انفیکشن پر نظر رکھیں - سوجن (oedema): ہاتھ اونچا رکھنا، ہلکی ریٹروگریڈ مالش (retrograde massage، یعنی انگلی کے سرے سے ہاتھ کی طرف)، ہلکی دباؤ والی پٹی - ورزشیں: طے شدہ قوس کے اندر پی آئی پی اور ڈی آئی پی جوڑوں کو محفوظ طریقے سے اپنی طاقت سے موڑنا اور سیدھا کرنا؛ ٹینڈن گلائیڈ ورزشیں؛ غیر متاثرہ جوڑوں (ڈی آئی پی، ایم سی پی (MCP)، کلائی، انگوٹھا) کی فعال حرکت؛ سرگرمی کے لیے بڈی اسٹریپنگ شروع کریں - ورزش کے اوقات کے درمیان اسپلنٹ ہر وقت پہنا جائے
اگلے مرحلے میں جانے کی شرائط - زخم تسلی بخش طریقے سے بھر رہا ہو؛ ایکسٹینسر لیگ (extensor lag، یعنی انگلی کا اپنی طاقت سے پوری طرح سیدھا نہ ہو پانا) پیدا نہ ہو رہا ہو (پشت والا لائحہ عمل)؛ موجودہ قوس کے اندر آرام دہ اور قابو میں حرکت
مرحلہ II — حرکت بڑھانا (ہفتے 3 سے 6)
موڑنے کی قوس کھولی جاتی ہے، اور پشت کی طرف سے آپریشن والی انگلیوں میں، جیسے جیسے سینٹرل سلپ مضبوط ہوتا ہے، سیدھا رکھنے والی حفاظت بتدریج کم کی جاتی ہے۔ اس عرصے کا مقصد یہ ہے کہ زخم کے سخت ریشے کے پختہ ہو کر حرکت کی حد کو طے کر دینے سے پہلے کارآمد قوس (تقریباً 40 سے 60 ڈگری) حاصل کر لی جائے۔
آپ کے ہینڈ تھراپسٹ کے لیے:
جائزے - پی آئی پی جوڑ کی فعال اور غیر فعال قوس؛ ایکسٹینسر لیگ (پشت والا لائحہ عمل)؛ پہلو کی طرف کا استحکام (coronal stability)؛ درد اور سوجن؛ زخم / زخم کے نشان کا جائزہ
آگاہی اور احتیاطیں - موڑنے کی اجازت شدہ قوس کو بتدریج بڑھائیں اور اسے عملی ہدف (تقریباً 40 سے 60 ڈگری) کی طرف لے جائیں - سامنے والا راستہ (volar): برداشت کے مطابق فعال موڑنا بڑھائیں؛ اگر سیدھا ہونا مکمل اور مستحکم ہو تو ہلکا غیر فعال موڑنا شامل کریں - پشت والا راستہ (dorsal): سینٹرل سلپ کے بھرنے کے مطابق سیدھا رکھنے والا اسپلنٹ بتدریج چھڑوائیں (عام طور پر ہفتے 4 سے 6 کے دوران دن کے وقت کا سہارا کم کرتے ہوئے)؛ ایکسٹینسر لیگ سے بچاؤ کریں: فعال طریقے سے سیدھا ہونے کی قیمت پر موڑنے کے پیچھے نہ پڑیں - پہلو کی طرف / مروڑنے والے بوجھ سے سختی سے بچنا جاری رکھیں؛ ابھی مزاحمت کے خلاف طاقت کی ورزشیں نہیں
علاج - ورزشیں: پی آئی پی جوڑ کو درجہ بدرجہ فعال اور مدد کے ساتھ فعال طریقے سے موڑنا اور سیدھا کرنا؛ پی آئی پی جوڑ کی حرکت پر توجہ کے لیے بلاکنگ ورزشیں (blocking exercises)؛ ٹینڈن گلائیڈ ورزشیں اور بڈی اسٹریپنگ جاری رکھیں؛ زخم بھر جانے کے بعد زخم کے نشان کی مالش شروع کریں - ساتھ والے جوڑوں کی پوری حرکت برقرار رکھیں
اگلے مرحلے میں جانے کی شرائط - زخم بھر چکا ہو؛ جوڑ پہلو کی سمت (coronal plane) میں مستحکم ہو؛ بغیر درد کی عملی قوس حاصل ہو چکی ہو؛ ایکسٹینسر لیگ کم سے کم ہو (پشت والا لائحہ عمل)
مرحلہ III — طاقت بڑھانا اور واپسی (ہفتے 6 سے 12 اور اس کے بعد)
جب حرکت قائم ہو جائے اور نرم بافتیں مضبوط ہو جائیں (تقریباً چھ ہفتوں پر)، تو ہلکی طاقت بڑھانے کی ورزشیں شروع ہوتی ہیں اور انہیں بتدریج بڑھایا جاتا ہے۔ طاقت کی ورزشیں جوڑ کی سیدھ میں (axial) رکھی جاتی ہیں (گرفت اور سیدھی لکیر میں بوجھ)، جبکہ امپلانٹ پر پہلو کی طرف / مروڑنے والے دباؤ سے طویل مدت تک بچا جاتا ہے۔
آپ کے ہینڈ تھراپسٹ کے لیے:
جائزے - دوسرے ہاتھ کے مقابلے میں گرفت اور چٹکی کی گرفت؛ پی آئی پی جوڑ کی آخری قوس؛ پہلو کی طرف کا استحکام؛ عملی اور کام سے متعلق مخصوص ٹیسٹ
آگاہی اور احتیاطیں - تقریباً چھ ہفتوں سے ہلکی گرفت مضبوط کرنے کی ورزشیں شروع کریں، اور بتدریج بڑھائیں - چٹکی پر بوجھ احتیاط سے شامل کریں اور آپریشن والے جوڑ پر پہلو کی طرف / مروڑنے والے زوردار بوجھ سے ہمیشہ بچنا جاری رکھیں (امپلانٹ کی لمبی عمر کے لیے) - حقیقت پسندانہ توقعات قائم کریں: دیرپا درد سے نجات بنیادی فائدہ ہے؛ آخری قوس محدود (تقریباً 40 سے 60 ڈگری) ہوتی ہے اور زیادہ تر تقریباً 3 ماہ تک طے ہو جاتی ہے
علاج - ورزشیں: گرفت / ورزش والی پُٹی (putty) کی بتدریج بڑھتی ورزشیں؛ درجہ بدرجہ عملی اور کام سے متعلق بوجھ؛ باقی رہ جانے والی حرکت اور زخم کے نشان پر کام جاری رکھیں - جب بغیر درد کی کارآمد قوس کے ساتھ مستحکم، آرام دہ اور کام کے قابل انگلی حاصل ہو جائے تو علاج ختم کرنے پر غور کریں - اگر صحت یابی رک جائے، جوڑ غیر مستحکم ہو جائے یا ٹیڑھا ہونے لگے، یا امپلانٹ کے ناکام ہونے کا شبہ ہو تو مریض کو دوبارہ علاج کرنے والے ڈاکٹر کے پاس بھیجیں
علاج ختم کرنے / واپسی کی شرائط - آرام دہ، بغیر درد کا، پہلو کی سمت میں مستحکم جوڑ جس کی عملی قوس ہو؛ مناسب گرفت؛ روزمرہ اور کام کی ضروریات پوری کرنے کے قابل
کام اور سرگرمیوں میں واپسی
ہاتھ کے ہلکے روزمرہ استعمال (کھانا، لکھنا، ہلکی ذاتی دیکھ بھال) کی شروع ہی سے، آرام کی حد میں، حوصلہ افزائی کی جاتی ہے، بشرطیکہ یہ سیدھی لکیر میں رہے اور آپریشن والی انگلی پر پہلو کی طرف یا مروڑنے والے زور سے بچا جائے۔ گاڑی چلانا عام طور پر اس وقت ممکن ہوتا ہے جب آپ اسٹیئرنگ کو آرام سے پکڑ سکیں اور گاڑی کو محفوظ طریقے سے قابو میں رکھ سکیں، آپ کسی پابندی والے اسپلنٹ سے باہر ہوں، اور آپ اب تیز اثر والی درد کش دوا نہ لے رہے ہوں؛ عام طور پر اس میں تقریباً دو ہفتے لگتے ہیں، اور اس کی تصدیق آپ کے معائنے پر کی جاتی ہے۔
زیادہ مضبوط گرفت اور بوجھ والے کام تقریباً چھ ہفتوں تک انتظار کرتے ہیں، اور پھر انہیں بتدریج بڑھایا جاتا ہے۔ بھاری جسمانی مشقت والا یا مروڑنے والا کام سب سے آخر میں دوبارہ شروع ہوتا ہے، اور اس کا فیصلہ صرف کیلنڈر سے نہیں بلکہ اس بنیاد پر ہوتا ہے کہ آپ کی انگلی آرام دہ اور مستحکم ہو اور گرفت مناسب ہو، جس کا اندازہ ڈاکٹر ہِرپرا اور آپ کا ہینڈ تھراپسٹ لگاتے ہیں۔ اس آپریشن کا دیرپا سودا یاد رکھیں: قابلِ اعتماد درد سے نجات اور تقریباً 40 سے 60 ڈگری کی کارآمد قوس، اور امپلانٹ کی حفاظت کے لیے جوڑ پر پہلو کی طرف کے دباؤ سے طویل مدت تک بچنا۔
اپنے پروٹوکول کے بعد
یہ پروٹوکول پریکٹس کے صحت یابی سے متعلق عمومی مشوروں کے ساتھ کام کرتا ہے؛ دیکھیں آپریشن کے بعد درد پر قابو پانا، زخم کی دیکھ بھال اور زخم کے نشان کی دیکھ بھال۔ اوپر دیا گیا مرحلہ وار منصوبہ سلیکون پی آئی پی جوڑ کی آرتھروپلاسٹی کے بعد بحالی کی شائع شدہ رہنمائی کی عکاسی کرتا ہے، اور آگے آپ کی صحت یابی میں ڈاکٹر ہِرپرا اور آپ کا ہینڈ تھراپسٹ انفرادی طور پر آپ کی رہنمائی کریں گے، اس بات کے مطابق کہ سرجری کا کون سا راستہ استعمال ہوا اور آپ کی انگلی کیسے بہتر ہو رہی ہے۔
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Silicone PIP Joint Replacement — Procedure Outcomes & Post-operative Rehabilitation (Swanson-type Arthroplasty for PIP Osteoarthritis)
Topic scope: post-operative rehabilitation after silicone (Swanson-type) proximal interphalangeal (PIP) joint arthroplasty for primary osteoarthritis. The worn joint surfaces are excised and a flexible silicone spacer is implanted; this is an interposition / encapsulation arthroplasty, not a rigidly-fixed mechanical hinge. The implant works as a flexible spacer around which a peri-implant fibrous capsule forms to provide stability. The dominant, reliable benefit is pain relief; the functional gain is a modest active arc (~40–60°), not restoration of normal range.
Defining principle of the rehab here: the rehabilitation pathway is dictated by the surgical approach, because the rate-limiting tissue is the extensor mechanism, not the implant. A volar (palmar) approach leaves the central slip and extensor mechanism intact → it permits immediate / early active motion (within 3–5 days). A dorsal approach must split or reflect the central slip to reach the joint → the extensor repair must be protected first with extension orthotics and a graded, short-arc flexion programme. Across both pathways the silicone spacer is stable in the sagittal (flexion–extension) plane but vulnerable in the coronal plane, so the programme deliberately avoids lateral / torsional load and tracks the joint in a pure sagittal arc (buddy strapping). Therapy aims to bank the useful arc before scar maturation fixes it while protecting extension and the implant — it is not an immobilise-to-heal construct in the volar case.
A. PROCEDURE OUTCOMES (silicone PIP arthroplasty for osteoarthritis)
Silicone PIP arthroplasty is a reliable pain-relieving operation with predictable but modest motion; the principal debates are over surgical approach and implant choice (silicone vs surface-replacement/pyrocarbon), not whether arthroplasty relieves pain.
- Pain relief is high and durable; motion gains are modest. A long-term series of Swanson silicone PIP arthroplasty for osteoarthritis (mean ~10-year follow-up) reported excellent pain relief (mean VAS ~0.4) with essentially unchanged arc (≈55° pre-op → ≈50° post-op) and high patient satisfaction — patients would have the surgery again despite limited motion gain [Bales, Wall & Stern, J Hand Surg Am 2014]. Moderate (level-IV long-term cohort).
- The volar approach can improve the active arc. A volar-approach silicone PIP series reported the active arc improving from ~33° to ~72°, with good function and satisfaction, by preserving the extensor mechanism and enabling early motion [Proubasta et al., J Hand Surg Am 2014]. Moderate–weak (level-IV).
- Radiographic implant deformation/fracture is common but poorly correlated with symptoms. In the long-term Swanson series most implants deformed and many fractured radiographically, yet clinical revision was uncommon (survivorship ~90% at ~10 years) and there was no correlation between radiographs and satisfaction [Bales, Wall & Stern 2014]. Strong natural-history signal within a cohort.
- Silicone vs surface-replacement and pyrocarbon implants give broadly comparable clinical results; no implant is clearly superior. Systematic review across implants/approaches found comparable outcomes with implant-/approach-specific complication profiles [Yamamoto et al., Plast Reconstr Surg 2017; Carlson Strother, Moran & Rizzo, JAAOS 2023]. Moderate (SR + narrative review).
- Pyrocarbon and resurfacing implants carry their own failure modes (subsidence, squeaking, intra-operative periprosthetic fracture, instability), informing implant choice rather than rehab [Watts et al., J Hand Surg Am 2012; Wagner et al. medium-term 2018 & intra-op fractures 2015; Branam et al. resurfacing-vs-silicone 2007]. Moderate.
B. REHABILITATION / THERAPY EVIDENCE
The central rehab questions are (1) how soon to move and (2) how to splint, and the answer to both is set by the surgical approach and the extensor mechanism. The evidence base is low-level (expert consensus / single-cohort therapy series) — there are no RCTs comparing PIP arthroplasty rehab pathways.
- Approach dictates the timeline (the core principle). Surgical reviews establish that a volar approach preserves the central slip and permits immediate active and passive motion, while a dorsal approach requires post-operative protection of the split/repaired central slip before flexion is advanced [Renfree, Bone Joint J 2022 (surgical approaches); Herren, Hand Clin 2017; Yamamoto et al. 2017]. Moderate (surgical evidence) — strong mechanistic basis.
- A structured 12-week, splint-based therapy programme is the consensus framework (dorsal pathway). Feldscher's hand-therapy protocol for PIP (pyrocarbon, central-slip-splitting dorsal approach) uses a volar static finger orthosis allowing a limited short-arc PIP/DIP active arc that is increased over the rehab course, with a hand-based resting splint (MCP flexed, PIP/DIP near 0°) for full-time use except during template-splint exercise [Feldscher, J Hand Ther 2010]. Weak (expert-consensus protocol).
- A defined controlled-motion program exists and reports good arcs. A controlled-motion rehabilitation program for PIP arthroplasty reported favourable range-of-motion outcomes, supporting graded controlled motion over rigid immobilisation [Ramanathan, Koludrovich & Evans, J Hand Ther 2021]. Weak (cohort / programme description).
- Static and dynamic extension splinting give similar results. A comparison of static vs dynamic splinting after PIP pyrocarbon arthroplasty found comparable outcomes, favouring static splinting for simplicity and patient convenience [Jennings & Livingstone / static-vs-dynamic cohort, J Hand Ther 2011]. Weak–moderate (comparative cohort).
- Coronal-plane protection is the durable, lifelong caveat. Collateral integrity and avoidance of lateral stress underpin long-term implant stability; collateral compromise drives instability/deviation [Carlo et al., collateral reconstruction, J Hand Surg Am 2016; Carlson Strother et al. 2023]. Consensus / mechanistic.
Recovery trajectory (expected, evidence-anchored)
| Phase | Window | Restraint (by approach) | Hand-therapy focus | Strength / load | Notes |
|---|---|---|---|---|---|
| I — Protect & initiate motion | Week 0–3 | Volar: active motion at 3–5 days, short flexion arc (~30°) in template/extension-block splint. Dorsal: PIP splinted near extension full-time; supervised short-arc flexion only | Protected sagittal PIP/DIP motion; tendon glides; buddy strapping; uninvolved-joint motion; no lateral/torsional load | None (no grip/pinch) | Implant stable in flexion–extension, vulnerable coronally |
| II — Advance motion | Week 3–6 | Progressively increase flexion arc toward ~40–60°. Dorsal: wean extension splint as central slip consolidates (≈wk 4–6); guard against extensor lag | Graded active/AAROM flexion–extension; blocking; scar massage once healed; continue buddy strapping | Still no resisted strengthening | Bank the useful arc before scar maturation fixes it |
| III — Strengthen & return | Week 6–12+ | Lifting/grip restrictions progressively lifted; lateral/twisting load avoided indefinitely | Light grip → cautious pinch; functional & work-specific loading | Grip from ~6 wk, graded | Pain relief is the durable gain; final arc (~40–60°) largely set by ~3 months |
(Phase windows mirror the precautions in the patient protocol; they are typical guides — not trial-derived deadlines — and the volar vs dorsal split is the dominant variable.)
C. KEY CONTROVERSIES / EVIDENCE QUALITY
- Volar vs dorsal approach (the rehab-defining question). The volar approach spares the extensor mechanism and permits early active motion (and a better reported arc), at the cost of being more technically demanding; the dorsal approach is more familiar but mandates extensor protection and a slower, splint-led flexion programme. Choice is surgeon-dependent and drives the entire rehab pathway. Moderate surgical evidence; no head-to-head rehab RCT.
- Implant choice (silicone vs surface-replacement vs pyrocarbon). No implant is clearly superior on clinical outcomes; silicone is durable for pain relief with high radiographic deformation/fracture that poorly predicts symptoms, while pyrocarbon/resurfacing trade different complication profiles (subsidence, instability, intra-operative fracture). Moderate (SR + cohorts).
- Static vs dynamic splinting (dorsal pathway). Comparable outcomes; static splinting is favoured for simplicity and convenience. Weak–moderate.
- Motion gain is modest and that is expected, not failure. Patients reliably lose pain but gain little arc (especially via dorsal/silicone); mislabelling the modest arc as a poor result misframes a successful pain-relieving operation. Counsel the ~40–60° expectation up front. Strong natural-history signal.
- Lifelong coronal-stress avoidance. Long-term stability depends on the peri-implant capsule and collaterals; forceful lateral/twisting load risks deviation, instability and implant failure. Consensus.
D. EVIDENCE STRENGTH FLAGS (summary)
- STRONG (mechanistic / natural-history): the surgical-approach principle (volar preserves extensor mechanism → early motion; dorsal splits central slip → protect extension first); the modest-arc / reliable-pain-relief outcome pattern; radiographic implant deformation poorly predicting symptoms.
- MODERATE: procedure outcomes are level-IV case series (long-term Swanson silicone series; volar approach series); implant-comparison systematic review/narrative review; surgical-approach reviews.
- WEAK / EXPERT CONSENSUS: the specific rehabilitation regimen — short-arc controlled motion, 12-week splint-based programme, static-vs-dynamic splinting equivalence, exact phase timings. These are low-level, expert-consensus / single-cohort therapy descriptions, not trial-derived; individualise to the operative approach and tissue quality.
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Bales JG, Wall LB, Stern PJ. Long-term results of Swanson silicone arthroplasty for proximal interphalangeal joint osteoarthritis. J Hand Surg Am. 2014. DOI: 10.1016/j.jhsa.2013.11.008
- Proubasta IR, Lamas CG, Natera L, et al. Silicone proximal interphalangeal joint arthroplasty for primary osteoarthritis using a volar approach. J Hand Surg Am. 2014;39(6). DOI: 10.1016/j.jhsa.2014.03.033
- Weistra K, Kan HJ, van Alebeek VAHJ, et al. Proximal interphalangeal joint arthroplasty using a silicone implant: a comparison between Integra and NeuFlex in 72 cases. HAND. 2022. DOI: 10.1177/15589447221122829
- Branam BR, Tuttle HG, Stern PJ, et al. Resurfacing arthroplasty versus silicone arthroplasty for proximal interphalangeal joint osteoarthritis. J Hand Surg Am. 2007. DOI: 10.1016/j.jhsa.2007.04.006
- Yamamoto M, Malay S, Fujihara Y, et al. A systematic review of different implants and approaches for proximal interphalangeal joint arthroplasty. Plast Reconstr Surg. 2017. DOI: 10.1097/prs.0000000000003260
- Renfree KJ. Surgical approaches for proximal interphalangeal joint arthroplasty. Bone Joint J. 2022;104-B(12). DOI: 10.1302/0301-620x.104b12.bjj-2022-0946
- Herren DB. Current European practice in the treatment of proximal interphalangeal joint arthritis. Hand Clin. 2017. DOI: 10.1016/j.hcl.2017.04.002
- Carlson Strother CR, Moran SL, Rizzo M. Small joint arthroplasty of the hand: an update on indications, outcomes, and complications. J Am Acad Orthop Surg. 2023;31(15). DOI: 10.5435/jaaos-d-23-00034
- Feldscher SB. Postoperative management for PIP joint pyrocarbon arthroplasty. J Hand Ther. 2010. DOI: 10.1016/j.jht.2009.10.011
- Ramanathan D, Koludrovich J, Evans P. A new controlled motion program for rehabilitation of the proximal interphalangeal joint arthroplasty. J Hand Ther. 2021. DOI: 10.1016/j.jht.2019.04.003
- Watts AC, Hearnden AJ, Trail IA, et al. Pyrocarbon proximal interphalangeal joint arthroplasty: minimum two-year follow-up. J Hand Surg Am. 2012. DOI: 10.1016/j.jhsa.2012.02.012
- Wagner ER, Weston JT, Houdek MT, et al. Medium-term outcomes with pyrocarbon proximal interphalangeal arthroplasty: a study of 170 consecutive arthroplasties. J Hand Surg Am. 2018. DOI: 10.1016/j.jhsa.2018.06.020
- Wagner ER, Van Demark R, Kor DJ, et al. Intraoperative periprosthetic fractures in proximal interphalangeal joint arthroplasty. J Hand Surg Am. 2015. DOI: 10.1016/j.jhsa.2015.06.101
- McGuire DT, White CD, Carter SL, et al. Pyrocarbon proximal interphalangeal joint arthroplasty: outcomes of a cohort study. J Hand Surg Eur Vol. 2011;37(6). DOI: 10.1177/1753193411434053
- Carlo J, Dell PC, Matthias R, et al. Collateral ligament reconstruction of the proximal interphalangeal joint. J Hand Surg Am. 2016;41(1). DOI: 10.1016/j.jhsa.2015.10.007
- Aversano FJ, Calfee RP. Salvaging a failed proximal interphalangeal joint implant. Hand Clin. 2018. DOI: 10.1016/j.hcl.2017.12.011
PIP arthroplasty rehabilitation literature (URLs)
- Feldscher SB. Postoperative management for PIP joint pyrocarbon arthroplasty. J Hand Ther. 2010. https://pubmed.ncbi.nlm.nih.gov/20036511/
- Ramanathan D, Koludrovich J, Evans P. A new controlled motion program for rehabilitation of the proximal interphalangeal joint arthroplasty. J Hand Ther. 2021. https://pubmed.ncbi.nlm.nih.gov/31481342/
- Static versus dynamic splinting for proximal interphalangeal joint pyrocarbon implant arthroplasty: a comparison of current and historical cohorts. J Hand Ther. 2011. https://pmc.ncbi.nlm.nih.gov/articles/PMC3143198/
- Proubasta IR, et al. Silicone proximal interphalangeal joint arthroplasty for primary osteoarthritis using a volar approach. J Hand Surg Am. 2014. https://pubmed.ncbi.nlm.nih.gov/24799141/
- Bales JG, Wall LB, Stern PJ. Long-term results of Swanson silicone arthroplasty for PIP joint osteoarthritis. J Hand Surg Am. 2014. https://pubmed.ncbi.nlm.nih.gov/24559624/
- The dorsal approach to silicone implant arthroplasty of the proximal interphalangeal joint. J Hand Surg Am. 2007. https://www.sciencedirect.com/science/article/abs/pii/S0363502307004662
- Proximal interphalangeal joint arthroplasty using a silicone implant: a comparison between Integra and NeuFlex. HAND. 2022. https://pmc.ncbi.nlm.nih.gov/articles/PMC10953532/