Patients › Shoulder
بازو کی اوپری ہڈی کے سرے کے فریکچر کا آپریشن: پلیٹ یا راڈ سے ہڈی جوڑنا (ORIF)
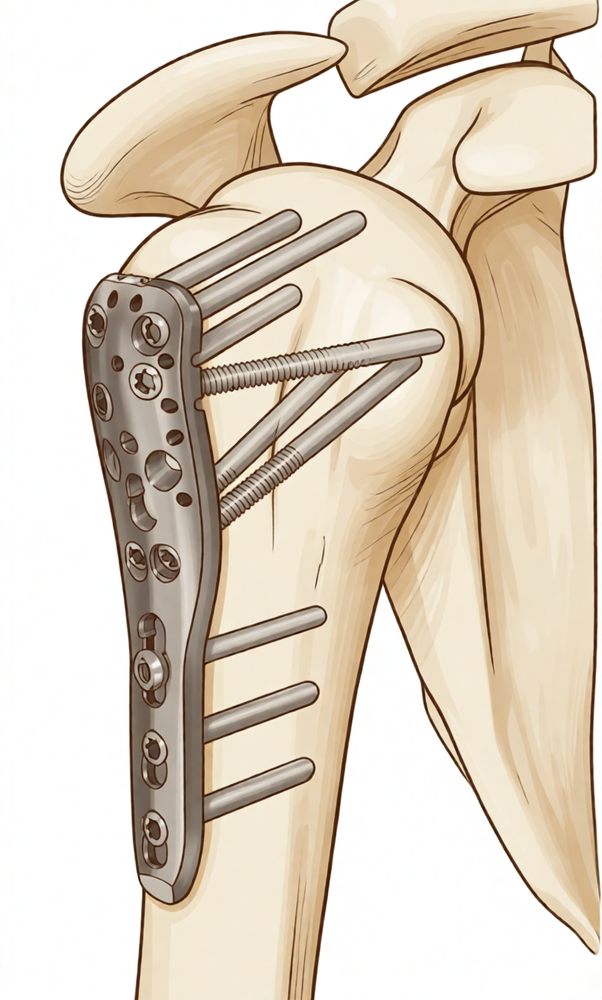
یہ آپریشن کیوں تجویز کیا گیا ہے
ڈاکٹر کیرن ہِرپرا، جو Mater Private Hospital Rockhampton میں بازو اور ہاتھ کے سرجن (upper-limb surgeon) ہیں، علاج کو آپ کی مخصوص چوٹ کے مطابق طے کرتے ہیں۔ مریض عام طور پر اپنے فیملی ڈاکٹر (GP) کے ریفرل پر ہمارے کلینک آتے ہیں؛ اگر کسی فزیوتھراپسٹ نے آپ کو ہمیں دکھانے کا مشورہ دیا ہے، تب بھی میڈیکیئر (Medicare) سے رقم کی واپسی (rebate) کا حق دار ہونے کے لیے آپ کو اپنے فیملی ڈاکٹر سے ریفرل (referral) لینا ہوگا۔ پہلی ملاقات پر ہم آپ سے آپ کی تکلیف کی تفصیل پوچھتے ہیں، آپ کے کندھے کا معائنہ کرتے ہیں، اور یہ جاننے کے لیے کہ مسئلہ کیا ہے، ضرورت ہو تو اسکین کرواتے ہیں۔
اس آپریشن کو اوپن ریڈکشن اینڈ انٹرنل فکسیشن (open reduction and internal fixation, ORIF) کہا جاتا ہے۔ اس کا مطلب ہے کہ آپ کے بازو کے اوپری حصے کی ٹوٹی ہوئی ہڈی کو واپس اپنی جگہ پر لا کر وہیں جما دیا جاتا ہے، عام طور پر دھات کی ایک پلیٹ اور پیچوں سے، یا بعض اوقات ہڈی کے اندر ڈالی گئی ایک راڈ سے۔ ہم عام طور پر اس کا مشورہ اس وقت دیتے ہیں جب ہڈی بری طرح اپنی جگہ سے ہٹ گئی ہو، یا ہڈی کئی ٹکڑوں میں ٹوٹ گئی ہو، کیونکہ ایسے فریکچر (ہڈی کا ٹوٹنا) شاذ و نادر ہی خود سے اپنی جگہ پر رہتے ہیں۔ کندھے کے بہت سے فریکچر سرجری کے بغیر جڑ جاتے ہیں، اس لیے ہم ہمیشہ آپ کے ساتھ مل کر دونوں راستوں پر غور کرتے ہیں۔ کچھ لوگوں کے لیے، خاص طور پر وہ جو باقی لحاظ سے تندرست اور صحت مند ہوں، سرجری سے کندھے کے حرکت کرتے رہنے اور اچھی طرح کام کرنے کا امکان بہتر ہوتا ہے۔ مقصد سادہ ہے: ایسا کندھا جو مستحکم ہو، جس میں درد کم ہو، اور جو آپ کی ضرورت کے کام کر سکے۔
آپریشن سے پہلے
سرجری طے ہو جانے کے بعد ہم فریکچر کا پورا نقشہ سمجھنے کے لیے ضروری اسکین کروائیں گے۔ اس کا مطلب عام طور پر ایک سے زیادہ زاویوں سے لیے گئے ایکسرے ہوتے ہیں، اور بعض اوقات سی ٹی اسکین، جو ہڈی کی تفصیلی تصویر بناتا ہے۔ اگر ہمیں جوڑ کے اردگرد کی نرم بافتوں، جیسے ٹینڈن (tendon)، یعنی وہ مضبوط ڈوری جو پٹھے کو ہڈی سے جوڑتی ہے، کو قریب سے دیکھنے کی ضرورت ہو تو ایم آر آئی یا الٹراساؤنڈ کیا جا سکتا ہے۔ زیادہ تر لوگوں کو کسی اور ٹیسٹ کی ضرورت نہیں ہوتی۔ اگر آپ کو دوسری طبی بیماریاں ہیں تو ہو سکتا ہے آپ کو خون کے ٹیسٹ یا بے ہوشی کے ڈاکٹر (anaesthetist) سے معائنے کی ضرورت ہو، یعنی وہ ڈاکٹر جو آپریشن کے دوران آپ کی دیکھ بھال کرتے ہیں۔ سرجری سے پہلے کے دنوں میں ہم آپ کو بتائیں گے کہ کون سی ادویات عارضی طور پر روکنی ہیں اور کون سی جاری رکھنی ہیں۔ آپ کو آپریشن سے سات گھنٹے پہلے کھانا پینا بند کرنا ہوگا۔ ہم اس سے کم وقت کے بجائے سات گھنٹے اس لیے کہتے ہیں تاکہ اگر آپریشن کی فہرست وقت سے پہلے آگے بڑھ جائے تو ہم آپ کا آپریشن پہلے کر سکیں۔ آپریشن کے بعد آپ کو گاڑی میں گھر لے جانے کے لیے کسی کا انتظام کریں، کیونکہ آپ خود گاڑی نہیں چلا سکیں گے۔ اپنی موجودہ ادویات کی فہرست ساتھ لائیں، اور ڈھیلے، آرام دہ کپڑے پہنیں جنہیں آسانی سے اتارا جا سکے۔
آپریشن کے دن
آپ ہسپتال کے سرجیکل داخلے کے شعبے میں پہنچیں گے، جہاں آپ کا اندراج ہوگا اور آپ کو آپریشن تھیٹر کے لیے تیار کیا جائے گا۔ وہیں آپ کی ملاقات بے ہوشی کے ڈاکٹر سے ہوگی۔ یہ آپریشن جنرل اینستھیزیا (مکمل بے ہوشی) کے ساتھ اعصابی بلاک (nerve block)، یعنی ایک انجکشن جو جسم کے ایک حصے کو سُن کر دیتا ہے، ملا کر کیا جاتا ہے۔ بے ہوشی کے ڈاکٹر آپریشن سے پہلے آپ سے ملیں گے اور دونوں حصوں کے بارے میں آپ کو سمجھائیں گے۔
پھر آپ کو آپریشن تھیٹر میں لے جایا جاتا ہے، جہاں آپریشن کیا جاتا ہے۔ اس کے بعد آپ ریکوری روم میں جاگیں گے، جہاں بے ہوشی کا اثر ختم ہونے تک نرسیں آپ کی نگرانی کرتی ہیں۔ جب آپ کی حالت مستحکم ہو جائے تو آپ وارڈ میں چلے جاتے ہیں۔
آپریشن میں کیا کیا جاتا ہے
اس آپریشن کو اوپن ریڈکشن اینڈ انٹرنل فکسیشن کہا جاتا ہے۔ اوپن (open) کا مطلب ہے کہ آپ کے سرجن ٹوٹی ہوئی ہڈی تک پہنچنے کے لیے آپریشن والی جگہ پر ایک چیرا لگاتے ہیں۔ ریڈکشن (reduction) کا مطلب ہے ٹوٹے ہوئے ٹکڑوں کو واپس ان کی معمول کی جگہ پر لانا۔ انٹرنل فکسیشن (internal fixation) کا مطلب ہے انہیں دھات کے ذریعے وہیں جما کر رکھنا۔
زیادہ تر آپ کے سرجن ہڈی پر پیچوں سے کسی ہوئی پلیٹ استعمال کرتے ہیں؛ بعض اوقات اس کے بجائے بازو کی ہڈی کے کھوکھلے درمیانی حصے کے اندر نیچے تک ڈالی گئی ایک راڈ استعمال کی جاتی ہے۔ دونوں فریکچر کو جڑنے تک مستحکم رکھتے ہیں۔ انتخاب آپ کے فریکچر کی شکل اور آپ کی ہڈی کی حالت پر منحصر ہوتا ہے۔ اگر فریکچر بازو کی ہڈی میں زیادہ نیچے تک گیا ہو تو بعض اوقات لمبی پلیٹ استعمال کی جاتی ہے۔ اگر ہڈی پتلی ہو تو آپ کے سرجن مرمت کو مضبوط رکھنے کے لیے اضافی سہارے لگا سکتے ہیں۔
جب ہڈی سیدھ میں آ کر مضبوطی سے جم جائے تو زخم کو ٹانکوں سے بند کر دیا جاتا ہے۔ اوپر زخم کی پٹی لگائی جاتی ہے، اور آپ یہ پٹی تقریباً 10 دن تک لگی رہنے دیتے ہیں۔
آپریشن کے بعد
اس آپریشن کے بعد زیادہ تر مریض ایک یا دو راتیں ہسپتال میں رہتے ہیں۔ آپ ریکوری روم میں جاگیں گے، پھر وارڈ میں منتقل ہو جائیں گے۔ نرسیں باقاعدگی سے آپ کو دیکھیں گی اور آپ کو آرام میں رکھنے کے لیے دوا دیں گی۔ آپ کا بازو ایک سادہ سلنگ (sling)، یعنی گلے سے لٹکی وہ پٹی جو بازو کو سہارا دیتی ہے، میں رہے گا، جو ورزشوں اور نہانے دھونے کے لیے اتار دی جاتی ہے۔ گھر جانے سے پہلے ایک نرس آپ کو دکھائے گی کہ محفوظ طریقے سے کیسے چلنا پھرنا ہے۔ گھر پہنچنے کے بعد پہلے 24 گھنٹے کسی کو آپ کے ساتھ رہنا چاہیے۔ ہم پٹی تقریباً 10 دن تک لگی رہنے دیتے ہیں؛ براہ کرم اس سے پہلے اسے نہ اتاریں، جب تک ہم آپ کو ایسا کرنے کو نہ کہیں۔ جب ہم آپ کو دیکھیں گے تو پٹی بدل دیں گے یا اتار دیں گے۔
صحت یابی
پہلے چند دنوں اور ہفتوں میں کچھ درد اور سوجن کی توقع رکھیں۔ یہ زخم بھرنے کا معمول کا حصہ ہے اور عام طور پر ہڈی جڑنے کے ساتھ کم ہو جاتا ہے۔ آرام، برف کی پٹیاں (ice packs)، اور آپ کے لیے تجویز کی گئی درد کش دوا تکلیف کم کرنے میں مدد دیں گی۔ جیسا کہ آپ کے فزیوتھراپسٹ آپ کو دکھائیں گے، شروع سے ہی اپنے ہاتھ، کلائی اور کہنی کو حرکت دیتے رہیں۔
آرام کے لیے آپ کا بازو ایک سادہ سلنگ میں رہتا ہے۔ یہ آپ کی ورزشوں اور نہانے دھونے کے لیے اتار دی جاتی ہے۔ آپ کے فزیوتھراپسٹ شروع میں ہلکی حرکات میں آپ کی رہنمائی کریں گے، پھر جیسے جیسے فریکچر جڑتا ہے، زیادہ طاقت والی ورزشوں کی طرف بڑھیں گے۔ گھر میں آپ چل پھر سکتے ہیں، سادہ کھانا بنا سکتے ہیں، اور اپنے دوسرے ہاتھ سے ہلکے کام کر سکتے ہیں۔ درد والے بازو سے کوئی بھاری چیز اٹھانے سے پرہیز کریں، اور جب تک آپ کو یہ نہ بتایا جائے کہ یہ محفوظ ہے، اس بازو پر وزن نہ ڈالیں۔
شروع میں سونا تکلیف دہ ہو سکتا ہے۔ بہت سے لوگوں کو کرسی پر ٹیک لگا کر یا اضافی تکیوں کے سہارے آرام کرنا آسان لگتا ہے۔
پیش رفت کے مراحل تاریخوں سے نہیں بلکہ واقعات سے آتے ہیں۔ سوجن کم ہو جانے کے بعد حرکت عام طور پر آسان محسوس ہوتی ہے۔ جب آپ کے سرجن ہڈی کے جڑنے سے مطمئن ہوں گے تو سلنگ ہمیشہ کے لیے اتر جائے گی۔ آپ کے سرجن کی اجازت کے بعد آپ دوبارہ گاڑی چلا سکتے ہیں، جو عام طور پر چھ ہفتے والے معائنے پر ملتی ہے؛ ہماری رہنمائی بازو اور ہاتھ کی سرجری کے بعد گاڑی چلانا دیکھیں۔ جیسے جیسے طاقت واپس آتی ہے، آپ سر سے اوپر ہاتھ بڑھانا اور بازو سے زیادہ کام لینا شروع کر دیں گے۔
صحت یابی ہر شخص میں مختلف ہوتی ہے۔ آپ کی صحت یابی کا دورانیہ مختلف ہو سکتا ہے، اور آپ کے سرجن اور فزیوتھراپسٹ ہر مرحلے پر آپ کی رہنمائی کریں گے۔
کیا مسائل پیدا ہو سکتے ہیں
زیادہ تر مریض ٹھیک رہتے ہیں، لیکن کبھی کبھار مسائل پیدا ہو سکتے ہیں۔ آپ کے سرجن اور ٹیم آپ کی قریب سے نگرانی کرتے ہیں تاکہ کسی بھی مسئلے کو جلد پہچانا جا سکے۔
بعض اوقات ہڈی ویسے نہیں جڑتی جیسے اسے جڑنا چاہیے۔ آپ کو فریکچر کی جگہ پر مسلسل درد، یا یہ احساس ہو سکتا ہے کہ وقت کے ساتھ بازو میں طاقت نہیں آ رہی۔ اگر درد کم نہ ہو رہا ہو تو اپنے اگلے معائنے پر ہمیں بتائیں۔
بعض اوقات چوٹ کی وجہ سے کندھے کے جوڑ کی گیند تک خون کی فراہمی متاثر ہو سکتی ہے۔ ایسا ہو تو مہینوں بعد جوڑ میں درد اور اکڑاؤ ہو سکتا ہے، اور حرکت توقع کے مطابق بہتر نہیں ہوتی۔ اپنے معائنے پر اس کا ذکر کریں تاکہ ہم اسکین کروا سکیں۔
ہڈی کو تھامنے والی دھات اپنی جگہ سے سرک یا ڈھیلی ہو سکتی ہے۔ آپ کو نئی کلک، رگڑ کا احساس، یا اچھی خاصی بہتری کے بعد درد کی واپسی محسوس ہو سکتی ہے۔ کچھ لوگوں کو جلد کے قریب کوئی پیچ یا پلیٹ محسوس ہوتی ہے۔ اگر ان میں سے کچھ بھی ہو تو کلینک سے رابطہ کریں۔ بعض اوقات دھات کو نکالنے یا درست کرنے کے لیے ایک چھوٹا آپریشن کرنا پڑتا ہے۔
کندھے کے اردگرد کے ٹینڈنوں میں جلن (irritation) پیدا ہو سکتی ہے۔ آپ کو بازو اٹھاتے وقت درد، یا بعض زاویوں پر اٹکاؤ محسوس ہو سکتا ہے۔ اپنے معائنے پر اس کا ذکر کریں۔
کندھا اکڑ کر جکڑا ہوا ہو سکتا ہے۔ پیچھے کی طرف ہاتھ لے جانے جیسی سادہ حرکات مشکل ہو سکتی ہیں۔ ابتدائی ورزشیں اس سے بچنے میں مدد دیتی ہیں، اس لیے اپنی فزیوتھراپی جاری رکھیں اور اگر حرکت بہتر نہ ہو رہی ہو تو اپنے فزیوتھراپسٹ کو بتائیں۔
زخم میں مسائل ہو سکتے ہیں۔ زخم سے باہر کی طرف پھیلتی ہوئی سرخی، رطوبت کے رسنے، یا ایسے گہرے، دھڑکتے ہوئے درد پر نظر رکھیں جو عام درد کش دواؤں سے کم نہ ہو۔ ان علامات کی صورت میں فوراً کلینک کو فون کریں۔ زخم کے نیچے خون کا تھوڑا سا جمع ہو جانا بھی سوجن کا سبب بن سکتا ہے؛ اگر ایسا ہو تو ہمیں بتائیں۔
سرجری کے دوران بازو کے قریب کے اعصاب کو چوٹ لگ سکتی ہے۔ آپ کو کلائی یا ہاتھ میں ایسا سُن پن، جھنجھناہٹ یا کمزوری محسوس ہو سکتی ہے جو پہلے نہیں تھی۔ اس کی فوراً اطلاع دیں۔
کندھے کی سرجری کے بعد خون کے لوتھڑے بن سکتے ہیں۔ اگر پنڈلی کے پچھلے حصے میں اچانک سوجن ہو اور اسے چھونے پر درد ہو، یا سانس پھولنے لگے، تو ہسپتال کی ایمرجنسی جائیں۔
اگر آپ تفصیل جاننا چاہتے ہیں تو اس صفحے پر پیچیدگیوں کا جدول ان کی عام شرحیں بتاتا ہے۔
ہمیں کب فون کریں
اگر آپ کو بخار ہو، یا اگر آپ کے زخم کے اردگرد کی جلد زیادہ سرخ ہو جائے، سوج جائے، یا اس سے رطوبت رسنے لگے تو فوراً ہمیں فون کریں۔ اگر آپ کو اچانک شدید درد ہو، پنڈلی کے پچھلے حصے میں اچانک سوجن ہو اور اسے چھونے پر درد ہو، یا سانس پھولنے لگے تو ہسپتال کی ایمرجنسی جائیں۔ یہ خون کے لوتھڑے کی علامات ہو سکتی ہیں۔ اگر آپ کا ہاتھ یا بازو سُن ہو جائے، ٹھنڈا محسوس ہو، یا آپ اسے حرکت نہ دے سکیں تو ہمیں فون کریں۔ کلائی یا ہاتھ میں نیا سُن پن یا جھنجھناہٹ ہو تو اس کے لیے بھی جلد فون کرنا ضروری ہے۔ اگر آپ کو یقین نہ ہو تو کلینک فون کریں، ہم آپ کی رہنمائی کریں گے۔
اس مسئلے کے بارے میں مزید کہاں پڑھیں
یہ صفحہ خود آپریشن کے بارے میں ہے۔ جس مسئلے کا یہ علاج کرتا ہے، بشمول اس کے کہ شواہد کیا بتاتے ہیں کہ سرجری کب فائدہ دیتی ہے اور کب نہیں، اس کی مزید تفصیل بازو کی اوپری ہڈی کے سرے کا فریکچر والے صفحے پر ہے۔
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Treatment for proximal humerus fractures remains controversial [4].
- Nonsurgical management of proximal humerus fractures demonstrates successful outcomes and union rates greater than 90% [4].
- Both intramedullary nails and locking plates can effectively restore shoulder function in the treatment of displaced proximal humeral fractures [1].
- The superiority of intramedullary nails over locking plates for restoring shoulder function in displaced proximal humeral fractures is unclear [1].
- Modern proximal humeral nail designs and techniques have demonstrated promising outcomes [2].
- Modern proximal humeral nail designs and techniques can provide stable fixation [2].
- Intramedullary nails are superior to locking plates in reducing total complication rates for proximal humerus fractures [3].
- Intramedullary nails are superior to locking plates in reducing intraoperative blood loss for proximal humerus fractures [3].
- Intramedullary nails are superior to locking plates in reducing operative time for proximal humerus fractures [3].
- Intramedullary nails are superior to locking plates in reducing postoperative fracture healing time for proximal humerus fractures [3].
- Intramedullary nails are superior to locking plates in reducing the postoperative humeral head necrosis rate for proximal humerus fractures [3].
- No superior treatment was suggested between locking plates and intramedullary nails for displaced proximal humeral fractures [5].
- Intramedullary nailing and plating demonstrate equivalent clinical outcomes for the surgical management of displaced proximal humerus fractures in adults [6].
- Patients undergoing ORIF for proximal humerus fracture dislocations have reasonable functional outcomes [7].
- Patients undergoing ORIF for proximal humerus fracture dislocations have relatively high avascular necrosis rates [7].
- Patients undergoing ORIF for proximal humerus fracture dislocations have relatively high reoperation rates [7].
- Intramedullary fixation represents an alternative treatment option for proximal humeral fractures [8].
- Intramedullary fixation for proximal humeral fractures has specific fixation and biologic advantages [8].
- Intramedullary fixation for proximal humeral fractures has reported outcomes comparable with other techniques [8].
- Fixation of proximal humerus fractures with proximal humerus locking plates is associated with a high rate of complications [10].
- Fixation of proximal humerus fractures with proximal humerus locking plates is associated with a high rate of reoperation [10].
- Limited evidence suggests that locking plate and intramedullary nail are both valuable options for the treatment of proximal humeral fractures [11].
- No single fixation method is a panacea for proximal humeral fractures [17].
- The choice of implant and method for proximal humeral fractures should be selected according to individual patient and fracture pattern characteristics based on clearly defined indications and contraindications [17].
- Augmentation of plate fixation for proximal humeral fractures seems to be a reliable and safe procedure [21].
- Augmentation of plate fixation for proximal humeral fractures mechanically increases construct stability [21].
- Augmentation of plate fixation for proximal humeral fractures reduces complication rates [21].
- Augmentation of plate fixation for proximal humeral fractures improves patient outcomes [21].
Anatomy & Pathophysiology
Bony Anatomy
- The proximal humeral anatomy comprises four main parts: the humeral head, greater tuberosity (GT), lesser tuberosity (LT), and humeral shaft [35].
- The articular head is spherical and has a diameter of 37 to 57 mm [35].
- The most superior portion of the articular surface of the humeral head averages 8 mm above the GT [35].
- Humeral version averages 29.8 degrees, with a range of 10 to 55 degrees [35].
- The humeral head is inclined approximately 130 degrees with respect to the humeral shaft [35].
- The bicipital groove lies between the GT and LT and serves as a pathway for the long head of the biceps [35].
- The distal aspect of the bicipital groove is internally rotated with respect to the proximal portion [35].
- The anatomic neck of the proximal humerus is located at the junction of the articular surface and the tuberosities [35].
- The surgical neck represents an indistinct region (metadiaphyseal junction) below the tuberosities but above the humeral shaft [35].
- The GT is located in a posterior-superior location with respect to the humeral shaft and serves as the attachment site for the supraspinatus, infraspinatus, and teres minor tendons [35].
- The LT is located on the anterior aspect of the proximal humerus and serves as the attachment site for the subscapularis tendon [35].
- The glenoid is a convex structure of shallow depth shaped like an inverted pear [35].
- The acromion, coracoacromial ligament, and coracoid process form the coracoacromial arch, a rigid bony-ligamentous structure that imparts stability to the shoulder girdle [35].
- The humeral head averages 19° of retroversion and 41° of inclination (neck-shaft angle) [38].
- The neck-shaft angle measures an average of 135 degrees, and the humeral head is retroverted an average of 30 degrees [36].
- The proximal humerus has three centers of ossification: the humeral head (4 to 6 months), the greater tuberosity (1 to 3 years), and the lesser tuberosity (3 to 5 years) [38].
- The ossification centers of the proximal humerus fuse to the shaft at age 17 to 20 years [38].
- The glenoid cavity is a shallow socket, approximately one third the size of the humeral head [36].
Vascular Supply
- The proximal humerus receives its blood supply from the anterior and posterior humeral circumflex branches from the third division of the axillary artery [35].
- The posterior humeral circumflex artery travels with the axillary nerve, enters the quadrilateral space posteriorly, and anastomoses with a branch of the anterior circumflex to supply the posterior cuff [35].
- The anterior humeral circumflex artery (AHCA) arises from the axillary artery at the inferior border of the subscapularis [35].
- The AHCA provides vascular inflow to the humeral head by way of its terminal anterolateral branch known as the artery of Laing (also known as the arcuate artery) [35].
- The ascending branch of the AHCA courses parallel to the lateral aspect of the long head biceps tendon and enters the humeral head at the interface of the bicipital groove and GT [35].
- Injury to the arcuate artery may result in osteonecrosis of the humeral head [35].
- Additional extraosseous collateral branches can permit humeral head perfusion despite complete ligation of the arcuate artery [35].
- The major blood supply to the humeral head is through the ascending branch of the anterior humeral circumflex artery, which penetrates the head at the bicipital groove and becomes the arcuate artery [36].
- The anterolateral ascending branch of the anterior humeral circumflex artery provides the primary blood supply to the humeral head [38].
- The terminal intraosseous portion of the anterior humeral circumflex artery enters at the proximal aspect of the intertubercular groove as the arcuate artery [38].
Pathophysiology and Displacement
- Following a fracture of the proximal humerus, displacement of each "part" occurs in a predictable manner based on the deforming forces created by the tendinous insertions of the pectoralis major, subscapularis, supraspinatus, and infraspinatus [35].
- The subscapularis inserts on the lesser tuberosity and causes medial displacement [35].
- The supraspinatus and infraspinatus insert on the greater tuberosity and cause superior and posterior displacement [35].
- The pectoralis major inserts on the humeral shaft and displaces it medially [35].
- A fracture involving the anatomic neck is prognostically worse than fractures involving other regions of the proximal humerus with respect to the potential disruption of the vascular supply to the humeral head and the subsequent development of avascular necrosis [35].
- Fractures of the anatomic neck have a poor prognosis because of complete disruption of the blood supply to the head [36].
- Surgical neck fractures are common, and with these, the blood supply to the head is preserved [36].
- PHFs alter complex interactions of joint surface anatomy, joint volume, atmospheric pressure, and joint fluid cohesion and adhesion, resulting in pain, decreased ROM and stiffness, and disability [35].
- Displaced PHFs can impede normal movement of the rotator cuff, subacromial bursa, and subdeltoid bursa passing underneath the coracoacromial arch, causing impingement and disruption of normal glenohumeral motion [35].
- In PHFs (displaced and nondisplaced fractures), the subdeltoid and subacromial bursae can become thickened and fibrotic, forming adhesions that can limit normal glenohumeral motion [35].
- Early ROM exercises after a fracture have been hypothesized to decrease the formation of such adhesions [35].
- The rotator cuff muscles serve as depressors of the humeral head to allow the deltoid to efficiently abduct the humerus [36].
- The infraspinatus and teres minor are external rotators, while the subscapularis is an internal rotator of the humerus [36].
- The deltoid and pectoralis major muscles, along with the rotator cuff, cause predictable displacement of fractures around the proximal humerus [36].
Classification
- Observer agreement for classifying proximal humeral fractures according to the AO-classification is low, with reported mean kappa values for interobserver agreement varying between 0.26 and 0.53 [51].
- Mean kappa values for interobserver agreement decreased from 0.53 for AO Types to 0.2 for AO Groups, suggesting decreased agreement with an increasing number of classification units [51].
- No study has assessed observer agreement on AO-subgroups [51].
- In a systematic review of locking plate fixation, the classification procedure was reported in only five out of twelve studies [51].
- In three studies within a systematic review of locking plate fixation, the classification was performed by one surgeon, and in two studies, it was performed by two or three surgeons [51].
- Classification type and group seem to be of minor importance for clinical outcome in most studies [51].
- Outcome after locking plate osteosynthesis in AO/OTA Type C fractures was comparable with outcome reported in displaced 4-part fractures [51].
- According to the ICD-10 classification system, fractures of the humeral head were the most common fracture type for proximal humerus fractures [54].
- Intramedullary nail fixation was utilized maximally (~ 20%) in fractures of the surgical neck (S42.22) [54].
- Intramedullary nail fixation was least likely used in humeral head fractures (S42.21) [54].
- Reverse shoulder arthroplasty (RSA) showed its highest utilization rate in humeral head fractures and fractures of the anatomical neck (S42.23) [54].
- Fractures of the greater tuberosity (S42.24) were mainly managed by screw fixation (40.4%) [54].
Clinical Presentation
- Adult proximal humeral fractures occur at an estimated annual rate of 6 per 10,000 persons in the United States [13].
- Proximal humeral fractures vary in location and complexity, potentially involving any combination of the surgical and anatomic necks of the humerus, as well as the greater and lesser tuberosities [13].
- The choice of treatment for proximal humeral fractures depends on the fracture type and severity, surgeon expertise, patient age, and patient health status [30].
- Nonsurgical management for proximal humerus fractures demonstrates successful outcomes and union rates greater than 90% [4].
- Most proximal humeral fractures in elderly patients can be treated nonoperatively with good functional outcomes [9].
- Over the past decade, most older adults who sustain proximal humerus fractures continue to receive nonoperative treatment [19].
- Multiple studies comparing nonoperative and operative treatment for displaced proximal humeral fractures in the geriatric population have demonstrated minimal differences in functional outcomes [13].
- Factors such as surgeon experience as well as the quality and maintenance of the reduction may influence operative outcomes for displaced proximal humeral fractures in the geriatric population [13].
- In the treatment of 2 and 3-part fractures involving the surgical neck, intramedullary nailing has demonstrated functional outcomes that are comparable with those of open reduction and internal fixation (ORIF) [13].
- Several authors have demonstrated the negative effect of osteopenia on outcomes after ORIF of proximal humeral fractures [13].
- Optimal management of osteoporotic proximal humeral fractures has evolved to include the use of locking plates and augmentation with intramedullary fibular grafts, calcium phosphate or sulfate cement, and iliac crest bone graft [66].
- Patients undergoing ORIF for proximal humerus fracture dislocations have reasonable functional outcomes but relatively high avascular necrosis and reoperation rates [7].
- Fixation of proximal humerus fractures with proximal humerus locking plates is associated with a high rate of complications and reoperation [10].
- Plate fixation was associated with a higher risk of avascular necrosis development than conservative treatment in patients with proximal humeral fractures [16].
- Considerable variability exists in the use of outcome measures across the proximal humerus fracture literature, making treatment comparison challenging [32].
Investigations
Imaging Protocols and Modalities
- At least two X-ray views should be obtained for shoulder imaging: an anteroposterior view in the plane of the glenoid and an axillary projection with the arm in abduction [43].
- The anteroposterior view in the plane of the scapula shows the superoinferior position of the humeral head relative to the glenoid, presence of osteophytes, joint space narrowing, degree of medial displacement, bone quality, loose bodies, and humeral head collapse or deformity [23].
- The axillary view taken with the arm in the functional position of elevation in the plane of the scapula is referred to as the "truth view" because it demonstrates glenohumeral relationships in the functional position of elevation [23].
- The standardized axillary "truth view" enables the measurement of posterior subluxation or "functional decentering" that is not evident in images taken with the arm at the side [23].
- Computed tomography (CT) is helpful for planning fracture surgery and shoulder joint replacement [43].
- Magnetic resonance imaging (MRI) is useful to identify osteonecrosis of the humeral head, bone tumours, labral tears, and rotator cuff tears [43].
- Ultrasound is a simple and accurate test for identifying rotator cuff tears and calcific tendinitis [43].
- The purpose of imaging the shoulder is to help establish the diagnosis, determine the severity of the pathoanatomy, assist in surgical planning, and enable the surgeon to illustrate the condition of the shoulder to the patient [23].
- Standardized plain films are almost always sufficient to garner the information needed for shoulder evaluation [23].
- Three-dimensional reconstructions can reveal fine details of shoulder anatomy, but this additional information rarely changes the planning or conduct of arthroplasty [23].
- Surgeons need to develop a judicious approach to imaging that yields necessary information while avoiding the tendency to "over-image" [45].
Preoperative Assessment and Fracture Characterization
- All available open reduction and internal fixation (ORIF) techniques require careful analysis of fracture type, fragment displacement, and bone quality, making preoperative CT extremely valuable for three- and four-part proximal humeral fractures [74].
- Imaging-based assessment of fracture stability does not reliably predict outcomes in patients with two-part proximal humeral fractures and may lead to unnecessary surgeries [73].
Outcome Measures
Treatment
Non-Operative Management
- Non-operative treatment is advocated for the majority of non-displaced and minimally displaced isolated tuberosity fractures with generally good outcomes [64].
- Most pediatric patients with proximal humerus fractures have favorable results, and complications are infrequent [14].
Operative Management: General Principles
- Treatment of displaced proximal humerus fractures must be individualized based on patient and fracture characteristics [25].
- No single fixation method is a panacea for proximal humeral fractures; choice of implant and method should be selected according to individual patient and fracture pattern characteristics based on clearly defined indications and contraindications [17].
- Surgical management of proximal humeral fractures in younger patients is challenging due to high expectations and the lack of a single device providing reproducible results [33].
- Technical strategies to maximize the success of surgical treatment for proximal humerus fractures emphasize innovations in technique and implant design to mitigate high complication rates [62].
Operative Management: Intramedullary Nailing
- Modern proximal humeral nail designs and techniques have demonstrated promising outcomes and can provide stable fixation [2].
- Intramedullary fixation represents an alternative treatment option for proximal humeral fractures with specific fixation and biologic advantages, including reported outcomes comparable with other techniques [8].
- Regaining full range of shoulder and elbow movements in combination with absence of complains regarding the shoulder or elbow joints has been striking, indicating that the unreamed technique and avoidance of locking screws could be important factors towards optimum outcomes [12].
- Retrograde elastic stable intramedullary nailing (ESIN) has become the method of choice for surgical treatment of proximal humerus fractures in children and adolescents based on many studies comparing this technique to direct percutaneous pinning [71].
Operative Management: Locking Plate Fixation
- Augmentation of plate fixation for proximal humeral fractures seems to be a reliable and safe procedure that mechanically increases construct stability and reduces complication rates while improving patient outcomes [21].
- Fixation of proximal humeral fractures in elderly patients using locked plates with or without cement augmentation has no significant difference in revision rate, but the implant failure and total complication rates may be lesser on using the cement-augmented locked plate for fixation than on using a locked plate alone [31].
- Augmentative procedures, including cortical strut augmentation, are being investigated to address the issue of osteopenia in proximal humeral fracture treatment; their role in the treatment of these fractures is unclear at this time [13].
Comparative Effectiveness: Nails vs. Plates
- The available evidence suggests that both intramedullary nails and locking plates can effectively restore shoulder function in the treatment of displaced proximal humeral fractures, with unclear superiority of either method [1].
- The intramedullary nail is superior to locking plate in reducing the total complication, intraoperative blood loss, operative time, postoperative fracture healing time and postoperative humeral head necrosis rate of PHF [3].
Operative Management: Fracture Dislocations and Arthroplasty
- In the geriatric population, reverse total shoulder arthroplasty has demonstrated improved functional outcomes, with a decreased rate of reoperation, compared with hemiarthroplasty [13].
- Tuberosity repair has been shown to improve functional outcomes and range of motion after both reverse total shoulder arthroplasty and hemiarthroplasty and should be performed at the time of arthroplasty [13].
- Comparative studies support the use of reverse shoulder arthroplasty in elderly patients with complex proximal humerus fractures because the functional outcomes and relief of pain are reliably improved [72].
Anesthesia
- Regional anaesthesia is a good option for postoperative analgesia in patients undergoing surgical repair of a proximal humerus fracture and is associated with fewer adverse events, a shorter recovery time, and a better functional outcome than those achieved by general anaesthesia alone [67].
Complications
General Complication Rates and Outcomes
- In a systematic review of late screw-related complications in locking plating, 33% of reported cases had at least one complication, with 11% of all complications being screw-related [20].
- Patients undergoing ORIF for proximal humerus fracture dislocations have relatively high avascular necrosis and reoperation rates [7].
- Open fractures and 4-part proximal humerus fractures had the highest complication rates following intramedullary nailing [79].
- A meta-analysis of randomized controlled trials did not support the treatment of open reduction and internal fixation to improve the functional outcome when compared with nonoperative treatment for treating elderly patients with displaced 3-part or 4-part proximal humeral fractures [75].
- In most studies of proximal humeral fractures, only 1 or 2 patients experiencing an alternative outcome or lost to follow-up would change the conclusions for the dichotomous outcome studied [29].
Avascular Necrosis
- The intramedullary nail is superior to locking plate in reducing the postoperative humeral head necrosis rate of proximal humerus fractures [3].
Screw and Implant-Related Complications
- Most late screw-related complications in locking plating were secondary screw perforations and screw cut-outs, being predominantly linked to poor bone quality [20].
- Screw loosening and retraction were found less frequently as a result of locking mechanism failure in locking plating of proximal humerus fractures [20].
- Screw perforation was the most frequent screw-related complication in locking plating, mostly reported in female patients older than 50 years, following four-part or AO/OTA type C fractures, and detected four weeks postoperatively [20].
- Locked humeral stems provide reliable diaphyseal fixation with a low incidence of screw-related complications in reverse total shoulder arthroplasty for complex proximal humerus fractures [78].
Augmentation and Allograft Outcomes
- Augmentation of plate fixation for proximal humeral fractures mechanically increases construct stability and reduces complication rates while improving patient outcomes [21].
- Patients with proximal humerus fractures treated with a locking compression plate augmented with a fibular allograft have decreased odds of a major complication when compared with patients treated with a locking compression plate alone [81].
Venous Thromboembolism
- Venous thromboembolism was the most frequently reported complication after shoulder arthroplasty when compared to ORIF, with reverse shoulder arthroplasty having the highest venous thromboembolism rate [70].
Salvage and Revision Surgery
- The failed fixation group performed significantly better than the failed hemiarthroplasty group in postoperative constant and shoulder abduction after salvage reverse shoulder arthroplasty [27].
- Revision surgery for failed arthroplasty of proximal humerus fracture is complex with a high likelihood of inferior outcomes compared with primary arthroplasty [77].
Non-Operative Management
- Complications following non-surgical management of proximal humeral fractures are described using heterogeneous terminology and definitions, calling for standardized definitions to improve evidence synthesis [34].
Recovery
- A systematic review of rehabilitation protocols in proximal humerus fracture management included 3507 patients and 3519 proximal humerus fractures [24].
- In the systematic review of rehabilitation protocols, 65.9% of the patients were female [24].
- The weighted mean age of patients in the rehabilitation protocol systematic review was 63.5 years [24].
- The follow-up duration in the rehabilitation protocol systematic review was 22.4 months [24].
- Of the 45 treatment cohorts included in the rehabilitation protocol systematic review, 33 were treated with ORIF with plate fixation and 5 were treated with ORIF with intramedullary nail [24].
- Of the included proximal humerus fractures in the rehabilitation protocol systematic review, 2220 were treated with ORIF with plating and 208 were treated with a nail [24].
- Ten studies included in the rehabilitation protocol systematic review included fracture dislocations in their cohorts [24].
- The levels of evidence in the rehabilitation protocol systematic review were Level I (15%), Level II (8%), Level III (25%), and Level IV (53%) [24].
- Patients 65 years of age with 3- or 4-part proximal humerus fractures achieve the most benefit in terms of range of motion, postoperative functional outcomes, tuberosity union, and overall complication rate when undergoing reverse total shoulder arthroplasty with a noncemented stem and early postoperative range of motion compared to reverse total shoulder arthroplasty with a cemented stem and delayed rehabilitation [69].
Key Evidence
- [L5] The available evidence suggests that both intramedullary nails and locking plates can effectively restore shoulder function in the treatment of displaced proximal humeral fractures, with unclear superiority of either method. [1] (10.1016/j.xrrt.2024.01.001)
- [L5] Modern proximal humeral nail designs and techniques have demonstrated promising outcomes and can provide stable fixation. [2] (10.1016/j.jse.2015.11.016)
- [L1] The intramedullary nail is superior to locking plate in reducing the total complication, intraoperative blood loss, operative time, postoperative fracture healing time and postoperative humeral head necrosis rate of PHF. [3] (10.1186/s13018-019-1345-0)
- [L5] Treatment for proximal humerus fractures remains controversial, with nonsurgical management demonstrating successful outcomes and union rates greater than 90%. [4] (10.5435/jaaos-d-24-01073)
- [L1] No superior treatment was suggested between locking plates and intramedullary nails for displaced proximal humeral fractures. [5] (10.1007/s00264-017-3683-z)
- [L1] Intramedullary nailing and plating demonstrate equivalent clinical outcomes for the surgical management of displaced proximal humerus fractures in adults. [6] (10.1016/j.jse.2026.02.016)
- [L4] Patients undergoing ORIF for proximal humerus fracture dislocations have reasonable functional outcomes but relatively high avascular necrosis and reoperation rates. [7] (10.1016/j.jse.2022.04.018)
- [L4] Intramedullary fixation represents an alternative treatment option for proximal humeral fractures with specific fixation and biologic advantages, including reported outcomes comparable with other techniques. [8] (10.5435/jaaos-d-18-00360)
- [L5] Most proximal humeral fractures in elderly patients can be treated nonoperatively with good functional outcomes. [9] (10.2106/jbjs.l.01293)
- [L4] Fixation of proximal humerus fractures with proximal humerus locking plates is associated with a high rate of complications and reoperation. [10] (10.1016/j.injury.2010.11.058)
- [L1] Limited evidence suggests that locking plate and intramedullary nail are both valuable options for the treatment of proximal humeral fractures. [11] (10.1186/s13018-015-0242-4)
- [L4] Regaining full range of shoulder and elbow movements in combination with absence of complains regarding the shoulder or elbow joints has been striking, indicating that the unreamed technique and avoidance of locking screws could be important factors towards optimum outcomes. [12] (10.1016/s0020-1383(13)70037-8)
- [L5] [13] (10.2106/jbjs.20.00665)
- [L5] Most pediatric patients with proximal humerus fractures have favorable results, and complications are infrequent. [14] (10.5435/jaaos-d-14-00033)
- [L1] Plate fixation was associated with a higher risk of AVN development than conservative treatment in patients with proximal humeral fractures. [16] (10.1186/1749-799x-9-31)
- [L4] No single fixation method is a panacea for proximal humeral fractures; choice of implant and method should be selected according to individual patient and fracture pattern characteristics based on clearly defined indications and contraindications. [17] (10.1016/j.injury.2010.10.016)
- [L4] Over the past decade, most older adults who sustain proximal humerus fractures continue to receive nonoperative treatment. [19] (10.1016/j.jseint.2021.08.006)
- [L2] [20] (10.1016/j.injury.2019.11.002)
- [L1] Augmentation of plate fixation for proximal humeral fractures seems to be a reliable and safe procedure that mechanically increases construct stability and reduces complication rates while improving patient outcomes. [21] (10.1007/s00402-019-03162-2)
- [L4] [24] (10.1177/17585732231182374)
- [L5] Treatment of displaced proximal humerus fractures must be individualized based on patient and fracture characteristics, with a general evolution toward humeral head preservation using options ranging from nonsurgical immobilization to various surgical techniques including locking plate fixation and hemiarthroplasty. [25] (10.5435/00124635-200701000-00003)
- [L2] The failed fixation group performed significantly better than the failed HA group in postoperative constant and shoulder abduction. [27] (10.1177/17585732221099200)
- [L2] In most studies of proximal humeral fractures, only 1 or 2 patients experiencing an alternative outcome or lost to follow-up would change the conclusions for the dichotomous outcome studied. [29] (10.1016/j.jse.2022.01.141)
- [L4] The choice of treatment for proximal humeral fractures depends on the fracture type and severity, surgeon expertise, patient age, and patient health status. [30] (10.5435/jaaos-d-15-00240)
- [L1] Fixation of proximal humeral fractures in elderly patients using locked plates with or without cement augmentation has no significant difference in revision rate, but the implant failure and total complication rates may be lesser on using the cement-augmented locked plate for fixation than on using a locked plate alone. [31] (10.1186/s12891-024-07502-1)
- [L4] Considerable variability exists in the use of outcome measures across the proximal humerus fracture literature, making treatment comparison challenging. [32] (10.1016/j.jse.2020.04.006)
- [L5] The paper concludes that surgical management of proximal humeral fractures in younger patients is challenging due to high expectations and the lack of a single device providing reproducible results. [33] (10.1016/j.jse.2010.12.006)
- [L1] This systematic review highlights significant heterogeneity in the terminology and definitions used to describe complications following non-surgical management of proximal humeral fractures, calling for standardized definitions to improve evidence synthesis. [34] (10.1186/s12891-019-2459-6)
- [L2] [51] (10.1016/j.injury.2011.08.025)
- [L4] [54] (10.1007/s00402-019-03252-1)
- [L5] This review highlights various technical strategies to maximize the success of surgical treatment for proximal humerus fractures, emphasizing innovations in technique and implant design to mitigate high complication rates. [62] (10.5435/jaaos-d-22-01211)
- [L4] Non-operative treatment is advocated for the majority of non-displaced and minimally displaced fractures with generally good outcomes, while displaced fractures may require arthroscopically assisted fixation or open/percutaneous reduction and internal fixation depending on fracture type and patient factors. [64] (10.1016/j.injury.2007.09.022)
- [L4] Optimal management of osteoporotic proximal humeral fractures has evolved to include the use of locking plates and augmentation with intramedullary fibular grafts, calcium phosphate or sulfate cement, and iliac crest bone graft. [66] (10.1016/j.jse.2012.04.003)
- [L1] This systematic review suggests that RA is a good option for postoperative analgesia in patients undergoing surgical repair of a proximal humerus fracture and is associated with fewer adverse events, a shorter recovery time, and a better functional outcome than those achieved by general anaesthesia alone. [67] (10.1007/s00402-019-03253-0)
- [L1] Patients 65 years of age with 3- or 4-part proximal humerus fractures achieve the most benefit in terms of ROM, postoperative functional outcomes, tuberosity union, and overall complication rate when undergoing rTSA with a noncemented stem and early postoperative ROM compared to rTSA with cemented stem and delayed rehabilitation. [69] (10.1016/j.jse.2024.03.040)
- [L4] Among the various procedures, VTE was the most frequently reported after SA when compared to ORIF, with RSA having the highest VTE rate. [70] (10.1016/j.xrrt.2023.06.003)
- [L5] [71] (10.1016/j.otsr.2013.06.010)
- [L4] Comparative studies support the use of reverse shoulder arthroplasty in elderly patients with complex proximal humerus fractures because the functional outcomes and relief of pain are reliably improved. [72] (10.5435/jaaos-d-13-00190)
- [L5] Imaging-based assessment of fracture stability does not reliably predict outcomes in patients with two-part proximal humeral fractures and may lead to unnecessary surgeries. [73] (10.1530/eor-2026-0043)
- [L4] All available ORIF techniques require careful analysis of fracture type, fragment displacement, and bone quality, making preoperative CT extremely valuable. [74] (10.1016/j.otsr.2012.12.006)
- [L1] The meta-analysis did not support the treatment of open reduction and internal fixation to improve the functional outcome when compared with nonoperative treatment for treating elderly patients with displaced 3-part or 4-part proximal humeral fractures. [75] (10.1371/journal.pone.0075464)
- [L5] Revision surgery for failed arthroplasty of proximal humerus fracture is complex with a high likelihood of inferior outcomes compared with primary arthroplasty. [77] (10.5435/jaaos-d-17-00051)
- [L4] Locked humeral stems provide reliable diaphyseal fixation with a low incidence of screw-related complications in reverse total shoulder arthroplasty for complex proximal humerus fractures. [78] (10.1016/j.xrrt.2025.100625)
- [L4] Open fractures and 4-part proximal humerus fractures had the highest complication rates. [79] (10.1016/j.jse.2024.07.049)
- [L1] The pooled WMD and prediction interval suggest that 95% of patients with proximal humerus fractures treated with an LCP augmented with a fibular allograft will have improved radiographic outcomes, improved ASES clinical outcome scores, and decreased odds of a major complication when compared with patients treated with an LCP alone. [81] (10.1016/j.jse.2021.11.004)
References
[1] Intramedullary versus locking plate fixation for proximal humerus fractures: indications and technical considerations. JSES Reviews, Reports, and Techniques. 2024. DOI: 10.1016/j.xrrt.2024.01.001
[2] Intramedullary nailing of the proximal humerus: evolution, technique, and results. Journal of Shoulder and Elbow Surgery. 2016. DOI: 10.1016/j.jse.2015.11.016
[3] Effect of intramedullary nail and locking plate in the treatment of proximal humerus fracture: an update systematic review and meta-analysis. Journal of Orthopaedic Surgery and Research. 2019. DOI: 10.1186/s13018-019-1345-0
[4] Contemporary Management of Proximal Humeral Fractures. Journal of the American Academy of Orthopaedic Surgeons. 2025. DOI: 10.5435/jaaos-d-24-01073
[5] Locking plates versus intramedullary nails in the management of displaced proximal humeral fractures: a systematic review and meta-analysis. International Orthopaedics. 2017. DOI: 10.1007/s00264-017-3683-z
[6] Effectiveness of intramedullary nailing vs. locked plating (open reduction and internal fixation) in adult displaced proximal humerus fractures: a systematic review and meta-analysis. Journal of Shoulder and Elbow Surgery. 2026. DOI: 10.1016/j.jse.2026.02.016
[7] Fracture dislocations of the proximal humerus treated with open reduction and internal fixation: a systematic review. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2022.04.018
[8] Intramedullary Fixation for Proximal Humeral Fractures. Journal of the American Academy of Orthopaedic Surgeons. 2020. DOI: 10.5435/jaaos-d-18-00360
[9] Proximal Humeral Fracture Treatment in Adults. Journal of Bone and Joint Surgery. 2014. DOI: 10.2106/jbjs.l.01293
[10] A systematic review of locking plate fixation of proximal humerus fractures. Injury. 2011. DOI: 10.1016/j.injury.2010.11.058
[11] Meta-analysis of locking plate versus intramedullary nail for treatment of proximal humeral fractures. Journal of Orthopaedic Surgery and Research. 2015. DOI: 10.1186/s13018-015-0242-4
[12] T1.11 The management of 100 humeral shaft fractures with “Garnavos” humeral nail. Injury. 2013. DOI: 10.1016/s0020-1383(13)70037-8
[13] Current Controversies in the Treatment of Geriatric Proximal Humeral Fractures. Journal of Bone and Joint Surgery. 2021. DOI: 10.2106/jbjs.20.00665
[14] Evaluation and Management of Pediatric Proximal Humerus Fractures. Journal of the American Academy of Orthopaedic Surgeons. 2015. DOI: 10.5435/jaaos-d-14-00033
[16] Avascular necrosis in proximal humeral fractures in patients treated with operative fixation: a meta-analysis. Journal of Orthopaedic Surgery and Research. 2014. DOI: 10.1186/1749-799x-9-31
[17] New trends in fixation of proximal humeral fractures: A review. Injury. 2011. DOI: 10.1016/j.injury.2010.10.016
[19] Trending a decade of proximal humerus fracture management in older adults. JSES International. 2022. DOI: 10.1016/j.jseint.2021.08.006
[20] Late screw-related complications in locking plating of proximal humerus fractures: A systematic review. Injury. 2019. DOI: 10.1016/j.injury.2019.11.002
[21] Augmentation of plate osteosynthesis for proximal humeral fractures: a systematic review of current biomechanical and clinical studies. Archives of Orthopaedic and Trauma Surgery. 2019. DOI: 10.1007/s00402-019-03162-2
[23] Rockwood And Matsen S The Shoulder. Arthroscopic Management of Prearthritic and Arthritic Conditions of the Shoulder and the Postarthroplasty Shoulder > Radiographic Evaluation.
[24] Rehabilitation protocols in proximal humerus fracture management: A systematic review. Shoulder & Elbow. 2023. DOI: 10.1177/17585732231182374
[25] Innovations in the Management of Displaced Proximal Humerus Fractures. Journal of the American Academy of Orthopaedic Surgeons. 2007. DOI: 10.5435/00124635-200701000-00003
[27] Outcomes after salvage reverse shoulder arthroplasty for failed primary fixation or hemiarthroplasty for proximal humerus fractures: A systematic review. Shoulder & Elbow. 2022. DOI: 10.1177/17585732221099200
[29] Fragility of randomized controlled trials on treatment of proximal humeral fracture. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2022.01.141
[30] Management of Acute Proximal Humeral Fractures. Journal of the American Academy of Orthopaedic Surgeons. 2017. DOI: 10.5435/jaaos-d-15-00240
[31] Cement-augmented locked plate fixation proximal humerus fractures in elderly patient: a systematic review and meta-analysis. BMC Musculoskeletal Disorders. 2024. DOI: 10.1186/s12891-024-07502-1
[32] Outcome measures reported for the management of proximal humeral fractures: a systematic review. Journal of Shoulder and Elbow Surgery. 2020. DOI: 10.1016/j.jse.2020.04.006
[33] Proximal humeral fractures in younger patients: fixation techniques and arthroplasty. Journal of Shoulder and Elbow Surgery. 2011. DOI: 10.1016/j.jse.2010.12.006
[34] Complications after non-surgical management of proximal humeral fractures: a systematic review of terms and definitions. BMC Musculoskeletal Disorders. 2019. DOI: 10.1186/s12891-019-2459-6
[35] Rockwood And Matsen S The Shoulder. Shoulder and Elbow Specialty Clinic Workers’ Survey > ANATOMY.
[36] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > SHOULDER AND ARM INJURIES.
[38] Aaos Comprehensive Orthopaedic Review 3. Anatomy of the Shoulder, Arm, and Elbow > I. Shoulder.
[43] Apley And Solomon S Concise System Of Orthopaedics And Trauma. INVESTIGATION.
[45] Rockwood And Matsen S The Shoulder. Developmental Anatomy of the Shoulder and Anatomy of the Glenohumeral Joint > SENIOR EDITOR COMMENTARY.
[51] Benefits and harms of locking plate osteosynthesis in intraarticular (OTA Type C) fractures of the proximal humerus: A systematic review. Injury. 2012. DOI: 10.1016/j.injury.2011.08.025
[54] Trends in surgical management of proximal humeral fractures in adults: a nationwide study of records in Germany from 2007 to 2016. Archives of Orthopaedic and Trauma Surgery. 2019. DOI: 10.1007/s00402-019-03252-1
[62] Technical Tips for Reduction and Stable Fixation of Proximal Humerus Fractures. Journal of the American Academy of Orthopaedic Surgeons. 2023. DOI: 10.5435/jaaos-d-22-01211
[64] Isolated tuberosity fractures of the proximal humerus: Current concepts. Injury. 2008. DOI: 10.1016/j.injury.2007.09.022
[66] Evaluation of the osteoporotic proximal humeral fracture and strategies for structural augmentation during surgical treatment. Journal of Shoulder and Elbow Surgery. 2012. DOI: 10.1016/j.jse.2012.04.003
[67] Regional anaesthesia for surgical repair of proximal humerus fractures: a systematic review and critical appraisal. Archives of Orthopaedic and Trauma Surgery. 2019. DOI: 10.1007/s00402-019-03253-0
[69] Optimal combination of arthroplasty type, fixation method, and postoperative rehabilitation protocol for complex proximal humerus fractures in the elderly: a network meta-analysis. Journal of Shoulder and Elbow Surgery. 2024. DOI: 10.1016/j.jse.2024.03.040
[70] Venous thromboembolism following surgical management of proximal humerus fractures: a systematic review. JSES Reviews, Reports, and Techniques. 2023. DOI: 10.1016/j.xrrt.2023.06.003
[71] Proximal humerus fractures in children and adolescents. Orthopaedics & Traumatology: Surgery & Research. 2014. DOI: 10.1016/j.otsr.2013.06.010
[72] Reverse Shoulder Arthroplasty for the Management of Proximal Humerus Fractures. Journal of the American Academy of Orthopaedic Surgeons. 2015. DOI: 10.5435/jaaos-d-13-00190
[73] Imaging-based assessment of fracture stability does not reliably predict outcomes in patients with two-part proximal humeral fractures and may lead to unnecessary surgeries. EFORT Open Reviews. 2026. DOI: 10.1530/eor-2026-0043
[74] Surgical treatment of three and four-part proximal humeral fractures. Orthopaedics & Traumatology: Surgery & Research. 2013. DOI: 10.1016/j.otsr.2012.12.006
[75] Internal Fixation Versus Nonoperative Treatment for Displaced 3-Part or 4-Part Proximal Humeral Fractures in Elderly Patients: A Meta-Analysis of Randomized Controlled Trials. PLoS ONE. 2013. DOI: 10.1371/journal.pone.0075464
[77] Management of the Failed Arthroplasty for Proximal Humerus Fracture. Journal of the American Academy of Orthopaedic Surgeons. 2019. DOI: 10.5435/jaaos-d-17-00051
[78] Use of locking humeral stems in reverse total shoulder arthroplasty for complex proximal humerus fractures: a scoping review. JSES Reviews, Reports, and Techniques. 2026. DOI: 10.1016/j.xrrt.2025.100625
[79] Complications following intramedullary nailing of proximal humerus and humeral shaft fractures: a systematic review. Journal of Shoulder and Elbow Surgery. 2025. DOI: 10.1016/j.jse.2024.07.049
[81] Improved outcomes for proximal humerus fracture open reduction internal fixation augmented with a fibular allograft in elderly patients: a systematic review and meta-analysis. Journal of Shoulder and Elbow Surgery. 2022. DOI: 10.1016/j.jse.2021.11.004