Patients › Rehabilitation
لیٹرل ایپی کونڈائلائٹس (ٹینس ایلبو، Lateral Epicondylitis)
ٹینس ایلبو کے لیے بوجھ پر مبنی بحالی کا پروگرام — پہلے درد کم کرنا اور پھر ٹینڈن کو بتدریج مضبوط کرنا — جس میں سرجری کے بغیر علاج اور ای سی آر بی (ECRB) ٹینڈن کی صفائی کے آپریشن کے بعد صحت یابی دونوں شامل ہیں۔

یہ صفحہ بتاتا ہے کہ ٹینس ایلبو (کہنی کے باہر کی طرف درد) کا انتظام کیسے کیا جاتا ہے اور اس کی بحالی کیسے کی جاتی ہے، چاہے آپ اس کا علاج سرجری کے بغیر کر رہے ہوں (جو تقریباً ہر ایک کے ساتھ ہوتا ہے) یا ٹینڈن (tendon)، یعنی وہ مضبوط ڈوری جو پٹھے کو ہڈی سے جوڑتی ہے، کی صفائی کے آپریشن کے بعد صحت یاب ہو رہے ہوں۔ اس کی نگرانی Mater Private Hospital Rockhampton میں ڈاکٹر کیرن ہِرپرا کرتے ہیں۔ یہ آپ کے گھریلو ورزش کے پروگرام سے شروع ہوتا ہے، جس کے بعد آپ کے فزیوتھراپسٹ یا ہینڈ تھراپسٹ (ہاتھ کی بحالی کے ماہر) کے لیے لکھا گیا منظم کلینیکل پروٹوکول ہے؛ اپنی تھراپی کی ملاقاتوں پر یہ صفحہ یا اس کی پی ڈی ایف ساتھ لائیں تاکہ آپ کی بحالی میں سب ایک ہی طریقے پر چلیں۔ آپ کا تھراپسٹ آپ کی صحت یابی کی پیش رفت کے مطابق اس منصوبے میں تبدیلی کر سکتا ہے۔
کیا توقع رکھیں
ٹینس ایلبو (lateral epicondylitis) کہنی کے باہر والی طرف کے ٹینڈن کا مسئلہ ہے، خاص طور پر کامن ایکسٹینسر ٹینڈن (common extensor tendon) کا، اور اس میں بھی خاص طور پر ایک چھوٹے پٹھے کا جسے ای سی آر بی (ECRB) کہتے ہیں۔ نام کے آخر میں "-itis" (سوزش) ہونے کے باوجود یہ ایسی سوزش نہیں ہے جو آرام کرنے سے ختم ہو جائے۔ یہ ٹینڈن میں گھساؤ کی تبدیلی ہے (ٹینڈینوسس، tendinosis)، جس میں ٹینڈن کے ریشے بے ترتیب ہو چکے ہوتے ہیں اور ٹھیک طرح سے نہیں بھرے ہوتے۔
یہ اس لیے اہم ہے کیونکہ اس سے علاج مکمل طور پر بدل جاتا ہے۔ آپ کہنی کو آرام دینے اور بچانے سے ٹھیک نہیں ہوتے؛ بلکہ لمبا آرام ٹینڈن کو کمزور کرتا ہے اور اس کے ٹھیک ہونے کو سست کر دیتا ہے۔ آپ ٹینڈن پر آہستہ آہستہ بوجھ ڈال کر ٹھیک ہوتے ہیں، تاکہ وہ خود کو نئے سرے سے ڈھالے اور کام اور گرفت کے لیے اپنی برداشت دوبارہ بنائے۔ طریقہ یہ ہے: پہلے درد کو کم کریں، پھر بتدریج طاقت بڑھائیں، ہلکی روک کر رکھنے والی (آئسومیٹرک، isometric) ورزشوں سے شروع کر کے قابو میں رکھی گئی، آہستہ طاقت کی ورزشوں تک، جیسے ٹائلر ٹوئسٹ (Tyler twist)۔
اچھی خبر یہ ہے کہ ٹینس ایلبو عام طور پر صحیح بوجھ والے پروگرام سے خود ہی ٹھیک ہو جاتا ہے۔ تقریباً 80 سے 90 فیصد لوگ ایک سال کے اندر بہتر ہو جاتے ہیں، اگرچہ کبھی کبھار مکمل طور پر ٹھیک ہونے میں 12 سے 18 ماہ لگ سکتے ہیں۔ سرجری پر صرف تب غور کیا جاتا ہے جب کم از کم چھ ماہ کی اچھے معیار کی، باقاعدہ بحالی ناکام ہو چکی ہو، اور صرف تھوڑے سے لوگ (تقریباً 4 سے 11 فیصد) کبھی اس مرحلے تک پہنچتے ہیں۔
احتیاطیں اور پابندیاں
یہ کریں:
- بازو کا استعمال جاری رکھیں: ٹینڈن پر بوجھ ڈالیں، اسے آرام نہ دیں۔
- درد کو اپنا رہنما بنائیں: ورزش کے دوران اور بعد میں ہلکا سا درد ٹھیک اور متوقع ہے؛ تیز یا بڑھتا ہوا درد ہو تو ورزش کم کر دیں۔
- ہتھیلی اوپر کی طرف رکھ کر چیزیں اٹھائیں (جیسے سوپ کا پیالہ اٹھاتے ہیں) تاکہ دکھتے ٹینڈن سے بوجھ ہٹ جائے۔
- گرفت اور اٹھانے والے کاموں کے دوران بازو کے نچلے حصے کے پٹھے پر کاؤنٹر فورس بریس (counterforce brace) استعمال کریں۔
یہ نہ کریں:
- سرجری کے بغیر علاج ہونے والے ٹینس ایلبو میں کہنی کو پلستر یا سلنگ (sling)، یعنی گلے سے لٹکی وہ پٹی جو بازو کو سہارا دیتی ہے، میں باندھ کر بے حرکت نہ کریں؛ ٹینڈینوسس کا یہ غلط علاج ہے۔ (سرجری کے بعد صورتحال مختلف ہے: پہلے ہفتے میں آرام کے لیے سلنگ استعمال کی جاتی ہے، جیسا کہ نیچے آپریشن کے بعد کے راستے میں بتایا گیا ہے۔)
- کہنی سیدھی اور کلائی مڑی ہوئی حالت میں درد بھڑکانے والی بھاری گرفت نہ کریں (مثال کے طور پر ہتھیلی نیچے کر کے کوئی بھاری چیز اٹھانا)۔
- اسٹیرائیڈ (کورٹیسون) کے انجکشن کی طرف جلدی نہ کریں۔ کورٹیسون سے چند ہفتے اچھا محسوس ہو سکتا ہے، لیکن شواہد بتاتے ہیں کہ 6 سے 12 ماہ پر اس کے نتائج فزیوتھراپی یا صرف انتظار کرنے کے مقابلے میں بدتر ہوتے ہیں اور مسئلہ زیادہ بار لوٹتا ہے۔ یہ علاج کا پہلا انتخاب نہیں ہے۔
آپ کی ورزشیں
Kieran Hirpara 4.0
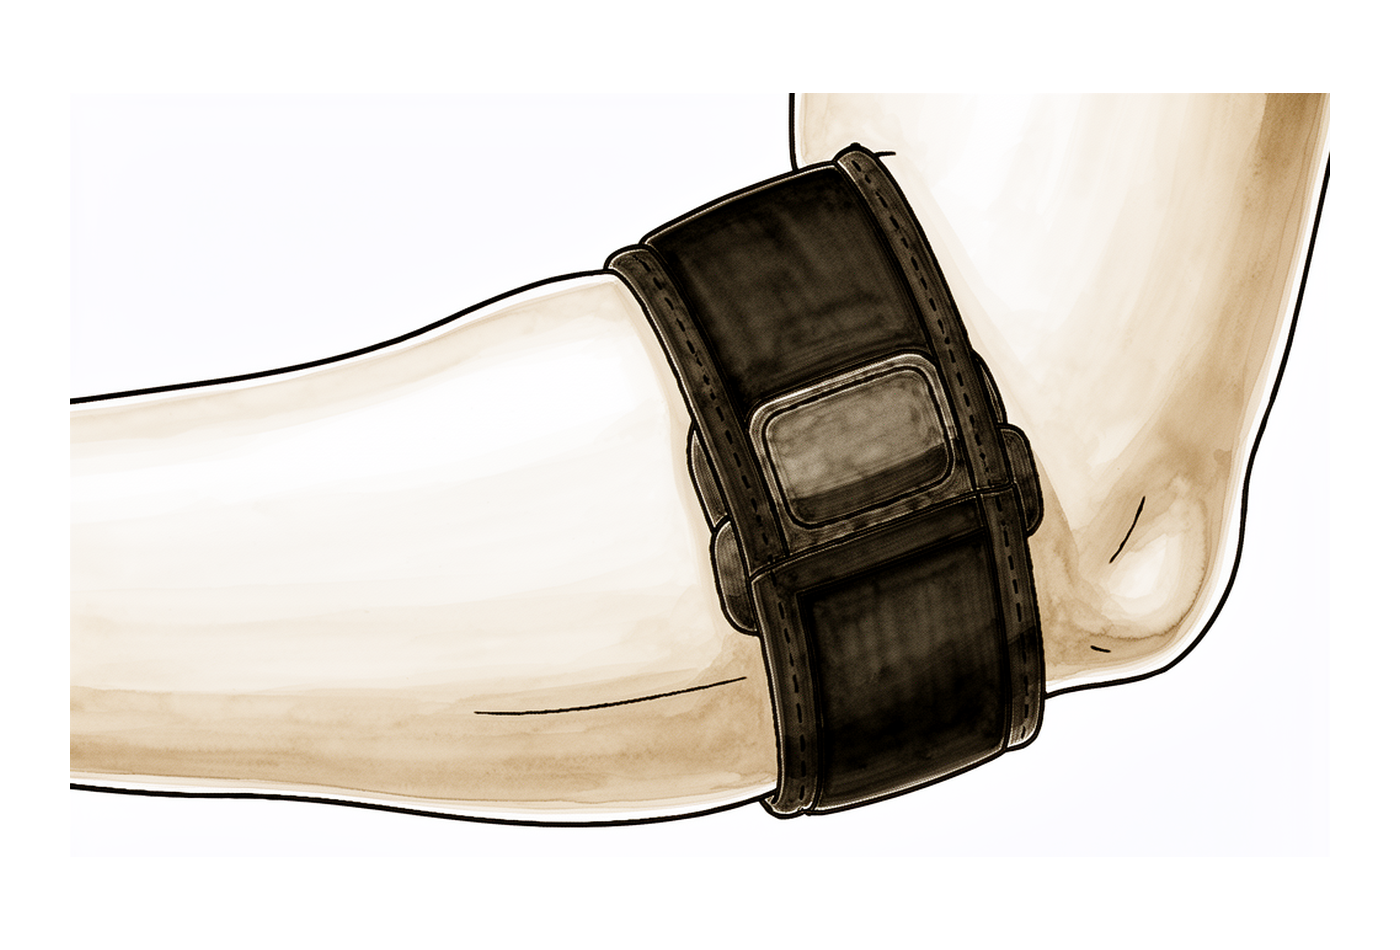
کاؤنٹر فورس بریس (counterforce brace)
کاؤنٹر فورس پٹی کو اپنے بازو کے نچلے حصے کے گرد، کہنی سے دو انگلیوں کی چوڑائی نیچے، پٹھے کے ابھرے ہوئے حصے پر باندھیں (خود ہڈی کے ابھار پر نہیں)۔ یہ مضبوطی سے بندھی ہو لیکن اتنی تنگ نہ ہو کہ آپ کے ہاتھ میں جھنجھناہٹ ہونے لگے۔ دکھتے ٹینڈن سے بوجھ ہٹانے کے لیے اسے گرفت اور اٹھانے والے کاموں کے دوران استعمال کریں؛ آرام کے وقت یا بستر میں اسے پہننے کی ضرورت نہیں۔
تکلیف بڑھانے والی سرگرمیوں کے دوران؛ اگر ہاتھ میں جھنجھناہٹ ہو تو ڈھیلا کر دیں
Kieran Hirpara 4.0
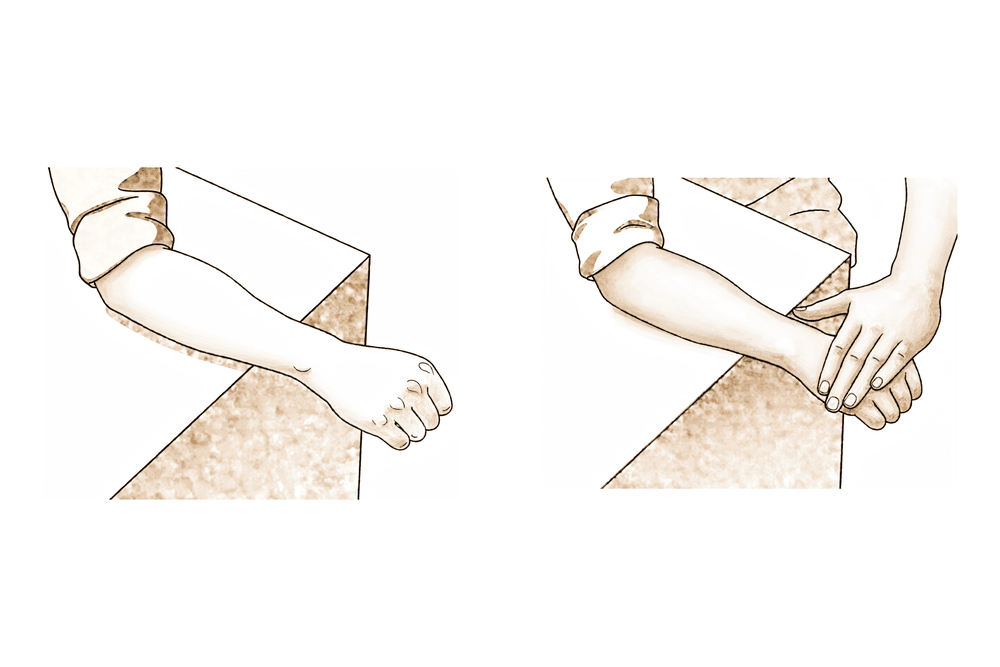
آئسومیٹرک (isometric) طریقے سے کلائی کو پیچھے موڑنا
اپنے بازو کا نچلا حصہ میز پر رکھیں، ہتھیلی نیچے کی طرف ہو اور ہاتھ میز کے کنارے سے باہر ہو۔ اپنا دوسرا ہاتھ دکھتے ہاتھ کی پشت پر رکھیں۔ ہاتھ کی پشت کو چھت کی طرف اٹھانے کی کوشش کریں جبکہ آپ کا دوسرا ہاتھ اسے روکے رکھے، تاکہ اصل میں کچھ حرکت نہ کرے — یہ روک کر، مزاحمت کے خلاف دبانے والی ورزش ہے۔ اس میں اچھا خاصا زور محسوس ہونا چاہیے لیکن تیز درد نہیں ہونا چاہیے۔ دباؤ کو روکے رکھیں، پھر ڈھیلا چھوڑ دیں۔
30 سے 45 سیکنڈ روکیں، 5 بار، دن میں 1 سے 2 مرتبہ
Kieran Hirpara 4.0
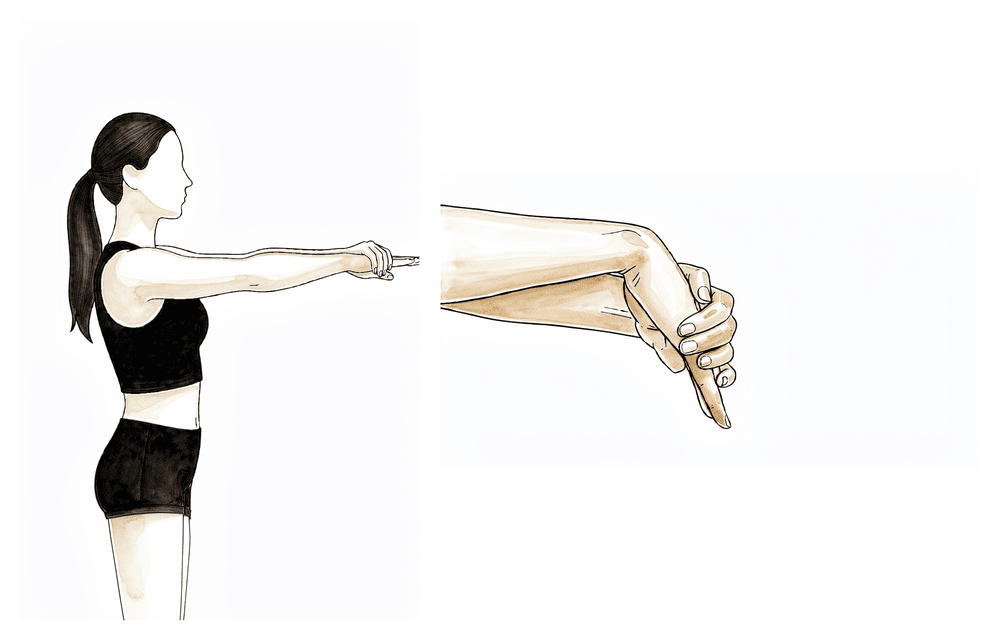
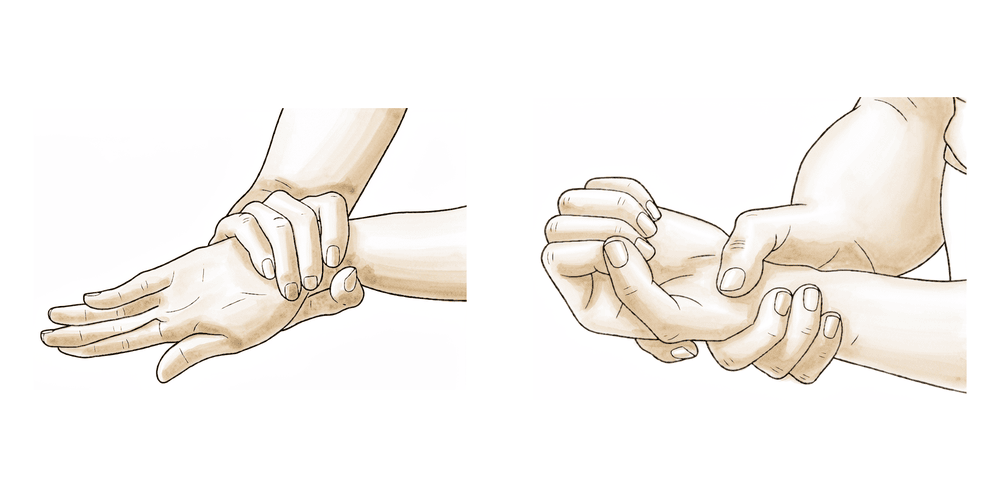
کلائی کو پیچھے موڑنے والے پٹھوں کا اسٹریچ
اپنا دکھتا بازو سامنے کی طرف پھیلائیں، کہنی سیدھی ہو اور ہتھیلی نیچے کی طرف ہو۔ دوسرے ہاتھ سے کلائی کو ہلکے سے نیچے موڑیں تاکہ انگلیاں فرش کی طرف ہوں، یہاں تک کہ آپ کو بازو کے نچلے حصے کے اوپر والی طرف آرام دہ کھنچاؤ محسوس ہو۔ کہنی سیدھی رکھیں۔ اگر کہنی سیدھی کرنے سے تیز درد ہو تو کہنی کو تھوڑا سا موڑ کر شروع کریں، اور تکلیف کم ہونے کے ساتھ کہنی کو پوری طرح سیدھا کرنے کی طرف بڑھیں۔
30 سیکنڈ روکیں، 3 بار، دن میں 2 سے 3 مرتبہ
Kieran Hirpara 4.0
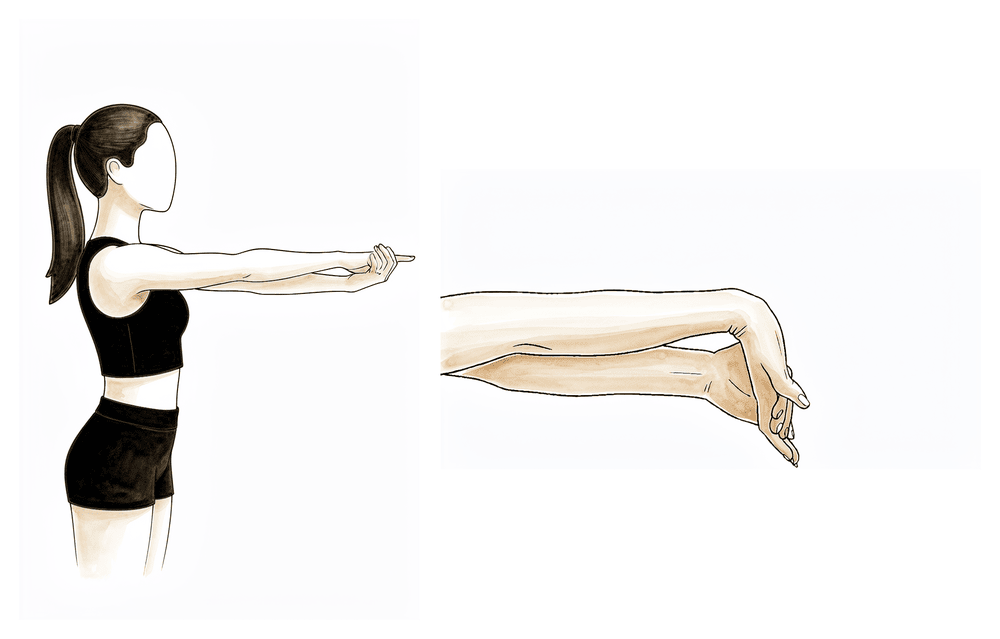
کلائی کو آگے موڑنے والے پٹھوں کا اسٹریچ
اپنا بازو سامنے کی طرف پھیلائیں، کہنی سیدھی ہو اور ہتھیلی اوپر کی طرف ہو۔ دوسرے ہاتھ سے انگلیوں اور کلائی کو ہلکے سے پیچھے اور نیچے کی طرف کھینچیں یہاں تک کہ آپ کو بازو کے نچلے حصے کی نچلی طرف آرام دہ کھنچاؤ محسوس ہو۔ کہنی سیدھی رکھیں۔
30 سیکنڈ روکیں، 3 بار، دن میں 2 سے 3 مرتبہ
Kieran Hirpara 4.0
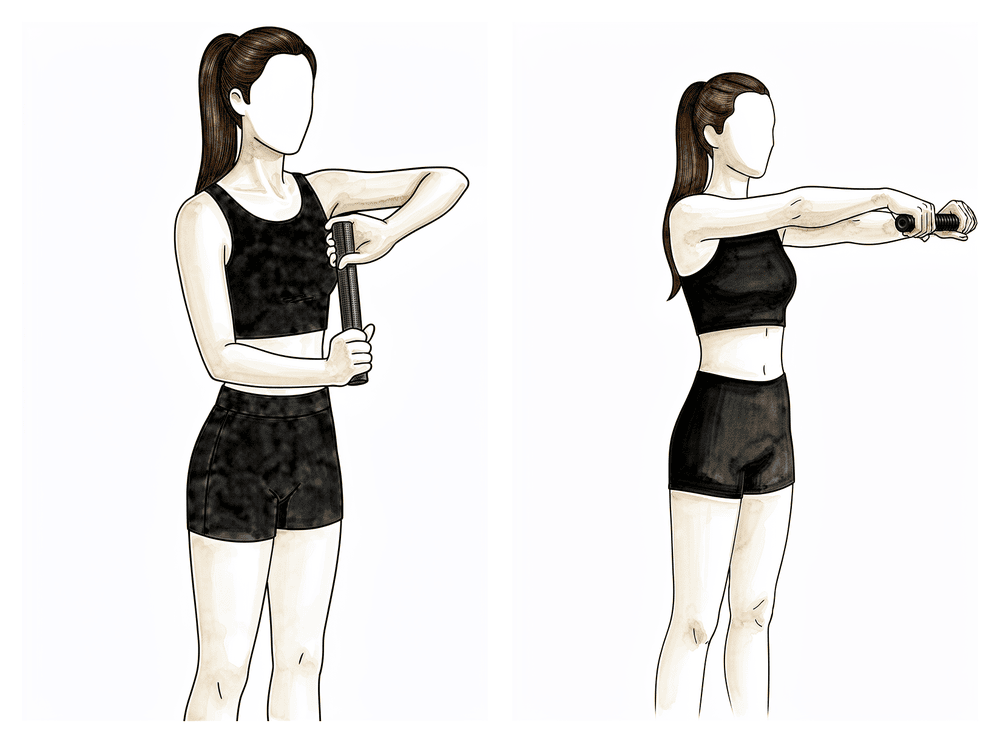
ٹائلر ٹوئسٹ (Tyler twist، کلائی کو ایکسینٹرک طریقے سے پیچھے موڑنا)
ایک لچکدار ربڑ کی سلاخ (FlexBar) اپنے دکھتے ہاتھ میں عمودی پکڑیں اور کلائی پیچھے کی طرف مڑی ہو۔ سلاخ کا اوپری حصہ اپنے دوسرے ہاتھ سے پکڑیں اور اسے مروڑیں۔ اب مروڑ برقرار رکھتے ہوئے سلاخ کو اپنے سامنے لائیں، اور اپنی دکھتی کلائی کو 3 سے 4 سیکنڈ میں قابو کے ساتھ آہستہ آہستہ کھلنے دیں — یہی آہستہ، قابو میں رکھا گیا نیچے آنا وہ حصہ ہے جو ٹینڈن کو مضبوط بناتا ہے۔ مروڑ کھلنے کے دوران محنت محسوس ہونی چاہیے، لیکن تیز درد نہیں۔ دوران ورزش اور بعد میں تھوڑی دیر ہلکا سا درد متوقع ہے اور ٹھیک ہے۔
15 کے 3 سیٹ، دن میں ایک بار (طاقت کی بنیادی ورزش)
Kieran Hirpara 4.0
بازو کے نچلے حصے کو گھمانا
اپنی کہنی پہلو کے ساتھ لگائیں اور اسے سیدھے زاویے (right angle) پر موڑیں۔ بازو کے نچلے حصے کو آہستہ سے گھمائیں تاکہ ہتھیلی اوپر کی طرف ہو، پھر اسے موڑیں تاکہ ہتھیلی نیچے کی طرف ہو، کہنی پہلو کے ساتھ ہی رہے۔ جب یہ آسان ہو جائے تو بوجھ بڑھانے کے لیے کوئی ہلکا وزن، جیسے ہتھوڑا یا ڈبہ، پکڑیں۔
ہر سمت میں 10 بار، دن میں 2 سے 3 مرتبہ؛ جب ہو سکے ہلکا وزن شامل کریں
Kieran Hirpara 4.0
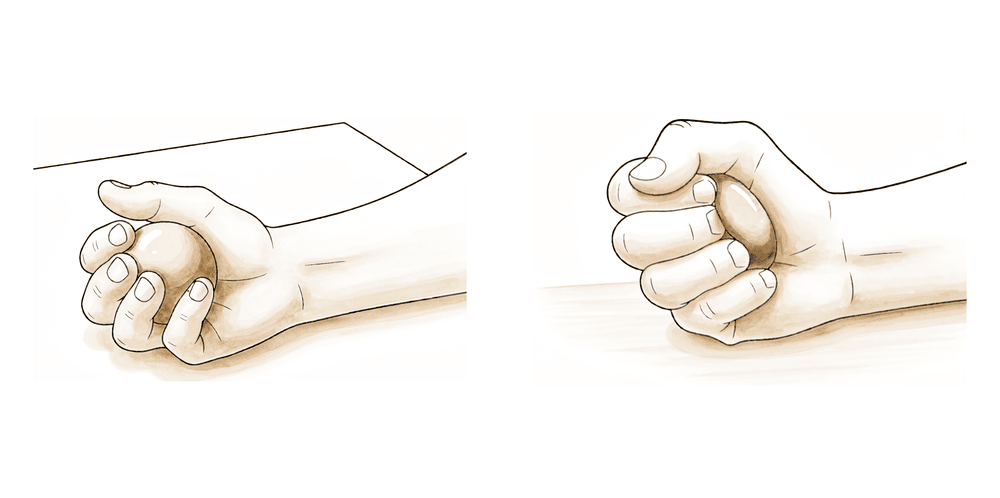
گرفت کی طاقت بڑھانا
ایک نرم گیند یا تھراپی پُٹی (therapy putty)، یعنی گوندھے ہوئے آٹے جیسا نرم مادہ، ہاتھ میں دبائیں، دباؤ کو تھوڑی دیر روکیں، پھر ڈھیلا چھوڑ دیں۔ جیسے جیسے آپ کا ٹینڈن زیادہ برداشت کرنے لگے، دباؤ کو آہستہ آہستہ بڑھائیں۔ اگر گرفت میں اب بھی بہت درد ہو تو بعد میں اور ہلکے سے شروع کریں — گرفت کی ورزش طاقت بڑھانے والے مرحلے کا حصہ ہے، جب ابتدائی جلن (irritation) ختم ہو چکی ہو۔
10 سے 15 بار دبائیں، دن میں 2 سے 3 مرتبہ؛ جتنا برداشت ہو دباؤ بڑھائیں
یہ آپ کے ہینڈ آؤٹ کی ورزشیں ہیں۔ یہ صحت یابی کی ترتیب کے مطابق ہیں: کاؤنٹر فورس بریس اور آئسومیٹرک طریقے سے روکنے والی ورزشیں شروع میں درد کم کرنے میں مدد کرتی ہیں، اسٹریچ بازو کے نچلے حصے کو لچکدار رکھتے ہیں، اور ٹائلر ٹوئسٹ، بازو کے نچلے حصے کو گھمانے اور گرفت کی ورزشیں ٹینڈن کو دوبارہ مضبوط بناتی ہیں۔ انہیں ڈاکٹر ہِرپرا اور اپنے تھراپسٹ کی ہدایت کے مطابق شروع کریں، اور یہ نہ سمجھیں کہ آپ کو پہلے دن سے سب ورزشیں کرنی ہیں؛ آپ کا تھراپسٹ بتائے گا کہ کن سے شروع کرنا ہے اور طاقت کی ورزشیں کب شامل کرنی ہیں۔
آپ کا کلینیکل پروٹوکول
اس صفحے کا باقی حصہ لیٹرل ایپی کونڈائلائٹس (ٹینس ایلبو) کے لیے کلینیکل بحالی کا پروٹوکول ہے۔ یہ حصہ آپ کے فزیوتھراپسٹ یا ہینڈ تھراپسٹ کو دینے کے لیے ہے، اور ہر مرحلہ آسان زبان میں اس وضاحت سے شروع ہوتا ہے کہ کیا ہو رہا ہے۔
پروٹوکول کے دو حصے ہیں: ایک سرجری کے بغیر علاج کا راستہ (non-operative pathway، جو عملاً ہر ایک کے لیے پہلا انتخاب ہے) اور ایک آپریشن کے بعد کا راستہ (post-operative pathway) اُن تھوڑے سے لوگوں کے لیے جن کا چھ ماہ یا اس سے زیادہ کے اچھے معیار کے قدامت پسند (سرجری کے بغیر) علاج کے ناکام ہونے کے بعد ای سی آر بی کی صفائی (ECRB debridement) کا آپریشن ہوتا ہے۔
سرجری کے بغیر علاج کا راستہ
بنیادی اصول ٹینڈن پر بتدریج بڑھتا بوجھ ہے، جس کی رہنمائی درد کرتا ہے۔ مقصد علامات کی مدت کو کم کرنا اور بوجھ برداشت کرنے کی صلاحیت بحال کرنا ہے، ٹینڈن کو آرام دینا نہیں۔
مرحلہ I — شدید مرحلہ / درد پر قابو (0 سے 2 ہفتے)
یہاں توجہ درد کم کرنے اور بغیر بوجھ کے حرکت بحال کرنے پر ہے۔ بازو کو باندھ کر بے حرکت نہیں کیا جاتا؛ یہ نسبتی آرام ہے، پلستر لگانا نہیں۔
آپ کے فزیوتھراپسٹ کے لیے:
- اہداف: درد کم کرنا؛ بغیر بوجھ کے مکمل فعال حرکت کی حد (AROM) بحال کرنا۔
- انتظام: سرگرمیوں میں تبدیلی، جوڑ کی حفاظت اور کام کرنے کے انداز (ergonomic) کے بارے میں مشورہ۔ اختیاری طور پر گرفت کے دوران ای سی آر بی کے شروع ہونے کی جگہ سے بوجھ ہٹانے کے لیے کامن ایکسٹینسر پٹھوں کے حصے پر کاؤنٹر فورس بریس؛ اگر کلائی کو پیچھے موڑنے والی سرگرمیوں میں شدید درد ہو تو کلائی کا (cock-up) اسپلنٹ استعمال کیا جا سکتا ہے۔ درد کم کرنے کے معاون طریقے: برف، نرم بافتوں / آلے کی مدد سے نرم بافتوں کی موبلائزیشن (IASTM)، ہلکی بے درد فعال حرکت (AROM)، اختیاری ڈرائی نیڈلنگ (dry needling)، اعصاب کو سرکانے کی ورزشیں (nerve glides)۔
- اگلے مرحلے میں جانے کے معیار: بغیر بوجھ کے مکمل فعال حرکت (AROM) بغیر درد کے؛ گھریلو پروگرام خود سے کر سکنا۔
مرحلہ II — نیم شدید مرحلہ / ابتدائی بوجھ (2 سے 4 ہفتے)
ٹینڈن پر بوجھ آہستہ سے شروع ہوتا ہے، اور بازو کے اوپری سلسلے (کندھے کی پچھلی چپٹی ہڈی اور روٹیٹر کف (rotator cuff)، یعنی ٹینڈنوں کا وہ گروپ جو کندھے کو تھامتا اور گھماتا ہے) پر بھی کام کیا جاتا ہے، کیونکہ بازو میں اوپر کی کمزوری کہنی پر زیادہ بوجھ کا سبب بنتی ہے۔
آپ کے فزیوتھراپسٹ کے لیے:
- اہداف: ٹینڈن پر بوجھ شروع کرنا؛ اوپر کے حرکی سلسلے (proximal kinetic chain) پر کام کرنا۔
- ورزشیں: کلائی کو پیچھے اور آگے موڑنے والے پٹھوں پر آئسومیٹرک بوجھ (ہلکا بوجھ؛ ری ایکٹو ٹینڈن کی خرابی (reactive tendinopathy) میں آئسومیٹرک ورزشیں اچھی طرح برداشت ہوتی ہیں اور درد کم کرتی ہیں)؛ کہنی 90 ڈگری پر رکھ کر کلائی کو آگے اور پیچھے موڑنے والے پٹھوں کے بتدریج اسٹریچ؛ اوپر کے حصے کا کام: سیریٹس اینٹیریئر (serratus anterior)، درمیانی / نچلا ٹریپیزیئس (trapezius)، روٹیٹر کف اور کندھے کی پچھلی چپٹی ہڈی کو مستحکم رکھنے والے پٹھے۔
- اگلے مرحلے میں جانے کے معیار: مکمل حرکت کی حد (ROM) برقرار؛ کہنی کو 90 ڈگری پر موڑ کر اسٹریچ برداشت کر سکنا؛ دوسرے بازو کی گرفت / طاقت کا تقریباً 70 فیصد۔
مرحلہ III — طاقت بڑھانا / واپسی (4 سے 6+ ہفتے، اکثر 12 ہفتوں تک)
اس مرحلے میں ٹینڈن دوبارہ مضبوط کیا جاتا ہے اور کام اور کھیل کے لیے بوجھ برداشت کرنے کی صلاحیت بحال کی جاتی ہے۔ ایکسینٹرک–کانسینٹرک (eccentric–concentric) بوجھ علاج کا بنیادی ذریعہ ہے۔
آپ کے فزیوتھراپسٹ کے لیے:
- اہداف: بوجھ برداشت کرنے اور کھیل / کام کی صلاحیت بحال کرنا۔
- ورزشیں: کلائی کو پیچھے موڑنے اور بازو کے نچلے حصے کو نیچے / اوپر گھمانے (pronation/supination) پر ایکسینٹرک–کانسینٹرک بوجھ؛ ٹائلر ٹوئسٹ (FlexBar) گھر پر ایکسینٹرک ورزش کا مثالی آلہ ہے۔ اسٹریچ کو کہنی سیدھی والی پوزیشن تک بڑھائیں؛ حرکت کے ساتھ موبلائزیشن (Mulligan)۔ گرفت کی طاقت اور کام / کھیل کے مطابق بوجھ؛ کھلاڑیوں کے لیے پلائیومیٹرک (plyometrics) ورزشیں۔ جیسے جیسے مریض کی علامات ختم ہوں، کاؤنٹر فورس بریس آہستہ آہستہ چھڑائیں۔ کھلاڑیوں کے سامان میں تبدیلی (گرفت کا سائز، تار کا کھنچاؤ، تکنیک)۔
- اگلے مرحلے میں جانے کے معیار (کھیل پر واپسی): دوسرے بازو کی طاقت کا تقریباً 90 فیصد، بے درد کارکردگی، اور خود سے انتظام کرنے کی صلاحیت۔
آپریشن کے بعد کا راستہ (ای سی آر بی کی صفائی، ریلیز کے ساتھ یا اس کے بغیر — ECRB debridement ± release)
سرجری اُن تقریباً 4 سے 11 فیصد لوگوں کے لیے رکھی جاتی ہے جن کا 6 ماہ یا اس سے زیادہ کا اچھے معیار کا قدامت پسند علاج ناکام رہے۔ کھلا نرشل (Nirschl) طرز کا ڈیبرائیڈمنٹ (صفائی) اور دوربین کے ذریعے ای سی آر بی کا ڈیبرائیڈمنٹ ملتے جلتے نتائج دیتے ہیں۔ نیچے دیا گیا ٹائم لائن لیٹرل ایپی کونڈائل کی صفائی کے لیے Brigham & Women's Standard of Care کے مطابق ہے۔
مرحلہ 1 — حفاظت (دن 1 سے 7)
پہلے ہفتے میں سلنگ صرف آرام کے لیے استعمال کی جاتی ہے۔
آپ کے فزیوتھراپسٹ کے لیے:
- آرام کے لیے سلنگ؛ برف 20 منٹ، دن میں 2 سے 3 مرتبہ؛ چیرے پر کہنی کا پیڈ۔
- ہاتھ، کلائی اور کہنی کی ہلکی بے درد فعال حرکت (AROM)؛ کندھے کی فعال حرکت (ROM)؛ کندھے کی پچھلی چپٹی ہڈی کے گرد پٹھوں کی ورزشیں۔
- روزمرہ کی ایسی سرگرمیاں (ADLs) کم سے کم کریں جو ایکسٹینسر نظام پر زور ڈالیں (اٹھانا، کہنی کو پوری طرح سیدھا کرنے کے ساتھ کلائی کو آگے موڑنا)؛ ایکسٹینسر پٹھوں سے بوجھ ہٹانے کے لیے ہتھیلی اوپر رکھ کر اٹھائیں؛ اگر شدید درد ہو تو اختیاری طور پر کلائی کا اسپلنٹ۔
مرحلہ 2 — ابتدائی حرکت (ہفتہ 2 سے 4)
آپ کے فزیوتھراپسٹ کے لیے:
- سلنگ بند کر دیں۔ درد کی برداشت کے اندر غیر فعال حرکت (PROM) اور فعال مدد والی حرکت شروع کریں۔
- ہلکی طاقت کی ورزشیں: فعال حرکت اور پوری طاقت سے کم زور والی آئسومیٹرک ورزشیں (sub-maximal isometrics)۔ زخم کے نشان کی دیکھ بھال شروع کریں۔
مرحلہ 3 — طاقت بڑھانا (ہفتہ 5 سے 7)
آپ کے فزیوتھراپسٹ کے لیے:
- مزاحمت والی طاقت کی ورزشیں آگے بڑھائیں (وزن / تھیرابینڈ، Theraband)، کلائی کو پیچھے موڑنے والے پٹھوں کی برداشت پر زور کے ساتھ (ہلکا بوجھ، زیادہ تکرار)۔ مکمل فعال اور غیر فعال حرکت (ROM) بحال کریں۔
- کامن ایکسٹینسر ٹینڈن پر کاؤنٹر فورس بریس شروع کریں (عصب کے دبنے سے بچنے کی ہدایت کے ساتھ)؛ ریشوں کے آر پار ہلکا مساج؛ روزمرہ کام کی تیاری شروع کریں۔
مرحلہ 4 — روزمرہ کارکردگی / واپسی (ہفتہ 8 سے 12)
آپ کے فزیوتھراپسٹ کے لیے:
- کام کے مطابق عملی تربیت؛ زیادہ محنت والے کام اور تفریحی سرگرمیوں پر واپسی۔
- بے درد روزمرہ سرگرمیوں (ADLs) اور طاقت کی ورزشوں کے لیے ضرورت کے مطابق کاؤنٹر فورس بریس جاری رکھیں۔
کام اور سرگرمیوں پر واپسی
اگر آپ ٹینس ایلبو کا علاج سرجری کے بغیر کر رہے ہیں تو کام سے چھٹی کی کوئی مقررہ مدت نہیں ہے؛ آپ پورے عرصے بازو استعمال کرتے رہ سکتے ہیں، سب سے بھاری گرفت اور اٹھانے والے کاموں میں تبدیلی کر کے اور انہیں کرنے کے لیے کاؤنٹر فورس بریس استعمال کر کے۔ حقیقت پسندانہ توقع یہ ہے کہ کہنی 6 سے 12 ماہ میں ٹھیک ہو جاتی ہے، اور زیادہ تر لوگ (80 سے 90 فیصد) ایک سال کے اندر بہتر ہو جاتے ہیں۔ یہ ٹینڈن کا آہستہ ٹھیک ہونے والا مسئلہ ہے، اس لیے پیش رفت دنوں میں نہیں بلکہ ہفتوں اور مہینوں میں ناپی جاتی ہے۔ بوجھ والے پروگرام پر قائم رہنا ہی آپ کو وہاں تک پہنچاتا ہے؛ راستے میں درد کا بھڑکنا عام بات ہے اور جب تک ہلکا سا درد اگلے دن تک ٹھیک ہو جائے، یہ پیچھے ہٹنا نہیں ہے۔
اگر آپ کی سرجری ہوئی ہے تو سلنگ پہلے ہفتے میں صرف آرام کے لیے ہے اور کہنی کے سنبھلنے پر چھوڑ دی جاتی ہے۔ طاقت کی ورزشیں ہفتہ 5 سے 7 کے دوران بڑھتی ہیں، اور زیادہ تر لوگ تقریباً ہفتہ 8 سے 12 تک کام اور تفریح پر عملی طور پر واپس آ جاتے ہیں۔ زیادہ بھاری اور کھیل سے متعلق سرگرمیاں اسی عرصے میں آہستہ آہستہ دوبارہ شروع کی جاتی ہیں، اس بات کو دیکھتے ہوئے کہ ٹینڈن بوجھ کو کیسے برداشت کرتا ہے۔
کھیل پر واپسی (دونوں راستوں میں) اس بات سے طے ہوتی ہے کہ آپ اپنے دوسرے بازو کی طاقت کے تقریباً 90 فیصد تک پہنچ جائیں، آپ کی کارکردگی بے درد ہو اور آپ خود انتظام کرنے کا اعتماد رکھتے ہوں، نہ کہ صرف کیلنڈر سے۔
آپ کے پروٹوکول کے بعد
یہ پروٹوکول کلینک کی صحت یابی سے متعلق عمومی ہدایات کے ساتھ کام کرتا ہے؛ دیکھیں آپریشن کے بعد درد پر قابو پانا اور، اگر آپ کی سرجری ہوئی ہے تو، زخم کی دیکھ بھال اور ہینڈ تھراپی کی بنیادی باتیں۔ اوپر دیا گیا مرحلہ وار منصوبہ ٹینس ایلبو کے بارے میں موجودہ بہترین شواہد کی عکاسی کرتا ہے (آرام کے بجائے ٹینڈن پر بتدریج بڑھتا بوجھ)، اور آپ کی آگے کی صحت یابی کی رہنمائی آپ کا فزیوتھراپسٹ یا ہینڈ تھراپسٹ ذاتی طور پر کرتا ہے، اس بات کے مطابق کہ آپ کی کہنی کیسے ترقی کر رہی ہے۔
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Lateral Epicondylitis (Tennis Elbow) — Non-operative & Post-operative Rehabilitation
Topic scope: (A) the natural history and stepped non-operative management of lateral epicondylitis (relative rest → progressive tendon loading: isometric → eccentric–concentric; counterforce bracing; controversies around corticosteroid and PRP injection), and (B) post-operative rehabilitation after open or arthroscopic ECRB debridement ± release, reserved for the minority who fail ≥6 months of quality conservative care.
Defining principle: despite the "-itis" suffix, lateral epicondylitis is a degenerative tendinopathy (tendinosis) of the extensor carpi radialis brevis (ECRB) origin, not an inflammatory condition. This reframes treatment away from rest and anti-inflammatory measures and toward progressive tendon loading — settle pain with isometrics, then rebuild load tolerance with eccentric–concentric loading (the Tyler twist / FlexBar). KH's stance: load the tendon, do not immobilise it; corticosteroid injection is avoided as first line because it is better short-term but worse at 6–12 months; surgery is a last resort after ≥6 months of genuine conservative care.
A. NATURAL HISTORY & NON-OPERATIVE MANAGEMENT
Natural history (self-limiting in most)
Lateral epicondylitis is self-limiting in the majority: roughly 80–90% resolve within about one year regardless of treatment, with the conservative literature ranging out to 12–18 months [Coonrad & Hooper 1973; Nirschl 1999]. This high spontaneous-resolution rate is the central methodological challenge of the field — any intervention must beat natural history, a high bar most fail to clear. The goal of therapy is therefore to shorten the symptomatic course and restore load tolerance, not to "cure" a condition that largely settles on its own.
Phased non-operative rehabilitation
First-line for essentially all comers. The therapeutic core is progressive tendon loading guided by pain.
Phase I — Acute / pain control (~0–2 weeks). Relative rest, NOT immobilisation — avoid full wrist/elbow casting (Nirschl). Activity modification, joint protection, ergonomics. Optional counterforce brace over the common extensor mass (offloads the ECRB origin during grip) ± a wrist cock-up splint if acutely painful. Adjuncts: ice, soft-tissue/IASTM, pain-free AROM, optional dry needling, nerve glides. Criterion to progress: full unloaded AROM without pain; independent with home program. Consensus / institutional protocol.
Phase II — Sub-acute / early loading (~2–4 weeks). Begin isometric wrist flexor/extensor loading (minimal load; isometrics are well tolerated and analgesic in reactive tendinopathy). Progressive stretching of wrist flexors/extensors with the elbow at 90°. Add proximal kinetic-chain work (serratus anterior, mid/lower trapezius, rotator cuff, scapular stabilisers — proximal deficits drive distal overload). Criteria to progress: full ROM maintained; tolerates stretch at 90° elbow flexion; ~70% contralateral grip/strength. Moderate (strengthening trials) / Consensus (timeline).
Phase III — Late / strengthening & return (~4–6+ weeks, often to 12 weeks). Eccentric–concentric loading of wrist extension and forearm pronation/supination is the core driver; the Tyler twist (FlexBar eccentric wrist-extension) is the prototypical home tool. Progress stretching to the elbow-extended position; add mobilisation-with-movement (Mulligan). Grip strengthening and task-/sport-specific loading; plyometrics for athletes. Gradually wean the counterforce brace as the patient becomes asymptomatic. Return-to-sport criteria: ~90% contralateral strength, pain-free function, self-management competence. Moderate–High (RCT/SR for exercise & loading) / Consensus (phase timings).
B. POST-OPERATIVE REHABILITATION (open or arthroscopic ECRB debridement ± release/repair)
Surgery is reserved for the ~4–11% who fail ≥6 months (commonly 6–12 months) of quality conservative care. Open Nirschl-type debridement and arthroscopic ECRB debridement give comparable complication and reoperation rates (national database, Arthroscopy 2022); arthroscopy additionally allows intra-articular inspection. The phased timeline below is the Brigham & Women's Standard of Care for lateral epicondyle debridement, cross-checked against community ECRB-release protocols.
| Phase | Window | Sling / support | Motion & strengthening | Notes |
|---|---|---|---|---|
| 1 — Protect | Days 1–7 | Sling for comfort; optional wrist splint if painful | Pain-free hand/wrist/elbow AROM; active shoulder ROM; periscapular work | Ice 20 min 2–3×/day; elbow pad over incision; lift palm-up to offload extensors |
| 2 — Early motion | Weeks 2–4 | Discontinue sling | PROM + active-assisted motion within pain tolerance; sub-maximal isometrics | Begin scar management |
| 3 — Strengthening | Weeks 5–7 | Introduce counterforce brace | Advance resistive strengthening (weights/Theraband); wrist-extensor endurance (light load, high rep); restore full A/PROM | Education to avoid nerve compression; cross-fibre massage |
| 4 — Functional / return | Weeks 8–12 | Counterforce brace as needed | Task-specific functional training; return to work/recreation | Functional return wk 8–12 |
Alternative published timelines (community ECRB-release protocols): wrist splint full-time 0–2 wk with no strengthening; full ROM goal by 4–6 wk; strengthening + transition to counterforce brace
6 wk; full activity ~8–10+ wk. Note: one comparative series found post-op bracing/immobilisation delayed symptom resolution versus PRP (mean time to full ROM 96 days surgery vs 42 days PRP) — reinforcing that early controlled motion, not protection, is the goal.
C. KEY CONTROVERSIES / EVIDENCE QUALITY
- Corticosteroid injection: better short-term, WORSE long-term. The Bisset/Smidt body of work (and the BMJ 2006 mobilisation-with-movement RCT) shows steroid gives early relief but higher recurrence and worse 6–12-month outcomes than physiotherapy or wait-and-see. Some authors now call it "always inadvisable" for lateral elbow (Orthop Trauma Surg Res 2019). Prior injection is associated with eventual surgery (a proxy for severity). Strong (Level-1 RCT).
- PRP / autologous blood: contested. Some Level-1 RCTs (Peerbooms 2010; Gosens 2-yr) show PRP superior to corticosteroid with ongoing 2-year benefit; others (Krogh 2013) found PRP ≈ glucocorticoid ≈ saline (no benefit over placebo). Meta-analyses are heterogeneous. Net: a reasonable second-line for refractory cases, but evidence is inconsistent. Conflicting (Level-1).
- Eccentric vs concentric vs isometric. Pure eccentric (Alfredson-style) is effective but not clearly superior; current view favours eccentric–concentric combined loading, with isometrics for early analgesia. Grip/isometric demands of the elbow differ from the Achilles, so blanket extrapolation of eccentric-only protocols is questioned. Moderate.
- Surgical indication/timing & technique. Reserve for failure of ≥6 months conservative care. Open vs arthroscopic debridement: no significant difference in complication or reoperation rates (national database, Arthroscopy 2022); choice is surgeon-/training-dependent. Repair after debridement vs debridement alone remains unsettled. Surgical incidence is declining, attributed to eccentric-exercise protocols and injections. Moderate.
- Self-limiting nature complicates all evidence: ~80–90% resolve within a year regardless of treatment, so any intervention must beat natural history. Strong (natural-history signal).
D. EVIDENCE STRENGTH FLAGS (summary)
- MODERATE–HIGH (RCT / SR): progressive loading (eccentric / eccentric–concentric) and exercise therapy for non-operative lateral epicondylitis; mobilisation-with-movement (BMJ 2006); the natural-history signal (~80–90% resolve within ~1 year).
- MODERATE (cohorts / database): post-operative ECRB debridement outcomes; equivalence of open vs arthroscopic debridement (no difference in complication/reoperation rates).
- CONSENSUS / institutional (Level-5): the phase timelines themselves derive from Standard-of-Care protocols (Brigham & Women's, Mass General Brigham, Campbell's/Nirschl) — broadly concordant across sources but not trial-derived.
- STRONG (against, Level-1): corticosteroid injection as first-line — better short-term, worse at 6–12 months.
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Bisset L et al. Mobilisation with movement and exercise, corticosteroid injection, or wait and see for tennis elbow: randomised trial. BMJ. 2006. DOI: 10.1136/bmj.38961.584653.AE
- Krogh TP et al. Treatment of lateral epicondylitis with platelet-rich plasma, glucocorticoid, or saline: a randomized, double-blind, placebo-controlled trial. Am J Sports Med. 2013. DOI: 10.1177/0363546512472975
- Peerbooms JC et al. Positive effect of an autologous platelet concentrate in lateral epicondylitis in a double-blind randomized controlled trial. Am J Sports Med. 2010. DOI: 10.1177/0363546509355445
- Gosens T et al. Ongoing positive effect of platelet-rich plasma versus corticosteroid injection in lateral epicondylitis: a double-blind randomized controlled trial with 2-year follow-up. Am J Sports Med. 2011. DOI: 10.1177/0363546510397173
- Ortega-Castillo M, Medina-Porqueres I. Effectiveness of the eccentric exercise therapy in physically active adults with symptomatic shoulder impingement or lateral epicondylar tendinopathy: a systematic review. J Sci Med Sport. 2016. DOI: 10.1016/j.jsams.2015.05.010
- Nirschl RP, Ashman ES. Elbow tendinopathy: tennis elbow. Clin Sports Med. 2003. (Current Concepts — Tendinosis of the Elbow, J Bone Joint Surg Am. 1999. DOI: 10.2106/00004623-199902000-00016)
- Coonrad RW, Hooper WR. Tennis elbow: its course, natural history, conservative and surgical management. J Bone Joint Surg Am. 1973. DOI: 10.2106/00004623-197355060-00002
- Lattermann C et al. Arthroscopic debridement of the extensor carpi radialis brevis for recalcitrant lateral epicondylitis. J Shoulder Elbow Surg. 2010. DOI: 10.1016/j.jse.2010.02.008
Lateral epicondylitis literature (URLs)
- Comparative efficacy and safety of nonsurgical treatment options for enthesopathy of the ECRB: a systematic review and meta-analysis of randomized trials. Am J Sports Med. 2018. https://pubmed.ncbi.nlm.nih.gov/29268037/
- Eccentric, eccentric–concentric, and eccentric–concentric + isometric training in lateral elbow tendinopathy. J Hand Ther. 2017. https://pubmed.ncbi.nlm.nih.gov/28732560/
- Role of strengthening during nonoperative treatment of lateral epicondyle tendinopathy. J Hand Ther. 2021. https://pubmed.ncbi.nlm.nih.gov/33041157/
- Chronic lateral elbow tendinopathy managed with a supervised graded exercise protocol. J Hand Ther. 2023. https://pubmed.ncbi.nlm.nih.gov/36127241/
- Management of lateral epicondylitis. Orthop Traumatol Surg Res. 2019. https://pubmed.ncbi.nlm.nih.gov/30414784/
- No difference in complication or reoperation rates between arthroscopic and open debridement for lateral epicondylitis: a national database study. Arthroscopy. 2022. https://pubmed.ncbi.nlm.nih.gov/34838651/
- Wang D et al. Trends in surgical practices for lateral epicondylitis among newly trained orthopaedic surgeons. Orthop J Sports Med. 2017. https://pubmed.ncbi.nlm.nih.gov/28840148/
- Factors associated with failure of nonoperative treatment in lateral epicondylitis. Am J Sports Med. 2015. https://pubmed.ncbi.nlm.nih.gov/26015443/
Published rehab protocols (patient-guidance — basis for the phase structure)
- Brigham & Women's Hospital — Post-Op Protocol for Lateral Epicondyle Debridement. https://www.brighamandwomens.org/assets/bwh/patients-and-families/rehabilitation-services/pdfs/elbow-lateral-epicondyle-debridement-postoperative-bwh.pdf
- Mass General Brigham Sports Medicine — Rehabilitation Protocol for Medial/Lateral Epicondylitis (non-operative), rev. April 2021. https://www.massgeneral.org/assets/MGH/pdf/orthopaedics/sports-medicine/physical-therapy/rehabilitation-protocol-for-medial-lateral-epicondylitis.pdf
- Beacon Orthopaedics — Lateral Epicondylitis ECRB Surgical Release Protocol. https://www.beaconortho.com/wp-content/uploads/Lateral-Epicondylitis-Release.pdf