Patients › Hand
انگلی کے درمیانی جوڑ (PIP joint) کا آرتھرائٹس
Osteoarthritis and inflammatory arthritis of the PIP joint — non-operative and surgical options.
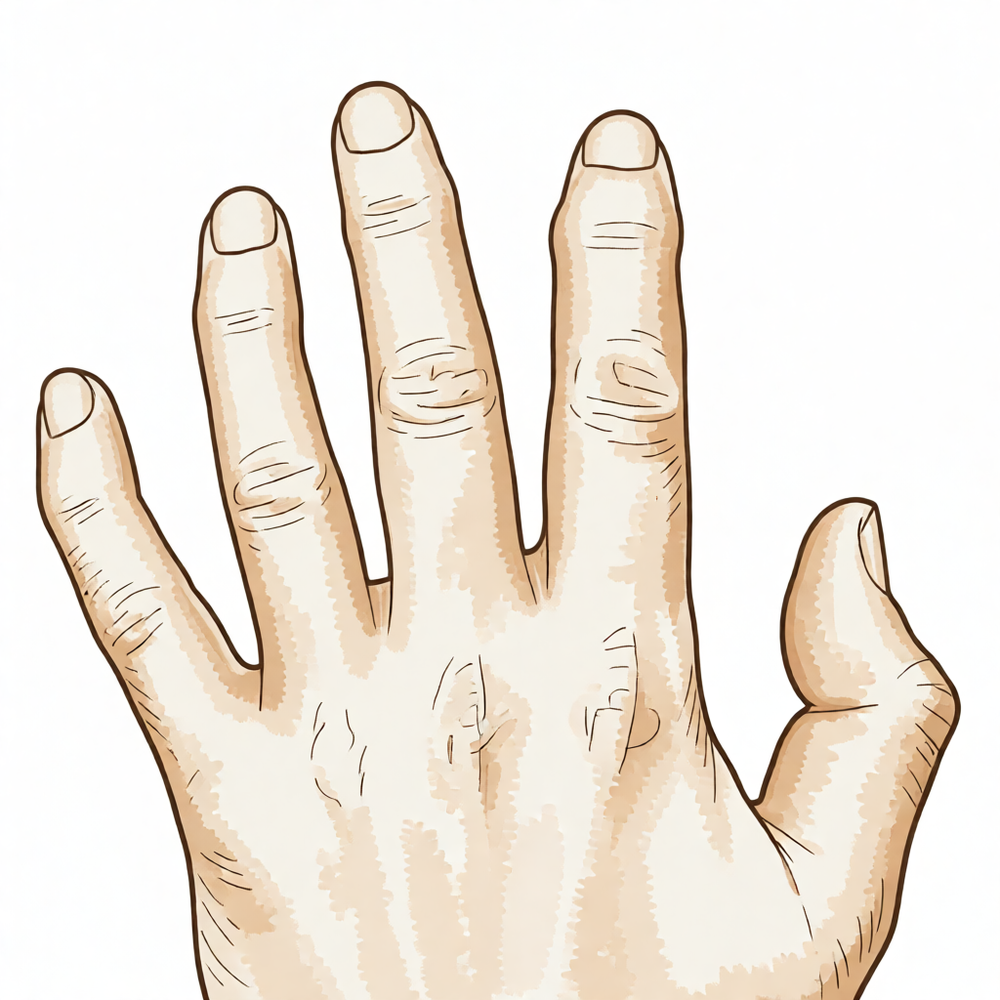
آپ کو کیا محسوس ہوتا ہے
آپ کی انگلی کے درمیان والا جوڑ (وہ جوڑ جسے آپ مٹھی بناتے وقت موڑتے ہیں) دردناک، اکڑا ہوا اور کبھی کبھی سوجا ہوا ہو جاتا ہے۔ درد عموماً دکھن کی صورت میں ہوتا ہے، جو جوڑ کے سامنے اور پیچھے دونوں طرف محسوس ہوتا ہے۔ یہ اکثر انگلی ہلانے پر بڑھ جاتا ہے، خاص طور پر جب آپ اسے کسی مزاحمت کے خلاف سیدھا کرتے ہیں۔ بعض اوقات یہ دکھن اوپر آپ کی انگلی کی جڑ کے جوڑ (knuckle) کی طرف پھیل جاتی ہے۔ جوڑ کو دبانے سے اس میں چھونے پر درد ہو سکتا ہے۔
روزمرہ کے وہ کام مشکل ہو جاتے ہیں جن میں چٹکی سے پکڑنا یا گرفت کرنا پڑتا ہے۔ انگوٹھے سے چٹکی بھرنے پر شہادت کی انگلی کے جوڑ پر ایک طرف سے زور پڑتا ہے، اس لیے بٹن، چابیاں اور چھوٹی چیزیں اٹھانا تکلیف دہ ہو سکتا ہے۔ انگلی ایک طرف کو ہٹ سکتی ہے یا ٹیڑھی رہ سکتی ہے، اور ہو سکتا ہے یہ پوری طرح نہ مڑے یا سیدھی نہ ہو۔ سوجن اور اکڑاؤ لمبے عرصے تک رہ سکتے ہیں، خاص طور پر اگر ماضی میں جوڑ کو چوٹ لگی ہو، جیسے موچ آنے یا جوڑ کے اپنی جگہ سے نکل جانے (dislocation) کے بعد۔
علامات ہمیشہ ایک ہی طرح نہیں بڑھتیں۔ بہت سے لوگ پاتے ہیں کہ آرتھرائٹس (جوڑ کی خرابی اور سوزش) کے آخری مراحل میں ان کی علامات شروع کے مقابلے میں کم ہوتی ہیں۔ اگر سادہ علاج کے تین ماہ یا اس سے زیادہ عرصے بعد بھی درد، اکڑاؤ یا ٹیڑھی انگلی ٹھیک نہ ہو تو عموماً اسی مرحلے پر سرجری پر غور کیا جاتا ہے۔
اگر آپ کی انگلی، ہاتھ یا بازو گرم، سرخ، سوجا ہوا اور دردناک ہو جائے، خاص طور پر بخار کے ساتھ، تو اسی دن ہسپتال کی ایمرجنسی جائیں۔ اگر آپ کی انگلی سفید پڑ جائے، ٹھنڈی ہو جائے، یا اس کا رنگ سفید یا نیلا ہو جائے، یا چوٹ کے بعد اچانک اس میں احساس یا حرکت ختم ہو جائے، تو اسی دن ہسپتال کی ایمرجنسی جائیں۔ اگر آپ کی علامات کم نہ ہو رہی ہوں، ہفتوں میں بڑھ رہی ہوں، آپ کو رات کو جگا دیں، یا آپ کو کام کرنے یا ہاتھ استعمال کرنے سے روک دیں، تو اپنے فیملی ڈاکٹر (GP) کو دکھائیں یا ماہر ڈاکٹر (specialist) سے معائنے کا کہیں۔
دراصل کیا ہو رہا ہے
آپ کی انگلی میں تین ہڈیاں ہوتی ہیں، اور درد والی جگہ درمیانی جوڑ ہے، جسے پی آئی پی جوڑ (PIP joint) کہتے ہیں۔ یہ ایک سادہ قبضہ (hinge) ہے۔ یہ صرف ایک ہی سمت میں مڑتا اور سیدھا ہوتا ہے، جیسے اچھی طرح تیل دیے ہوئے قبضوں پر لگا دروازہ۔ صحت مند حالت میں ہڈیوں کے سرے ایک دوسرے میں اچھی طرح بیٹھ جاتے ہیں، جس سے انگلی سیدھی ہونے پر جوڑ مستحکم رہتا ہے۔
ہر ہڈی کے سرے پر ایک چکنی، پھسلواں تہہ چڑھی ہوتی ہے جسے کارٹلیج (cartilage) کہتے ہیں۔ اسے ٹائر کی اوپری ربڑ کی تہہ (tread)، یا دو ہڈیوں کے درمیان جھٹکا جذب کرنے والی چیز سمجھیں۔ آرتھرائٹس میں یہ تہہ گھس جاتی ہے۔ پھر ہڈیوں کے سرے پھسلنے کے بجائے ایک دوسرے پر رگڑ کھاتے ہیں۔ جسم اس کے جواب میں جوڑ کے کناروں کے گرد اضافی ہڈی بنا لیتا ہے، اور جوڑ کی اندرونی جھلی موٹی ہو جاتی ہے۔ یہی رگڑ اور موٹا پن دکھن، سوجن اور رگڑ کا وہ احساس پیدا کرتے ہیں جو آپ محسوس کر سکتے ہیں۔
جوڑ مضبوط پٹیوں میں بھی لپٹا ہوتا ہے جنہیں لیگامنٹ (ligament) کہتے ہیں، اور یہ دونوں ہڈیوں کو ایک سیدھ میں رکھتی ہیں، کچھ ویسے ہی جیسے رسیاں خیمے کو تھامے رکھتی ہیں۔ آرتھرائٹس اور پرانی چوٹیں ان پٹیوں کو کھینچ دیتی ہیں اور ان میں زخم بھرنے سے بننے والا سخت ریشہ (scar tissue) پیدا کر دیتی ہیں۔ جب یہ ڈھیلی ہو جاتی ہیں تو انگلی ایک طرف کو ہٹ سکتی ہے یا ٹیڑھی رہ سکتی ہے، اور جوڑ غیر مستحکم محسوس ہو سکتا ہے۔ اس کے بعد اکڑاؤ آتا ہے، کیونکہ جب دردناک جوڑ حرکت نہیں کرتا تو لیگامنٹ اور جوڑ کی جھلی (capsule) کا یہی غلاف سخت ہو جاتا ہے۔
یہاں پرانی چوٹ اہمیت رکھتی ہے۔ موچ آنے یا جوڑ کے اپنی جگہ سے نکل جانے کے بعد اس جوڑ میں دیرپا مسائل پیدا ہونے کا امکان رہتا ہے۔ اس کے آس پاس کی چوٹوں کا نتیجہ تقریباً 30 فیصد کیسوں میں اچھا نہیں رہتا، اور جوڑ کا ڈھیلا پن (instability)، درد، اکڑاؤ یا ایسی انگلی رہ جاتی ہے جو پوری طرح سیدھی نہ ہو۔ اس طرح کا نقصان آرتھرائٹس کو اس سے پہلے بھی شروع کر سکتا ہے جتنا صرف گھساؤ سے ہوتا۔
ایک خاص صورت جاننے کے لائق ہے۔ اگر درمیانی جوڑ کو سیدھا کرنے والی پٹی کمزور ہو جائے تو انگلی درمیانی جوڑ پر مڑ جاتی ہے جبکہ آخری جوڑ الٹی سمت میں پیچھے کی طرف مڑ جاتا ہے۔ ڈاکٹر اسے بوٹونیئر ڈیفارمیٹی (boutonniere deformity) کہتے ہیں۔ شروع میں آپ خود انگلی کو سیدھا کر سکتے ہیں اور ہاتھ کا کام بہت کم متاثر ہوتا ہے۔ بعد میں سختی جم جاتی ہے اور انگلی سیدھی نہیں ہوتی، حتیٰ کہ جب کوئی دوسرا شخص اسے آپ کے لیے حرکت دینے کی کوشش کرے۔
ہم اس کے لیے کیا کر سکتے ہیں
ڈاکٹر کیرن ہِرپرا، جو Mater Private Hospital Rockhampton میں بازو اور ہاتھ کے سرجن (upper-limb surgeon) ہیں، سب سے کم مداخلت والے ان طریقوں سے آغاز کرتے ہیں جو آپ کی حالت کے لیے مناسب ہوں۔ مریض عام طور پر اپنے فیملی ڈاکٹر (GP) کے بھیجنے پر ہمارے کلینک آتے ہیں؛ اگر کسی فزیوتھراپسٹ نے آپ کو ہمیں دکھانے کا مشورہ دیا ہے، تب بھی میڈیکیئر (Medicare) کی رقم واپسی کا حق دار ہونے کے لیے آپ کو اپنے فیملی ڈاکٹر سے ریفرل (referral) لینا ہوگا۔ پہلی ملاقات میں ہم آپ سے تکلیف کی تفصیل لیتے ہیں، آپ کی انگلی کا معائنہ کرتے ہیں، اور ضرورت ہو تو ایکسرے کرواتے ہیں۔ اس طرح کے پرانے مسئلے میں ہم عموماً پہلے بغیر آپریشن کے علاج آزماتے ہیں اور سرجری پر اس وقت غور کرتے ہیں جب اس سے کافی بہتری نہ آئی ہو۔
پہلے قدم وہ ہیں جو آپ خود کر سکتے ہیں۔ ہاتھ استعمال کرنے کا طریقہ بدلنا، تاکہ آپ مختلف انداز سے چٹکی سے پکڑیں اور گرفت کریں، دردناک جوڑ سے بوجھ ہٹا دیتا ہے۔ ہینڈ تھراپی (ہاتھ کی بحالی کا علاج) کا مقصد جوڑ کو حرکت میں رکھنا اور آپ کی گرفت کو کام کرتے رکھنا ہے۔ اسپلنٹ یا پلستر انگلی کو زیادہ سیدھا رکھ سکتا ہے؛ کچھ لوگوں میں مرحلہ وار پلستر (serial casting)، جس میں پلستر کو مرحلوں میں بدلا جاتا ہے، مڑی ہوئی حالت میں اکڑ جانے والی انگلی کو درست کر سکتا ہے۔ ان اقدامات کے بارے میں رائے قائم کرنے سے پہلے انہیں کم از کم 3 ماہ دیں۔
درد کش گولیاں اور سوزش کم کرنے والی دوا، اگر اپنے فیملی ڈاکٹر کے مشورے کے مطابق لی جائیں، دکھن کو اتنا کم کر سکتی ہیں کہ آپ ہاتھ استعمال کرتے رہیں۔ ہم اس جوڑ کے لیے انجکشن استعمال نہیں کرتے۔
اگر 3 ماہ بعد بھی سادہ علاج سے فائدہ نہ ہوا ہو، اور ایکسرے پر آرتھرائٹس نظر آئے اور ساتھ میں درد بھی جاری ہو، تو سرجری ایک اختیار بن جاتی ہے۔ دو بنیادی آپریشن یہ ہیں: جوڑ کی جگہ امپلانٹ (جسم میں لگایا گیا مصنوعی پرزہ) لگانا، جس سے کچھ حرکت باقی رہتی ہے، یا جوڑ کا فیوژن (دو ہڈیوں کو جوڑ کر ایک کر دینا)، جو جوڑ کی حرکت کو مکمل طور پر روک کر درد ختم کر دیتا ہے۔ آپ کے لیے کون سا مناسب ہے، یہ خود جوڑ پر منحصر ہے: کیا وہ مستحکم ہے، کون سی انگلی ہے، اور آپ کو اپنے ہاتھ سے کیا کام لینا ہے۔ ہم آپ کے ساتھ مل کر اس انتخاب پر بات کریں گے۔ کسی بھی آپریشن سے پہلے ہم جانچتے ہیں کہ جوڑ کے گرد کے ٹینڈن (tendon)، یعنی وہ مضبوط ڈوریاں جو پٹھے کو ہڈی سے جوڑتی ہیں، سلامت ہیں اور جوڑ میں ابھی کچھ استحکام باقی ہے، کیونکہ جوڑ کی تبدیلی کے لیے دونوں ضروری ہیں۔ بہت ٹیڑھی انگلی، یعنی جو ایک طرف 30 ڈگری سے زیادہ ہٹی ہوئی ہو، جوڑ کی تبدیلی سے درست کرنا مشکل ہے اور اس میں ناکامی کا امکان زیادہ ہے۔
کیا توقع رکھیں
اس جوڑ کا آرتھرائٹس عموماً خود بخود ختم نہیں ہوتا۔ دکھن اور اکڑاؤ عموماً برقرار رہتے ہیں، اور سادہ علاج انہیں ختم کرنے کے بجائے کم کرتا ہے۔ بہت سے لوگ پاتے ہیں کہ برسوں کے ساتھ ان کی علامات کم ہو جاتی ہیں، لیکن جوڑ شاذ و نادر ہی پہلے جیسا ہو پاتا ہے۔
علاج کے بغیر آگے کی صورتحال اس پر منحصر ہے کہ مسئلے کی وجہ کیا ہے۔ موچ یا جوڑ کے اپنی جگہ سے نکل جانے جیسی پرانی چوٹ کے بعد اچھا نتیجہ نہ آنا عام ہے: مسلسل درد، اکڑاؤ، جوڑ کا ڈھیلا پن، یا ایسی انگلی جو پوری طرح سیدھی نہ ہو۔ اکڑی ہوئی، مڑی ہوئی انگلی کو کبھی کبھی اسپلنٹ یا مرحلہ وار پلستر سے درست کیا جا سکتا ہے، جس میں پلستر کو مرحلوں میں بدلا جاتا ہے۔ جوڑ کو حرکت میں رکھنا ضروری ہے، کیونکہ جو دردناک جوڑ استعمال نہ ہو وہ مزید اکڑ جاتا ہے۔
علاج سے زیادہ تر لوگوں کو اتنا آرام مل جاتا ہے کہ وہ اپنا ہاتھ استعمال کرتے رہیں۔ بغیر آپریشن کے علاج کو کم از کم 3 ماہ کا پورا موقع دیا جائے تو بہت سے لوگوں کی علامات کم ہو جاتی ہیں۔ جہاں سرجری کی ضرورت ہو، وہاں دونوں اختیارات کے نتائج کی ایک حقیقت پسندانہ تصویر ہے۔ جوڑ کی تبدیلی درد سے آرام دیتی ہے اور کچھ حرکت باقی رکھتی ہے، لیکن وقت کے ساتھ حرکت کم ہو سکتی ہے، اور اس جوڑ کی تبدیلی کے بعد مزید آپریشن عام ہیں۔ جوڑ کا فیوژن قابلِ اعتماد طور پر درد ختم کر دیتا ہے، لیکن اس کی قیمت اس انگلی کی ساری حرکت ہے۔ اگر جوڑ کی تبدیلی ناکام ہو جائے تو اسے سنبھالنے کا عام طریقہ جوڑ کا فیوژن ہے۔
صحت یابی تیز نہیں بلکہ بتدریج ہوتی ہے۔ اس جوڑ کی چوٹ یا سرجری کے بعد آرام دہ حرکت اور گرفت دوبارہ حاصل کرنا واقعی مشکل ہے، اور پیش رفت مہینوں میں ناپی جاتی ہے۔ سرجری کے بعد ہینڈ تھراپی Extend Rehabilitation میں Ruby Doolan کے ساتھ ہوتی ہے؛ وہ آپ کی تھراپی کی رہنمائی کرتی ہیں اور آپ کو جس اسپلنٹ کی بھی ضرورت ہو وہ بناتی ہیں۔ کچھ لوگ پاتے ہیں کہ انگلی کے بہتر سیدھا ہونے سے ہاتھ کا کام اتنا آسان نہیں ہوتا جتنی انہیں امید تھی، اور علاج شروع ہونے سے پہلے یہ جاننا مفید ہے۔
ڈاکٹر کو کب دکھائیں
اگر آپ کی انگلی دردناک، اکڑی ہوئی یا ٹیڑھی ہو اور ہینڈ تھراپی، اسپلنٹ یا دوا جیسے سادہ علاج کے 3 ماہ یا اس سے زیادہ عرصے بعد بھی ٹھیک نہ ہوئی ہو تو اپنے فیملی ڈاکٹر کو دکھائیں یا ماہر ڈاکٹر سے معائنے کا کہیں۔ اگر علامات ہفتوں میں بڑھ رہی ہوں، آپ کو رات کو جگا دیں، یا آپ کو کام کرنے یا ہاتھ استعمال کرنے سے روک دیں، تو اس سے پہلے ہی دکھائیں۔ اس جوڑ میں موچ آنے یا اس کے اپنی جگہ سے نکل جانے کے بعد بلا تاخیر معائنہ کروائیں، کیونکہ سوجن، اکڑاؤ اور کام کی صلاحیت میں کمی لمبے عرصے تک رہ سکتی ہے، اور فریکچر (ہڈی کا ٹوٹنا) کے ساتھ جوڑ کے نکل جانے (fracture-dislocation) سے مستقل ٹیڑھا پن جلد پیدا ہو سکتا ہے۔ اگر آپ کی انگلی، ہاتھ یا بازو گرم، سرخ، سوجا ہوا اور دردناک ہو جائے، خاص طور پر بخار کے ساتھ، تو اسی دن ہسپتال کی ایمرجنسی جائیں۔ اگر آپ کی انگلی سفید پڑ جائے، ٹھنڈی ہو جائے، یا اس کا رنگ سفید یا نیلا ہو جائے، یا چوٹ کے بعد اچانک اس میں احساس یا حرکت ختم ہو جائے تو اسی دن جائیں۔
مزید تفصیل
Advanced reading: the deeper science (optional)
یہ حصہ اس سے زیادہ تفصیل میں جاتا ہے جتنی آپ کو اپنے علاج کے فیصلوں کے لیے ضرورت ہے۔ انگلی کے درمیانی جوڑ کے آرتھرائٹس کے بارے میں اضافی مطالعہ اس لیے فائدہ مند ہے کہ جوڑ کا فیوژن کرنے یا اسے بدلنے کے درمیان انتخاب ایک ایسی چیز سے طے ہوتا ہے جس کے بارے میں زیادہ تر لوگ پوچھنے کا سوچتے بھی نہیں، یعنی یہ کہ جوڑ مستحکم ہے یا نہیں، اور اس لیے بھی کہ کون سی انگلی ہے، یہ اتنا ہی اہم ہے جتنا یہ کہ ایکسرے کیا دکھاتا ہے۔
آپریشن کا انتخاب شدت نہیں بلکہ استحکام طے کرتا ہے
دو آپریشن دستیاب ہیں۔ فیوژن جوڑ کو ایک منتخب حالت میں مستقل طور پر جوڑ دیتا ہے، اور ساری حرکت کی قیمت پر قابلِ اعتماد طریقے سے درد ختم کر دیتا ہے۔ جوڑ کی تبدیلی حرکت کو برقرار رکھتی ہے۔
1,868 مریضوں پر مشتمل موازنہ یہ طے کرتا ہے کہ ہر ایک کب مناسب ہے۔ مستحکم جوڑوں کے لیے سلیکون امپلانٹ اب بھی ایک قیمتی انتخاب ہیں، جبکہ سطح بدلنے والے امپلانٹ غیر مستحکم یا ایک طرف کو مڑے ہوئے جوڑوں کے لیے بہتر ہو سکتے ہیں، اگرچہ ان میں دوبارہ آپریشن کا خطرہ زیادہ ہوتا ہے [1]۔
یہاں اہم متغیر استحکام ہے۔ سلیکون امپلانٹ قبضہ نہیں بلکہ ایک لچکدار درمیانی ٹکڑا (spacer) ہے؛ یہ ہڈیوں کے سروں کے درمیان بیٹھ کر انہیں اپنے گرد حرکت کرنے دیتا ہے، جس کے لیے ضروری ہے کہ اردگرد کے لیگامنٹ (ligament)، یعنی وہ مضبوط بندھن جو ایک ہڈی کو دوسری ہڈی سے جوڑتا ہے، استحکام فراہم کریں۔ جہاں یہ لیگامنٹ ناکام ہو چکے ہوں اور جوڑ ایک طرف کو مڑ جائے، وہاں درمیانی ٹکڑے کے پاس سہارے کے لیے کچھ نہیں ہوتا، اسی لیے سطح بدلنے والے ڈیزائن کی طرف رجوع کیا جاتا ہے، اور اسی لیے زیادہ جکڑے ہوئے امپلانٹ کے ساتھ دوبارہ آپریشن کی شرح بھی زیادہ ہوتی ہے۔
کون سی انگلی ہے، اس سے مشورہ بدل جاتا ہے
یہ وہ حصہ ہے جو شاذ و نادر ہی سمجھایا جاتا ہے۔ شہادت کی انگلی چٹکی کی گرفت میں انگوٹھے سے دبتے ہوئے ایک بڑی آڑی قوت سہتی ہے، اور یہی قوت ہے جسے بدلا ہوا جوڑ سب سے کم برداشت کرتا ہے۔ انگوٹھی والی انگلی اور چھوٹی انگلی زیادہ تر گرفت کے لیے استعمال ہوتی ہیں، جہاں بوجھ انگلی کے آر پار نہیں بلکہ اس کی لمبائی کے رخ پڑتا ہے۔
اس کا عملی نتیجہ یہ ہے کہ جوڑ کی تبدیلی عموماً چھوٹی انگلی والی طرف کی انگلیوں (ulnar fingers) کے لیے زیادہ موزوں ہے، اور شہادت کی انگلی میں اکثر فیوژن کو ترجیح دی جاتی ہے، جہاں چٹکی کے لیے ایک مستحکم ستون حرکت سے زیادہ قیمتی ہے۔ اس لیے ایکسرے پر ایک جیسے نظر آنے والے دو جوڑوں کے لیے صرف ہاتھ میں ان کی جگہ کی بنیاد پر مختلف مشورے دیے جا سکتے ہیں۔
فیوژن قابلِ اعتماد ہے، اور طریقہ توقع سے کم اہم ہے
جہاں فیوژن کا انتخاب کیا جائے، وہاں طریقے پر بحث محدود ہے۔ 1,923 مریضوں میں، بیان کیے گئے تمام طریقے جوڑ کے گھسنے والے آرتھرائٹس (osteoarthritis) والے جوڑ کو جوڑنے کا مقصد حاصل کر سکتے ہیں، اور حالیہ تحقیقی تحریروں میں دباؤ ڈال کر جوڑنے والے طریقوں (compression techniques) کی طرف رجحان ہے [2]۔ 286 مریضوں میں طریقوں کا براہِ راست موازنہ کرنے پر ان میں جڑنے کا وقت، ہڈیوں کا نہ جڑنا (nonunion) اور پیچیدگیوں کی شرحیں ملتی جلتی تھیں، البتہ پیچ سے فیوژن میں تار سے فیوژن کے مقابلے میں ہڈیوں کے نہ جڑنے کی شرح کم تھی، اگرچہ اس ڈیٹا کی نمایاں حدود ہیں [3]۔
جہاں جوڑ گھساؤ کے بجائے چوٹ سے تباہ ہوا ہو
درمیانی ہڈی کی بنیاد سے گزرنے والا فریکچر (ہڈی کا ٹوٹنا) براہِ راست جوڑ کی سطح کو تباہ کر دیتا ہے۔ جہاں آدھی سے زیادہ سطح متاثر ہو، وہاں ایک راستہ یہ ہے کہ کلائی کی ہیمیٹ ہڈی (hamate) سے لیے گئے ٹکڑے (graft) سے اسے دوبارہ بنایا جائے، جس کی بناوٹ کھوئی ہوئی جوڑ کی سطح سے ملتی جلتی ہے۔
ہیمی ہیمیٹ آٹوگرافٹ (hemi-hamate autograft، مریض کی اپنی ہیمیٹ ہڈی سے لیا گیا ٹکڑا) ان تازہ اور پرانی فریکچر اور جوڑ نکلنے کی چوٹوں (fracture-dislocations) کے لیے قابلِ اعتماد سمجھا جا سکتا ہے جن میں جوڑ کا 50 فیصد سے زیادہ حصہ متاثر ہو، اگرچہ طویل مدتی فالو اپ کی ضرورت ہے، خاص طور پر بعد میں ہونے والے آرتھرائٹس کی شرح جاننے کے لیے [4]۔ 235 مریضوں کے ایک الگ جائزے میں پایا گیا کہ اس سے علامات میں آرام ملتا ہے اور ہاتھ کا کام بحال ہوتا ہے [5]۔
بعد کے آرتھرائٹس کے بارے میں یہ باقی سوال ہی دیانت دارانہ احتیاط ہے: گرافٹ جوڑ کی شکل بحال کر دیتا ہے، لیکن یہ ابھی معلوم نہیں کہ دوبارہ بنائی گئی سطح قدرتی سطح کی رفتار سے ہی گھستی ہے یا نہیں۔
حوالہ جات
[1] Forster N, Schindele S, Audigé L, Marks M. Complications, reoperations and revisions after proximal interphalangeal joint arthroplasty: a systematic review. J Hand Surg Eur Vol. 2018;43(10):1066-75. https://doi.org/10.1177/1753193418770606
[2] Millrose M, Gesslein M, Ittermann T, Kim S, Vonderlind H, Ruettermann M. Arthrodesis of the proximal interphalangeal joint of the finger, a systematic review. EFORT Open Rev. 2022;7(1):49-58. https://doi.org/10.1530/EOR-21-0102
[3] Faulkner H, An V, Lawson RD, Graham DJ, Sivakumar BS. Proximal interphalangeal joint arthrodesis techniques: a systematic review. Hand (N Y). 2021;18(1):74-9. https://doi.org/10.1177/1558944721998019
[4] Frueh FS, Calcagni M, Lindenblatt N. The hemi-hamate autograft arthroplasty in proximal interphalangeal joint reconstruction: a systematic review. J Hand Surg Eur Vol. 2014;40(1):24-32. https://doi.org/10.1177/1753193414554356
[5] Faulkner H, Graham DJ, Hile M, Lawson RD, Sivakumar BS. Hemi-hamate arthroplasty for base of middle phalanx fracture: a systematic review. Hand (N Y). 2021;18(2):300-6. https://doi.org/10.1177/15589447211014623
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Reoperations following primary nonconstrained PIP joint arthroplasties are common [1].
- Extensor mechanism dysfunction is the most frequent cause of reoperation following primary nonconstrained PIP joint arthroplasties [1].
- Maintaining motion and function following trauma and/or surgery of the PIP joint remains very challenging [2].
- PIPJ arthrodesis has very few contraindications [3].
- PIPJ arthrodesis has an excellent overall success rate [3].
- PIPJ arthrodesis is an excellent option for surgical management of PIPJ arthritis [3].
- Clinical outcomes for PIP joint replacements with pyrocarbon implants are variable [4].
- PIP joint replacements with pyrocarbon implants have substantially good survivorship [4].
- Complications regularly arise after PIP joint injuries [5].
- Complications after PIP joint injuries can often be prevented through early detection of injury and appropriate initial treatment protocols [5].
- Ultimate salvage for the failed PIP joint arthroplasty may require arthrodesis [6].
- Ultimate salvage for the failed PIP joint arthroplasty may require amputation [6].
- Primary PIPA utilization for patients with OA has increased [7].
- Revision PIPA utilization has decreased [7].
- Surgery performed better than collagenase at early and 2-year follow-up in PIP joints [8].
- Reoperations following primary non-constrained PIP arthroplasties are common [9].
- Initial reports of PIP joint surface replacement implants are encouraging [10].
- Component loosening typical of earlier designs has not been a problem to date for new-generation PIP joint surface replacement implants [10].
- The reoperation rate after pyrocarbon PIP arthroplasty was 30% [11].
- Pyrocarbon PIPJ replacement is a safe and effective treatment for arthritis of the PIPJ [12].
- Pyrocarbon PIPJ replacement provides excellent pain relief [12].
- Pyrocarbon PIPJ replacement increases the arc of motion by more than double the preoperative range [12].
- PIP joint denervation provides durable, effective pain relief [13].
- PIP joint denervation has high patient satisfaction [13].
- PIP joint denervation remains effective despite osteoarthritis progression [13].
- PIP joint denervation supports its consideration as a surgical option for symptomatic PIP joint osteoarthritis [13].
- PIPJ implant arthroplasty is a good and reliable option for symptomatic PIPJ degenerative, post-traumatic or inflammatory arthritis given the proper clinical setting [14].
- It proposes the best surgical approach for a given surgery on the PIP joint based on pearls and pitfalls [15].
- Patients returned to work after a median of 8 weeks following PIP arthroplasty [16].
- Intraoperative fractures occur in about 5% of PIP joint arthroplasties [21].
- Intraoperative fractures do not appear to influence outcomes, including revision surgery, refracture rate, or other early complications [21].
- Periprosthetic joint infection is uncommon after PIP arthroplasties [22].
- The CapFlex-PIP implant demonstrates favourable medium-term results in surface replacing arthroplasty of the proximal interphalangeal joint [23].
- Various techniques for PIP joint arthrodesis can achieve good functional results [24].
- No optimal procedure for PIP joint arthrodesis has yet been found due to the diversity of available methods [24].
- Treatment of the long finger may be a relative contraindication to PIPJ arthroplasty [26].
- The survival of pyrocarbon PIP joint arthroplasty was 85% at 5 years of follow-up [27].
- Pyrocarbon PIP joint arthroplasty has high patient satisfaction [27].
- The available PIPJ arthrodesis techniques have similar fusion time outcomes [61].
- The available PIPJ arthrodesis techniques have similar nonunion rate outcomes [61].
- The available PIPJ arthrodesis techniques have similar complication rate outcomes [61].
Anatomy & Pathophysiology
Joint Mechanics and Stability
- The proximal interphalangeal (PIP) joint is a simple hinge joint that allows for motion in the flexion-extension axis only [35].
- In full extension, PIP joint stability is maintained by the highly congruent bony architecture [35].
- In flexion, the capsuloligamentous structures that envelope the PIP joint maintain stability [35].
- The capsuloligamentous structures of the PIP joint include the dorsal capsule, volar plate, and collateral ligaments [35].
- Unlike the metacarpophalangeal (MCP) joint, the PIP joint's capsuloligamentous structures are essentially isometric throughout the arc of motion [35].
- The PIP joint has unique anatomy that predisposes it to stiffness [35].
- The position of the PIP joint depends on the equilibrium of forces acting at that level, which is subject to the position of the immediately proximal articulation [74].
- The metacarpophalangeal joint affects the position of the proximal interphalangeal joint [74].
- Single articular movements around a fixed perpendicular axis simply do not exist in the hand [74].
- Almost all movements in the hand are around oblique and variable axes, resulting in combined movements permitting optimal orientation of the phalanges at the time of prehension [74].
Soft Tissue Anatomy and Extensor Mechanism
- The principal bony insertion of the extrinsic digital extensors is on the dorsal proximal aspect of the middle phalanx [46].
- Distal interphalangeal joint extension is achieved through the conjoined lateral bands, which are composed of tendinous slips from the extrinsic and intrinsic tendons [46].
- The deep head of each dorsal interosseous muscle forms a lateral tendon, or lateral band, at the level of the MCP joint [66].
- The deep head of the dorsal interosseous muscle flexes and weakly abducts the proximal phalanx while extending the middle and distal phalanges [66].
- Oblique fibers (spiral fibers) from the lateral bands sweep over the distal third of the proximal phalanx to insert onto the lateral tubercles at the base of the middle phalanx [66].
- The oblique fibers extend the middle phalanx at the PIP joint [66].
- The lateral bands are joined by the lateral slips of the extensor tendon to form the conjoined lateral band [66].
- The two conjoined lateral bands to each finger unite at the distal third of the middle phalanx to form the terminal tendon [66].
- The terminal tendon inserts at the base of the distal phalanx to extend it [66].
- The volar interossei form the ulnar lateral band of the index finger and the radial lateral band of the ring and little fingers [66].
- The volar interossei send oblique or spiral fibers that insert onto the base of the middle phalanx at its lateral tubercle [66].
- The flexor digitorum superficialis tendon bifurcates around the flexor digitorum profundus at the beginning of the A2 pulley [73].
- The flexor digitorum superficialis tendon inserts via radial and ulnar slips into the proximal metaphysis of the middle phalanx [73].
- The primary function of the flexor digitorum superficialis is digital flexion at the proximal interphalangeal joint [73].
- The flexor digitorum profundus provides digital flexion at both the proximal and distal interphalangeal joints [73].
- The A3 annular pulley is located over the proximal interphalangeal joint [73].
Pathophysiology of Arthritis and Stiffness
- Proximal interphalangeal joint arthritides are broadly categorized into nonerosive and erosive osteoarthritis (OA), posttraumatic arthritis, and inflammatory arthritis [58].
- Idiopathic or primary OA occurs as a consequence of abnormal mechanical stress that leads to damage of cartilage and subchondral bone, with subsequent cytokine and growth factor activation [58].
- Individual genetics mediate the cellular responses in idiopathic or primary OA [58].
- Erosive OA is described as a separate entity, but this remains controversial, with many suggesting that it is merely a more aggressive form of nonerosive, primary OA [58].
- Inflammatory OA occurs when connective tissues are diseased, allowing for normal use to incite arthritic damage [58].
- The initial phase of PIP joint osteoarthritis is an inflammatory process that comes to a halt at a later stage [18].
- Many patients have fewer symptoms at the end stage of PIP joint osteoarthritis than at the beginning [18].
- Radiographs and symptoms do not correlate in PIP joint osteoarthritis [18].
- The pathogenesis of the PIP joint contracture is attributed to a cycle of edema, immobilization, and tissue adherence of the capsuloligamentous structures [35].
- PIP joint stiffness may be the result of both traumatic and atraumatic conditions, such as Dupuytren disease, infection, and neurological injury [35].
- PIP joint stiffness remains an unsolved problem in hand surgery, with poor prognosis in complex cases even after complete arthrolysis and tenolysis [31].
- Inappropriate management of PIP joint injuries may result in chronic pain, stiffness, deformity, or premature degenerative arthritis [33].
- An extensive review of 96 injuries about the PIP joint found a 30% poor recovery rate, as characterized by joint instability, poor function, pain, or flexion deformities [33].
- Suboptimal treatment of intra-articular fractures typically leads to functional impairment of the hand [51].
- Chronic unreduced dislocations of the proximal interphalangeal joint are uncommon [17].
- Closed reduction of chronic PIP joint dislocations is rarely successful owing to soft tissue contractures [17].
- A functional range of motion with a stable joint can be achieved in chronic PIP dislocations as long as articular cartilage is relatively preserved [17].
- Various injury patterns for PIP joint dislocation have been described from hyperextension to rotational torque injuries [17].
- Different combinations of structures are injured in PIP dislocations based on mechanism, including collateral ligaments, volar plate, and the central slip of the extensor mechanism [17].
- Dorsal dislocations represent almost all PIP joint dislocations [118].
- Dorsal PIP dislocations are characterized by forced hyperextension, axial load, and radial or ulnar deviation [118].
- Dorsal PIP dislocations involve volar plate rupture at its distal attachment [118].
- Dorsal PIP dislocations involve a split between the accessory collateral ligament and proper collateral ligament with detachment of the proper collateral ligament from its proximal attachment [118].
- In dorsal PIP dislocations, the volar plate is maintained beneath the condyle, held by intact attachment to the accessory collateral ligament [118].
- When a torsional mechanism is involved in dorsal PIP dislocations, soft tissue interposition can block reduction [118].
- Lateral PIP dislocations are less common and characterized by direct radial or ulnar stress on the PIP joint with axial load [118].
- In lateral PIP dislocations, the collateral ligament on the side of the force fails under tension, avulsing from its proximal attachment [118].
- Continued force in lateral PIP dislocations causes disruption of the volar plate on the side of the force [118].
- Volar PIP dislocations are the least common and may involve a rotatory component [118].
- Volar PIP dislocation requires force in two vectors: ulnar or radial deviation causing rupture of the collateral ligament and volar plate [118].
- In uncomplicated dorsal PIP dislocations, the central slip of the extensor mechanism ruptures or avulses from the dorsal lip of the middle phalanx [116].
- The intact lateral bands initially can perform joint extension even though the central slip is ruptured in dorsal PIP dislocations [116].
- Failure to immobilize the joint in extension to allow central slip healing can eventually lead to stretching of the triangular ligament holding the lateral bands [116].
- Subluxated lateral bands can no longer extend the PIP joint, and the tightening of the terminal extensor slip leads to hyperextension of the distal interphalangeal (DIP) joint, resulting in the classic boutonniere deformity [116].
- Complex volar PIP dislocations involve rotary displacement with a collateral ligament tear secondary to lateral stress combined with an anteriorly directed force [116].
- In complicated volar PIP dislocations, the central slip, lateral band, or torn collateral ligament may be interposed within the joint, thereby necessitating open reduction [116].
- Open dislocations are predominantly dorsal dislocations of the index and middle fingers [101].
- Restoration of stability allowing early motion and a smooth articular surface are the goals of treatment for dorsal fracture-dislocations of the PIP joint [110].
- Percent articular involvement and relative fragment displacement are objective measurements that can help characterize joint stability and assist with decision-making in PIP joint injuries [25].
- Proper biomechanics of a joint must be restored to achieve full, functional range of motion [80].
- Despite the wealth of knowledge regarding the anatomy of the PIP joint, it remains a subject of ongoing investigation, and evolving understanding of its biomechanical properties will continue to improve treatment and reconstructive designs [81].
Classification
- The diagnosis of PIP joint osteoarthritis is based mainly on the clinical picture and confirmed by radiographs [18].
- Radiographs and symptoms do not correlate, which is the main reason that classifications and staging based on radiographs are rarely used [18].
- Radiographic evaluation of bone quality, specifically defects and cyst formation, plays a crucial role in the indication of possible surgical treatment options [18].
- The presence of stiffness and deformity plays a crucial role in the indication of possible surgical treatment options [18].
- The SCARF classification allows non-hand specialists to specify the type of every PIP joint dislocation and understand each case [50].
- Treatment of PIP joint fracture dislocations is based on joint stability, fracture fragment size, and soft tissue injuries [34].
- Percent articular involvement and relative fragment displacement are objective measurements that can help characterize joint stability and assist with decision-making [25].
- A classification of injuries about the PIP joint has been suggested to provide a practical guide to management [33].
Clinical Presentation
Diagnosis and Radiographic Findings
- The diagnosis of osteoarthritis of the PIP joint is based mainly on the clinical picture and confirmed by radiographs [18].
- The index PIP joint is often deviated to the ulnar side due to mechanical forces in pinching with the thumb [18].
Disease Course and Symptoms
- Many patients have fewer symptoms at the end stage of the disease than at the beginning [18].
- It is common for patients to experience a prolonged duration of swelling, stiffness, and dysfunction following PIP joint sprains [19].
- Proximal interphalangeal joint pain in trigger finger patients results from long symptom duration and consequent joint pathology [28].
- PIP joint pain in trigger finger patients is incompletely resolved after A1 pulley release, leading to worse surgical outcomes than expected [28].
- Patients with pre-existing PIP tenderness should be informed about the possibility of sustaining residual minor pain for up to 3 months after surgery [55].
Functional Impairment and Stiffness
- Arthritis of the PIP joint can lead to considerable hand impairment [58].
- Small perturbations in hand function can have substantial effects on an individual's quality of life, including vocational activities, avocational activities, financial stability, and psychosocial health [58].
- PIP joint stiffness remains an unsolved problem in hand surgery [31].
- The prognosis for PIP joint stiffness is poor in complex cases even after complete arthrolysis and tenolysis [31].
- A review of 96 injuries about the PIP joint found a 30% poor recovery rate, characterized by joint instability, poor function, pain, or flexion deformities [33].
- Clinical results for PIP joint dislocations and fracture-dislocations vary and are often difficult to predict due to the complexity of fracture patterns and potential for sub-acute or chronic presentation [37].
- Fracture dislocations of the PIP joint may rapidly develop fixed deformity, leaving a patient with a poor outlook for complete correction [52].
- The association of persistent subluxation and early arthrosis in dorsal PIP joint fracture dislocations needs further study [57].
Investigations
- A careful physical examination is essential to direct care and future testing if indicated [45].
- Diagnostic tests such as imaging and serum laboratory studies are useful in determining pathology but can be expensive, time consuming, and often nonspecific [45].
- Early recognition of joint instability is essential for adequate treatment of injuries of the PIP joint [29].
- Timely diagnosis is imperative, especially if there is any persistent incongruity of the joint, as fracture dislocations of the PIP joint may rapidly develop fixed deformity [52].
- An 8-MHz Doppler tone assessment may be used to identify superficially displaced neurovascular bundles when Dupuytren cords lie beneath soft fleshy prominences [79].
- MRI is probably most useful in identifying additional pathology such as flexor tendon bowstringing [79].
- MRI may be helpful in providing a quantitative noninvasive measure of cellularity of affected areas, which is an index of biologic activity [79].
Treatment
Arthroplasty
- Reoperations following primary nonconstrained PIP joint arthroplasties are common, with extensor mechanism dysfunction being the most frequent cause [1].
- Clinical outcomes for PIP joint replacements with pyrocarbon implants are variable despite substantially good survivorship [4].
- Pyrocarbon PIPJ replacement provides excellent pain relief and increases the arc of motion by more than double the preoperative range [12].
- The survival of pyrocarbon PIP joint arthroplasty was 85% at 5 years of follow-up, with high patient satisfaction [27].
- The Ascension pyrocarbon PIP joint replacement is an effective and reliable treatment for the painful, mobile arthritic PIP joint, maintaining useful motion and providing effective pain relief [40].
- Implant arthroplasty of the PIP, MCP, and TMC joints predictably produces pain relief and high satisfaction but has historically suffered from high rates of complications [59].
- Patients should be advised that PIPJ ROM deteriorates over time following arthroplasty [20].
- Pre-requisites for PIP joint arthroplasty are intact tendons and at least some residual joint stability [92].
- Corrections of a lateral deviation beyond 30° are difficult and likely to fail in PIP arthroplasty [92].
- The data demonstrate an increased use of primary PIPA utilization for patients with OA, whereas revision PIPA decreased [7].
- Initial reports of PIP and MCP joint surface replacement implants are encouraging, particularly because component loosening typical of earlier designs has not been a problem to date [10].
Arthrodesis
- PIPJ arthrodesis has very few contraindications, with an excellent overall success rate, making it an excellent option for surgical management of PIPJ arthritis [3].
- Ultimate salvage for the failed PIP joint arthroplasty may require arthrodesis or even amputation [6].
- While various techniques for PIP joint arthrodesis can achieve good functional results, no optimal procedure has yet been found due to the diversity of available methods [24].
- The available PIPJ arthrodesis techniques have similar fusion time, nonunion rate, and complication rate outcomes [61].
- Results suggest that the angles suggested by Murray (2016) are too flexed and that most patients prefer a PIPJ arthrodesis in more extension [56].
Denervation
- PIP joint denervation provides durable, effective pain relief with high patient satisfaction, despite osteoarthritis progression, supporting its consideration as a surgical option for symptomatic PIP joint osteoarthritis [13].
Non-Operative and Adjunctive
- The addition of a PIPJ extension orthosis in the presence of traumatic PIPJ fixed flexion deformities is more effective for improving PIPJ extension than hand therapy alone [63].
- Collagenase clostridium histolyticum treatment is effective for isolated or combined PIP joint contractures [104].
- Surgery performed better than collagenase at early and 2-year follow-up in PIP joints and similarly in MCP joints [8].
- Clinical success (0 to 5 of full extension) occurred in 27% of PIP joints after one injection and in 34% after the last injection for collagenase treatment of Dupuytren contracture [43].
- Range of motion for all 644 joints increased from 51 to 71 and 75 after first and last collagenase injections, respectively [43].
- A logical sequential approach to releasing PIP joint contractures in Dupuytren's disease, prioritizing gentle passive manipulation and less aggressive surgeries, yields better results than aggressive interventions [120].
Rehabilitation and Postoperative Care
- The postoperative rehabilitation protocol for PIP arthroplasty includes a dynamic PIP extension-assist splint worn during the day limiting ROM to 0° to 30° of extension-flexion for the first week [53].
- A static resting splint is worn at night and during rest periods, with the MCP joint in 20° of flexion and the PIP and DIP joints maintained in full extension [53].
- All exercises in the dynamic splint should be done hourly with ten repetitions [53].
- When hyperextension of the PIP joint is present, an extension block can be added to block the PIP joint at 30° or more of flexion, with a night static flexion block at 60° to 90° for 3 weeks [53].
- Patients with RA will require individual assessment of preoperative deformity and may require up to 3 weeks of immobilization before initiation of therapy in order to provide for softtissue repair healing to ensure a stable joint [53].
- Complications regularly arise after PIP joint injuries, yet they can often be prevented through early detection of injury and appropriate initial treatment protocols [5].
Complications
Arthroplasty Complications
- Intraoperative fractures in PIP joint arthroplasty do not appear to influence outcomes, including revision surgery, refracture rate, or other early complications [21].
- The revision rate for the LPM PIPJ prosthesis was 29% at a maximum follow-up of 6 years [39].
- An additional 20% rate of adverse clinical and radiological outcomes was observed for the LPM PIPJ prosthesis at a maximum follow-up of 6 years [39].
- Patients should be advised that PIPJ range of motion deteriorates over time following arthroplasty [20].
- Multi-digit PIP joint arthroplasty performed during a single operation resulted in 7% intraoperative fractures, 1% postoperative fractures, and 3% infections [62].
- Multi-digit PIP joint arthroplasty performed on two or more different dates resulted in 12% intraoperative fractures, 2% postoperative fractures, and 4% infections [62].
- Ultimate salvage for a failed PIP joint arthroplasty may require arthrodesis or amputation [6].
Injury and Non-Arthroplasty Complications
- A review of 96 PIP joint injuries found a 30% poor recovery rate characterized by joint instability, poor function, pain, or flexion deformities [33].
- Proximal interphalangeal joint pain in trigger finger patients is incompletely resolved after A1 pulley release [28].
- Incomplete resolution of PIP joint pain after A1 pulley release leads to worse surgical outcomes than expected [28].
Recovery
Postoperative Rehabilitation and Splinting
- Postoperative therapy for PIP joint arthroplasty typically begins 1 week after surgery [53].
- A dynamic PIP extension-assist splint is worn during the day and limits range of motion to 0° to 30° of extension-flexion for the first week [53].
- A static resting splint is worn at night and during rest periods, maintaining the MCP joint in 20° of flexion and the PIP and DIP joints in full extension [53].
- Exercises in the dynamic splint are performed hourly with ten repetitions [53].
- Hyperextension and extension lag must be avoided, with therapy or splinting adjusted immediately if either is present [53].
- If PIP joint hyperextension is present, an extension block can be added to block the joint at 30° or more of flexion [53].
- When hyperextension is managed with an extension block, a night static flexion block at 60° to 90° is applied for 3 weeks [53].
- After the 3-week period of hyperextension management, dynamic extension is reinstituted to zero [53].
- Patients with rheumatoid arthritis may require up to 3 weeks of immobilization before initiating therapy to allow for soft tissue repair healing [53].
Functional Outcomes and Return to Work
- Pyrocarbon PIP joint replacement increases the arc of motion by more than double the preoperative range [12].
- PIP joint range of motion deteriorates over time following pyrolytic carbon hemiarthroplasty [20].
- PIP joint denervation provides durable, effective pain relief with high patient satisfaction despite osteoarthritis progression [13].
Complications and Reoperations
- Ultimate salvage for a failed PIP joint arthroplasty may require arthrodesis or even amputation [6].
- Complications regularly arise after PIP joint injuries but can often be prevented through early detection and appropriate initial treatment protocols [5].
Implant-Specific Recovery Data
- The survival of the MatOrtho proximal interphalangeal joint arthroplasty was 85% at a minimum of 2-years follow-up [94].
- The revision rate of the LPM PIPJ prosthesis was 29% at a maximum follow-up of 6 years [39].
- In a 10-year prospective study of pyrocarbon PIP prostheses, 10 joints in 10 patients required further operations during the follow-up period [44].
- Two patients in the 10-year pyrocarbon PIP cohort had the prosthesis extracted and underwent joint arthrodesis because of persisting pain [44].
- One patient in the 10-year pyrocarbon PIP cohort with rheumatoid arthritis and a previous PIP synovectomy developed skin necrosis and infection, leading to prosthesis extraction after 2 weeks [44].
- Three patients in the 10-year pyrocarbon PIP cohort had limited range of motion and underwent tenolysis and/or arthrolysis [44].
- Two patients in the 10-year pyrocarbon PIP cohort developed hyperextension of the PIP joint with painful snapping and were treated by a Littler tendonplasty [44].
Key Evidence
- [L4] Reoperations following primary nonconstrained PIP joint arthroplasties are common, with extensor mechanism dysfunction being the most frequent cause. [1] (10.1016/j.jhsa.2011.06.002)
- [L5] Maintaining motion and function following trauma and/or surgery of the PIP joint remains very challenging. [2] (10.1016/j.hcl.2017.12.003)
- [L5] PIPJ arthrodesis has very few contraindications, with an excellent overall success rate, making it an excellent option for surgical management of PIPJ arthritis. [3] (10.1016/j.hcl.2017.12.007)
- [L4] Despite substantially good survivorship, clinical outcomes for PIP joint replacements with pyrocarbon implants are variable. [4] (10.1302/2058-5241.2.160041)
- [L5] Complications regularly arise after PIP joint injuries, yet they can often be prevented through early detection of injury and appropriate initial treatment protocols. [5] (10.1016/j.hcl.2017.12.014)
- [L5] Ultimate salvage for the failed PIP joint arthroplasty may require arthrodesis or even amputation. [6] (10.1016/j.hcl.2017.12.011)
- [L4] The data demonstrate an increased use of primary PIPA utilization for patients with OA, whereas revision PIPA decreased. [7] (10.1177/1558944719837009)
- [L3] Surgery performed better than collagenase at early and 2-year follow-up in PIP joints and similarly in MCP joints. [8] (10.1007/s00402-018-3034-6)
- [L4] Reoperations following primary non-constrained PIP arthroplasties are common. [9] (10.1016/s0363-5023(11)60049-x)
- [L5] Initial reports of PIP and MCP joint surface replacement implants are encouraging, particularly because component loosening typical of earlier designs has not been a problem to date. [10] (10.5435/00124635-200309000-00002)
- [Paper] The reoperation rate after pyrocarbon PIP arthroplasty was 30%. [11] (10.1055/s-0040-1709088)
- [L4] Pyrocarbon PIPJ replacement is a safe and effective treatment for arthritis of the PIPJ, providing excellent pain relief and increasing the arc of motion by more than double the preoperative range. [12] (10.1177/1753193411434053)
- [L4] PIP joint denervation provides durable, effective pain relief with high patient satisfaction, despite osteoarthritis progression, supporting its consideration as a surgical option for symptomatic PIP joint osteoarthritis. [13] (10.1016/j.jhsa.2026.01.033)
- [L4] PIPJ implant arthroplasty is a good and reliable option for symptomatic PIPJ degenerative, post-traumatic or inflammatory arthritis given the proper clinical setting. [14] (10.1177/17531934241265837)
- [L5] It proposes the best surgical approach for a given surgery on the PIP joint based on pearls and pitfalls. [15] (10.1016/j.jhsa.2015.11.013)
- [L3] Patients returned to work after a median of 8 weeks following PIP arthroplasty. [16] (10.1177/15589447221141485)
- [L4] [17] (10.1016/j.jhsa.2020.07.002)
- [L5] [18] (10.1016/j.hcl.2017.04.002)
- [L4] It is common for patients to experience a prolonged duration of swelling, stiffness, and dysfunction following PIP joint sprains. [19] (10.1016/j.jhsa.2023.01.025)
- [L4] Patients should be advised that PIPJ ROM deteriorates over time. [20] (10.1016/j.jhsa.2023.11.007)
- [L3] Intraoperative fractures occur in about 5% of PIP joint arthroplasties and do not appear to influence outcomes, including revision surgery, refracture rate, or other early complications. [21] (10.1016/j.jhsa.2015.06.101)
- [L4] PJI is uncommon after MCP or PIP arthroplasties. [22] (10.1016/j.jhsa.2024.12.008)
- [L4] The CapFlex-PIP implant demonstrates favourable medium-term results in surface replacing arthroplasty of the proximal interphalangeal joint. [23] (10.1177/1753193420977244)
- [Paper] The review concludes that while various techniques for PIP joint arthrodesis can achieve good functional results, no optimal procedure has yet been found due to the diversity of available methods. [24] (10.1055/a-0833-8729)
- [L3] Percent articular involvement and relative fragment displacement are objective measurements that can help characterize joint stability and assist with decision-making. [25] (10.1177/1558944719895621)
- [L1] Treatment of the long finger may be a relative contraindication to PIPJ arthroplasty. [26] (10.1177/1558944718791186)
- [L4] The survival of pyrocarbon PIP joint arthroplasty was 85% at 5 years of follow-up, with high patient satisfaction. [27] (10.1016/j.jhsa.2012.02.012)
- [L4] Proximal interphalangeal joint pain in trigger finger patients results from long symptom duration and consequent joint pathology, and is incompletely resolved after A1 pulley release, leading to worse surgical outcomes than expected. [28] (10.1177/1753193418809771)
- [L5] Early recognition of joint instability is essential for adequate treatment of injuries of the PIP joint. [29] (10.5435/00124635-200011000-00006)
- [L5] PIP joint stiffness remains an unsolved problem in hand surgery, with poor prognosis in complex cases even after complete arthrolysis and tenolysis. [31] (10.1177/17531934221143690)
- [L5] [33] (10.1016/j.hcl.2006.05.003)
- [L5] This article serves as a reference for the current understanding and best practices in treating PIP joint fracture dislocations, emphasizing that treatment is based on joint stability, fracture fragment size, and soft tissue injuries. [34] (10.1016/j.hcl.2017.12.005)
- [L5] [35] (10.1016/j.jhsa.2015.06.118)
- [L5] Clinical results for PIP joint dislocations and fracture-dislocations vary and are often difficult to predict due to the complexity of fracture patterns and potential for sub-acute or chronic presentation. [37] (10.1177/17531934231183259)
- [L4] The revision rate of 29% and a further 20% rate of adverse clinical and radiological outcomes for the LPM PIPJ prosthesis at a maximum follow-up of 6 years is unacceptable. [39] (10.1177/1753193408094920)
- [L4] The Ascension pyrocarbon PIP joint replacement is an effective and reliable treatment for the painful, mobile arthritic PIP joint, maintaining useful motion and providing effective pain relief. [40] (10.1177/1753193414566552)
- [L2] [43] (10.1016/j.jhsa.2015.02.018)
- [L4] [44] (10.1177/1753193413479527)
- [L2] Even other than hand specialists can specify the type of every PIP joint dislocation by using the SCARF classification and will have better understanding of each case. [50] (10.1016/j.jos.2019.08.007)
- [L5] Suboptimal treatment of intra-articular fractures typically leads to functional impairment of the hand. [51] (10.1177/1753193414559464)
- [L5] Timely diagnosis is imperative, especially if there is any persistent incongruity of the joint, as fracture dislocations of the PIP joint may rapidly develop fixed deformity, leaving an athlete with a poor outlook for complete correction. [52] (10.1016/j.hcl.2012.05.036)
- [L5] [53] (10.5435/00124635-200703000-00009)
- [L2] Patients with pre-existing PIP tenderness should be informed about the possibility of sustaining residual minor pain for up to 3 months after surgery. [55] (10.1186/s12891-023-06130-5)
- [L4] Results suggest that the angles suggested by Murray (2016) are too flexed and that most patients prefer a PIPJ arthrodesis in more extension. [56] (10.1177/1753193419893202)
- [Paper] The association of persistent subluxation and early arthrosis in dorsal PIP joint fracture dislocations needs further study. [57] (10.1055/s-0039-1697063)
- [L5] [58] (10.1016/j.jhsa.2010.09.002)
- [L4] Implant arthroplasty of the PIP, MCP, and TMC joints predictably produces pain relief and high satisfaction but has historically suffered from high rates of complications. [59] (10.1016/j.jhsa.2017.07.030)
- [L4] The available PIPJ arthrodesis techniques have similar fusion time, nonunion rate, and complication rate outcomes. [61] (10.1177/1558944721998019)
- [L4] [62] (10.1177/1753193418765691)
- [L1] In contrast, the addition of a PIPJ extension orthosis in the presence of traumatic PIPJ fixed flexion deformities is more effective for improving PIPJ extension than hand therapy alone. [63] (10.1016/j.jht.2023.12.018)
- [L5] Proper biomechanics of a joint must be restored to achieve full, functional range of motion. [80] (10.1016/j.hcl.2017.12.008)
- [L5] Despite the wealth of knowledge regarding the anatomy of the PIPJ, it remains a subject of ongoing investigation, and evolving understanding of its biomechanical properties will continue to improve treatment and reconstructive designs. [81] (10.1016/j.hcl.2017.12.002)
- [L5] [92] (10.1302/2058-5241.4.180042)
- [L4] The survival of the MatOrtho proximal interphalangeal joint arthroplasty was 85% at a minimum of 2-years follow-up. [94] (10.1177/1753193415614251)
- [L4] Open dislocations are predominantly dorsal dislocations of the index and middle fingers. [101] (10.1177/17531934251405707)
- [L3] Collagenase clostridium histolyticum treatment is effective for isolated or combined PIP joint contractures. [104] (10.1016/j.jhsg.2024.05.009)
- [L5] Restoration of stability allowing early motion and a smooth articular surface are the goals of treatment. [110] (10.1016/j.jhsa.2015.08.023)
- [L5] [116] (10.1016/j.hcl.2009.05.008)
- [L5] [118] (10.1016/j.hcl.2017.12.004)
- [Textbook] A logical sequential approach to releasing PIP joint contractures in Dupuytren's disease, prioritizing gentle passive manipulation and less aggressive surgeries, yields better results than aggressive interventions. [120] (10.1007/978-3-642-22697-7_30)
References
[1] Reoperations Following Proximal Interphalangeal Joint Nonconstrained Arthroplasties. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2011.06.002
[2] Surgical Exposure of the Proximal Interphalangeal Joint. Hand Clinics. 2018. DOI: 10.1016/j.hcl.2017.12.003
[3] Proximal Interphalangeal Joint Fusion. Hand Clinics. 2018. DOI: 10.1016/j.hcl.2017.12.007
[4] Proximal interphalangeal (PIP) joint replacements with pyrolytic carbon implants in the hand. EFORT Open Reviews. 2017. DOI: 10.1302/2058-5241.2.160041
[5] Complications of Proximal Interphalangeal Joint Injuries. Hand Clinics. 2018. DOI: 10.1016/j.hcl.2017.12.014
[6] Salvaging a Failed Proximal Interphalangeal Joint Implant. Hand Clinics. 2018. DOI: 10.1016/j.hcl.2017.12.011
[7] Trends in Primary Proximal Interphalangeal Joint System and Revisions for Osteoarthritis of the Hand in the Medicare Database. HAND. 2019. DOI: 10.1177/1558944719837009
[8] Range of motion, postoperative rehabilitation and patient satisfaction in MCP and PIP joints affected by Dupuytren Tubiana stage 1–3: collagenase enzymatic fasciotomy or limited fasciectomy? A clinical study in 52 patients. Archives of Orthopaedic and Trauma Surgery. 2018. DOI: 10.1007/s00402-018-3034-6
[9] Reoperations following Proximal Interphalangeal Joint Unconstrained Arthroplasty. The Journal of Hand Surgery. 2011. DOI: 10.1016/s0363-5023(11)60049-x
[10] New-Generation Implant Arthroplasties of the Finger Joints. Journal of the American Academy of Orthopaedic Surgeons. 2003. DOI: 10.5435/00124635-200309000-00002
[11] Factors Associated with Reoperation after Pyrocarbon Proximal Interphalangeal Joint Arthroplasty for the Arthritic Joint: A Retrospective Cohort Study. Journal of Hand and Microsurgery. 2021. DOI: 10.1055/s-0040-1709088
[12] Pyrocarbon proximal interphalangeal joint arthroplasty: outcomes of a cohort study. Journal of Hand Surgery (European Volume). 2011. DOI: 10.1177/1753193411434053
[13] Long-term Survival of Proximal Interphalangeal Joint Denervation of the Hand: Time-to-Event Analysis. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2026.01.033
[14] Proximal interphalangeal joint arthroplasty: current trends and evidence-based practice. Journal of Hand Surgery (European Volume). 2024. DOI: 10.1177/17531934241265837
[15] Surgical Approaches to the Proximal Interphalangeal Joint. The Journal of Hand Surgery. 2016. DOI: 10.1016/j.jhsa.2015.11.013
[16] Type of Work and Preoperative Ability to Perform Work Affect Return to Usual Work Following Proximal Interphalangeal Joint Arthroplasty for Osteoarthritis. HAND. 2022. DOI: 10.1177/15589447221141485
[17] Open Reduction of Neglected Dislocations of the Proximal Interphalangeal Joint. The Journal of Hand Surgery. 2020. DOI: 10.1016/j.jhsa.2020.07.002
[18] Current European Practice in the Treatment of Proximal Interphalangeal Joint Arthritis. Hand Clinics. 2017. DOI: 10.1016/j.hcl.2017.04.002
[19] Swelling, Stiffness, and Dysfunction Following Proximal Interphalangeal Joint Sprains. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2023.01.025
[20] Pyrolytic Carbon Hemiarthroplasty for Proximal Interphalangeal Joint Arthritis, Long-Term Follow-Up. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2023.11.007
[21] Intraoperative Periprosthetic Fractures in Proximal Interphalangeal Joint Arthroplasty. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.06.101
[22] Incidence and Presentation of Periprosthetic Joint Infection After Primary Metacarpophalangeal and Proximal Interphalangeal Arthroplasty. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2024.12.008
[23] Surface replacing arthroplasty of the proximal interphalangeal joint using the CapFlex-PIP implant: a prospective study with 5-year outcomes. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420977244
[24] Die Arthrodese des Fingermittelgelenkes: eine Literaturanalyse. Handchirurgie · Mikrochirurgie · Plastische Chirurgie. 2019. DOI: 10.1055/a-0833-8729
[25] Dorsal Subluxation of the Proximal Interphalangeal Joint After Volar Base Fracture of the Middle Phalanx. HAND. 2020. DOI: 10.1177/1558944719895621
[26] Prosthetic Arthroplasty of Proximal Interphalangeal Joints for Treatment of Osteoarthritis and Posttraumatic Arthritis: Systematic Review and Meta-Analysis Comparing the Three Ulnar Digits With the Index Finger. HAND. 2018. DOI: 10.1177/1558944718791186
[27] Pyrocarbon Proximal Interphalangeal Joint Arthroplasty: Minimum Two-Year Follow-Up. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.02.012
[28] Clinical significance of proximal interphalangeal joint pain in patients with trigger fingers. Journal of Hand Surgery (European Volume). 2018. DOI: 10.1177/1753193418809771
[29] Fractures of the Proximal Interphalangeal Joint. Journal of the American Academy of Orthopaedic Surgeons. 2000. DOI: 10.5435/00124635-200011000-00006
[31] The stiff proximal interphalangeal joint – an unsolved problem?. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934221143690
[33] Management of Proximal Interphalangeal Joint Injuries. Hand Clinics. 2006. DOI: 10.1016/j.hcl.2006.05.003
[34] Management of Proximal Interphalangeal Joint Fracture Dislocations. Hand Clinics. 2018. DOI: 10.1016/j.hcl.2017.12.005
[35] Hand Therapy Modalities for Proximal Interphalangeal Joint Stiffness. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.06.118
[37] Proximal interphalangeal joint dislocations and fracture-dislocations. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231183259
[39] A Report on the Early Failure of the LPM Proximal Interphalangeal Joint Replacement. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193408094920
[40] Pyrocarbon proximal interphalangeal joint arthroplasty: a medium to long term follow-up of a single surgeon series. Journal of Hand Surgery (European Volume). 2015. DOI: 10.1177/1753193414566552
[43] Efficacy and Safety of Collagenase Clostridium Histolyticum in the Treatment of Proximal Interphalangeal Joints in Dupuytren Contracture: Combined Analysis of 4 Phase 3 Clinical Trials. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.02.018
[44] Ten years’ experience with a pyrocarbon prosthesis replacing the proximal interphalangeal joint. A prospective clinical and radiographic follow-up. Journal of Hand Surgery (European Volume). 2013. DOI: 10.1177/1753193413479527
[45] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[46] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > Image DISORDERS OF THE MUSCULATURE OF THE HAND.
[50] Ratio of dislocation types of the proximal interphalangeal joint of the fingers: A new classification system for initial therapy. Journal of Orthopaedic Science. 2019. DOI: 10.1016/j.jos.2019.08.007
[51] Management of difficult intra-articular fractures or fracture dislocations of the proximal interphalangeal joint. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193414559464
[52] Proximal Interphalangeal Joint Fracture Dislocations. Hand Clinics. 2012. DOI: 10.1016/j.hcl.2012.05.036
[53] Proximal Interphalangeal Joint Arthroplasty. Journal of the American Academy of Orthopaedic Surgeons. 2007. DOI: 10.5435/00124635-200703000-00009
[55] Dorsal proximal interphalangeal joint tenderness is associated with prolonged postoperative pain after A1 pulley release for trigger fingers. BMC Musculoskeletal Disorders. 2023. DOI: 10.1186/s12891-023-06130-5
[56] Patient satisfaction with the angle of fusion of the proximal interphalangeal joint. Journal of Hand Surgery (European Volume). 2019. DOI: 10.1177/1753193419893202
[57] Postoperative Dorsal Proximal Interphalangeal Joint Subluxation in Volar Base Middle Phalanx Fractures. Journal of Hand and Microsurgery. 2020. DOI: 10.1055/s-0039-1697063
[58] Proximal Interphalangeal Joint Arthritis. The Journal of Hand Surgery. 2010. DOI: 10.1016/j.jhsa.2010.09.002
[59] Implant Arthroplasty for Proximal Interphalangeal, Metacarpophalangeal, and Trapeziometacarpal Joint Degeneration. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.07.030
[61] Proximal Interphalangeal Joint Arthrodesis Techniques: A Systematic Review. HAND. 2021. DOI: 10.1177/1558944721998019
[62] Impact of multi- versus single finger proximal interphalangeal joint arthroplasty: analysis of 249 fingers treated in 15 years. Journal of Hand Surgery (European Volume). 2018. DOI: 10.1177/1753193418765691
[63] Orthotic interventions for restoring proximal interphalangeal joint motion for patients with hand injuries or conditions: A systematic review and meta-analysis. Journal of Hand Therapy. 2024. DOI: 10.1016/j.jht.2023.12.018
[66] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[73] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > FLEXOR TENDON INJURY.
[74] Exam Of The Hand Wrist 2Ed. 1.3 MOVEMENTS OF THE HAND AND WRIST > Gliding mechanisms.
[79] Dupuytren S Disease And Related Hyperproliferative Disorders. 54. The Future of Dupuytren’s Research and Treatment > 54.4 Mechanical Measurements and Procedures > 54.4.4 Imaging.
[80] Advances in Proximal Interphalangeal Joint Arthroplasty. Hand Clinics. 2018. DOI: 10.1016/j.hcl.2017.12.008
[81] Anatomy and Biomechanics of the Finger Proximal Interphalangeal Joint. Hand Clinics. 2018. DOI: 10.1016/j.hcl.2017.12.002
[92] The proximal interphalangeal joint: arthritis and deformity. EFORT Open Reviews. 2019. DOI: 10.1302/2058-5241.4.180042
[94] MatOrtho proximal interphalangeal joint arthroplasty: minimum 2-year follow-up. Journal of Hand Surgery (European Volume). 2016. DOI: 10.1177/1753193415614251
[101] Patterns of proximal interphalangeal joint dislocations. Journal of Hand Surgery (European Volume). 2026. DOI: 10.1177/17531934251405707
[104] Clinical Outcomes of Collagenase Injections in Management of Dupuytren Contracture of the Proximal Interphalangeal Joint. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2024.05.009
[110] Dorsal Fracture-Dislocations of the Proximal Interphalangeal Joint. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.08.023
[116] Management of Proximal Interphalangeal Joint Dislocations in Athletes. Hand Clinics. 2009. DOI: 10.1016/j.hcl.2009.05.008
[118] Treating Proximal Interphalangeal Joint Dislocations. Hand Clinics. 2018. DOI: 10.1016/j.hcl.2017.12.004
[120] 30. A Logical Approach to Release of the Contracted Proximal Interphalangeal Joint in Dupuytren’s Disease. Dupuytren’s Disease and Related Hyperproliferative Disorders. 2012. DOI: 10.1007/978-3-642-22697-7_30