Patients › Hand
انگلی کے درمیانی جوڑ (PIP) کی تبدیلی
PIP joint replacement addresses painful arthritis in the middle finger joint when non-surgical options fail.
یہ آپریشن کیوں تجویز کیا گیا ہے
ڈاکٹر کیرن ہِرپرا، جو Mater Private Hospital Rockhampton میں بازو اور ہاتھ کے سرجن (upper-limb surgeon) ہیں، علاج کا آغاز ان کم سے کم چیر پھاڑ والے طریقوں سے کرتے ہیں جو آپ کی حالت کے لیے موزوں ہوں۔ مریضوں کو عام طور پر ان کے فیملی ڈاکٹر (GP) ہمارے کلینک بھیجتے ہیں؛ اگر کسی فزیوتھراپسٹ نے آپ کو ہم سے ملنے کا مشورہ دیا ہے، تب بھی میڈیکیئر (Medicare) سے رقم کی واپسی (rebate) کا اہل ہونے کے لیے آپ کو اپنے فیملی ڈاکٹر سے ریفرل (referral) لینا ہو گا۔ آپ کی ملاقات پر ہم آپ سے آپ کی تکلیف کی تفصیل پوچھتے ہیں، آپ کے ہاتھ کا معائنہ کرتے ہیں، اور ضرورت ہو تو امیجنگ (ایکسرے یا اسکین جیسی تصاویر) کا انتظام کرتے ہیں۔ اس سے ہمیں معلوم ہوتا ہے کہ جوڑ میں کیا خرابی ہے۔
یہ آپریشن انگلی کے درمیانی جوڑ کو ایک مصنوعی امپلانٹ (جسم میں لگایا گیا مصنوعی پرزہ) سے بدل دیتا ہے۔ یہ عام طور پر ان لوگوں کو پیش کیا جاتا ہے جنہیں جوڑ کے گھسنے والا آرتھرائٹس (wear-and-tear arthritis، جوڑ کی خرابی اور سوزش) یا چوٹ کے بعد ہونے والا آرتھرائٹس ہو، اور زیادہ تر عمر رسیدہ اور کم متحرک مریضوں کو۔ اس کا مقصد جوڑ کو حرکت کے قابل رکھنا اور اسے فیوژن (fusion) سے بچانا ہے، یعنی ہڈیوں کو مستقل طور پر آپس میں جوڑ دینے سے۔
طویل عرصے سے موجود آرتھرائٹس میں ہم عام طور پر پہلے آپریشن کے بغیر علاج آزماتے ہیں۔ اس میں ہاتھ کے استعمال کا طریقہ بدلنا، ہینڈ تھراپی (ہاتھ کی بحالی کا علاج)، یا اسپلنٹ (splint، انگلی کو سہارا دینے والا سانچہ) لگانا شامل ہو سکتا ہے۔ اگر ان سے کافی بہتری نہ آئے تو پھر ہم آپ کے ساتھ سرجری پر بات کرتے ہیں۔ اس کے بنیادی مقاصد درد سے نجات اور ایک ایسا جوڑ ہیں جسے آپ استعمال کر سکیں۔
آپریشن سے پہلے
آپ کے آپریشن کی منصوبہ بندی کے لیے ہم آپ کی انگلی کے ایکسرے لیتے ہیں، اور کبھی کبھی ساتھ میں ایم آر آئی یا الٹراساؤنڈ اسکین بھی کرواتے ہیں۔ یہ تصاویر گھسے ہوئے جوڑ کو دکھاتی ہیں اور صحیح امپلانٹ کے انتخاب میں ہماری مدد کرتی ہیں۔
سرجری سے پہلے کے ہفتوں میں چند عملی تیاریاں کر لیں۔ آپریشن سے سات گھنٹے پہلے کھانا پینا بند کر دیں۔ ہم چھ کے بجائے سات گھنٹے اس لیے کہتے ہیں تاکہ اگر آپریشن کی فہرست وقت سے پہلے چل رہی ہو تو آپ کی باری پہلے لائی جا سکے۔ آپ کے سرجن آپ کو بتائیں گے کہ اپنی باقاعدہ دواؤں میں سے کون سی دوا کب بند کرنی ہے۔ جو کچھ بھی آپ لیتے ہیں اس سب کی لکھی ہوئی فہرست ساتھ لائیں۔ کسی ایسے شخص کا انتظام کریں جو آپریشن کے بعد آپ کو گاڑی میں گھر لے جائے، کیونکہ آپ خود گاڑی نہیں چلا سکیں گے۔ ڈھیلے، آرام دہ کپڑے پہنیں جن کی آستینیں آسانی سے آپ کے ہاتھ پر سے گزر جائیں۔
اگر آپ کو کوئی اور طبی مسئلہ ہو تو ہو سکتا ہے آپ کو خون کے ٹیسٹ یا بے ہوشی کے ڈاکٹر (anaesthetist، وہ ڈاکٹر جو اینستھیزیا دیتے ہیں) سے معائنے کی ضرورت ہو۔ زیادہ تر لوگوں کو ان میں سے کسی کی بھی ضرورت نہیں ہوتی۔
آپریشن کے دن
آپ ہسپتال کے سرجری کے داخلے کے شعبے میں پہنچتے ہیں۔ عملہ آپ کا اندراج کرتا ہے اور آپ کو آپریشن تھیٹر کے لیے تیار کرتا ہے۔ پھر آپ کی ملاقات بے ہوشی کے ڈاکٹر سے ہوتی ہے۔ یہ آپریشن جنرل اینستھیزیا (مکمل بے ہوشی) میں کیا جاتا ہے۔ آپریشن کے دوران آپ پوری طرح بے ہوش ہوں گے۔ کچھ مریضوں کو آپریشن کے بعد درد میں آرام کے لیے ریجنل اعصابی بلاک (regional nerve block)، یعنی ایک انجکشن جو جسم کے ایک حصے کو سُن کر دیتا ہے، بھی دیا جا سکتا ہے؛ بے ہوشی کے ڈاکٹر آپ کے انفرادی حالات کی بنیاد پر اسی دن اس کا فیصلہ کرتے ہیں۔
اس کے بعد آپ کو آپریشن تھیٹر لے جایا جاتا ہے، جہاں آپریشن کیا جاتا ہے۔ آپریشن مکمل ہونے پر آپ ریکوری روم میں جاگتے ہیں۔ وہاں نرسیں آپ کی نگرانی کرتی ہیں جب تک اینستھیزیا کا اثر ختم ہو رہا ہوتا ہے۔ جب آپ کی حالت مستحکم ہو جائے تو آپ یا تو وارڈ میں منتقل ہو جاتے ہیں یا اسی دن گھر چلے جاتے ہیں۔ ان میں سے کیا ہو گا، اس کا انحصار طریقۂ کار پر اور اس بات پر ہے کہ آپ کی صحت یابی کیسی جا رہی ہے۔
آپریشن میں کیا کیا جاتا ہے
ڈاکٹر ہِرپرا یہ آپریشن آپ کی انگلی کی ہتھیلی والی طرف، عین درد والے جوڑ کے اوپر، ایک ہی چیرے کے ذریعے کرتے ہیں۔ جوڑ کو اس طرف سے کھولنے سے انگلی کو سیدھا کرنے والے ٹینڈن (tendon)، یعنی وہ مضبوط ڈوری جو پٹھے کو ہڈی سے جوڑتی ہے، کو چھیڑا نہیں جاتا، اور اس سے آپ کو سرجری کے کچھ ہی عرصے بعد حرکت شروع کرنے میں مدد ملتی ہے۔
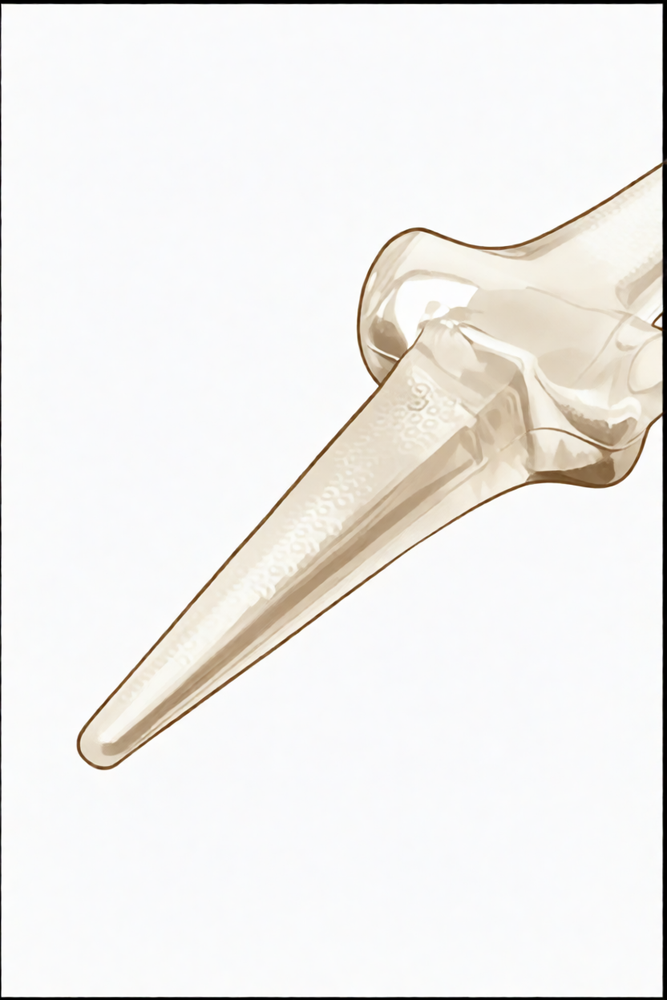
جوڑ کھولنے کے بعد آپ کے سرجن جوڑ کی گھسی ہوئی اور خراب سطحیں نکال دیتے ہیں۔ ان کی جگہ ایک مصنوعی امپلانٹ لگایا جاتا ہے جو انگلی کی دونوں ہڈیوں کے درمیان ایک نئی، ہموار سطح بناتا ہے۔ امپلانٹ اس طرح بنایا گیا ہے کہ جوڑ مڑ اور سیدھا ہو سکے، اور وہ درد کم ہو جو کھردری، گھسی ہوئی سطحوں کی وجہ سے ہو رہا تھا۔
پھر زخم کو ٹانکوں سے بند کر دیا جاتا ہے اور اس کے اوپر زخم کی پٹی رکھ دی جاتی ہے۔ آپ اسی پٹی کے ساتھ گھر جائیں گے، اور تقریباً 10 دن بعد جب یہ اتاری جائے گی تو ہم آپ کے ساتھ زخم کا معائنہ کریں گے۔
آپریشن کے بعد
اس آپریشن کے بعد زیادہ تر مریض ایک رات ہسپتال میں رہتے ہیں، اگرچہ کچھ اسی دن گھر جا سکتے ہیں۔ آپ ریکوری روم میں جاگتے ہیں، پھر وارڈ میں منتقل ہو جاتے ہیں۔ نرسیں باقاعدگی سے آپ کو دیکھتی ہیں اور ضرورت کے مطابق درد کی دوا دیتی ہیں۔ آپ کی انگلی پر زخم کی پٹی ہو گی، اور ہم یہ پٹی تقریباً 10 دن تک لگی رہنے دیتے ہیں؛ براہِ کرم اس سے پہلے اسے نہ اتاریں، سوائے اس کے کہ ہم آپ کو ایسا کرنے کو کہیں۔ جب ہم آپ سے ملیں گے تو اسے بدل دیں گے یا اتار دیں گے۔ جیسے ہی آپ خود کو قابل محسوس کریں، آپ اٹھ کر چل پھر سکتے ہیں، اور نرسیں آپ کی مدد کریں گی۔ براہِ کرم گھر پہنچنے کے بعد پہلے 24 گھنٹے کسی کو اپنے ساتھ رکھیں۔
صحت یابی
پہلے چند دن آپ کی انگلی میں درد اور سوجن رہے گی۔ یہ آہستہ آہستہ کم ہو جاتی ہے۔ اپنے ہاتھ کو تکیے پر اونچا رکھنا، بیٹھتے یا سوتے وقت بھی، سوجن کم کرنے میں مدد دیتا ہے۔ اپنی ٹیم کی ہدایت کے مطابق درد کی عام دوا تکلیف کم کر دے گی۔
آپ کی زخم کی پٹی تقریباً 10 دن لگی رہتی ہے، اور جب ہم آپ سے ملیں گے تو زخم کا معائنہ کریں گے۔ اس کے بعد آپ کی صحت یابی کی رہنمائی Extend Rehabilitation میں Ruby Doolan کے ساتھ ہینڈ تھراپی کے ذریعے ہوتی ہے۔ روبی ایک ہینڈ تھراپسٹ (ہاتھ کی بحالی کی ماہر) ہیں: وہ آپ کی ورزشوں کی رہنمائی کرتی ہیں اور آپ کی انگلی کے لیے جو بھی اسپلنٹ درکار ہو وہ بناتی ہیں۔ آپ گھر پر انگلی کو آہستہ سے موڑنے اور سیدھا کرنے کی حرکتیں کریں گے، تھوڑی تھوڑی اور بار بار۔ مقصد یہ ہے کہ جوڑ آہستہ آہستہ اپنی حرکت واپس حاصل کرے اور اس دوران بھرتا ہوا ٹینڈن محفوظ رہے، اس لیے درد کے باوجود زور لگانے کے بجائے وہی منصوبہ اپنائیں جو وہ آپ کو دیں۔
روزمرہ زندگی میں، شروع میں آپ زیادہ تر کام اپنے دوسرے ہاتھ سے کریں گے۔ جیسے ہی آپ خود کو قابل محسوس کریں، آپ کپڑے پہن سکتے ہیں، سادہ کھانا تیار کر سکتے ہیں اور گھر میں چل پھر سکتے ہیں۔ جب تک آپ کی انگلی اسپلنٹ میں ہو اور اس کی وجہ سے آپ اسٹیئرنگ کو محفوظ طریقے سے نہ پکڑ سکیں، آپ گاڑی نہیں چلائیں گے۔ اسپلنٹ اترنے اور آپ کے سرجن کی اجازت کے بعد گاڑی چلانا دوبارہ شروع کیا جا سکتا ہے؛ ہمارا صفحہ بازو اور ہاتھ کی سرجری کے بعد گاڑی چلانا دیکھیں۔
جیسے جیسے سوجن کم ہوتی ہے اور حرکت واپس آتی ہے، آپ محسوس کریں گے کہ جوڑ زیادہ مڑ رہا ہے اور آپ کے زیادہ کام آ رہا ہے۔ پیش رفت کے سنگِ میل ایسے ہی مراحل سے جڑے ہیں، تاریخوں سے نہیں۔
ہر شخص اپنی رفتار سے ٹھیک ہوتا ہے، اس لیے آپ کی صحت یابی کا دورانیہ مختلف ہو سکتا ہے۔ آپ کے سرجن اور آپ کی ہینڈ تھراپسٹ ہر قدم پر آپ کی رہنمائی کریں گے۔
کیا مسائل پیدا ہو سکتے ہیں
زیادہ تر مریض اچھی طرح ٹھیک ہو جاتے ہیں، لیکن کبھی کبھار مسائل پیدا ہو سکتے ہیں۔ آپ کے سرجن اور ٹیم آپ کی قریب سے نگرانی کرتے ہیں تاکہ کسی بھی مسئلے کو جلد پہچان سکیں۔
کبھی کبھی خود امپلانٹ مسئلہ پیدا کرتا ہے۔ یہ ڈھیلا ہو سکتا ہے، یا اس کے اردگرد کی ہڈی میں چھوٹی سی دراڑ آ سکتی ہے۔ آپ کو جوڑ میں نیا درد، یہ احساس کہ انگلی پہلے سے کم مستحکم ہے، یا حرکت کرتے وقت کٹ کٹ کی آواز یا رگڑ کا احساس ہو سکتا ہے۔ جوڑ کی اندرونی جھلی میں بھی جلن (irritation) اور سوجن ہو سکتی ہے۔ اگر جوڑ دوبارہ ٹیڑھا ہونے لگے، یا انگلی اتنی نہ مڑے یا سیدھی نہ ہو جتنی پہلے ہوتی تھی، تو اپنے اگلے معائنے پر اس کا ذکر کریں۔ یہ تبدیلیاں درد نہ ہونے کی صورت میں بھی دکھانے کے قابل ہیں۔
امپلانٹ ٹوٹ سکتا ہے۔ سلیکون امپلانٹ (ایک نرم، لچکدار درمیانی ٹکڑا) میں، ٹوٹا ہوا امپلانٹ اکثر ایسا درد پیدا کرتا ہے جو کچھ عرصہ بہتری کے بعد واپس آ جاتا ہے۔ اگر آپ کی انگلی میں دوبارہ درد ہونے لگے، یا درد کے ساتھ یا اس کے بغیر حرکت محدود رہے، تو ہمیں بتائیں۔ کبھی کبھی انگلی ایک طرف کو جھکنے لگتی ہے، جو پہلے نہیں تھا۔ ان میں سے کوئی بھی تبدیلی ہو تو امپلانٹ کا معائنہ ہونا چاہیے۔
جوڑ میں ڈھیلا پن (instability) پیدا ہو سکتا ہے۔ انگلی دائیں بائیں ہلتی ہوئی محسوس ہو سکتی ہے، یا جزوی طور پر اپنی جگہ سے کھسک سکتی ہے۔ جو جوڑ واضح طور پر ٹیڑھا نظر آئے اس پر جلد توجہ کی ضرورت ہے، اس لیے اپنی اگلی ملاقات کا انتظار کرنے کے بجائے کلینک کو فون کریں۔
اکڑاؤ پیدا ہو سکتا ہے۔ ہو سکتا ہے انگلی پوری طرح نہ مڑے یا سیدھی نہ ہو، اور جوڑ سخت محسوس ہو۔ درد کے ساتھ مستقل اکڑاؤ کا معائنہ ہونا چاہیے۔
انفیکشن کم ہوتا ہے لیکن سنگین ہے۔ ایسے گہرے، دھڑکتے ہوئے درد پر نظر رکھیں جو درد کی عام دواؤں سے کم نہ ہو، زخم سے باہر کی طرف پھیلتی ہوئی سرخی، گرمی، یا زخم سے رطوبت کا اخراج۔ اگر آپ کو یہ علامات نظر آئیں تو فوراً کلینک سے رابطہ کریں، یا اگر کلینک کے اوقات کے بعد کا وقت ہو تو ہسپتال کی ایمرجنسی جائیں۔
امپلانٹ کے اردگرد کی ہڈی میں فریکچر (ہڈی کا ٹوٹنا) سرجری کے دوران یا بعد میں ہو سکتا ہے۔ بعد میں اچانک درد، سوجن یا انگلی کی شکل میں تبدیلی ہو تو اس کی اطلاع دیں۔
اگر کوئی مسئلہ پیدا ہو جائے تو کبھی کبھی مزید سرجری کی ضرورت پڑتی ہے۔ اس کا مطلب امپلانٹ کو ٹھیک کرنا یا بدلنا ہو سکتا ہے، یا بعض صورتوں میں اس کے بجائے ہڈیوں کو مستقل طور پر آپس میں جوڑ دینا۔ اگر ایسا ضروری ہو گیا تو ہم آپ کو اس کی پوری تفصیل سمجھائیں گے۔
اگر آپ تفصیلات جاننا چاہیں تو اس صفحے پر پیچیدگیوں کی جدول میں عام شرحیں درج ہیں۔
ہمیں کب فون کریں
زیادہ تر مسائل انہی طریقوں سے ظاہر ہوتے ہیں جو ہم نے اوپر بیان کیے ہیں، لیکن چند پر فوری توجہ کی ضرورت ہوتی ہے۔ اگر آپ کو بخار ہو، اگر آپ کے زخم کے اردگرد سرخی پھیل رہی ہو، یا اس سے نئی رطوبت نکل رہی ہو تو ہمیں فوراً فون کریں۔ اگر آپ کو اچانک شدید درد ہو، یا آپ کی انگلی سُن ہو جائے یا آپ اسے حرکت نہ دے سکیں تو ہمیں فون کریں۔ اگر آپ کی پنڈلی میں سوجن یا درد ہو، یا سانس پھولے، تو ہسپتال کی ایمرجنسی جائیں، کیونکہ یہ خون کے لوتھڑے کی علامت ہو سکتی ہیں۔ اگر کلینک کے اوقات کے بعد کا وقت ہو اور آپ فکرمند ہوں، تو صبح تک انتظار کرنے کے بجائے ایمرجنسی جائیں۔
اس مسئلے کے بارے میں مزید کہاں پڑھیں
یہ صفحہ خود آپریشن کے بارے میں ہے۔ جس مسئلے کا یہ علاج کرتا ہے، اور اس بارے میں کہ شواہد کیا بتاتے ہیں کہ سرجری کب فائدہ دیتی ہے اور کب نہیں، اس کی مزید تفصیل انگلی کے درمیانی جوڑ (PIP) کا آرتھرائٹس صفحے پر موجود ہے۔
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Anatomy & Pathophysiology
General Hand Architecture
- The hand is composed of 19 bones, 17 articulations, and 19 muscles situated entirely within the hand [2].
- The hand contains approximately the same number of tendons activated by the forearm muscles as it has intrinsic muscles [2].
- The hand functions as an organ designed to obtain information and an organ of execution [2].
- The hand moves within a large volume of space with the shoulder as the apex, allowing it to reach any part of the body fairly easily due to the mobility of the shoulder, elbow, and wrist [2].
- The open hand with fingers extended and in contact forms a balanced graceful oval in its longitudinal axis [2].
- The dorsal aspect of the hand is convex, while the anterior, palmar or volar aspect is concave [2].
- The distal half of the hand is separated into five digits which flex toward the palm [2].
- The thumb has a more proximal and lateral position than the four fingers, allowing movement inward and outward from the palm [2].
- The four fingers are the distal extension of the carpometacarpal part of the hand [2].
- The hinges of finger movements are located at the thenar crease and at the transverse distal palmar crease, not at the bases of the digits [2].
- When fingers are extended and separated, their tips lie on the circumference of a circle whose center is the head of the third metacarpal [2].
Osseous and Arch Anatomy
- The metacarpal arch possesses adaptability due to the mobility of the peripheral metacarpals [7].
- The index metacarpal is the most firmly fixed of the metacarpals [7].
- The ring metacarpal has about 10 degrees of mobility in flexion and extension [7].
- The fifth metacarpal is semi-independent and has a range of flexion–extension of approximately 20 degrees [7].
- The second to fifth metacarpals are bound together by fibrous structures, the most distal of which is the deep transverse intermetacarpal ligament [7].
- The deep transverse intermetacarpal ligament is also known as the interglenoid ligament because it ties together the anterior glenoid ligaments of the metacarpophalangeal articulations [7].
- The longitudinal arches of the hand are composed of a fixed carpometacarpal portion and a mobile digital portion [7].
- The metacarpophalangeal articulations serve as the keystones of the longitudinal arches [7].
- The thick anterior glenoid capsules, known as volar plates, prevent hyperextension at the metacarpophalangeal joints [7].
- The stability of the metacarpophalangeal joints is essential to the support of both the longitudinal and transverse metacarpal arches [7].
Intrinsic Musculature and Extensor Mechanism
- There are seven interosseous muscles in the hand, consisting of four dorsal and three volar muscles [4].
- The dorsal interossei are abductors, while the volar interossei are adductors [4].
- The middle finger has two dorsal interossei and no volar interossei because the central axis of the hand lies within it [4].
- Each dorsal interosseous muscle, with the exception of the third, has two muscle heads: a superficial head and a deep head [4].
- The superficial head of the dorsal interosseous muscles abducts and weakly flexes the proximal phalanx [4].
- The deep head of the dorsal interosseous muscles flexes and weakly abducts the proximal phalanx while extending the middle and distal phalanges [4].
- Transverse fibers arch dorsally from each lateral band to join over the dorsum of the finger, flexing the proximal phalanx [4].
- Oblique fibers, also called spiral fibers, from the lateral bands insert onto the lateral tubercles at the base of the middle phalanx to extend the middle phalanx at the PIP joint [4].
- The lateral bands are joined by the lateral slips of the extensor tendon to form the conjoined lateral band [4].
- The two conjoined lateral bands to each finger unite at the distal third of the middle phalanx to form the terminal tendon [4].
- The terminal tendon inserts at the base of the distal phalanx to extend it [4].
- The volar interossei have only one muscle head and do not insert onto the proximal phalanx [4].
- The volar interossei form the ulnar lateral band of the index finger and the radial lateral band of the ring and little fingers [4].
- The flexor digiti quinti brevis is structurally and functionally similar to the deep head of the dorsal interossei, forming the ulnar lateral band of the little finger [4].
Cutaneous Anatomy
- Functional cutaneous units in the hand are similar to those described in the face [3].
- One dorsal cutaneous unit extends from the wrist to the proximal interphalangeal joints of the fingers and the interphalangeal joint of the thumb [3].
- The dorsal covering of the interphalangeal articulations forms a unique cutaneous unit characterized by considerable excess of skin when digits are in extension [3].
- The fine tight skin of the dorsal aspect of the middle phalanx forms a distinct cutaneous unit [3].
- The dorsal integument of the distal phalanx is distinct due to the nail bed with its matrix [3].
- The palm forms a cutaneous unit extending from the distal transverse crease of the wrist up to the transverse crease at the base of the digits [3].
- The palmar integument is subdivided into two zones by the oppositional crease of the thumb, which constitutes the oblique axis of the hand [3].
- The skin of the radial portion of the palm covers the thenar eminence and is relatively well vascularized and mobile [3].
- The skin of the ulnar and distal portion of the palm covers the hypothenar eminence where skin mobility is poor [3].
- The central triangular part of the palm has fixed and poorly vascularized skin that covers almost directly the superficial palmar aponeurosis [3].
- The integument of the palmar face of the digits is subdivided into phalangeal units separated by digital flexion folds [3].
- When a digit is completely flexed, the integument of adjacent phalanges comes into contact in the zones of the flexion creases, establishing areas of cutaneous contact in the form of a diamond [3].
- The sides of the diamond-shaped cutaneous contact zones do not undergo variations in length during flexion and extension movements [3].
- Incisions made along the lines of the diamond-shaped cutaneous contact zones present a minimal chance of retraction [3].
- The web spaces are formed from the union of two nonsymmetrical cutaneous surfaces [3].
- The dorsal slope of the web space has a gradual incline and supple skin that is not adherent to the subjacent region [3].
- The palmar surface of the web space is flat and precipitously interrupted, with skin densely adherent to the commissural skeleton [3].
- The commissural skeleton is formed by the interdigital palmar ligament between the fingers and by the distal transverse ligament at the level of the thumb web [3].
Vascular Anatomy
- The arteries of the thumb vary in both size and number, making surgical reconstruction delicate [8].
- The layout of thumb arteries is the result of innumerable variations regarding origin, transit, connections, and size [8].
- In anatomical studies, only 15% of dissections of the palmar arteries of the thumb fall into the classical "typical" category [8].
- The princeps pollicis artery is the terminal branch of the radial artery that crosses the first intermetacarpal space [8].
- The princeps pollicis artery runs along the ulnar side of the first metacarpal bone and along the volar surface of the adductor muscle [8].
- The princeps pollicis artery emerges onto the subcutaneous palmar tissue at the level of the cutaneous flexion crease of the metacarpophalangeal joint [8].
- At the metacarpophalangeal flexion crease, the princeps pollicis divides into two terminal rami known as the collateral palmar arteries of the thumb [8].
- The collateral palmar arteries run along the digital tunnel symmetrically and are of equal caliber [8].
- An arcade located deep in the flexor tendon joins together the two palmar arteries at the level of the distal metaphysis of the first phalanx [8].
- Vessels entering the vincula and irrigating the flexor tendon originate from the subtendinous anastomosis at the neck of the first phalanx [8].
- In the second segment of the thumb, the main artery is the ulnar collateral artery [8].
- The subtendinous anastomosis situated at the level of the neck of the first phalanx acts as a moderator between the two collateral arteries [8].
- In the pulp segment of the thumb, the two arteries are of similar size and run through thick fatty subcutaneous padding [8].
- The dorsal arteries of the thumb originate from palmar arteries at the level of the first metacarpal [8].
- The ulnar dorso-collateral artery generally stems from the princeps pollicis onto the medial border of the neck of the first metacarpal [8].
Surgical Anatomy and Incisions
- Distal palmar incisions are typically transverse, while proximal palmar incisions tend to be more longitudinal [9].
- Proximal palmar incisions should parallel the thenar crease [9].
- Incisions extended proximal to the wrist should not cross the flexor wrist creases at a right angle [9].
- The most important structure in the thenar area is the recurrent branch (motor) of the median nerve [9].
- Anatomic studies show that there is no single longitudinal incision in the proximal palm that completely avoids the palmar cutaneous branches of the median and ulnar nerves [9].
- The superficial volar neurovascular arch should be protected when deeper exposure is required in the distal palm [9].
- Structures lying between the metacarpal heads in the distal palm are not protected by the palmar fascia [9].
- Midlateral incisions described for fingers are suitable for the thumb, with the radial side being more accessible [9].
- A midlateral thumb incision can be extended by curving its proximal end at the midmetacarpal area to create a flap on the palmar surface of the thumb [9].
- Care must be taken to avoid injury to the dorsal branch of the superficial radial nerve when using a radial midlateral incision on the thumb [9].
Investigations
- Clinical evaluation of the hand and wrist requires combining patient history with a careful physical examination to pinpoint or narrow the scope of possible pathologic processes [1].
- Diagnostic tests such as imaging and serum laboratory studies are useful in determining pathology but can be expensive, time-consuming, and often nonspecific [1].
- A careful physical examination is essential to direct care and future testing if indicated [1].
- The skeleton of the hand and wrist consists of 27 bones, of which 19 are long bones [12].
- The skeleton is divided into five rays, each ray making up a polyarticulated chain comprising the metacarpals and phalanges [12].
- The base of each metacarpal articulates with the distal row of the carpus [12].
- The carpus articulates with the skeleton of the forearm through its proximal row [12].
- The radioulnocarpal articulation has two axes of movement to which is added a third—pronation and supination from the forearm [12].
- The wrist has three axes of movement, permitting the hand to be positioned in any spatial configuration and allowing it to be placed as needed for grasping [12].
- The radial ray or first ray is the shortest and is made up of only three bones—a metacarpal and two phalanges [12].
- The trapezium is clearly angled out in front of the carpal plane so that the first metacarpal makes an angle of about 45 degrees with the second metacarpal in the sagittal plane [12].
- The lengths of the metacarpals vary, with the thumb metacarpal being the shortest and the index finger the longest [12].
- The proximal and particularly the middle phalanges of the middle and ring fingers are longer than those of the index finger [12].
- The epiphyseal plates are located at the proximal ends of the phalanges and the first metacarpal [12].
- The epiphyseal plates are located at the distal ends of the other metacarpals [12].
References
[1] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[2] Exam Of The Hand Wrist 2Ed. INTRODUCTION.
[3] Exam Of The Hand Wrist 2Ed. Functional cutaneous units.
[4] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[7] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[8] Exam Of The Hand Wrist 2Ed. Techniques of investigation of the arterial supply by J P Melki > Vascularization of the thumb > Palmar aspect.
[9] Campbell S Operative Orthopaedics 4 Volume Set. RESULTS OF SUTURE OF THE SCIATIC NERVE > PALMAR INCISIONS.
[12] Exam Of The Hand Wrist 2Ed. 1.1 SKELETON OF THE HAND > The osseous skeleton.