Patients › Rehabilitation
ہنسلی کی ہڈی کا بیرونی سرا نکالنا (Distal Clavicle Excision)
Rehabilitation after isolated arthroscopic distal clavicle excision; combined cases follow the rotator cuff repair protocol.
یہ پروٹوکول (protocol، یعنی بحالی کا مرحلہ وار منصوبہ) Mater Private Hospital Rockhampton میں ڈاکٹر کیرن ہِرپرا کے کیے گئے اس آپریشن کے بعد آپ کی صحت یابی میں رہنمائی کرتا ہے جس میں دوربین کے ذریعے ہنسلی کی ہڈی کا بیرونی سرا نکالا جاتا ہے (distal clavicle excision، جسے اے سی جوڑ کا ایکسیژن (AC joint excision) یا ممفرڈ آپریشن (Mumford procedure) بھی کہا جاتا ہے)۔ نیچے ہر مرحلہ آسان زبان میں اس وضاحت سے شروع ہوتا ہے کہ سب سے زیادہ اہم کیا ہے، اور اس کے بعد آپ کے فزیوتھراپسٹ کے لیے لکھا گیا باقاعدہ پروٹوکول آتا ہے؛ فزیوتھراپی کی پہلی ملاقات پر یہ صفحہ یا اس کی پی ڈی ایف ساتھ لائیں تاکہ آپ کی بحالی میں سب کا آپس میں رابطہ رہے۔ آپ کا فزیوتھراپسٹ آپ کو اگلے مرحلوں میں اس بنیاد پر لے جائے گا کہ آپ کا کندھا کیسے ٹھیک ہو رہا ہے، نہ کہ کیلنڈر کی بنیاد پر۔
یہ پروٹوکول صرف ہنسلی کی ہڈی کا بیرونی سرا نکالنے کے اکیلے آپریشن کے لیے ہے۔ اگر آپ کے آپریشن میں روٹیٹر کف (rotator cuff)، یعنی ٹینڈنوں کا وہ گروپ جو کندھے کو تھامتا اور گھماتا ہے، کی مرمت بھی شامل تھی، تو اس کے بجائے روٹیٹر کف کی مرمت کا پروٹوکول اپنائیں، کیونکہ مرمت شدہ ٹینڈن (tendon)، یعنی وہ مضبوط ڈوری جو پٹھے کو ہڈی سے جوڑتی ہے، بحالی کی رفتار کو سست رکھتا ہے۔ (ہنسلی کی ہڈی کا بیرونی سرا نکالنے کا آپریشن اکثر سب ایکرومیئل ڈی کمپریشن (subacromial decompression، کندھے کی ہڈی کے ابھار کے نیچے جگہ کشادہ کرنا) کے ساتھ بھی کیا جاتا ہے؛ اس صورت میں بھی نیچے دیا گیا پروٹوکول اسی طرح لاگو ہوتا ہے۔)
اگر سرجری کے بعد آپ کو اپنے زخم کے بارے میں کوئی بھی تشویش ہو تو کلینک سے رابطہ کریں۔ اکثر یہ مددگار ہوتا ہے کہ آپ زخم کی تصویر لے کر جائزے کے لیے ای میل کر دیں۔
کیا توقع رکھیں
اس آپریشن میں ہنسلی کی ہڈی کے سرے سے چند ملی میٹر ہڈی نکال دی جاتی ہے، تاکہ اے سی جوڑ (AC joint، کندھے کے اوپر والا چھوٹا جوڑ) کی گھسی ہوئی سطحیں آپس میں مزید نہ رگڑیں۔ کوئی ایسی چیز مرمت نہیں کی جاتی جسے ٹھیک ہوتے وقت بچانے کی ضرورت ہو، اس لیے بحالی تیزی سے آگے بڑھتی ہے: سلنگ (sling)، یعنی گلے سے لٹکی وہ پٹی جو بازو کو سہارا دیتی ہے، صرف آرام کے لیے ہے اور زیادہ تر لوگ پہلے ایک دو ہفتوں میں اسے چھوڑ دیتے ہیں، حرکت فوراً شروع ہو جاتی ہے، اور اس آپریشن کے تمام شائع شدہ پروٹوکول آرام کے بجائے جلد حرکت کی طرف لے جاتے ہیں۔
دو باتیں اس آپریشن کے لیے خاص ہیں اور پروٹوکول کو انہی کے مطابق ترتیب دیا گیا ہے:
- ہاتھ کو جسم کے آگے سے دوسری طرف لے جانا سب سے دیر سے ٹھیک ہوتا ہے۔ جسم کے آگے سے دوسری طرف لے جانے والی حرکتیں (horizontal adduction) اس جگہ کو دباتی ہیں جہاں سے ہڈی نکالی گئی تھی، اس لیے اکثر یہی وہ آخری حرکتیں ہوتی ہیں جو آرام دہ محسوس ہوتی ہیں۔ شروع میں ان سے جان بوجھ کر پرہیز کیا جاتا ہے، پھر انہیں آہستہ آہستہ دوبارہ شامل کیا جاتا ہے۔
- بھاری زور سے دھکیلنے والی ورزشیں سب سے آخر میں آتی ہیں۔ وہ ورزشیں جو اے سی جوڑ پر زیادہ بوجھ ڈالتی ہیں (بینچ پریس (bench press)، ڈِپس (dips) اور پُش اَپس (push-ups)) سب سے آخر میں واپس آتی ہیں، عام طور پر تین سے چار ماہ کے دوران۔ باقی زیادہ تر سرگرمیاں اس سے کافی پہلے واپس آ جاتی ہیں۔
پورا سفر ایک نظر میں:
- مرحلہ I — ابتدائی بحالی اور حرکت — ہفتہ 0 سے 2
- مرحلہ II — حرکت کی حد بحال کرنا — ہفتہ 2 سے 6
- مرحلہ III — طاقت بڑھانا اور سرگرمیوں میں واپسی — ہفتہ 6 سے 12
- مرحلہ IV — مکمل سرگرمیوں میں واپسی — ہفتہ 12 اور اس کے بعد
زیادہ تر لوگ پہلے دو ایک ہفتوں میں بازو کو روزمرہ کے ہلکے کاموں کے لیے استعمال کرنے لگتے ہیں، چار سے چھ ہفتوں تک زیادہ تر معمول کی سرگرمیوں پر واپس آ جاتے ہیں، اور آٹھ سے بارہ ہفتوں کے درمیان کھیل اور بھاری کام پر لوٹ آتے ہیں۔ ایسے کھلاڑی جن کے کھیل میں بار بار سر سے اوپر بازو چلانا پڑتا ہے (گیند پھینکنا، تیراکی، ٹینس) عام طور پر کچھ زیادہ وقت لیتے ہیں، تقریباً دو سے چار ماہ۔
مرحلہ I — ابتدائی بحالی اور حرکت (ہفتہ 0 سے 2)
Kieran Hirpara 4.0
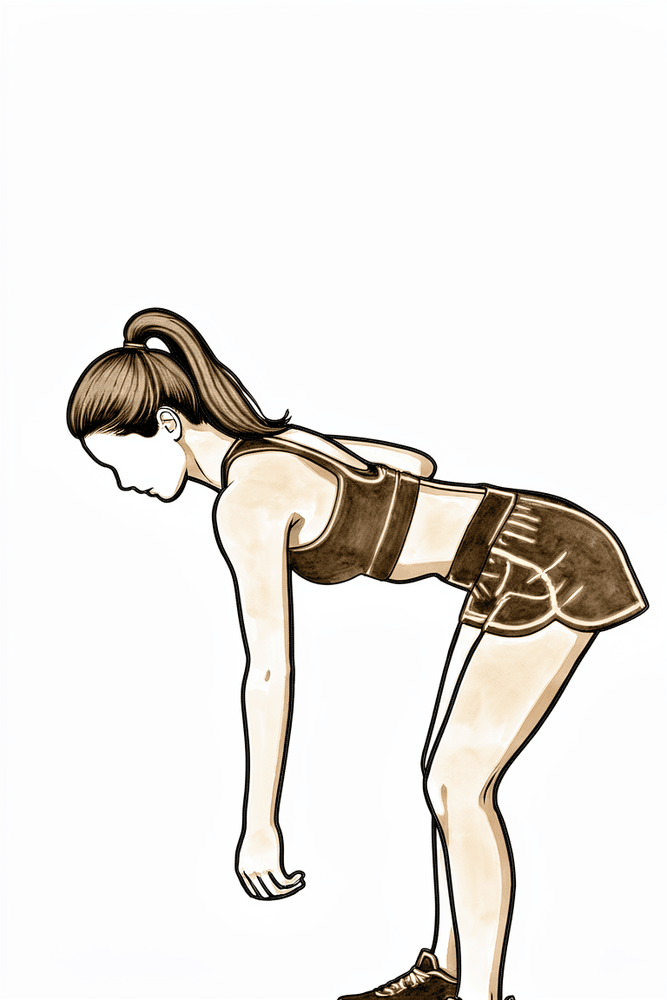
پینڈولم ورزش (pendulum)
کمر سے آگے کی طرف جھکیں اور آپریشن والے بازو کو جسم سے دور آرام سے لٹکنے دیں۔ بازو کو چھوٹے، ڈھیلے دائروں میں جھولنے دیں — حرکت آپ کے جسم سے آئے، کندھے کے پٹھوں سے نہیں۔ پہلے دن سے شروع کریں اور آرام کی حد میں رہیں۔
گھر پر ورزش کا پروگرام، دن میں 3 سے 5 بار
Kieran Hirpara 4.0
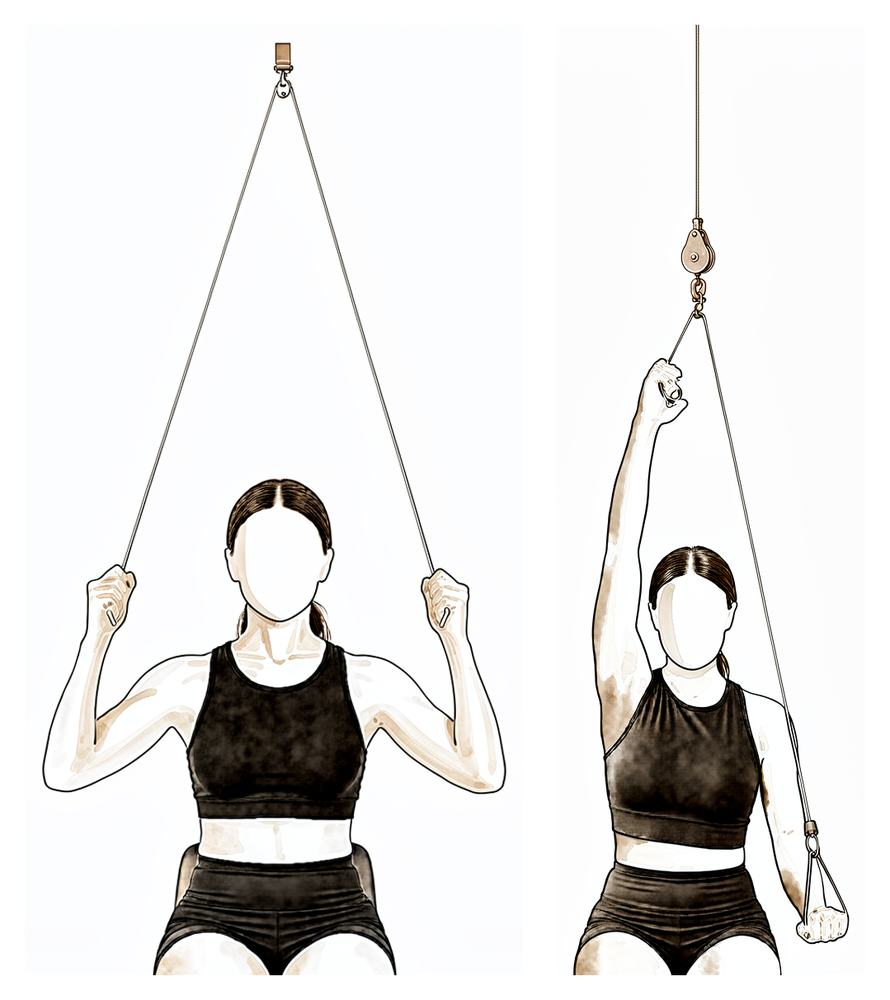
پُلی کی مدد سے بازو اوپر اٹھانا
دروازے کے اوپر لگی پُلی (pulley) کے نیچے بیٹھیں اور ہر ہاتھ میں ایک ہینڈل پکڑیں۔ ٹھیک بازو سے نیچے کھینچیں تاکہ آپریشن والا بازو اوپر اٹھے، اسے ڈھیلا رہنے دیں، پھر اسے قابو کے ساتھ واپس نیچے لائیں۔ آرام کی حد میں کام کریں اور جتنا برداشت ہو اونچائی بڑھاتے جائیں۔
گھر پر ورزش کا پروگرام، دن میں 3 سے 5 بار
Kieran Hirpara 4.0
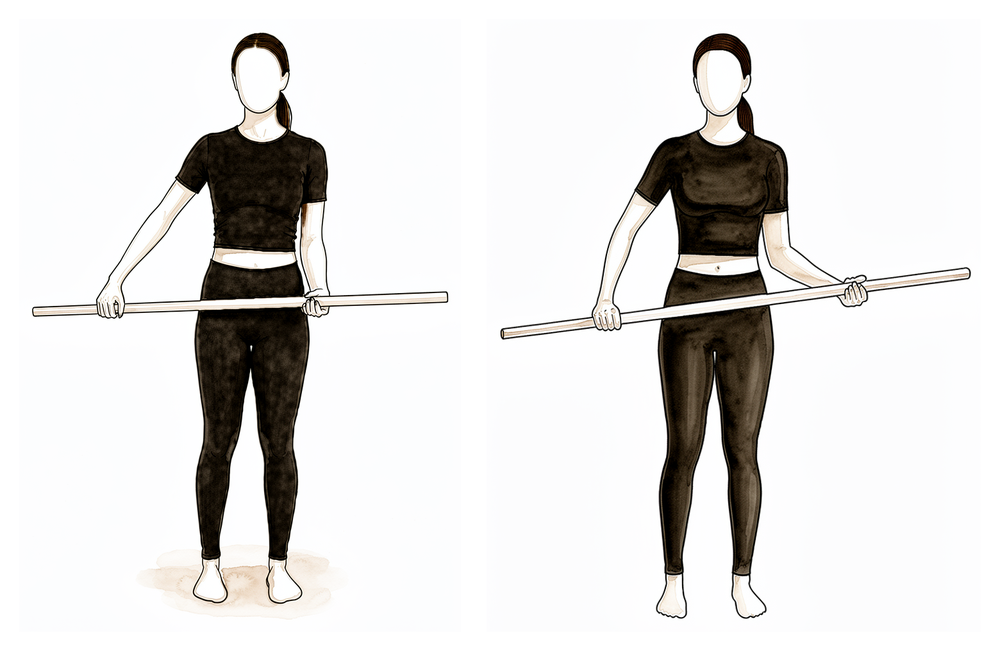
چھڑی کی مدد سے باہر کی طرف گھماؤ
کمر کے بل لیٹیں اور دونوں ہاتھوں میں ایک چھڑی یا لاٹھی پکڑیں، کہنیاں سیدھے زاویے پر مڑی ہوں اور پہلوؤں سے لگی ہوں۔ ٹھیک بازو سے آپریشن والے بازو کے نچلے حصے کو آہستہ سے باہر کی طرف، جسم سے دور دھکیلیں، پھر واپس لائیں۔ آپریشن والا بازو ڈھیلا رہے اور سارا کام چھڑی کرے۔
گھر پر ورزش کا پروگرام، دن میں 3 سے 5 بار
Kieran Hirpara 4.0
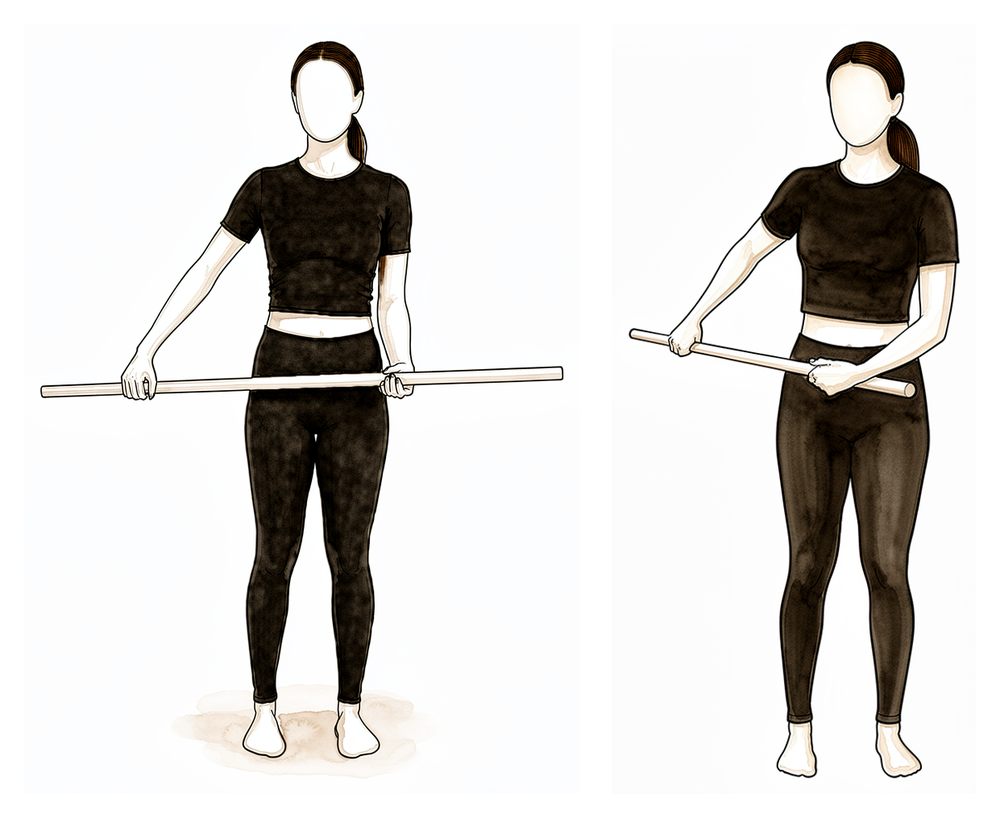
کمر کے پیچھے اندر کی طرف گھماؤ
کمر کے پیچھے ایک چھڑی یا لاٹھی پکڑیں، آپریشن والا ہاتھ نیچے اور ٹھیک ہاتھ اوپر ہو۔ ٹھیک بازو سے آپریشن والے ہاتھ کو آہستہ سے کمر پر اوپر کی طرف کھینچیں، پھر نیچے لائیں۔ آرام کی حد میں حرکت کریں — یہ حرکت آہستہ آہستہ واپس آتی ہے۔
گھر پر ورزش کا پروگرام، دن میں 3 سے 5 بار
Kieran Hirpara 4.0
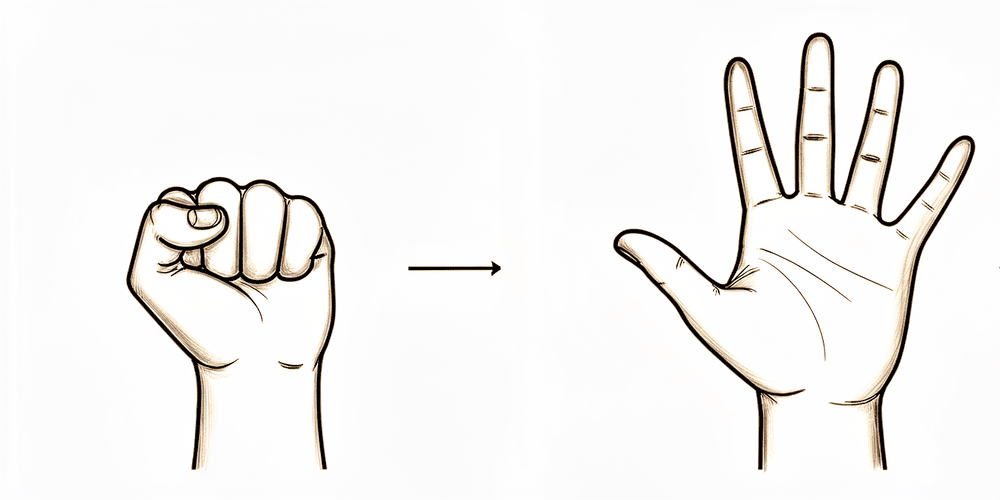
گرفت مضبوط کرنا
پوری مٹھی بند کریں، پھر انگلیوں کو کھول کر سیدھا کریں۔ گرفت کی ورزش کے لیے نرم گیند یا لپیٹی ہوئی جراب دبائی جا سکتی ہے۔ پہلے دن سے کہنی، کلائی اور ہاتھ کو حرکت میں رکھیں۔
اپنے فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
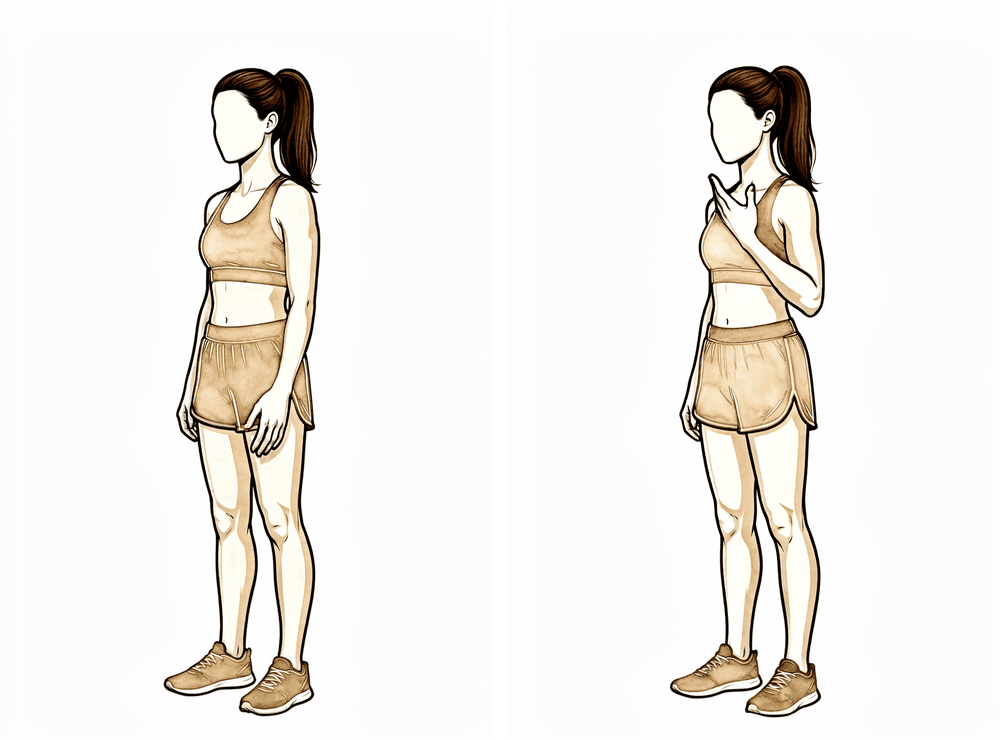
کہنی موڑنا
بازو کا اوپری حصہ پہلو کے ساتھ ٹکا کر، کہنی کو جتنا آرام سے مڑ سکے موڑیں، پھر اسے پوری طرح سیدھا کریں۔ صرف کہنی حرکت کرے — کندھے کو ڈھیلا رکھیں۔ پہلے دن سے کہنی، بازو کا نچلا حصہ، کلائی اور ہاتھ حرکت میں رکھیں۔
اپنے فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
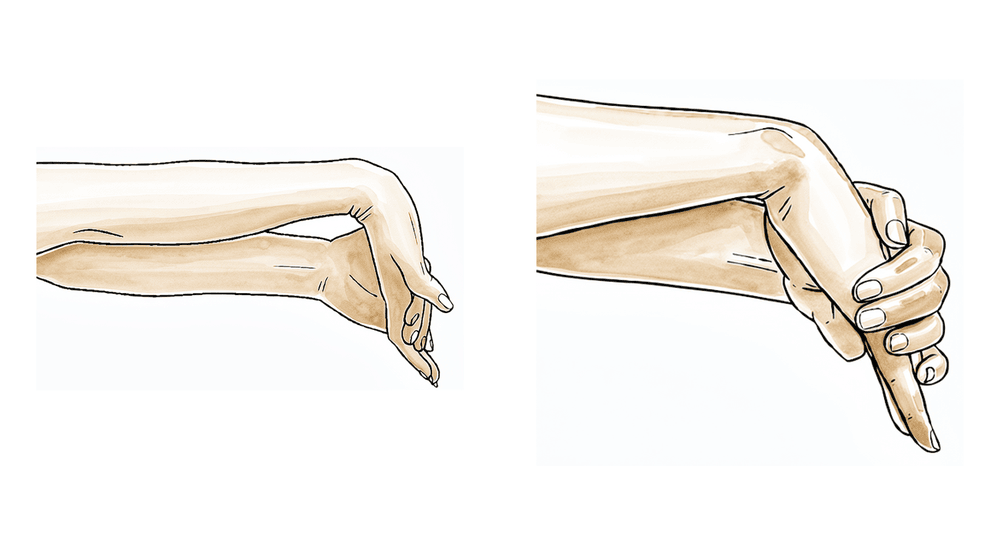
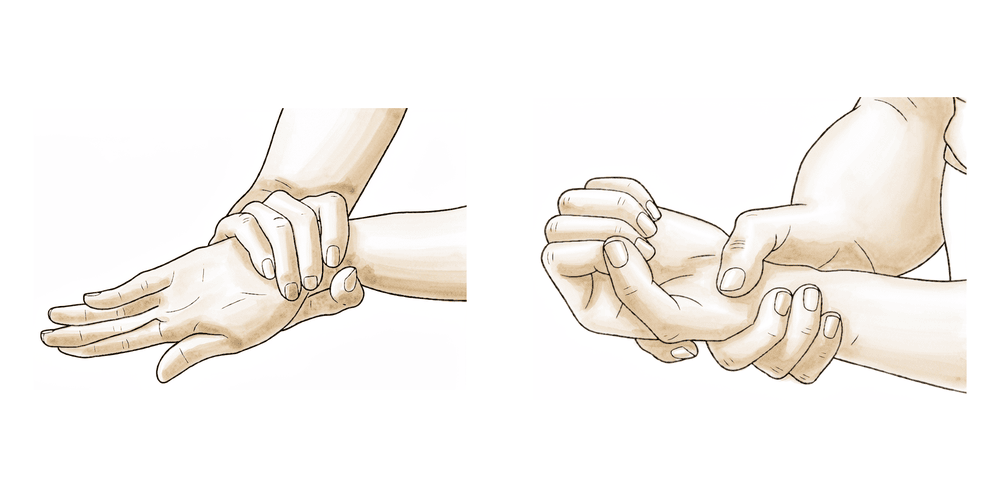
کلائی کی حرکت
بازو سلنگ سے باہر نکال کر، کلائی کو آگے، پیچھے اور دائیں بائیں موڑ کر حرکت میں رکھیں۔ پہلے دن سے پورے بازو کو کام میں رکھنے سے کندھا جلد سنبھلتا ہے۔
اپنے فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
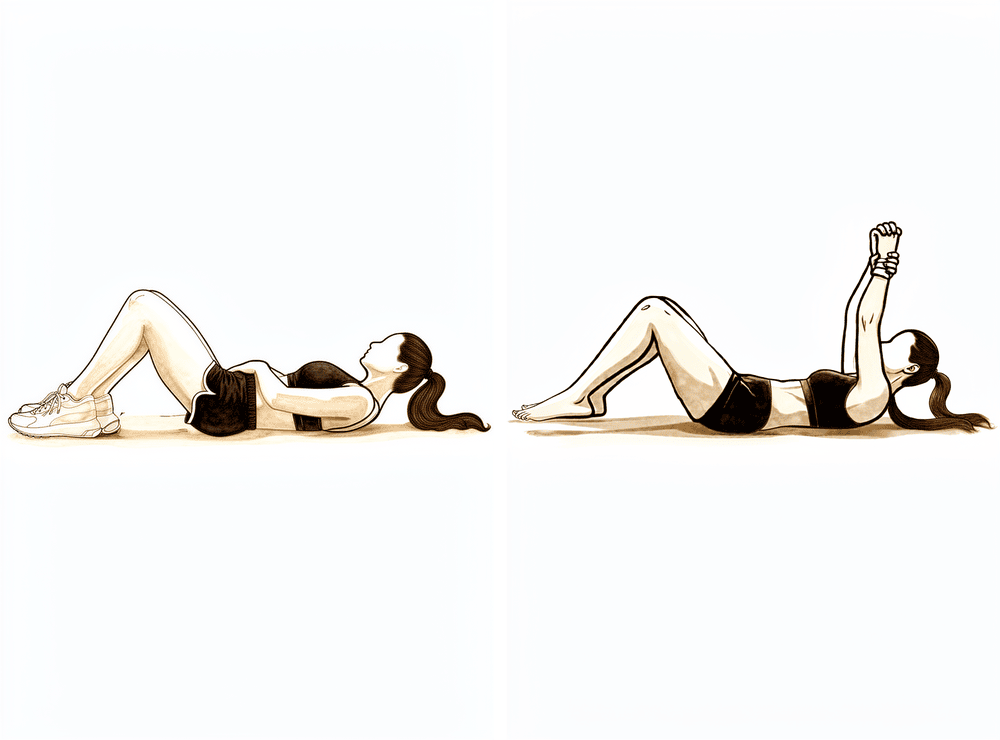
بازو کے نچلے حصے کو گھمانا
کہنی پہلو سے لگا کر اور سیدھے زاویے پر موڑ کر، ہتھیلی کو اوپر چھت کی طرف اور پھر نیچے فرش کی طرف گھمائیں۔ جب کندھا آرام کر رہا ہو تو پہلے دن سے بازو کے نچلے حصے کو حرکت میں رکھیں۔
اپنے فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
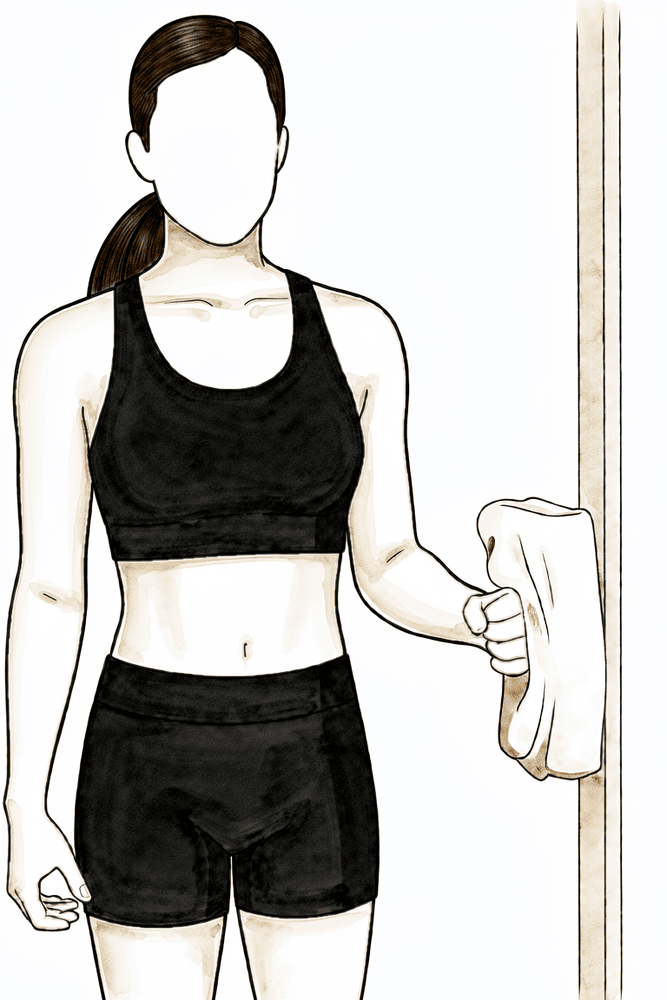
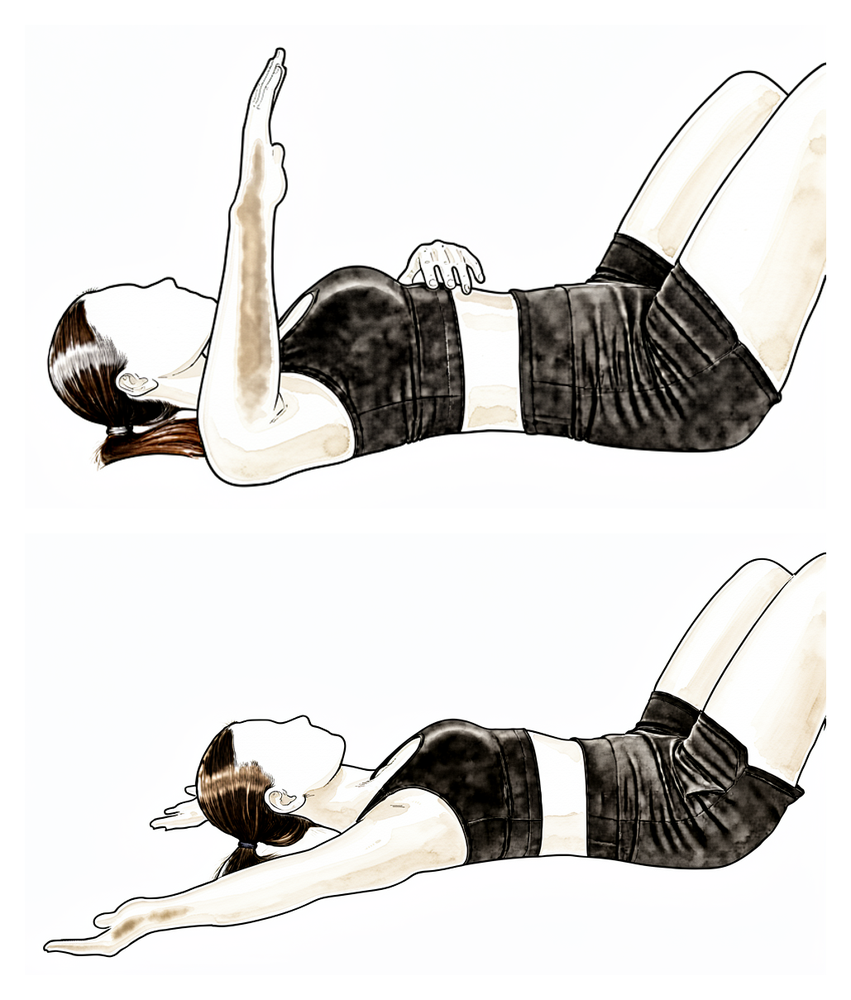
مدد سے بازو کو سامنے سے اوپر اٹھانا (لیٹ کر)
کمر کے بل لیٹیں اور ٹھیک بازو کی مدد سے آپریشن والے بازو کو ہلکے اسٹریچ کے طور پر سر کے اوپر تک اٹھائیں، پھر ٹھیک بازو کی مدد جاری رکھتے ہوئے اسے واپس نیچے لائیں۔ لیٹنے سے کشش ثقل مدد کرتی ہے اور کندھے کے پٹھے ڈھیلے رہتے ہیں۔ آرام کی حد میں کام کریں۔
گھر پر ورزش کا پروگرام، دن میں 3 سے 5 بار
Kieran Hirpara 4.0
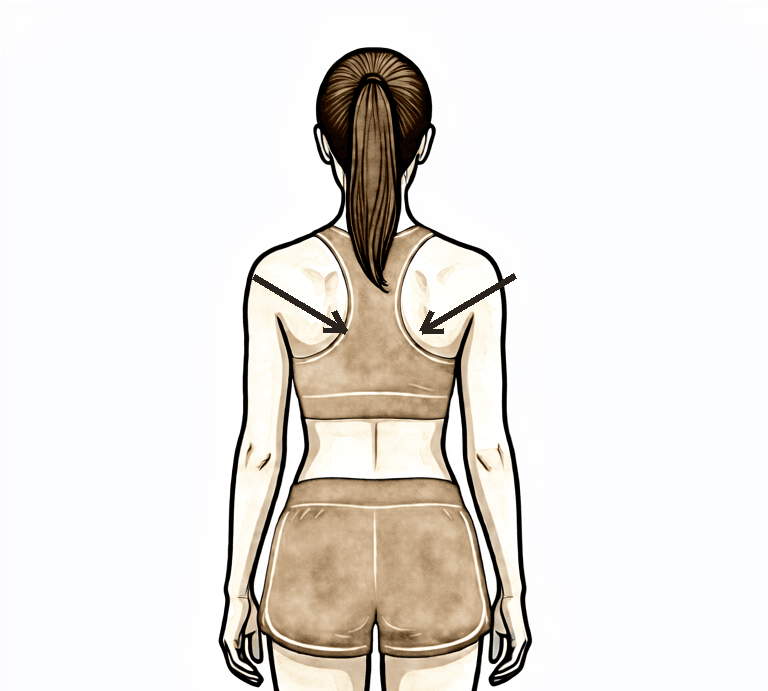
آئسومیٹرک باہر کی طرف گھماؤ
کہنی پہلو سے لگا کر اور سیدھے زاویے پر موڑ کر کھڑے ہوں، ہاتھ کی پشت دیوار یا دروازے کی چوکھٹ سے لگی ہو۔ بازو کو حرکت دیے بغیر آہستہ سے باہر کی طرف اس پر دبائیں، چند سیکنڈ روکیں، پھر ڈھیلا چھوڑ دیں۔ یہ صرف ہلکی آئسومیٹرک (isometric) ورزش ہے — نہ کوئی حرکت ہو اور نہ کوئی زور پڑے۔ آرام کی حد میں رہیں۔
اپنے فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
کندھے کی پچھلی ہڈیوں کو جمانا (scapular setting)
سیدھے بیٹھ کر یا کھڑے ہو کر، کندھے کی پچھلی چپٹی ہڈیوں کو آہستہ سے پیچھے ایک دوسرے کی طرف اور نیچے، کانوں سے دور کھینچیں۔ چند سیکنڈ روکیں، پھر ڈھیلا چھوڑ دیں۔ شروع سے کندھے کی پچھلی ہڈیوں کی درست حرکت باقی پروگرام کو بہتر کام کرنے دیتی ہے۔
اپنے فزیوتھراپسٹ کی ہدایت کے مطابق
پہلے دو ہفتوں کا مقصد درد اور سوجن کو کم کرنا اور ساتھ ساتھ کندھے کو حرکت میں لانا ہے۔ برف باقاعدگی سے لگائیں: پہلے ایک دو ہفتوں میں دن میں تین سے چار بار لگانا عام ہے۔ سلنگ صرف آرام کے لیے ہے: جتنا فائدہ دے اتنا کم یا زیادہ پہنیں، بازو کو اکثر باہر نکالیں، اور جیسے ہی آپ اس کے بغیر آرام محسوس کریں اسے استعمال کرنا چھوڑ دیں۔ بہت سے لوگوں کو یہ گھر سے باہر سب سے زیادہ مفید لگتی ہے، تاکہ لوگ بازو سے نہ ٹکرائیں۔ کندھے کے کسی بھی آپریشن کے بعد کم از کم چھ ہفتے تک گاڑی نہ چلائیں، چاہے سلنگ اتر چکی ہو؛ آپ کے سرجن آپ کو گاڑی چلانے کی اجازت دیں گے، عام طور پر چھ ہفتے والے معائنے پر۔
حرکت فوراً شروع کریں: پہلے دن سے آپ کی کہنی، کلائی اور ہاتھ حرکت میں رہنے چاہئیں، اور ساتھ ہی پینڈولم (pendulum) کی ہلکی ورزشیں اور مدد سے کندھے کی حرکتیں کریں (آپریشن والے بازو کو اوپر اور باہر کی طرف اٹھانے کے لیے دوسرا بازو، چھڑی یا پُلی (pulley) استعمال کریں)۔ ورزشوں سے پہلے اور فزیوتھراپی کی ملاقاتوں سے پہلے اپنی درد کش دوا لیں۔ ابھی صرف ایک حرکت نہیں کرنی: ہاتھ کو جسم کے آگے سے مخالف کندھے کی طرف لے جانا۔
آپ کے فزیوتھراپسٹ کے لیے:
اہداف
- درد اور سوجن کو کم کرنا
- حرکت کی ابتدائی حد: مرحلے کے آخر تک بازو کو سامنے سے اوپر اٹھانا (forward flexion) تقریباً 140 ڈگری اور بازو پہلو کے ساتھ رکھ کر باہر کی طرف گھماؤ (external rotation) تقریباً 40 ڈگری
- گھر پر ورزشوں کا پروگرام خود سے کر سکنا
علاج
- سلنگ صرف آرام کے لیے: آرام کے مطابق پہلے 1 سے 2 ہفتوں کے اندر آہستہ آہستہ کم کر کے بند کر دیں
- برف سے ٹکور (cryotherapy) دن میں 3 سے 4 بار، خاص طور پر ورزش کے بعد
- گردن، کہنی، بازو کے نچلے حصے (forearm)، کلائی اور ہاتھ کی فعال حرکت (active range of motion) فوراً شروع کریں
- پہلے دن سے پینڈولم ورزشیں
- برداشت کے مطابق کندھے کی غیر فعال (passive) اور مدد سے فعال (active-assisted) حرکت: سامنے سے اوپر اٹھانا، باہر کی طرف گھماؤ اور کمر کے پیچھے اندر کی طرف گھماؤ (internal rotation)، پُلی، چھڑی یا چھڑی نما ڈنڈے اور کمر کے بل لیٹ کر کشش ثقل کی مدد والی پوزیشنوں کے ذریعے
- کندھے کی پچھلی چپٹی ہڈی (shoulder blade) کو درست جگہ پر جمانا (scapular setting) اور اس کے اردگرد کی حرکت؛ شروع سے ہی کندھے کی پچھلی ہڈی اور بازو کی ہڈی کی ہم آہنگ حرکت (scapulohumeral rhythm) پر توجہ
- گرفت مضبوط کرنا؛ جتنا درد اجازت دے کندھے کی ہلکی آئسومیٹرک ورزشیں (isometric، پٹھے کو حرکت دیے بغیر زور لگانا)
- ورزشوں اور فزیوتھراپی سیشن سے پہلے درد کش دوا
- گھر پر ورزشوں کا پروگرام دن میں 3 سے 5 بار
احتیاطیں
- ہاتھ کو جسم کے آگے سے دوسری طرف لے جانے (horizontal adduction) سے پرہیز کریں
- ہلکی آئسومیٹرک ورزشوں کے علاوہ کندھے کی کوئی مزاحمتی (resisted) ورزش نہ کریں
- روزمرہ کی ہلکی چیزوں سے زیادہ کچھ نہ اٹھائیں؛ بازو پر وزن نہ ڈالیں (کرسی یا بستر سے بازو کے زور پر نہ اٹھیں)
- چھ ہفتے تک گاڑی نہ چلائیں (یہ کندھے کے ہر آپریشن پر لاگو ہوتا ہے)
اگلے مرحلے میں جانے کی شرائط
- سلنگ چھوٹ چکی ہو اور درد کم ہو رہا ہو
- مدد سے بازو کو تقریباً 140 ڈگری تک اوپر اٹھانا اور تقریباً 40 ڈگری تک باہر کی طرف گھمانا آرام سے ہو سکے
مرحلہ II — حرکت کی حد بحال کرنا (ہفتہ 2 سے 6)
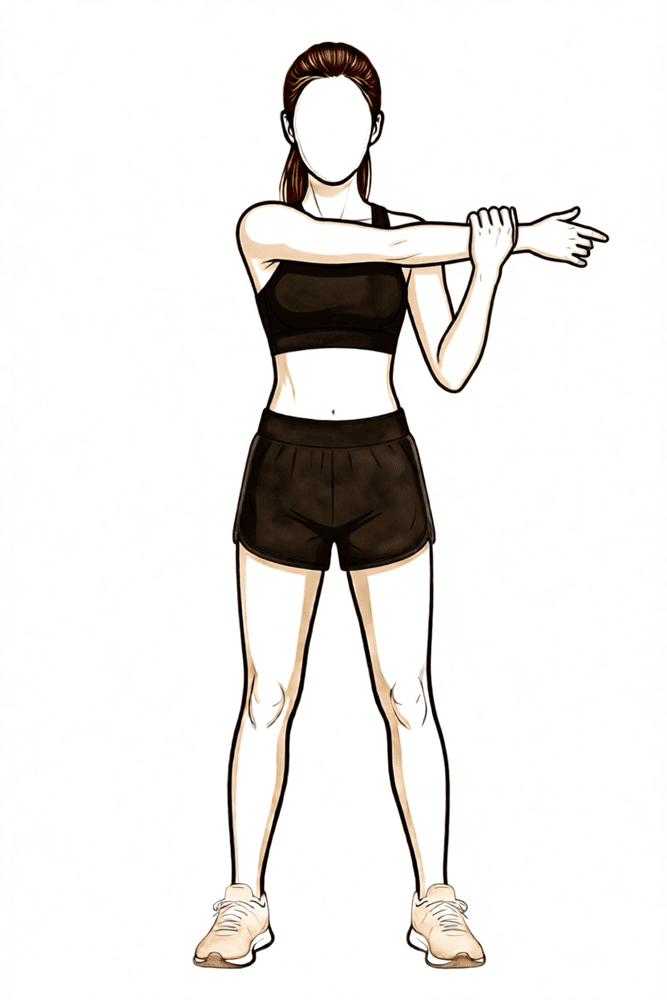
Kieran Hirpara 4.0
سینے کے آگے سے اسٹریچ (cross-body stretch)
آپریشن والے بازو کو سینے کے آگے سے دوسری طرف لائیں اور دوسرے ہاتھ کو کہنی سے اوپر رکھ کر اسے آہستہ سے مزید آگے کھینچیں۔ اسے علامات کے مطابق آہستہ آہستہ دوبارہ شامل کریں — اس آپریشن کے بعد حرکت کے آخر میں کچھ چبھن کا احساس عام ہے اور وقت کے ساتھ ختم ہو جاتا ہے۔
اپنے فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
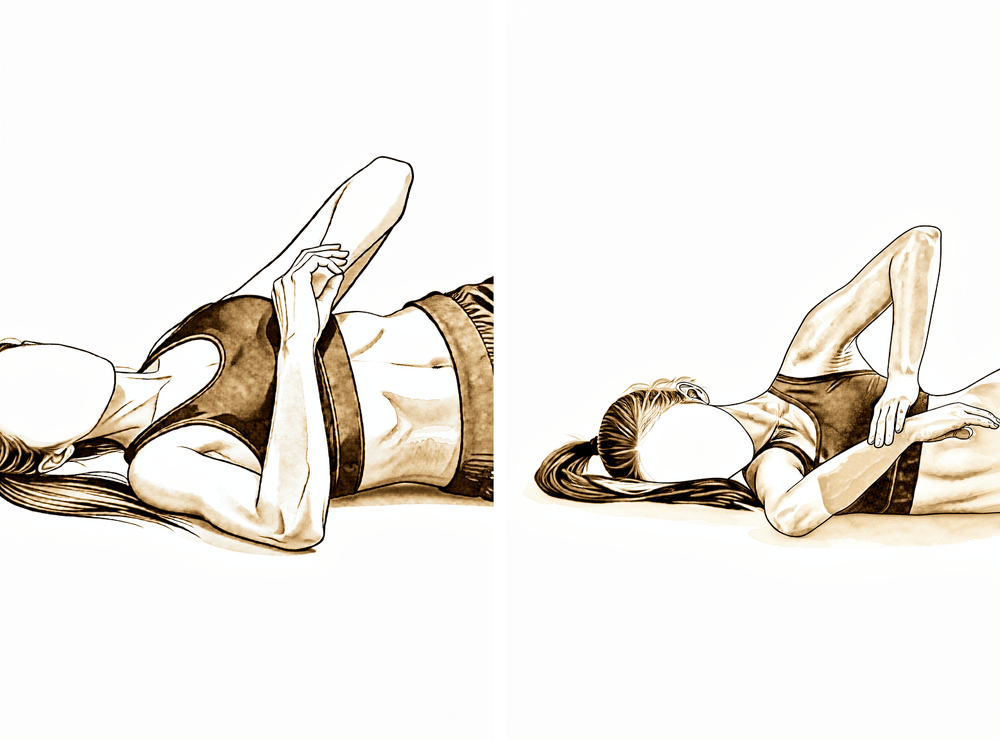
سلیپر اسٹریچ (sleeper stretch)
آپریشن والی کروٹ پر لیٹیں، وہ بازو سامنے کی طرف ہو اور کہنی سیدھے زاویے پر مڑی ہو۔ ٹھیک ہاتھ سے بازو کے نچلے حصے کو آہستہ سے بستر کی طرف دبائیں، یہاں تک کہ کندھے کے پچھلے حصے میں کھنچاؤ محسوس ہو، پھر ڈھیلا چھوڑ دیں۔ یہ ہلکا پچھلا اسٹریچ ہاتھ کو کمر کے پیچھے لے جانے کی صلاحیت بحال کرنے میں مدد کرتا ہے۔ اتنا اسٹریچ کریں کہ واضح تکلیف ہو، تیز درد نہیں۔
اپنے فزیوتھراپسٹ کی ہدایت کے مطابق
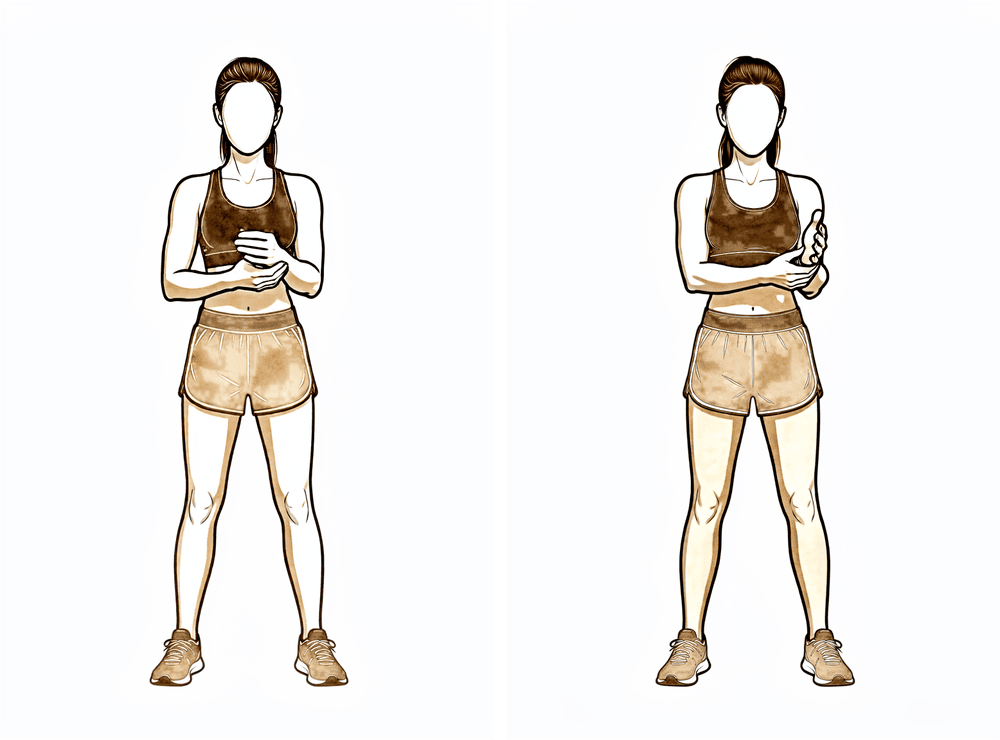
Kieran Hirpara 4.0
ربڑ کی پٹی سے باہر کی طرف گھماؤ
کہنی پہلو سے لگا کر اور سیدھے زاویے پر موڑ کر کھڑے ہوں، اور ایک طرف بندھی ہوئی ربڑ کی پٹی پکڑیں۔ کہنی کو پہلو سے لگائے رکھتے ہوئے بازو کے نچلے حصے کو پٹی کے زور کے خلاف باہر کی طرف گھمائیں، پھر آہستہ سے واپس لائیں۔ جب آپ کی حرکت تقریباً مکمل ہو جائے تب شروع کریں — ہلکی مزاحمت کے ساتھ زیادہ تکرار کریں۔
زیادہ تکرار، کم وزن؛ اپنے فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
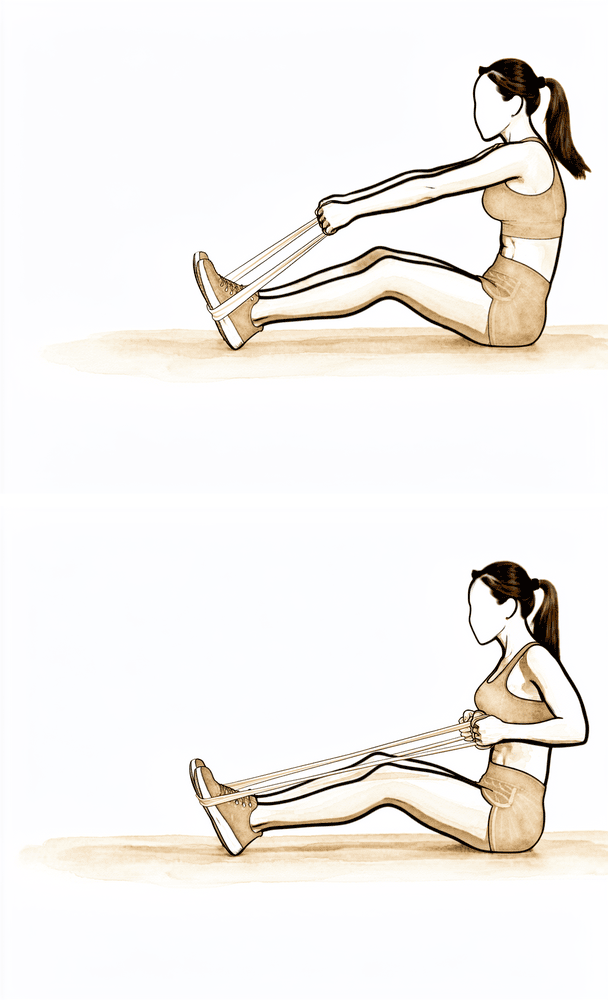
نیچی رو (low row)
اپنے سامنے تقریباً کمر کی اونچائی پر بندھی ہوئی ربڑ کی پٹی پکڑیں۔ بازو کو کافی حد تک سیدھا رکھتے ہوئے اسے پیچھے اور نیچے کولہے کی طرف کھینچیں، کندھے کی پچھلی ہڈی کو نیچے اور پیچھے کی طرف دبائیں، پھر آہستہ سے واپس لائیں۔ اس سے کندھے کی پچھلی ہڈی کے وہ پٹھے مضبوط ہوتے ہیں جو طاقت واپس آنے کے ساتھ کندھے کو مستحکم رکھتے ہیں۔
زیادہ تکرار، کم وزن؛ اپنے فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
لیٹ کر 90/90 پر باہر کی طرف گھماؤ
کمر کے بل لیٹیں، بازو پہلو سے باہر کندھے کی اونچائی پر ہو اور کہنی سیدھے زاویے پر مڑی ہو، تکیے کے سہارے۔ بازو کے نچلے حصے کو آہستہ سے جتنا آرام سے ہو سکے سر کی طرف پیچھے گھمائیں، پھر قابو کے ساتھ واپس لائیں۔ اس سے اٹھی ہوئی پوزیشن میں گھماؤ بحال ہوتا ہے۔
10 بار، اپنے فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
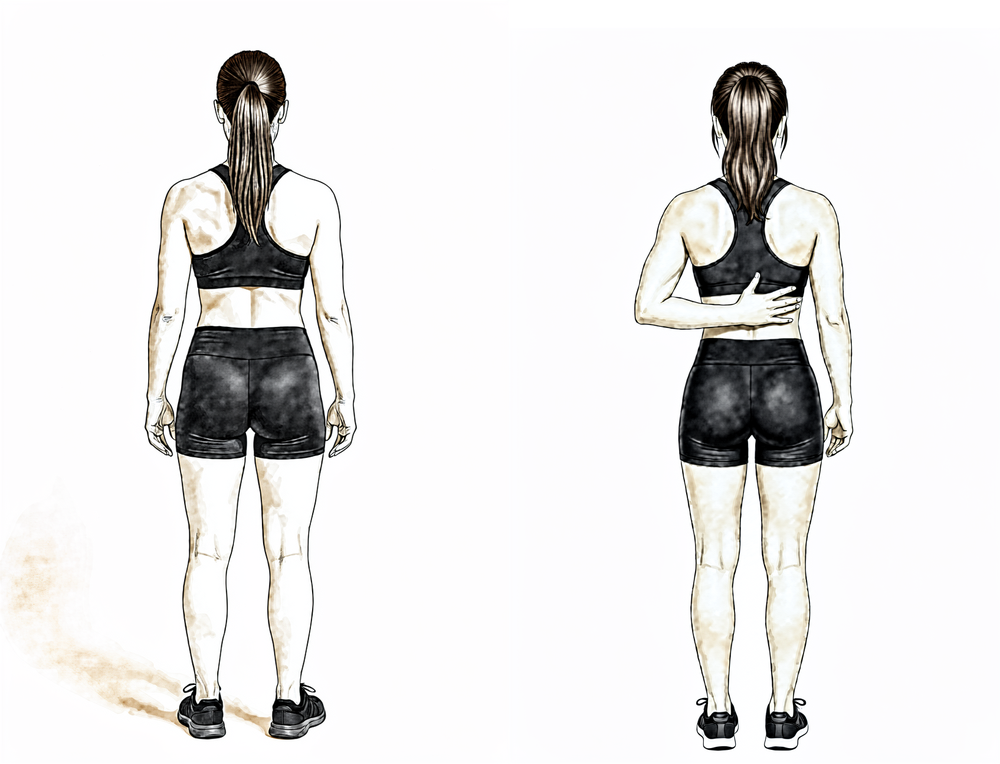
ہاتھ کو کمر کے پیچھے لے جانا
کھڑے ہو کر آپریشن والے ہاتھ کی پشت کمر کے نچلے حصے پر رکھیں اور اپنے پٹھوں کی مدد سے اسے آہستہ سے ریڑھ کی ہڈی کے ساتھ جتنا آرام سے ہو سکے اوپر سرکائیں، پھر نیچے لائیں۔ صرف آرام دہ حد میں حرکت کریں اور کبھی زبردستی نہ کریں۔
اپنے فزیوتھراپسٹ کی ہدایت کے مطابق
سلنگ اترنے کے بعد اس مرحلے میں کندھے کو ہر سمت میں مکمل حرکت کی طرف لے جایا جاتا ہے: پہلے مدد سے حرکت، پھر بازو کی اپنی طاقت سے۔ جب آپ کی حرکت تقریباً مکمل ہو جائے تو روٹیٹر کف اور کندھے کی پچھلی ہڈی کے پٹھوں کو ربڑ کی پٹی (elastic band) اور ہلکے وزن سے آہستہ آہستہ مضبوط کرنا شروع کیا جاتا ہے۔ روزمرہ کاموں کے لیے بازو کو معمول کے مطابق استعمال کریں، لیکن وزن اٹھانا محدود رکھیں (تقریباً 5 کلوگرام سے زیادہ نہیں) اور ایسی کسی بھی چیز سے ابھی رکے رہیں جس میں بازو سے زور سے دھکیلنا پڑے یا اس پر بھاری بوجھ پڑے۔ اس مرحلے کے دوران ہاتھ کو جسم کے آگے سے دوسری طرف لے جانا آرام کے مطابق آہستہ آہستہ دوبارہ شامل کیا جاتا ہے؛ اس حرکت کے آخر میں کچھ چبھن کا احساس عام ہے اور وقت کے ساتھ ختم ہو جاتا ہے۔ بہت سے لوگوں کو اسٹریچ سے پہلے گرم ٹکور اور بعد میں برف مفید لگتی ہے، اور جسم کے نچلے حصے کی ہلکی ورزش جیسے پیدل چلنا، ورزش والی سائیکل یا ہلکی دوڑ عام طور پر تقریباً چوتھے ہفتے سے دوبارہ شروع ہو جاتی ہے۔
آپ کے فزیوتھراپسٹ کے لیے:
اہداف
- مرحلے کے آخر تک تمام سمتوں میں مکمل یا تقریباً مکمل فعال حرکت
- کندھے کی پچھلی ہڈی اور بازو کی ہڈی کی حرکت کا معمول پر آ جانا (scapulohumeral kinematics)
- فعال حرکت تقریباً مکمل ہونے پر روٹیٹر کف اور کندھے کی پچھلی ہڈی کے اردگرد کے پٹھوں کو مضبوط کرنا شروع کریں
علاج
- غیر فعال اور مدد سے فعال حرکت کو بڑھا کر تمام سمتوں میں فعال حرکت تک لے جائیں: سامنے سے اور کندھے کی پچھلی ہڈی کی سمت میں اوپر اٹھانا (flexion اور scapular-plane elevation) مکمل حد کی طرف، بازو پہلو کے ساتھ اور برداشت کے مطابق 90 ڈگری تک باہر اٹھا کر (abduction) باہر کی طرف گھماؤ، اور کمر کے پیچھے اندر کی طرف گھماؤ کے ساتھ جوڑ کی پچھلی جھلی (posterior capsule) کا ہلکا اسٹریچ
- جسم کے آگے سے دوسری طرف لے جانے (cross-body adduction) کی حرکت کو علامات کے مطابق آہستہ آہستہ دوبارہ شامل کریں
- ضرورت کے مطابق ہاتھ سے علاج (manual therapy) اور کندھے کے جوڑ کی موبلائزیشن (glenohumeral mobilisation)
- فعال حرکت تقریباً مکمل ہونے پر آئسومیٹرک ورزشوں سے آگے بڑھ کر ربڑ کی پٹی سے روٹیٹر کف اور کندھے کی پچھلی ہڈی کو سہارا دینے والے پٹھوں کو مضبوط کریں: زیادہ تکرار، کم وزن
- پسند کے مطابق سیشن سے پہلے گرم ٹکور اور بعد میں برف؛ ورزشوں سے پہلے درد کش دوا
- روزمرہ کی معمول کی سرگرمیوں میں درجہ بدرجہ واپسی؛ تقریباً ہفتہ 4 سے جسم کے نچلے حصے کی ہلکی ورزش (پیدل چلنا، ایک جگہ کھڑی ورزش والی سائیکل، ہلکی دوڑ)
احتیاطیں
- وزن اٹھانا ہلکا رکھیں: آپریشن والی طرف تقریباً 5 کلوگرام یا اس سے کم
- حرکت کی آخری حد پر بوجھ کے ساتھ جسم کے آگے سے دوسری طرف لے جانے اور امپنجمنٹ (کندھے میں ٹینڈن کا رگڑ کھانا) والی پوزیشنوں سے پرہیز کریں
- زور سے دھکیلنے والی ورزشیں نہ کریں: بینچ پریس، ڈِپس، پُش اَپس
- اگر کندھے میں جلن (irritation) جلدی بھڑک اٹھتی ہو تو باہر اٹھانے اور گھمانے کو ملا کر (90/90) اسٹریچ کرنا مؤخر کر دیں
اگلے مرحلے میں جانے کی شرائط
- زیادہ تکلیف کے بغیر مکمل یا تقریباً مکمل فعال حرکت
- ربڑ کی پٹی سے طاقت کی ورزشیں درد بھڑکے بغیر برداشت ہو جائیں
مرحلہ III — طاقت بڑھانا اور سرگرمیوں میں واپسی (ہفتہ 6 سے 12)
Kieran Hirpara 4.0
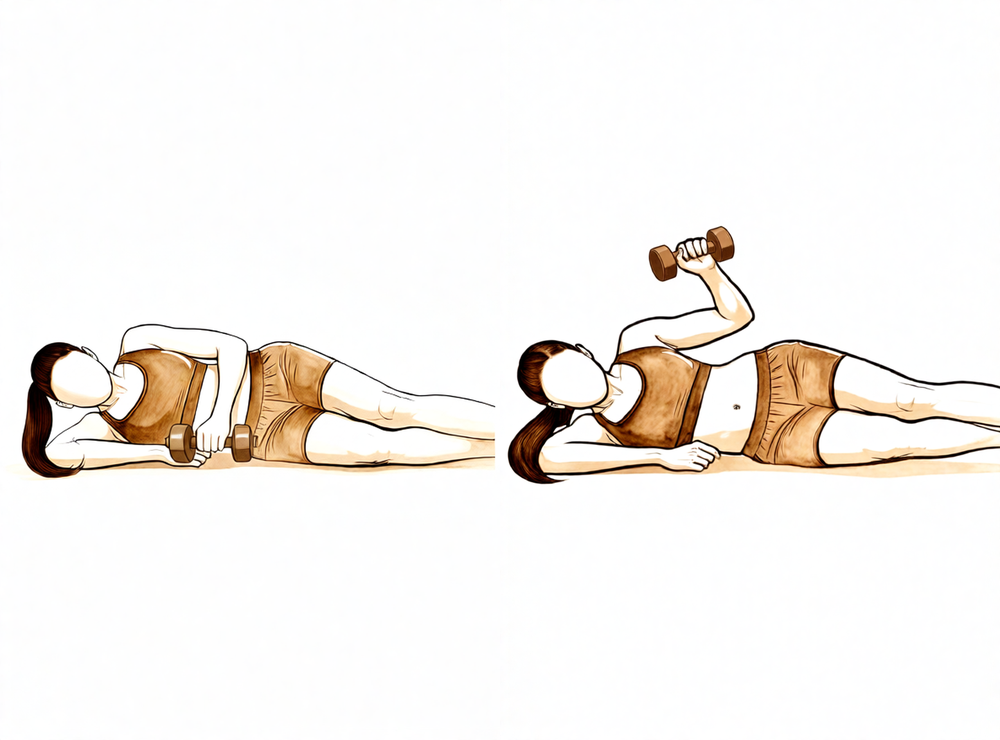
کروٹ کے بل لیٹ کر وزن کے ساتھ باہر کی طرف گھماؤ
اس کروٹ پر لیٹیں جس طرف آپریشن نہیں ہوا، اوپر والی کہنی سیدھے زاویے پر مڑی ہو اور جسم سے لگی ہو۔ ہلکا وزن پکڑ کر بازو کے نچلے حصے کو اوپر چھت کی طرف گھمائیں، پھر آہستہ سے نیچے لائیں۔ اس سے آپ کی روٹیٹر کف (rotator cuff) کو مضبوط کرنے کی ورزش ربڑ کی پٹی سے ڈمبل تک آگے بڑھتی ہے۔
2 سے 3 سیٹ، ہر سیٹ میں 8 سے 15 بار، کم وزن
Kieran Hirpara 4.0
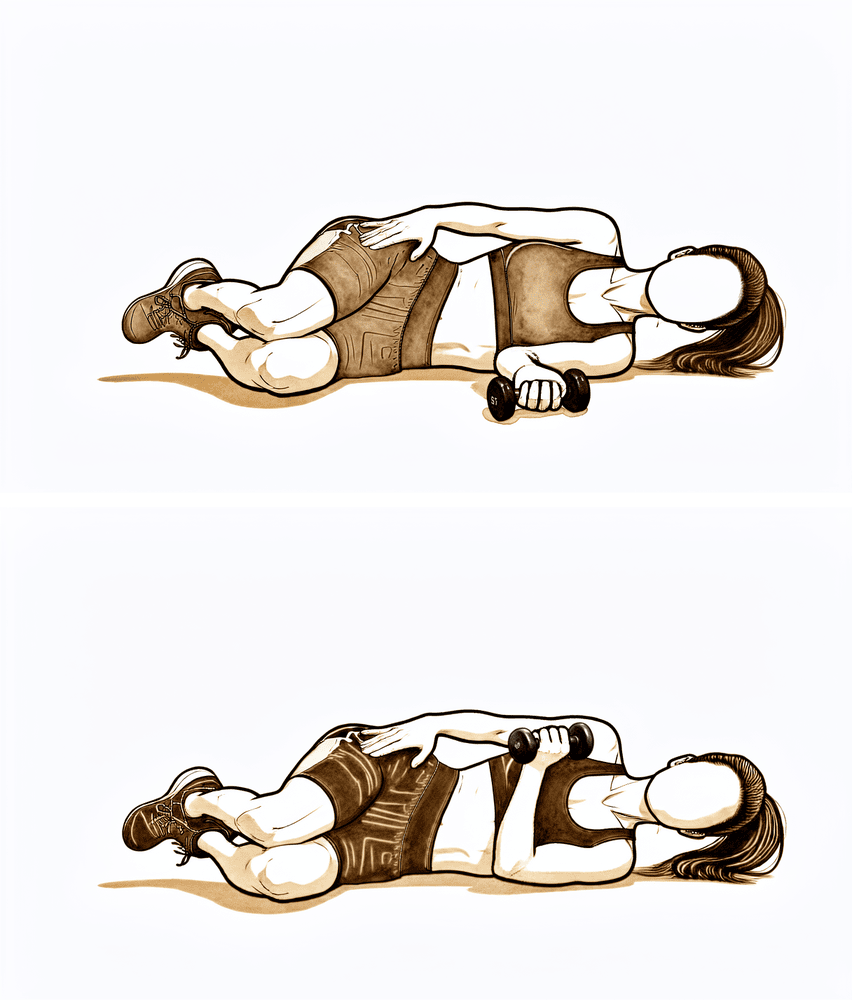
کروٹ کے بل لیٹ کر وزن کے ساتھ اندر کی طرف گھماؤ
آپریشن والی کروٹ پر لیٹیں، اس بازو کی کہنی سیدھے زاویے پر مڑی ہو اور جسم سے لگی ہو۔ ہلکا وزن پکڑ کر بازو کے نچلے حصے کو اوپر جسم کی طرف اٹھائیں، پھر آہستہ سے نیچے لائیں۔ یہ باہر کی طرف گھماؤ والی ورزش کے ساتھ روٹیٹر کف کی مضبوطی میں توازن پیدا کرتی ہے۔
2 سے 3 سیٹ، ہر سیٹ میں 8 سے 15 بار، کم وزن
Kieran Hirpara 4.0
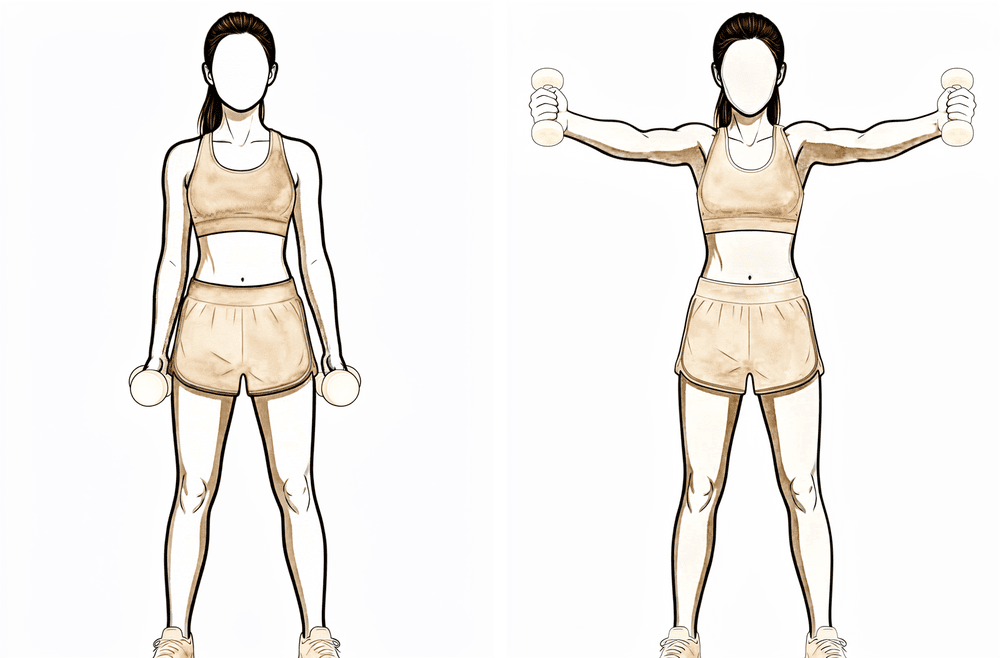
انگوٹھا اوپر رکھ کر بازو اٹھانا (full-can scaption)
ہر ہاتھ میں ہلکا وزن پکڑ کر کھڑے ہوں، بازو اپنے سامنے تھوڑا باہر کی طرف تقریباً 30 ڈگری کے زاویے پر ہوں اور انگوٹھے اوپر کی طرف ہوں۔ بازوؤں کو کندھے کی اونچائی تک اٹھائیں، پھر آہستہ سے نیچے لائیں۔ اس سے ڈیلٹائیڈ (deltoid) اور روٹیٹر کف دونوں ایک آرام دہ درمیانی حد میں ایک ساتھ مضبوط ہوتے ہیں۔
2 سے 3 سیٹ، ہر سیٹ میں 8 سے 15 بار، کم وزن
Kieran Hirpara 4.0
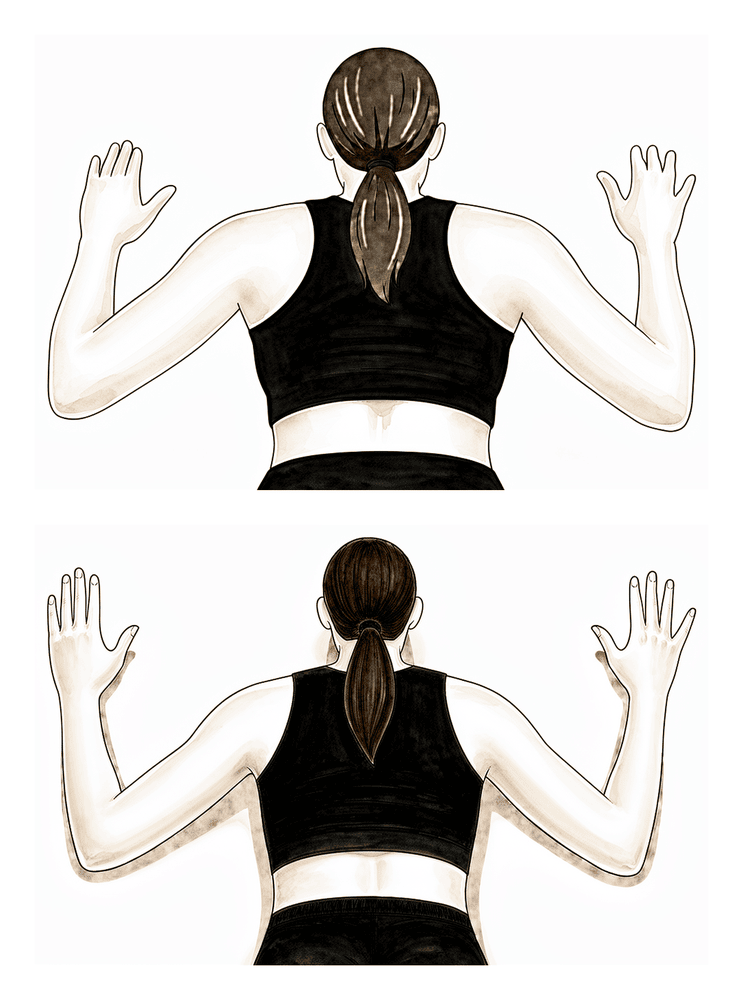
الٹے لیٹ کر W ورزش (prone W)
پیٹ کے بل لیٹیں، بازو پہلوؤں کے ساتھ ہوں۔ کہنیوں کو پیچھے اور نیچے کولہوں کی طرف کھینچ کر W کی شکل بنائیں اور ساتھ ہی کندھے کی پچھلی ہڈیوں کو ایک دوسرے کی طرف دبائیں، پھر آہستہ سے نیچے لائیں۔ اس سے کندھے کی پچھلی ہڈی کے نچلے پٹھے مضبوط ہوتے ہیں جو کندھے کی درست حرکت کو سہارا دیتے ہیں۔
2 سے 3 سیٹ، ہر سیٹ میں 8 سے 15 بار
Kieran Hirpara 4.0
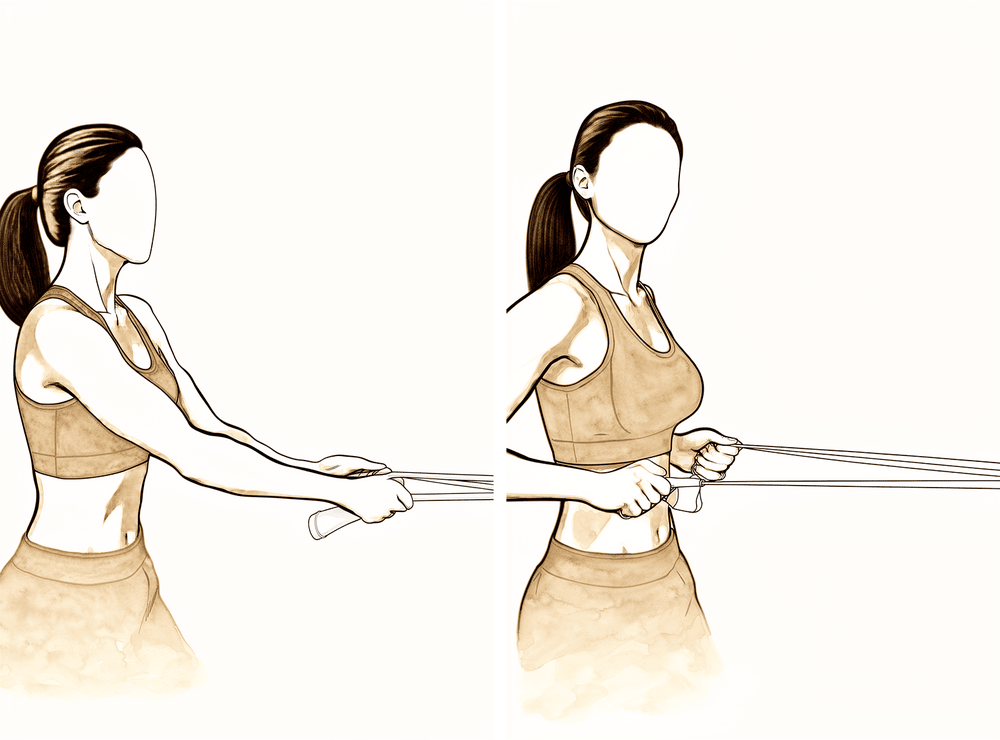
کھڑے ہو کر رو (standing row)
اپنے سامنے ربڑ کی پٹی یا ہلکا وزن پکڑیں اور اسے پیچھے جسم کی طرف کھینچیں، کہنی کو اپنے پیچھے لے جائیں اور کندھے کی پچھلی ہڈی کو اندر کی طرف دبائیں، پھر آہستہ سے واپس لائیں۔ اس سے کمر کے درمیانی حصے اور کندھے کی پچھلی ہڈی کی وہ طاقت بنتی ہے جو سرگرمیوں میں واپسی کے دوران آپ کے کندھے کو سہارا دیتی ہے۔
2 سے 3 سیٹ، ہر سیٹ میں 8 سے 15 بار
Kieran Hirpara 4.0
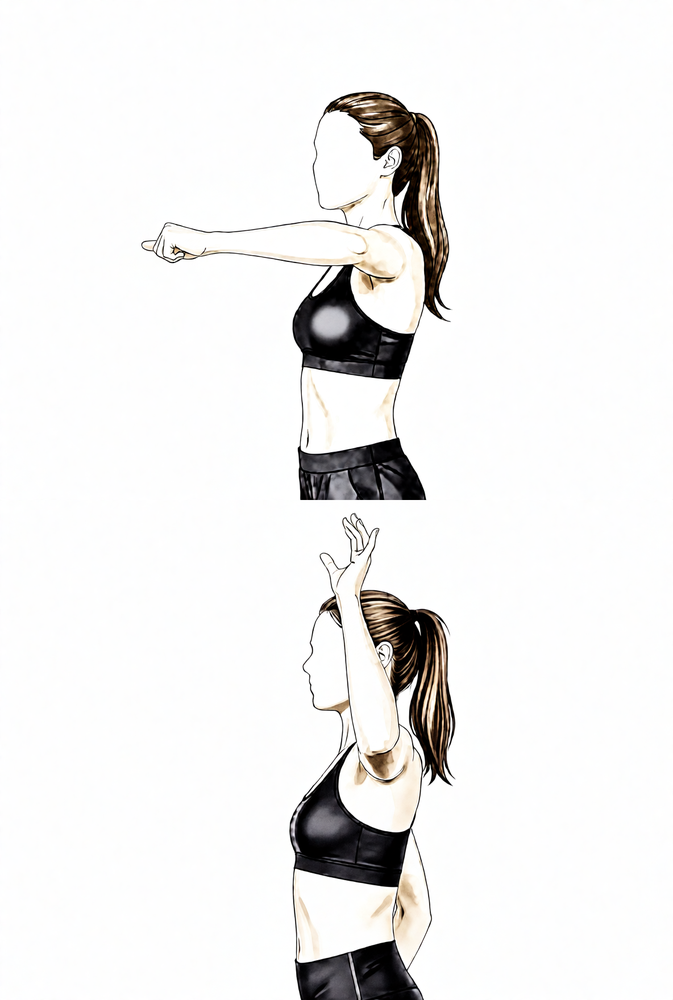
بازو اٹھا کر باہر کی طرف گھماؤ
بازو پہلو سے باہر کندھے کی اونچائی پر رکھ کر اور کہنی 90 ڈگری پر موڑ کر، بازو کے نچلے حصے کو اوپر اور پیچھے کی طرف گھمائیں، پھر قابو کے ساتھ واپس لائیں۔ حرکت کو ہموار اور آرام دہ حد میں رکھیں۔ اس سے اٹھی ہوئی پوزیشن میں باہر کی طرف گھماؤ کی تربیت ہوتی ہے۔
اپنے فزیوتھراپسٹ کی ہدایت کے مطابق — ہلکا اور قابو میں
مکمل حرکت واپس آنے کے بعد توجہ طاقت دوبارہ بنانے اور آپ کو اپنے کاموں پر واپس لانے کی طرف جاتی ہے۔ روٹیٹر کف، ڈیلٹائیڈ (deltoid) اور کندھے کی پچھلی ہڈی کے پٹھوں کے لیے مزاحمتی ورزش ربڑ کی پٹی سے ڈمبل تک بڑھتی ہے، اور ورزش زیادہ عملی ہو جاتی ہے: جم کی ورزش، تیراکی، گیند پھینکنے والوں کے لیے درجہ بدرجہ پھینکنے کا پروگرام، اور کام کی ذمہ داریوں اور کھیل میں مرحلہ وار واپسی۔ زیادہ تر لوگ اسی مرحلے میں، تقریباً آٹھ سے بارہ ہفتوں کے درمیان، کھیل اور بھاری کام پر واپس آتے ہیں، اور اس میں کیلنڈر کے بجائے آرام اور طاقت کو رہنما بنایا جاتا ہے۔ زور سے دھکیلنے والی وہ ورزشیں جو اے سی جوڑ پر سب سے زیادہ بوجھ ڈالتی ہیں (بینچ پریس، ڈِپس اور پُش اَپس) سب سے آخر میں دوبارہ شامل کی جاتی ہیں، ہلکے وزن اور کم گہرائی سے شروع کر کے۔
آپ کے فزیوتھراپسٹ کے لیے:
اہداف
- کندھے کے ڈھانچے (shoulder girdle) کی طاقت، برداشت اور اعصاب اور پٹھوں کے باہمی کنٹرول (neuromuscular control) کو بحال کرنا
- کام کی ذمہ داریوں، تفریحی سرگرمیوں اور کھیل کی مخصوص تربیت میں درجہ بدرجہ واپسی
علاج
- روٹیٹر کف، ڈیلٹائیڈ اور کندھے کی پچھلی ہڈی کو سہارا دینے والے پٹھوں کے لیے بتدریج بڑھتی مزاحمتی ورزش: ربڑ کی پٹی سے ہلکے ڈمبل تک، عام طور پر 2 سے 3 سیٹ، ہر سیٹ میں 8 سے 15 بار
- ایکسینٹرک ورزش (eccentric، پٹھے کے لمبا ہوتے ہوئے زور لگانا)، کلوزڈ چین ورزش (closed-chain، ہاتھ کسی سطح پر ٹکا کر) اور مرحلے کے آخر میں، جہاں مریض کے کھیل سے متعلق ہو، پلائیومیٹرک مشقیں (plyometric، تیز اور جھٹکے دار حرکت والی مشقیں) شامل کریں
- عملی اور کھیل کی مخصوص تربیت: تیراکی، گیند پھینکنے والوں کے لیے وقفوں والا پھینکنے کا پروگرام (interval throwing program)، کنٹرول شدہ حالات میں کھیل کی مشقیں
- شرائط پوری ہونے کی بنیاد پر کام کی مکمل ذمہ داریوں اور کھیل میں درجہ بدرجہ واپسی
احتیاطیں
- اے سی جوڑ پر بوجھ ڈالنے والی دھکیلنے کی ورزشیں (بینچ پریس، ڈِپس، پُش اَپس) سب سے آخر میں دوبارہ شامل کریں: ہلکے وزن اور کم حد سے شروع کریں، اور کہنیوں کو جسم کی لکیر سے نیچے یا پیچھے جانے سے روکیں
- آگے بڑھنا علامات کے مطابق ہی رہے: جلن (irritation) والا اے سی جوڑ بوجھ میں تھوڑی دیر کی کمی سے ٹھیک ہوتا ہے، درد کے باوجود زور لگاتے رہنے سے نہیں
اگلے مرحلے میں جانے کی شرائط
- مکمل، درد کے بغیر عملی حرکت
- بوجھ ڈالنے پر آپریشن والی جگہ پر نہ درد ہو اور نہ چھونے پر درد
- جانچ میں طاقت دوسری طرف کے قریب پہنچ رہی ہو
مرحلہ IV — مکمل سرگرمیوں میں واپسی (ہفتہ 12 اور اس کے بعد)
Kieran Hirpara 4.0
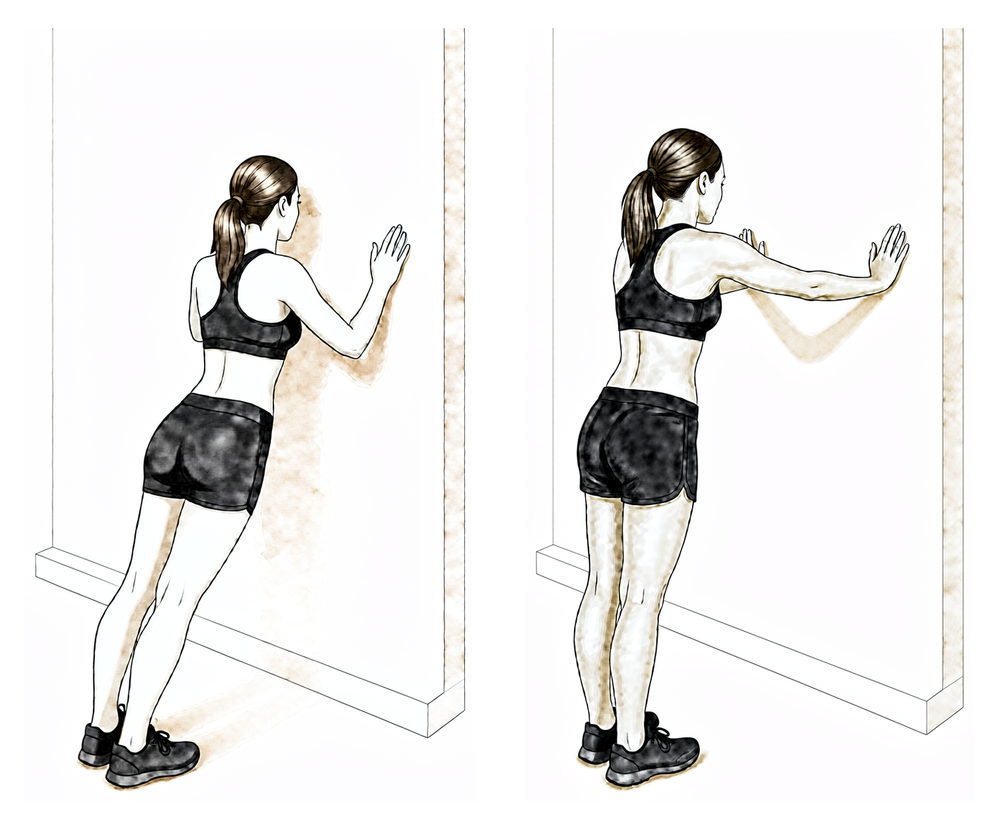
پُش اَپ پلس (push-up plus)
یہ زور سے دھکیلنے والی ورزشوں میں مرحلہ وار واپسی کا حصہ ہے، اس لیے یہ سب سے آخر میں آتی ہے۔ دیوار کے سہارے یا گھٹنوں کے بل کم گہرائی سے شروع کریں، اور کہنیوں کو جسم کی لکیر سے پیچھے جانے سے روکیں۔ ہر پُش اَپ کے اوپر پہنچ کر تھوڑا اور دھکیلیں تاکہ کمر کا اوپری حصہ گول ہو جائے، پھر قابو کے ساتھ نیچے آئیں۔ گہرائی اور وزن صرف اسی صورت میں بڑھائیں جب اے سی جوڑ (AC joint) آرام دہ رہے — اس جگہ پر دکھن واپس آنے کا مطلب ہے کہ ورزش کم کی جائے۔
اپنے فزیوتھراپسٹ کی ہدایت کے مطابق
آخری مرحلہ بغیر کسی پابندی کے سرگرمیوں میں واپسی کا ہے۔ روزمرہ زندگی اور زیادہ تر کھیل عموماً اس وقت سے کافی پہلے واپس آ چکے ہوتے ہیں؛ اب صرف سب سے بھاری بوجھ باقی رہ جاتا ہے۔ جم میں دھکیلنے کی طاقت بتدریج دوبارہ بنائی جاتی ہے، اور بینچ پریس میں پہلے جیسی کارکردگی پر واپس آنے میں تقریباً چار ماہ تک لگ سکتے ہیں۔ جن کھلاڑیوں کے کھیل میں بار بار سر سے اوپر بازو چلانا پڑتا ہے انہیں سرجری کے بعد تقریباً دو سے چار ماہ میں واپس لایا جاتا ہے۔ کھیل اور بھاری کام پر مکمل واپسی کی تصدیق آپ کے فالو اپ معائنے پر کی جاتی ہے، جس کی بنیاد مکمل حرکت، بوجھ ڈالنے پر آرام اور تسلی بخش معائنہ ہے۔
آپ کے فزیوتھراپسٹ کے لیے:
اہداف
- کام، جم اور کھیل میں بغیر پابندی کے واپسی
- طویل مدت تک کندھے کے ڈھانچے کی طاقت اور حرکت کے درست طریقے کو برقرار رکھنا
علاج
- برداشت کے مطابق جم اور کھیل کی مخصوص کنڈیشننگ کو آگے بڑھائیں، جس میں بتدریج بھاری دھکیلنے کی ورزشیں شامل ہیں اور ایسی تکنیک پر توجہ دی جائے جو اے سی جوڑ پر زور کو محدود رکھے (کنٹرول شدہ گہرائی، کہنیاں جسم کی لکیر سے پیچھے نہ جائیں)
- جہاں متعلق ہو، وقفوں والا پھینکنے کا پروگرام اور سر سے اوپر والے کھیلوں کی درجہ بدرجہ مشقیں مکمل کریں
احتیاطیں
- آگے بڑھنا علامات کے مطابق ہی رہے: کسی خاص وزن اٹھانے پر اے سی جوڑ کی جگہ پر بار بار دکھن ہونا اس بات کا اشارہ ہے کہ آگے بڑھنے سے پہلے وزن یا تکنیک بدلی جائے
اپنے پروٹوکول کے بعد
اوپر دیے گئے مراحل ہنسلی کی ہڈی کا بیرونی سرا نکالنے کے بعد بحالی کے شائع شدہ پروٹوکولز سے اخذ کیے گئے ہیں (Saint Louis University Department of Orthopaedic Surgery، University of Utah Sports Medicine، Sports Surgery New York، Palm Beach Orthopaedic Institute، OrthoVirginia اور Specialty Physicians of Illinois)، اور ہفتوں کی حدیں مقررہ نہیں بلکہ عام اندازے کے طور پر دی گئی ہیں۔ آپ کی بحالی میں رہنمائی آپ کا فزیوتھراپسٹ، پریکٹس کے ساتھ مل کر، انفرادی طور پر اس بنیاد پر کرتا ہے کہ آپ کا کندھا کیسے ٹھیک ہو رہا ہے۔ یہ صفحہ پریکٹس کے صحت یابی کے عمومی مشوروں کے ساتھ کام کرتا ہے؛ دیکھیں آپریشن کے بعد درد پر قابو پانا اور زخم کی دیکھ بھال۔ خود آپریشن کے بارے میں جاننے کے لیے دیکھیں ہنسلی کی ہڈی کا بیرونی سرا نکالنا۔
اس آپریشن اور اس کے بعد بحالی کے پیچھے طبی شواہد (جن میں کھلے اور دوربین والے آپریشن کا موازنہ، کتنی ہڈی نکالی جاتی ہے اور کیوں، اور وہ شائع شدہ پروٹوکولز شامل ہیں جن سے یہ صفحہ اخذ کیا گیا ہے) مکمل حوالوں کے ساتھ شواہد والے حصے میں بیان کیے گئے ہیں، جو اس صفحے کے اوپر سے پی ڈی ایف کی صورت میں دستیاب ہے۔
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Distal Clavicle Excision (Mumford) — Surgical Rationale & Post-operative Rehabilitation
Topic scope: the evidence underpinning distal clavicle excision (DCE) — also called distal clavicle resection, AC joint excision, or the Mumford procedure — for the two main indications (acromioclavicular [AC] joint osteoarthritis and distal clavicular osteolysis, the "weightlifter's shoulder"), and the post-operative rehabilitation that follows. Covers open vs arthroscopic technique, direct vs indirect (bursal) approach, how much bone to resect, the iatrogenic-instability risk of over-resection, and the (consensus-based) phased rehab timeline.
Defining principle of the rehab here: DCE removes a few millimetres of worn bone from the end of the collarbone and repairs nothing that needs months of protection — provided the AC ligaments and superior/posterior capsule are preserved. So (like a debridement or subacromial decompression, and unlike a cuff repair, labral repair or AC-joint stabilisation) this is an early-motion pathway: a short sling for comfort only, movement from day one, strengthening as range returns. The single important caveat runs the other way: if the surgeon resects too much bone, or the stabilising AC ligaments/capsule are violated, the joint can become iatrogenically unstable — which is why technique (resection amount, ligament preservation) matters more here than the rehab calendar. The two operation-specific quirks the rehab respects are that cross-body (horizontal adduction) movement compresses the resected area and is the slowest to settle, and heavy pressing (bench press, dips, push-ups) loads the AC joint hardest and returns last.
A. THE OPERATION & ITS INDICATIONS
DCE removes the worn or eroded outer end of the clavicle so the acromion and clavicle no longer grind at the AC joint. Two indications dominate:
- AC joint osteoarthritis — degenerative wear, often with a history of prior AC injury or simply age-related change. Surgery follows failed non-operative care (activity modification, analgesia, AC joint corticosteroid injection).
- Distal clavicular osteolysis ("weightlifter's shoulder") — atraumatic, repetitive-microtrauma resorption of the distal clavicle seen in weightlifters and overhead athletes. Activity modification and rehabilitation are first-line; injection or surgery is reserved for refractory cases or athletes unwilling to stop loading [StatPearls 2023; Charron 1998].
DCE is frequently combined with subacromial decompression (for room/co-existing impingement) and the rehab is unchanged by that addition. If a rotator cuff repair is also performed, the slower protected cuff-repair pathway takes over.
B. EVIDENCE BY THEME
1. Open vs arthroscopic — equivalent long-term outcome, faster arthroscopic recovery
A randomised, prospective trial (Robertson et al., corpus, DOI 10.1016/j.jse.2006.10.006) and a systematic review (Pensak et al., Arthroscopy 2010) found similar long-term functional outcomes for open and arthroscopic DCE, with both arthroscopic techniques exceeding 90% good/excellent results. Across measures there was a trend toward earlier or better outcomes after arthroscopic treatment — less post-operative pain and a quicker return to daily activities — without a difference in the final result [Robertson RCT; Pensak SR 2010]. A second comparative cohort reached the same conclusion (corpus, DOI 10.1177/0363546511419633). Moderate (RCT + SR + cohort).
2. Direct vs indirect (bursal) arthroscopic approach — direct is faster
Among arthroscopic techniques, the direct (superior, top-down) approach permits a quicker return to athletic activity than the indirect/bursal approach, with equivalent long-term results — one comparison reporting a mean return to sport of ~21 days (direct) vs ~42 days (indirect) [Pensak SR 2010; arthroscopic-approach comparison]. Moderate.
3. How much bone to resect — and why over-resection is dangerous
This is the central technical controversy and the reason DCE rehab cannot be reduced to a calendar:
- The stabilising superior and posterior AC ligament/capsule runs from the anterior acromion to the posterior distal clavicle, and the coracoclavicular (trapezoid) ligament inserts on the clavicle undersurface roughly 22–25 mm from the tip [Renfree; capsule/ligament-insertion cadaveric study, corpus DOI 10.1016/j.arthro.2009.04.072; clavicular-strut cadaveric study, corpus DOI 10.1016/j.jse.2013.01.004].
- Anatomic work suggests as little as ~2.3–2.6 mm of resection can begin to violate the superior AC ligament [Renfree, via PMC6930955]; biomechanical models show AC joint anteroposterior translation increases after either open or arthroscopic excision, and stability falls as the resection lengthens [Blazar; resection-length biomechanical model, corpus DOI 10.1016/j.arthro.2007.07.004; DCE-vs-symmetric-resection biomechanics, corpus DOI 10.1177/0363546512469873].
- The practical consensus is to resect enough to abolish bony contact but no more — commonly quoted as ~5 mm (sufficient to clear contact in cadaveric models) up to ~8 mm, and not beyond ~8 mm, preserving the posterior/superior capsule and AC ligaments [PMC6930955; StatPearls 2023; resection-length biomechanics, corpus DOI 10.1016/j.arthro.2007.07.004].
- Over-resection or capsular violation can produce iatrogenic AC instability — a recognised (though uncommon) cause of persistent pain after DCE that may itself require ligament reconstruction [iatrogenic-instability case, PMC6930955; Painful Conditions of the AC Joint, corpus DOI 10.5435/00124635-199905000-00004].
Moderate (cadaveric/biomechanical + anatomic + expert consensus); exact safe threshold is debated.
4. Outcomes & return to activity
DCE is a reliable, high-satisfaction operation for the right indication — arthroscopic series report >90% good/excellent results [Robertson RCT; Pensak SR 2010]. For osteolysis in weightlifters, an arthroscopic-resection series reported return to sport at a mean of ~3 days and to the preoperative weight-training program at ~9 days, remaining asymptomatic and able to progress load beyond pre-operative levels at ~19-month follow-up [Charron, Am J Sports Med 1998, PMID 9548111]. Across the literature, most everyday activity returns within weeks and heavy pressing/overhead sport over ~3–4 months, consistent with the published rehab protocols. Moderate (cohort). A noted exception: worse ("poor") results cluster in patients with pre-existing post-traumatic AC instability or Workers'-Compensation claims [Pensak SR 2010] — DCE alone does not fix an unstable joint.
C. PHASED POST-OPERATIVE TIMELINE (isolated DCE ± subacromial decompression)
Week ranges are typical, not fixed — progression is criteria-based, guided by the physiotherapist.
| Phase | Window | Sling | ROM / use | Strengthening | Operation-specific notes |
|---|---|---|---|---|---|
| I — Early recovery & movement | Week 0–2 | Comfort only; weaned/discarded within 1–2 weeks | Elbow/wrist/hand + pendulums from day 1; passive + active-assisted shoulder elevation/ER/behind-the-back IR; scapular setting | Grip; gentle isometrics as pain allows | Avoid cross-body (horizontal) adduction — it compresses the resected area. No driving in the sling; no weight-bearing through the arm |
| II — Restoring range | Week 2–6 | Off | Progress assisted → active ROM to full in all planes; reintroduce cross-body adduction gradually (end-range pinching is common, settles) | Begin cuff + scapular band work once active range near full; lifting ≤ ~5 kg | Light lower-body conditioning (walk/bike/jog) from ~wk 4 |
| III — Strengthening & return | Week 6–12 | Off | Full functional ROM | Bands → dumbbells; functional + sport-specific; most return to sport/heavier work ~8–12 wk | Reintroduce AC-loading presses (bench/dips/push-ups) last — light, shallow depth, elbows not behind the body line |
| IV — Return to full activity | Week 12+ | Off | Full | Progressive heavy pressing; return to previous bench performance can take ~4 months; overhead athletes progressed over ~2–4 months | Symptom-guided — recurrent AC ache with a lift = adjust load/technique before progressing |
The phased structure is drawn from published surgeon/physiotherapy protocols (Saint Louis University; University of Utah Sports Medicine; Sports Surgery New York; Palm Beach Orthopaedic Institute; OrthoVirginia; Specialty Physicians of Illinois — see Citations). These are consensus/expert documents; no rehab RCT defines the optimal post-DCE regimen.
D. KEY CONTROVERSIES / EVIDENCE QUALITY
- How much bone to resect is the real debate, not the rehab. Too little leaves residual bony contact; too much risks iatrogenic instability. The safe window (~5–8 mm, capsule preserved) is supported by cadaveric/biomechanical and anatomic work, not by an RCT — exact thresholds vary by source. Moderate, technique-dependent.
- Open vs arthroscopic, direct vs indirect. Long-term outcomes converge; arthroscopic (and specifically the direct approach) recovers faster. Moderate (RCT + SR).
- Patient selection matters more than approach. Pre-existing AC instability and Workers'-Compensation status predict poorer results — DCE treats a worn/eroded joint, not an unstable one. Moderate.
- The rehab protocol itself is consensus. Phase timings come from surgeon patient-guidance protocols, not a rehab trial. Weak/consensus.
E. EVIDENCE STRENGTH FLAGS (summary)
- MODERATE (RCT / SR): open vs arthroscopic equivalence with faster arthroscopic recovery (Robertson RCT; Pensak SR 2010, >90% good/excellent); direct > indirect for return speed.
- MODERATE (cadaveric / biomechanical / anatomic): resection-length vs stability relationship and the iatrogenic-instability mechanism (resection-length model, corpus DOI 10.1016/j.arthro.2007.07.004; DCE-vs-symmetric biomechanics, corpus DOI 10.1177/0363546512469873; capsule/ligament insertions, corpus DOI 10.1016/j.arthro.2009.04.072).
- MODERATE (cohort): osteolysis-in-weightlifters return-to-sport (Charron 1998); high overall satisfaction; poorer results with pre-existing instability / WorkCover.
- WEAK / CONSENSUS: the post-operative rehabilitation protocol (surgeon patient-guidance documents; no defining rehab RCT); the exact "safe" resection threshold.
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Robertson WJ, et al. Arthroscopic versus open distal clavicle excision: comparative results at six months and one year from a randomized, prospective clinical trial. J Shoulder Elbow Surg. 2007. DOI: 10.1016/j.jse.2006.10.006
- Arthroscopic versus open distal clavicle excision (comparative cohort). Am J Sports Med. 2011. DOI: 10.1177/0363546511419633
- The biomechanical stability of distal clavicle excision versus symmetric acromioclavicular joint resection. Am J Sports Med. 2013. DOI: 10.1177/0363546512469873
- Arthroscopic distal clavicle resection: a biomechanical analysis of resection length and joint compliance in a cadaveric model. Arthroscopy. 2007. DOI: 10.1016/j.arthro.2007.07.004
- Analysis of the capsule and ligament insertions about the acromioclavicular joint: a cadaveric study. Arthroscopy. 2009. DOI: 10.1016/j.arthro.2009.04.072
- Acromioclavicular joint ligamentous system contributing to clavicular strut function: a cadaveric study. J Shoulder Elbow Surg. 2013. DOI: 10.1016/j.jse.2013.01.004
- Painful conditions of the acromioclavicular joint. J Am Acad Orthop Surg (JAAOS). 1999. DOI: 10.5435/00124635-199905000-00004
Literature (URLs)
- Pensak M, et al. Open versus arthroscopic distal clavicle resection (systematic review; >90% good/excellent, direct > indirect return). Arthroscopy. 2010. PMID 20434670. https://pubmed.ncbi.nlm.nih.gov/20434670/
- Charron KM, et al. Arthroscopic distal clavicle resection for isolated atraumatic osteolysis in weight lifters (return to sport ~3 d, training ~9 d). Am J Sports Med. 1998. PMID 9548111. https://pubmed.ncbi.nlm.nih.gov/9548111/
- Distal clavicular osteolysis (cause, activity-modification first line, ~8 mm resection preserving AC ligaments). StatPearls. 2023. https://www.ncbi.nlm.nih.gov/books/NBK582148/
- Distal clavicular augmentation with AC and CC ligament reconstruction in iatrogenic AC instability (~5 mm safe-resection guidance; Renfree ~2.3–2.6 mm violates superior AC ligament; trapezoid 22–25 mm from tip; Blazar AP-translation increase). PMC6930955. https://pmc.ncbi.nlm.nih.gov/articles/PMC6930955/
- A sports medicine clinician's guide to the diagnosis and management of distal clavicular osteolysis. PubMed. https://pubmed.ncbi.nlm.nih.gov/37294199/
- Distal clavicular osteolysis (review). Physiopedia. https://www.physio-pedia.com/Distal_Clavicular_Osteolysis
Published rehab protocols (patient-guidance — basis for the phase structure)
- Saint Louis University Dept of Orthopaedic Surgery. Subacromial Decompression / Distal Clavicle Excision Rehab Protocol. https://www.slu.edu/medicine/orthopaedic-surgery/sports-medicine/-pdf/shoulder-subacromial-decompression-and-distal-clavicle-excision.pdf
- Burks RT. Distal Clavicle Resection/Mumford Post-Op Protocol. University of Utah Sports Medicine. https://www.robertburksmd.med.utah.edu/pdfs/distal-clavicle-resection-mumford-protocol.pdf
- Sports Surgery New York. Arthroscopic Subacromial Decompression / Distal Clavicle Excision Rehab Protocol. https://www.sportssurgerynewyork.com/pdf/arthroscopic-subacromial-decompression-distal-clavicle-excision-rehab-protocol.pdf
- Hill B. Rehabilitation Protocol: Distal Clavicle Excision. Palm Beach Orthopaedic Institute. https://www.pboi.com/pdf/hill-pt-distal-clavicle-excision.pdf
- Eastwood D. Distal Clavicle Resection Therapy Protocol. OrthoVirginia. https://www.orthovirginia.com/wp-content/uploads/2022/09/Eastwood-distal-clavicle-resection-PT-protocol.pdf
- Mahylis JM. Distal Clavicle Excision Rehabilitation Protocol. Specialty Physicians of Illinois. https://jaredmahylismd.com/pdfs/distal-clavicle-excision-rehabilitation-protocol.pdf