Patients › Rehabilitation
کلائی کا جزوی فیوژن
گھسی ہوئی کلائی کے جزوی فیوژن (کیپیٹولیونیٹ فیوژن، جس میں عموماً اسکیفائیڈ ہڈی بھی نکال دی جاتی ہے) کے بعد صحت یابی کا محفوظ منصوبہ: تقریباً چھ سے آٹھ ہفتے میں ہڈیوں کے جڑنے تک کلائی کو بے حرکت رکھا جاتا ہے، پھر کلائی کی کارآمد مگر جان بوجھ کر کم رکھی گئی حرکت اور گرفت کی طاقت بتدریج بحال کی جاتی ہے۔
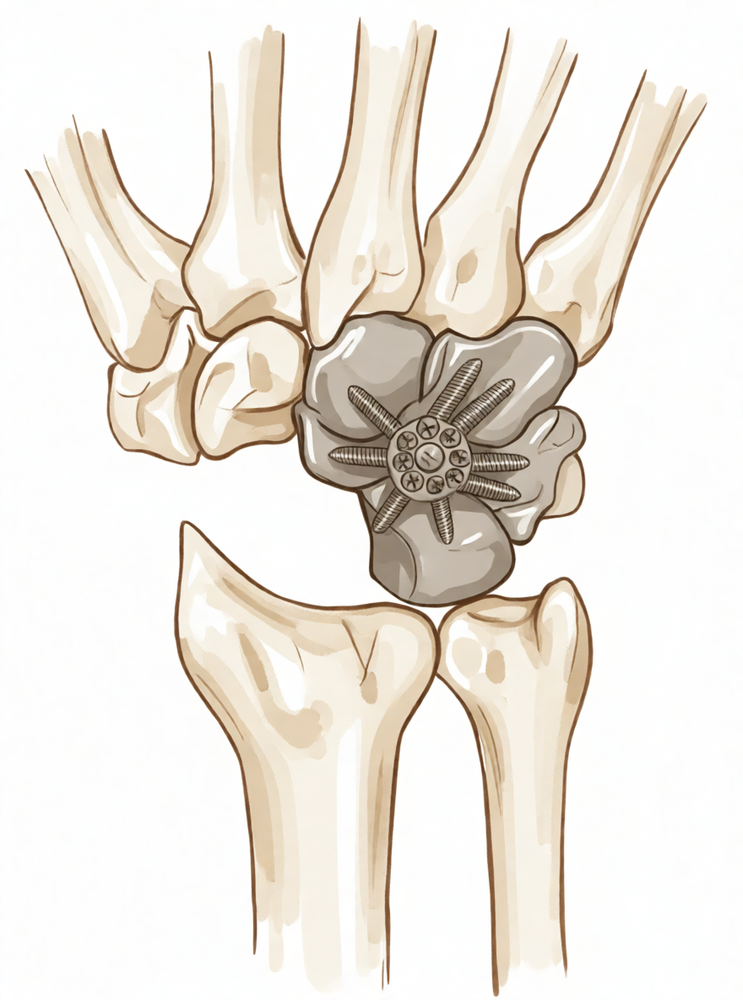
یہ پروٹوکول کلائی کے جزوی فیوژن (partial wrist fusion) کے بعد آپ کی صحت یابی میں رہنمائی کرتا ہے (یہ ایک ایسا آپریشن ہے جس میں گھسی ہوئی اسکیفائیڈ ہڈی (scaphoid، کلائی کی ایک چھوٹی ہڈی) نکال دی جاتی ہے اور کلائی کے درمیان کی چھوٹی ہڈیوں کو جوڑ کر ایک کر دیا جاتا ہے، اکثر کیپیٹیٹ (capitate) کو لیونیٹ (lunate) سے، جسے کیپیٹولیونیٹ فیوژن (capitolunate fusion) کہتے ہیں)، اور یہ آپریشن ڈاکٹر کیرن ہِرپرا Mater Private Hospital Rockhampton میں کرتے ہیں۔ یہ صفحہ گھر پر کی جانے والی ورزشوں کے پروگرام سے شروع ہوتا ہے، جس کے بعد وہ باقاعدہ طبی پروٹوکول ہے جو آپ کے ہینڈ تھراپسٹ (ہاتھ کی بحالی کے ماہر) کے لیے لکھا گیا ہے: تھراپی کی اپنی پہلی ملاقات پر یہ صفحہ یا اس کی پی ڈی ایف ساتھ لائیں تاکہ آپ کی بحالی میں سب ایک ساتھ رہیں۔ آپ کا ہینڈ تھراپسٹ آپ کی صحت یابی کی پیش رفت کے مطابق منصوبے میں تبدیلی کر سکتا ہے۔
اگر آپریشن کے بعد آپ کو اپنے زخم کے بارے میں کوئی تشویش ہو تو کلینک سے رابطہ کریں۔ اکثر یہ مددگار ہوتا ہے کہ زخم کی تصویر لے کر جائزے کے لیے ای میل کر دیں۔
کیا توقع رکھیں
کلائی کا جزوی فیوژن ایسی کلائی کا علاج ہے جو آرتھرائٹس (جوڑ کی خرابی اور سوزش) کی وجہ سے گھس چکی ہو، اور یہ گھساؤ اسکیفائیڈ ہڈی کے کسی پرانے مسئلے کے بعد ایک خاص راستے پر پھیلتا ہے: یا تو اسکیفائیڈ اور لیونیٹ کو جوڑنے والے لیگامنٹ کی چوٹ ("SLAC" کلائی) (لیگامنٹ (ligament)، یعنی وہ مضبوط بندھن جو ایک ہڈی کو دوسری ہڈی سے جوڑتا ہے)، یا اسکیفائیڈ کا کوئی پرانا فریکچر (ہڈی کا ٹوٹنا) جو کبھی نہیں جڑا ("SNAC" کلائی)۔ خراب اسکیفائیڈ ہڈی نکال دی جاتی ہے، اور کلائی کے درمیانی حصے کی ہڈیوں کو آپس میں جوڑ کر ایک کر دیا جاتا ہے تاکہ وہ مزید ایک دوسرے سے نہ رگڑیں۔ ڈاکٹر ہِرپرا اکثر کیپیٹیٹ کو لیونیٹ سے جوڑتے ہیں (کیپیٹولیونیٹ فیوژن)، اور بعض اوقات ساتھ والی ہڈیوں کو بھی شامل کرتے ہیں؛ جب لیونیٹ، کیپیٹیٹ، ٹرائیکویٹرم (triquetrum) اور ہیمیٹ (hamate) چاروں کو جوڑ دیا جائے تو اسے فور کارنر فیوژن (four-corner fusion) کہتے ہیں، اور اس کی صحت یابی بھی انہی اصولوں پر چلتی ہے۔
اس آپریشن کا بنیادی خیال یہ ہے کہ کلائی کا صرف ایک حصہ جوڑا جاتا ہے، پوری کلائی نہیں۔ لیونیٹ اور بازو کے نچلے حصے کی ہڈی ریڈیس (radius) کے درمیان والے جوڑ کو جان بوجھ کر نہیں چھیڑا جاتا۔ یہی بچایا گیا جوڑ کلائی کو حرکت کرتے رہنے دیتا ہے:
- گھسی ہوئی سطحوں کو جوڑنے سے درد ختم ہو جاتا ہے: یہی اصل مقصد ہے، اور یہ قابلِ اعتماد طور پر حاصل ہو جاتا ہے۔
- ریڈیس اور لیونیٹ کا جوڑ برقرار رہنے کا مطلب ہے کہ آپ کی کلائی میں کام کی حرکت باقی رہتی ہے۔ اس کے بدلے حرکت کم ہو جاتی ہے: زیادہ تر لوگوں میں کلائی موڑنے کی حد پہلے کے تقریباً آدھے سے دو تہائی تک رہ جاتی ہے، اور گرفت کی طاقت دوسری طرف کے تقریباً تین چوتھائی کے برابر ہوتی ہے۔ یہ ایک عام اور متوقع نتیجہ ہے (پیچیدگی نہیں)، اور درد والی، گھسی ہوئی کلائی کے لیے یہ عموماً بہت فائدہ مند سودا ہوتا ہے۔
جوڑی گئی ہڈیوں کو فریکچر کی طرح پختگی سے آپس میں جڑنے کے لیے وقت چاہیے۔ جب تک یہ ہو رہا ہو، تقریباً پہلے چھ ہفتے کلائی کو اسپلنٹ میں بے حرکت رکھا جاتا ہے۔ اس عرصے میں انگلیوں، انگوٹھے اور بازو کے نچلے حصے (forearm) کو آزادانہ حرکت دی جاتی رہتی ہے، لیکن خود کلائی کو آرام دیا جاتا ہے۔ جب سرجن ایکسرے پر تصدیق کر دیں کہ ہڈیاں جڑ گئی ہیں (united)، تو پہلے کلائی کی حرکت اور پھر طاقت بڑھانے کی ورزشیں احتیاط سے مرحلہ وار شروع کی جاتی ہیں۔ شروع ہی سے اپنی توقعات درست رکھنا (پوری طرح حرکت کرنے والی کلائی کے بجائے ایک آرام دہ اور کارآمد کلائی) صحت یابی کا ایک اہم حصہ ہے۔
احتیاطیں اور پابندیاں
- اپنی کلائی کو اسپلنٹ میں اس وقت تک بے حرکت رکھیں جب تک آپ کے سرجن تصدیق نہ کر دیں کہ فیوژن بھر گیا ہے (عموماً تقریباً چھ ہفتے): کلائی کو حرکت دینے سے پہلے ہڈیوں کا جڑنا ضروری ہے۔
- پہلے دن سے اپنی انگلیوں، انگوٹھے اور بازو کے نچلے حصے کو حرکت دیتے رہیں، لیکن اجازت ملنے تک خود کلائی کو ہرگز حرکت نہ دیں۔
- جب تک فیوژن کے پختہ ہونے کی تصدیق نہ ہو جائے، ہرگز نہ زور سے گرفت کریں، نہ کچھ اٹھائیں، نہ دھکیلیں، نہ کھینچیں اور نہ کلائی پر وزن ڈالیں: اس سے بھرتی ہوئی ہڈی اور کسی بھی پلیٹ، پیچ یا اسٹیپل (staples) کی حفاظت ہوتی ہے۔
- حرکت کی آخری حد کم رہنے کی توقع رکھیں: یہ کلائی کے ایک حصے کو جوڑنے کا طے شدہ نتیجہ ہے، اس بات کی علامت نہیں کہ کچھ غلط ہو گیا ہے۔
- اسپلنٹ اور زخم کی پٹی کو صاف اور خشک رکھیں، اور جب تک آپ اسپلنٹ میں ہوں یا اسٹیئرنگ کو محفوظ طریقے سے قابو نہ کر سکیں، ہرگز گاڑی نہ چلائیں۔
زخم، سوجن اور زخم کے نشان کی دیکھ بھال کے لیے کلینک کی زخم کی دیکھ بھال سے متعلق رہنمائی دیکھیں۔
آپ کی ورزشیں
Kieran Hirpara 4.0
انگلیوں اور انگوٹھے کی حرکت
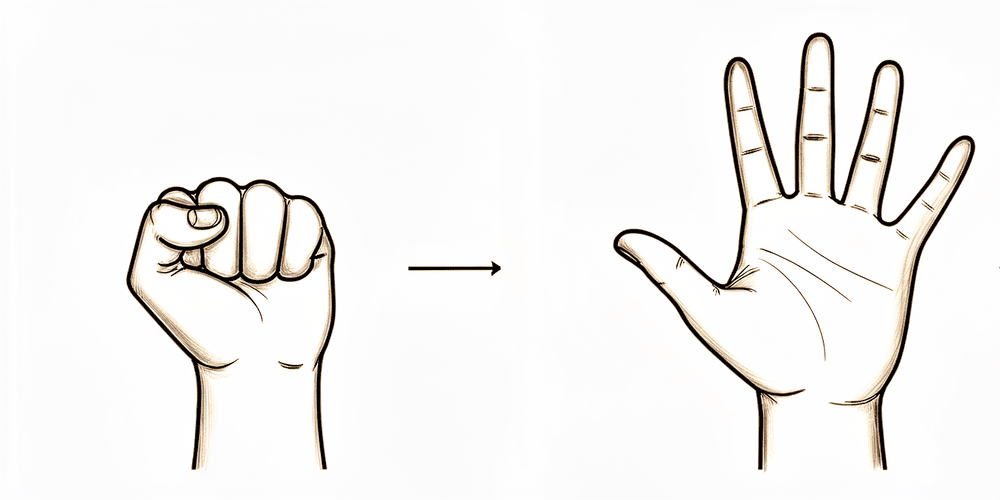
آپریشن کے دن سے، جب کلائی خود پلستر یا اسپلنٹ میں آرام کر رہی ہو، اپنی انگلیوں اور انگوٹھے کو حرکت دیتے رہیں۔ اپنی تمام انگلیاں پوری طرح سیدھی کریں، پھر پوری مٹھی بنائیں، پھر انگوٹھے کو باری باری ہر انگلی کے سرے سے ملائیں۔ اس سے ہاتھ اکڑتا نہیں اور کلائی کی ہڈیوں کے جڑنے کے دوران ٹینڈن آسانی سے سرکتے رہتے ہیں۔ خود کلائی کو حرکت نہ دیں۔
ہر ایک 10 بار، دن میں کئی بار، شروع سے روزانہ
Kieran Hirpara 4.0
بازو کے نچلے حصے کو گھمانا (ہتھیلی اوپر / ہتھیلی نیچے)
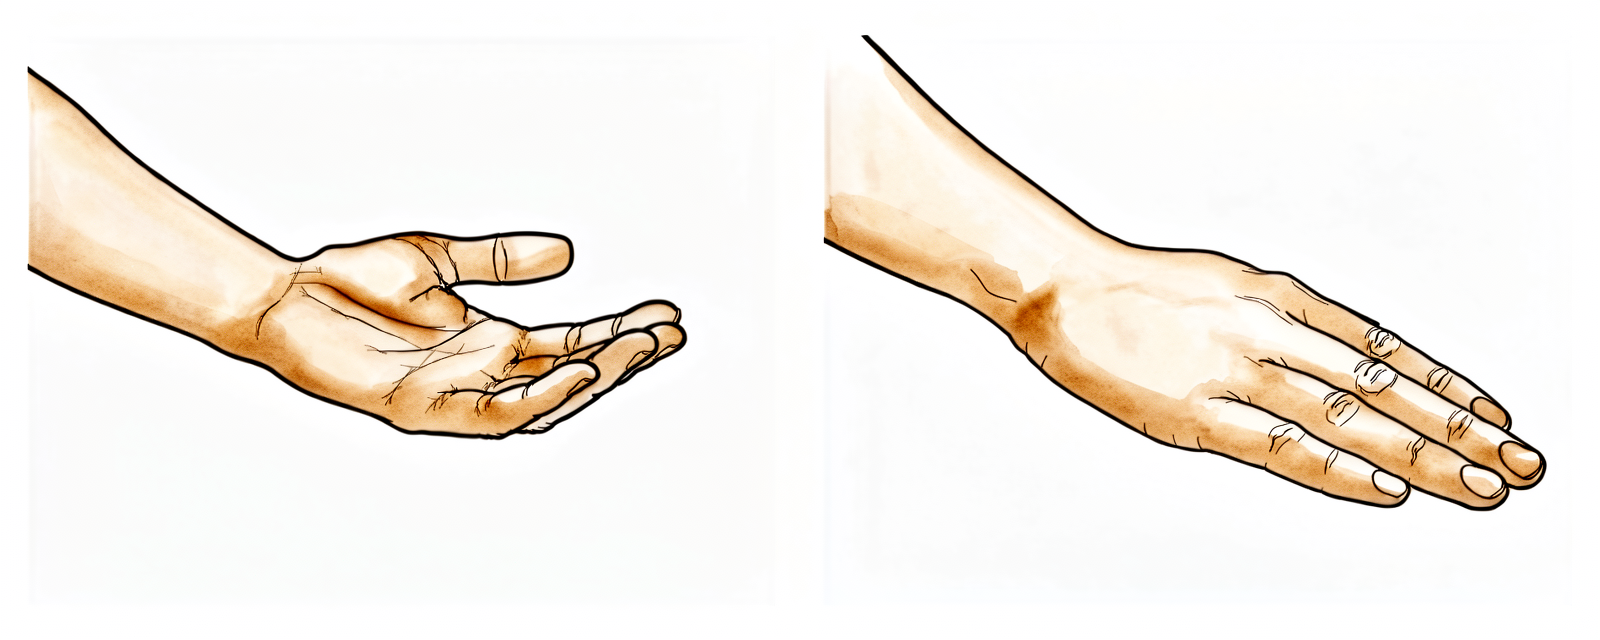
کہنی کو پہلو سے لگا کر قائمہ زاویے (right angle) پر موڑیں، پھر آہستہ سے ہتھیلی کو اوپر چھت کی طرف اور پھر نیچے فرش کی طرف گھمائیں۔ حرکت بازو کے نچلے حصے سے ہونی چاہیے، کلائی سے نہیں۔ اس سے بازو کا نچلا حصہ لچکدار رہتا ہے اور بھرتا ہوا فیوژن متاثر نہیں ہوتا، اس لیے یہ ورزش فوراً شروع کی جا سکتی ہے۔
ہر سمت میں 10 بار، دن میں 2 سے 3 بار
Kieran Hirpara 4.0
کلائی کی حرکت (ہڈیوں کے جڑنے کے بعد)
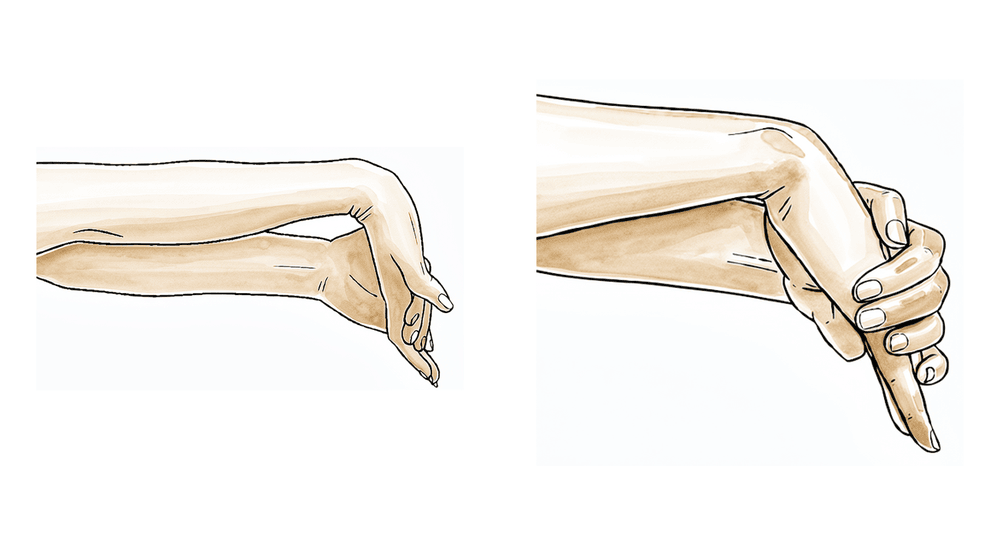
یہ بعد کے مرحلے کی ورزش ہے — صرف اس وقت جب فیوژن بھر جائے اور آپ کے سرجن اور ہینڈ تھراپسٹ کلائی کی حرکت کی اجازت دے دیں (عموماً تقریباً چھ سے آٹھ ہفتے بعد)۔ کلائی کو آہستہ سے اوپر (پیچھے کی طرف) اور نیچے (آگے کی طرف) موڑیں، پھر اسے انگوٹھے کی طرف اور چھوٹی انگلی کی طرف جھکائیں، اور صرف اتنا ہی حرکت دیں جتنا آرام سے ہو سکے۔ یاد رکھیں کہ کلائی کا جوڑا گیا حصہ حرکت نہیں کرے گا — آپ وہ حرکت بحال کر رہے ہیں جو بچائے گئے جوڑ سے آتی ہے، اس لیے آخری حد پہلے سے کم ہوگی، اور یہ متوقع ہے۔
ہر سمت میں 10 بار، دن میں 2 سے 3 بار، آرام کی حد کے اندر (ہڈیوں کے جڑنے کے بعد)
Kieran Hirpara 4.0
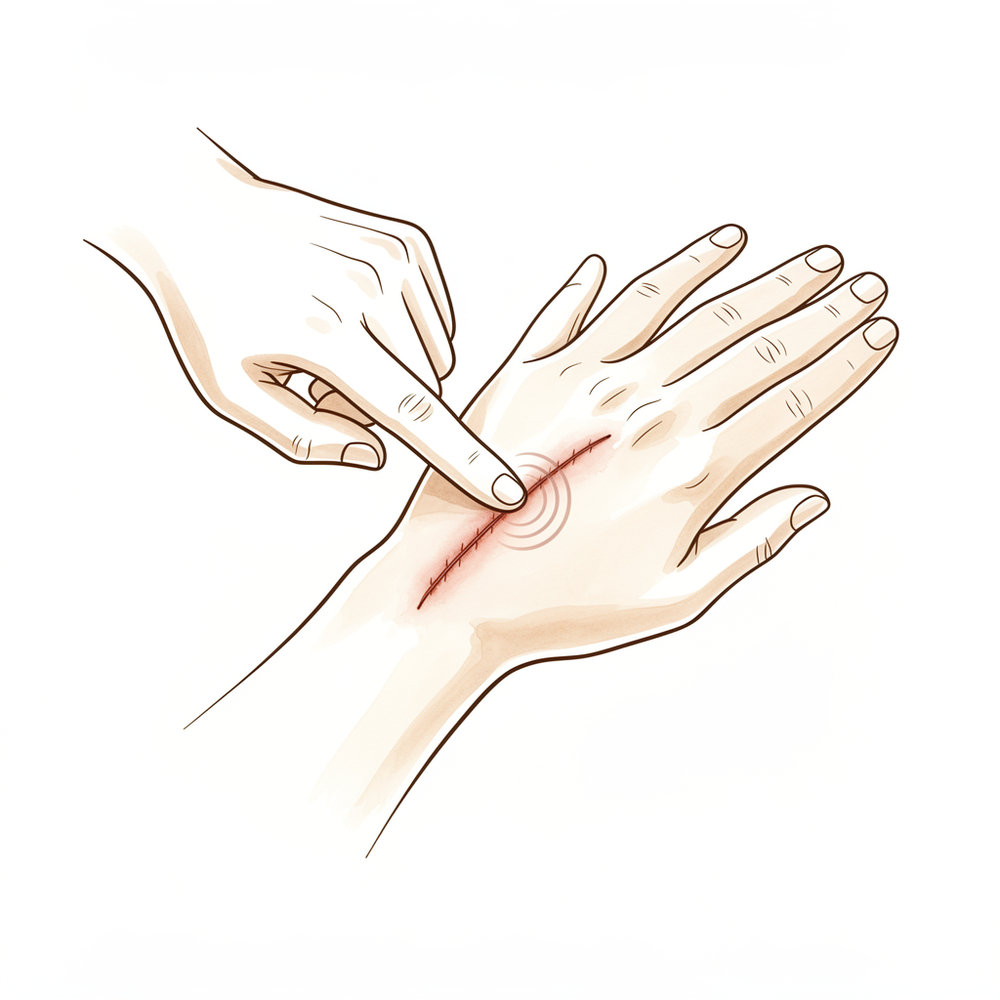
زخم کے نشان کی دیکھ بھال
جب زخم پوری طرح بھر جائے اور خشک ہو، تو دوسرے ہاتھ کے انگوٹھے سے چھوٹے، مضبوط دائروں میں تھوڑا سا بغیر خوشبو والا موئسچرائزر لگا کر چند منٹ زخم کے نشان کی مالش کریں۔ اس سے نشان نرم ہوتا ہے اور اس کی حساسیت کم ہوتی ہے۔ جب تک زخم بند نہ ہو جائے اور آپ کا تھراپسٹ مطمئن نہ ہو، یہ شروع نہ کریں۔
2 سے 3 منٹ، دن میں دو بار، زخم بھر جانے کے بعد
Kieran Hirpara 4.0
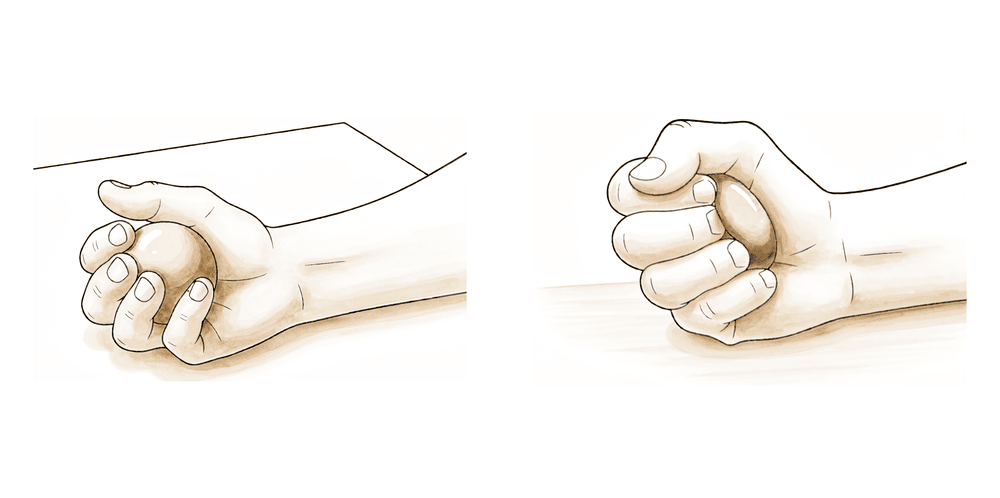
گرفت کی طاقت بڑھانا
یہ بعد کے مرحلے کی ورزش ہے — صرف اس وقت شروع کی جاتی ہے جب فیوژن مضبوط ہو جائے اور طاقت بڑھانے کی اجازت مل جائے (عموماً تقریباً بارہ ہفتے سے)۔ ایک نرم گیند یا تھراپی پُٹی (putty) کو ہتھیلی میں دبائیں، تھوڑی دیر روکیں، پھر چھوڑ دیں۔ کئی ہفتوں میں زور آہستہ آہستہ بڑھائیں۔ بھاری گرفت، وزن اٹھانا اور کلائی پر وزن ڈالنا اس وقت تک روکے رکھے جاتے ہیں جب تک آپ کے سرجن تصدیق نہ کر دیں کہ ہڈیاں پوری طرح جڑ گئی ہیں۔
10 سے 15 بار دبائیں، دن میں 2 سے 3 بار، بتدریج بڑھاتے ہوئے (بعد کا مرحلہ)
یہ آپ کے ہینڈ آؤٹ میں دی گئی ورزشیں ہیں۔ انہیں صرف ڈاکٹر ہِرپرا اور اپنے ہینڈ تھراپسٹ کی رہنمائی کے مطابق شروع کریں، اور آپ کو جو بھی حد اور پابندیاں بتائی گئی ہیں ان کے اندر رہیں۔ ابتدائی ورزشیں بھرتے ہوئے فیوژن کو چھیڑے بغیر انگلیوں، انگوٹھے اور بازو کے نچلے حصے کو حرکت میں رکھتی ہیں؛ خود کلائی پلستر یا اسپلنٹ میں بے حرکت رہتی ہے۔ کلائی کی حرکت اور گرفت کی طاقت بڑھانے کی ورزشیں بعد کے مراحل کا حصہ ہیں اور جب تک آپ کے سرجن تصدیق نہ کر دیں کہ ہڈیاں جڑ گئی ہیں، انہیں شروع نہیں کرنا چاہیے۔ جس چیز سے کلائی پر تیز درد ہو اسے روک دیں۔
آپ کا طبی پروٹوکول
اس صفحے کا باقی حصہ کلائی کے جزوی فیوژن (کیپیٹولیونیٹ فیوژن، اسکیفائیڈ نکالنے کے ساتھ یا بغیر؛ یہی اصول فور کارنر فیوژن پر بھی لاگو ہوتے ہیں) کے بعد بحالی کا مرحلہ وار طبی پروٹوکول ہے۔ یہ حصہ آپ کے ہینڈ تھراپسٹ کو دیا جانا ہے، اور ہر مرحلہ عام فہم زبان میں اس وضاحت سے شروع ہوتا ہے کہ کیا ہو رہا ہے۔ ٹینڈن (tendon)، یعنی وہ مضبوط ڈوری جو پٹھے کو ہڈی سے جوڑتی ہے، کی مرمت کے برعکس یہاں جوڑی گئی ساخت ہڈی کی ہے، اور اگلے مرحلے میں جانے کا فیصلہ کسی طے شدہ کیلنڈر سے نہیں بلکہ ایکسرے پر فیوژن کے جڑنے (radiographic union) سے ہوتا ہے۔ جب تک سرجن ہڈیوں کے جڑنے کی تصدیق نہ کریں، کلائی کو بے حرکت رکھا جاتا ہے اور صرف انگلیوں، انگوٹھے اور بازو کے نچلے حصے کو حرکت دی جاتی ہے؛ اس کے بعد پہلے کلائی کی حرکت کی حد اور پھر اس پر بوجھ بحال کیا جاتا ہے، اور حقیقت پسندانہ حد یہ ہے کہ موڑنے اور سیدھا کرنے (flexion–extension) کی حرکت دوسری کلائی کے تقریباً 50 سے 65 فیصد تک اور گرفت تقریباً 70 سے 80 فیصد تک پہنچتی ہے۔
علاج شروع کرنے سے پہلے مریض کی آپریشن رپورٹ دیکھیں اور استعمال کی گئی فکسیشن (گول پلیٹ یا کلائی کی پشت پر لگی پلیٹ، بغیر سر والے کمپریشن پیچ، اسٹیپل یا کے-وائر (K-wires)) کی تصدیق کریں، اور یہ بھی کہ آیا اسکیفائیڈ نکالی گئی تھی۔ جب تک علاج کرنے والے سرجن ایکسرے پر ہڈیوں کے جڑنے کی تصدیق نہ کر دیں، کلائی کی حرکت ہرگز شروع نہ کریں (عموماً 6 سے 8 ہفتے، اور پیچ یا اسٹیپل کی فکسیشن میں بعض اوقات اس سے زیادہ)۔ پہلی ملاقات سے ہی مریض کو سمجھائیں کہ مقصد پوری حرکت نہیں بلکہ ایسی کلائی ہے جو درد سے پاک اور کارآمد ہو اور جس کی حرکت کی حد جان بوجھ کر کم رکھی گئی ہو۔
مرحلہ 1 — ہڈیوں کے جڑنے تک محفوظ طریقے سے بے حرکت رکھنا (ہفتہ 0 سے تقریباً ہفتہ 6 تا 8 تک)
فیوژن فریکچر کی طرح بھر رہا ہوتا ہے، اس لیے ہڈیوں کے جڑنے تک کلائی کو بے حرکت رکھا جاتا ہے۔ اکڑاؤ اور ٹینڈن کے چپک جانے (tendon adhesion) سے بچانے کے لیے ہاتھ اور بازو کے نچلے حصے کو پوری طرح حرکت میں رکھا جاتا ہے، لیکن کلائی کو حرکت نہیں دی جاتی۔
آپ کے ہینڈ تھراپسٹ کے لیے:
تعلیم اور احتیاطیں - جب تک سرجن ایکسرے پر ہڈیوں کے جڑنے کی تصدیق نہ کریں (عموماً 6 سے 8 ہفتے)، کلائی کو پلستر یا اسپلنٹ میں بے حرکت رکھیں - اس مرحلے میں کلائی کی نہ ایکٹو (active) حرکت اور نہ پیسو (passive) حرکت - آپریشن والی کلائی سے نہ گرفت، نہ کچھ اٹھانا، نہ دھکیلنا، نہ کھینچنا اور نہ اس پر وزن ڈالنا - شروع ہی سے توقع واضح کر دیں: حرکت کی آخری حد کم ہوگی (ریڈیس اور لیونیٹ کا جوڑ برقرار رکھا جاتا ہے؛ کلائی کا درمیانی (midcarpal) جوڑ جوڑ دیا جاتا ہے)
علاج - زخم: ہدایت کے مطابق سرجیکل پٹیاں؛ تقریباً 10 سے 14 دن تک موٹی پٹی/اسپلنٹ، پھر بازو کے نچلے حصے کا چھوٹا پلستر (short-arm cast) یا تھرموپلاسٹک اسپلنٹ (thermoplastic splint، گرم کر کے ناپ کے مطابق ڈھالا گیا اسپلنٹ)؛ انفیکشن کے لیے نگرانی کریں - سوجن (oedema): دل کی سطح سے اوپر اونچا رکھنا، ہاتھ کو ہلکے سے بار بار کھولنا بند کرنا (pumping)، ضرورت کے مطابق برف - ورزشیں: انگلیوں، انگوٹھے اور ایم سی پی/آئی پی (MCP/IP) جوڑوں کی پوری ایکٹو حرکت کی حد (ROM)؛ بازو کے نچلے حصے کو ہتھیلی نیچے اور اوپر کی طرف گھمانا (pronation/supination)؛ کندھے اور کہنی کی ہلکی حرکت؛ کلائی کی کوئی حرکت نہیں
اگلے مرحلے میں جانے کی شرائط - سرجن کی جانب سے ایکسرے پر ہڈیوں کے جڑنے کی تصدیق (صرف کیلنڈر کی بنیاد پر آگے نہ بڑھیں)؛ زخم بھر گیا ہو؛ سوجن قابو میں ہو
مرحلہ 2 — کلائی کی حرکت کی بحالی (ہڈیوں کے جڑنے سے، یعنی تقریباً ہفتہ 6 تا 8 سے، ہفتہ 12 تک)
جب سرجن تصدیق کر دیں کہ فیوژن پختہ ہو گیا ہے، تو کلائی پلستر سے باہر آ جاتی ہے اور کلائی کی ہلکی حرکت شروع ہوتی ہے۔ پیش رفت بتدریج ہوتی ہے؛ مریض کو یاد دلایا جاتا ہے کہ جوڑا گیا حصہ حرکت نہیں کرے گا اور حاصل ہونے والی حرکت کی حد پہلے سے کم ہوگی۔
آپ کے ہینڈ تھراپسٹ کے لیے:
جائزے - کلائی کی ایکٹو اور پیسو حرکت کی حد (موڑنا/سیدھا کرنا، انگوٹھے اور چھوٹی انگلی کی طرف جھکانا)، بازو کے نچلے حصے کی گردش، گرفت کی ابتدائی پیمائش، درد اور سوجن، زخم/نشان کا جائزہ
تعلیم اور احتیاطیں - آرام کی حد کے اندر کلائی کی ایکٹو اور مدد کے ساتھ ایکٹو (active-assisted) حرکت شروع کریں؛ سیشنوں کے درمیان آرام/حفاظت کے لیے اتارے جا سکنے والے کلائی کے اسپلنٹ پر منتقل ہوں - طاقت بڑھانے کی اجازت ملنے تک کلائی سے بھاری گرفت، بوجھ اٹھانے اور وزن ڈالنے سے بچتے رہیں - کم حرکت کی توقع کو دہرائیں (ہدف: دوسری کلائی کے موڑنے اور سیدھا کرنے کی حد کا تقریباً 50 سے 65 فیصد)
علاج - ورزشیں: کلائی کو ایکٹو/مدد کے ساتھ ایکٹو طریقے سے موڑنا، سیدھا کرنا، انگوٹھے اور چھوٹی انگلی کی طرف جھکانا؛ زخم پوری طرح بھر جانے پر زخم کے نشان کی مالش اور حساسیت کم کرنے (desensitisation) کا آغاز کریں؛ انگلیوں/انگوٹھے کی پوری حرکت اور بازو کے نچلے حصے کی گردش جاری رکھیں؛ ضرورت کے مطابق سوجن کا انتظام
اگلے مرحلے میں جانے کی شرائط - متوقع کم حد کے اندر کلائی کی آرام دہ اور قابو میں حرکت؛ درد کم ہو رہا ہو؛ طاقت بڑھانے کے لیے سرجن کی اجازت
مرحلہ 3 — طاقت بڑھانا اور معمول کے کاموں پر واپسی (تقریباً ہفتہ 12 سے)
فیوژن پختہ ہونے اور حرکت اپنی کارآمد حد تک بحال ہونے کے بعد، طاقت بڑھانے کی ورزشیں اور بتدریج بوجھ ڈالنا شروع ہوتا ہے اور کئی ہفتوں میں بڑھایا جاتا ہے۔ جسمانی مشقت والے کام اور کھیل پر واپسی مقررہ شرائط پوری ہونے پر ہوتی ہے۔
آپ کے ہینڈ تھراپسٹ کے لیے:
جائزے - دوسری طرف کے مقابلے میں گرفت اور چٹکی کی گرفت کی طاقت؛ بوجھ ڈالنے پر درد/سوجن کا ردعمل؛ روزمرہ کاموں اور پیشے کے مطابق عملی جانچ
تعلیم اور احتیاطیں - اجازت ملنے پر گرفت اور کلائی کی طاقت کو بتدریج بڑھانا شروع کریں (تھراپی پُٹّی (putty)، گیند، پھر درجہ بدرجہ مزاحمت) - بوجھ اور وزن والے کام بتدریج شامل کریں؛ ایک دم سب کچھ کرنے کے بجائے کئی ہفتوں میں بڑھائیں - متوقع نتیجہ: گرفت دوسری طرف کے تقریباً 70 سے 80 فیصد کی طرف بحال ہوتی ہے، اور کارآمد، درد سے پاک، کم حد والی حرکت
علاج - ورزشیں: گرفت اور بازو کے نچلے حصے/کلائی کی طاقت کو بتدریج بڑھانا؛ درجہ بدرجہ عملی سرگرمیاں اور کام کی مشق؛ زخم کے نشان کی دیکھ بھال اور حرکت کی حد برقرار رکھنا جاری رکھیں - اگر کلائی کو پیچھے کی طرف سیدھا کرنے پر کلائی کی پشت پر مسلسل درد ہو (ممکنہ کلائی کی پشت پر ہڈیوں کا ٹکراؤ (dorsal impingement))، ہڈیوں کے نہ جڑنے (nonunion) کا شبہ ہو، یا صحت یابی ایک جگہ رک جائے تو اس پر نظر رکھیں اور مریض کو دوبارہ سرجن کے پاس بھیجیں - جب طاقت اور کارکردگی مریض کی روزمرہ اور پیشہ ورانہ ضروریات کے لیے کافی ہو جائے تو علاج ختم کرنے پر غور کریں
بوجھ / کام پر واپسی کی شرائط - پختہ جڑا ہوا فیوژن، بحال شدہ حد کے اندر درد نہ ہو، کام کے لیے کافی گرفت؛ بھاری جسمانی کام تقریباً 4 سے 6 ماہ تک مؤخر رکھیں اور پھر بتدریج بڑھائیں
کام اور سرگرمیوں پر واپسی
ہاتھ کا ہلکا روزمرہ استعمال (کھانا کھانا، لکھنا، ہلکی ذاتی دیکھ بھال) شروع سے ہی آرام کی حد کے اندر کرنے کی ترغیب دی جاتی ہے، بشرطیکہ اس سے کلائی پر بوجھ نہ پڑے اور وہ مڑے نہیں۔ جب تک آپ کی کلائی پلستر میں ہو یا آپ اسٹیئرنگ کو محفوظ طریقے سے قابو نہ کر سکیں، آپ ہرگز گاڑی نہ چلائیں، اس لیے ابتدائی ہفتوں میں آنے جانے کے لیے مدد کا انتظام کر لیں؛ جب آپ پلستر سے باہر آ جائیں اور گاڑی کو اعتماد سے قابو کر سکیں، جس کی تصدیق آپ کے معائنے پر کی جائے گی، تو گاڑی چلانا دوبارہ شروع ہو جاتا ہے۔
کلائی سے گرفت کرنے، کچھ اٹھانے اور کلائی پر وزن ڈالنے کے لیے اس وقت تک انتظار کیا جاتا ہے جب تک فیوژن کے پختہ ہونے کی تصدیق نہ ہو جائے (عموماً تقریباً چھ سے آٹھ ہفتے بعد)، اور پھر انہیں بتدریج بڑھایا جاتا ہے۔ دفتری یا ہلکا کام کرنے والے لوگ اکثر تقریباً تین ماہ میں کام پر واپس آ جاتے ہیں؛ زیادہ بھاری جسمانی مشقت والے کام میں واپسی عموماً چار سے چھ ماہ کے قریب ہوتی ہے اور مرحلہ وار دوبارہ شروع کی جاتی ہے۔ پورے عرصے یہ یاد رکھیں کہ طے شدہ نتیجہ ایک آرام دہ اور کارآمد کلائی ہے جس کی حرکت کی حد کم ہوتی ہے، اور اس کا اندازہ اس سے لگایا جاتا ہے کہ کلائی کیسی محسوس ہوتی ہے اور کیسے کام کرتی ہے؛ رفتار کا تعین صرف کیلنڈر نہیں بلکہ ڈاکٹر ہِرپرا اور آپ کا ہینڈ تھراپسٹ کرتے ہیں۔
آپ کے پروٹوکول کے بعد
یہ پروٹوکول کلینک کے صحت یابی سے متعلق عمومی مشوروں کے ساتھ مل کر کام کرتا ہے: دیکھیں آپریشن کے بعد درد پر قابو پانا، زخم کی دیکھ بھال اور زخم کے نشان کی دیکھ بھال۔ اوپر دیا گیا مرحلہ وار منصوبہ کلائی کے جزوی فیوژن کے بعد بحالی سے متعلق شائع شدہ رہنمائی کی عکاسی کرتا ہے، اور آپ کی آگے کی صحت یابی میں ڈاکٹر ہِرپرا اور آپ کا ہینڈ تھراپسٹ اس بات کے مطابق انفرادی طور پر رہنمائی کرتے ہیں کہ آپ کی کلائی کیسے بھر رہی ہے اور کیسے آگے بڑھ رہی ہے۔
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Partial Wrist Fusion — Procedure Outcomes & Post-operative Rehabilitation (Capitolunate / Four-Corner Arthrodesis with Scaphoid Excision)
Topic scope: post-operative rehabilitation after midcarpal partial wrist arthrodesis for scapholunate advanced collapse (SLAC) or scaphoid nonunion advanced collapse (SNAC). The index procedure here is a capitolunate fusion (the capitate fused to the lunate, usually with excision of the worn scaphoid); the closely related four-corner fusion (lunate–capitate– triquetrum–hamate) follows the same rehabilitation principles. This is a bony arthrodesis, so the rehabilitation is a union-gated pathway: the mid-wrist is immobilised until the fusion consolidates, after which a deliberately reduced wrist arc and grip are restored.
Defining principle of the rehab here: a partial wrist fusion is a motion-preserving salvage. The arthritic midcarpal surfaces are fused to abolish pain, while the radiolunate joint is intentionally preserved to retain movement. The construct that needs protecting is healing bone (plate, headless screws, staples or K-wires across the fusion), not a soft-tissue repair — so progression is gated by radiographic union, not a calendar. Counselling the patient that the planned end-point is a pain-free, functional wrist with a reduced arc (~50–65% of normal flexion–extension, ~70–80% grip) is itself part of the treatment: the reduced motion is the intended trade-off, not a failure. The two principal branch points are the fixation method (which sets the immobilisation window and union risk) and whether scaphoid excision was performed (standard in the SLAC/SNAC setting).
A. PROCEDURE OUTCOMES (capitolunate / four-corner fusion for SLAC–SNAC)
Partial wrist fusion is a well-established, durable salvage for the SLAC/SNAC wrist. The dominant debate is which motion-preserving salvage (four-corner / capitolunate fusion vs proximal row carpectomy), not whether to operate; both reliably relieve pain at the cost of some motion.
- Reliable pain relief with a useful but reduced arc. Across series, midcarpal fusion abolishes the painful midcarpal arthritis while preserving radiolunate motion. Typical results are roughly 50–65% of contralateral flexion–extension and ~70–80% of contralateral grip strength, with high rates of pain relief and return to work — the expected, planned trade-off of a partial fusion [Enna Hand Clin 2005; Strauch J Hand Surg Am 2011; Merrell J Hand Surg Am 2008; long-term series J Wrist Surg 2015]. Moderate (cohort/consensus).
- Capitolunate fusion (± scaphoid excision) performs comparably to full four-corner fusion while fusing fewer joints, simplifying the construct. A systematic review of capitolunate arthrodesis and comparative work report comparable motion, grip and union to four-corner fusion, supporting it as a sound index choice [Dunn J Hand Surg Am 2020 (systematic review); lunocapitate series J Hand Surg Eur 2009; J Chin Med Assoc 2017]. Moderate.
- A meta-analysis of two-, three- and four-corner constructs finds the number of fused columns does not materially change motion, grip, union or complications — biomechanically consistent with the radiolunate joint being the motion-determining segment [Hundepool J Hand Surg Am 2025 (SR/meta-analysis); Hernandez-Soria J Hand Surg Am 2016 (capitate-position biomechanics)]. Moderate (SR) + mechanistic.
- Modern fixation is forgiving but union is not guaranteed. Circular dorsal plates, headless compression screws and nitinol staples all achieve consolidation in the great majority, with nonunion and dorsal impingement the characteristic failures to watch for [Merrell J Hand Surg Am 2008 (circular plate); Ahmady J Hand Surg Glob Online 2025 (nitinol staples)]. Moderate.
B. REHABILITATION / THERAPY EVIDENCE
The rehab questions are (1) how long to immobilise, (2) what gates the start of wrist motion, and (3) how to set the patient's expectation of reduced motion. The evidence and published surgeon protocols converge on a union-gated sequence: immobilise the wrist (mobilise the hand and forearm) for ~6–8 weeks, then restore a reduced arc, then strengthen.
- Immobilise until radiographic union, not by the calendar. Because the construct is bony, wrist motion is withheld until the surgeon confirms consolidation — typically 6–8 weeks, longer with some screw/staple fixations. Published institutional protocols use a bulky dressing/splint for ~10–14 days, a short-arm cast to ~4–6 weeks, then a removable splint as motion begins. Moderate (consensus protocols).
- Keep the hand and forearm fully mobile from day one. Immediate active finger, thumb and forearm rotation prevents stiffness and tendon adhesion without disturbing the fusion — the same glide-preserving logic used across hand rehab. Consensus.
- Restore motion gradually after union, against a realistic ceiling. Once united, active and active-assisted wrist ROM is introduced; patients should be counselled that the fused midcarpal segment will not move and the achievable arc is smaller than pre-operatively (the radiolunate joint alone supplies wrist motion). Consensus + mechanistic (capitate-position biomechanics, Hernandez-Soria 2016).
- Strengthen and load only once the fusion is solid. Grip and loaded/weight-bearing work begins after union and is built up gradually; heavy manual demands are deferred to ~4–6 months. Consensus.
Recovery trajectory (expected, evidence-anchored)
| Phase | Window | Restraint | Hand use / therapy focus | Strength / load | Notes |
|---|---|---|---|---|---|
| I — Immobilisation (union) | Week 0 to ~6–8 | Wrist immobilised (cast/splint) | Full active finger, thumb & forearm motion; oedema control, elevation; no wrist motion | None through the wrist | Fusion knits like a fracture; progress is gated by radiographic union, not the calendar |
| II — Restoring wrist motion | From union (~wk 6–8) to 12 | Heavy-load avoidance; removable splint | Begin active/active-assisted wrist flexion/extension & deviation; scar massage once healed | No loaded grip yet | Counsel the reduced-arc expectation (~50–65% of normal flexion–extension) |
| III — Strengthening & return | From ~12 weeks (post-union) | Restrictions lifted progressively | Progressive grip/wrist strengthening; graded job simulation | Grip recovers toward ~70–80% of the other side | Desk work ~3 months; heavy manual ~4–6 months. Watch for dorsal impingement / nonunion |
(Phase windows mirror the precautions in the patient protocol and published surgeon protocols; they are typical guides anchored to union, not trial-derived deadlines.)
C. KEY CONTROVERSIES / EVIDENCE QUALITY
- Capitolunate vs four-corner vs proximal row carpectomy (PRC). All three are accepted motion-preserving salvages for SLAC/SNAC. PRC tends to give a slightly larger arc and avoids fusion-specific complications (nonunion, dorsal impingement, hardware), while fusion may give marginally better grip and is preferred where capitate-head or proximal-capitate cartilage is compromised. Systematic reviews and a meta-analysis find no consistent superiority of one over the other; choice is individualised [Mulford J Hand Surg Eur 2009; J Hand Surg Am 2024 meta-analysis; Strauch J Hand Surg Am 2011]. Moderate (SR/meta-analysis of mostly observational data).
- Capitolunate vs full four-corner construct. Fusing fewer columns (capitolunate) simplifies the construct without clearly compromising motion, grip or union versus four-corner — consistent with the radiolunate joint being the motion-determining segment [Dunn 2020 SR; Hundepool 2025 meta-analysis; Hernandez-Soria 2016]. Moderate.
- When can wrist motion safely start? Union timing varies with fixation, and protocols differ on exact cast duration. The defensible position is surgeon-confirmed radiographic union gates wrist ROM rather than a fixed week number. Weak–moderate (consensus; protocol variation).
- Reduced motion is the plan, not a complication. The preserved radiolunate joint supplies a smaller arc by design; mislabelling the expected ~50–65% range as a poor result drives unnecessary dissatisfaction. Strong mechanistically; cohort-supported.
- Characteristic failures: nonunion and dorsal impingement. Both are recognised, fixation-related complications; persistent dorsal wrist pain on extension or a non-progressing fusion warrants surgical review rather than more therapy [Merrell 2008; Ahmady 2025; long-term series 2015]. Moderate.
D. EVIDENCE STRENGTH FLAGS (summary)
- STRONG (mechanistic / well-supported): the reduced final arc is the planned consequence of preserving the radiolunate joint while fusing the midcarpal segment (capitate-position biomechanics); reliable pain relief from the fusion.
- MODERATE: typical outcome envelope (~50–65% flexion–extension, ~70–80% grip); equivalence of capitolunate and four-corner constructs; no consistent superiority of fusion vs PRC (SR/meta-analysis of largely observational data); modern fixation achieves high union with defined nonunion / dorsal impingement risk.
- WEAK / CONSENSUS: the specific union-gated immobilise → restore-motion → strengthen therapy sequence and exact phase timings (institutional/surgeon protocols, anchored to radiographic union rather than trial-derived).
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Enna M, Hoepfner P, Weiss AC. Scaphoid excision with four-corner fusion. Hand Clin. 2005. DOI: 10.1016/j.hcl.2005.08.012
- Dunn JC, Polmear MM, Scanaliato JP, et al. Capitolunate arthrodesis: a systematic review. J Hand Surg Am. 2020. DOI: 10.1016/j.jhsa.2019.10.007
- Hundepool CA, Duraku LS, Quanjel TJ, et al. Two-, three-, or four-corner arthrodesis for midcarpal osteoarthritis: a systematic review and meta-analysis. J Hand Surg Am. 2025. DOI: 10.1016/j.jhsa.2023.04.018
- Strauch RJ. Scapholunate advanced collapse and scaphoid nonunion advanced collapse arthritis — update on evaluation and treatment. J Hand Surg Am. 2011. DOI: 10.1016/j.jhsa.2011.01.018
- Merrell GA, McDermott EM, Weiss AC. Four-corner arthrodesis using a circular plate and distal radius bone grafting: a consecutive case series. J Hand Surg Am. 2008. DOI: 10.1016/j.jhsa.2008.02.001
- Hernandez-Soria A, Das De S, Model Z, et al. The effect of capitate position on coronal plane wrist motion after simulated 4-corner arthrodesis. J Hand Surg Am. 2016. DOI: 10.1016/j.jhsa.2016.07.101
- Ahmady AA, Zalzaleh M, Riedel BB. Midterm outcomes of four-corner fusion surgery using nitinol staples. J Hand Surg Glob Online. 2025. DOI: 10.1016/j.jhsg.2025.100805
- Mulford JS, Ceulemans LJ, Nam D, Axelrod TS. Proximal row carpectomy vs four corner fusion for scapholunate (SLAC) or scaphoid nonunion advanced collapse (SNAC) wrists: a systematic review of outcomes. J Hand Surg Eur Vol. 2009. DOI: 10.1177/1753193408100954
- Four-corner fusion versus proximal row carpectomy for scapholunate advanced collapse and scaphoid nonunion advanced collapse wrist: a systematic review and meta-analysis. J Hand Surg Am. 2024. DOI: 10.1016/j.jhsa.2024.01.011
- Long-term results of lunocapitate arthrodesis with scaphoid excision for SLAC and SNAC wrists. J Hand Surg Eur Vol. 2009. DOI: 10.1177/1753193409105683
- Lunocapitate fusion with scaphoid excision for the treatment of scaphoid nonunion advanced collapse or scapholunate advanced collapse wrist. J Chin Med Assoc. 2017. DOI: 10.1016/j.jcma.2016.10.001
- The long-term outcome of four-corner fusion. J Wrist Surg. 2015. DOI: 10.1055/s-0035-1549277
Partial wrist fusion rehabilitation literature (protocols & guidance — basis for the union-gated phase structure)
- University of Virginia Department of Orthopaedic Surgery. Wrist Partial Fusion (4-Corner) Rehabilitation Guidelines. https://med.virginia.edu/orthopaedic-surgery/wp-content/uploads/sites/242/2024/09/Wrist-Partial-Fusion-4-corner.pdf
- Oregon Health & Science University (OHSU). Four-Corner Partial Wrist Fusion — Surgery Guide. https://www.ohsu.edu/sites/default/files/2020-12/Four-Corner%20Partial%20Wrist%20Fusion.pdf
- Alaska Orthopedic Specialists. Four-Corner Fusion with Scaphoid Excision — Post-operative Protocol. https://www.akortho.com/wp-content/uploads/Four-Corner-Fusion-with-Scaphoid-Excision-1.pdf
- Twin Cities Orthopedics (Olson). Scaphoid Excision 4-Corner Fusion Post-operative Protocol. https://www.toportho.com/wp-content/uploads/2024/10/olson-_4-Corner-Fusion-Protocol.pdf
- The long-term outcome of four-corner fusion (open-access full text). PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC4408128/