Patients › Wrist
ڈسٹل ریڈیس کا او آر آئی ایف آپریشن (ORIF، کلائی کی ٹوٹی ہڈی کو کھول کر جوڑنا)
Open reduction and volar plate fixation of the distal radius — operation, recovery, rehabilitation.
یہ آپریشن کیوں تجویز کیا گیا ہے
ڈاکٹر کیرن ہِرپرا، جو Mater Private Hospital Rockhampton میں بازو اور ہاتھ کے سرجن (upper-limb surgeon) ہیں، علاج کو آپ کی مخصوص چوٹ کے مطابق طے کرتے ہیں۔ مریضوں کو عموماً ان کے فیملی ڈاکٹر (GP) ہمارے کلینک بھیجتے ہیں؛ اگر کسی فزیوتھراپسٹ نے آپ کو ہم سے ملنے کا مشورہ دیا ہے تب بھی میڈیکیئر (Medicare) کی واپسی رقم کا اہل ہونے کے لیے آپ کو اپنے فیملی ڈاکٹر سے ریفرل (referral) لینا ہو گا۔ آپ کی ملاقات پر ہم آپ کی تکلیف کی تفصیل پوچھتے ہیں، آپ کی کلائی کا معائنہ کرتے ہیں، اور ضرورت ہو تو ایکسرے یا اسکین کرواتے ہیں۔ اس معائنے سے ہمیں پتہ چلتا ہے کہ فریکچر (ہڈی کا ٹوٹنا) غیر مستحکم ہے یا جوڑ کے اندر تک چلا گیا ہے، اور یہی وہ صورت ہے جب عموماً آپریشن کا مشورہ دیا جاتا ہے۔
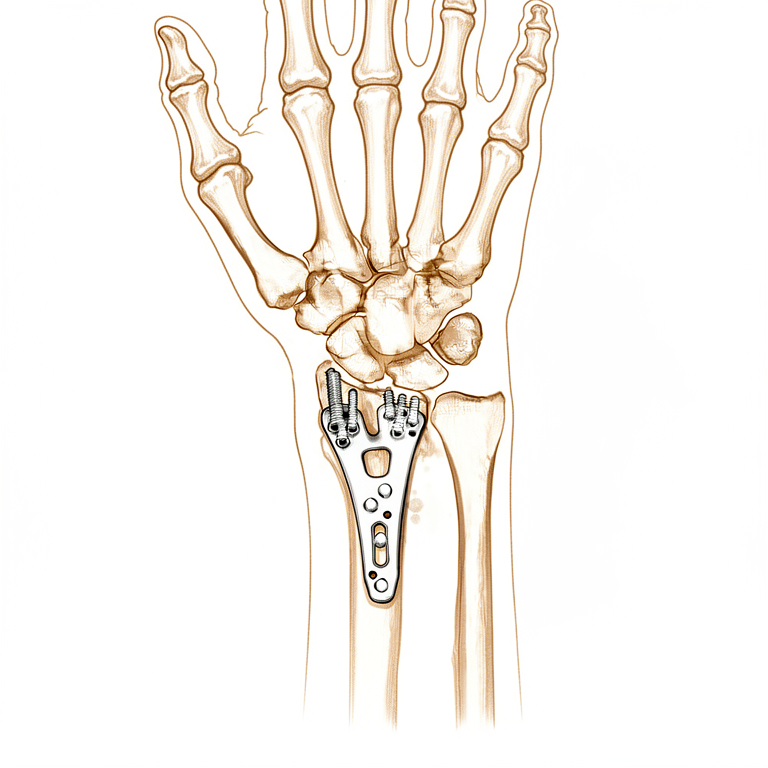
اس آپریشن کو اوپن ریڈکشن اینڈ انٹرنل فکسیشن (open reduction and internal fixation) کہتے ہیں۔ سادہ الفاظ میں اس کا مطلب ہے کہ ٹوٹی ہوئی ہڈی کو اس کی عام جگہ پر واپس لایا جاتا ہے اور دھات کی ایک چھوٹی پلیٹ اور پیچوں سے وہیں تھام دیا جاتا ہے۔ اس قسم کے زیادہ تر کلائی کے فریکچروں میں کلائی کی ہتھیلی والی طرف پلیٹ لگانا معمول کا طریقہ ہے۔ کم شدید فریکچروں میں اکثر پہلے آپریشن کے بغیر علاج، جیسے پلستر یا اسپلنٹ، آزمایا جاتا ہے۔ جب ہڈی غیر مستحکم ہو یا اپنی جگہ سے ہٹ گئی ہو تو فوراً آپریشن تجویز کیا جا سکتا ہے، کیونکہ ہو سکتا ہے پلستر ٹکڑوں کو اپنی جگہ پر نہ تھام سکے۔
مقصد یہ ہے کہ کلائی اچھی حالت میں جڑے، تاکہ آپ اپنا ہاتھ ہلا سکیں اور جلد اپنی معمول کی سرگرمیوں پر واپس آ سکیں۔
آپریشن سے پہلے
آپریشن کے دن آپ کو آپریشن کے وقت سے سات گھنٹے پہلے کھانا پینا بند کرنا ہو گا۔ ہم چھ کے بجائے سات گھنٹے اس لیے کہتے ہیں تاکہ اگر آپریشن کی فہرست وقت سے پہلے چلے تو آپ کا آپریشن پہلے کیا جا سکے۔ آپ کے سرجن بتائیں گے کہ آپریشن کے دن آپ اپنی باقاعدہ دواؤں میں سے کون سی نہ لیں اور کون سی معمول کے مطابق لیں۔ جو کچھ بھی آپ لیتے ہیں اس کی لکھی ہوئی فہرست ساتھ لائیں، جس میں گولیاں، قطرے اور میڈیکل اسٹور سے لی گئی ہر چیز شامل ہو۔ بعد میں آپ کو گھر لے جانے کے لیے کسی کا انتظام کریں، کیونکہ آپ خود گاڑی نہیں چلا سکیں گے۔ ڈھیلے، آرام دہ کپڑے پہنیں جن کی آستین آسانی سے اتر سکے۔
آپریشن کی منصوبہ بندی کے لیے ہم کئی زاویوں سے لیے گئے ایکسرے استعمال کرتے ہیں۔ بعض اوقات سی ٹی اسکین (تفصیلی ایکسرے) یا ایم آر آئی اسکین (ایسا اسکین جو لیگامنٹ جیسی نرم بافتیں دکھاتا ہے) کی بھی ضرورت ہوتی ہے۔ اگر آپ کو کوئی اور طبی مسائل ہیں تو آپریشن کے دن سے پہلے خون کے ٹیسٹ یا بے ہوشی کے ڈاکٹر (anaesthetist) سے معائنے کی ضرورت ہو سکتی ہے۔
آپریشن کے دن
آپ ہسپتال کے سرجری کے داخلے کے شعبے میں پہنچیں گے، جہاں آپ کا اندراج ہو گا اور آپ کو آپریشن تھیٹر کے لیے تیار کیا جائے گا۔ وہیں آپ کی ملاقات بے ہوشی کے ڈاکٹر سے ہو گی۔ یہ آپریشن جنرل اینستھیزیا (مکمل بے ہوشی) میں کیا جاتا ہے۔ آپریشن کے دوران آپ مکمل طور پر بے ہوش ہوں گے۔ کچھ مریضوں کو آپریشن کے بعد درد سے آرام کے لیے اعصابی بلاک (nerve block)، یعنی ایک انجکشن جو جسم کے ایک حصے کو سُن کر دیتا ہے، بھی دیا جا سکتا ہے؛ بے ہوشی کے ڈاکٹر آپ کے انفرادی حالات کی بنیاد پر اس دن فیصلہ کرتے ہیں۔
پھر آپ کو آپریشن تھیٹر میں لے جایا جاتا ہے، جہاں آپریشن کیا جاتا ہے۔ اس کے بعد آپ ریکوری روم میں جاگیں گے، جہاں بے ہوشی کی دوا کا اثر ختم ہونے تک نرسیں آپ کی نگرانی کرتی ہیں۔ جب آپ کی حالت مستحکم ہو جائے تو طریقۂ کار اور آپ کی بحالی کے لحاظ سے آپ یا تو وارڈ میں جائیں گے یا گھر۔
آپریشن میں کیا کیا جاتا ہے
آپریشن آپ کی کلائی کی ہتھیلی والی طرف ایک چیرے کے ذریعے کیا جاتا ہے۔ اس راستے سے آپ کے سرجن ہڈی کے ٹوٹے ہوئے ٹکڑوں کو ان کی عام جگہ پر واپس لاتے ہیں۔ پھر دھات کی ایک چھوٹی پلیٹ کو ہڈی کے مطابق شکل دی جاتی ہے اور پیچوں سے اپنی جگہ پر لگا دی جاتی ہے۔ پلیٹ کلائی کی ہڈی کے سامنے والے حصے پر بیٹھتی ہے، جہاں اس کے اور آپ کے انگوٹھے اور انگلیوں کو حرکت دینے والے ٹینڈنوں (tendons)، یعنی وہ مضبوط ڈوریاں جو پٹھے کو ہڈی سے جوڑتی ہیں، کے درمیان بافت کی ایک تہہ ہوتی ہے۔
بعض اوقات جوڑ کی سطح کو خود قریب سے دیکھنے کی ضرورت ہوتی ہے۔ ایسی صورت میں آپ کے سرجن ہڈی کے ٹکڑوں کو سیدھ میں لاتے وقت جوڑ کے اندر دیکھنے کے لیے ایک ننھے کیمرے والا پتلا آلہ (دوربین) استعمال کر سکتے ہیں۔ اس سے پلیٹ لگانے سے پہلے اس بات کی تصدیق میں مدد ملتی ہے کہ جوڑ کی سطح ہموار اور برابر ہے۔
جب ہڈی مضبوطی سے تھام لی جائے تو آپ کے سرجن آپریشن کے دوران لیے گئے ایکسرے سے اس کی حالت چیک کرتے ہیں۔ پھر زخم کو ٹانکوں سے بند کیا جاتا ہے اور اوپر زخم کی پٹی رکھ دی جاتی ہے۔
پلیٹ اور پیچ مستقل طور پر آپ کی کلائی میں رہتے ہیں۔ وہ ہڈی کے جڑنے تک اسے مستحکم رکھتے ہیں، جیسے اندرونی اسپلنٹ۔ کچھ فریکچروں میں اضافی سہارے کی ضرورت ہوتی ہے۔ اگر ہڈی کئی ٹکڑوں میں ٹوٹی ہو تو آپ کے سرجن کلائی کی پشت پر دوسری پلیٹ لگا سکتے ہیں، یا خالی جگہیں بھرنے اور ہڈی کے جڑنے میں مدد کے لیے بون گرافٹ (bone graft، ہڈی کا ٹکڑا یا ہڈی کا متبادل) استعمال کر سکتے ہیں۔
آپ زخم کی پٹی لگی حالت میں گھر جائیں گے۔ ہم آپ سے کہتے ہیں کہ اسے خشک رکھیں اور تقریباً 10 دن تک اپنی جگہ لگا رہنے دیں، جب آپ زخم کا معائنہ کروانے کے لیے دوبارہ ہم سے ملیں گے۔
آپریشن کے بعد
جب آپ جاگیں گے تو آپ ریکوری وارڈ میں ہوں گے، جہاں بے ہوشی کی دوا کا اثر ختم ہونے کے دوران نرسیں آپ پر گہری نظر رکھتی ہیں۔ آپ کی کلائی نرم پٹی میں لپٹی ہو گی، اور آپ کو آرام میں رکھنے کے لیے ہم درد کش دوا دیں گے۔ آپ عموماً جلد ہی اٹھ کر چل پھر سکتے ہیں، اور پہلی بار نرسنگ ٹیم کا کوئی فرد آپ کی مدد کرے گا۔ چونکہ بے ہوشی کی دوا کچھ دیر تک آپ کو لڑکھڑاہٹ کا شکار کر سکتی ہے، اس لیے گھر جانے کے بعد پہلے 24 گھنٹے کسی کو اپنے ساتھ رکھیں۔ زیادہ تر مریض اس آپریشن کے بعد ایک رات ہسپتال میں رہتے ہیں، اگرچہ کچھ اسی دن گھر جا سکتے ہیں۔ ہم زخم کی پٹی تقریباً 10 دن تک لگی رہنے دیتے ہیں؛ اس سے پہلے اسے نہ اتاریں، جب تک ہم آپ کو ایسا کرنے کو نہ کہیں۔ جب ہم آپ سے ملتے ہیں تو اسے بدلتے یا اتارتے ہیں۔
صحت یابی
پہلے چند دن آپ کی کلائی میں درد اور سوجن رہے گی، اور یہ معمول کی بات ہے۔ آرام، ہاتھ کو تکیوں پر اونچا رکھنا، اور ہماری دی ہوئی درد کش دوا تکلیف کم کریں گے۔ سوجن عموماً اگلے ہفتوں میں کم ہو جاتی ہے، اگرچہ پوری طرح اترنے میں کچھ وقت لگ سکتا ہے۔
آپ پلستر کے بجائے نرم پٹی کے ساتھ گھر جائیں گے، اس لیے زیادہ تر لوگوں کو روزمرہ زندگی توقع سے آسان لگتی ہے۔ آپ فوراً اٹھ کر چل پھر سکتے ہیں، اور کپڑے پہننے، کھانے اور نہانے دھونے کے لیے اپنا دوسرا ہاتھ استعمال کر سکتے ہیں۔ زخم کی پٹی خشک رکھیں۔ ہینڈ تھراپی آپ کی صحت یابی کا اہم حصہ ہے: آپ Extend Rehabilitation میں ہماری ہینڈ تھراپسٹ (ہاتھ کی بحالی کی ماہر) Ruby Doolan سے ملیں گے، جو آپ کی ورزشوں میں رہنمائی کریں گی اور ضرورت ہو تو آپ کے لیے اسپلنٹ بنائیں گی۔ انگلیوں کو جلد ہلانا اکڑاؤ میں مدد دیتا ہے اور ہڈی جڑنے میں معاون ہوتا ہے۔
ہفتے گزرنے کے ساتھ آپ دیکھیں گے کہ سوجن کم ہو رہی ہے اور حرکت واپس آ رہی ہے۔ آپ کی تھراپسٹ آپ کو گرفت مضبوط کرنے اور کلائی کو دوبارہ موڑنے کی ورزشیں سکھائیں گی۔ جب آپ خود کو مستحکم محسوس کریں تو گھر پر ہلکے کام کر سکتے ہیں، لیکن جب تک ہم نہ بتائیں کہ یہ محفوظ ہے، نہ کوئی بھاری چیز اٹھائیں اور نہ ہی کلائی پر وزن ڈالیں۔ کلائی جڑنے کے دوران آپ گاڑی نہیں چلائیں گے؛ جب زخم کی پٹی اتر جائے اور آپ کے سرجن اجازت دے دیں تو گاڑی چلانا دوبارہ شروع کیا جا سکتا ہے، اور بازو اور ہاتھ کی سرجری کے بعد گاڑی چلانے کے بارے میں ہمارا صفحہ مزید وضاحت کرتا ہے۔
ہر شخص اپنی رفتار سے ٹھیک ہوتا ہے، اس لیے آپ کا وقت مختلف ہو سکتا ہے۔ ہم راستے میں آپ سے ملتے رہیں گے اور ہر مرحلے میں آپ کی رہنمائی کریں گے۔
کیا مسائل پیدا ہو سکتے ہیں
زیادہ تر مریض ٹھیک رہتے ہیں، لیکن کبھی کبھار مسائل پیدا ہو سکتے ہیں۔ آپ کے سرجن اور ٹیم کسی بھی مسئلے کو جلد پکڑنے کے لیے آپ کی قریبی نگرانی کرتے ہیں۔
بعض اوقات دھات کی پلیٹ یا پیچ جلن (irritation) پیدا کرتے ہیں۔ آپ کو جلد کے نیچے ایک تیز ابھار، یا کلائی ہلاتے وقت رگڑ کا احساس ہو سکتا ہے۔ اگر یہ آپ کو پریشان کرے تو اپنے اگلے معائنے پر اس کا ذکر کریں۔
انگوٹھے کو سیدھا کرنے والا ٹینڈن کبھی کبھار گھس کر ٹوٹ سکتا ہے۔ آپ کو یہ اچانک محسوس ہو گا: آپ اپنا انگوٹھا اوپر سیدھا نہیں اٹھا پائیں گے، اور انگوٹھے کی پشت ڈھیلی محسوس ہو گی۔ یہ عموماً آپریشن کے تقریباً 3 ماہ بعد ہوتا ہے، بعض اوقات کسی پیشگی درد کے بغیر۔ اگر آپ کا انگوٹھا اس طرح کام کرنا چھوڑ دے تو بلا تاخیر کلینک سے رابطہ کریں۔
وہ عصب جو آپ کے انگوٹھے، شہادت کی انگلی اور درمیانی انگلی کو احساس دیتا ہے، اس میں جلن ہو سکتی ہے۔ آپ کو ان انگلیوں میں جھنجھناہٹ، سوئیاں چبھنے جیسا احساس، یا کہیں کہیں سُن پن محسوس ہو سکتا ہے۔ ہلکی علامات عام ہیں اور اکثر ٹھیک ہو جاتی ہیں۔ جو سُن پن بہتر نہ ہو رہا ہو، اس کا ذکر اپنی معائنے کی ملاقات پر کریں۔
زخم میں انفیکشن غیر معمولی ہے لیکن اس پر جلد توجہ کی ضرورت ہوتی ہے۔ گہرے، دھڑکتے ہوئے درد پر نظر رکھیں جو سادہ درد کش دواؤں سے کم نہ ہو، زخم سے باہر کی طرف پھیلتی سرخی، گرمی، یا پٹی سے رستا ہوا مائع۔ اگر آپ کو ان میں سے کچھ بھی نظر آئے تو فوراً کلینک کو فون کریں، یا اگر دفتری اوقات کے بعد کا وقت ہو تو ہسپتال کی ایمرجنسی جائیں۔
کبھی کبھار ہڈی جڑنے سے پہلے اپنی جگہ سے ہٹ جاتی ہے، یا جڑنے کا عمل سست ہوتا ہے۔ آپ کو کلائی میں نئی رگڑ یا کھٹکا، بڑھتا ہوا درد، یا کلائی کا جواب دے جانا محسوس ہو سکتا ہے۔ اپنے معائنے پر ہمیں بتائیں تاکہ ہم ایکسرے سے ہڈی کی حالت چیک کر سکیں۔
کچھ کلائیاں جڑنے کے بعد بھی اکڑی ہوئی رہتی ہیں یا ان میں چھونے پر درد رہتا ہے۔ آپ کو ہاتھ گھمانا، کلائی کو پیچھے موڑنا، یا گرفت کرنا توقع سے زیادہ مشکل لگ سکتا ہے۔ ہینڈ تھراپی اور آپ کی تھراپسٹ کی دی ہوئی ورزشیں اس کا بنیادی علاج ہیں۔
تمباکو نوشی اور کسی بھی شکل میں نکوٹین، بشمول پیچ اور گم کے، ان میں سے کئی مسائل کا امکان بڑھا دیتی ہے، جن میں زخم کا انفیکشن، ہڈی کا سست جڑنا اور مزید سرجری شامل ہیں۔ اگر ممکن ہو تو آپریشن سے پہلے اسے چھوڑ دینا فائدہ مند ہے۔
اگر آپ تفصیل جاننا چاہیں تو اس صفحے پر پیچیدگیوں کا جدول عام شرحیں بتاتا ہے۔
ہمیں کب فون کریں
زیادہ تر مسائل انتباہی علامات دیتے ہیں۔ اگر آپ کو بخار ہو، یا زخم زیادہ سرخ یا گرم ہو جائے یا اس سے مائع رسے تو ہمیں فون کریں۔ اگر سادہ درد کش دواؤں کے باوجود درد بڑھتا ہی جائے تو ہمیں فون کریں۔ اگر آپ کو پنڈلی میں سوجن یا درد ہو، یا اچانک سانس پھولنے لگے تو ہسپتال کی ایمرجنسی جائیں، کیونکہ یہ خون کے لوتھڑے کی علامت ہو سکتے ہیں۔ اگر آپ کی انگلیاں سُن ہو جائیں اور سُن ہی رہیں، یا آپ انہیں بالکل ہلا نہ سکیں تو ہسپتال کی ایمرجنسی جائیں۔ اگر آپ کا انگوٹھا سیدھا اٹھنا بند ہو جائے تو بلا تاخیر کلینک سے رابطہ کریں۔ شک ہو تو ہمیں فون کریں۔
اس مسئلے کے بارے میں مزید کہاں پڑھیں
یہ صفحہ خود آپریشن کے بارے میں ہے۔ جس مسئلے کا یہ علاج کرتا ہے، بشمول اس کے کہ شواہد کیا بتاتے ہیں کہ آپریشن کب مدد کرتا ہے اور کب نہیں، اس کی مزید تفصیل ڈسٹل ریڈیس فریکچر کے صفحے پر ہے۔
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- A network meta-analysis of randomized trials found that open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture in terms of early and sustained functional recovery and a reduction in fracture healing complications [7].
- In adults, early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial functional effect compared to late mobilization at earlier stages [1].
- The mean differences in DASH scores at 6 weeks for early mobilization compared to late mobilization surpass the minimal clinically important difference [1].
- Substantial variations in surgical direct costs for distal radius ORIF exist, with implant choice being the predominant driver [3].
- In comminuted intra-articular distal radius fractures, placing the distal row of screws greater than 3mm from subchondral bone was associated with increased odds of worsening ulnar variance [2].
- The Lift-Off Screw (LOS) length can be calculated, and the technique can potentially be used with any distal radius periarticular locking plate with locking options in the shaft [5].
- Radial column plating of the distal radius is a safe treatment modality and a valuable adjunct in the setting of complex distal radius fractures [6].
- Patients undergoing radial column plating of the distal radius should be counseled that there is a 28% chance that hardware removal may be required [6].
- The treatment of displaced intra-articular distal radius fractures with a dorsally versus a volarly placed interlocking plate system demonstrated similar clinical results [9].
Anatomy & Pathophysiology
Bony Anatomy
- The distal radius articular surface is biconcave and consists of scaphoid and lunate facets [31].
- The distal radioulnar joint (DRUJ) articulates with the ulna at the sigmoid notch [31].
- Lister tubercle is a small dorsal prominence that serves as a landmark for the dorsal approach to the wrist [31].
- Lister tubercle is a cause of attritional rupture of the extensor pollicis longus (EPL) after a distal radius fracture [31].
- The distal radial metaphysis has thin cortex and is vulnerable to bending forces [31].
- The brachioradialis insertion on the radial styloid acts as a deforming force in distal radius fractures [31].
- In a normal wrist with neutral ulnar variance, the distal radius bears 80% of axial load [31].
- The carpus encompasses two rows of eight bones that serve as a bridge between the forearm and the hand [19].
- The proximal carpal row from radial to ulnar includes the scaphoid, lunate, and triquetrum [19].
- The distal carpal row from radial to ulnar includes the trapezium, trapezoid, capitate, and hamate [19].
- The scaphoid is a small, irregular S-shaped tubular bone located in the proximal carpal row on the radial aspect of the wrist [25].
- The scaphoid lies entirely within the wrist joint at a 45-degree plane to the longitudinal and horizontal axis of the wrist [25].
- The scaphoid articulates with the trapezium/trapezoid, radius, capitate, and lunate [25].
- The scaphoid has a surface extensively covered with articular cartilage (over 80%), resulting in reduced capacity for periosteal healing and an increased tendency for delayed union and nonunion [25].
- The scaphoid is ridged across its nonarticular dorsoradial surface, along which the critical dorsal ridge vessels traverse [25].
- The dorsal ridge of the scaphoid is the insertion point for both the dorsal component of the scapholunate and intercarpal ligaments [25].
- The radioscapocapitate ligament does not attach to the bone itself but crosses the waist, acting as a sling across it allowing it to rotate [25].
- There are no tendon attachments to the scaphoid [25].
- The scaphoid acts as a midcarpal joint “bridge” linking and synchronizing the motions of the proximal and distal carpal rows as part of the key intercalated segment [25].
- Motion of the scaphoid includes rotation proximally and gliding distally, while providing stability to the midcarpal joint [25].
Vascular Anatomy
- The blood supply of the scaphoid is largely retrograde and meagre, provided by two vascular pedicles originating from the scaphoid branches of the radial artery [25].
- The dorsal branch of the scaphoid blood supply enters via small foramina along the spiral groove and dorsal ridge, supplying 70% to 80% of the scaphoid proximally, including the proximal pole [25].
- The volar branch of the scaphoid blood supply enters via the scaphoid tubercle and supplies the remaining 20% to 30% of the distal scaphoid [25].
- The waist of the scaphoid has minimal or no perforating vasculature [25].
- No vessels perforate the proximal dorsal cartilaginous area or through the scapholunate ligament [25].
- Proximal scaphoid fractures are associated with at least temporary disruption of the interosseous blood supply to the proximal pole [25].
Ligamentous Anatomy
- The extrinsic ligaments of the carpus connect the carpal bones to the forearm bones proximally and the metacarpals distally [27].
- The extrinsic palmar radiocarpal ligaments include the transverse carpal, radioscaphocapitate (RSC), radioscapholunate (RSL), radial collateral, long radiolunate (RLT), and short radiolunate ligaments [27].
- The extrinsic ulnocarpal ligaments include the ulnotriquetral (dorsal and palmar), ulnolunate, and ulnocapitate ligaments [27].
- Strong oblique extrinsic palmar radial ligaments prevent the carpus from translating medially on the angulated slope of the distal radius through two V-shaped ligamentous bands [27].
- The proximal V-shaped ligamentous band connects the forearm to the proximal carpal row and includes the long radiolunate, radioscapholunate, ulnolunate, and ulnotriquetral ligaments [27].
- The distal V-shaped ligamentous band connects the forearm to the distal carpal row and includes the radioscaphocapitate and ulnocapitate ligaments [27].
- A V-shaped interligamentous sulcus over the capitolunate articulation, known as the space of Poirier, is an interval of capsular weakness [27].
- Maximal space of Poirier is seen when the wrist is dorsiflexed, with the space almost disappearing in palmar flexion [27].
- The lunate displaces into the carpal canal through the space of Poirier during dorsal dislocations [27].
- The arcuate ligament is found in the central third of the palmar joint capsule and is formed from the interdigitation of transverse fibers of the radioscaphocapitate, ulnocapitate, triquetrocapitate, and volar scaphotriquetral ligaments [27].
- The arcuate ligament forms a support sling for the midcarpal region, particularly the head of the capitate [27].
- The extrinsic dorsal carpal ligaments include the dorsal radiocarpal (DRC) ligament and the dorsal intercarpal ligament, which form a V-shaped configuration [27].
- The ulnodorsal capsule of the wrist is reinforced by the ulnolunate and ulnotriquetral ligaments and the floors of the fifth and sixth extensor compartments [27].
- The intrinsic ligaments connect individual carpal bones to one another and are intra-articular short fibers [27].
- The intrinsic ligaments include the palmar midcarpal ligaments (scaphotrapeziotrapezoid, scaphocapitate, triquetrocapiate, triquetrohamate), the proximal interosseous ligaments (scapholunate, lunotriquetral), and the distal interosseous ligaments (trapeziotrapezoid, trapeziocapitate, capitohamate) [27].
- The V-shaped scaphotrapezium–trapezoid ligament on the radial side of the wrist provides stability to the scaphoid–trapezium–trapezoid articulation as well as the scaphoid itself [27].
- The scaphocapitate ligament is a large robust ligament that provides midcarpal stability [27].
Pathophysiology & Biomechanics
- Distal radius fractures are the most common fractures of the upper extremity, with over 300,000 cases per year in the United States [31].
- Distal radius fractures have a bimodal distribution: young patients typically sustain high-energy trauma, while elderly patients typically sustain low-energy falls [31].
- In elderly patients, distal radius fractures are the most common upper extremity osteoporotic fracture [31].
- Normal radiographic parameters for the distal radius include an average radial height of 11 mm, radial inclination of 22 degrees, and volar tilt of 11 degrees [31].
- Acceptable radiographic deviations for distal radius fractures include less than 5 mm of shortening, less than a 5-degree change in radial inclination, and less than 10-degree dorsal angulation [31].
- Ulnar variance is assessed with the forearm in neutral rotation and compared with the contralateral side [31].
- The distal radioulnar joint (DRUJ) alignment is assessed on a true lateral radiograph [31].
- Ligamentous injuries associated with distal radius fractures include scapholunate (SL), lunotriquetral (LT), or triangular fibrocartilage complex (TFCC) injuries [31].
- Radiocarpal dislocation or “inferior arc” injury is highly unstable and difficult to reduce closed [31].
- Computed tomography (CT) is used for detail of complex intraarticular patterns, while magnetic resonance imaging (MRI) is used for occult fracture, bone contusion, and associated soft tissue injury [31].
- Placing the distal row of screws greater than 3mm from subchondral bone in comminuted intra-articular distal radius fractures is associated with increased odds of worsening ulnar variance [2].
Classification
- In adults, early mobilization for distal radius fractures treated with open reduction and internal fixation may have a beneficial functional effect compared to late mobilization at earlier stages [1].
- The mean difference in DASH scores at 6 weeks between early and late mobilization for distal radius fractures treated with ORIF surpasses the minimal clinically important difference [1].
- In comminuted intra-articular distal radius fractures, placing the distal row of screws greater than 3mm from subchondral bone is associated with increased odds of worsening ulnar variance [2].
- The Lift-Off Screw (LOS) length can be calculated for accurate sagittal tilt correction in a distal radius fracture model [5].
- The Lift-Off Screw technique can potentially be used with any distal radius periarticular locking plate that has locking options in the shaft [5].
- Open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture in terms of early and sustained functional recovery [7].
- Open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture in terms of a reduction in fracture healing complications [7].
- The lifetime risk of distal radius fracture is 15% for women and 2% for men [13].
- Most distal radius fractures are treated nonsurgically with a plaster cast after closed reduction [13].
- The number of distal radius fractures receiving surgical intervention has increased as surgical treatment has advanced and the general population ages [13].
- Surgical methods for distal radius fractures have shifted from percutaneous pinning or external fixation to open reduction and internal fixation [13].
- The benefit of immediate structural rigidity of fractures, even in osteoporotic bone, after ORIF using volar plating and screws enables early cast removal and mobilization of the hand [13].
- ORIF using volar plating and screws has become the preferred surgical approach among hand and orthopedic surgeons for distal radius fractures [13].
- Complication rates following ORIF of distal radius fractures vary from 0% to 60% [13].
- A systematic review of 55 studies including 3,911 fractures reported complication rates following ORIF of distal radius fractures varying from 0% to 60% [13].
Clinical Presentation
- The mean difference in DASH scores at 6 weeks for early mobilization compared to late mobilization in distal radius fractures treated with ORIF surpasses the minimal clinically important difference [1].
- A network meta-analysis of randomized trials indicates that open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture in terms of early and sustained functional recovery [7].
- Open reduction and internal fixation with a plate is associated with a reduction in fracture healing complications for adult patients with a distal radius fracture compared to other interventions in a network meta-analysis of randomized trials [7].
- The benefit of immediate structural rigidity of distal radius fractures after ORIF using volar plating and screws enables early cast removal and mobilization of the hand [13].
- Complication rates following ORIF of distal radius fractures have been reported to vary from 0% to 60% in a systematic review of 55 studies including 3,911 fractures [13].
Investigations
Imaging Protocols and Diagnostic Sensitivity
- Standard scaphoid radiographs are used for primary assessment to detect displacement and associated fractures in radiocarpal instability [29].
- Provocative stress tests may be required to demonstrate dynamic radiocarpal instability [29].
- CT may be required to better define associated bony injuries in radiocarpal instability [29].
- MRI can be used to determine the extent of ligamentous disruption in radiocarpal instability [29].
- A decrease in the ulnocarpal index may provide the only clue to diagnosis in cases of subtle ulnar translation [29].
- CT is more sensitive for diagnosing a scaphoid fracture and is useful for confirming alignment of bone fragments if surgery is planned [34].
- MRI is the definitive way to confirm or exclude a diagnosis of scaphoid fracture if the technique is available [34].
- 10–15% of scaphoid fractures are not visible on initial X-rays [28].
- If initial X-rays are normal but clinical suspicion remains, the wrist should be immobilized and re-imaged in 2 weeks or via MRI [28].
- Secondary imaging modalities are predominantly used in the assessment of scaphoid fractures and the diagnosis of intercarpal ligament injury and any associated instability [35].
- Ultrasound scanning (USS) is used for suspected carpal fractures and ligament injuries [35].
- CT (2D/3D) is used for suspected carpal fractures, fracture displacement, malunion, nonunion, and bone loss [35].
- Dynamic CT is used by some for ligament injuries [35].
- Bone scintigraphy is used for suspected carpal fractures and avulsion injuries [35].
- Arthrography ± videofluoroscopy is used for ligament injuries [35].
- MRI is used for suspected carpal fractures, avascular necrosis (AVN) of carpal bones, and ligament injuries [35].
- Wrist arthroscopy is used for suspected carpal fractures, fracture displacement, and ligament injuries [35].
- Live/video fluoroscopic evaluation of the wrist provides diagnostic clarity for dynamic instability with sensitivities reported between 86% and 95% and specificity between 80% and 97% for diagnosing scapholunate ligament injury [35].
- Ultrasound scanning (USS) provides an additional tool for the detection of carpal ligament injuries, though the technique is operator dependent [35].
Radiographic Measurements and Instability Patterns
- The lateral intrascaphoid angle is normally 30 degrees ±5 degrees on a sagittal view, with an angle greater than 35 degrees used as a cut-off for displacement [35].
- The AP intrascaphoid angle is normally 40 degrees ± 5 degrees on coronal views [35].
- The dorsal cortical angle is normally 140 degrees, with values greater than 160 degrees considered abnormal on a sagittal view [35].
- The scaphoid height-to-length ratio is normally 0.60, with values greater than 0.65 considered abnormal on a sagittal view [35].
- Intraobserver reliability for the lateral intrascaphoid angle is poor, while interobserver reliability is poor to moderate [35].
- Intraobserver reliability for the dorsal cortical angle is moderate to excellent, while interobserver reliability is moderate to excellent [35].
- Intraobserver reliability for the scaphoid height-to-length ratio is excellent, while interobserver reliability is moderate to excellent [35].
- Dorsal intercalated segmental instability (DISI) is characterized by the lunate tilting backwards and the scaphoid tilting somewhat volarwards [28].
- Volar intercalated segment instability (VISI) is characterized by the lunate and scaphoid tilting somewhat volarwards and the capitate and metacarpals lying anterior (volar) to the radius [28].
- In a normal lateral X-ray, the axes of the radius, lunate, capitate, and third metacarpal are co-linear, and the scaphoid projects at an angle of about 45 degrees to this line [28].
- DISI pattern is most commonly associated with displaced scaphoid fractures and scapholunate dissociation (SLD) [35].
- Assessment of Gilula's lines can aid in the diagnosis of perilunate dislocations [35].
Anatomical Context for Imaging Interpretation
- The proximal carpal row has no direct tendon attachments, and its movement results from bone shape, interaction with other bones, and ligament attachments [19].
- The pisiform bone is a sesamoid bone enclosed within the sheath of the flexor carpi ulnaris tendon and should not theoretically be considered within the proximal carpal row [19].
- The trapezium articulates with the first metacarpal, the trapezoid with the second, the capitate with the third, and the hamate with the fourth and fifth metacarpals [19].
- There is 30 to 40 degrees of flexion–extension and rotation at the metacarpotrapezial joint [19].
- Motion at the distal carpal row is controlled by the extrinsic wrist flexors and extensors [19].
- The ligaments of the wrist are predominantly contained within the joint capsule [19].
- Apart from the scaphocapitate ligament, carpal ligaments are not described consistently across anatomical studies [19].
Treatment
Surgical Approach and Technique
- Open reduction and internal fixation (ORIF) with a plate offers the best results for adult patients with distal radius fractures in terms of early and sustained functional recovery and a reduction in fracture healing complications [7].
- The immediate structural rigidity of fractures after ORIF using volar plating and screws enables early cast removal and mobilization of the hand [13].
- The large tenaculum clamp facilitates anatomical restoration of volar tilt and volar translation while allowing intraoperative fluoroscopy [22].
- The use of a large tenaculum clamp potentially minimizes complications such as flexor tendon abrasion or rupture [22].
- The lift-off screw technique can potentially be used with any distal radius periarticular locking plate with locking options in the shaft [5].
Implant Selection and Positioning
- Substantial variations in surgical direct costs for distal radius ORIF exist, and implant choice is the predominant driver [3].
- Placing the distal row of screws greater than 3mm from subchondral bone was associated with increased odds of worsening ulnar variance in comminuted intra-articular distal radius fractures [2].
Postoperative Management
- Early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial effect compared to late mobilization at earlier stages [1].
- Mean differences in DASH scores at 6 weeks for early mobilization compared to late mobilization surpass the minimal clinically important difference [1].
Complications and Hardware
- There is a 28% chance that hardware removal may be required for patients treated with radial column plating of the distal radius [6].
Complications
- Complication rates following open reduction and internal fixation (ORIF) of distal radius fractures have been reported to vary from 0% to 60% [13].
- A systematic review of 55 studies including 3,911 fractures found no standard for evaluating what should be defined as a complication after ORIF using volar plating [13].
- In a retrospective study of 822 patients, the complication rate following volar locking plate fixation of distal radius fractures was determined as the primary aim [13].
- Radial column plating of the distal radius is associated with a 28% chance that hardware removal may be required [6].
- Open reduction and internal fixation with a plate offers a reduction in fracture healing complications compared to other treatments for adult patients with distal radius fractures [7].
- Early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial functional effect compared to late mobilization, with mean differences in DASH scores at 6 weeks surpassing the minimal clinically important difference [1].
Recovery
- Early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial functional effect compared to late mobilization at earlier stages [1].
Key Evidence
- [L1] Functionally, at earlier stages, early mobilization for patients with distal radius fractures treated with ORIF may have a beneficial effect compared to late mobilization, with mean differences in DASH scores at 6 weeks surpassing the minimal clinically important difference. [1] (10.1186/s13018-021-02837-0)
- [L4] In this two-center retrospective cohort of comminuted intra-articular distal radius fractures, placing the distal row of screws greater than 3mm from subchondral bone was associated with increased odds of worsening ulnar variance. [2] (10.1016/j.jhsa.2025.03.016)
- [L3] Substantial variations in surgical direct costs for distal radius ORIF exist, and implant choice is the predominant driver. [3] (10.1016/j.jhsa.2018.04.015)
- [L5] The LOS length can be calculated, and this technique can potentially be used with any distal radius periarticular locking plate with locking options in the shaft. [5] (10.1016/j.jhsa.2018.02.011)
- [L4] Radial column plating of the distal radius is a safe treatment modality and a valuable adjunct in the setting of complex distal radius fractures, but patients should be counseled that there is a 28% chance that hardware removal may be required. [6] (10.1177/1558944718760861)
- [L1] A network meta-analysis of randomized trials revealed that open reduction and internal fixation with a plate offers the best results for adult patients with a distal radius fracture, in terms of early and sustained functional recovery and a reduction in fracture healing complications. [7] (10.5435/jaaos-d-18-00424)
- [L3] The treatment of displaced intra-articular distal radius fractures with a dorsally versus a volarly placed interlocking plate system demonstrated similar clinical results. [9] (10.1177/1558944716675129)
- [L4] [13] (10.1016/j.jhsa.2022.11.012)
- [L4] The large tenaculum clamp facilitates anatomical restoration of volar tilt and volar translation while allowing intraoperative fluoroscopy, potentially minimizing complications such as flexor tendon abrasion or rupture. [22] (10.1016/j.jhsa.2018.11.017)
References
[1] In adults, early mobilization may be beneficial for distal radius fractures treated with open reduction and internal fixation: a systematic review and meta-analysis. Journal of Orthopaedic Surgery and Research. 2021. DOI: 10.1186/s13018-021-02837-0
[2] The Association Between Distal Screw and Articular Subsidence in the Open Treatment of Intra-articular Distal Radius Fractures. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2025.03.016
[3] Evaluation of Factors Driving Cost Variation for Distal Radius Fracture Open Reduction Internal Fixation. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.04.015
[5] Lift-Off Screw Results in Accurate Sagittal Tilt Correction in a Distal Radius Fracture Model. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.02.011
[6] Complications of Radial Column Plating of the Distal Radius. HAND. 2018. DOI: 10.1177/1558944718760861
[7] Interventions for Distal Radius Fractures: A Network Meta-analysis of Randomized Trials. Journal of the American Academy of Orthopaedic Surgeons. 2019. DOI: 10.5435/jaaos-d-18-00424
[9] Management of Intra-Articular Distal Radius Fractures: Volar or Dorsal Locking Plate—Which Has Fewer Complications?. HAND. 2016. DOI: 10.1177/1558944716675129
[13] Complications After Volar Locking Plate Fixation of Distal Radius Fractures: A Retrospective Study of 822 Patients. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2022.11.012
[19] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Pathoanatomy and Applied Anatomy Relating to Carpal Fractures and Dislocations.
[22] Use of a Large Tenaculum Clamp as a Reduction Technique for Treatment of Distal Radius Fractures. The Journal of Hand Surgery. 2019. DOI: 10.1016/j.jhsa.2018.11.017
[25] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Pathoanatomy and Applied Anatomy Related to Scaphoid Fractures.
[27] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Extrinsic Ligaments.
[28] Apley And Solomon S Concise System Of Orthopaedics And Trauma. FRACTURES OF THE DISTAL RADIUS IN CHILDREN > Imaging.
[29] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Assessment of Radiocarpal Instability.
[31] Miller S Review Of Orthopaedics. SECTION 16 PATELLAR TRACKING IN TOTAL KNEE ARTHROPLASTY > DISTAL RADIUS FRACTURES.
[34] Apley And Solomon S Concise System Of Orthopaedics And Trauma. FRACTURES OF THE DISTAL RADIUS IN CHILDREN > FRACTURE OF THE SCAPHOID.
[35] Rockwood And Green S Fractures In Adults. 42: Fractures of the Distal Radius and Ulna > Secondary Imaging Methods.