Patients › Wrist
کلائی کا مکمل فیوژن (Total Wrist Fusion)
Wrist fusion permanently joins wrist bones to relieve pain from arthritis or injury.
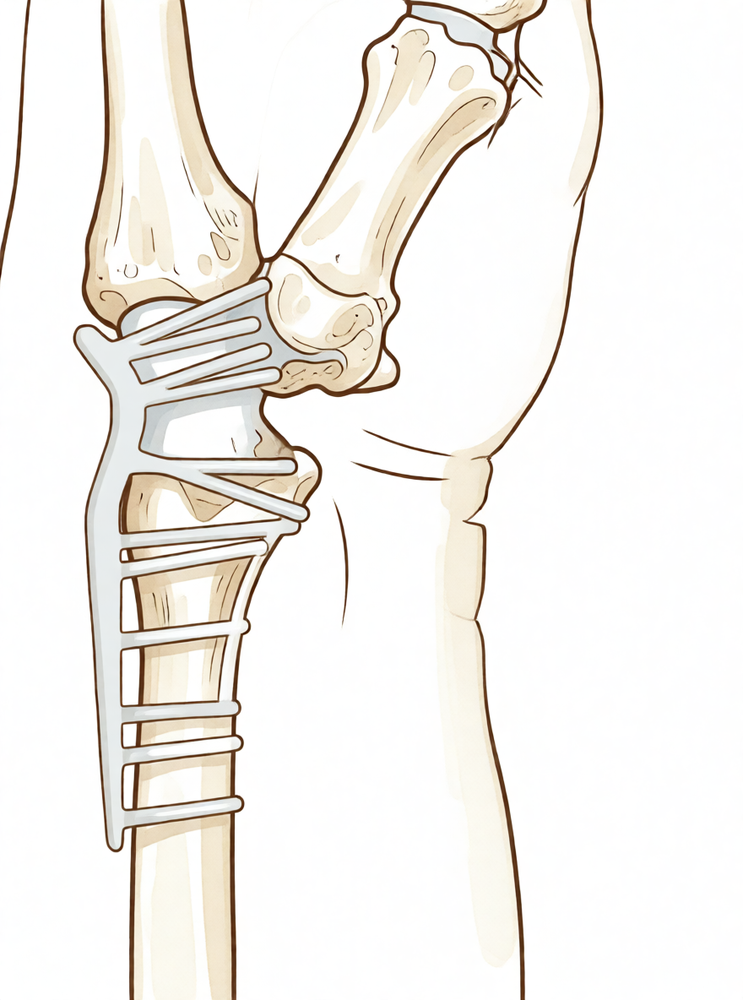
یہ آپریشن کیوں تجویز کیا گیا ہے
ڈاکٹر کیرن ہِرپرا، جو Mater Private Hospital Rockhampton میں بازو اور ہاتھ کے سرجن (upper-limb surgeon) ہیں، سب سے کم چیر پھاڑ والے ان طریقوں سے آغاز کرتے ہیں جو آپ کی حالت کے لیے موزوں ہوں۔ مریض عموماً اپنے فیملی ڈاکٹر (GP) کے ذریعے ہمارے کلینک بھیجے جاتے ہیں؛ اگر کسی فزیوتھراپسٹ نے آپ کو ہمیں دکھانے کا مشورہ دیا ہے، تب بھی میڈیکیئر (Medicare) کی رقم واپسی کا حق دار ہونے کے لیے آپ کو اپنے فیملی ڈاکٹر سے ریفرل (referral) کی ضرورت ہوگی۔ کلینک میں معائنہ، جس میں آپ کی تکلیف کی تاریخ، جسمانی معائنہ اور ضرورت ہو تو اسکین شامل ہیں، تشخیص طے کرتا ہے۔
کلائی کا آرتھرائٹس (جوڑ کی خرابی اور سوزش) درد، گرفت کی کمزوری اور کبھی کبھی ایسی کلائی کا سبب بنتا ہے جو مستحکم نہیں رہتی۔ بہت سے لوگوں کے لیے پہلے بغیر آپریشن کا علاج کیا جاتا ہے: سرگرمیوں میں تبدیلی، ہینڈ تھراپی، اسپلنٹ یا انجکشن۔ جب ان اقدامات سے آپ کو کافی بہتری نہ ملی ہو تو ہم کلائی کا مکمل فیوژن (دو ہڈیوں کو جوڑ کر ایک کر دینا) تجویز کرتے ہیں۔ یہ آپریشن کلائی کی ہڈیوں کو آپس میں جوڑ دیتا ہے تاکہ وہ ایک ٹھوس ٹکڑے کی صورت میں جڑ جائیں۔ اس سے گھسی ہوئی جوڑ کی سطحوں کے درمیان دردناک رگڑ رک جاتی ہے۔ یہ عموماً چوٹ کے بعد جوڑ کے گھسنے والے شدید آرتھرائٹس (wear-and-tear arthritis) کے لیے، یا ریومیٹائیڈ آرتھرائٹس سے خراب ہونے والی ایسی کلائی کے لیے تجویز کیا جاتا ہے جو غیر مستحکم یا ٹیڑھی ہو گئی ہو۔ اگر کلائی کے جوڑ کی پچھلی تبدیلی (wrist replacement) ناکام ہو گئی ہو تو بھی اس پر غور کیا جا سکتا ہے۔ مقصد ایک مستحکم، مضبوط کلائی ہے جس میں درد بہت کم ہو، تاکہ آپ اعتماد کے ساتھ اپنا ہاتھ استعمال کر سکیں۔
آپریشن سے پہلے
آپ کے سرجن آپ کی کلائی کے اسکین، جیسے ایکسرے یا ایم آر آئی اسکین، کی مدد سے آپریشن کی منصوبہ بندی کریں گے۔ ایم آر آئی ایک طاقتور مقناطیس کے ذریعے تفصیلی تصاویر لیتا ہے اور ایسے مسائل دکھا سکتا ہے جو عام ایکسرے میں نظر نہیں آتے۔ سرجری سے پہلے آپ کو اپنی دواؤں کے بارے میں واضح ہدایات دی جائیں گی۔ کچھ دواؤں کو تھوڑے عرصے کے لیے روکنا پڑ سکتا ہے، اور آپ کے سرجن آپ کو بتائیں گے کہ کون سی اور کتنے عرصے کے لیے۔ آپریشن کے وقت سے سات گھنٹے پہلے کھانا پینا بند کر دیں۔ ہم چھ کے بجائے سات گھنٹے اس لیے کہتے ہیں تاکہ اگر آپریشن کی فہرست وقت سے پہلے چلے تو آپ کو پہلے بلایا جا سکے۔ بعد میں آپ کو گھر لے جانے کے لیے کسی کا انتظام کریں۔ اپنی موجودہ دواؤں کی فہرست ساتھ لائیں۔ ڈھیلے، آرام دہ کپڑے پہنیں۔ اگر آپ کو کوئی اور طبی مسئلہ ہے تو ہو سکتا ہے آپ کو خون کے ٹیسٹ کروانے یا بے ہوشی کے ڈاکٹر (anaesthetist) سے معائنہ کروانے کی ضرورت ہو۔
آپریشن کے دن
آپ ہسپتال کے سرجری کے داخلے کے شعبے میں پہنچیں گے، جہاں آپ کا اندراج کیا جائے گا اور آپ کو آپریشن تھیٹر کے لیے تیار کیا جائے گا۔ وہاں آپ کی ملاقات بے ہوشی کے ڈاکٹر سے ہوگی۔ یہ آپریشن جنرل اینستھیزیا (مکمل بے ہوشی) میں کیا جاتا ہے۔ آپریشن کے دوران آپ مکمل طور پر بے ہوش ہوں گے۔ کچھ مریضوں کو آپریشن کے بعد درد سے آرام کے لیے اعصابی بلاک (nerve block)، یعنی ایک انجکشن جو جسم کے ایک حصے کو سُن کر دیتا ہے، بھی دیا جا سکتا ہے؛ بے ہوشی کے ڈاکٹر آپ کے انفرادی حالات کی بنیاد پر اسی دن اس کا فیصلہ کرتے ہیں۔ پھر آپ کو آپریشن تھیٹر لے جایا جاتا ہے، جہاں آپریشن کیا جاتا ہے۔
آپ ریکوری روم میں ہوش میں آتے ہیں، جہاں بے ہوشی کا اثر ختم ہونے تک نرسیں آپ کی نگرانی کرتی ہیں۔ جب آپ کی حالت مستحکم ہو جائے تو آپریشن کی نوعیت اور آپ کی صحت یابی کے لحاظ سے آپ یا تو وارڈ میں جاتے ہیں یا گھر چلے جاتے ہیں۔
آپریشن میں کیا کیا جاتا ہے
آپ کے سرجن آپ کی کلائی کی پشت پر ایک چیرا لگاتے ہیں۔ اس راستے سے وہ کلائی کی چھوٹی ہڈیوں اور بازو کی ہڈی کے سرے کے درمیان گھسی ہوئی جوڑ کی سطحوں تک پہنچتے ہیں۔ وہ ان سطحوں سے باقی ماندہ چکنی کارٹلیج (cartilage)، یعنی جوڑ میں ہڈیوں کے سروں پر چکنی، لچکدار تہہ، اور ساتھ ہی کوئی سخت ہو چکی ہڈی بھی نکال دیتے ہیں، تاکہ جوڑی جانے والی ہر جوڑ کی دونوں طرف تازہ، خون والی ہڈی سامنے آ جائے۔ کھلی ہڈی کا کھلی ہڈی سے یہی ملاپ ہڈیوں کو ایک ٹھوس ٹکڑے کی صورت میں جڑنے دیتا ہے۔
پھر آپ کے سرجن ہڈیوں کو کام کے لیے موزوں حالت میں سیدھا کرتے ہیں اور جڑنے تک انہیں ساکن رکھتے ہیں۔ دھات کی ایک خاص شکل کی پلیٹ کلائی کی پشت پر لگائی جاتی ہے اور پیچوں سے ہڈیوں میں کس دی جاتی ہے۔ پلیٹ ہر چیز کو اپنی جگہ پر رکھتی ہے تاکہ جڑنے کے دوران ہڈیاں اپنی جگہ سے نہ ہلیں۔ کچھ صورتوں میں، جڑنے میں مدد کے لیے آپ کے سرجن تھوڑا سا اضافی ہڈی کا گرافٹ (bone graft، ہڈی کا اضافی ٹکڑا) بھی لگا سکتے ہیں۔
جب ہڈیاں مضبوطی سے اپنی جگہ پر ہوں تو آپ کے سرجن چیرے کو ٹانکوں سے بند کرتے ہیں اور زخم کی پٹی لگاتے ہیں۔
آپریشن کے بعد
آپ ریکوری روم میں ہوش میں آئیں گے، جہاں بے ہوشی کا اثر ختم ہونے کے دوران نرسیں آپ پر نظر رکھیں گی۔ آپ کی کلائی کو اسپلنٹ یا پلستر سے سہارا دیا جائے گا، اور زخم پر پٹی ہوگی۔ ہم پٹی تقریباً 10 دن تک لگی رہنے دیتے ہیں؛ براہِ کرم اس سے پہلے اسے نہ اتاریں جب تک ہم آپ کو نہ کہیں۔ جب ہم آپ کو دیکھتے ہیں تو اسے بدلتے یا اتارتے ہیں۔ ہسپتال سے جانے سے پہلے آپ کے لیے درد سے آرام کا منصوبہ بنایا جاتا ہے، اور اگر آپ کو تکلیف ہو تو نرسیں اس میں ردوبدل کر سکتی ہیں۔ آپ سرجری کے دن ہی اپنے دوسرے ہاتھ کا سہارا لے کر اٹھ سکیں گے اور چل پھر سکیں گے۔ زیادہ تر مریض اس آپریشن کے بعد ایک رات ہسپتال میں رہتے ہیں، اگرچہ کچھ اسی دن گھر جا سکتے ہیں۔ براہِ کرم انتظام کریں کہ گھر پہنچنے کے بعد پہلے 24 گھنٹے کوئی آپ کے ساتھ رہے۔
صحت یابی
پہلے چند دنوں میں آپ کی کلائی میں درد اور سوجن ہوگی۔ یہ آہستہ آہستہ ٹھیک ہو جاتا ہے۔ ہاتھ کو تکیوں پر اونچا رکھنا، رات کو بھی، سوجن اور تکلیف کو کم کرنے میں مدد کرتا ہے۔ درد بڑھنے کا انتظار کرنے کے بجائے وہ درد کی دوا لیں جو آپ کے لیے تجویز کی گئی ہے۔
جب تک ہڈیاں آپس میں جڑ رہی ہیں، آپ کی کلائی اسپلنٹ یا پلستر میں رہے گی۔ آپ روزمرہ کے کاموں جیسے کپڑے پہننے، کھانے اور نہانے دھونے کے لیے اپنا دوسرا ہاتھ استعمال کریں گے۔ آپ گھر میں چل پھر سکتے ہیں اور ہلکی سرگرمیاں کر سکتے ہیں، لیکن جب تک آپ کی کلائی کو ساکن رکھا گیا ہو، آپ ہرگز گاڑی نہ چلائیں۔ جب پلستر یا اسپلنٹ اتر جائے اور آپ کے سرجن اجازت دے دیں تو گاڑی چلانا شروع کیا جا سکتا ہے؛ بازو اور ہاتھ کی سرجری کے بعد گاڑی چلانا کے بارے میں ہمارا صفحہ اس کی مزید تفصیل بتاتا ہے۔
ہینڈ تھراپی سرجری کے جلد بعد شروع ہوتی ہے اور آپ کی انگلیوں، کلائی اور بازو کے نچلے حصے میں اکڑاؤ کو روکنے میں مدد کرتی ہے۔ آپ کی ہینڈ تھراپسٹ (ہاتھ کی بحالی کی ماہر)، Ruby Doolan جو Extend Rehabilitation میں ہیں، آپ کی ورزشوں میں رہنمائی کریں گی اور جس اسپلنٹ کی ضرورت ہو وہ بنائیں گی۔ ہلکی حرکت جلد شروع کرنے سے آپ مفید حرکت جلد دوبارہ حاصل کر لیتے ہیں اور اکثر مجموعی طور پر تھراپی کے لیے کم بار آنا پڑتا ہے۔
چونکہ کلائی کی ہڈیاں جڑ جاتی ہیں، اس لیے آپ کی کلائی کا وہ حصہ اب نہیں مڑے گا۔ زیادہ تر لوگ اچھی طرح ڈھل جاتے ہیں اور کچھ نئی عادتوں کے ساتھ اپنی روزمرہ سرگرمیاں سنبھال لیتے ہیں۔ آپ کا بازو اب بھی گھوم سکتا ہے، اس لیے بہت سے کام آرام دہ رہتے ہیں۔ جب ہڈیاں جڑ جائیں اور آپ کی گرفت مضبوط محسوس ہو تو آپ آہستہ آہستہ کام اور دوسری سرگرمیوں پر واپس آ سکتے ہیں۔
ہر شخص اپنی رفتار سے ٹھیک ہوتا ہے، اس لیے آپ کا وقت مختلف ہو سکتا ہے۔ آپ کے سرجن اور آپ کی ہینڈ تھراپسٹ ہر قدم پر آپ کی رہنمائی کریں گے۔
کیا مسائل پیدا ہو سکتے ہیں
زیادہ تر مریض ٹھیک رہتے ہیں، لیکن کبھی کبھار مسائل پیدا ہو سکتے ہیں۔ آپ کے سرجن اور ٹیم کسی بھی مسئلے کو جلد پکڑنے کے لیے آپ کی قریب سے نگرانی کرتے ہیں۔
دھات کی پلیٹ اور پیچ ہڈیوں کو جڑنے تک ساکن رکھتے ہیں۔ کبھی کبھی یہ دھاتی پرزے تکلیف کا باعث بنتے ہیں یا تھوڑا سا اپنی جگہ سے ہل جاتے ہیں۔ آپ کو جلد کے نیچے کوئی تیز کنارہ محسوس ہو سکتا ہے، یا پلیٹ کے اوپر ستانے والی دکھن جو عام درد کش دوا سے ٹھیک نہ ہو۔ اگر اس سے آپ کو پریشانی ہو تو اپنے اگلے معائنے پر اس کا ذکر کریں۔ ہڈیاں جڑ جانے کے بعد دھاتی پرزے نکالے جا سکتے ہیں۔
کبھی کبھار کلائی کی ہڈیاں منصوبے کے مطابق آپس میں نہیں جڑتیں۔ اسے ہڈیوں کا نہ جڑنا (nonunion) کہتے ہیں۔ اس مسئلے والے بہت سے لوگوں کو بالکل کچھ محسوس نہیں ہوتا، اور اس سے کوئی علامات نہیں ہوتیں۔ اگر اس خلا سے ایسا درد ہو جو ٹھیک نہ ہو تو آپ کے سرجن معائنے پر آپ کے ساتھ مختلف طریقوں پر بات کریں گے۔
کلائی کے درمیان سے گزرنے والا عصب سرجری کے بعد سوجن کی وجہ سے دب سکتا ہے۔ اسے کارپل ٹنل سنڈروم (کلائی میں عصب کا دبنا) کہتے ہیں۔ آپ کو انگوٹھے، شہادت کی انگلی اور درمیانی انگلی میں جھنجھناہٹ، سوئیاں چبھنے جیسا احساس یا سُن پن محسوس ہوگا، جو اکثر رات کو زیادہ ہوتا ہے۔ اگر ایسا ہو تو اپنے سرجن کو بتائیں۔ اس کا علاج عموماً عصب پر دباؤ ختم کرنے کے ایک چھوٹے آپریشن سے کیا جا سکتا ہے۔
زخم بھرنے میں مسائل ہو سکتے ہیں۔ اپنی پٹی کے ارد گرد جلد پر نظر رکھیں کہ کہیں سرخی پھیل تو نہیں رہی، گرمائش بڑھ تو نہیں رہی، رطوبت تو نہیں رِس رہی یا ناگوار بو تو نہیں آ رہی۔ جو زخم ٹھیک نہ ہو رہا ہو اسے علاج کی ضرورت ہو سکتی ہے۔ اگر آپ کو یہ علامات نظر آئیں تو اپنی اگلی ملاقات کا انتظار کرنے کے بجائے فوراً کلینک سے رابطہ کریں۔
ٹینڈن (tendon)، یعنی وہ مضبوط ڈوری جو پٹھے کو ہڈی سے جوڑتی ہے، کبھی کبھار کلائی کے قریب جلن (irritation) کا شکار ہو سکتے ہیں یا پھٹ سکتے ہیں۔ آپ کو اچانک کمزوری محسوس ہو سکتی ہے، مثلاً کوئی انگلی جو ٹھیک سے سیدھی نہ ہو، اور ساتھ ہاتھ کی پشت پر سوجن یا چھونے پر درد۔ اس کے بارے میں جلد اپنے سرجن کو بتائیں۔
اگر آپ کی کلائی کے جوڑ کی پچھلی تبدیلی ناکام ہو گئی ہو، تو اس کے بعد کیا جانے والا فیوژن پھر بھی مسئلے کو ٹھیک کر سکتا ہے، اگرچہ صحت یابی پہلی بار کے فیوژن کے مقابلے میں تھوڑی سست ہو سکتی ہے۔
اگر آپ تفصیلات جاننا چاہتے ہیں تو اس صفحے پر پیچیدگیوں کا جدول عام شرحیں بتاتا ہے۔
ہمیں کب فون کریں
زیادہ تر مسائل پہلے چند ہفتوں میں ظاہر ہوتے ہیں۔ اگر آپ کو بخار ہو، یا آپ کے زخم کے ارد گرد جلد زیادہ سرخ، گرم ہو جائے یا اس سے رطوبت رسنے لگے تو ہمیں فون کریں۔ اگر آپ کا درد اچانک بڑھ جائے، یا آپ کو ایسی جھنجھناہٹ یا سُن پن محسوس ہو جو پہلے نہیں تھا، تو ہمیں فون کریں۔ اگر آپ کی پنڈلی سوجی ہوئی اور دردناک ہو، یا آپ کا سانس پھولنے لگے، تو ہسپتال کی ایمرجنسی جائیں۔ اگر آپ اپنے ہاتھ یا انگلیوں کو بالکل محسوس نہ کر سکیں یا بالکل حرکت نہ دے سکیں تو ہسپتال کی ایمرجنسی جائیں۔
اس مسئلے کے بارے میں مزید کہاں پڑھیں
یہ صفحہ خود آپریشن کے بارے میں ہے۔ جس مسئلے کا یہ علاج کرتا ہے، بشمول اس کے کہ شواہد سرجری کے فائدہ مند ہونے اور نہ ہونے کے بارے میں کیا بتاتے ہیں، اس کی مزید تفصیل کلائی کے آرتھرائٹس (wrist osteoarthritis) والے صفحے پر ہے۔
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Anatomy & Pathophysiology
Bony Anatomy
- The wrist is the anatomic region between the forearm and the hand, including the distal radioulnar, radiocarpal, and ulnocarpal joints and the eight carpal bones [2].
- The proximal row of carpal bones consists of the scaphoid, lunate, triquetrum, and pisiform [2].
- The distal row of carpal bones consists of the trapezium, trapezoid, capitate, and hamate [2].
- The pisiform and trapezoid are the smallest carpal bones, while the capitate is the largest [2].
- The capitate articulates with seven other carpal bones, whereas the pisiform articulates with only one (the triquetrum) [2].
- The radiocarpal joint is formed by the articulation of the distal radius with the scaphoid and lunate, and the triquetrum on the triangular fibrocartilage [2].
- The distal concave articular surfaces of the proximal carpal row form the midcarpal articulations with the distal row [2].
- The distal ulnar convexity articulates at the lesser sigmoid notch of the distal radius [2].
- The sigmoid notch articular surface accommodates the ulnar head through two thirds of its arc [2].
- There is approximately a 20-degree inclination of the distal ulna at its articulation with the radius [2].
- The ulnar styloid lies dorsal to the ulnar head and extends distally [2].
- The distal radius has three articular components: the scaphoid fossa, the lunate fossa, and the sigmoid notch [6].
- A ridge between the scaphoid and lunate fossae corresponds with the scapholunate interval [6].
- The radial styloid allows attachment of the brachioradialis tendon and is the origin of the radial scapholunate and radial lunocapitate ligaments [6].
- The concave elliptical distal radius is oriented in the sagittal plane with an average of 11 degrees of volar tilt [6].
- In the frontal plane, the average radial inclination of the distal radius is 23 degrees [6].
- Radial length, measured from the tip of the radial styloid to the ulnar articular surface, averages 13 mm [6].
- The interosseous membrane connects the shafts of the radius and ulna, with a thickened central portion important for force transmission [6].
Ligamentous Anatomy
- The triangular fibrocartilage complex (TFCC) attaches to the ulnar margin of the lunate fossa of the radius [2].
- The TFCC includes the ulnar collateral ligament, dorsal and volar radioulnar ligaments, articular disc, meniscal homologue, extensor carpi ulnaris sheath, and ulnolunate and ulnotriquetral ligaments [2].
- Extrinsic carpal ligaments connect the radius or the ulna to the carpus [7].
- Volar extrinsic ligaments are generally stronger than dorsal ligaments [7].
- The radioscaphocapitate ligament connects to the waist of the scaphoid and limits ulnar translation of the carpus [7].
- The long radiolunate ligament helps limit ulnar translocation of the carpus [7].
- The short radiolunate ligament helps control lunate position [7].
- The radioscapholunate ligament is a vascular conduit (ligament of Testut) rather than a true ligament [7].
- The ulnolunate ligament attaches to the palmar radioulnar ligament and the lunate [7].
- The ulnocapitate ligament attaches to the ulnar head and is the most superficial or palmar ulnocarpal ligament [7].
- The ulnotriquetral ligament attaches to the palmar radioulnar ligament and the triquetrum [7].
- The dorsal radiocarpal ligament has a trapezoidal shape, passing from the dorsal rim of the distal radius to the lunate and triquetrum [7].
- The dorsal radiocarpal ligament is associated with dorsal and volar intercalated segmental stabilities [7].
- Intrinsic carpal ligaments originate and insert within the carpus [7].
- The scapholunate interosseous ligament (SLIL) is a major stabilizer of the wrist and the most commonly injured wrist ligament [7].
- The SLIL is C-shaped, consisting of dorsal, palmar, and interosseous portions, with the dorsal portion being the strongest and thickest [7].
- The SLIL provides a flexion force on the lunate due to its attachment to the scaphoid [7].
- The lunotriquetral interosseous ligament (LTIL) is C-shaped, with the volar portion being the thickest and strongest [7].
- The LTIL provides an extension moment on the lunate due to its attachment to the triquetrum [7].
- The capitohamate ligament is a thick ligament measuring 5 × 5 mm in cross section, with extensions to the third or fourth metacarpals [7].
- The dorsal intercarpal ligament passes from the dorsal tubercle of the triquetrum to the distal pole of the scaphoid [7].
- The dorsal intercarpal ligament reinforces the elastic dorsal wrist capsule and stabilizes the scapholunate articulation [7].
- The space of Poirier is an area adjacent to the proximal capitate without ligamentous attachment, situated ulnar to the radioscaphocapitate ligament and radial to the long radiolunate ligament [7].
- The space of Poirier is a weak area vulnerable to instability, through which the distal carpal row separates from the lunate during a perilunate dislocation [7].
- The dorsal wrist ganglion is typically located directly over the scapholunate ligament [16].
Biomechanics and Kinematics
- The wrist joint’s motion planes include flexion, extension, radial deviation, ulnar deviation, and circumduction [7].
- There is minimal carpal motion with pronosupination [7].
- Approximately 62° of wrist extension occurs through the radiocarpal joint [7].
- 62% of wrist flexion occurs through the midcarpal joint [7].
- The midcarpal joint is mostly responsible for 20° of radial deviation and 40° of ulnar deviation [7].
- The midcarpal joint is responsible for the “dart thrower’s motion,” which involves moving from radial extension into ulnar flexion positioning of the wrist [7].
- The radius bears 80% of the axial load transmitted through the radiocarpal joint in neutral ulnar variance [7].
- The ulna bears 20% of the axial load transmitted through the radiocarpal joint in neutral ulnar variance [7].
- The proximal row of carpal bones forms an intercalated segment between the distal carpal row and the distal radius, bound into a functional unit by the SLIL and LTIL [7].
- The distal row of carpal bones is rigid with little motion between its bones due to stout intercarpal ligaments, acting as a functional unit with the scaphoid bridging both rows [7].
- During wrist flexion from neutral, the distal row flexes and ulnarly deviates slightly while the scaphoid pronates [7].
- During wrist flexion from neutral, the proximal row flexes differentially, with more rotation through the scaphoid, followed by the triquetrum and the lunate [7].
- During wrist flexion from neutral, the proximal row translates dorsally [7].
- During wrist extension from neutral, the distal row extends and radially deviates slightly while the scaphoid supinates [7].
- During wrist extension from neutral, the proximal row extends differentially, with more motion in the scaphoid, followed by the triquetrum and then the lunate [7].
- During wrist extension from neutral, the proximal row translates palmarly [7].
- The eight carpal bones represent the most complex articular system in the human body [3].
- Injuries to the wrist mechanism can lead to instability, resulting in a painful lack of motion, strength, and function [3].
Investigations
Magnetic Resonance Imaging
- MRI was first reported for hand and wrist imaging in 1986 [8].
- The primary advantages of MRI compared with CT and radiography are improved tissue characterization, especially of soft tissues such as ligamentous structures in the wrist and synovium in the hand, and the lack of ionizing radiation [8].
- MRI is the modality of choice for imaging radiographically occult fractures of the hand and wrist [8].
- Early MRI was limited by low magnetic field strength (0.15 T) and limited image options and processing [8].
- Modern MRI is generally at 1.5T or 3T with a wide variety of imaging options and powerful image processing [8].
- 3T is much preferred for hand and wrist imaging, especially for imaging small fields of view [8].
- Dedicated extremity magnets have been marketed, but image quality is poor compared with conventional MR imaging [8].
- 7T MRI has recently become approved for clinical use [8].
- 7T MRI has more than double the magnetic field strength of 3T MRI and has the potential to become a powerful tool for hand and wrist imaging as applications are developed [8].
- MRI with contrast enhancement is most commonly used to determine whether soft-tissue lesions are solid or cystic [8].
- In rheumatologic imaging, MRI with contrast enhancement is used to better visualize erosions and synovial burden [8].
- Dynamic contrast enhancement has been used with inconsistent results to assess for the presence of avascular necrosis in the lunate or scaphoid after injury [8].
- MR angiography of the hand and wrist can be helpful in situations such as diagnosis of the hypothenar hammer syndrome [8].
- MR arthrography can be performed for evaluation of the triangular fibrocartilage and intercarpal ligament tears, but this is generally unnecessary with the increasing availability of high field MRI [8].
Computed Tomography and Other Modalities
- Hybrid SPECT/CT has been used for the diagnosis of radiographic occult fractures of the wrist [4].
- Cone-beam CT has been used in the diagnosis of scaphoid fractures [4].
- CT and MRI have a diagnostic impact on wrist injuries in young adults [4].
- Cine MRI is a new approach to the diagnosis of scapholunate dissociation [4].
- Cone-beam computed tomography arthrography is an innovative modality for the evaluation of wrist ligament and cartilage injuries [4].
- 3D analysis of the wrist has been described [4].
- Normal and variant anatomy of the wrist and hand can be evaluated on MR imaging [4].
- Low-field MRI has been used for scaphoid fracture evaluation [5].
- Occult wrist fractures can be detected by magnetic resonance imaging [5].
- MR imaging has been used to evaluate the triangular fibrocartilage complex [5].
- MR imaging and computed tomography arthrography have been used for preoperative evaluation of the ulnar collateral ligament [5].
- Histologic and magnetic resonance imaging correlations have been established in Kienbock’s disease [5].
- MRI diagnosis of occult dorsal wrist ganglion has been evaluated [5].
Radiography and Stress Views
- Distal radioulnar joint stress radiography has been used for detecting radioulnar ligament injury [4].
- Radiographic stress views have been compared for scapholunate dynamic instability in a cadaver model [4].
- Simple plain radiographic signs and measures have been evaluated for the accuracy of diagnosing acute scapholunate ligament injuries of the wrist [9].
- Radiographic clues have been described for determining carpal instability and treatment protocol for scaphoid fractures [9].
References
[2] Campbell S Operative Orthopaedics 4 Volume Set. NERVE INJURIES AT THE LEVEL OF THE HAND AND WRIST > ANATOMY.
[3] Green S Operative Hand Surgery. INTRODUCTION.
[4] Campbell S Operative Orthopaedics 4 Volume Set. ANATOMIC RECONSTRUCTION OF THE DISTAL RADIOULNAR LIGAMENTS > RADIOGRAPHIC TECHNIQUES.
[5] Campbell S Operative Orthopaedics 4 Volume Set. ELBOW, WRIST, AND HAND.
[6] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 2Musculoskeletal Trauma Surgery > FRACTURES AND DISLOCATIONS OF THE DISTAL AND MID-FOREARM.
[7] Aaos Comprehensive Orthopaedic Review 3. Carpal Instability* > II. Anatomy and Biomechanics (See Chapter 92).
[8] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Imaging: Advances in Imaging of the Hand and Upper Extremity > Magnetic Resonance Imaging.
[9] Campbell S Operative Orthopaedics 4 Volume Set. ANATOMIC RECONSTRUCTION OF THE DISTAL RADIOULNAR LIGAMENTS > DIAGNOSIS AND EVALUATION.
[16] Green S Operative Hand Surgery. BOX 59.1 Ganglions of the Hand and Wrist > Operative Treatment > Dorsal Wrist Ganglion.