Patients › Hand
فلیکسر ٹینڈن کے غلاف کے گینگلیئن کو نکالنے کا آپریشن
Excision of a flexor tendon sheath ganglion — when surgery is considered for painful or limiting cysts.
یہ آپریشن کیوں تجویز کیا گیا ہے
ڈاکٹر کیرن ہِرپرا، جو Mater Private Hospital Rockhampton میں بازو اور ہاتھ کے سرجن (upper-limb surgeon) ہیں، سب سے کم چیر پھاڑ والے ان طریقوں سے شروع کرتے ہیں جو آپ کی حالت کے لیے موزوں ہوں۔ مریضوں کو عموماً ان کا فیملی ڈاکٹر (GP) ہمارے کلینک میں ریفر کرتا ہے؛ اگر کسی فزیوتھراپسٹ نے آپ کو ہم سے ملنے کا مشورہ دیا ہے، تب بھی میڈیکیئر (Medicare) کی رقم کی واپسی (rebate) کا اہل ہونے کے لیے آپ کو اپنے فیملی ڈاکٹر سے ریفرل (referral) لینا ہوگا۔ ملاقات کے دوران ہم آپ سے تفصیل پوچھتے ہیں، آپ کے ہاتھ کا معائنہ کرتے ہیں، اور اگر یہ تصدیق کرنے کے لیے ضرورت ہو کہ گانٹھ گینگلیئن ہی ہے تو ایکسرے یا اسکین کا انتظام کرتے ہیں۔
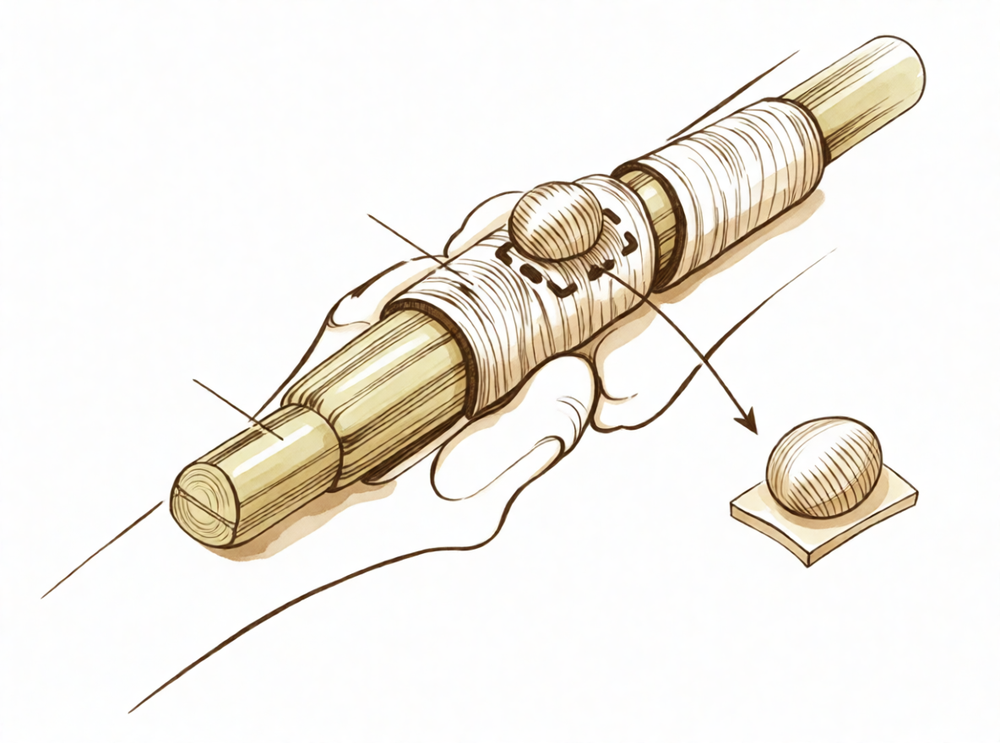
فلیکسر ٹینڈن کے غلاف کا گینگلیئن (flexor tendon sheath ganglion) ایک چھوٹی، بے ضرر گانٹھ ہے جو گاڑھے سیال سے بھری ہوتی ہے۔ یہ ٹشو کی اس سرنگ کے ساتھ ہوتی ہے جس میں سے آپ کی انگلی کے ٹینڈن (tendon)، یعنی وہ مضبوط ڈوریاں جو پٹھے کو ہڈی سے جوڑتی ہیں، پھسل کر گزرتے ہیں۔ یہ آپریشن اس گانٹھ کو آپریشن والی جگہ کے اوپر لگائے گئے ایک ہی چیرے سے نکال دیتا ہے۔
زیادہ تر گینگلیئن کا علاج پہلے سرجری کے بغیر کیا جاتا ہے۔ سوئی سے سیال نکالا جا سکتا ہے، اور آپریشن کا مشورہ دینے سے پہلے عموماً یہی آزمایا جاتا ہے۔ کچھ گینگلیئن خود بھی سکڑ جاتے ہیں، اور بچوں میں جو سسٹ ٹھیک ہوتا ہے وہ عموماً 18 ماہ کے اندر ٹھیک ہو جاتا ہے۔
جب ان آسان اقدامات کے بعد بھی گانٹھ تکلیف دیتی رہے تو سرجری کی پیشکش کی جاتی ہے۔ یہ تکلیف درد، گرفت کی کمزوری، یا ایسی گانٹھ ہو سکتی ہے جو انگلی ہلاتے وقت اٹکتی ہو۔ گینگلیئن کو نکالنے کا مقصد اس درد کو ختم کرنا اور آپ کی انگلی اور ہاتھ کو ٹھیک طرح سے کام کرنے دینا ہے۔
آپریشن سے پہلے
آپ کا سرجن ملاقات کے دوران منصوبے کی تصدیق کرے گا اور آپ کو بتائے گا کہ تیاری کے لیے کیا کرنا ہے۔ آپ سے کہا جائے گا کہ سرجری سے 7 گھنٹے پہلے کچھ نہ کھائیں اور نہ پئیں۔ ہم معمول کے 6 کے بجائے 7 گھنٹے اس لیے کہتے ہیں تاکہ اگر آپریشن کی فہرست وقت سے پہلے چلے تو آپ کو پہلے بلایا جا سکے۔ ہو سکتا ہے آپ کو آپریشن سے پہلے اپنی کچھ باقاعدہ دوائیں روکنی پڑیں۔ آپ کا سرجن آپ کو اس بارے میں واضح ہدایات دے گا، اس لیے جو کچھ بھی آپ لیتے ہیں اس کی فہرست ساتھ لائیں۔ بعد میں کسی کو اپنے ساتھ گھر لے جانے کے لیے انتظام کریں، اور آرام دہ، ڈھیلے کپڑے پہنیں۔ آپریشن کی منصوبہ بندی کے لیے ایکسرے، الٹراساؤنڈ یا ایم آر آئی اسکین استعمال کیا جا سکتا ہے۔ اگر آپ کو صحت کے دوسرے مسائل ہیں تو آپ کو خون کے ٹیسٹ یا بے ہوشی کے ڈاکٹر (anaesthetist) سے معائنے کی ضرورت پڑ سکتی ہے۔
آپریشن کے دن
آپ ہسپتال کے سرجری کے داخلے کے شعبے میں پہنچتے ہیں، جہاں آپ کا اندراج ہوتا ہے اور آپ کو آپریشن تھیٹر کے لیے تیار کیا جاتا ہے۔ وہاں آپ بے ہوشی کے ڈاکٹر سے ملیں گے۔ یہ آپریشن جنرل اینستھیزیا (مکمل بے ہوشی) میں کیا جاتا ہے۔ آپریشن کے دوران آپ پوری طرح بے ہوش ہوں گے۔ کچھ مریضوں کو آپریشن کے بعد درد میں آرام کے لیے اعصابی بلاک (nerve block)، یعنی ایک انجکشن جو جسم کے ایک حصے کو سُن کر دیتا ہے، بھی دیا جا سکتا ہے؛ بے ہوشی کے ڈاکٹر اس دن آپ کے انفرادی حالات کی بنیاد پر اس کا فیصلہ کرتے ہیں۔ پھر آپ کو آپریشن تھیٹر لے جایا جاتا ہے، جہاں آپریشن کیا جاتا ہے۔ اس کے بعد آپ ریکوری روم میں جاگتے ہیں، جہاں نرسیں بے ہوشی کا اثر ختم ہونے تک آپ کی نگرانی کرتی ہیں۔ جب آپ کی حالت مستحکم ہو جائے تو، آپریشن اور آپ کی صحت یابی کے لحاظ سے، آپ یا تو وارڈ میں جاتے ہیں یا گھر چلے جاتے ہیں۔
آپریشن میں کیا کیا جاتا ہے
یہ آپریشن گانٹھ کے اوپر لگائے گئے ایک ہی چیرے سے گینگلیئن کو نکال دیتا ہے۔ آپ کا سرجن ٹشو کی اس سرنگ کے ارد گرد احتیاط سے کام کرتا ہے جس میں سے آپ کی انگلی کے ٹینڈن پھسل کر گزرتے ہیں، اور گینگلیئن کو اس چھوٹی ڈنڈی سمیت نکال دیتا ہے جو اسے اس سرنگ سے جوڑتی ہے۔ پوری گانٹھ کو اس کی جڑ سمیت نکالنے سے اس کے دوبارہ ہونے کا امکان کم ہوتا ہے۔
چیرے کو ٹانکوں سے بند کیا جاتا ہے۔ آپریشن تھیٹر سے نکلنے سے پہلے زخم پر پٹی لگا دی جاتی ہے۔
آپ کا سرجن آپریشن کے دوران ارد گرد کے ٹشو کا بھی جائزہ لے گا۔ اگر گینگلیئن کے دباؤ سے ٹینڈن کا کوئی حصہ کمزور ہو گیا ہو، تو اس ٹینڈن کو محفوظ رکھا جاتا ہے اور اسے نقصان نہیں پہنچایا جاتا۔
آپریشن کے بعد
یہ عموماً ایک ہی دن کا آپریشن ہوتا ہے، اس لیے آپ اسی دن گھر جانے کی توقع رکھ سکتے ہیں، اگرچہ کبھی کبھار مریض رات بھر رکتے ہیں۔ آپ ریکوری روم میں جاگتے ہیں، جہاں نرسیں بے ہوشی کا اثر ختم ہونے تک آپ پر نظر رکھتی ہیں۔ آپ کے ہاتھ پر زخم کے اوپر نرم پٹی ہوگی، اور ہم آپ کو آرام دہ رکھنے کے لیے درد کش دوا دیں گے۔ جیسے ہی آپ کو اپنے قدموں پر ٹھہراؤ محسوس ہو، آپ چل پھر سکتے ہیں۔ گھر پہنچنے کے بعد پہلے 24 گھنٹے کسی کو آپ کے ساتھ رہنا چاہیے۔ ہم پٹی تقریباً 10 دن تک لگی رہنے دیتے ہیں؛ براہِ کرم اس سے پہلے اسے نہ اتاریں جب تک ہم نہ کہیں۔ جب ہم آپ کو دیکھیں گے تو ہم اسے بدلیں گے یا اتار دیں گے۔
صحت یابی
پہلے چند دنوں میں آپ کے ہاتھ میں درد اور تھوڑی سوجن ہوگی۔ یہ آہستہ آہستہ کم ہو جاتی ہے۔ ہاتھ کو تکیے پر اونچا رکھنے سے، بیٹھے یا سوتے ہوئے بھی، سوجن اور تکلیف کم کرنے میں مدد ملتی ہے۔ ہم جو درد کش دوا دیں گے وہ آپ کو اس وقت تک آرام دہ رکھے گی جب تک سب سے مشکل وقت گزر نہ جائے۔
آپ زخم پر نرم پٹی کے ساتھ گھر جاتے ہیں۔ ہم اسے تقریباً 10 دن تک لگی رہنے دیتے ہیں اور جب آپ کو دیکھیں گے تو اسے بدلیں گے یا اتار دیں گے۔ آپ کی انگلی اور ہاتھ پٹی کے اندر آرام کی حد تک آہستہ سے حرکت کر سکتے ہیں۔ آپ کو پلستر یا بریس کی ضرورت نہیں ہوگی۔
سرجری کے بعد ہینڈ تھراپی (ہاتھ کی بحالی کا علاج) Extend Rehabilitation میں Ruby Doolan کے ساتھ ہوتی ہے۔ روبی ایک ہینڈ تھراپسٹ (ہاتھ کی بحالی کی ماہر) ہیں، اس لیے وہ آپ کی ورزشوں کی رہنمائی کریں گی اور جس اسپلنٹ کی بھی ضرورت ہو اسے بنائیں گی۔ یہ ورزشیں زخم کے بھرنے کے دوران آپ کی انگلی کو حرکت میں رکھتی ہیں اور اسے اکڑنے سے روکتی ہیں۔ آپ یہ گھر پر، تھوڑی تھوڑی اور بار بار کرتے ہیں۔
روزمرہ کے کام مرحلہ وار واپس آتے ہیں۔ جب زخم آرام دہ ہو جائے اور آپ ہاتھ کو بچائے بغیر اسٹیئرنگ وہیل کو پکڑ اور گھما سکیں، تو عموماً آپ دوبارہ گاڑی چلا سکتے ہیں۔ آپ اس بارے میں مزید ہمارے صفحے بازو اور ہاتھ کی سرجری کے بعد گاڑی چلانا پر پڑھ سکتے ہیں۔ کام پر واپسی اس پر منحصر ہے کہ آپ کے کام میں کیا شامل ہے، اور آپ کا تھراپسٹ آپ کو بتائے گا کہ آپ کا ہاتھ کب تیار ہے۔
صحت یابی ہر شخص میں مختلف ہوتی ہے۔ آپ کا وقت مختلف ہو سکتا ہے، اور آپ کا سرجن اور ہینڈ تھراپسٹ پورے راستے آپ کی رہنمائی کریں گے۔
کیا مسائل پیدا ہو سکتے ہیں
زیادہ تر مریض ٹھیک رہتے ہیں، لیکن کبھی کبھار مسائل پیدا ہو سکتے ہیں۔ آپ کا سرجن اور ٹیم کسی بھی مسئلے کو جلد پکڑنے کے لیے آپ کی کڑی نگرانی کرتے ہیں۔
بعض اوقات گانٹھ اسی جگہ دوبارہ بن جاتی ہے۔ آپ کو پرانے نشان کے قریب ایک چھوٹی، سخت سوجن محسوس یا نظر آئے گی۔ اگر آپ یہ دیکھیں تو اگلے معائنے پر اس کا ذکر کریں۔
آپریشن والی جگہ کے قریب سے اعصاب گزرتے ہیں۔ سرجری کے دوران کسی عصب کو چوٹ لگ سکتی ہے یا اس میں جلن (irritation) پیدا ہو سکتی ہے۔ یہ جھنجھناہٹ، سوئیاں چبھنے جیسے احساس، یا چیرے کے قریب جلد کے کسی سُن حصے کی طرح محسوس ہو سکتا ہے۔ اس میں سے زیادہ تر ٹھیک ہو جاتا ہے، لیکن بعض اوقات جہاں عصب متاثر ہوا ہو وہاں چھونے پر دردناک ایک چھوٹی سی جگہ یا گٹھلی بن جاتی ہے۔ اگر آپ کا سُن پن یا جھنجھناہٹ ٹھیک نہیں ہو رہی تو معائنے پر اپنے سرجن کو بتائیں۔
انگلی کے کنارے کے ساتھ ساتھ چلنے والے چھوٹے اعصاب اور خون کی نالیاں قریب ہی ہوتی ہیں۔ انہیں چوٹ لگنا غیر معمولی ہے، لیکن آپریشن کے دوران آپ کا سرجن اس کا خیال رکھتا ہے۔
زخم میں انفیکشن ہو سکتا ہے۔ چیرے سے باہر کی طرف پھیلتی سرخی، بڑھتے ہوئے درد، گرمی، یا زخم سے رطوبت کے اخراج پر نظر رکھیں۔ آپ کو بخار جیسا محسوس ہو سکتا ہے۔ اگر آپ ان میں سے کوئی بھی علامت دیکھیں تو فوراً کلینک کو فون کریں، یا اگر دفتری اوقات ختم ہو چکے ہوں تو ہسپتال کی ایمرجنسی جائیں۔
سرجری کے بعد زخم کے نیچے خون جمع ہو سکتا ہے۔ یہ ایک سخت، چھونے پر دردناک سوجن کی طرح نظر آتا ہے جو پہلے ایک دو دن میں ظاہر ہوتی ہے۔ اگر یہ بڑی یا دردناک ہو تو اسے آپریشن تھیٹر میں نکالنے کی ضرورت پڑ سکتی ہے۔ اگر آپ یہ دیکھیں تو کلینک کو فون کریں۔
بھرتے ہوئے زخم کا نشان ابھرا ہوا، موٹا اور سرخ ہو سکتا ہے۔ اسے ہائپرٹرافک نشان (hypertrophic scar) کہتے ہیں۔ یہ سخت اور کبھی کبھی خارش والا محسوس ہو سکتا ہے۔ اپنے معائنے پر اس کا ذکر کریں، کیونکہ علاج مدد کر سکتا ہے۔
زخم کے قریب ٹینڈن کے غلاف میں سوزش ہو سکتی ہے۔ یہ انگلی ہلاتے وقت چرچراہٹ یا کلک کی طرح محسوس ہوتی ہے، اور ٹینڈن کے ساتھ ساتھ چھونے پر درد ہوتا ہے۔ اگلے معائنے پر اس کا ذکر کریں۔
آپ کی انگلی یا کلائی بھی کچھ عرصے کے لیے اکڑی ہوئی محسوس ہو سکتی ہے۔ ہلکی حرکت اور ہینڈ تھراپی کی ورزشیں اس سے بچانے میں مدد کرتی ہیں۔ اگر اکڑاؤ بہتر نہ ہو تو اپنے تھراپسٹ یا سرجن کو بتائیں۔
اگر آپ تفصیل جاننا چاہیں تو اس صفحے پر پیچیدگیوں کی جدول میں عام شرحیں درج ہیں۔
ہمیں کب فون کریں
زیادہ تر مسائل معائنے پر پکڑے جاتے ہیں، لیکن کچھ پر جلد توجہ کی ضرورت ہوتی ہے۔ اگر آپ کو بخار ہو، چیرے کے ارد گرد سرخی پھیل رہی ہو، یا زخم سے رطوبت کا اخراج ہو تو ہمیں فون کریں۔ اگر درد اچانک بڑھ جائے، یا پہلے ایک دو دن میں چیرے کے قریب سخت، چھونے پر دردناک سوجن ظاہر ہو تو ہمیں فون کریں۔ اگر آپ کی پنڈلی میں سوجن یا درد ہو، یا سانس پھولنے لگے تو ہسپتال کی ایمرجنسی جائیں۔ یہ خون کے لوتھڑے کی علامات ہو سکتی ہیں۔ اگر آپ کی انگلیاں سُن، ٹھنڈی یا سفید پڑ جائیں، یا آپ اپنی انگلی یا ہاتھ کو اس وقت حرکت نہ دے سکیں جب آپ کو اس کی توقع ہو، تو بھی ہمیں فون کریں۔ اگر دفتری اوقات ختم ہو چکے ہوں تو ہسپتال کی ایمرجنسی جائیں۔
اس مسئلے کے بارے میں مزید کہاں پڑھیں
یہ صفحہ خود آپریشن کے بارے میں ہے۔ جس مسئلے کا یہ علاج کرتا ہے، اس کی تفصیل، بشمول اس کے کہ شواہد کیا بتاتے ہیں کہ سرجری کب مدد کرتی ہے اور کب نہیں، فلیکسر ٹینڈن کے غلاف کا گینگلیئن والے صفحے پر دی گئی ہے۔
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Anatomy & Pathophysiology
General Hand Architecture
- The hand is composed of 19 bones, 17 articulations, and 19 muscles situated entirely within the hand [2].
- The hand contains approximately the same number of tendons activated by forearm muscles as it has intrinsic muscles [2].
- The open hand with fingers extended and in contact forms a balanced graceful oval in its longitudinal axis [2].
- The proximal carpometacarpal half of the hand is flattened and presents two faces with unique anatomical and functional significance [2].
- The posterior or dorsal aspect of the hand is convex, while the anterior, palmar, or volar aspect is concave [2].
- The distal half of the hand is separated into five digits that flex toward the palm [2].
- The thumb has a more proximal and lateral position than the four fingers, allowing movement inward and outward from the palm [2].
- The hinges for finger flexion and extension are located at the thenar crease and the transverse distal palmar crease, not at the bases of the digits [2].
- When fingers are extended and separated, their tips lie on the circumference of a circle whose center is the head of the third metacarpal [2].
Cutaneous Units
- The dorsum of the hand contains a cutaneous unit extending from the wrist to the proximal interphalangeal joints of the fingers and the interphalangeal joint of the thumb [3].
- The dorsal covering of the interphalangeal articulations forms a unique cutaneous unit characterized by considerable excess of skin when digits are in extension [3].
- The fine tight skin of the dorsal aspect of the middle phalanx forms a distinct cutaneous unit [3].
- The dorsal integument of the distal phalanx is distinct due to the presence of the nail bed and its matrix [3].
- The palm forms a cutaneous unit extending from the distal transverse crease of the wrist up to the transverse crease at the base of the digits [3].
- The palmar integument is subdivided into two zones by the oppositional crease of the thumb, which constitutes the oblique axis of the hand [3].
- The skin of the radial portion of the palm covers the thenar eminence and external part of the palm and is relatively well vascularized and mobile [3].
- The skin of the ulnar and distal portion covers the hypothenar eminence, where skin mobility is poor [3].
- The central triangular part of the palm has fixed, poorly vascularized skin that covers almost directly the superficial palmar aponeurosis [3].
- The integument of the palmar face of the digits is subdivided into phalangeal units separated by digital flexion folds [3].
- When a digit is completely flexed, the integument of adjacent phalanges comes into contact in the zones of the flexion creases, establishing areas of cutaneous contact in the form of a diamond [3].
- The sides of the diamond-shaped cutaneous contact zones do not undergo variations in length during flexion and extension movements [3].
- Incisions made along the lines of the diamond-shaped cutaneous contact zones present a minimal chance of retraction [3].
- The web spaces are formed from the union of two nonsymmetrical cutaneous surfaces [3].
- The dorsal slope of the web space has a gradual incline and supple skin that is not adherent to the subjacent region [3].
- The palmar surface of the web space is flat, precipitously interrupted, and densely adherent to the commissural skeleton [3].
- The commissural skeleton is formed by the interdigital palmar (natatory) ligament between fingers and by the distal transverse ligament at the level of the thumb web [3].
Intrinsic Muscles
- There are seven interosseous muscles in the hand, consisting of four dorsal and three volar muscles [4].
- The dorsal interossei are abductors [4].
- The volar interossei are adductors [4].
- The middle finger has two dorsal interossei and no volar interossei because the central axis of the hand lies within it [4].
- Each dorsal interosseous muscle, with the exception of the third, has two muscle heads [4].
- The superficial head of the dorsal interosseous muscles arises most dorsally from the shaft of contiguous metacarpals and inserts deeply by a medial tendon onto the lateral tubercle of the base of the proximal phalanx [4].
- The superficial head of the dorsal interosseous muscles abducts and weakly flexes the proximal phalanx [4].
- The deep head of each dorsal interosseous muscle forms a lateral tendon, or lateral band, at the level of the metacarpophalangeal joint [4].
- The deep head of the dorsal interosseous muscles flexes and weakly abducts the proximal phalanx while extending the middle and distal phalanges [4].
- At the level of the middle of the proximal phalanx, transverse fibers arch dorsally from each lateral band to join each other over the dorsum of the finger, flexing the proximal phalanx [4].
- Oblique fibers, or spiral fibers, from the lateral bands sweep over the distal third of the proximal phalanx to insert onto the lateral tubercles at the base of the middle phalanx [4].
- The oblique fibers extend the middle phalanx at the proximal interphalangeal joint [4].
- The lateral bands are joined by the lateral slips of the extensor tendon to form the conjoined lateral band [4].
- The two conjoined lateral bands to each finger unite at the distal third of the middle phalanx to form the terminal tendon [4].
- The terminal tendon inserts at the base of the distal phalanx to extend it [4].
- The flexor digiti quinti brevis is structurally and functionally similar to the deep head of the dorsal interossei, forming the ulnar lateral band of the little finger [4].
- Each volar interosseous muscle has only one muscle head and none insert onto the proximal phalanx [4].
- The volar interossei form the ulnar lateral band of the index finger and the radial lateral band of the ring and little fingers [4].
- The abductor digiti quinti and flexor digiti quinti brevis are similar in structure and function to the superficial and deep heads of the dorsal interossei, respectively [4].
- The abductor digiti quinti arises from the fifth metacarpal and inserts onto the ulnar lateral tubercle at the base of the proximal phalanx of the little finger [4].
- The opponens digiti quinti lies deepest among the hypothenar muscles, arising from the pisohamate ligament and hook of the hamate [4].
- The opponens digiti quinti inserts onto the ulnar side of the diaphysis of the fifth metacarpal, which it flexes and supinates [4].
Arches and Stability
- The metacarpal arch is endowed with a great deal of adaptability because of the mobility of the peripheral metacarpals [7].
- The peripheral metacarpals form the sides of the cup or palmar gutter and can deepen the concavity as they approach each other [7].
- The thumb metacarpal is independent and articulates with the trapezium [7].
- The middle metacarpals are united to the carpus by the intrinsic interlocking encasement of the bones themselves [7].
- The index metacarpal is the most firmly fixed [7].
- The ring metacarpal is a transitional element to the fifth metacarpal and has about 10 degrees of mobility in flexion and extension [7].
- The fifth metacarpal is semi-independent, articulates with the hamate, and is restrained on its radial side by its articulation with the base of the fourth metacarpal [7].
- The fifth metacarpal has a range of flexion–extension of approximately 20 degrees [7].
- The second to fifth metacarpals are bound together by various fibrous structures, the most distal of which is the deep transverse intermetacarpal ligament [7].
- The deep transverse intermetacarpal ligament is better named the interglenoid ligament because it ties together the anterior glenoid ligaments of the metacarpophalangeal articulations, known as the volar plates [7].
- The longitudinal arches are composed of a fixed portion, the carpometacarpal, and a mobile portion, the digits [7].
- The keystones of the longitudinal arches are the metacarpophalangeal articulations [7].
- The thick anterior glenoid capsules, or volar plates, of the metacarpophalangeal joints prevent hyperextension [7].
- The volar plates are interconnected by the transverse interglenoid ligament [7].
- The stability of the metacarpophalangeal joints is essential to the support of the longitudinal arch as well as of the transverse metacarpal arch [7].
Vascular Anatomy
- The arteries of the thumb vary in both size and number, making surgical reconstruction delicate [8].
- The palmar arteries of the thumb can be schematized by dividing the thumb into three segments defined by the metacarpophalangeal and interphalangeal flexion creases [8].
- In the classical layout, the princeps pollicis artery, a terminal branch of the radial artery, crosses the first intermetacarpal space and runs along the ulnar side of the first metacarpal bone [8].
- The princeps pollicis artery runs along the volar surface of the adductor muscle and emerges onto the subcutaneous palmar tissue at the level of the cutaneous flexion crease of the metacarpophalangeal joint [8].
- At the metacarpophalangeal joint level, the princeps pollicis artery divides into two terminal rami, the collateral palmar arteries of the thumb [8].
- The collateral palmar arteries run along the digital tunnel symmetrically and are of equal caliber, heading distally to unite in the pulp arcade [8].
- During transit in the digital tunnel, the collateral palmar arteries break off into numerous collateral branches that are cutaneous, articular, or osseous [8].
- An arcade located deep in the flexor tendon joins the two arteries at the level of the distal metaphysis of the first phalanx [8].
- Vessels originating from the subtendinous arcade enter the vincula and irrigate the flexor tendon [8].
- Only 15% of anatomical dissections of the palmar arteries of the thumb fall into the classical "typical" category [8].
- In the first segment of the thumb (between opposition crease and metacarpophalangeal flexion crease), arteries of surgical interest are rarely found on the volar surface [8].
- In the second segment, the two arteries run alongside the flexor tendon and behind the collateral nerves [8].
- In the second segment, the main artery is the ulnar collateral artery, which is more often easier to dissect than the radial collateral artery [8].
- In the second segment, a subtendinous anastomosis situated at the level of the neck of the first phalanx acts as a moderator between the two arteries [8].
- In the third segment (pulp segment), the two arteries are of similar size and run through thick fatty subcutaneous padding [8].
- In the pulp segment, the arteries cross over and convert into the ends of the digital nerves at the level of the median axis [8].
- The posterior area of the thumb is vascularized by two arteries that originate from palmar arteries at the level of the first metacarpal [8].
- These dorsal arteries run laterally along the metacarpophalangeal joint and continue obliquely from volar to dorsal, heading distally on the side of the two distal phalanges [8].
- At the level of the neck of the first phalanx, an anastomosis originating from palmar arteries can be found for the dorsal supply [8].
- The dorsal arteries are joined by three arcades: one inconstant arcade under the extensor tendon at the neck of the first phalanx, the arcade of the nail matrix, and the arcade of the nailbed [8].
Surgical Anatomy and Incisions
- Distal palmar incisions are transverse, while proximal palmar incisions tend to be more longitudinal with the distal end curving radially to parallel the closest major skin crease [9].
- An incision of any desired length can be made across the palm provided that underlying digital nerves and other vital structures are protected [9].
- After skin and underlying fat are incised, the fat is dissected from the palmar fascia and carried with the skin flaps [9].
- Most vital structures in the palm are deep to the palmar fascia [9].
- In the distal palm, structures lying between the metacarpal heads are not protected by the palmar fascia [9].
- The superficial volar neurovascular arch should be protected when deeper exposure is required [9].
- Incisions in the more proximal palm should parallel the thenar crease [9].
- Incisions extended proximal to the wrist should not cross the flexor wrist creases at a right angle [9].
- The most important structure in the thenar area is the recurrent branch (motor) of the median nerve, which should be exposed and protected if its exact location is in doubt [9].
- Care should be taken to avoid injury to the palmar cutaneous branches of the median and ulnar nerves [9].
- There is no single longitudinal incision in the proximal palm that completely avoids the palmar cutaneous branches of the median and ulnar nerves [9].
- The volar zigzag finger incision does not require mobilizing either neurovascular bundle and directly exposes the volar surface of the flexor tendon sheath [9].
- The volar midoblique incision crosses the flexion creases obliquely in the midline of the finger between the neurovascular bundles [9].
- Midlateral incisions described for fingers are suitable for the thumb, with the radial side being more accessible [9].
- A radial midlateral thumb incision can be extended by curving its proximal end at the midmetacarpal area to create a flap on the palmar surface of the thumb [9].
- Care should be taken to avoid the dorsal branch of the superficial radial nerve to the radial side of the thumb during radial midlateral incisions [9].
Investigations
- Clinical evaluation of the hand and wrist requires combining patient history with a careful physical examination to pinpoint or narrow the scope of possible pathologic processes [1].
- Diagnostic tests such as imaging and serum laboratory studies are useful in determining pathology but can be expensive, time consuming, and often nonspecific [1].
- A careful physical examination is essential to direct care and future testing if indicated [1].
- An 8-MHz Doppler tone assessment may be used to identify superficially displaced neurovascular bundles when Dupuytren cords lie beneath soft fleshy prominences [11].
- False-negatives are possible with 8-MHz Doppler tone assessment for identifying neurovascular bundles [11].
- MRI is probably most useful in identifying additional pathology such as flexor tendon bowstringing [11].
- MRI may be helpful in providing a quantitative noninvasive measure of cellularity of affected areas, which is an index of biologic activity [11].
- The potential of MRI as a staging tool based on cellularity measurement has not been investigated yet on a large scale [11].
References
[1] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[2] Exam Of The Hand Wrist 2Ed. INTRODUCTION.
[3] Exam Of The Hand Wrist 2Ed. Functional cutaneous units.
[4] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[7] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[8] Exam Of The Hand Wrist 2Ed. Techniques of investigation of the arterial supply by J P Melki > Vascularization of the thumb > Palmar aspect.
[9] Campbell S Operative Orthopaedics 4 Volume Set. RESULTS OF SUTURE OF THE SCIATIC NERVE > PALMAR INCISIONS.
[11] Dupuytren S Disease And Related Hyperproliferative Disorders. 54. The Future of Dupuytren’s Research and Treatment > 54.4 Mechanical Measurements and Procedures > 54.4.4 Imaging.