Patients › General-Health
آٹولوگس ٹینوسائٹ امپلانٹیشن (ATI)
Cultured tendon-cell injection (OrthoATI) for chronic tendinopathy — how it is made and given, what the published evidence does and does not show, and its regulatory standing in Australia.
یہ کیا ہے
آٹولوگس ٹینوسائٹ امپلانٹیشن (autologous tenocyte implantation) — جسے عموماً مختصر کر کے اے ٹی آئی (ATI) کہا جاتا ہے، اور جو آسٹریلیا میں OrthoATI کے برانڈ نام سے فروخت ہوتی ہے — آپ کے اپنے ٹینڈن (tendon، یعنی وہ مضبوط ڈوری جو پٹھے کو ہڈی سے جوڑتی ہے) کے خلیوں کا ایک انجکشن ہے، جو کسی ایسے ٹینڈن میں لگایا جاتا ہے جو ٹھیک نہیں ہوا۔
"آٹولوگس" کا مطلب ہے کہ خلیے آپ کے اپنے جسم سے لیے جاتے ہیں۔ "ٹینوسائٹس" (tenocytes) وہ خلیے ہیں جو ٹینڈن کے اندر رہتے ہیں اور وہ کولیجن (collagen) بناتے ہیں جو اسے مضبوطی دیتا ہے۔ اس علاج کے پیچھے یہ خیال ہے کہ ٹینڈن کا پرانا مسئلہ دراصل سوزش نہیں ہوتا — یہ ٹینڈن کا ایک ایسا حصہ ہوتا ہے جہاں مرمت کا عمل رک گیا ہو اور جن خلیوں کو اسے دوبارہ بنانا چاہیے تھا وہ مر چکے ہوں۔ اے ٹی آئی کا مقصد اس حصے کو آپ کے جسم کی کسی دوسری جگہ سے لیے گئے صحت مند ٹینڈن کے خلیوں سے دوبارہ بھرنا ہے۔
اس کے لیے دو بار آنا پڑتا ہے، جن کے درمیان کئی ہفتوں کا وقفہ ہوتا ہے۔
- پہلے، بایوپسی (biopsy، نمونہ لینا)۔ لوکل اینستھیزیا (صرف اس حصے کو سُن کرنا) کے تحت، ایک سوئی سے ٹینڈن کا بہت چھوٹا سا نمونہ لیا جاتا ہے، عموماً گھٹنے کی چپنی کے بالکل نیچے والے ٹینڈن (patellar tendon) سے۔ آپ کا خون کا ٹیسٹ بھی ہوگا، کیونکہ لیبارٹری کے لیے لازمی ہے کہ آپ کے خلیے اگانے سے پہلے ہیپاٹائٹس اور ایچ آئی وی (HIV) کی جانچ کرے۔
- پھر لیبارٹری خلیے اگاتی ہے۔ آپ کا نمونہ خلیے اگانے کی ایک لائسنس یافتہ لیبارٹری (cell-culture facility) میں جاتا ہے، جہاں ٹینڈن کے خلیوں کو الگ کیا جاتا ہے اور تقریباً تین سے پانچ ہفتوں میں ان کی تعداد بڑھائی جاتی ہے، یہاں تک کہ وہ کئی ملین ہو جائیں۔
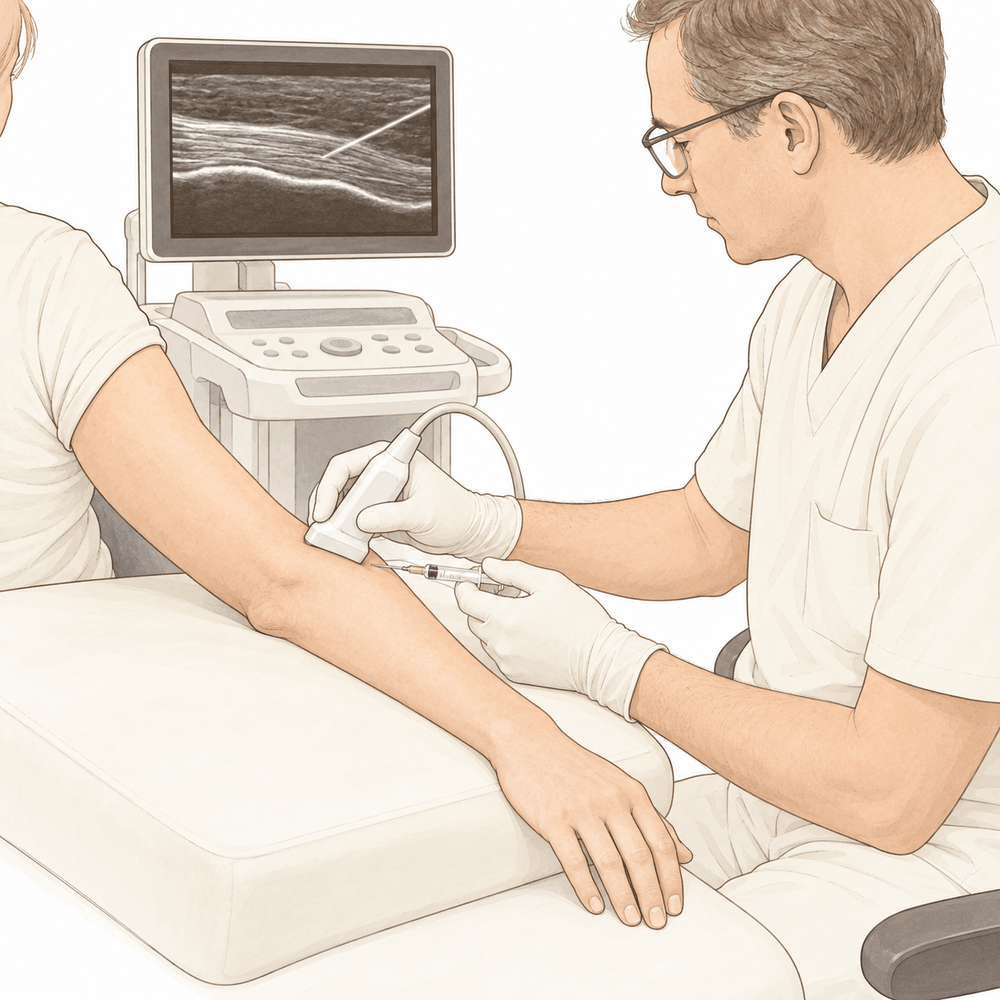
- پھر انجکشن۔ آپ کے اپنے خلیے تھوڑی سی مقدار کے مائع کی شکل میں واپس آتے ہیں، اور ایک ڈاکٹر الٹراساؤنڈ کی مدد سے سوئی کی سمت طے کرتے ہوئے انہیں براہِ راست ٹینڈن کے خراب حصے میں انجکشن کرتا ہے۔ یہ لوکل اینستھیزیا کے تحت کیا جاتا ہے۔ اس میں نہ کوئی آپریشن ہوتا ہے اور نہ کوئی چیرا۔
اس کے بعد، شائع شدہ تحقیقات میں لوگوں سے کہا گیا کہ وہ دو دن آرام کریں، چار ہفتوں تک صرف ہلکا گھریلو یا دفتری کام کریں، اور دن میں چار بار سادہ اسٹریچ کریں۔ ان میں فزیوتھراپی کے ذریعے طاقت بڑھانے کا کوئی باقاعدہ پروگرام استعمال نہیں کیا گیا، اور کام اور کھیل پر پابندیاں چار ہفتوں بعد ختم کر دی گئیں۔
یہ علاج ٹینس ایلبو (کہنی کے باہر کی طرف درد)، روٹیٹر کف (rotator cuff، یعنی ٹینڈنوں کا وہ گروپ جو کندھے کو تھامتا اور گھماتا ہے) کے ٹینڈن کے مسائل، کولہے کے گلوٹیل (gluteal) ٹینڈن کے مسائل اور ایڑی کے ٹینڈن (Achilles tendon) کے مسائل کے لیے استعمال ہوا ہے۔ تقریباً تمام شائع شدہ تحقیق ٹینس ایلبو پر ہے۔
کیا یہ مؤثر ہے؟
یہ وہ حصہ ہے جو مختصر جواب کے بجائے محتاط جواب کا حق دار ہے، کیونکہ اے ٹی آئی کے بارے میں جو دعوے کیے جاتے ہیں اور جو حقیقت میں ثابت ہوا ہے، وہ ایک ہی چیز نہیں ہیں۔
جو کچھ شائع ہوا ہے وہ واقعی حوصلہ افزا ہے، لیکن وہ کم مریضوں پر مبنی ہے اور اس میں موازنے کا کوئی گروپ نہیں تھا۔ سن 2025 میں شائع ہونے والے ایک آزاد جائزے میں دنیا بھر کی طبی تحقیق کو کھنگالا گیا اور کل 50 مریضوں پر مشتمل پانچ تحقیقات ملیں — تین چھوٹی کیس سیریز (case series) اور ایک ایک مریض کی دو رپورٹیں، سب کی سب آسٹریلیا میں کی گئیں۔ ٹینس ایلبو کی مرکزی تحقیق میں 16 ایسے لوگ شامل تھے جنہیں شدید اور پرانا ٹینس ایلبو تھا اور جن پر باقی ہر علاج پہلے ناکام ہو چکا تھا؛ 12 ماہ میں ان کے سب سے شدید درد میں 86 فیصد اور بازو کے کام کے اسکور میں 91 فیصد بہتری آئی، اور ایم آر آئی پر ٹینڈن کی شکل بھی بہتر ہوئی۔ جب اسی گروپ کا اوسطاً 4.5 سال بعد دوبارہ معائنہ کیا گیا، تو یہ فوائد برقرار تھے۔
لیکن ان میں سے کسی تحقیق میں موازنے کا گروپ نہیں تھا۔ کسی کو نقلی انجکشن نہیں دیا گیا، اور موازنے کے لیے کسی کو بغیر علاج کے نہیں چھوڑا گیا۔ یہ بات جتنی لگتی ہے اس سے زیادہ اہم ہے، اور اس کی دو وجوہات ہیں۔ ٹینڈن کا درد علاج کی توقع سے بہت زیادہ متاثر ہوتا ہے — ٹینس ایلبو میں، ایک ٹرائل نے اصل سرجری کا موازنہ نقلی سرجری سے کیا، جس میں نہ مریض کو معلوم تھا اور نہ جانچنے والے کو کہ کس کی کون سی سرجری ہوئی، اور اصل آپریشن کا کوئی فائدہ نہیں ملا۔ اور ٹینس ایلبو خود بخود بھی ٹھیک ہو جاتا ہے: رینڈمائزڈ ٹرائلز (randomised trials) کے بغیر علاج والے اور پلیسبو (نقلی علاج) والے گروپوں کو ملا کر دیکھا جائے تو تقریباً 90 فیصد لوگ ایک سال کے اندر بہتر ہو جاتے ہیں [12]۔
اے ٹی آئی کے حق میں جس ٹرائل کا سب سے زیادہ حوالہ دیا جاتا ہے، وہ کبھی شائع نہیں ہوا۔ نومبر 2023 میں OrthoATI بنانے والی کمپنی نے اسٹاک ایکسچینج کو 48 افراد پر مشتمل ایک ٹرائل کے نتائج کا اعلان کیا، جس میں شدید ٹینس ایلبو کے لیے اے ٹی آئی کا موازنہ سرجری سے کیا گیا تھا، اور بتایا کہ انجکشن کا نتیجہ آپریشن سے بہتر رہا اور لوگ تقریباً ایک ماہ پہلے کام پر واپس آ گئے۔ تقریباً تین سال بعد بھی یہ ٹرائل کسی طبی جریدے میں شائع نہیں ہوا، اس لیے کوئی آزاد ڈاکٹر یہ جانچ نہیں سکا کہ یہ کیسے کیا گیا۔ اس میں شامل ہر شخص جانتا تھا کہ اسے کون سا علاج مل رہا ہے، بنیادی پیمائش ایک سوالنامہ تھا جو مریضوں نے خود بھرا، اور ٹرائل اسی کمپنی نے چلایا جو یہ پروڈکٹ فروخت کرتی ہے۔ ان میں سے کسی بات کا مطلب یہ نہیں کہ نتیجہ غلط ہے۔ اس کا مطلب یہ ہے کہ اسے ابھی تک ان لوگوں نے نہیں پرکھا جن کا کام اسے پرکھنا ہے۔
ایک ٹرائل ایسا تھا جو اس سوال کا فیصلہ کر سکتا تھا، اور وہ خاموش ہو گیا ہے۔ نیدرلینڈز کے ایک ہسپتال نے اے ٹی آئی کی واحد صحیح معنوں میں بلائنڈ (blinded) تحقیق کی جو کبھی رجسٹر ہوئی: ایڑی کے ٹینڈن کے درد والے 90 لوگ، جن میں سے آدھوں کو ٹینڈن کے خلیے دیے گئے اور آدھوں کو نمکین پانی کا انجکشن، اور نہ مریضوں کو معلوم تھا نہ ان کا معائنہ کرنے والے ڈاکٹروں کو کہ کس کو کیا ملا۔ یہ 2014 میں مکمل ہوا۔ اس کے بعد کے بارہ سالوں میں اس کے نتائج کہیں بھی شائع نہیں ہوئے۔
اس لیے سچا خلاصہ یہ ہے: محفوظ، منطقی طور پر معقول، موازنے کے بغیر کی گئی تحقیقات میں مسلسل مثبت، اور ابھی تک غیر ثابت شدہ۔ 2025 کے جائزے کا اپنا نتیجہ یہ تھا کہ ضدی ٹینڈن مسائل کے لیے اے ٹی آئی دوسرے درجے کا ایک معقول آپشن ہو سکتا ہے، لیکن اس سے پہلے کہ کوئی کہہ سکے کہ یہ کام کرتا ہے، موازنے کا گروپ ضروری ہے۔
اس کے خطرات کیا ہیں؟
حفاظت کا ریکارڈ شواہد کا سب سے مضبوط حصہ ہے، اور جہاں تک یہ جاتا ہے، تسلی بخش ہے۔
- جس کہنی یا ٹینڈن کا علاج کیا جا رہا ہو، وہاں شائع شدہ سیریز میں نہ کوئی انفیکشن رپورٹ ہوا، نہ ٹینڈن کا پھٹنا، نہ ٹینڈن میں خون بہنا، نہ عصب کی چوٹ اور نہ ہڈی کا غیر ضروری بننا۔
- گھٹنے میں، جہاں سے بایوپسی لی جاتی ہے، تکلیف ہلکی اور تھوڑی دیر کی رہی ہے۔ ٹینس ایلبو کی مرکزی تحقیق میں، بایوپسی کے چار گھنٹے بعد گھٹنے کا اوسط درد 10 میں سے 2 سے کم تھا اور چار ہفتوں تک ختم ہو چکا تھا، اور کوئی دیرپا مسئلہ نہیں ہوا۔ کولہے کی تحقیق میں، 12 میں سے 3 لوگوں کو بایوپسی کی جگہ پر ہلکا درد ہوا جو سوزش کم کرنے والے جیل سے ٹھیک ہو گیا۔
- سب سے عام مایوسی کوئی پیچیدگی نہیں بلکہ علاج کا اثر نہ ہونا ہے۔ ٹینس ایلبو کی مرکزی تحقیق میں ایک شخص، کام پر وزن اٹھاتے ہوئے کہنی کو دوبارہ چوٹ لگنے کے بعد، تین ماہ پر بھی بہتر نہیں تھا، اور بعد میں اس کی سرجری ہوئی۔
دو دیانت دارانہ وضاحتیں۔ پہلی، پوری شائع شدہ تحقیق میں صرف 50 مریض ہیں، اس لیے کوئی کم ہونے والی پیچیدگی ابھی سامنے نہیں آئی ہوگی — 50 لوگوں میں بے داغ ریکارڈ ایسے مسئلے کو خارج نہیں کر سکتا جو ہر 100 میں سے 1 کو ہوتا ہو۔ دوسری، پانچ شائع شدہ تحقیقات میں سے دو نے مضر اثرات کو باقاعدہ طور پر دیکھا ہی نہیں، اس لیے "کوئی رپورٹ نہیں ہوا" بالکل وہی بات نہیں جو "کوئی نہیں ہوا"۔
ایک خطرہ ایسا بھی ہے جو طبی نہیں۔ یہ ایک غیر منظور شدہ پروڈکٹ ہے، علاج کی ادائیگی نجی طور پر کی جاتی ہے، اور بایوپسی آپ کو اس عمل کا پابند کر دیتی ہے، اس سے پہلے کہ کسی کو معلوم ہو کہ آپ کے خلیے اچھی طرح اگیں گے یا انجکشن آپ کی مدد کرے گا۔
کیا یہ آپ کے لیے مناسب ہے؟
اے ٹی آئی پہلا قدم نہیں ہے، اور کوئی سمجھ دار شخص اسے پہلے قدم کے طور پر پیش نہیں کرتا۔ اس پر تحقیق صرف ان لوگوں میں ہوئی ہے جن کا ٹینڈن کا مسئلہ کم از کم چھ ماہ سے چل رہا تھا اور جو پہلے ہی عام علاج بغیر کامیابی کے کروا چکے تھے۔ ٹینس ایلبو کی تحقیقات میں اس کا مطلب تھا بریس، فزیوتھراپی اور کم از کم ایک کورٹیسون کا انجکشن۔
یہ سمجھنا مفید ہے کہ آسٹریلیا میں قانونی طور پر اس کی کیا حیثیت ہے، کیونکہ اس سے فیصلہ متاثر ہوتا ہے۔ OrthoATI آسٹریلین رجسٹر آف تھیراپیوٹک گڈز (Australian Register of Therapeutic Goods) میں رجسٹرڈ نہیں ہے۔ یہ تھیراپیوٹک گڈز ایڈمنسٹریشن (Therapeutic Goods Administration) کی اسپیشل ایکسیس اسکیم (Special Access Scheme) کے تحت فراہم کی جاتی ہے، جو وہ راستہ ہے جس کے ذریعے ایک ڈاکٹر کسی ایک مریض کے لیے غیر منظور شدہ پروڈکٹ حاصل کر سکتا ہے۔ یہ ایک جائز اور عام طور پر استعمال ہونے والا راستہ ہے، لیکن اس کے دو نتائج ہیں: آپ کے ڈاکٹر اس فیصلے کی ذاتی ذمہ داری لیتے ہیں اور انہیں آپ کو بتانا ہوتا ہے کہ یہ پروڈکٹ منظور شدہ نہیں ہے، اور یہ میڈیکیئر (Medicare) سے ادا ہونے والا علاج نہیں ہے، اس لیے خلیوں کی تیاری والے حصے کی ادائیگی آپ کو خود کرنی ہوتی ہے۔ یہ بات بایوپسی سے پہلے تحریری طور پر مانگیں، بعد میں نہیں۔
اگر مندرجہ ذیل تمام باتیں درست ہوں تو اس پر بات کرنا مفید ہو سکتا ہے۔
- آپ کا ٹینڈن کا مسئلہ چھ ماہ سے کہیں زیادہ عرصے سے چل رہا ہے اور واقعی معذور کر دینے والا ہے۔
- آپ نے فزیوتھراپسٹ کے ساتھ ٹینڈن پر بتدریج بوجھ ڈالنے اور طاقت بڑھانے کا پروگرام پوری طرح مکمل کیا ہے — صرف آزمایا نہیں — اور اس سے فائدہ نہیں ہوا۔
- تشخیص کی الٹراساؤنڈ یا ایم آر آئی پر تصدیق ہو چکی ہے، اس لیے واضح ہے کہ درد ٹینڈن سے آ رہا ہے۔
- آپ قبول کرتے ہیں کہ آپ ایک غیر ثابت شدہ علاج چن رہے ہیں، اور آپ آپریشن کروانے یا انتظار کرتے رہنے کے بجائے یہ کرنا پسند کریں گے۔
غالباً یہ صحیح انتخاب نہیں اگر آپ کی علامات حال ہی میں شروع ہوئی ہیں، اگر آپ نے ابھی تک بحالی کا باقاعدہ پروگرام نہیں کیا، اگر درد کی کوئی اور وجہ ہو جیسے دبا ہوا عصب، یا اگر یہ سننا کہ "ہم ابھی نہیں جانتے کہ یہ کام کرتا ہے یا نہیں" ایسی بات نہیں جس کے ساتھ آپ اطمینان سے رہ سکیں۔
ان میں سے کسی بات پر غور کرنے سے پہلے ڈاکٹر کیرن ہِرپرا آپ کے ساتھ متبادل طریقوں پر بات کریں گے — منظم طریقے سے بوجھ ڈالنے والا پروگرام جاری رکھنا، بریس، مزید انجکشن جیسے کورٹیسون یا پی آر پی (PRP)، اور جہاں مناسب ہو آپریشن — اور آپ کو صاف صاف بتائیں گے کہ ضدی ٹینس ایلبو کے کسی بھی علاج کے پیچھے، سرجری سمیت، مضبوط شواہد موجود نہیں ہیں۔
خلاصہ
اے ٹی آئی آپ کے اپنے، لیبارٹری میں اگائے گئے ٹینڈن کے خلیوں کا ایک ایسا انجکشن ہے جسے جسم اچھی طرح برداشت کرتا ہے، جس کا حفاظتی ریکارڈ صاف ہے، اور جن تھوڑے سے لوگوں پر تحقیق ہوئی ہے ان میں بہتری کا ایک مستقل اور دیرپا انداز نظر آیا ہے۔
ساتھ ہی، اس وقت یہ ایک غیر منظور شدہ پروڈکٹ ہے جس کی حمایت میں پانچ شائع شدہ تحقیقات اور 50 مریض ہیں، اور ان میں سے کسی میں موازنے کا گروپ نہیں تھا۔ جس ٹرائل کو اس کی تشہیر کے لیے استعمال کیا جاتا ہے وہ کبھی شائع نہیں ہوا؛ اور وہ واحد بلائنڈ ٹرائل جو اسے صحیح طریقے سے پرکھ سکتا تھا، اس کے نتائج کبھی سامنے نہیں آئے۔ ایک ایسی بیماری میں جس میں زیادہ تر لوگ ایک سال کے اندر خود ہی ٹھیک ہو جاتے ہیں، اور جس میں سرجری بھی نقلی آپریشن سے بہتر ثابت نہیں ہوئی، یہ کہنے کے لیے اتنا کافی نہیں کہ یہ کام کرتا ہے۔
اگر آپ اس پر غور کر رہے ہیں، تو مفید سوال یہ نہیں کہ "کیا سائنس امید افزا لگتی ہے" — وہ لگتی ہے۔ مفید سوال یہ ہے کہ کیا آپ ایک ایسے علاج کے لیے پیسے دینے اور خود کو اس کا پابند کرنے میں مطمئن ہیں جس کے فائدے کو ابھی تک بیماری کے قدرتی طور پر ٹھیک ہونے اور علاج کروانے کی توقع کے اثر سے الگ کر کے نہیں دیکھا گیا۔ ایک اچھی طرح باخبر شخص کے لیے یہ ایک معقول انتخاب ہے۔ لیکن کسی کو بھی باتوں میں لا کر اس پر راضی نہیں کیا جانا چاہیے۔
مزید تفصیل
Advanced reading: the deeper science (optional)
یہ حصہ آپ کے اپنے علاج کے فیصلے کے لیے ضرورت سے زیادہ تفصیل میں جاتا ہے۔ آٹولوگس ٹینوسائٹ امپلانٹیشن اضافی مطالعے کے قابل اس لیے ہے کہ یہ ایک ایسے مسئلے کی غیر معمولی طور پر واضح مثال ہے جو پوری ری جنریٹو آرتھوپیڈکس (regenerative orthopaedics، جسم کے خلیوں سے بافت کو دوبارہ بنانے والے علاج) میں پایا جاتا ہے: ایک علاج حیاتیاتی طور پر معقول ہو سکتا ہے، اس کے بعد مسلسل بہتری نظر آ سکتی ہے، وہ مکمل طور پر محفوظ ہو سکتا ہے، اور پھر بھی یہ ثابت نہ ہوا ہو کہ وہ کام کرتا ہے، اور اس کی وجہ تقریباً کبھی حیاتیات نہیں ہوتی۔ وجہ تحقیقات کا ڈیزائن ہوتا ہے۔
ٹینڈن کے خلیے واپس ڈالنے سے فائدے کی امید کیوں کی گئی
ٹینڈن کا پرانا درد ٹینڈن کی سوزش (tendinitis) نہیں ہوتا۔ جب خراب ہو چکی بافت کا معائنہ کیا جاتا ہے، تو اس میں بہت کم سوزش ہوتی ہے۔ اس کے بجائے اس میں بے ترتیب کولیجن، نئی خون کی نالیوں اور اعصاب کا اندر بڑھ آنا، اور وہاں رہنے والے خلیوں کی ایک مشکل میں پھنسی آبادی ہوتی ہے۔ پرانے ٹینس ایلبو میں ایکسٹینسر کارپی ریڈیالس بریوس (extensor carpi radialis brevis، کلائی کو پیچھے کی طرف موڑنے والا ایک پٹھا) کے جڑنے کی جگہ پر، خود ٹینڈن کے خلیوں میں خلیوں کی خود کار موت (apoptosis) اور آٹوفیجک موت (autophagic cell death) دونوں دکھائی جا سکتی ہیں [1]۔ عمر رسیدہ ٹینڈن کے خلیے آکسیجن کے دباؤ پر منحصر Rac1 سگنلنگ کے ذریعے ٹینڈن کی خرابی والی حالت (tendinotic phenotype) کی طرف بڑھتے ہیں [2]۔ اس تصویر کے مطابق خراب حصے میں سوزش نہیں ہوتی، بلکہ وہ خلیوں سے خالی ہو چکا ہوتا ہے، اور اسے کولیجن بنانے والے صحت مند خلیوں سے دوبارہ بھرنا ایک منطقی کوشش ہے۔
اے ٹی آئی میں استعمال ہونے والے خلیوں کو صرف جمع نہیں کیا جاتا بلکہ ان کی خصوصیات کی جانچ بھی کی جاتی ہے۔ کہنی کی بنیادی تحقیق میں، لیبارٹری میں اگائے گئے خلیوں کا فلو سائٹومیٹری (flow cytometry) اور کوانٹیٹیٹو ریئل ٹائم پی سی آر (quantitative real-time PCR) سے تجزیہ کیا گیا اور دکھایا گیا کہ ان میں ٹینڈن کے خلیوں کی ایسی پہچان موجود ہے جو میزینکائمل اسٹیم سیلز (mesenchymal stem cells) سے الگ کی جا سکتی ہے، اور تقریباً 2 ملی لیٹر مائع، جس میں فی ملی لیٹر 2 سے 5 × 10⁶ خلیے 10 فیصد آٹولوگس سیرم (مریض کے اپنے خون کا سیرم) میں تھے، 18 گیج کی سوئی کے ذریعے ایک یا دو بار میں خراب حصے میں ڈالا گیا؛ جان بوجھ کر بار بار سوئی چبھونے کا طریقہ (peppering) استعمال نہیں کیا گیا، کیونکہ مقصد خون بہانا نہیں بلکہ خلیے رکھنا تھا [3]۔
اس ڈیزائن کے اندر ایک مفروضہ ایسا ہے جس کا شاذ و نادر ہی جائزہ لیا جاتا ہے۔ عطیہ دینے والا ٹینڈن گھٹنے کی چپنی کے نیچے والا ٹینڈن ہے؛ جبکہ ہدف کہنی کے باہر کی وہ جگہ ہے جہاں کلائی اور انگلیوں کو سیدھا کرنے والے پٹھوں کے ٹینڈن ہڈی سے جڑتے ہیں (common extensor origin)۔ مختلف جگہوں کے ٹینڈن کے خلیے ایک دوسرے کا بدل نہیں ہوتے، انسان کے فلیکسر (flexor، موڑنے والے) اور ایکسٹینسر (extensor، سیدھا کرنے والے) ٹینڈنوں کے خلیے لیبارٹری میں (in vitro) اپنی نشوونما اور میٹرکس (matrix) کے رویے میں قابلِ پیمائش حد تک مختلف ہوتے ہیں [4]، اس لیے یہ بنیادی مفروضہ کہ گھٹنے سے لیا گیا ٹینڈن کا خلیہ انجکشن کے بعد کہنی کے ٹینڈن کے خلیے کی طرح برتاؤ کرے گا، ایک ایسا مفروضہ ہے جسے طبی تحقیقات جانچنے کے بجائے ویسے ہی اپنا لیتی ہیں۔ بنانے والی کمپنی کا اپنا لیبارٹری کام بتاتا ہے کہ عطیہ دینے والے کی عمر اور عطیے کی جگہ خلیوں کی نشوونما یا حیاتیاتی سرگرمی کو کم نہیں کرتی، جو اس مسئلے کے ایک حصے کا جواب ہے، لیکن یہ لیبارٹری کی پلیٹ میں ناپا گیا نتیجہ ہے، اور اسی گروپ کا ہے جو یہ پروڈکٹ فروخت کرتا ہے۔
پچاس مریضوں نے دراصل کیا دکھایا
سن 2025 میں شائع ہونے والے ایک آزاد منظم جائزے (systematic review) نے، جس کے لیے کوئی بیرونی فنڈنگ نہیں تھی اور جس میں مفادات کا کوئی ٹکراؤ ظاہر نہیں کیا گیا، 174 ریکارڈز کو کھنگالا اور شامل کیے جانے کے قابل پانچ تحقیقات پائیں جن میں مجموعی طور پر 50 مریض تھے: تین کیس سیریز اور دو کیس رپورٹیں، سب 2013 اور 2018 کے درمیان آسٹریلیا میں کی گئیں [5]۔ یہی اس ٹیکنالوجی کا کل شائع شدہ طبی ثبوت ہے، جسم کی تمام جگہوں کو ملا کر۔
اس کے اندر کہنی کے اعداد و شمار سب سے مضبوط ہیں۔ شدید پرانے ٹینس ایلبو والے سولہ مریضوں میں، جن کی علامات کا اوسط دورانیہ 29 ماہ تھا اور جو سب پہلے سے سرجری کی فہرست میں تھے، زیادہ سے زیادہ درد کا VAS اسکور 5.94 سے 12 ماہ پر 86 فیصد اور QuickDASH اسکور 45.88 سے 91 فیصد بہتر ہوا، اور ایم آر آئی پر ٹینڈن کی خرابی اور پھٹاؤ کا ملا جلا اسکور 2 سے 6 کے پیمانے پر 4.31 سے گھٹ کر 2.88 ہو گیا [3]۔ اوسطاً 4.51 سال بعد دوبارہ معائنے پر، درد اب بھی 78 فیصد اور QuickDASH 84 فیصد بہتر تھا، گرفت کی طاقت ایک سال والی قدر سے آگے بڑھتی رہی (19.85 کلوگرام سے بڑھ کر ایک سال پر 37.38 کلوگرام، اور آخری معائنے پر 46.60 کلوگرام)، اور ایم آر آئی اسکور 2.87 تھا جبکہ ایک سال پر 2.88 تھا، اور دو کے سوا تمام مریضوں کا اسکور بالکل یکساں رہا [6]۔ اس سے پہلے کی تکنیک، جس میں ٹینڈن سے لیے گئے خلیوں کے بجائے جلد سے لیے گئے ٹینڈن جیسے خلیے استعمال کیے گئے، نے 12 مریضوں میں چھ ماہ پر درمیانی (median) PRTEE اسکور 78 سے گھٹا کر 12 کر دیا [7]۔
اس تحقیق کے اندر دو نتائج اس سے زیادہ توجہ کے مستحق ہیں جتنی انہیں عام طور پر ملتی ہے۔ پہلا، کولہے کے گلوٹیل ٹینڈن کی خرابی (gluteal tendinopathy) کی سیریز میں طبی اسکور بہتر ہوئے اور 24 ماہ تک برقرار رہے، لیکن ایم آر آئی پر ٹینڈن کی شکل میں کوئی نمایاں تبدیلی نہیں آئی [8]، اس لیے ساخت کی مرمت والی بات کہنی سے ہٹ کر دہرائی نہیں جاتی۔ دوسرا، جانوروں پر ایک کنٹرولڈ تجربے میں، ٹینڈن کے خلیوں سے بھرے اسکیفولڈز (scaffolds، خلیوں کو تھامنے والا ڈھانچہ) نے کم عمر اور بوڑھے جانوروں میں روٹیٹر کف کے بھرنے کو بہتر کیا، لیکن بالغ جانوروں میں بالکل کوئی اثر نہیں کیا [9]۔ ایک ایسا علاج جس کا تجرباتی فائدہ اسی عمر کے گروپ میں غائب ہو جائے جسے حقیقت میں ٹینڈن کی خرابی ہوتی ہے، تسلی بخش نتیجہ نہیں ہے، اور یہ نتیجہ اس ٹیکنالوجی کی کسی تشہیری تفصیل میں نظر نہیں آتا۔
یہ بھی واضح نہیں کہ خلیہ لازماً لیبارٹری میں اگایا گیا ٹینڈن کا خلیہ ہی ہو۔ جلد کے فائبروبلاسٹس (dermal fibroblasts)، جنہیں حاصل کرنا کہیں زیادہ سستا ہے، نے ایک رینڈمائزڈ انسانی ٹرائل میں 2 سینٹی میٹر سے بڑے روٹیٹر کف کے پھٹاؤ کی دوربین کے ذریعے مرمت کے بعد دوبارہ پھٹنے کی شرح کم کی [10]۔ اگر خلیے پہنچانا ہی اصل مؤثر جز ہے، تو ہو سکتا ہے مہنگا خلیہ ضروری نہ ہو۔
ایسے ٹرائل کو کیسے سمجھیں جسے آپ پڑھ نہیں سکتے
اے ٹی آئی کے لیے جس نتیجے کا سب سے زیادہ حوالہ دیا جاتا ہے وہ شدید پرانے ٹینس ایلبو میں سرجری کے مقابلے میں 48 مریضوں کا ایک رینڈمائزڈ موازنہ ہے، جس کا اعلان Orthocell نے 14 نومبر 2023 کو آسٹریلوی اسٹاک ایکسچینج (ASX) کو کیا (https://announcements.asx.com.au/asxpdf/20231114/pdf/05x9jhkpjfmzbp.pdf) اور جسے آسٹریلین آرتھوپیڈک ایسوسی ایشن (Australian Orthopaedic Association) کے سالانہ اجلاس میں پیش کیا گیا۔ اس میں 12 ماہ پر سرجری کے مقابلے میں QuickDASH میں 15.7 پوائنٹ کی برتری (p = 0.0028) اور کام پر واپسی سرجری کے 51 دن کے مقابلے میں 19 دن میں رپورٹ کی گئی۔ تقریباً تین سال بعد بھی یہ PubMed یا Europe PMC میں درج نہیں ہے۔ اس سے چار مخصوص مسائل پیدا ہوتے ہیں، اور ان میں سے کوئی بھی کسی کی ایمانداری پر شک کرنے پر منحصر نہیں۔
ڈیزائن نے ایک چیز کو پرکھا اور سرخی کسی اور چیز کا دعویٰ کرتی ہے۔ یہ 15 پوائنٹ کی QuickDASH حد کے ساتھ ایک نان انفیریئرٹی ٹرائل (non-inferiority trial) تھا، یعنی اسے یہ نتیجہ نکالنے کے لیے بنایا گیا تھا کہ "قابلِ ذکر حد تک بدتر نہیں"، اور یہ کامیابی کا فیصلہ دیتا چاہے اے ٹی آئی 15 پوائنٹ تک کمتر ہوتا۔ پندرہ پوائنٹ تقریباً QuickDASH کے پورے کم سے کم طبی لحاظ سے اہم فرق (minimal clinically important difference) کے برابر ہیں۔ اس ڈھانچے سے برتری کا دعویٰ کرنا اس نتیجے سے مختلف ہے جس کی حمایت کے لیے نمونے کے سائز کا حساب لگایا گیا تھا۔
جو کچھ ناپا گیا وہ سب ذاتی احساس پر مبنی تھا، اور کوئی بھی بلائنڈ نہیں تھا۔ QuickDASH اور VAS مریض خود بھرتے ہیں، اور ہر شریک جانتا تھا کہ اسے آپریشن ملا ہے یا خلیوں کا نیا انجکشن۔ ٹینس ایلبو ٹھیک وہ بیماری ہے جس میں یہ بات قبول نہیں کی جانی چاہیے: ایک آئندہ (prospective)، رینڈمائزڈ، ڈبل بلائنڈ، پلیسبو کنٹرولڈ (double-blinded, placebo-controlled) ٹرائل میں، خراب ہو چکے ECRB کو سرجری سے نکالنے سے نقلی سرجری کے مقابلے میں کوئی اضافی فائدہ نہیں ہوا [11]۔ ایک ایسے آپریشن کے مقابلے میں کھلا (open-label) موازنہ، جو خود پلیسبو سے بہتر نہیں، انجکشن میں حیاتیاتی اثر ثابت نہیں کر سکتا؛ یہ صرف یہ دکھا سکتا ہے کہ ایک ایسی بیماری میں دو علاج کے راستے ملتے جلتے نظر آتے ہیں جس میں بغیر علاج کے تقریباً 90 فیصد لوگ ایک سال کے اندر ٹھیک ہو جاتے ہیں [12]۔
اڑتالیس مریض ایک ایسی تحقیق میں بہت کم ہیں جس کا کمزور ہونا پہلے سے معلوم ہے۔ لیٹرل ایپی کونڈائلائٹس (lateral epicondylitis، یعنی ٹینس ایلبو) کے بغیر آپریشن علاج کے رینڈمائزڈ ٹرائلز کے ایک فریجیلیٹی تجزیے (fragility analysis) میں پایا گیا کہ صرف تین مریضوں کے نتائج الٹ جانے سے رپورٹ کی گئی شماریاتی اہمیت ختم ہو جائے گی [13]۔
اسے اسپانسر نے چلایا، اور اسپانسرشپ ٹھیک اسی بیماری میں نتائج کو قابلِ پیمائش حد تک متاثر کرتی ہے۔ لیٹرل ایپی کونڈائلائٹس کے لیے پلیٹلیٹ رچ پلازما (platelet-rich plasma) کے رینڈمائزڈ ٹرائلز میں صنعت سے وابستگی زیادہ سازگار نتائج سے منسلک ہے [14]۔ اس سے بہت ملتی جلتی میزینکائمل اسٹرومل سیل (mesenchymal stromal cell) کی تحقیق میں، زیادہ تر ٹرائلز میں نتائج کو بڑھا چڑھا کر پیش کیا گیا ہے (spin) [15]، اور خلاصوں (abstracts) میں انہی مقالوں کے مرکزی متن کے مقابلے میں شماریاتی طور پر نمایاں (statistically significant) پی ویلیوز (p-values) کا تناسب نمایاں طور پر زیادہ رپورٹ کیا جاتا ہے [16]۔ آرتھوپیڈک بایولوجکس (orthopaedic biologics) کی رپورٹنگ کے معیارات پر عام طور پر کم عمل کیا جاتا ہے [17]، اسی لیے خلیوں کی خوراک، ان کا زندہ ہونا (viability) اور پیسج نمبر (passage number) عموماً شائع شدہ مواد سے معلوم نہیں ہو سکتے، اور اسٹاک ایکسچینج کے اعلان سے تو بالکل نہیں۔
وہ ٹرائل جو اس سوال کا جواب دے دیتا
یہ ٹرائل NCT01343836 کے طور پر رجسٹر ہوا (https://clinicaltrials.gov/study/NCT01343836)، اسے Erasmus Medical Center میں تحقیق کاروں نے خود شروع کیا، یہ شریک، دیکھ بھال کرنے والے، تحقیق کار اور نتائج جانچنے والے، چاروں کی سطح پر کواڈرپل بلائنڈ (quadruple-blinded) تھا، اور اس میں ایڑی کے ٹینڈن کی پرانی خرابی (chronic Achilles tendinopathy) والے 90 مریضوں کو قرعہ اندازی سے آٹولوگس ٹینوسائٹ امپلانٹیشن یا ٹینڈن کے اندر نمکین پانی (intratendinous saline) کے لیے چنا گیا، اور دونوں کے ساتھ ایسینٹرک لوڈنگ (eccentric loading، ٹینڈن کو لمبا ہوتے ہوئے بوجھ دینے والی ورزش) کروائی گئی۔ بنیادی پیمانہ 24 ہفتوں پر VISA-A اسکور تھا۔ یہ جون 2014 میں مکمل ہوا۔
اس کے کوئی نتائج پوسٹ نہیں کیے گئے۔ رجسٹریشن کو آخری بار فروری 2015 میں اپ ڈیٹ کیا گیا۔ PubMed یا Europe PMC میں کوئی اشاعت درج نہیں؛ رجسٹریشن کا حوالہ دینے والے واحد مقالے وہ جائزے ہیں جو صرف اس کے وجود کا ذکر کرتے ہیں۔
کسی ٹیکنالوجی کے واحد پلیسبو کنٹرولڈ تجربے کی بارہ سال کی خاموشی بذاتِ خود ایک معلومات ہے۔ یہ منفی نتیجے کا ثبوت نہیں، ٹرائلز فنڈنگ، عملے اور تھیسس مکمل کرنے کی وجوہات سے بھی اتنی ہی بار رپورٹ نہیں ہوتے جتنی شرمندگی والے نتائج کی وجہ سے، لیکن اس عدم توازن کو نظر انداز کرنا مشکل ہے: اسپانسر کا چلایا ہوا کھلا ٹرائل مکمل ہونے کے چند ہفتوں کے اندر اعلان کر دیا گیا، اور آزاد بلائنڈ ٹرائل کی طرف سے کبھی کوئی خبر نہیں آئی۔
اس کا اصل فیصلہ کس چیز سے ہوگا
ایک ایسا ٹرائل جس میں اے ٹی آئی کا موازنہ نقلی انجکشن سے ہو، جانچنے والا بلائنڈ ہو، ٹینڈن کی ایک ہی جگہ پر ہو، 12 ماہ پر مریض کی طرف سے رپورٹ کیا گیا بنیادی پیمانہ ہو اور ساتھ امیجنگ کا ایک اور بنیادی پیمانہ ہو جسے ایک بلائنڈ ریڈیالوجسٹ پڑھے۔ QuickDASH میں 15 پوائنٹ کے حقیقی فرق کا پتہ لگانے کے لیے ہر گروپ میں تقریباً 130 مریض۔ پہلے سے رجسٹر کیا گیا ہو، CONSORT کے مطابق رپورٹ کیا گیا ہو، اور خلیوں کی خوراک اور ان کا زندہ ہونا MIBO معیار کے مطابق ظاہر کیا گیا ہو۔ اس میں تکنیکی طور پر کچھ بھی مشکل نہیں؛ بس پہلی ابتدائی تحقیق کے بعد کے سترہ سالوں میں یہ کیا ہی نہیں گیا۔ جب تک ایسا نہیں ہوتا، ٹینڈن کی بیماری کے لیے خلیوں کا علاج وہی رہے گا جو آزاد جائزے بیان کرتے ہیں: اب تک جانچی گئی ٹینڈن کی ہر جگہ پر محفوظ [18]، اور 2025 کے منظم جائزے کے الفاظ میں، ضدی ٹینڈن کی خرابی کے لیے دوسرے درجے کا ایک معقول آپشن جس کے بارے میں ابھی یہ نہیں کہا جا سکتا کہ یہ کام کرتا ہے، کیونکہ کسی نے موازنے کا گروپ شامل نہیں کیا [5]۔
حوالہ جات
[1] Chen J, Wang A, Xu J, Zheng M. In chronic lateral epicondylitis, apoptosis and autophagic cell death occur in the extensor carpi radialis brevis origin. J Shoulder Elbow Surg. 2010;19(3):355-362. https://doi.org/10.1016/j.jse.2009.07.064 [2] McBeath R, Edwards R, Parks S, O'Hara B, Taormina M, Shapiro I, Osterman AL. Tendinosis Results From Oxygen Tension-Dependent Rac1 Signaling in Aging Tenocytes. J Hand Surg Am. 2018;43(9):S39-S40. https://doi.org/10.1016/j.jhsa.2018.06.085 [3] Wang A, Breidahl W, Mackie KE, Lin Z, Qin A, Chen J, Zheng MH. Autologous Tenocyte Injection for the Treatment of Severe, Chronic Resistant Lateral Epicondylitis: A Pilot Study. Am J Sports Med. 2013;41(12):2925-2932. https://doi.org/10.1177/0363546513504285 [4] Evans CE, Trail IA. An in Vitro Comparison of Human Flexor and Extensor Tendon Cells. J Hand Surg Br. 2001;26(4):307-313. https://doi.org/10.1054/jhsb.2001.0593 [5] Demeco A, de Sire A, Salerno A, Marotta N, Comuni B, Gabbi M, Lippi L, Invernizzi M, Ammendolia A, Costantino C. Effects of Autologous Tenocyte Injection for Overuse and Degenerative Tendinopathies: A Systematic Review. J Funct Morphol Kinesiol. 2025;10(1):95. https://doi.org/10.3390/jfmk10010095 [6] Wang A, Mackie K, Breidahl W, Wang T, Zheng MH. Evidence for the Durability of Autologous Tenocyte Injection for Treatment of Chronic Resistant Lateral Epicondylitis: Mean 4.5-Year Clinical Follow-up. Am J Sports Med. 2015;43(7):1775-1783. https://doi.org/10.1177/0363546515579185 [7] Connell D, Datir A, Alyas F, Curtis M. Treatment of lateral epicondylitis using skin-derived tenocyte-like cells. Br J Sports Med. 2009;43(4):293-298. https://doi.org/10.1136/bjsm.2008.056457 [8] Bucher TA, Ebert JR, Smith A, Breidahl W, Fallon M, Wang T, Zheng M, Janes GC. Autologous Tenocyte Injection for the Treatment of Chronic Recalcitrant Gluteal Tendinopathy: A Prospective Pilot Study. Orthop J Sports Med. 2017;5(2):2325967116688866. https://doi.org/10.1177/2325967116688866 [9] Huegel J, Kim DH, Cirone JM, Pardes AM, Morris TR, Nuss CA, Mauck RL, Soslowsky LJ, Kuntz AF. Autologous tendon-derived cell-seeded nanofibrous scaffolds improve rotator cuff repair in an age-dependent fashion. J Orthop Res. 2016;35(6):1250-1257. https://doi.org/10.1002/jor.23381 [10] Kim YK, Kim YT, Won Y, Jang YH, Hwang ST, Han J, Jeon S, Kim SH, Oh JH. Efficacy of an Autologous Dermal Fibroblast Injection in Reducing the Retear Rate After Arthroscopic Rotator Cuff Repair. Am J Sports Med. 2025;53(3):592-599. https://doi.org/10.1177/03635465241311605 [11] Kroslak M, Murrell GAC. Surgical Treatment of Lateral Epicondylitis: A Prospective, Randomized, Double-Blinded, Placebo-Controlled Clinical Trial. Am J Sports Med. 2018;46(5):1106-1113. https://doi.org/10.1177/0363546517753385 [12] Ikonen J, Lähdeoja T, Ardern CL, Buchbinder R, Reito A, Karjalainen T. Persistent Tennis Elbow Symptoms Have Little Prognostic Value: A Systematic Review and Meta-analysis. Clin Orthop Relat Res. 2021;480(4):647-660. https://doi.org/10.1097/corr.0000000000002058 [13] Shah R, Yu A, Kelley MG, Yendluri A, Bienstock D, Nietsch K, Megafu MN, Li X, Kelly JD, Parisien RL. Randomized controlled trial outcomes for nonoperative management of lateral epicondylitis of the elbow are statistically fragile. JSES Rev Rep Tech. 2025;5(4):798-804. https://doi.org/10.1016/j.xrrt.2025.03.008 [14] Castonguay JB, Kotlier JL, Fathi A, Petrigliano FA, Liu JN. Industry affiliation influence on randomized controlled trials for platelet-rich plasma in the treatment of lateral epicondylitis. JSES Int. 2024;8(6):1284-1289. https://doi.org/10.1016/j.jseint.2024.06.010 [15] Woolley K, Milan N, Master Z, Feeley BT. Evaluation of Spin in Clinical Trials of Mesenchymal Stromal Cells for the Treatment of Knee Osteoarthritis: A Systematic Review. Am J Sports Med. 2025;53(9):2264-2272. https://doi.org/10.1177/03635465241274155 [16] Milan N, Woolley K, Master Z, Feeley BT. Analysis of P Values in the Abstract Compared With the Main Text of Randomized Controlled Trials and Clinical Trials of Mesenchymal Stromal Cells for the Treatment of Knee Osteoarthritis. Orthop J Sports Med. 2025;13(10):23259671251374306. https://doi.org/10.1177/23259671251374306 [17] Robert G, Butler JJ, Tishelman J, Lorentz N, Robertson D, Krebsbach S, Rubin J, Kennedy JG. Poor Adherence to the Minimum Information for Studies Evaluating Biologics in Orthopaedics (MIBO) Guidelines. Clin Orthop Relat Res. 2025;484(3):591-599. https://doi.org/10.1097/corr.0000000000003711 [18] Mirghaderi SP, Valizadeh Z, Shadman K, Lafosse T, Oryadi-Zanjani L, Yekaninejad MS, Nabian MH. Cell therapy efficacy and safety in treating tendon disorders: a systemic review of clinical studies. J Exp Orthop. 2022;9(1):85. https://doi.org/10.1186/s40634-022-00520-9