Patients › Rehabilitation
روٹیٹر کف کی مرمت
Staged rehabilitation protocol after rotator cuff repair at Mater Private Hospital Rockhampton, with the early exercise program.
یہ پروٹوکول (protocol) ڈاکٹر کیرن ہِرپرا کے ذریعے Mater Private Hospital Rockhampton میں ہونے والی روٹیٹر کف (rotator cuff) کی مرمت کے بعد آپ کی صحت یابی میں رہنمائی کرتا ہے؛ روٹیٹر کف ٹینڈنوں کا وہ گروپ ہے جو کندھے کو تھامتا اور گھماتا ہے۔ اس میں ہر مرحلے کی سادہ زبان میں وضاحت کے ساتھ ایک باقاعدہ پروگرام دیا گیا ہے جو آپ اپنے فزیوتھراپسٹ کو دکھا سکتے ہیں؛ اپنی پہلی ملاقات پر یہ صفحہ یا اس کی پی ڈی ایف ساتھ لائیں تاکہ آپ کی بحالی کا کام مربوط رہے۔ آپ کا فزیوتھراپسٹ آپ کی صحت یابی کی رفتار کے مطابق منصوبے میں تبدیلی کر سکتا ہے۔
اگر سرجری کے بعد آپ کو اپنے زخم کے بارے میں کوئی تشویش ہو تو کلینک سے رابطہ کریں۔ اکثر زخم کی تصویر لے کر معائنے کے لیے ای میل کر دینا مفید ہوتا ہے۔
کیا توقع رکھیں
روٹیٹر کف کی مرمت میں پھٹے ہوئے ٹینڈن (tendon)، یعنی وہ مضبوط ڈوری جو پٹھے کو ہڈی سے جوڑتی ہے، کو دوبارہ ہڈی سے جوڑا جاتا ہے، اور یہ پورا پروگرام اسی قدرتی طور پر دوبارہ جڑنے کے عمل کی حفاظت کے لیے ہے۔ چھ ہفتے پر مرمت ابھی نازک ہوتی ہے اور کئی مہینوں تک پختہ ہوتی رہتی ہے: زخم بھرنے سے متعلق تحقیقات میں چھ ہفتے پر اس کی طاقت معمول کی صرف تقریباً ایک چوتھائی ہوتی ہے، بارہ ہفتے پر تقریباً آدھی، اور کم از کم چھ ماہ تک یہ پوری طاقت کے قریب نہیں پہنچتی۔ اسی لیے حرکت اور بوجھ ایک ساتھ نہیں بلکہ مرحلہ وار واپس شامل کیے جاتے ہیں۔
جلدی زور لگانے کا دل چاہتا ہے، لیکن شواہد تسلی بخش ہیں۔ عام چھوٹے اور درمیانے پھٹاؤ میں، جلدی حرکت شروع کرنے سے جو اضافی حرکت کی حد ملتی ہے وہ عارضی ہوتی ہے، اور ایک سال تک جلدی شروع کرنے اور تھوڑا بعد میں شروع کرنے میں کوئی فرق نہیں رہتا۔ پہلے ہفتوں میں صبر کرنے سے لمبے عرصے میں آپ کا کوئی نقصان نہیں ہوتا، اور یہ مرمت کی اس وقت حفاظت کرتا ہے جب وہ سب سے کمزور ہوتی ہے۔ اس بات کے بھی اچھے شواہد ہیں کہ بالکل پہلے ہفتے میں سخت علاج شروع کرنا فائدے سے زیادہ نقصان دیتا ہے، اس لیے ابتدائی ہفتے جان بوجھ کر ہلکے رکھے جاتے ہیں۔
اپنے کندھے کے لیے آپ جو سب سے مفید کام کر سکتے ہیں وہ ہے شروع میں مرمت کی حفاظت کرنا۔ زیادہ تر دوبارہ پھٹاؤ پہلے تین سے چھ ماہ میں ہوتے ہیں، اور جو مریض ابتدائی پابندیوں پر عمل نہیں کرتے ان میں ٹینڈن کے دوبارہ پھٹنے کا امکان کہیں زیادہ ہوتا ہے۔ پروٹوکول پر قائم رہنا کسی بھی ورزش سے زیادہ اہم ہے۔
روٹیٹر کف کی مرمت کے ساتھ اکثر اسی آپریشن میں دوسرے عمل بھی کیے جاتے ہیں: سب سے عام طور پر کندھے کی چھت والی ہڈی کے نیچے جگہ کھولنا (subacromial decompression)، ہنسلی کی ہڈی کے باہری سرے کو نکالنا (distal clavicle excision)، بائسیپس (biceps) ٹینڈن کو ہڈی پر نئی جگہ جوڑنا (tenodesis)، یا سپراسکیپولر عصب (suprascapular nerve) پر سے دباؤ ختم کرنا۔ جب ایسا ہو تو پوری صحت یابی اسی پروٹوکول کے مطابق ہوتی ہے: مرمت شدہ ٹینڈن سب سے آہستہ بھرنے والا حصہ ہے، اور اسی کا ٹائم ٹیبل رفتار طے کرتا ہے۔
آپ کا ٹائم ٹیبل اس پھٹاؤ کے سائز پر منحصر ہے جس کی مرمت کی گئی۔ رفتار طے کرنے والی یہی سب سے بڑی چیز ہے، کیونکہ بڑے پھٹاؤ زیادہ آہستہ بھرتے ہیں اور ان کے دوبارہ پھٹنے کا امکان زیادہ ہوتا ہے۔ ڈاکٹر ہِرپرا آپ کو بتائیں گے کہ آپ کی مرمت کس گروپ میں آتی ہے، اور نیچے یہ صفحہ پروگرام کو دو واضح عنوانات والے راستوں میں تقسیم کرتا ہے:
- چھوٹے اور درمیانے پھٹاؤ: ایک یا دو ٹینڈن، ٹشو کی اچھی حالت۔
- بڑے اور بہت بڑے پھٹاؤ: بڑے پھٹاؤ، دو یا زیادہ ٹینڈن، یا ٹشو کی کمزور حالت۔ مراحل وہی ہیں، لیکن زیادہ دیر تک رکھے جاتے ہیں اور زیادہ احتیاط سے آگے بڑھائے جاتے ہیں: محفوظ حرکت زیادہ دیر تک جاری رکھی جاتی ہے، اپنے زور سے حرکت بعد میں واپس آتی ہے، اور طاقت بڑھانے کا کام دیر سے شروع ہوتا ہے۔
آپریشن
آپ کی روٹیٹر کف کی مرمت آرتھروسکوپی (دوربین کے ذریعے آپریشن) سے، یا کبھی کبھار ایک چھوٹے کھلے چیرے کے ذریعے کی جاتی ہے۔ پھٹے ہوئے ٹینڈن کو بازو کے اوپری حصے کی ہڈی (humerus) کے اوپر اس کی اصل جڑنے کی جگہ پر دوبارہ جوڑا جاتا ہے، اور بحالی کا کام یہ ہے کہ جب تک یہ جوڑ بھر رہا ہو اس کی حفاظت کی جائے، پھر آہستہ آہستہ پوری حرکت، طاقت اور کارکردگی دوبارہ بنائی جائے۔
سلنگ پہننا
آپ کندھے کی ایک سادہ سلنگ پہنیں گے، یعنی گلے سے لٹکی وہ پٹی (sling) جو بازو کو سہارا دیتی ہے، نہ کہ بازو کو جسم سے دور رکھنے والے تکیے والی سلنگ (abduction pillow sling)۔ دونوں کے نتائج میں کوئی ثابت شدہ فرق نہیں ہے، اور سادہ سلنگ کے ساتھ رہنا کہیں زیادہ آسان ہے۔ ڈاکٹر ہِرپرا بڑے اور بہت بڑے پھٹاؤ سمیت ہر کف کی مرمت کے لیے سادہ سلنگ استعمال کرتے ہیں۔
- دن کے وقت سہارے کے لیے سلنگ 6 ہفتے تک پہنیں، خاص طور پر جب آپ گھر سے باہر ہوں یا دوسرے لوگوں کے درمیان ہوں۔
- سلنگ پہن کر نہ سوئیں۔ یہ صرف دن کے وقت کے سہارے کے لیے ہے؛ اسے اتار کر سوئیں، اور بازو کو آرام دہ حالت میں تکیے پر سہارا دے کر رکھیں۔
- نہانے اور ورزشوں کے لیے اسے اتار دیں (جب آپ کو طریقہ سکھا دیا جائے)۔ جب بھی سلنگ اتری ہو، اپنا بازو ڈھیلا اور پہلو کے ساتھ رکھیں۔
- اگر کندھا سوجا ہوا ہو یا درد کر رہا ہو تو برف استعمال کریں، خاص طور پر ورزش کے بعد۔
- درد سے آرام کے لیے، جب تک آپ کو کچھ اور نہ بتایا گیا ہو، باقاعدگی سے پیراسیٹامول کے ساتھ سوزش کم کرنے والی دوا (جیسے آئبوپروفین) لیں، جیسا کہ آپریشن کے بعد درد پر قابو میں بتایا گیا ہے۔ ورزش سے پہلے ایک خوراک لینے سے مدد ملتی ہے۔
سلنگ استعمال کرتے وقت اپنے بیٹھنے اور کھڑے ہونے کے انداز پر دھیان دیں: کان، کندھے اور کولہے ایک سیدھ میں رکھیں اور جھک کر نہ بیٹھیں۔ درست انداز آپ کی کمر کو محفوظ رکھتا ہے اور کندھے کو اکڑنے سے بچانے میں مدد دیتا ہے۔
اہم احتیاطیں: یہ ہرگز نہ کریں
- تقریباً 6 ہفتے تک کندھے کو اس کے اپنے زور سے ہرگز حرکت نہ دیں (4 ہفتے پر مرمت کی طاقت معمول کی صرف تقریباً 20 فیصد ہوتی ہے)۔
- ہاتھ یا بازو سے 6 ہفتے تک ہرگز کچھ نہ اٹھائیں، نہ دھکیلیں، نہ کھینچیں، اور نہ ہی ان پر وزن ڈالیں۔
- شروع میں بازو کو سیدھا سامنے والی (neutral) پوزیشن سے آگے باہر کی طرف ہرگز نہ گھمائیں۔
- اگر سامنے والے کف ٹینڈن (subscapularis) کی مرمت کی گئی ہو: پہلے 12 ہفتے تک بازو کو خود باہر کی طرف گھمانے (external rotation) کو تقریباً 30 ڈگری کے اندر رکھیں، اور اس دوران بازو کو (مزاحمت کے خلاف) خود اندر کی طرف نہ گھمائیں؛ اس سے سامنے والی مرمت محفوظ رہتی ہے۔ آپ کے سرجن آپ کو بتائیں گے کہ یہ آپ پر لاگو ہوتا ہے یا نہیں۔
- انگوٹھا نیچے کر کے بازو اٹھانے والی "خالی ڈبہ" (empty-can) ورزش ہرگز نہ کریں۔ کبھی بھی نہیں۔
- شروع میں کمر کے پیچھے ہاتھ ہرگز نہ لے جائیں، اور کسی بھی اچانک جھٹکے یا دھکے سے بچیں۔
- جب تک سلنگ ضروری ہو (6 ہفتے) گاڑی ہرگز نہ چلائیں۔
چھوٹے اور درمیانے پھٹاؤ
یہ راستہ ایک یا دو ٹینڈنوں کے ایسے پھٹاؤ کے لیے ہے جن میں ٹشو اچھی حالت میں ہو۔ جہاں کسی مرحلے میں ہفتے کا نمبر دیا گیا ہے، وہی آپ کا ٹائم ٹیبل ہے۔
چھوٹے اور درمیانے پھٹاؤ — پہلا مرحلہ: حفاظت (0 سے 6 ہفتے)

Kieran Hirpara 4.0
خون کی گردش اور گہرے سانس
آپریشن کے بعد کی پیچیدگیوں کا خطرہ کم کرنے کے لیے، روزانہ کم از کم 30 منٹ پیدل چلنے کی کوشش کریں (یہ سب ایک ساتھ کرنا ضروری نہیں)، اور ہر گھنٹے 4 سے 6 گہرے سانس لیں۔
پورے دن کے دوران
Kieran Hirpara 4.0
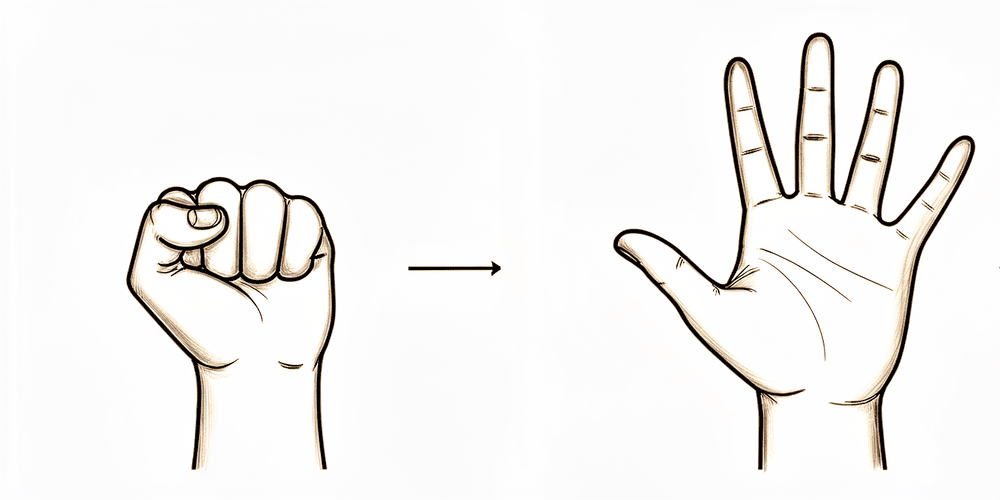
ہاتھ کھولنا اور بند کرنا
ہاتھ کی مضبوط مٹھی بنائیں، پھر اسے پوری طرح کھول دیں۔ اس سے آپ کا ہاتھ حرکت میں رہتا ہے اور اکڑاؤ اور سوجن سے بچاؤ میں مدد ملتی ہے۔
ہر گھنٹے 10 بار
Kieran Hirpara 4.0
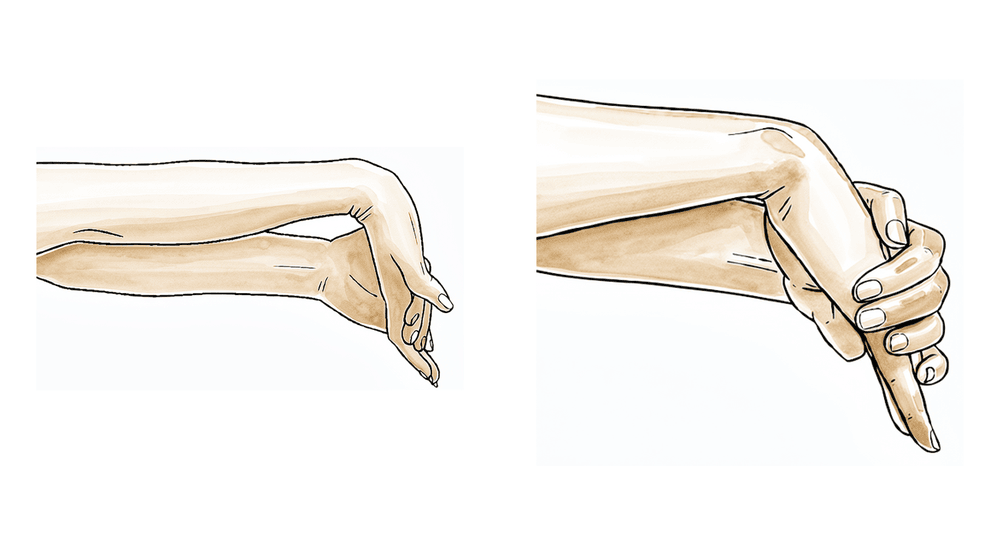
کلائی کو خود موڑنا
اپنی کلائی کو آہستگی سے آگے، پھر پیچھے، اتنا موڑیں جتنا آرام سے ہو سکے۔
ہر گھنٹے 10 سے 15 بار
Kieran Hirpara 4.0
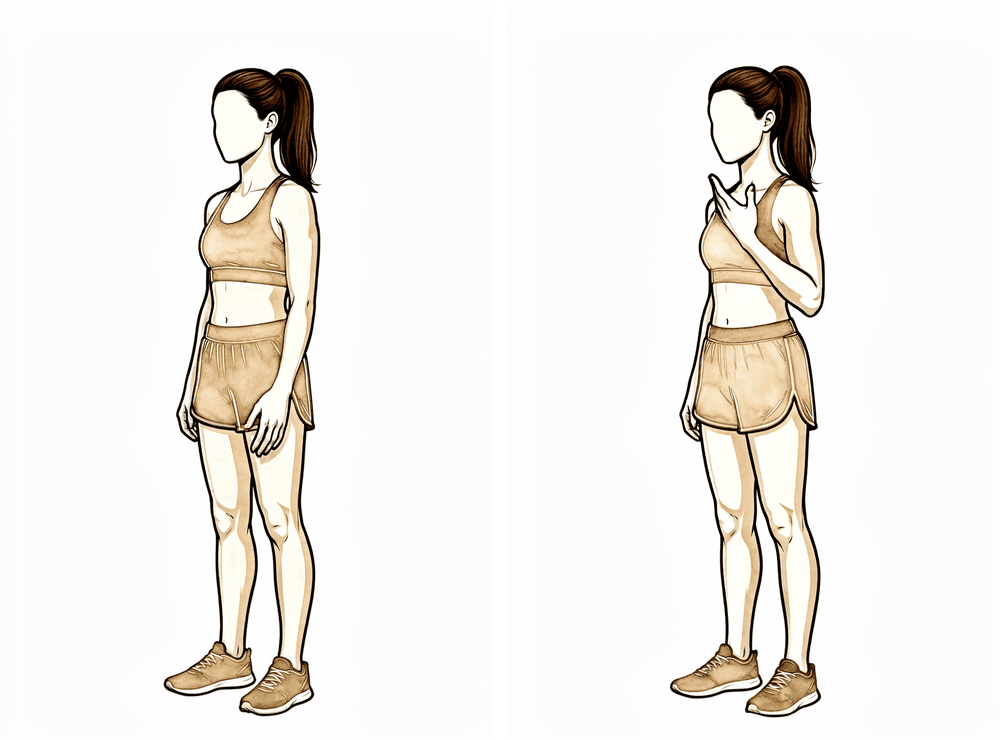
کہنی کو خود موڑنا
ہتھیلی اوپر کی طرف رکھ کر اپنی کہنی کو آہستگی سے جتنا ہو سکے موڑیں، پھر بازو کو دوبارہ سیدھا کریں۔ بازو کا اوپری حصہ اپنے پہلو سے لگا کر رکھیں۔
ہر بار 10 سے 15 مرتبہ، دن میں 2 سے 3 بار
Kieran Hirpara 4.0
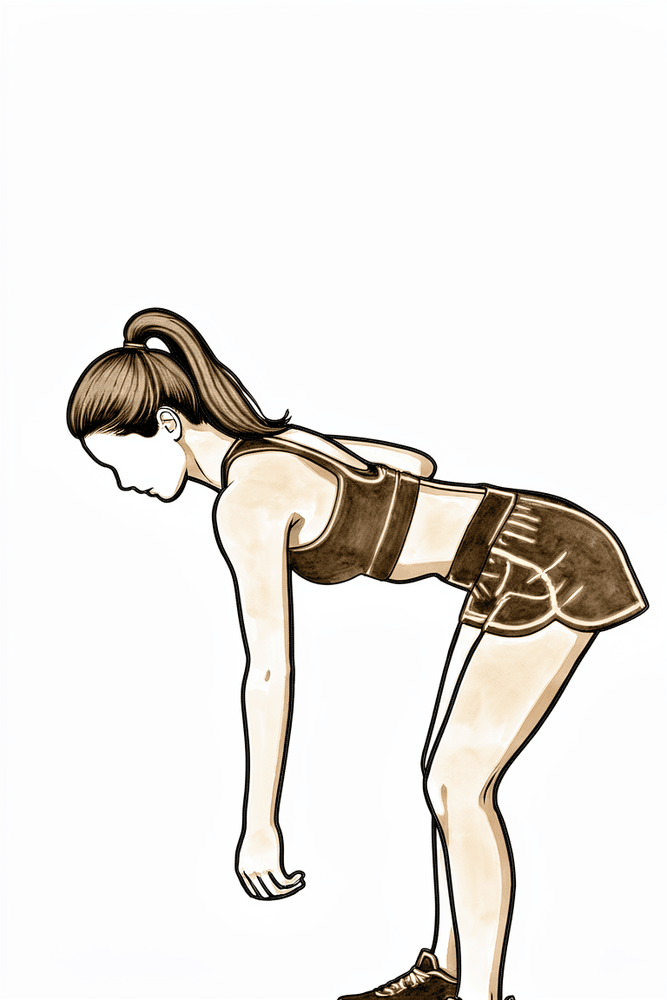
پینڈولم کی طرح بازو جھلانا
آگے کی طرف جھکیں اور آپریشن والے بازو کو بالکل ڈھیلا چھوڑ کر نیچے لٹکنے دیں۔ اپنے جسم کو ہلا کر چھوٹے چھوٹے دائرے بنائیں — پہلے گھڑی کی سوئی کی سمت میں، پھر الٹی سمت میں — کندھے کے پٹھوں کو استعمال کر کے ہرگز نہیں۔ بازو کو آہستگی سے آگے پیچھے اور دائیں بائیں بھی جھلائیں۔ دائرہ چھوٹا رکھیں (تقریباً 20 سینٹی میٹر سے کم)۔ آپریشن والا بازو پورا وقت ڈھیلا رہتا ہے — آپ اسے اٹھا نہیں رہے۔
ہر سمت میں 10 بار، دن میں 2 سے 3 مرتبہ
Kieran Hirpara 4.0
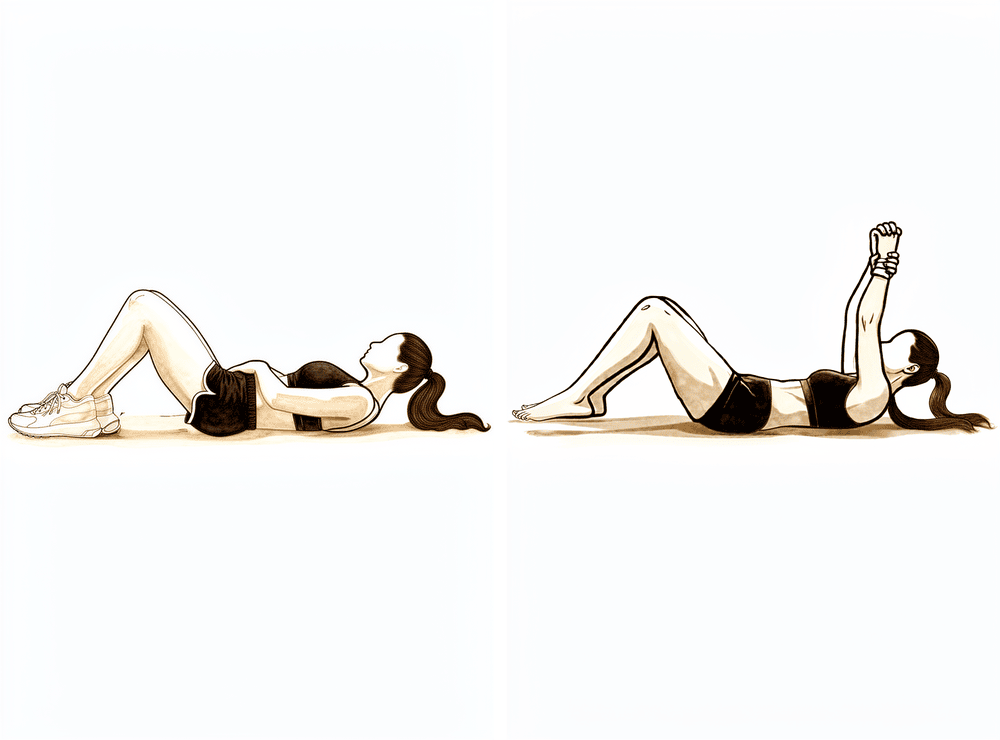
لیٹ کر مدد سے بازو آگے اٹھانا
کمر کے بل لیٹ جائیں۔ اپنا صحت مند ہاتھ آپریشن والے بازو کی کہنی کے نیچے رکھیں اور اس کی مدد سے آپریشن والے بازو کو چھت کی طرف اٹھائیں — آپ کا آپریشن والا کندھا ڈھیلا رہتا ہے اور کام آپ کا صحت مند ہاتھ کرتا ہے۔ اس مرحلے میں کندھے کی اونچائی (تقریباً 90 ڈگری) سے اوپر ہرگز نہ اٹھائیں۔ آہستہ آہستہ واپس شروع کی جگہ پر نیچے لائیں۔
ہر بار 10 مرتبہ، دن میں 2 سے 3 بار
Kieran Hirpara 4.0
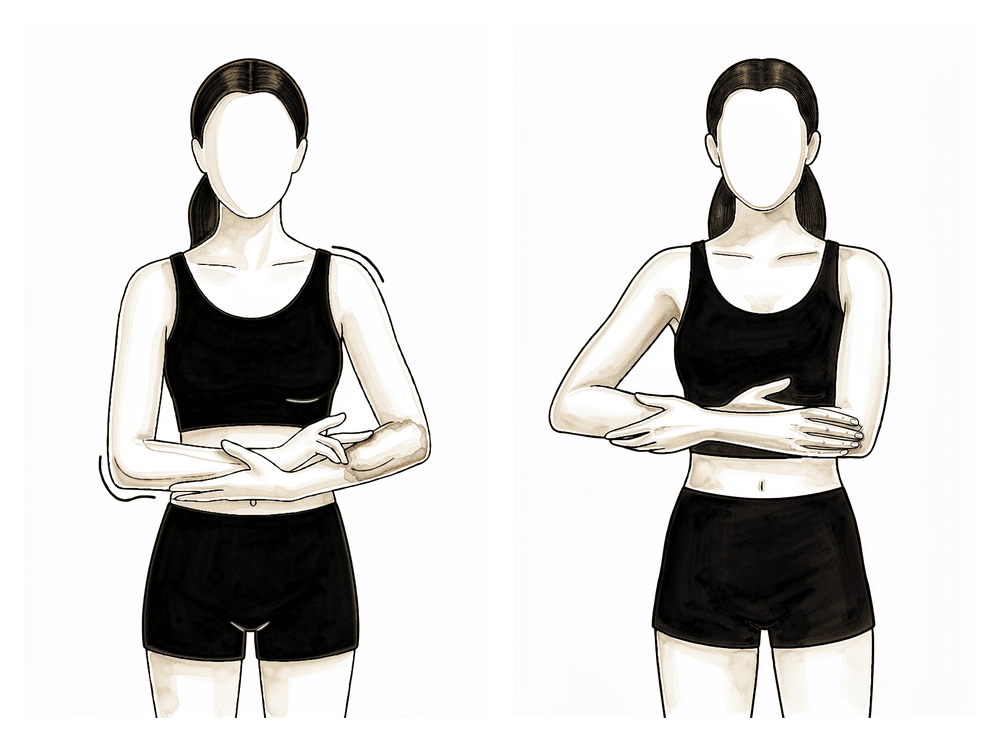
بازو کو سہارا دے کر پہلو کی طرف لے جانا
بیٹھ کر اور تھوڑا سا آگے جھک کر، آپریشن والے بازو کو اپنے صحت مند بازو میں تھام لیں اور اسے پہلو کی طرف لے جانے میں مدد دیں — جیسے کسی بچے کو جھلا رہے ہوں۔ آپ کا آپریشن والا کندھا ڈھیلا رہتا ہے؛ حرکت آپ کا صحت مند بازو دیتا ہے۔
ہر بار 10 مرتبہ، دن میں 2 سے 3 بار
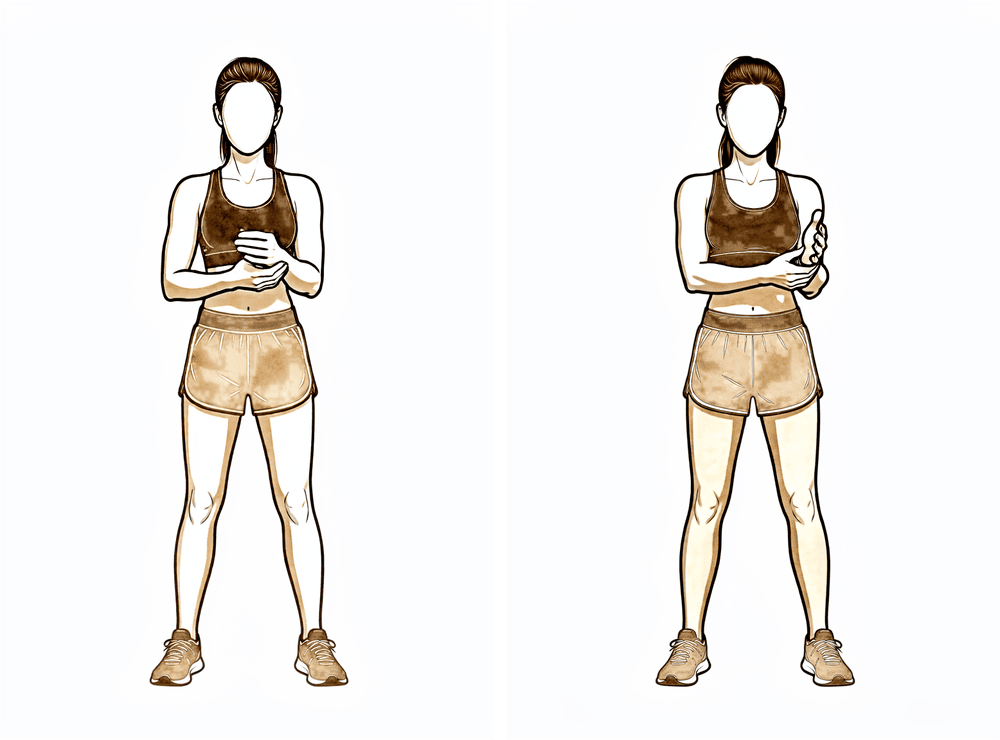
Kieran Hirpara 4.0
مدد سے سیدھی پوزیشن تک باہر کی طرف گھمانا
بیٹھ کر یا کھڑے ہو کر، کہنی کو پہلو سے لگا کر رکھیں اور ہاتھ کو پیٹ پر رکھ کر شروع کریں۔ بازو کے نچلے حصے کو آہستگی سے باہر کی طرف صرف سیدھا سامنے والی (neutral) پوزیشن تک گھمائیں — اس سے آگے نہیں۔ سیدھی پوزیشن سے آگے ہرگز نہ گھمائیں۔ آہستہ سے واپس لائیں۔
ہر بار 10 مرتبہ، دن میں 2 سے 3 بار
Kieran Hirpara 4.0
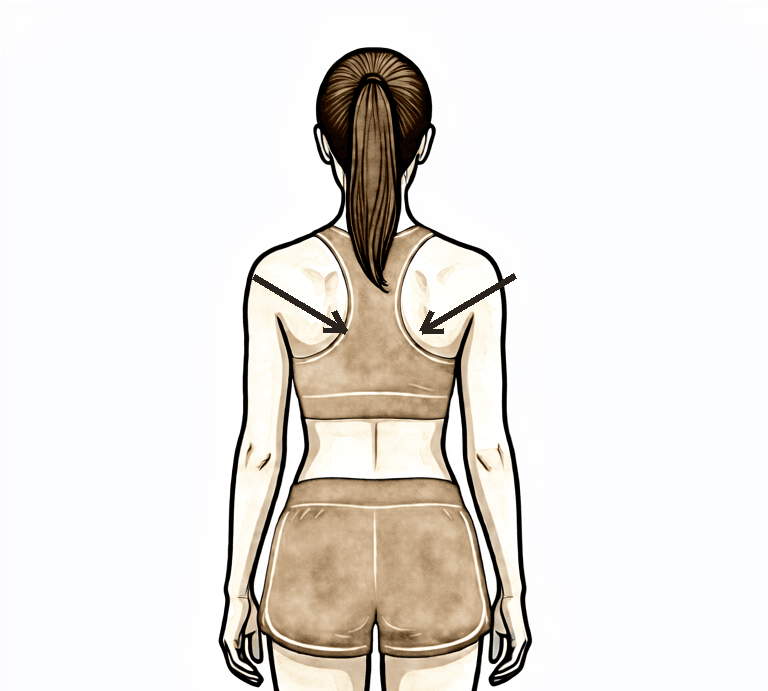
کندھے کی پچھلی ہڈی کو جمانا
اپنے کندھے کی پچھلی چپٹی ہڈیوں (shoulder blades) کو آہستگی سے نیچے اور ایک دوسرے کی طرف دبائیں، روکیں، پھر ڈھیلا چھوڑ دیں۔ یہ پٹھوں کو ہلکا سا متحرک کرنے والی ورزش ہے — آپ کا بازو حرکت نہیں کرتا۔
ہر بار 5 سیکنڈ روکیں، 5 مرتبہ، دن میں 2 سے 3 بار
Kieran Hirpara 4.0
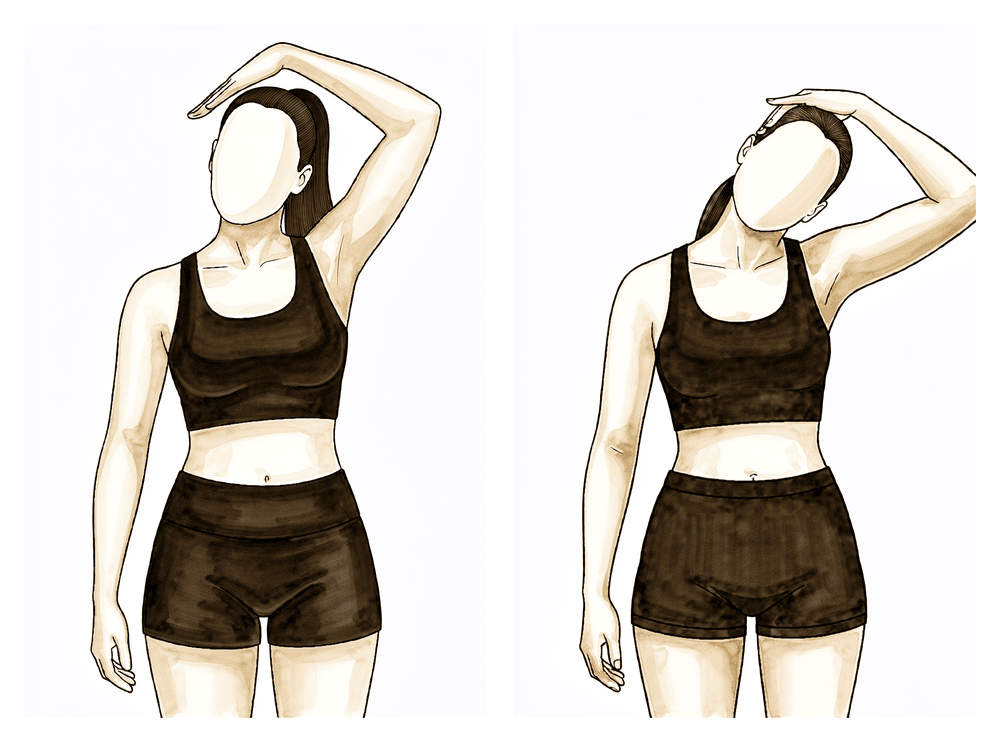
گردن کا پہلو والا اسٹریچ
اپنے صحت مند بازو سے آہستگی سے اپنا کان صحت مند کندھے کی طرف، آپریشن والی طرف سے دور، لائیں یہاں تک کہ گردن میں آرام دہ کھنچاؤ محسوس ہو۔
ہر بار 10 سیکنڈ روکیں، 3 مرتبہ، دن میں 2 سے 3 بار
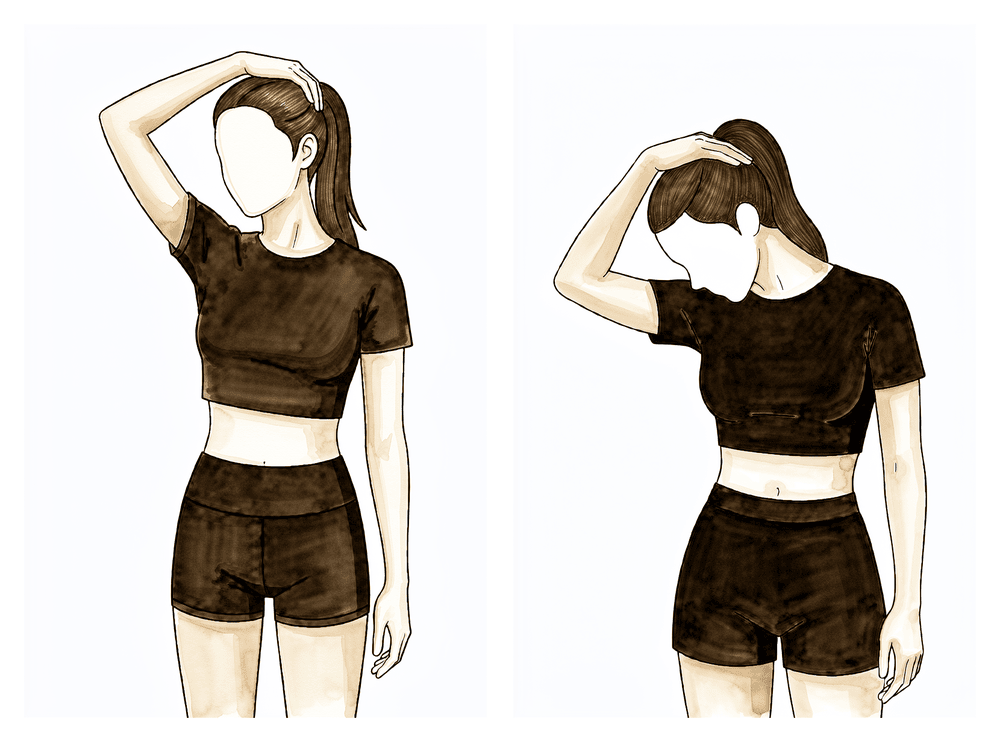
Kieran Hirpara 4.0
بغل کی طرف گردن کا اسٹریچ
اپنے صحت مند بازو سے آہستگی سے اپنی ناک کو نیچے اپنی بغل کی طرف، آپریشن والی طرف سے دور، لائیں یہاں تک کہ آرام دہ کھنچاؤ محسوس ہو۔
ہر بار 10 سیکنڈ روکیں، 3 مرتبہ، دن میں 2 سے 3 بار
پہلے چھ ہفتے ایک ہی بات کے بارے میں ہیں: مرمت کی حفاظت کرنا جب ٹینڈن ہڈی سے جڑنا شروع کرتا ہے۔ آپ دن کے وقت سہارے کے لیے سادہ سلنگ پہنے رہتے ہیں، اسے اتار کر سوتے ہیں، برف سے سوجن پر قابو رکھتے ہیں، اور ہلکی ورزشیں کرتے ہیں جو مرمت شدہ ٹینڈن پر بوجھ ڈالے بغیر آپ کے ہاتھ، کلائی، کہنی اور گردن کو حرکت میں رکھتی ہیں۔ آپ کا فزیوتھراپسٹ (یا آپ خود، اپنے صحت مند بازو کی مدد سے) آپ کے کندھے کو آہستگی سے حرکت دیتا ہے؛ آپ بالکل ڈھیلے رہتے ہیں۔
- سلنگ: دن کے وقت سہارے کے لیے سادہ سلنگ؛ سلنگ اتار کر سوئیں؛ ورزشوں اور صفائی کے لیے اتار دیں۔
- اجازت شدہ حرکت: صرف مدد سے اور غیر فعال (passive) حرکت؛ کندھے کے اپنے زور سے کچھ نہیں۔ یہ کام آپ کے صحت مند بازو یا ایک چھڑی سے لیا جاتا ہے۔ شروع میں مدد سے بازو کو آگے اٹھانے کو آہستہ آہستہ تقریباً 90 ڈگری (آدھے راستے) تک بڑھائیں، اور مدد سے باہر کی طرف گھمانا صرف سیدھا سامنے والی (neutral) پوزیشن تک کریں۔
- ورزشیں: پینڈولم کی طرح بازو جھلانا؛ لیٹ کر مدد سے بازو آگے اٹھانا؛ بازو کو سہارا دے کر پہلو کی طرف لے جانا؛ مدد سے سیدھی پوزیشن تک باہر کی طرف گھمانا؛ ہاتھ، کلائی اور کہنی کی ہلکی حرکت؛ کندھے کی پچھلی چپٹی ہڈی (shoulder blade) اور گردن کی ورزشیں۔
آپ اگلے مرحلے کے لیے تب تیار ہیں جب: آپ کا درد کم ہو رہا ہو اور عام درد کش دوا سے قابو میں ہو (درد کے پیمانے پر 10 میں سے تقریباً 3 یا اس سے کم)؛ مدد سے بازو آرام سے تقریباً 90 ڈگری تک آگے اٹھ جائے؛ مدد سے باہر کی طرف گھمانا آرام سے سیدھی (neutral) پوزیشن تک پہنچ جائے؛ آپ کا زخم کسی مسئلے کی علامت کے بغیر بھر گیا ہو؛ اور اس بات کی کوئی علامت نہ ہو کہ مرمت پر ضرورت سے زیادہ زور پڑا ہے۔
چھوٹے اور درمیانے پھٹاؤ — دوسرا مرحلہ: حرکت کی بحالی (6 سے 12 ہفتے)
Kieran Hirpara 4.0
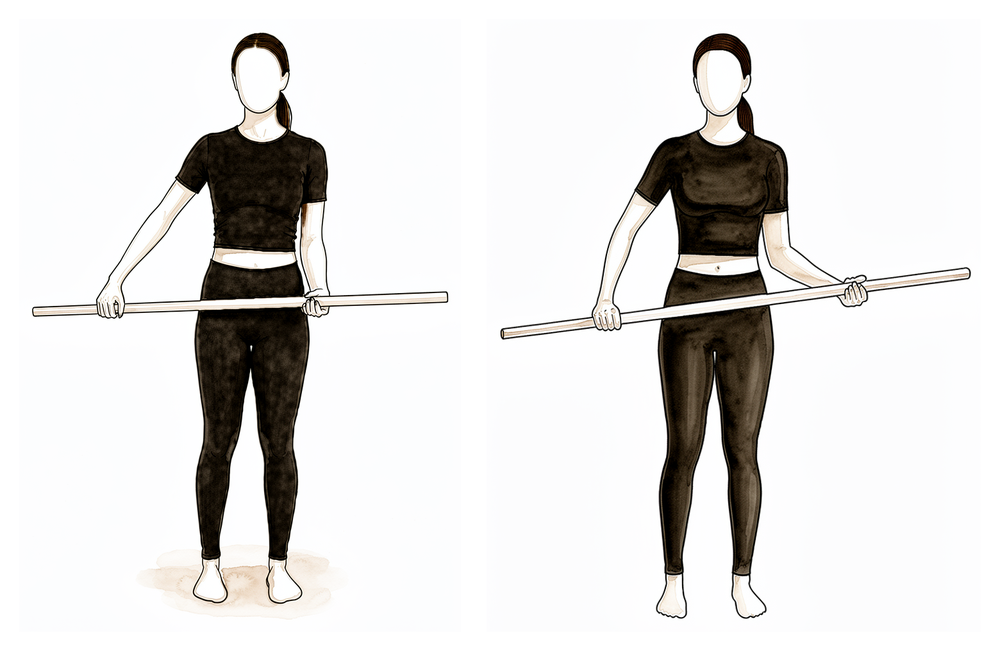
لیٹ کر مدد سے بازو آگے اٹھانا
کمر کے بل لیٹ کر، دونوں ہاتھوں میں ایک چھڑی پکڑیں اور صحت مند بازو کی مدد سے آپریشن والے بازو کو آگے اور اوپر اٹھائیں — آپریشن والا کندھا ڈھیلا رہتا ہے۔ اس مرحلے کے دوران آہستہ آہستہ تقریباً 120 ڈگری (اوپر تک کا تقریباً دو تہائی راستہ) تک پہنچیں، اور اسی حد کے اندر رہیں جو آپ کا فزیوتھراپسٹ طے کرے۔ ہموار حرکت کریں، کبھی زور زبردستی نہ کریں، اور قابو کے ساتھ نیچے لائیں۔
ہر بار 10 مرتبہ، دن میں 2 سے 3 بار
Kieran Hirpara 4.0
چھڑی کی مدد سے باہر کی طرف گھمانا
کمر کے بل لیٹ کر، کہنی پہلو سے لگی ہوئی اور 90 ڈگری پر مڑی ہوئی ہو، دونوں ہاتھوں میں چھڑی پکڑیں اور صحت مند بازو سے آپریشن والے ہاتھ کو آہستگی سے باہر کی طرف دھکیلیں۔ اسی حد کے اندر رہیں جو آپ کا فزیوتھراپسٹ طے کرے اور کبھی زور زبردستی نہ کریں۔
ہر بار 10 مرتبہ، دن میں 2 سے 3 بار
Kieran Hirpara 4.0
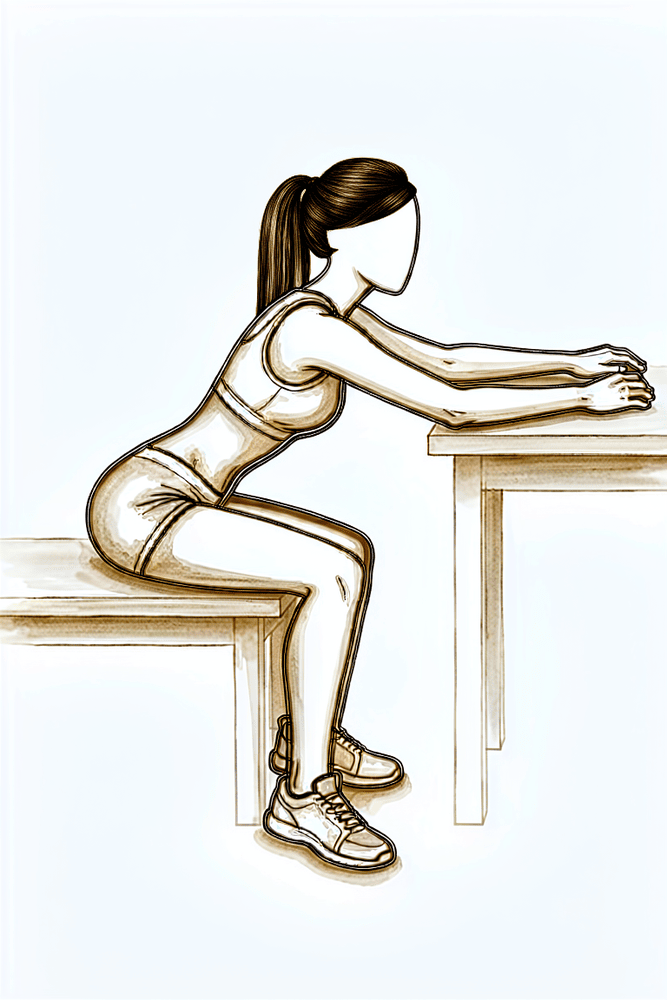
بیٹھ کر میز پر ہاتھ پھسلانا
تقریباً 6ویں ہفتے سے، میز پر بیٹھ جائیں اور آپریشن والا ہاتھ ایک تولیے پر رکھیں۔ ہاتھ کو سطح پر آگے پھسلائیں تاکہ بازو آگے اور اوپر کی طرف جائے، اور وزن میز کو اٹھانے دیں، پھر واپس پھسلائیں۔ یہی ورزش آپ کے فزیوتھراپسٹ کی ہدایت کے مطابق پہلو کی طرف بھی کی جا سکتی ہے۔
ہر بار 10 مرتبہ، دن میں 2 سے 3 بار
Kieran Hirpara 4.0
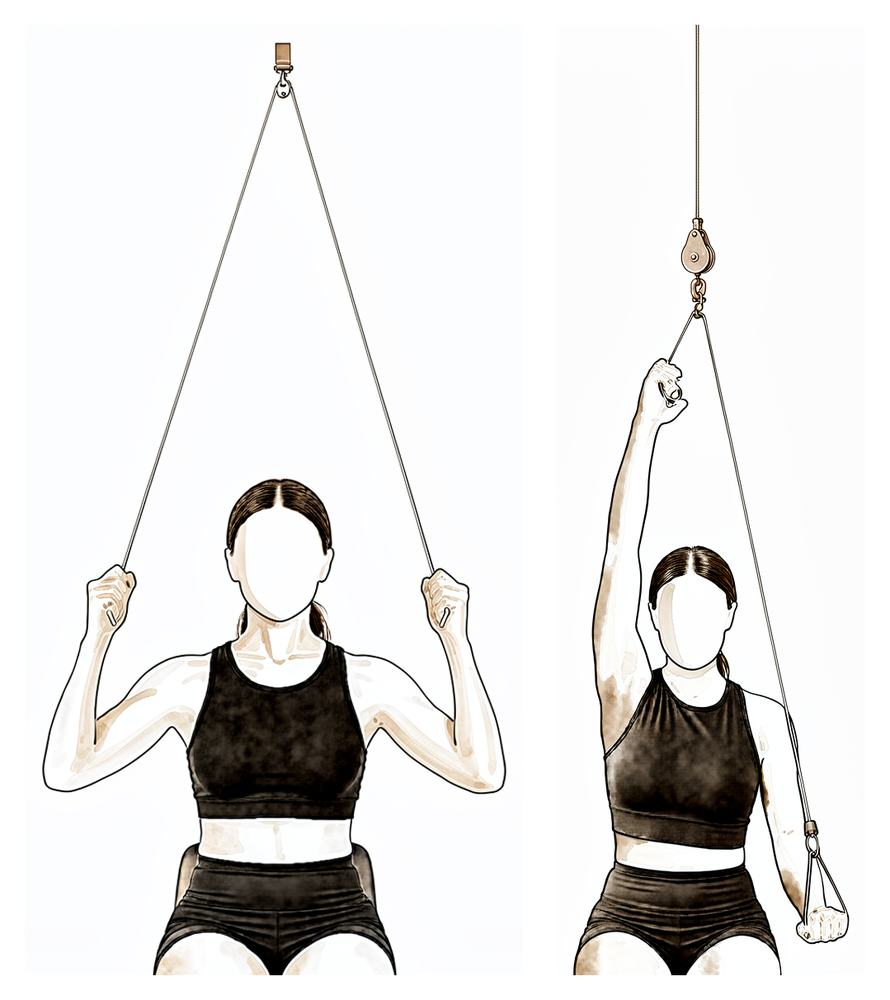
دروازے پر لگی چرخی
تقریباً 6ویں ہفتے سے، دروازے کے اوپر لگی چرخی (over-door pulley) کے نیچے بیٹھیں اور ہر ہاتھ میں ایک ہینڈل پکڑیں۔ صحت مند بازو سے نیچے کھینچیں تاکہ آپریشن والا بازو اوپر اٹھے، آپریشن والے بازو کو ڈھیلا رکھیں، پھر اسے آہستہ آہستہ نیچے لائیں۔
فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
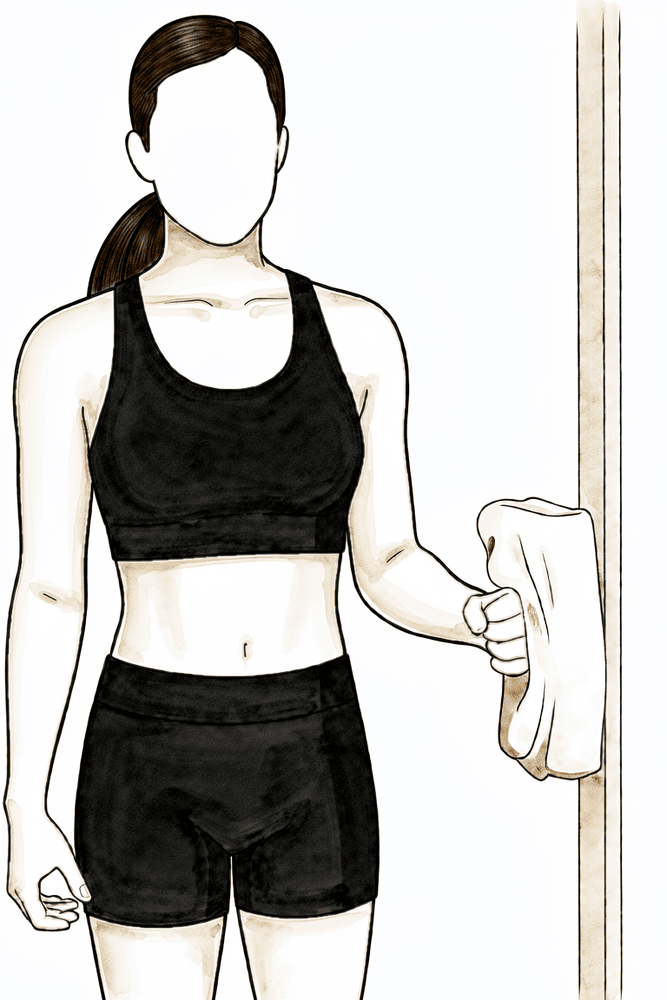
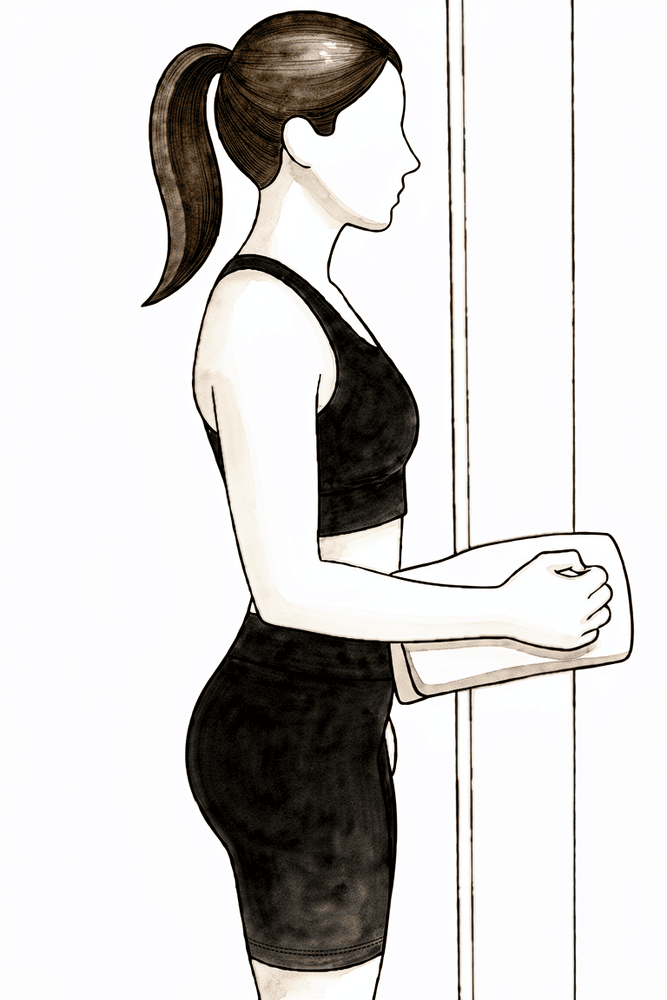
آئسومیٹرک طریقے سے باہر کی طرف گھمانا
تقریباً 8ویں ہفتے سے، اگر آپ کا فزیوتھراپسٹ متفق ہو۔ کہنی کو پہلو سے لگا کر اور 90 ڈگری پر موڑ کر کھڑے ہوں، ہاتھ کی پشت دیوار یا دروازے کی چوکھٹ کے قریب ہو۔ ہاتھ کی پشت کو آہستگی سے باہر کی طرف سطح پر دبائیں، بازو کو ذرا بھی حرکت دیے بغیر — ہلکا زور، اپنی طاقت کا تقریباً ایک چوتھائی، اور کوئی درد نہ ہو۔ روکیں، پھر ڈھیلا چھوڑ دیں۔
تقریباً 5 سیکنڈ روکیں، ہلکا زور (تقریباً 25 فیصد)، فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
آئسومیٹرک طریقے سے اندر کی طرف گھمانا
تقریباً 8ویں ہفتے سے، اگر آپ کا فزیوتھراپسٹ متفق ہو — لیکن اگر سامنے والے کف ٹینڈن (subscapularis) کی مرمت کی گئی ہو تو 12ویں ہفتے سے پہلے ہرگز نہیں۔ کہنی کو پہلو سے لگا کر کھڑے ہوں، ہتھیلی دیوار سے لگی ہو۔ ہتھیلی کو، بازو کو ذرا بھی حرکت دیے بغیر، آہستگی سے اندر کی طرف دبائیں — تقریباً ایک چوتھائی زور، اور کوئی درد نہ ہو۔ روکیں، پھر ڈھیلا چھوڑ دیں۔
تقریباً 5 سیکنڈ روکیں، ہلکا زور (تقریباً 25 فیصد)، فزیوتھراپسٹ کی ہدایت کے مطابق
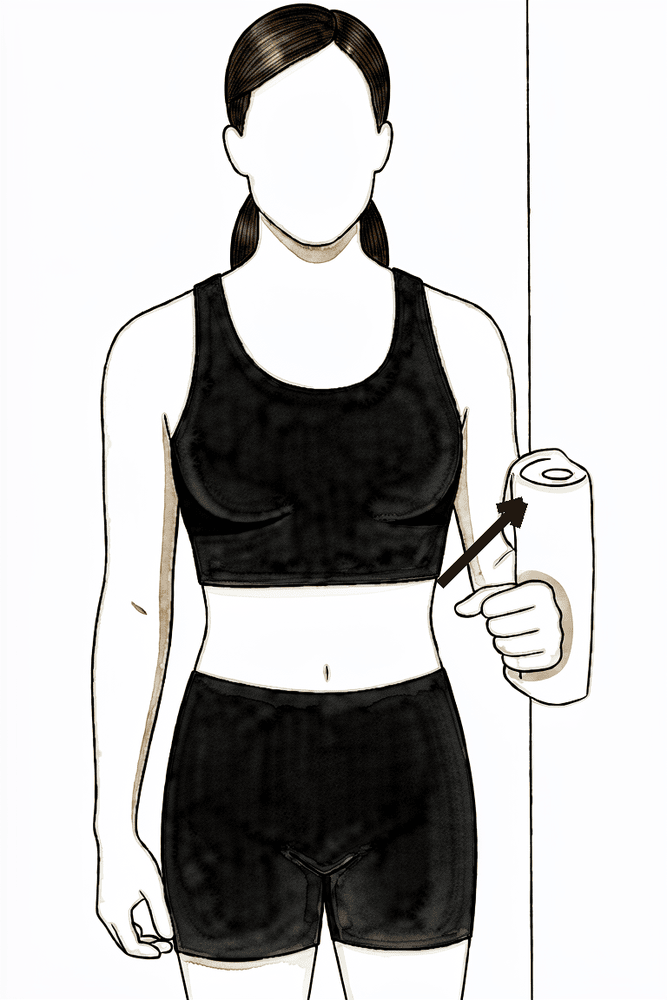
Kieran Hirpara 4.0
آئسومیٹرک طریقے سے بازو کو پہلو کی طرف دبانا
تقریباً 8ویں ہفتے سے، اگر آپ کا فزیوتھراپسٹ متفق ہو۔ دیوار کی طرف پہلو کر کے کھڑے ہوں، بازو کے اوپری حصے کا باہری رخ دیوار کے قریب ہو اور کہنی پہلو سے لگی ہو۔ بازو کو ذرا بھی حرکت دیے بغیر آہستگی سے باہر کی طرف دیوار پر دبائیں — تقریباً ایک چوتھائی زور، کوئی درد نہیں۔ روکیں، پھر ڈھیلا چھوڑ دیں۔
تقریباً 5 سیکنڈ روکیں، ہلکا زور (تقریباً 25 فیصد)، فزیوتھراپسٹ کی ہدایت کے مطابق
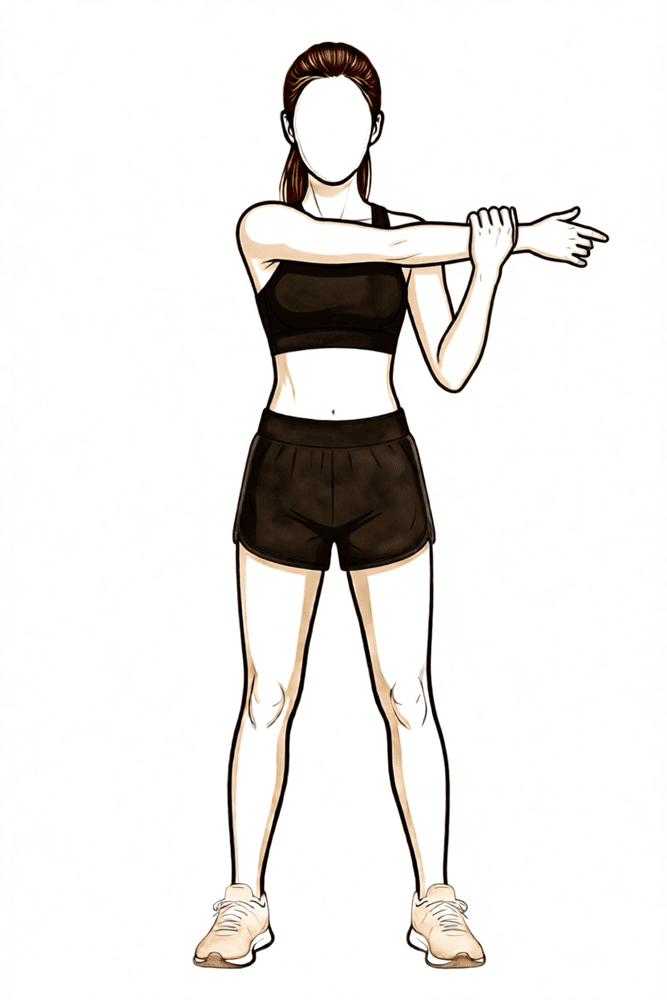
Kieran Hirpara 4.0
سینے کے آر پار اسٹریچ
صرف اس مرحلے کے آخر میں (9ویں ہفتے کے بعد)۔ صحت مند ہاتھ سے آپریشن والے بازو کو آہستگی سے سینے کے آر پار کھینچیں یہاں تک کہ کندھے کے پچھلے حصے میں آرام دہ کھنچاؤ محسوس ہو۔ اسے ہلکا رکھیں — زور زبردستی نہ کریں۔
ہر بار 10 سے 20 سیکنڈ روکیں، چند مرتبہ، فزیوتھراپسٹ کی ہدایت کے مطابق
مرمت بھر رہی ہے لیکن ابھی کمزور ہے: چھ ہفتے پر اس کی طاقت معمول کی صرف تقریباً 20 سے 30 فیصد ہوتی ہے۔ اس لیے یہ مرحلہ طاقت نہیں بلکہ حرکت بحال کرتا ہے۔ اب سلنگ اتر چکی ہے۔ آپ مدد سے حرکت سے آگے بڑھ کر بازو کو اپنے زور سے حرکت دینا شروع کرتے ہیں؛ آغاز آسان پوزیشنوں سے ہوتا ہے (لیٹ کر، یا میز پر ہاتھ پھسلا کر، جہاں کشش ثقل کا بوجھ ہٹ جاتا ہے) اور آہستہ آہستہ سیدھی پوزیشن تک پہنچا جاتا ہے۔ اس مرحلے کے آخر میں پٹھوں کو ہلکا سا متحرک کرنے والی آئسومیٹرک (isometric) ورزشیں شامل کی جاتی ہیں۔
- سلنگ: آہستہ آہستہ چھوڑ دی جاتی ہے (4 سے 6 ہفتے تک زیادہ تر پہلے ہی چھوٹ چکی ہوتی ہے)۔
- اجازت شدہ حرکت: مدد سے پوری حرکت، اور تقریباً 6ویں ہفتے سے آہستہ آہستہ اپنے زور سے حرکت۔ مدد سے یا خود بازو آگے اٹھانے کو تقریباً 120 ڈگری اور اس سے آگے تک بڑھائیں۔
- ورزشیں: لیٹ کر مدد سے بازو آگے اٹھانا؛ چھڑی کی مدد سے باہر کی طرف گھمانا؛ بیٹھ کر میز پر ہاتھ پھسلانا؛ دروازے پر لگی چرخی (over-door pulley)؛ تقریباً 8ویں ہفتے سے ہلکی آئسومیٹرک (دبا کر روکے رکھنے والی) ورزشیں: باہر کی طرف گھمانا، اندر کی طرف گھمانا اور بازو کو پہلو کی طرف دبانا (abduction)؛ مرحلے کے آخر میں (9ویں ہفتے کے بعد) سینے کے آر پار اسٹریچ۔
آپ اگلے مرحلے کے لیے تب تیار ہیں جب: آپ اپنے زور سے بازو کو اچھے قابو کے ساتھ کم از کم 115 سے 120 ڈگری تک آگے اٹھا سکیں (کندھا اچکائے یا کندھے کی پچھلی ہڈی کو اوپر کھینچے بغیر)؛ مدد سے یا غیر فعال حرکت پوری یا تقریباً پوری اور درد کے بغیر ہو؛ ہلکی آئسومیٹرک ورزشیں بعد میں درد بھڑکائے بغیر برداشت ہو جائیں؛ اور مزاحمت والا کام شروع کرنے سے پہلے درد 10 میں سے تقریباً 2 سے زیادہ نہ ہو۔
چھوٹے اور درمیانے پھٹاؤ — تیسرا مرحلہ: طاقت بڑھانا (12 سے 16 ہفتے)
Kieran Hirpara 4.0
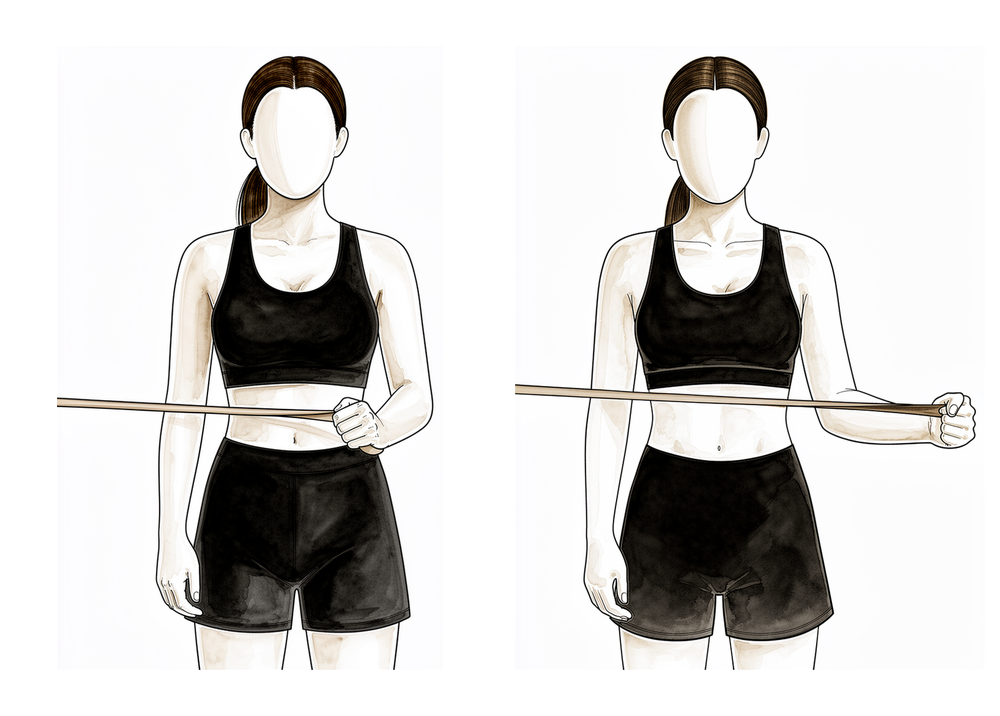
کندھے کی اونچائی پر باہر کی طرف گھمانا (بینڈ)
تقریباً 12ویں ہفتے سے، جب سر سے اوپر حرکت آرام دہ ہو جائے۔ بازو کو پہلو کی طرف کندھے کی اونچائی تک اٹھا کر اور کہنی کو 90 ڈگری پر موڑ کر، بازو کے نچلے حصے کو ہلکے بینڈ کے خلاف اوپر کی طرف گھمائیں، پھر قابو کے ساتھ واپس لائیں۔ بھاری مزاحمت نہیں، بلکہ ہلکا بینڈ اور زیادہ بار دہرانا استعمال کریں۔
فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
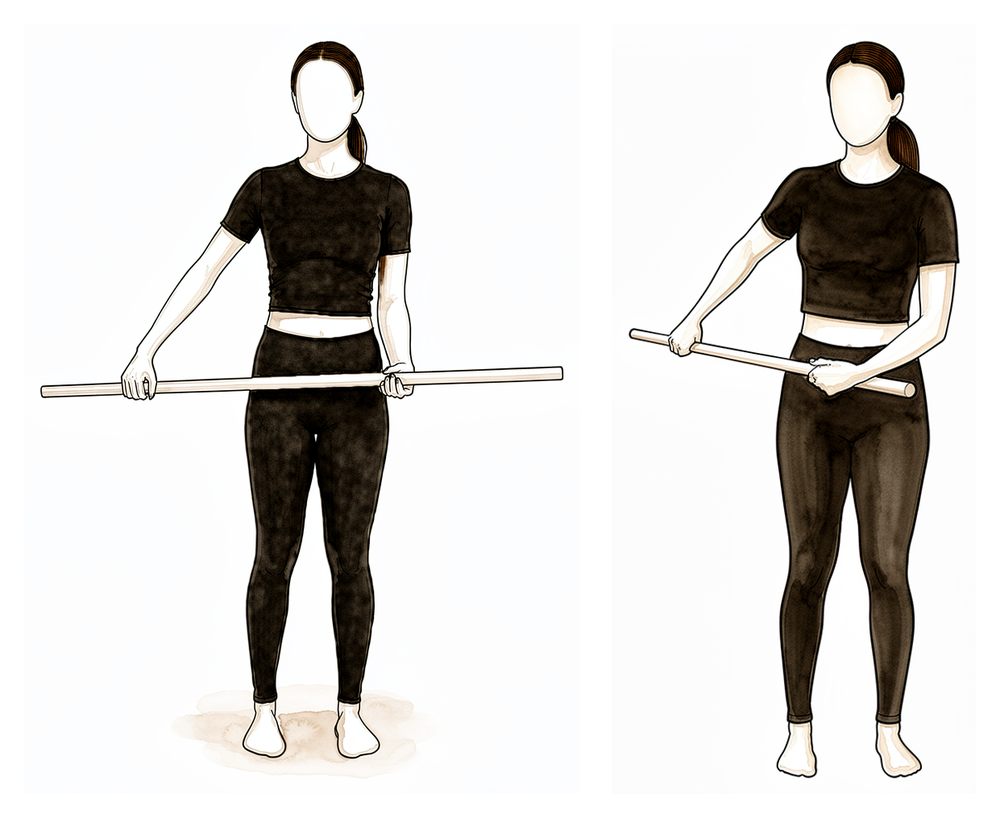
چھڑی کے ساتھ اندر کی طرف گھمانا
تقریباً 12ویں ہفتے سے (اگر سامنے والے کف ٹینڈن کی مرمت کی گئی ہو تو اس سے بعد میں)۔ کمر کے پیچھے ایک چھڑی پکڑیں اور صحت مند ہاتھ سے آپریشن والے ہاتھ کو آہستگی سے کمر پر اوپر کی طرف کھینچیں، پھر قابو کے ساتھ نیچے لائیں۔ اسے آرام دہ اور اپنے فزیوتھراپسٹ کی مقرر کردہ حد کے اندر رکھیں۔
فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
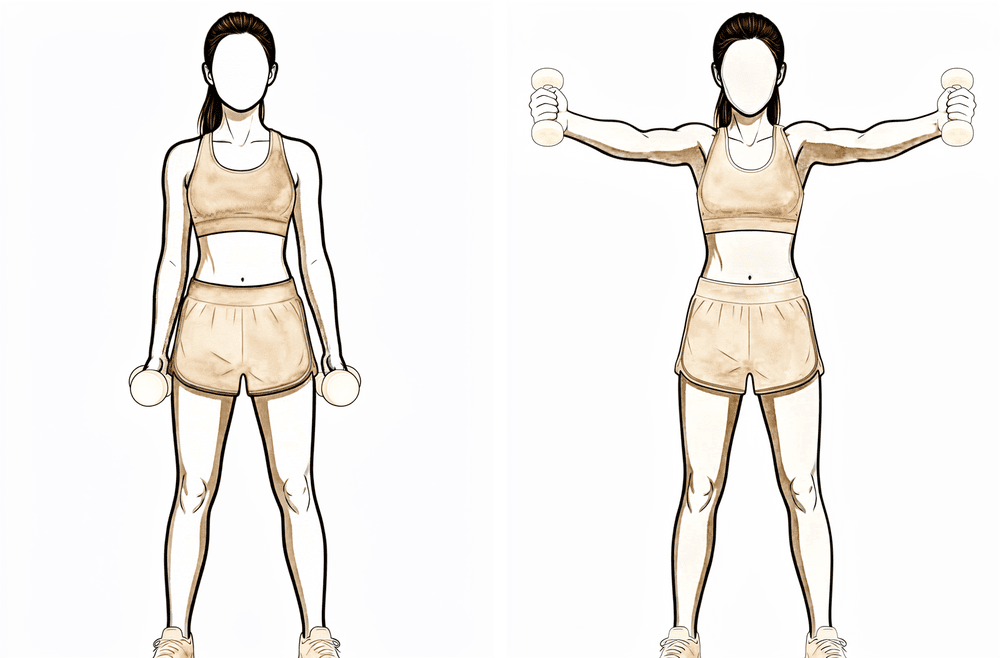
بھرا ڈبہ لفٹ (full-can)
تقریباً 12ویں ہفتے سے، جب آگے اٹھانا آرام دہ ہو جائے۔ اپنے بازو کو آگے اور تھوڑا سا پہلو کی طرف اٹھائیں اور انگوٹھا اوپر کی طرف رکھیں — یعنی "بھرا ڈبہ" پوزیشن — پھر قابو کے ساتھ نیچے لائیں۔ انگوٹھا نیچے کی طرف رکھ کر ("خالی ڈبہ") ہرگز نہ اٹھائیں۔
فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
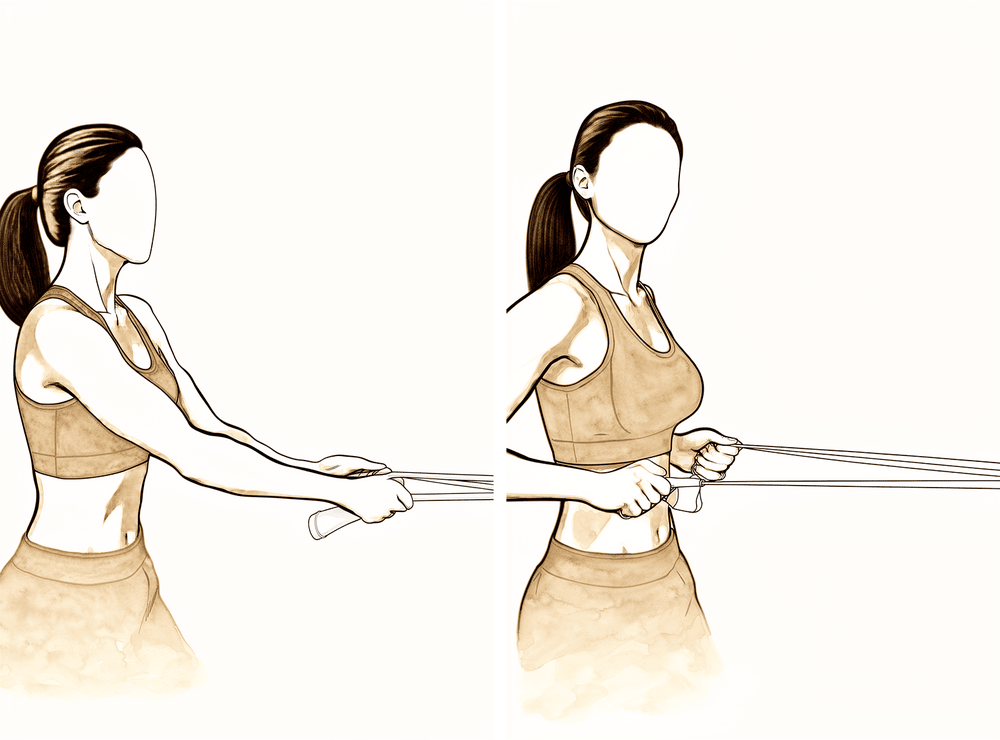
لو رو (کندھے کی پچھلی ہڈی کو جمانا)
تقریباً 12ویں ہفتے سے۔ اپنے پاس کسی مضبوط سطح پر ہاتھ رکھ کر، نیچے اور پیچھے کی طرف دبائیں تاکہ کندھے کی پچھلی ہڈی نیچے اور اندر کی طرف آئے، اور تھوڑی دیر روکیں۔ اس سے کندھے کی پچھلی ہڈی مستحکم ہوتی ہے (آپ کا فزیوتھراپسٹ اسے "انفیریئر گلائیڈ" (inferior glide) کہہ سکتا ہے)۔
فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
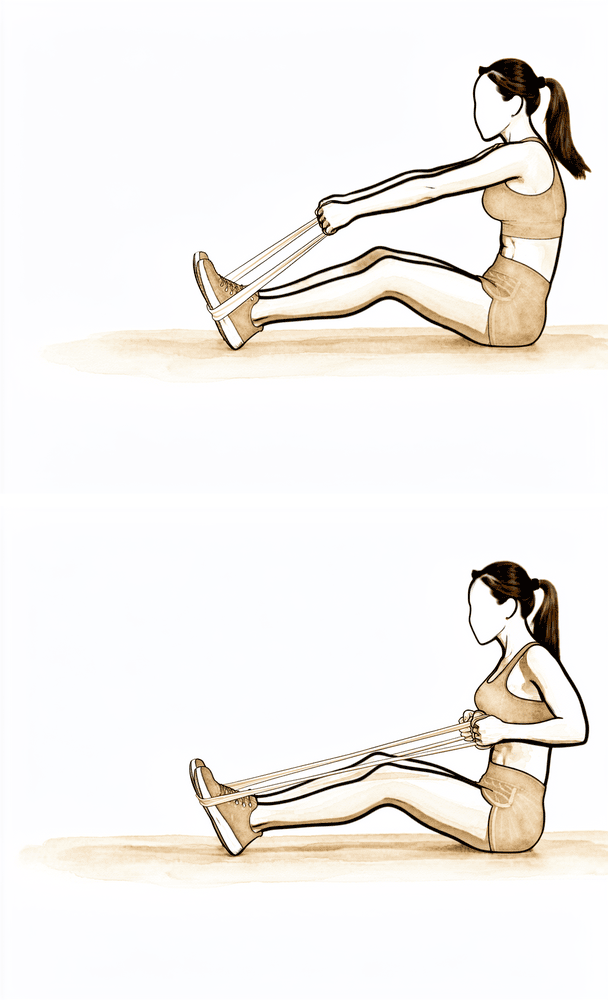
ربڑ بینڈ کے ساتھ رو (row)
تقریباً 12ویں ہفتے سے۔ اپنے سامنے باندھے گئے بینڈ کے ہینڈل اپنی طرف کھینچیں، کہنیوں کو پیچھے لے جائیں اور کندھے کی پچھلی ہڈیوں کو ایک دوسرے کی طرف دبائیں، پھر قابو کے ساتھ واپس لائیں۔ ہلکا بینڈ، زیادہ بار دہرانا؛ اگر کندھے میں درد ہونے لگے تو روک دیں۔
فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
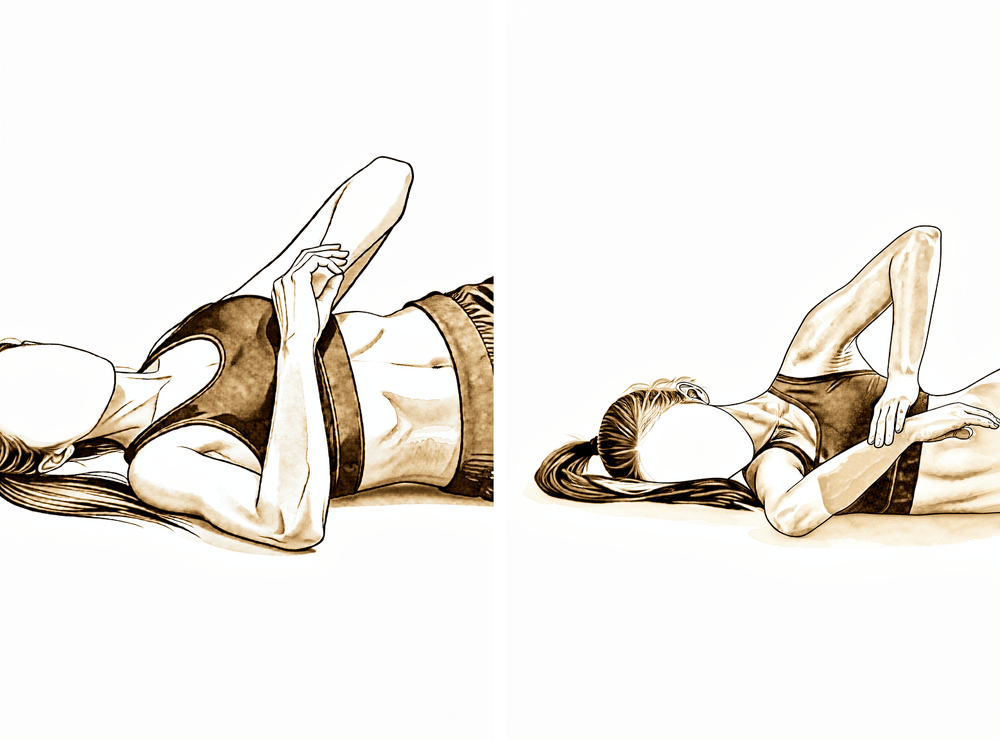
سلیپر اسٹریچ
تقریباً 12ویں ہفتے سے، اگر آپ کا فزیوتھراپسٹ ہدایت دے۔ آپریشن والی کروٹ پر لیٹ جائیں، بازو آگے اور کہنی مڑی ہوئی ہو۔ اوپر والے ہاتھ سے بازو کے نچلے حصے کو آہستگی سے بستر کی طرف نیچے دبائیں یہاں تک کہ کندھے کے پچھلے حصے میں آرام دہ کھنچاؤ محسوس ہو۔ صرف ہلکا — زور زبردستی نہ کریں۔
ہر بار 10 سے 20 سیکنڈ روکیں، چند مرتبہ، فزیوتھراپسٹ کی ہدایت کے مطابق
Kieran Hirpara 4.0
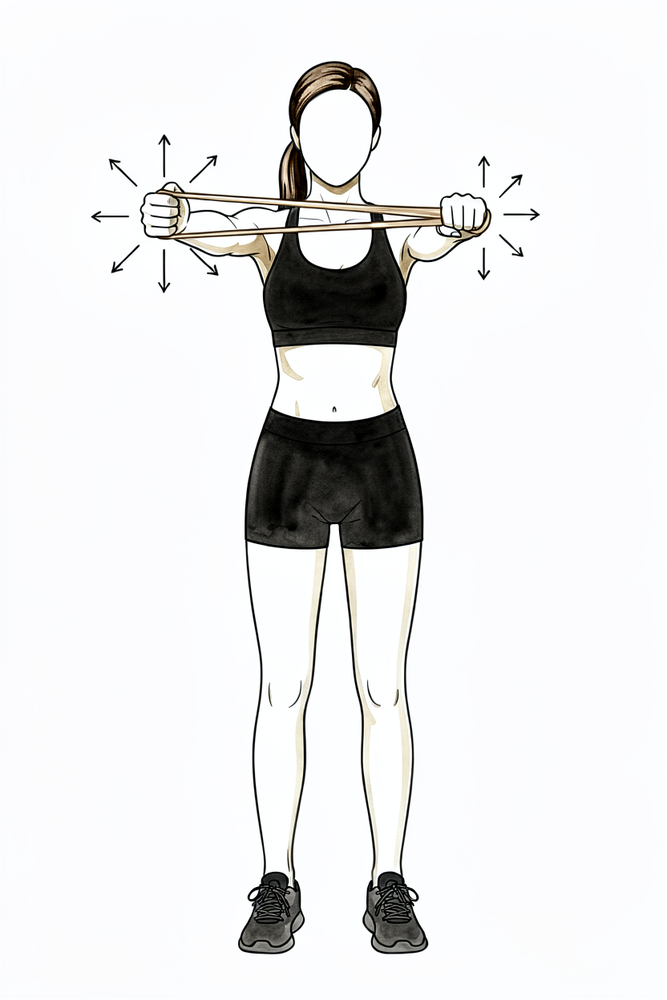
ردھمک اسٹیبلائزیشن
بازو کو اپنے سامنے تقریباً کندھے کی اونچائی پر سہارا دے کر رکھیں، اور اپنے فزیوتھراپسٹ سے (یا اپنے صحت مند ہاتھ سے) مختلف سمتوں سے چھوٹے، ہلکے دھکے لگوائیں جبکہ آپ بازو کو ساکت اور مستحکم رکھیں — اسے حرکت نہ کرنے دیں۔ اس سے کندھے کو مستحکم رکھنے والے پٹھے ردعمل دینا سیکھتے ہیں۔ تمام زور ہلکے رکھیں۔
فزیوتھراپسٹ کی ہدایت کے مطابق
یہ وہ مرحلہ ہے جب مرمت سب سے تیزی سے پختہ ہوتی ہے، اور توجہ حرکت واپس لانے سے ہٹ کر طاقت، برداشت اور قابو دوبارہ بنانے پر آ جاتی ہے۔ ہلکے ربڑ بینڈ اور ہلکے وزن کے ساتھ مزاحمت والا کام تقریباً 12ویں ہفتے سے شروع ہوتا ہے: زیادہ بار دہرانا، کم وزن۔ سنہری اصول ہے ایک وقت میں ایک سمت: آپ کسی سمت میں طاقت تب ہی بڑھائیں جب اس سمت میں آپ کی حرکت تقریباً پوری اور آرام دہ ہو۔ بازو ہمیشہ انگوٹھا اوپر رکھ کر اٹھائیں، کبھی انگوٹھا نیچے کر کے نہیں۔
- سلنگ: کوئی نہیں؛ پوری حرکت متوقع ہے۔
- ورزشیں: کندھے کی اونچائی پر بینڈ کے ساتھ باہر کی طرف گھمانا؛ چھڑی کے ساتھ اندر کی طرف گھمانا؛ "بھرا ڈبہ" (full-can) لفٹ؛ لو رو (low row)، یعنی کندھے کی پچھلی ہڈی کو جمانا؛ ربڑ بینڈ کے ساتھ رو (row)؛ سلیپر اسٹریچ (sleeper stretch)۔ آپ کا فزیوتھراپسٹ قابو دوبارہ سکھانے کے لیے ردھمک اسٹیبلائزیشن (rhythmic stabilisation) بھی شامل کر سکتا ہے (ہلکی ورزشیں جن میں وہ آپ کے بازو پر ہلکا دباؤ ڈالتے ہیں اور آپ بازو کو ساکت رکھ کر مزاحمت کرتے ہیں)؛ یہ ہاتھوں سے کرایا جانے والا کام ہے جس کا کوئی خاکہ نہیں دیا گیا۔
آپ اگلے مرحلے کے لیے تب تیار ہیں جب: آپ کو اپنے زور سے پوری اور درد کے بغیر حرکت حاصل ہو اور کندھے کی پچھلی ہڈی پر یکساں قابو ہو؛ طاقت کی ورزشوں کے بعد درد یا سوجن نہ ہو؛ کندھے کی پچھلی ہڈی کی سیدھ میں مزاحمت کے ساتھ بازو اٹھانا آرام دہ ہو؛ اور گھمانے کی طاقت دوسری طرف کے برابر پہنچ رہی ہو (ہلکی جانچ پر تقریباً 80 فیصد؛ پوری طاقت کی جانچ بہت بعد میں ہوتی ہے)۔
چھوٹے اور درمیانے پھٹاؤ — چوتھا مرحلہ: کھیل اور کام پر واپسی (16 سے 24 ہفتے)
Kieran Hirpara 4.0
ہلکے وزن کے ساتھ بھرا ڈبہ لفٹ
پہلے جیسی بھرا ڈبہ لفٹ، اب ہلکے وزن کے ساتھ، اور بوجھ آہستہ آہستہ بڑھائیں۔ انگوٹھا اوپر رکھیں۔ اگر کندھے میں درد ہو یا بعد میں سوجن ہو جائے تو روک دیں۔
فزیوتھراپسٹ کی ہدایت کے مطابق
یہ مرحلہ پوری طرح کام کرنے والے کندھے کی طرف واپسی کا پل ہے، اور اس کے بعد کھیل اور بھاری کام پر مرحلہ وار واپسی۔ آپ اپنی حاصل کردہ حرکت کی حد برقرار رکھتے ہیں اور اسے اعتماد سے استعمال کرنے کے لیے طاقت، زور اور برداشت بناتے ہیں: ہاتھ بڑھانا، چیزیں اٹھا کر لے جانا، سر سے اوپر کام کرنا۔ واپسی اچانک نہیں بلکہ مرحلہ وار ہوتی ہے؛ کھیل کے لیے، وقفوں والا پروگرام (interval programme) جو مقدار اور شدت کو قدم بہ قدم بڑھاتا ہے، واپسی کا سب سے محفوظ راستہ ہے۔
- سلنگ: کوئی نہیں۔
- ورزشیں: ہلکے اور آہستہ آہستہ بڑھتے وزن کے ساتھ "بھرا ڈبہ" لفٹ؛ کھیل اور کام کے مطابق جسمانی تیاری، بتدریج بڑھتا بوجھ، اور مرحلے کے آخر میں مناسب ہو تو قابو کے ساتھ تیز رفتار (پلائیومیٹرک) ورزشیں۔
آپ واپسی کے لیے تب تیار ہیں جب: آپ کے گھمانے کی طاقت دوسری طرف کی کم از کم 85 سے 90 فیصد ہو؛ آپ کو پوری، درد کے بغیر حرکت حاصل ہو اور زیادہ بوجھ پر ردعمل کے طور پر سوجن نہ ہو؛ اور آپ اپنے کھیل یا کام سے متعلق مخصوص ٹیسٹ پاس کر لیں۔ کھیل یا بھاری کام پر واپسی عموماً تقریباً 4 سے 6 ماہ میں ہوتی ہے، جو ان شرائط کو پورا کرنے اور ڈاکٹر ہِرپرا اور آپ کے فزیوتھراپسٹ کی اجازت پر منحصر ہے، صرف کیلنڈر پر نہیں۔
بڑے اور بہت بڑے پھٹاؤ
یہ راستہ بڑے پھٹاؤ کے لیے ہے (دو یا زیادہ ٹینڈن، یا ٹشو کی کمزور حالت)۔ مراحل وہی ہیں، لیکن بھرنے میں مدد کے لیے ہر مرحلہ زیادہ دیر تک رکھا جاتا ہے اور زیادہ احتیاط سے آگے بڑھایا جاتا ہے۔ کچھ سرجن اس گروپ میں باقاعدہ بحالی کا علاج جان بوجھ کر دیر سے شروع کرواتے ہیں؛ ڈاکٹر ہِرپرا آپ کو جو خاص ہدایت دیں اس پر عمل کریں۔ بڑے یا بہت بڑے پھٹاؤ میں بھی سلنگ سادہ سلنگ ہی ہوتی ہے، جس میں بازو کو جسم سے دور رکھنے والا تکیہ نہیں ہوتا۔
بڑے اور بہت بڑے پھٹاؤ — پہلا مرحلہ: حفاظت (0 سے 6 ہفتے)
Kieran Hirpara 4.0
پینڈولم کی طرح بازو جھلانا
آگے کی طرف جھکیں اور آپریشن والے بازو کو بالکل ڈھیلا چھوڑ کر نیچے لٹکنے دیں۔ اپنے جسم کو ہلا کر چھوٹے دائرے بنائیں، کندھے کے پٹھوں کو استعمال کر کے ہرگز نہیں۔ آپریشن والا بازو پورا وقت ڈھیلا رہتا ہے۔
ہر سمت میں 10 بار، دن میں 2 سے 3 مرتبہ
Kieran Hirpara 4.0
ہاتھ کھولنا اور بند کرنا
مضبوط مٹھی بنائیں، پھر ہاتھ پوری طرح کھول دیں۔ اس سے ہاتھ حرکت میں رہتا ہے اور سوجن کم ہوتی ہے۔
ہر گھنٹے 10 بار
Kieran Hirpara 4.0
کلائی کو خود موڑنا
اپنی کلائی کو آہستگی سے آگے، پھر پیچھے، اتنا موڑیں جتنا آرام سے ہو سکے۔
ہر گھنٹے 10 سے 15 بار
Kieran Hirpara 4.0
کہنی کو خود موڑنا
ہتھیلی اوپر رکھ کر اپنی کہنی کو آہستگی سے موڑیں، پھر سیدھا کریں، اور بازو کا اوپری حصہ اپنے پہلو سے لگا کر رکھیں۔
ہر بار 10 سے 15 مرتبہ، دن میں 2 سے 3 بار
Kieran Hirpara 4.0
کندھے کی پچھلی ہڈی کو جمانا
اپنے کندھے کی پچھلی ہڈیوں کو آہستگی سے نیچے اور ایک دوسرے کی طرف دبائیں، روکیں، پھر ڈھیلا چھوڑ دیں۔ آپ کا بازو حرکت نہیں کرتا۔
ہر بار 5 سیکنڈ روکیں، 5 مرتبہ، دن میں 2 سے 3 بار
یہ چھوٹے اور درمیانے پھٹاؤ والے راستے جیسا ہی ہے، لیکن حرکت کو سختی سے محفوظ رکھا جاتا ہے اور زیادہ آہستہ آگے بڑھایا جاتا ہے۔ آپ کا فزیوتھراپسٹ یا آپ کا صحت مند بازو آپ کے کندھے کو حرکت دیتا ہے؛ آپ ڈھیلے رہتے ہیں۔ اس گروپ میں بھرنے میں مدد کے لیے باقاعدہ بحالی کا علاج کبھی کبھی دیر سے شروع کیا جاتا ہے۔
- سلنگ: دن کے وقت سہارے کے لیے سادہ سلنگ؛ سلنگ اتار کر سوئیں؛ ورزشوں اور صفائی کے لیے اتار دیں۔
- اجازت شدہ حرکت: صرف محفوظ غیر فعال حرکت، اس حد تک جو ڈاکٹر ہِرپرا طے کریں؛ عام طور پر چھوٹے اور درمیانے پھٹاؤ والے راستے سے کم حد۔
- ورزشیں: پینڈولم کی طرح بازو جھلانا؛ ہدایت کے مطابق ہلکی، محفوظ، مدد سے حرکت؛ ہاتھ، کلائی اور کہنی کی حرکت؛ کندھے کی پچھلی ہڈی کو جمانا۔
آپ اگلے مرحلے کے لیے تب تیار ہیں جب: آپ کا درد قابو میں ہو؛ اس بات کی کوئی علامت نہ ہو کہ مرمت پر ضرورت سے زیادہ زور پڑا ہے؛ اور ڈاکٹر ہِرپرا آپ کو آگے بڑھنے کی اجازت دیں (اس گروپ میں ہر مریض کا منصوبہ الگ ہوتا ہے؛ صرف کیلنڈر دیکھ کر آگے نہ بڑھیں)۔
بڑے اور بہت بڑے پھٹاؤ — دوسرا مرحلہ: حرکت کی بحالی (6 سے 12 ہفتے)
تقریباً 6ویں ہفتے سلنگ اتر جاتی ہے، لیکن اپنے زور سے حرکت چھوٹے اور درمیانے راستے کے مقابلے میں بعد میں اور ہر مریض کے حساب سے الگ دوبارہ شروع کی جاتی ہے، تاکہ مرمت زیادہ دیر تک محفوظ رہے۔ کف پر مزاحمت والا کام جان بوجھ کر روک کر رکھا جاتا ہے۔
- سلنگ: تقریباً 6ویں ہفتے آہستہ آہستہ چھوڑ دی جاتی ہے۔
- اجازت شدہ حرکت: مدد سے حرکت، جو چھوٹے اور درمیانے راستے کے مقابلے میں بعد میں اپنے زور سے حرکت کی طرف بڑھتی ہے؛ صحیح وقت آپ کا فزیوتھراپسٹ آپ کے بھرنے کی رفتار کی بنیاد پر طے کرتا ہے۔
- ورزشیں: وہی ورزشیں جو چھوٹے اور درمیانے پھٹاؤ کے دوسرے مرحلے میں ہیں (لیٹ کر مدد سے بازو آگے اٹھانا، چھڑی کی مدد سے باہر کی طرف گھمانا، میز پر ہاتھ پھسلانا، دروازے پر لگی چرخی)، لیکن انہیں زیادہ آہستہ آگے بڑھایا جاتا ہے؛ کف پر مزاحمت والا کام مؤخر کیا جاتا ہے۔
آپ اگلے مرحلے کے لیے تب تیار ہیں جب: آپ کی اپنے زور سے حرکت مسلسل بہتر ہو رہی ہو؛ مدد سے یا غیر فعال حرکت پوری ہو؛ کندھے کی پچھلی ہڈی پر اچھا قابو ہو؛ اور آپ کی ٹیم مطمئن ہو کہ مرمت اتنی اچھی طرح بھر رہی ہے کہ بوجھ ڈالنا شروع کیا جا سکے۔
بڑے اور بہت بڑے پھٹاؤ — تیسرا مرحلہ: طاقت بڑھانا (تقریباً 16ویں ہفتے سے)
Kieran Hirpara 4.0
ردھمک اسٹیبلائزیشن
بازو کو اپنے سامنے تقریباً کندھے کی اونچائی پر سہارا دے کر رکھیں، اور اپنے فزیوتھراپسٹ سے (یا اپنے صحت مند ہاتھ سے) مختلف سمتوں سے چھوٹے، ہلکے دھکے لگوائیں جبکہ آپ بازو کو ساکت اور مستحکم رکھیں — اسے حرکت نہ کرنے دیں۔ اس سے کندھے کو مستحکم رکھنے والے پٹھے ردعمل دینا سیکھتے ہیں۔ تمام زور ہلکے رکھیں۔
فزیوتھراپسٹ کی ہدایت کے مطابق
طاقت بڑھانے کا کام 12ویں ہفتے کے بجائے تقریباً 16ویں ہفتے تک مؤخر کیا جاتا ہے، کیونکہ بڑی مرمت کو پختہ ہونے میں زیادہ وقت چاہیے۔ اس کے بعد طریقہ وہی ہے جو چھوٹے اور درمیانے پھٹاؤ کے طاقت والے مرحلے میں ہے: ہلکے بینڈ اور وزن، زیادہ بار دہرانا، کم بوجھ، ایک وقت میں ایک سمت، اور ہمیشہ انگوٹھا اوپر۔
- سلنگ: کوئی نہیں؛ پوری حرکت متوقع ہے۔
- ورزشیں: وہی جو چھوٹے اور درمیانے پھٹاؤ کے طاقت والے مرحلے میں ہیں (بینڈ کے ساتھ باہر کی طرف گھمانا، چھڑی کے ساتھ اندر کی طرف گھمانا، "بھرا ڈبہ" لفٹ، لو رو، بینڈ کے ساتھ رو، سلیپر اسٹریچ)، جو بعد میں شروع کی جاتی ہیں اور آہستہ آہستہ بڑھائی جاتی ہیں۔ قابو بہتر ہونے پر ردھمک اسٹیبلائزیشن (ہاتھوں سے کرائی جانے والی، بازو کو ساکت رکھنے کی ورزشیں) شامل کی جا سکتی ہے۔
آپ اگلے مرحلے کے لیے تب تیار ہیں جب: آپ کو اپنے زور سے پوری اور درد کے بغیر حرکت حاصل ہو؛ طاقت کی ورزشوں کے بعد درد یا سوجن نہ ہو؛ اور دوسری طرف کے مقابلے میں آپ کی طاقت یکساں طور پر بڑھ رہی ہو۔
بڑے اور بہت بڑے پھٹاؤ — چوتھا مرحلہ: کھیل اور کام پر واپسی (6 ماہ اور اس کے بعد)
بڑے اور بہت بڑے پھٹاؤ میں کھیل اور بھاری کام پر واپسی بعد میں ہوتی ہے، عموماً چھ ماہ یا اس سے زیادہ، اور اکثر اس سے بھی زیادہ، اور واپسی زیادہ آہستہ ہوتی ہے اور اس کی شرح بھی کم ہوتی ہے۔ آگے بڑھنے کا طریقہ وہی مرحلہ وار، شرائط پر مبنی ہے جو چھوٹے اور درمیانے راستے میں ہے۔
- سلنگ: کوئی نہیں۔
- ورزشیں: بتدریج بڑھتا بوجھ اور کھیل یا کام کے مطابق جسمانی تیاری، جو آہستہ آہستہ بڑھائی جائے۔
آپ واپسی کے لیے تب تیار ہیں جب: ڈاکٹر ہِرپرا اور آپ کا فزیوتھراپسٹ دونوں آپ کو اجازت دیں؛ آپ کے گھمانے کی طاقت دوسری طرف کی کم از کم 85 فیصد ہو؛ اور آپ کو پوری، درد کے بغیر حرکت اور برداشت حاصل ہو اور بوجھ پر ردعمل کے طور پر سوجن نہ ہو۔ چھ ماہ یا اس سے زیادہ کی توقع رکھیں (اکثر اس سے بھی زیادہ) اور فیصلہ کیلنڈر کے بجائے ان شرائط کو پورا کرنے کی بنیاد پر کریں۔
کھیل اور کام پر واپسی
ہر مرمت میں واپسی شرائط پر مبنی ہوتی ہے (درد کے بغیر، اور مناسب حرکت کی حد، طاقت اور برداشت کے ساتھ) اور اس کی منظوری ڈاکٹر ہِرپرا اور آپ کے فزیوتھراپسٹ دونوں دیتے ہیں؛ اس کا فیصلہ صرف کیلنڈر سے نہیں ہوتا۔
- چھوٹے اور درمیانے پھٹاؤ: بیٹھ کر کیا جانے والا کام چند ہفتوں میں؛ 12 سے 16 ہفتے سے زیادہ بھاری طاقت کی ورزشیں؛ تقریباً 4 سے 6 ماہ سے کھیل یا بھاری کام پر واپسی۔
- بڑے اور بہت بڑے پھٹاؤ: 6 ماہ یا اس سے زیادہ، اکثر اس سے بھی زیادہ، اور زیادہ آہستہ اور محتاط طریقے سے آگے بڑھنا۔
سر سے اوپر والے اور پھینکنے والے کھیلوں کے لیے، بغیر پابندی کے کھیلنے سے پہلے مرحلہ وار وقفوں والا پروگرام مکمل کریں۔ پوری (زیادہ سے زیادہ) طاقت کی جانچ سرجری کے 9 سے 12 ماہ بعد تک مؤخر کی جاتی ہے۔
آپ کی ابتدائی ورزشیں
یہ ابتدائی (حفاظتی) مرحلے کی ہلکی ورزشیں ہیں، جو وارڈ میں شروع ہوتی ہیں اور گھر پر جاری رہتی ہیں، اور انہیں آپریشن والے بازو کو سلنگ سے باہر نکال کر اور کندھے کے پٹھوں کو ڈھیلا رکھ کر کیا جاتا ہے۔ انہیں اپنے فزیوتھراپسٹ کی رہنمائی کے مطابق شروع کریں، اور جس چیز سے کندھے میں تیز درد ہو اسے روک دیں۔ یہ اوپر ہر راستے کے پہلے مرحلے میں دی گئی ہیں۔
پروٹوکول کے بعد
یہ پروٹوکول کلینک کی صحت یابی سے متعلق عمومی ہدایات کے ساتھ مل کر کام کرتا ہے؛ دیکھیں آپریشن کے بعد درد پر قابو اور زخم کی دیکھ بھال۔ خود آپریشن کے بارے میں جاننے کے لیے دیکھیں روٹیٹر کف کی مرمت۔
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Rotator Cuff Repair — Best-Evidence Rehabilitation Protocol
Scope: arthroscopic (and mini-open) rotator cuff repair (RCR). Two evidence sources combined: (1) local RAG corpus of 180,000+ Orthopaedic articles (citations below carry the journal/year), and (2) authoritative published institutional rehabilitation protocols (URLs below).
Each claim is flagged [STRONG] (RCT / meta-analysis / systematic review) or [CONSENSUS] (institutional protocol, narrative review, expert opinion) where relevant.
1. Consensus phased timeline (small/medium, "standard" 1–2 tendon repair)
Synthesised primarily from the Brigham & Women's Hospital (BWH) Arthroscopic RCR protocol and the BWH Standard of Care, cross-checked against the published institutional consensus. [CONSENSUS] for the exact week windows; [STRONG] that no specific week-by-week schedule is proven superior across all sizes (see controversies — Baumgarten 2009 Level I/II review; Chan 2014 meta-analysis).
| Phase | Weeks | Sling | ROM allowed | Active ROM | Strengthening | Precautions |
|---|---|---|---|---|---|---|
| I — Passive motion / protective ("healing") | 0–6 | Sling + small abduction cushion worn at all times, including sleep; remove only for exercise/icing/hygiene. Weaned wks 4–6. | PROM/AAROM only. Pendulums. Supine passive forward elevation to ~90–100°; passive ER (arm near side) to ~30°. Progress toward 120–140° FE / 30–60° ER by end of phase. | None. No active shoulder motion (tendon ~20% of normal strength at 4 wks). Active elbow/wrist/hand OK (curls only if biceps not involved). | Submaximal scapular + cuff setting; manual scapular work only. No resisted shoulder. | No active abduction/elevation; no pushing off with the arm for 6 wks. |
| II — Active-assisted -> active ROM | 6–12 | Discontinued (weaned wks 4–6). | Full PROM/AAROM to tolerance; supine->seated AAROM with cane/towel. | AAROM starts ~6 wks; AROM starts ~6–8 wks (gravity-eliminated -> upright). Goal >115° active FE before Phase III. | Begin light isotonic for deltoid, non-repaired cuff, scapula at ~10–12 wks (small tears); delayed to 16 wks for large/massive. | Avoid empty-can raises ever; no straight-arm lateral raises; light waist-level use only early. |
| III — Strengthening | 12–16 | None. | Should have full ROM with good stability. | Full active use for ADLs; return to full work + modified recreation. | Progressive cuff/scapular/deltoid strengthening; endurance/power. | <=5 lb lifting; no sudden jerk/push; thumb-up (full-can) raises only. |
| IV — Return to sport/work prep | 16–24 | None. | Maintain full ROM. | Sport/work-specific conditioning, plyometrics, progressive weight program. | Advanced/sport-specific strengthening. | <=10 lb until cleared; no painful progressions. |
| Return to sport / heavy work | >=4–6 months (often 6 mo; up to 12 mo for full recovery) | — | — | — | — | Surgeon + therapist clearance; pain-free, adequate ROM + endurance. |
Tendon-healing biology underpinning the schedule (BWH protocol): repair strength ~20% of normal at 4 wks, ~40% at 8 wks, ~60% at 12 wks, ~70% at 16 wks, ~80% at 32 wks — the rationale for no active motion before 6 wks and no strengthening before 12 wks. [CONSENSUS] (institutional, biologically grounded).
2. Small/medium vs large/massive tears (the key size distinction)
[STRONG] Tear size is the dominant modifier of healing/retear risk: weighted mean retear ~26.6% overall (Chamberlain/Namdari/Keener, What's New in Shoulder & Elbow Surgery, JBJS 2015), rising to ">90% in massive tears" (Hsu, Horneff, Gee, Immobilization After Rotator Cuff Repair, Orthop Clin North Am 2016). Retear correlates with larger tear size, advanced age, fatty infiltration.
| Variable | Small / medium (<3 cm, 1–2 tendons, good tissue) | Large / massive (>3–5 cm, >=2 tendons, poor tissue) |
|---|---|---|
| Sling/immobilizer duration | 4–6 wks | 6 wks (commonly), abduction pillow; some delay PT to 6 wks to protect healing |
| PT start | within first 6 wks | may be delayed up to 6 wks to promote healing (BWH hybrid protocol) |
| Active ROM start | ~6–8 wks | later, individualised; protect repair longer |
| Strengthening start | ~10–12 wks | delayed to ~16 wks |
| Return to sport/heavy work | 4–6 months | >=6 months, frequently longer; lower/slower return |
[STRONG] Review of online RCR protocols (Coda et al., Arthrosc Sports Med Rehabil 2020): for large/massive tears, sling/immobilizer use ranged 4–10 wks, with the plurality (~55%) at 6 wks. [STRONG] Substantial between-protocol variability exists (Galetta et al., J Shoulder Elbow Surg 2021, ACGME-program protocol survey; Coda 2020) — i.e., no single validated schedule; size-stratification is consensus-driven.
Return-to-work pooled data: [STRONG] Haunschild et al. (Am J Sports Med 2021) systematic review/meta-analysis quantifies return-to-work after primary RCR (timeline varies with job demand; heavy-labor return slower).
3. KEY CONTROVERSY — Early vs Delayed (immobilization) passive motion after arthroscopic RCR
This is the central evidence debate. Two competing concerns: early PROM reduces post-op stiffness; delayed/immobilization may protect tendon-to-bone healing (reduce retear), especially in larger tears.
Evidence FOR early passive motion (less stiffness, no proven healing penalty in small/medium)
- [STRONG] Keener et al. RCT — early vs delayed passive motion after arthroscopic repair of full-thickness tears, 114 patients, small-to-medium tears (cited in Braman/Neviaser/Parsons, What's New in Shoulder and Elbow Surgery, JBJS 2014): the landmark RCT in this debate; early motion improved early ROM without a clear healing penalty in this size class.
- [STRONG] Mazzocca et al. RCT (Arthroscopy 2017): no difference between delayed and early motion in WORC scores, clinical outcomes, or structural failure at 6 months; both protocols equivalent on patient-reported outcomes.
- [STRONG] Saltzman et al. (J Shoulder Elbow Surg 2017) — systematic review of overlapping meta-analyses: early-motion protocols may give superior early ROM; differences trend toward equivalence by ~1 year.
- [STRONG] Li et al. meta-analysis (Medicine 2018): early passive motion (EPM) gives superior ROM recovery, with the caveat below.
Evidence FOR delayed motion / immobilization (protect healing, lower retear in larger tears)
- [STRONG] Chan et al. meta-analysis (J Shoulder Elbow Surg 2014): documents the shift toward delaying motion over healing concerns; early motion improves ROM but raises healing-integrity questions.
- [STRONG] Li et al. meta-analysis (Medicine 2018): EPM "may adversely affect shoulder function" and "might result in lower rates of tendon healing in large-sized tears" — i.e., the early-motion benefit is size-dependent and may cost healing in big tears.
- [STRONG] Gallagher et al. systematic review (Phys Sportsmed 2015): early aggressive rehab may compromise repair integrity; conclusions size/quality dependent.
- [STRONG] Stillson et al. (J Am Acad Orthop Surg 2022, large Medicare cohort): strong association between starting PT within 1 week post-op and increased revision/revision-surgery rates — the largest study to date on rehab timing; cautions against very early aggressive therapy.
- Supporting basic-science: delayed early passive motion was harmless to cuff healing in animal models (rabbit model cited in Thigpen/Shaffer/Kissenberth, Clin Sports Med 2015, "Knowing the Speed Limit").
Current consensus
[STRONG/CONSENSUS] The meta-analytic bottom line (Mazzocca 2017 RCT; Saltzman 2017; Chan 2014): for small-to-medium tears, early and delayed PROM converge by ~6–12 months — timing is largely surgeon preference and does not change final outcome, so either is defensible. For large/massive tears (and poor tissue), the balance tips toward a delayed / protected approach to favor healing and lower retear (Li 2018; Hsu 2016), and very early (<1 wk) aggressive PT should be avoided (Stillson 2022). This is exactly the size-stratified pattern the BWH protocol encodes (delay PT/strengthening for large/massive). Note Cochrane-level certainty remains low — no protocol is proven superior on patient-important outcomes (Baumgarten 2009 Level I/II review found insufficient evidence for a single optimal protocol).
4. Practice shift to flag
- Historical default = early passive motion (minimize stiffness). Over the last decade the field moved toward delaying/protecting motion in larger tears on healing grounds (Chan 2014; Li 2018), then partially back toward equipoise for small/medium tears as RCTs/meta-analyses showed equivalent final outcomes (Mazzocca 2017; Saltzman 2017).
- Newest signal: avoid ultra-early (<1 week) PT regardless — associated with higher revision rates (Stillson 2022, Medicare cohort). Net current practice = size-stratified: standard 6-wk sling + passive-only phase, active ROM ~6–8 wks, strengthening ~12 wks for small/medium and ~16 wks for large/massive, RTS 4–6+ months.
CITATIONS
RAG corpus articles (title / journal / year)
- Keener et al. — early vs delayed passive motion after arthroscopic full-thickness RCR (small–medium, n=114). Cited in Braman J, Neviaser A, Parsons B. What's New in Shoulder and Elbow Surgery. J Bone Joint Surg. 2014;96(20). [STRONG — RCT]
- Mazzocca AD, Arciero RA, Shea KP, et al. The Effect of Early Range of Motion on Quality of Life, Clinical Outcome, and Repair Integrity After Arthroscopic Rotator Cuff Repair. Arthroscopy. 2017;33(6). [STRONG — RCT]
- Chan K, MacDermid JC, Hoppe DJ, et al. Delayed versus early motion after arthroscopic rotator cuff repair: a meta-analysis. J Shoulder Elbow Surg. 2014. [STRONG — meta-analysis]
- Saltzman BM, Zuke WA, Go B, et al. Does early motion lead to a higher failure rate or better outcomes after arthroscopic rotator cuff repair? A systematic review of overlapping meta-analyses. J Shoulder Elbow Surg. 2017;26(9):1681-1691. [STRONG]
- Li S, Sun H, Luo X, et al. The clinical effect of rehabilitation following arthroscopic rotator cuff repair (meta-analysis). Medicine. 2018. [STRONG — meta-analysis]
- Gallagher BP, Bishop ME, Tjoumakaris FP, et al. Early versus delayed rehabilitation following arthroscopic rotator cuff repair: A systematic review. Phys Sportsmed. 2015. [STRONG]
- Stillson QA, Sun JQ, Maninang M, et al. Effect of Physical Therapy and Rehabilitation Timing on Rotator Cuff Repair Revisions and Capsulitis. J Am Acad Orthop Surg. 2022 (large Medicare cohort). [STRONG]
- Baumgarten KM, Vidal AF, Wright RW. Rotator Cuff Repair Rehabilitation: A Level I and II Systematic Review. Sports Health. 2009 (insufficient evidence for a single optimal protocol). [STRONG]
- Parsons BO, Gruson KI, Chen DD, et al. Does slower rehabilitation after arthroscopic rotator cuff repair lead to long-term stiffness? J Shoulder Elbow Surg. 2010;19(7):1034-1039. [moderate]
- Thigpen CA, Shaffer MA, Kissenberth MJ. Knowing the Speed Limit. Clin Sports Med. 2015. [CONSENSUS/review]
- Chamberlain AM, Namdari S, Keener JD. What's New in Shoulder and Elbow Surgery? J Bone Joint Surg. 2015;97(20) (retear ~26.6%; predictors). [STRONG — pooled]
- Hsu JE, Horneff JG, Gee AO. Immobilization After Rotator Cuff Repair. Orthop Clin North Am. 2016 (retear up to >90% massive). [CONSENSUS/review]
- Coda RG, Cheema SG, Hermanns CA, et al. A Review of Online Rehabilitation Protocols Designated for Rotator Cuff Repairs. Arthrosc Sports Med Rehabil. 2020;2(3) (sling 4–10 wks; ~55% at 6 wks for large/massive). [STRONG — protocol systematic review]
- Galetta MD, Keller RE, Sabbag OD, et al. Rehabilitation variability after rotator cuff repair. J Shoulder Elbow Surg. 2021;30(6) (ACGME program protocol variability). [STRONG]
- Haunschild ED, Gilat R, Lavoie-Gagne O, et al. Return to Work After Primary Rotator Cuff Repair: A Systematic Review and Meta-analysis. Am J Sports Med. 2021. [STRONG]
Published institutional protocols (URLs)
- Brigham & Women's Hospital — Arthroscopic Rotator Cuff Repair Protocol (hybrid patient/therapist; full phased timeline, tear-size stratification): https://www.brighamandwomens.org/assets/BWH/patients-and-families/rehabilitation-services/pdfs/shoulder-arthroscopic-rct-repair-protocol-hybrid-patient-therapist.pdf
- Brigham & Women's Hospital — Standard of Care: Arthroscopic repair of a rotator cuff tear (small/medium/large-massive protocol families; literature review): https://www.brighamandwomens.org/assets/BWH/patients-and-families/rehabilitation-services/pdfs/shoulder-rotator-cuff-repair-arthroscopic.pdf
Overall evidence grade: the biology-based phase structure is [CONSENSUS] (well-aligned across institutions). The early-vs-delayed motion question is supported by multiple [STRONG] RCTs and meta-analyses, which converge on equivalence for small/medium tears and a protect-healing tilt for large/massive — but Cochrane-level certainty for any single optimal schedule remains LOW.