Patients › Rehabilitation
ڈی کویروین ریلیز
ڈی کویروین ٹینوسائنووائٹس (de Quervain's tenosynovitis، کلائی کی انگوٹھے والی طرف ٹینڈنوں کی سوزش) کے لیے کلائی کی پشت کے پہلے خانے (first dorsal compartment) کو آپریشن سے کھولنے کے بعد جلد حرکت والا صحت یابی کا منصوبہ، جس میں مختصر مدت کے لیے آرام کا سہارا، اکڑاؤ سے بچنے کے لیے شروع سے انگوٹھے اور کلائی کی ہلکی حرکت، زخم کے نشان کی دیکھ بھال، اور تقریباً چار سے چھ ہفتوں تک گرفت اور چٹکی کی طاقت کی بتدریج بحالی شامل ہے۔

یہ پروٹوکول ڈی کویروین ریلیز (de Quervain's release) کے بعد آپ کی صحت یابی میں رہنمائی کرتا ہے۔ یہ ایک چھوٹا آپریشن ہے جس میں آپ کی کلائی کی انگوٹھے والی طرف کے ٹینڈنوں (tendons)، یعنی ان مضبوط ڈوریوں جو پٹھے کو ہڈی سے جوڑتی ہیں، کے اوپر موجود تنگ سرنگ کو کھولا جاتا ہے، اور یہ صحت یابی ڈاکٹر کیرن ہِرپرا کے ساتھ Mater Private Hospital Rockhampton میں ہوتی ہے۔ یہ صفحہ گھر پر کی جانے والی ورزشوں کے پروگرام سے شروع ہوتا ہے، جس کے بعد وہ باقاعدہ طبی پروٹوکول ہے جو آپ کے ہینڈ تھراپسٹ (ہاتھ کی بحالی کے ماہر) کے لیے لکھا گیا ہے؛ تھراپی کی اپنی پہلی ملاقات پر یہ صفحہ یا اس کی پی ڈی ایف ساتھ لائیں تاکہ آپ کی بحالی میں سب ایک ساتھ رہیں۔ آپ کا ہینڈ تھراپسٹ آپ کی صحت یابی کی پیش رفت کے مطابق منصوبے میں تبدیلی کر سکتا ہے۔
اگر آپریشن کے بعد آپ کو اپنے زخم کے بارے میں کوئی تشویش ہو تو کلینک سے رابطہ کریں۔ اکثر یہ مددگار ہوتا ہے کہ زخم کی تصویر لے کر جائزے کے لیے ای میل کر دیں۔
کیا توقع رکھیں
ڈی کویروین ٹینوسائنووائٹس (de Quervain's tenosynovitis، کلائی کی انگوٹھے والی طرف ٹینڈنوں کی سوزش) ان دو ٹینڈنوں میں جلن (irritation) ہے جو آپ کے انگوٹھے تک جاتے ہیں (abductor pollicis longus اور extensor pollicis brevis)، اس جگہ جہاں وہ کلائی کی انگوٹھے والی طرف ایک تنگ سرنگ (کلائی کی پشت کا پہلا خانہ، first dorsal compartment) سے گزرتے ہیں۔ ریلیز ایک چھوٹا آپریشن ہے جو اس سرنگ کو کھول دیتا ہے تاکہ ٹینڈنوں کو آزادی سے پھسلنے کی جگہ مل جائے، اور اس سے درد اور ٹینڈن کا اٹکنا ٹھیک ہو جاتا ہے۔
چونکہ کسی چیز کو ٹانکوں سے دوبارہ جوڑا یا کسا نہیں جاتا (سرنگ کو صرف کھولا جاتا ہے اور اسے کھلا ہی رہنا ہوتا ہے)، اس لیے یہ جلد حرکت شروع کرنے والی صحت یابی ہے، طویل حفاظت والی نہیں۔ یہاں کوئی ایسی مرمت نہیں جسے بھرنے کے لیے مہینوں درکار ہوں۔ بحالی کا پورا مقصد یہ ہے کہ ٹینڈن آپریشن کی بھرتی ہوئی جگہ میں حرکت کرتے رہیں تاکہ وہ وہاں چپک نہ جائیں، جبکہ چھوٹا زخم اور اس کے اوپر جلد کے اعصاب (nerves) پرسکون ہو جائیں۔
اس لیے منصوبہ سادہ ہے: پہلے چند دنوں سے لے کر تقریباً ایک یا دو ہفتے تک نرم پٹی (کبھی کبھی صرف آرام کے لیے انگوٹھے کا ہلکا اسپلنٹ)، انگوٹھے اور کلائی کی ہلکی حرکت جلد شروع کرنا، زخم بھر جانے کے بعد زخم کے نشان کی دیکھ بھال، اور گرفت اور چٹکی کی طاقت کو بتدریج بڑھانا۔ زیادہ تر لوگ تقریباً چار سے چھ ہفتوں تک آرام سے معمول کی سرگرمیوں پر واپس آ جاتے ہیں۔
اس خاص آپریشن کے بعد دو چیزوں پر نظر رکھی جاتی ہے۔ پہلی جلد کا ایک چھوٹا عصب ہے، یعنی ریڈیل عصب کی حسی شاخ (radial sensory nerve)، جس کی شاخیں آپریشن کی جگہ کے عین سامنے سے آر پار گزرتی ہیں؛ اس میں کچھ عرصے تک جھنجھناہٹ یا چھونے پر درد رہ سکتا ہے، اور عصب کو پرسکون کرنے کا ابتدائی کام اسی کے لیے ہے۔ دوسری چیز ٹینڈنوں کی جگہ ہے: اگر سرنگ ہتھیلی کی طرف بہت زیادہ کھل جائے تو کبھی کبھار انگوٹھا حرکت دینے پر کوئی ٹینڈن آگے کی طرف کھسک سکتا ہے (subluxate)۔ دونوں غیر معمولی ہیں، اور آپ کا ہینڈ تھراپسٹ ان پر نظر رکھے گا۔
احتیاطیں اور پابندیاں
- شروع سے ہی انگوٹھے اور کلائی کو حرکت دیتے رہیں: یہاں علاج ہلکی حرکت ہے، آرام نہیں۔ بہت کم حرکت کرنے سے پیدا ہونے والا اکڑاؤ ہی وہ اصل چیز ہے جس سے ہم بچنا چاہتے ہیں۔
- آرام کے لیے دیا گیا کوئی بھی اسپلنٹ صرف ہدایت کے مطابق اور صرف پہلے چند دنوں سے ایک یا دو ہفتے تک استعمال کریں: یہ آرام کے لیے ہے، حفاظت کے لیے نہیں، اور ورزشوں کے لیے اسے اتار دینا چاہیے۔
- زخم بھرنے تک اسے صاف اور خشک رکھیں؛ جب تک پٹیاں اتر نہ جائیں اور جلد بند نہ ہو جائے، زخم کے نشان کی مالش شروع نہ کریں۔
- تقریباً تین سے چار ہفتے تک بھاری گرفت، زور سے چٹکی بھرنے، وزن اٹھانے اور مروڑنے (کپڑا نچوڑنا، سخت بند مرتبان کھولنا، بھاری اوزار) سے پرہیز کریں، پھر آہستہ آہستہ دوبارہ بڑھائیں۔
- اگر آپ کو انگوٹھے اور کلائی کی پشت پر جھنجھناہٹ، سُن پن یا تیز، بجلی کی طرح دوڑتا ہوا احساس محسوس ہو، یا انگوٹھا حرکت دینے پر کوئی ٹینڈن جھٹکے سے اچھلے یا کھسکے، تو اپنے تھراپسٹ یا کلینک کو بتائیں۔
زخم، سوجن اور زخم کے نشان کی دیکھ بھال کے لیے کلینک کی زخم کی دیکھ بھال سے متعلق رہنمائی دیکھیں۔
آپ کی ورزشیں
Kieran Hirpara 4.0
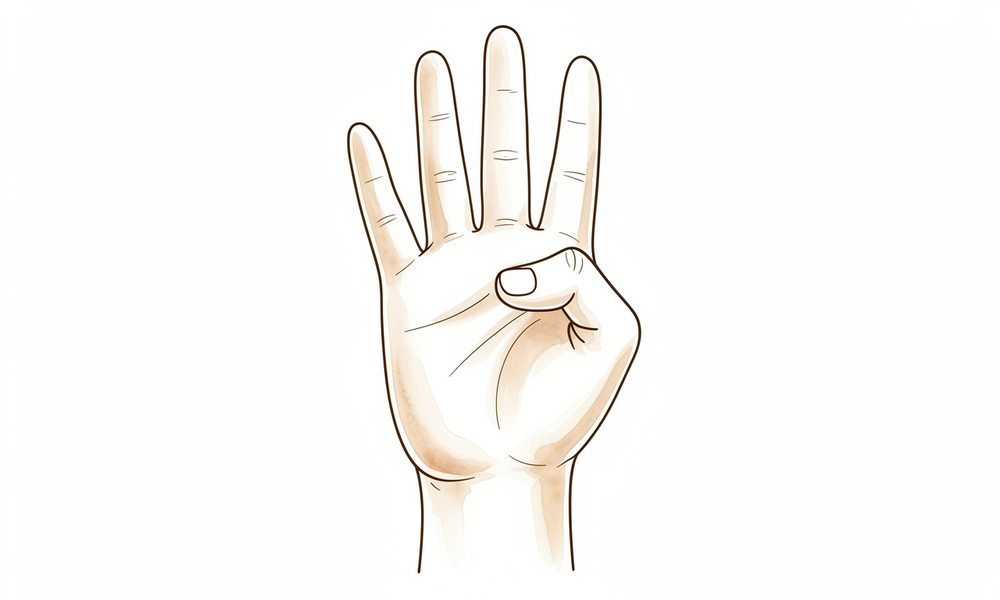
انگوٹھے کی حرکت (موڑنا، سیدھا کرنا اور ہتھیلی کے پار لے جانا)
اپنے انگوٹھے کو آہستگی سے اس کی پوری حد تک حرکت دیں: اس کا سرا ہتھیلی کی طرف نیچے موڑیں، اسے سیدھا کریں، پھر پورے انگوٹھے کو ہتھیلی کے پار لے جا کر چھوٹی انگلی کی جڑ کو چھوئیں اور پھر واپس باہر کی طرف پورا کھول دیں۔ حرکت آہستہ اور آرام دہ رکھیں۔ انگوٹھے کی جلد حرکت کھولے گئے ٹینڈنوں کو پھسلتا رکھتی ہے تاکہ وہ بھرتے ہوئے زخم کے نشان میں چپک نہ جائیں۔
ہر حرکت 10 بار، دن میں 3 سے 4 بار، آرام کی حد میں
Kieran Hirpara 4.0
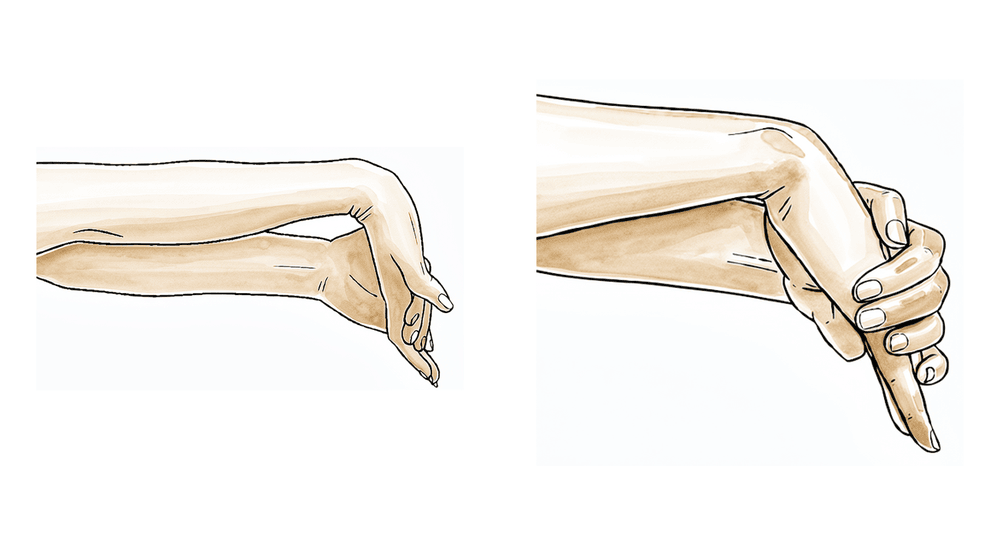
کلائی کی حرکت (اوپر، نیچے اور دائیں بائیں)
بازو کے نچلے حصے کو میز پر ٹکا کر کلائی کو آہستگی سے اوپر اور نیچے موڑیں، پھر اسے دائیں بائیں جھکائیں (پہلے انگوٹھے کی طرف، پھر چھوٹی انگلی کی طرف)۔ صرف اتنا حرکت دیں جتنا آرام دہ ہو۔ اس سے زخم ٹھیک ہونے کے دوران کلائی لچکدار رہتی ہے۔
ہر سمت میں 10 بار، دن میں 3 سے 4 بار
Kieran Hirpara 4.0
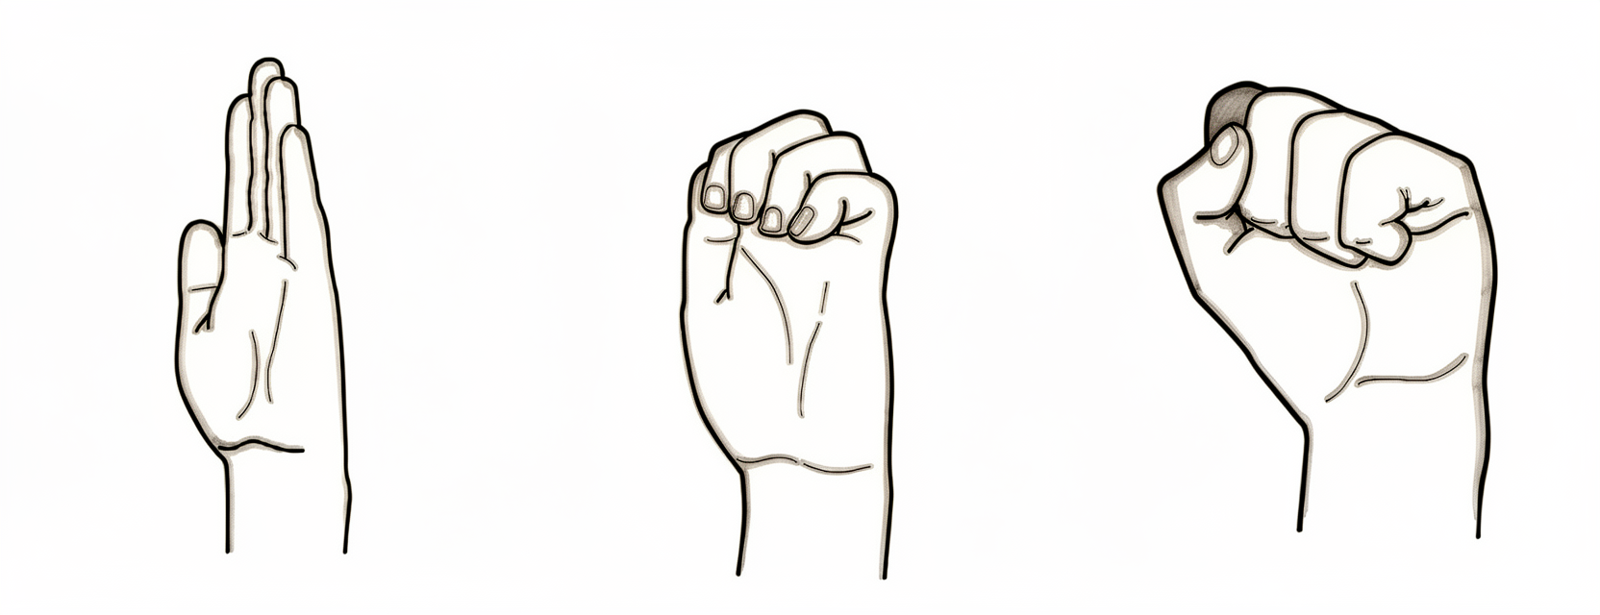
ٹینڈن گلائیڈز (انگوٹھے اور انگلیوں کو پھسلانے کی ورزش)
اپنا ہاتھ پورا کھولیں، پھر انگوٹھے کو پھسلا کر باری باری ہر انگلی کے سرے کو چھوئیں، پھر ڈھیلی مٹھی بنائیں اور دوبارہ کھول دیں۔ مقصد ہموار پھسلن ہے، زور نہیں۔ ابتدائی ہفتوں میں اکڑاؤ اور چپکنے (adhesions) سے بچنے کے لیے سب سے اہم کام یہی ہے کہ ٹینڈن کھولی گئی سرنگ میں حرکت کرتے رہیں۔
5 سے 10 آہستہ چکر، دن میں 3 سے 4 بار
Kieran Hirpara 4.0
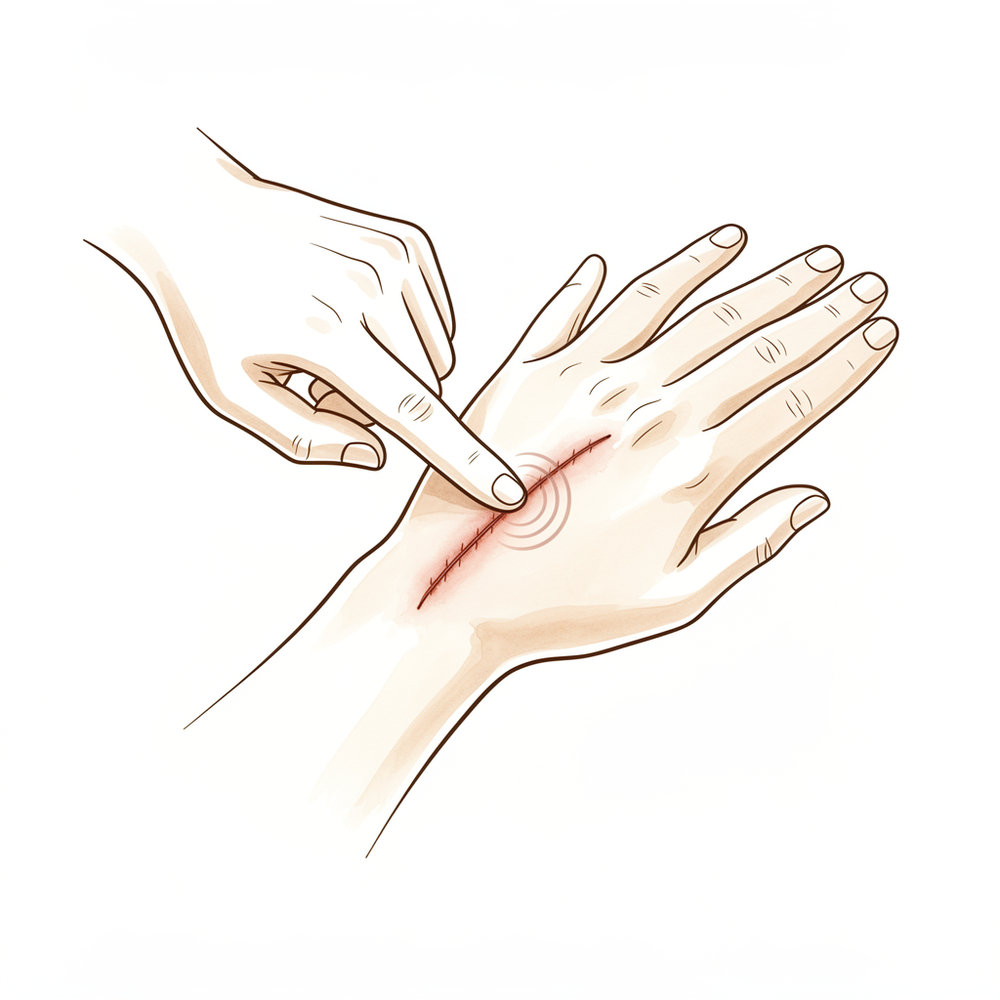
زخم کے نشان کی مالش
جب زخم پوری طرح بھر جائے اور پٹیاں اتر جائیں (عموماً تقریباً دو ہفتے سے)، تو زخم کے نشان پر تھوڑا سا سادہ موئسچرائزر لگا کر ایک یا دو منٹ چھوٹے دائروں میں دبا کر ملیں۔ اس سے زخم کا نشان نرم ہوتا ہے اور جلد اور اس کے نیچے عصب کی ان شاخوں کو پرسکون ہونے میں مدد ملتی ہے جن میں چھونے پر درد ہوتا ہے۔ اگر وہ جگہ ابھی کھلی ہو یا اس سے رطوبت رس رہی ہو تو مالش روک دیں۔
1 سے 2 منٹ، دن میں 2 سے 3 بار، زخم بھر جانے کے بعد
Kieran Hirpara 4.0
گرفت اور چٹکی کی طاقت بڑھانا
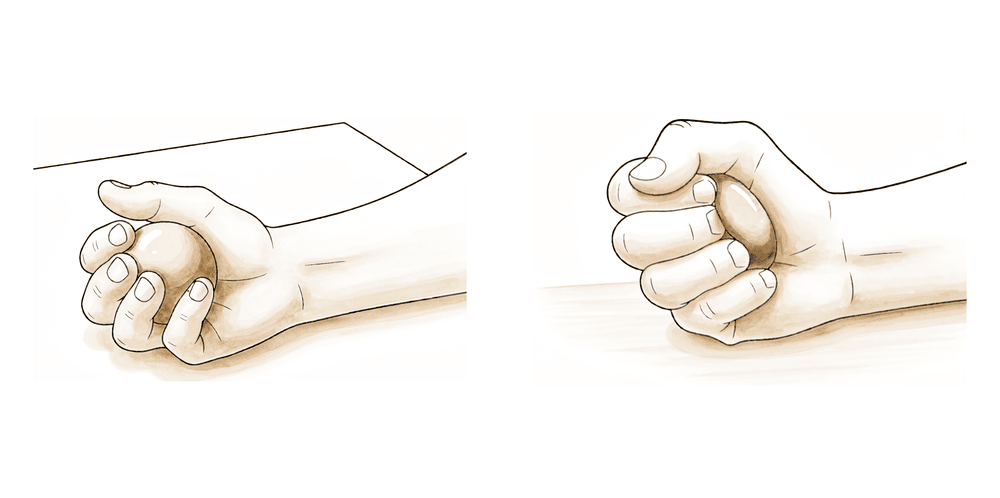
یہ بعد میں کی جانے والی ورزش ہے — عموماً تقریباً تین سے چار ہفتے سے، جب زخم بھر چکا ہو اور حرکت آرام دہ ہو۔ گرفت کے لیے ایک نرم گیند یا تھراپی پُٹی (putty) دبائیں، اور چٹکی کے لیے پُٹی کا ایک چھوٹا ٹکڑا انگوٹھے اور انگلیوں کے سروں کے درمیان دبائیں۔ زور آہستہ آہستہ بڑھائیں۔ اس سے وہ طاقت دوبارہ بنتی ہے جو سرجری کے بعد ہمیشہ کچھ کم ہو جاتی ہے۔
10 سے 15 بار دبانا/چٹکی بھرنا، دن میں 2 سے 3 بار (تقریباً 3 سے 4 ہفتے سے)
Kieran Hirpara 4.0
ریڈیل عصب کی گلائیڈ (اگر کلائی کی پشت میں جھنجھناہٹ ہو یا چھونے پر درد ہو)
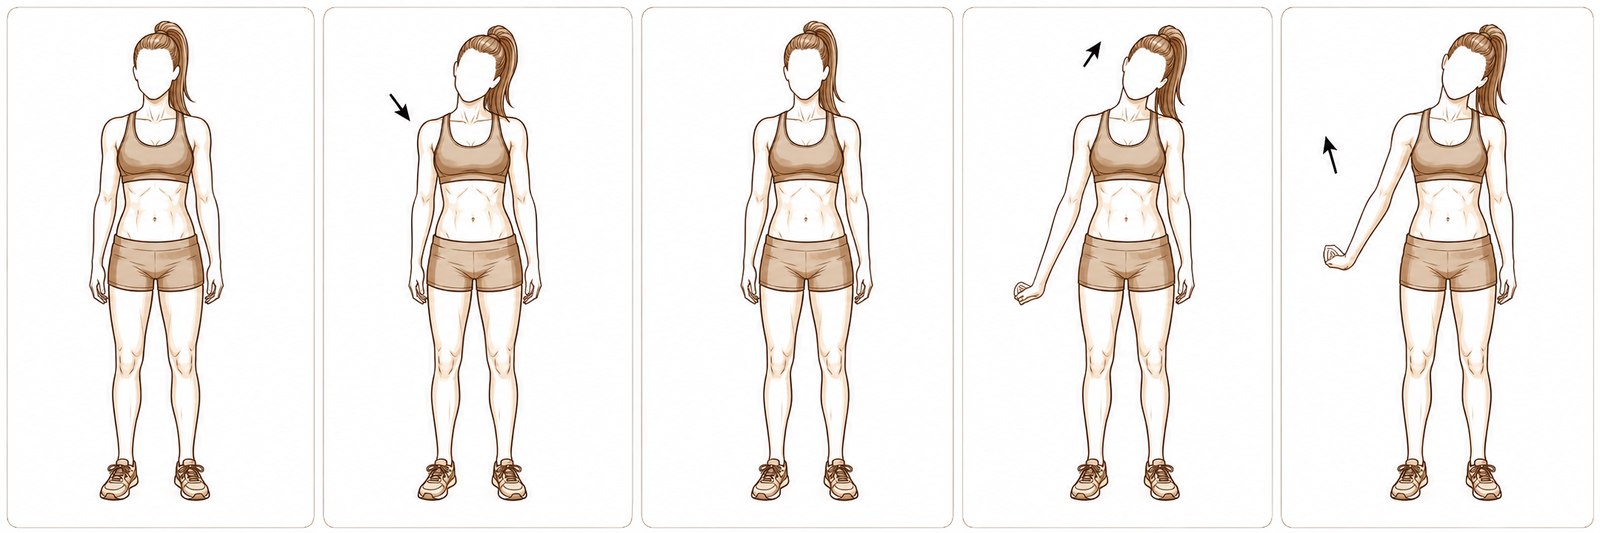
یہ صرف اس صورت میں کریں جب آپ کا ہینڈ تھراپسٹ اسے شروع کرائے — انگوٹھے اور کلائی کی پشت پر جھنجھناہٹ، چھونے پر درد یا حساسیت کے لیے۔ بازو سامنے کی طرف رکھ کر کلائی اور انگوٹھے کو آہستگی سے نیچے کی طرف ہلکے کھنچاؤ میں لائیں یہاں تک کہ آپ کو ہلکا سا کھنچاؤ محسوس ہو، ایک لمحہ رکیں، پھر چھوڑ دیں۔ اس سے کبھی درد نہیں ہونا چاہیے اور نہ ہی جھنجھناہٹ بڑھنی چاہیے۔ اس سے جلد کا وہ چھوٹا عصب پرسکون ہوتا ہے جو آپریشن کی جگہ کے عین اوپر سے گزرتا ہے۔
5 سے 10 آہستہ گلائیڈز، دن میں 1 سے 2 بار، صرف رہنمائی کے مطابق
یہ آپ کو دیے گئے ورزشوں کے پرچے کی ورزشیں ہیں۔ انہیں ڈاکٹر ہِرپرا اور اپنے ہینڈ تھراپسٹ کی رہنمائی کے مطابق شروع کریں۔ ابتدائی ورزشیں (انگوٹھے کی حرکت، کلائی کی حرکت اور ٹینڈن گلائیڈز یعنی ٹینڈنوں کو پھسلانے والی ورزشیں) ہر چیز کو حرکت میں رکھتی اور پھسلاتی ہیں تاکہ کھولے گئے ٹینڈن چپک نہ جائیں؛ یہ پہلے چند دنوں کے اندر، آرام کی حد میں شروع ہوتی ہیں۔ زخم کے نشان کی مالش زخم بھرنے کے بعد شروع ہوتی ہے۔ گرفت اور چٹکی کی طاقت بڑھانے کی ورزش بعد میں شامل کی جاتی ہے، عموماً تقریباً تین سے چار ہفتے سے۔ عصب کی گلائیڈ (nerve glide) صرف اس صورت میں شامل کی جاتی ہے جب کلائی کے اوپر کی جلد میں جھنجھناہٹ ہو یا چھونے پر درد ہو۔ جو بھی ورزش کلائی کی انگوٹھے والی طرف تیز یا بجلی کی طرح دوڑتا ہوا درد پیدا کرے، اسے روک دیں۔
آپ کا طبی پروٹوکول
اس صفحے کا باقی حصہ ڈی کویروین (کلائی کی پشت کے پہلے خانے، first dorsal compartment) ریلیز کے بعد بحالی کا مرحلہ وار طبی پروٹوکول ہے۔ یہ حصہ آپ کے ہینڈ تھراپسٹ کو دیا جانا ہے، اور ہر مرحلہ عام فہم زبان میں اس وضاحت سے شروع ہوتا ہے کہ کیا ہو رہا ہے۔ یہ دباؤ ختم کرنے کا آپریشن (decompression) ہے، مرمت نہیں: کلائی کی پشت کا پہلا خانہ کاٹ کر کھولا جاتا ہے اور اسے کھلا ہی رہنا ہوتا ہے، اس لیے کسی مرمت کی حفاظت کی ضرورت نہیں۔ لہٰذا یہ پروگرام جلد حرکت اور ٹینڈن گلائیڈ پر مبنی راستہ ہے: اے پی ایل/ای پی بی (APL/EPB) ٹینڈنوں کو آپریشن کی جگہ میں پھسلتا رکھیں تاکہ وہ چپک نہ جائیں (adhesion)، سوجن (oedema) پر قابو رکھیں، زخم کے نشان اور ریڈیل عصب کی حسی شاخ کا خیال رکھیں، اور گرفت اور چٹکی بحال کریں۔
علاج سے پہلے مریض کی آپریشن رپورٹ دیکھیں اور علاج کرنے والے سرجن سے ان باتوں کے بارے میں رابطہ کریں: ریلیز کی تفصیل (لمبائی کے رخ یا پشت کی طرف چیرا، longitudinal/dorsal incision؛ اور آیا ای پی بی کا کوئی الگ ذیلی غلاف یا پردہ، EPB sub-sheath/septum، ملا اور کھولا گیا)، ہتھیلی کی طرف ٹینڈن کے کھسکنے (volar tendon subluxation) سے بچاؤ کے لیے ریلیز کا پشت کی طرف ہونا، اور ریڈیل عصب کی حسی شاخ کو کس طرح سنبھالا گیا۔ ڈاکٹر ہِرپرا پشت کی طرف/لمبائی کے رخ کے راستے سے کھلا آپریشن (open release) کرتے ہیں، ریڈیل عصب کی حسی شاخوں کی حفاظت کرتے ہیں اور ہتھیلی کی طرف کھسکنے سے بچنے کے لیے ریلیز کو پشت کی طرف رکھتے ہیں؛ حرکت روکنا صرف آرام کے لیے ہے (نرم پٹی، اور ضرورت ہو تو چند دنوں سے تقریباً 1 سے 2 ہفتے تک انگوٹھے کا چھوٹا اسپائیکا اسپلنٹ، thumb spica)، اور انگوٹھے اور کلائی کی جلد حرکت معمول کا طریقہ ہے۔
پہلا مرحلہ — جلد حرکت، سوجن اور زخم کی دیکھ بھال (ہفتہ 0 سے تقریباً 2)
پہلے ایک یا دو ہفتے زخم کی حفاظت کی جاتی ہے اور سوجن کم کی جاتی ہے، جبکہ حرکت فوراً شروع ہو جاتی ہے۔ یہاں حرکت کی کوئی محفوظ حد نہیں جس کی پابندی کرنی ہو: مقصد یہ ہے کہ کھولے گئے ٹینڈن فوراً پھسلنا شروع کریں۔ کوئی بھی اسپلنٹ صرف آرام کے لیے ہے اور ورزشوں کے لیے اتار دیا جاتا ہے۔
آپ کے ہینڈ تھراپسٹ کے لیے:
تعلیم اور احتیاطیں - یہ دباؤ ختم کرنے کا آپریشن (decompression) ہے: حفاظت کے لیے کوئی مرمت نہیں؛ جلد ایکٹو حرکت ہی مطلوبہ معمول ہے - صرف آرام کے لیے سہارا: پہلے چند دنوں سے تقریباً 1 سے 2 ہفتے تک نرم پٹی، اور ضرورت ہو تو چھوٹا انگوٹھے کا اسپائیکا اسپلنٹ (thumb spica)؛ ورزشوں اور نہانے دھونے کے لیے اتار دیں - زخم بھرنے تک اسے صاف اور خشک رکھیں؛ جلد بند ہونے تک زخم کے نشان کا کام مؤخر کریں - اس دوران زور کی گرفت، زور کی چٹکی، وزن اٹھانے اور کلائی مروڑنے سے پرہیز کریں - ریڈیل عصب کی حسی شاخ کے علاقے (انگوٹھے اور کلائی کی پشت، انگوٹھے والی طرف؛ dorsoradial) میں جھنجھناہٹ (paraesthesiae)، حد سے زیادہ حساسیت یا ٹینل کی علامت (Tinel's) کی جانچ کریں؛ مزاحمت کے ساتھ یا ایکٹو طور پر انگوٹھا سیدھا کرنے اور باہر کھولنے (extension–abduction) پر اے پی ایل/ای پی بی کے کھسکنے (subluxation) کی جانچ کریں
علاج کا طریقہ - زخم: ہدایت کے مطابق سرجیکل پٹیاں؛ انفیکشن پر نظر رکھیں - سوجن: اونچا رکھنا، دل کی طرف ہلکی مالش (retrograde massage)، ضرورت کے مطابق برف - ورزشیں: انگوٹھے کی ایکٹو حرکت کی حد (ROM) (موڑنا/سیدھا کرنا، ہتھیلی کی طرف اور انگوٹھے والی طرف کھولنا یعنی palmar + radial abduction، انگوٹھے کو انگلیوں کے مقابل لانا یعنی opposition)، کلائی کی ایکٹو حرکت کی حد، اے پی ایل/ای پی بی ٹینڈن گلائیڈز، انگلیوں کی پوری ایکٹو حرکت کی حد؛ آرام کی حد میں ہاتھ کا ہلکا روزمرہ استعمال
اگلے مرحلے میں جانے کی شرائط - زخم بھر گیا ہو یا ٹھیک ہو رہا ہو؛ سوجن قابو میں ہو؛ انگوٹھے اور کلائی کی ایکٹو حرکت آرام دہ ہو
دوسرا مرحلہ — حرکت کی بحالی اور زخم کے نشان کی دیکھ بھال (تقریباً ہفتہ 2 سے 4)
زخم بھر جانے کے بعد آرام والا اسپلنٹ چھوڑ دیا جاتا ہے اور توجہ پوری، آرام دہ حرکت کے ساتھ ساتھ زخم کے نشان کی دیکھ بھال اور عصب کی حساسیت کم کرنے (desensitisation) کے فعال کام پر آ جاتی ہے۔ اس مدت کے آخر کی طرف ہلکی طاقت بڑھانے کی ورزشیں شروع ہوتی ہیں۔
آپ کے ہینڈ تھراپسٹ کے لیے:
جانچ - انگوٹھے اور کلائی کی ایکٹو/پیسو حرکت کی حد؛ زخم کے نشان کی کیفیت؛ ریڈیل عصب کی حسی شاخ کی علامات؛ ٹینڈن کھسکنے (subluxation) کی جانچ
تعلیم اور احتیاطیں - آرام والا کوئی بھی اسپلنٹ بند کر دیں؛ ہاتھ کے معمول کے ہلکے استعمال کی حوصلہ افزائی کریں - تقریباً 3 سے 4 ہفتے تک بھاری یا زور کی گرفت اور چٹکی سے پرہیز جاری رکھیں
علاج کا طریقہ - زخم کا نشان: زخم بھرنے کے بعد مالش اور سلیکون/موئسچرائزر؛ حد سے زیادہ حساس ہو تو حساسیت کم کرنے کی مشقیں - عصب: اگر عصب میں جلن ہو تو ریڈیل عصب کی حسی شاخ کی گلائیڈز/حساسیت کم کرنے کی مشقیں؛ وزن ڈالنے سے پہلے اسے پرسکون کریں - ورزشیں: انگوٹھے اور کلائی کی پوری حرکت کی حد تک آگے بڑھیں؛ ٹینڈن گلائیڈز جاری رکھیں؛ تقریباً 3 سے 4 ہفتے سے ہلکی گرفت/چٹکی شروع کریں (تھراپی پُٹی یعنی putty، نرم گیند)
اگلے مرحلے میں جانے کی شرائط - انگوٹھے اور کلائی کی پوری، بغیر درد کی حرکت؛ بھرا ہوا اور حرکت پذیر زخم کا نشان؛ عصب کی علامات کم ہو رہی ہوں
تیسرا مرحلہ — طاقت بڑھانا اور سرگرمی پر واپسی (تقریباً ہفتہ 4 سے 6 اور اس کے بعد)
حرکت بحال ہونے اور زخم پختہ ہو جانے کے بعد گرفت اور چٹکی کی طاقت بڑھائی جاتی ہے اور مریض کو پوری سرگرمی پر واپس لایا جاتا ہے۔ زیادہ تر لوگ تقریباً چار سے چھ ہفتوں تک ہاتھ کا آرام دہ معمول کا استعمال کرنے لگتے ہیں؛ زیادہ بھاری جسمانی کاموں میں کچھ زیادہ وقت لگتا ہے اور ان کا فیصلہ مقررہ معیار (criteria) کی بنیاد پر ہوتا ہے۔
آپ کے ہینڈ تھراپسٹ کے لیے:
جانچ - دوسری طرف کے مقابلے میں گرفت اور چٹکی کی طاقت؛ وزن ڈالنے پر درد؛ مناسب ہو تو روزمرہ کام اور ملازمت سے متعلق جانچ
تعلیم اور احتیاطیں - گرفت، چٹکی، وزن اٹھانے اور مروڑنے کی طرف بتدریج واپسی؛ آرام اور طاقت کی اجازت کے مطابق پوری سرگرمی - انگوٹھے اور کلائی کی پشت کی طرف (dorsoradial) مسلسل درد یا جھنجھناہٹ، یا ٹینڈن کے جھٹکے سے اچھلنے کی صورت میں علاج کرنے والے سرجن کے پاس واپس بھیجیں (عصب کی گانٹھ یعنی neuroma، نامکمل ریلیز، یا ہتھیلی کی طرف ٹینڈن کے کھسکنے پر غور کریں)
علاج کا طریقہ - ورزشیں: گرفت اور چٹکی کی بتدریج بڑھتی ہوئی طاقت کی ورزشیں؛ مخصوص کاموں اور ملازمت سے متعلق وزن ڈالنا؛ زخم کے نشان اور عصب کا باقی ماندہ کام جاری رکھیں - جب طاقت تقریباً دونوں طرف برابر ہو اور ہاتھ کا کام بحال ہو جائے تو علاج ختم (discharge) کرنے پر غور کریں - اگر صحت یابی رک جائے یا نتیجہ اچھا نہ ہو تو علاج کرنے والے ڈاکٹر کے پاس واپس بھیجنے پر غور کریں
علاج ختم کرنے / پوری سرگرمی پر واپسی کی شرائط - گرفت اور چٹکی تقریباً دونوں طرف برابر؛ روزمرہ اور ملازمت سے متعلق بغیر درد استعمال
کام اور سرگرمیوں پر واپسی
ہاتھ کے ہلکے روزمرہ استعمال (کھانا، لکھنا، کپڑے پہننا، ہلکے کام) کی شروع سے ہی آرام کی حد میں حوصلہ افزائی کی جاتی ہے۔ چونکہ آپریشن کلائی پر ہوتا ہے اور ہاتھ کو آزادی سے حرکت کرنے اور محفوظ طریقے سے گرفت کرنے کی ضرورت ہوتی ہے، اس لیے گاڑی چلانا اس وقت دوبارہ شروع ہوتا ہے جب زخم آرام دہ ہو، آرام والا کوئی بھی اسپلنٹ اتر چکا ہو، اور آپ اسٹیئرنگ کو اعتماد سے پکڑ اور گھما سکیں؛ زیادہ تر لوگوں کے لیے یہ پہلے ایک یا دو ہفتوں کے اندر ہوتا ہے، جس کی تصدیق آپ کے معائنے پر کی جاتی ہے۔
زور کی گرفت، چٹکی، وزن اٹھانا اور مروڑنا تقریباً تین سے چار ہفتے تک مؤخر رہتے ہیں اور پھر بتدریج بڑھائے جاتے ہیں۔ دفتری اور ہلکا کام اکثر چند دنوں سے ایک یا دو ہفتوں کے اندر دوبارہ شروع ہو جاتا ہے؛ زیادہ بھاری جسمانی مشقت والا کام، جس میں انگوٹھے اور کلائی پر بار بار مضبوط بوجھ پڑتا ہے، عموماً تقریباً چار سے چھ ہفتوں تک دوبارہ شروع ہو جاتا ہے، اور اس کا فیصلہ ڈاکٹر ہِرپرا اور آپ کا ہینڈ تھراپسٹ صرف کیلنڈر کے بجائے آپ کی بحال ہونے والی طاقت اور آرام کی بنیاد پر کرتے ہیں۔
آپ کے پروٹوکول کے بعد
یہ پروٹوکول کلینک کے صحت یابی سے متعلق عمومی مشوروں کے ساتھ مل کر کام کرتا ہے: آپریشن کے بعد درد پر قابو پانا، زخم کی دیکھ بھال اور زخم کے نشان کی دیکھ بھال دیکھیں۔ اوپر دیا گیا مرحلہ وار منصوبہ ڈی کویروین ریلیز کے بعد بحالی سے متعلق شائع شدہ رہنمائی کی عکاسی کرتا ہے، اور آپ کی آگے کی صحت یابی میں ڈاکٹر ہِرپرا اور آپ کا ہینڈ تھراپسٹ آپ کے ہاتھ کی پیش رفت کے مطابق انفرادی طور پر رہنمائی کرتے ہیں۔
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
de Quervain's Release — Procedure Outcomes & Post-operative Rehabilitation (First Dorsal Compartment Release)
Topic scope: post-operative rehabilitation after surgical release of the first dorsal compartment of the wrist (abductor pollicis longus, APL, and extensor pollicis brevis, EPB) for refractory de Quervain's tenosynovitis. This is a decompression, not a reconstruction: the fibro-osseous tunnel is opened and is meant to stay open, so the rehabilitation is an early-motion pathway built around tendon gliding, oedema and scar control, and protection of the overlying radial sensory nerve — rather than months of protected healing.
Defining principle of the rehab here: de Quervain's release relieves a tendon entrapment and does not create a construct that needs protection. The divided extensor retinaculum is meant to stay divided. So (unlike a tendon or ligament repair) immediate, gentle active thumb and wrist motion is the default, and the only deliberate restraints are brief comfort support and a short window of heavy-grip/pinch/twist avoidance while the wound heals. The therapy programme exists to keep the APL/EPB tendons gliding through the healing surgical bed so they do not adhere, to settle the radial sensory nerve branches that cross the incision, and to rebuild grip and pinch — not to immobilise. The single branch points are (1) whether a separate EPB sub-sheath/septum was present and released (its retention is a classic cause of failed release) and (2) keeping the release dorsal so the tendons do not subluxate volarly.
A. PROCEDURE OUTCOMES (open release; endoscopic and retinaculum-sparing variants)
Surgical release of the first dorsal compartment is a reliable operation for de Quervain's that has failed non-operative care: the great majority of patients obtain durable symptom relief, and the principal debates are over technique details (incision orientation, completeness of EPB sub-sheath release, whether to preserve/lengthen the retinaculum) rather than whether to decompress.
- Open release gives durable, high-quality long-term outcomes. A series of 80 cases with a mean 9.5-year follow-up reported sustained relief with a low complication profile, establishing the long-term reliability of open release [Garçon et al., Orthop Traumatol Surg Res 2018]. Moderate (long-term cohort).
- Functional recovery is good and objectively measurable. A series using DASH scores to evaluate first-extensor-compartment release for refractory disease documented good functional outcomes, and emphasised identifying and releasing a separate EPB sub-compartment (septum) when present [Lee et al., Clin Orthop Surg 2014]. DASH is a validated, widely used outcome instrument across hand and wrist conditions [Baltzer, Novak & McCabe, J Hand Surg Am 2014 — scoping review]. Moderate (cohort) + instrument SR.
- Endoscopic and open release are broadly comparable. A comparative study of endoscopic versus open release found favourable results for the endoscopic approach with attention to the radial sensory nerve, while open release remains the standard reference technique [Kang et al., Bone Joint J 2013]. Moderate (comparative).
- The retinaculum can be partly resected, simply divided, or reconstructed. Partial resection of the extensor retinaculum gives good short-term results [Altay et al., Orthop Traumatol Surg Res 2011]; simple release and Z-plasty (retinaculum-lengthening) reconstruction give comparable outcomes, with Z-plasty proposed to reduce subluxation risk at the cost of complexity [Kim, Baek & Lee, J Hand Surg Eur 2019]. A longitudinal-incision technique series likewise reports good functional outcomes [Mangukiya et al., Musculoskelet Surg 2019]. Moderate (comparative/cohort).
- Dissatisfaction does occur and is worth counselling for. A focused study of dissatisfaction after first dorsal compartment release found that a minority of patients remain dissatisfied, often linked to residual pain, nerve symptoms or incomplete relief — a reminder that outcomes are good but not universal [Rogozinski & Lourie, J Hand Surg Am 2016]. Moderate (cohort).
B. REHABILITATION / THERAPY EVIDENCE
The central rehab questions are (1) whether to immobilise the thumb/wrist afterwards and for how long, and (2) whether formal hand therapy changes the outcome. The published base specific to post-de-Quervain-release rehabilitation is thin and consensus-driven: there are no high-quality trials comparing immobilisation regimens or therapy protocols. Practice converges on brief comfort support and early motion, with hand therapy used selectively.
- Early motion is the rationalised default; prolonged immobilisation is not supported. Because the release is a decompression with no construct to protect, early active thumb and wrist motion is used to keep the APL/EPB tendons gliding and prevent adhesion. Immobilisation, where used, is a soft dressing or short thumb spica for comfort only for days to ~1–2 weeks. The supporting evidence is mechanistic/consensus, mirroring the well-established early-motion rationale after other upper-limb decompressions. Weak–moderate (mechanism strong, outcome data sparse).
- De Quervain's is not always an isolated problem — therapy assessment matters. A hand-therapy review highlights that de Quervain's syndrome may coexist with other dorsoradial/wrist pathology, so post-operative therapy should reassess rather than assume a single diagnosis — relevant when symptoms persist after release [Redvers-Chubb, Hand Therapy 2015]. Consensus (narrative/therapy review).
- Hand therapy focus is glide, scar and nerve, then strength. The programme priorities are tendon gliding (adhesion prevention), oedema control, scar management and radial sensory nerve desensitisation, and graded grip/pinch strengthening. The benefit of formal supervised therapy over a home programme is not established by trial data; selective therapy is defensible. Weak / consensus.
Recovery trajectory (expected, evidence-anchored)
| Phase | Window | Restraint | Hand use / therapy focus | Strength / load | Notes |
|---|---|---|---|---|---|
| I — Early motion, oedema & wound care | Week 0–~2 | Comfort support only (soft dressing ± short thumb spica) | Immediate active thumb + wrist motion; APL/EPB tendon glides; elevation/oedema control; screen radial sensory nerve + subluxation | Light functional use only | No construct to protect; motion is the treatment. Keep wound clean/dry |
| II — Restore motion & scar/nerve care | Week ~2–4 | Splint discarded once healed | Full thumb + wrist ROM; scar massage once wound healed; radial sensory nerve glides/desensitisation if irritable | Begin light grip/pinch (putty, ball) from ~3–4 wk | Avoid forceful grip/pinch/twist until ~3–4 wk |
| III — Strengthening & return | Week ~4–6+ | Restrictions lifted, graded | Progressive grip/pinch and task-specific loading | Return to near-symmetrical grip/pinch; full activity as strength allows | Light/desk work days–1–2 wk; manual work ~4–6 wk, criterion-based |
(Phase windows are typical clinical guides, not trial-derived deadlines. Driving resumes once the wound is comfortable, any comfort splint is off, and the patient can grip and steer confidently — commonly within 1–2 weeks.)
C. KEY CONTROVERSIES / EVIDENCE QUALITY
- The EPB sub-sheath (septum) must be sought and released. A separate EPB sub-compartment is common and, if missed, is a classic cause of persistent symptoms / failed release. Series that emphasise identifying and releasing it report good outcomes [Lee 2014]. Moderate — strong mechanistic consensus.
- Volar tendon subluxation if released too volar. Dividing the retinaculum too far towards the palmar side can let the APL/EPB tendons subluxate volarly with thumb motion. Keeping the release dorsal, and retinaculum-lengthening (Z-plasty) reconstructions, are described specifically to mitigate this [Kim 2019; Altay 2011]. Moderate (technique-comparative).
- Radial sensory nerve injury is the signature complication. The superficial radial nerve branches cross the operative field; injury or scar entrapment produces dorsoradial numbness, hypersensitivity or painful neuroma and is a leading driver of dissatisfaction [Ilyas et al., J Am Acad Orthop Surg 2007; Rogozinski 2016]. Careful exposure with nerve protection is emphasised across open and endoscopic techniques [Kang 2013]. Moderate.
- Immobilise or move early? No trial settles the optimal post-operative regimen; consensus favours brief comfort support and early motion (decompression logic) over prolonged splinting. Weak — consensus, not trial-derived.
- Outcomes are good but not universal. A measurable minority remain dissatisfied, usually from residual pain, nerve symptoms or incomplete release — worth explicit pre-operative counselling [Rogozinski 2016]. Moderate.
D. EVIDENCE STRENGTH FLAGS (summary)
- MODERATE (cohort / comparative): durable long-term relief from open release (9.5-yr cohort); good DASH-measured functional outcomes; comparability of endoscopic vs open and of simple release vs Z-plasty / partial retinaculum resection; radial sensory nerve injury as the signature complication; a real, defined dissatisfaction rate.
- WEAK / CONSENSUS: the early-motion, glide-based rehabilitation programme itself (mechanistically rationalised; no trial comparing immobilisation regimens or therapy protocols after de Quervain's release); the role of formal supervised therapy vs a home programme; exact phase timings and return-to-activity windows (typical guides, not trial-derived). Outcomes and the two signature complications (radial sensory nerve injury; volar subluxation) are better studied than the rehabilitation protocol.
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Garçon JJ, Charruau B, Marteau E, et al. Results of surgical treatment of De Quervain's tenosynovitis: 80 cases with a mean follow-up of 9.5 years. Orthop Traumatol Surg Res. 2018. DOI: 10.1016/j.otsr.2018.04.022 (PMID 29909297)
- Lee HJ, Kim PT, Aminata IW, et al. Surgical Release of the First Extensor Compartment for Refractory de Quervain's Tenosynovitis: Surgical Findings and Functional Evaluation Using DASH Scores. Clin Orthop Surg. 2014. DOI: 10.4055/cios.2014.6.4.405
- Ilyas AM, Ast M, Schaffer AA, et al. de Quervain Tenosynovitis of the Wrist. J Am Acad Orthop Surg. 2007. DOI: 10.5435/00124635-200712000-00009 (PMID 18063716)
- Kang HJ, Koh IH, Jang JW, et al. Endoscopic versus open release in patients with de Quervain's tenosynovitis. Bone Joint J. 2013. DOI: 10.1302/0301-620X.95B7.31486 (PMID 23814248)
- Altay M, Ertürk C, Işıkan UE. De Quervain's disease treatment using partial resection of the extensor retinaculum: A short-term results survey. Orthop Traumatol Surg Res. 2011. DOI: 10.1016/j.otsr.2011.03.015
- Kim J, Baek J, Lee J. Comparison between simple release and Z-plasty of retinaculum for de Quervain's disease: a retrospective study. J Hand Surg Eur Vol. 2019. DOI: 10.1177/1753193418818341 (PMID 30669923)
- Mangukiya HJ, Kale A, Mahajan NP, et al. Functional outcome of De Quervain's tenosynovitis with longitudinal incision in surgically treated patients. Musculoskelet Surg. 2019. DOI: 10.1007/s12306-018-0585-1
- Rogozinski B, Lourie GM. Dissatisfaction After First Dorsal Compartment Release for de Quervain Tendinopathy. J Hand Surg Am. 2016;41(1). DOI: 10.1016/j.jhsa.2015.09.020 (PMID 26481556)
- Baltzer H, Novak CB, McCabe SJ. A Scoping Review of Disabilities of the Arm, Shoulder, and Hand Scores for Hand and Wrist Conditions. J Hand Surg Am. 2014. DOI: 10.1016/j.jhsa.2014.07.050 (PMID 25227601)
- Redvers-Chubb K. De Quervain's syndrome: It may not be an isolated pathology. Hand Therapy. 2015. DOI: 10.1177/1758998315599796
de Quervain's release literature (URLs)
- Lee HJ, et al. Surgical Release of the First Extensor Compartment for Refractory de Quervain's Tenosynovitis (DASH outcomes; EPB septum). Clin Orthop Surg 2014 (open access). https://doi.org/10.4055/cios.2014.6.4.405
- Garçon JJ, et al. Results of surgical treatment of De Quervain's tenosynovitis: 80 cases, mean 9.5-year follow-up. Orthop Traumatol Surg Res 2018. https://doi.org/10.1016/j.otsr.2018.04.022
- Ilyas AM, et al. de Quervain Tenosynovitis of the Wrist (review — radial sensory nerve, surgical technique, complications). J Am Acad Orthop Surg 2007. https://doi.org/10.5435/00124635-200712000-00009
- Rogozinski B, Lourie GM. Dissatisfaction After First Dorsal Compartment Release for de Quervain Tendinopathy. J Hand Surg Am 2016. https://doi.org/10.1016/j.jhsa.2015.09.020