Patients › Hand
انگلی کے جوڑ (knuckle) کی تبدیلی (MCPJ)
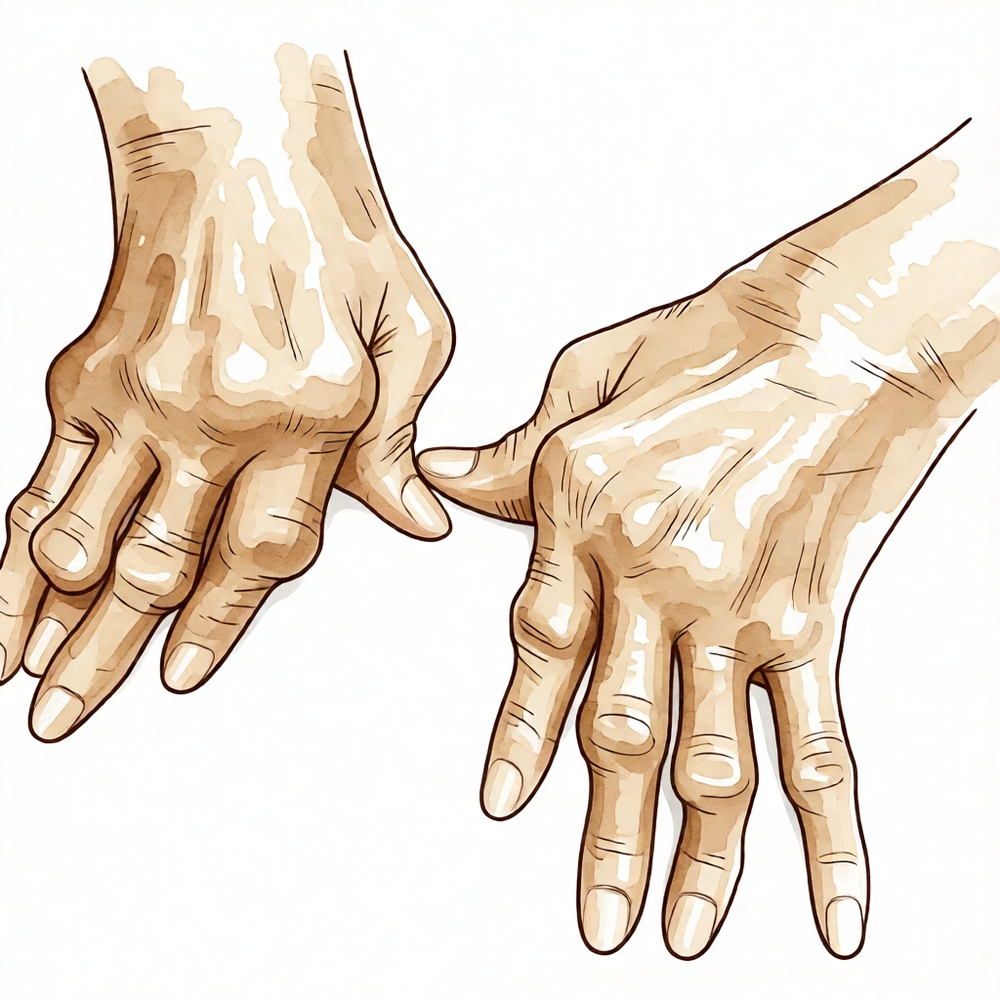
یہ آپریشن کیوں تجویز کیا گیا ہے
ڈاکٹر کیرن ہِرپرا، جو Mater Private Hospital Rockhampton میں بازو اور ہاتھ کے سرجن (upper-limb surgeon) ہیں، علاج کا آغاز ان کم سے کم چیر پھاڑ والے طریقوں سے کرتے ہیں جو آپ کی حالت کے لیے موزوں ہوں۔ مریضوں کو عام طور پر ان کا فیملی ڈاکٹر (GP) ہمارے کلینک میں بھیجتا ہے؛ اگر کسی فزیوتھراپسٹ نے آپ کو ہمارے پاس آنے کا مشورہ دیا ہے، تب بھی میڈیکیئر (Medicare) کی رقم کی واپسی (rebate) کا اہل ہونے کے لیے آپ کو اپنے فیملی ڈاکٹر سے ریفرل (referral) لینا ہوگا۔ آپ کی ملاقات میں ہم آپ کی بیماری کی تفصیل پوچھتے ہیں، آپ کے ہاتھ کا معائنہ کرتے ہیں، اور اگر ضرورت ہو تو تصویری ٹیسٹ (imaging) کرواتے ہیں۔ اس سے ہمیں پتا چلتا ہے کہ جوڑ میں کیا ہو رہا ہے۔
یہ آپریشن انگلی کے جوڑ (knuckle)، یعنی وہ جوڑ جہاں آپ کی انگلی یا انگوٹھا ہاتھ سے ملتا ہے، کو ایک مصنوعی امپلانٹ (جسم میں لگایا گیا مصنوعی پرزہ) سے بدل دیتا ہے۔ یہ عام طور پر اس وقت تجویز کیا جاتا ہے جب آرتھرائٹس (جوڑ کی خرابی اور سوزش) کی وجہ سے جوڑ کی سطح بہت زیادہ گھس چکی ہو اور دوسرے علاج سے کافی آرام نہ ملا ہو۔ جوڑ کے گھسنے کے پرانے مسائل میں ہم عام طور پر پہلے آپریشن کے بغیر علاج آزماتے ہیں: سرگرمیوں میں تبدیلی، فزیوتھراپی یا ہینڈ تھراپی، اور اسپلنٹ۔ آپریشن پر اس وقت غور کیا جاتا ہے جب ان اقدامات سے کافی فائدہ نہ ہوا ہو۔ مقصد درد سے نجات، ہاتھ کا بہتر استعمال، اور ساتھ والے جوڑوں کی حفاظت ہے۔ کچھ لوگوں میں یہ اس جوڑ کو دوبارہ مستحکم بھی کرتا ہے جو ڈھیلا ہو گیا ہو یا ٹیڑھا ہو گیا ہو۔
آپریشن سے پہلے
آپریشن سے پہلے کے ہفتوں میں ہم آپ کے ہاتھ کی نئی تصاویر، جیسے ایکسرے، ایم آر آئی یا الٹراساؤنڈ، کے ذریعے منصوبے کی تصدیق کرتے ہیں۔ ان سے ہمیں گھسا ہوا جوڑ نظر آتا ہے اور صحیح امپلانٹ چننے میں مدد ملتی ہے۔ آپ کو کھانا پینا بند کرنے (fasting) کے بارے میں واضح ہدایات دی جائیں گی: آپریشن سے سات گھنٹے پہلے تک کچھ نہ کھائیں اور نہ پئیں۔ ہم اس سے کم وقت کے بجائے سات گھنٹے اس لیے کہتے ہیں تاکہ اگر آپریشن کی فہرست وقت سے پہلے چل رہی ہو تو آپ کا آپریشن پہلے کیا جا سکے۔ کچھ دواؤں کو آپریشن سے پہلے روکنا پڑتا ہے، اور آپ کا سرجن آپ کو بتائے گا کہ کون سی دوائیں اور کب۔ اگر آپ کو دوسری بیماریاں ہیں تو آپ کو خون کے ٹیسٹ یا بے ہوشی کے ڈاکٹر (anaesthetist) سے معائنے کی ضرورت پڑ سکتی ہے۔ آپریشن کے دن اپنی موجودہ دواؤں کی فہرست ساتھ لائیں، گھر واپس جانے کے لیے سواری کا انتظام کریں، اور ڈھیلی آستینوں والے آرام دہ کپڑے پہنیں۔
آپریشن کے دن
آپ ہسپتال کے سرجری کے داخلے کے شعبے میں پہنچتے ہیں، جہاں آپ کا اندراج کیا جاتا ہے اور آپ کو آپریشن تھیٹر کے لیے تیار کیا جاتا ہے۔ آپ کی ملاقات بے ہوشی کے ڈاکٹر سے ہوتی ہے، یعنی وہ ڈاکٹر جو آپریشن کے دوران آپ کی بے ہوشی اور درد پر قابو کا خیال رکھتا ہے۔ یہ آپریشن جنرل اینستھیزیا (مکمل بے ہوشی) میں کیا جاتا ہے۔ آپریشن کے بعد درد سے آرام کے لیے بعض اوقات اس کے ساتھ اعصابی بلاک (nerve block)، یعنی ایک انجکشن جو جسم کے ایک حصے کو سُن کر دیتا ہے، بھی لگایا جاتا ہے؛ بے ہوشی کے ڈاکٹر آپریشن کے دن اس بارے میں آپ سے بات کریں گے۔ اس کے بعد آپ کو آپریشن تھیٹر میں لے جایا جاتا ہے، جہاں آپریشن کیا جاتا ہے۔
آپریشن ختم ہونے کے بعد آپ ریکوری روم میں جاگتے ہیں۔ بے ہوشی کا اثر ختم ہونے تک نرسیں آپ کی نگرانی کرتی ہیں۔ جب آپ کی حالت مستحکم ہو جائے، تو آپ یا تو وارڈ میں منتقل ہو جاتے ہیں یا اسی دن گھر چلے جاتے ہیں، یہ اس بات پر منحصر ہے کہ کون سا آپریشن ہوا ہے اور آپ کی صحت یابی کیسی جا رہی ہے۔
آپریشن میں کیا کیا جاتا ہے
آپ کا سرجن آپ کی انگلی کے جوڑ کی پشت پر ایک چھوٹا چیرا لگا کر گھسی ہوئی جوڑ کی سطحوں تک پہنچتا ہے۔ ہڈیوں کے خراب سرے ہٹا دیے جاتے ہیں اور انہیں امپلانٹ کے لیے جگہ بنانے کے لحاظ سے شکل دی جاتی ہے۔ سب سے عام امپلانٹ ایک لچکدار درمیانی پرزہ (spacer) ہوتا ہے جو دونوں ہڈیوں کے درمیان رہتا ہے، جس سے جوڑ دوبارہ مڑ سکتا ہے اور درد کم ہوتا ہے۔ مقصد درد سے نجات، بہتر حرکت، اور ساتھ والے جوڑوں کی حفاظت ہے۔
مختلف امپلانٹ مختلف جوڑوں اور مختلف مسائل کے لیے موزوں ہوتے ہیں۔ کچھ لوگوں کے لیے نرم سلیکون کا درمیانی پرزہ استعمال کیا جاتا ہے۔ دوسروں کے لیے، خاص طور پر جہاں آس پاس کے لیگامنٹ (ligament)، یعنی وہ مضبوط بندھن جو ایک ہڈی کو دوسری ہڈی سے جوڑتا ہے، مضبوط ہوں اور ساتھ والی انگلیاں سہارا دیتی ہوں، قدرتی جوڑ کی سطح کی شکل کا ایک سخت امپلانٹ چنا جاتا ہے۔ آپ کا سرجن وہ امپلانٹ چنتا ہے جو آپ کے جوڑ اور آپ کی حالت کے مطابق ہو۔
امپلانٹ اپنی جگہ لگ جانے کے بعد، آپ کا سرجن جانچتا ہے کہ انگلی سیدھ میں ہے اور آسانی سے حرکت کرتی ہے، اور جوڑ کے گرد نرم بافتوں کو متوازن کرتا ہے تاکہ جوڑ مستحکم رہے۔ چیرے کو ٹانکوں سے بند کر کے اس پر زخم کی پٹی لگا دی جاتی ہے۔ یہ پٹی تقریباً 10 دن تک لگی رہتی ہے، جس کی وضاحت 'آپریشن کے بعد' والے حصے میں کی گئی ہے۔
انگوٹھے کے کچھ جوڑوں میں، ہڈیوں کو آپس میں جوڑ دینا (فیوژن، یعنی دو ہڈیوں کو جوڑ کر ایک کر دینا) امپلانٹ کا ایک متبادل ہے۔ اس سے دردناک جوڑ ختم ہو جاتا ہے لیکن اس کا مطلب یہ ہے کہ انگوٹھے کا وہ حصہ اب مڑتا نہیں۔ رضامندی کے فارم (consent form) پر دستخط کرنے سے پہلے آپ کا سرجن آپ سے بات کرے گا کہ کون سا راستہ آپ کے جوڑ کے لیے موزوں ہے۔
آپریشن کے بعد
آپ ریکوری روم میں جاگیں گے، جہاں بے ہوشی کا اثر ختم ہونے تک نرسیں آپ پر کڑی نظر رکھیں گی۔ آپ کے ہاتھ پر ایک بڑی موٹی پٹی ہوگی، اور آپ کو آرام میں رکھنے کے لیے ہم آپ کو درد کی دوا دیں گے۔ گھر پہنچنے کے بعد پہلے 24 گھنٹے تک کسی کو آپ کے ساتھ رہنا چاہیے۔ آپ معمول کے مطابق چل پھر سکتے ہیں، لیکن آرام سے رہیں اور جب بیٹھیں تو اپنا ہاتھ تکیے پر اونچا رکھیں۔ آپ کی ٹیم آپ کو بتائے گی کہ آپ اسی دن گھر جائیں گے یا ایک رات ہسپتال میں رہیں گے۔ ہم پٹی تقریباً 10 دن تک لگی رہنے دیتے ہیں؛ براہِ کرم اس سے پہلے اسے نہ اتاریں، جب تک ہم آپ کو ایسا کرنے کو نہ کہیں۔ جب ہم آپ کو دیکھتے ہیں تو پٹی بدل دیتے ہیں یا اتار دیتے ہیں۔
صحت یابی
پہلے چند دنوں تک آپ کے ہاتھ میں درد اور سوجن رہے گی، اور انگلی کا جوڑ اکڑا ہوا محسوس ہو سکتا ہے اور اسے چھونے پر درد ہو سکتا ہے۔ ہاتھ کو تکیے پر اونچا رکھنے سے سوجن کم ہوتی ہے، اور جو درد کی دوا ہم آپ کو دیتے ہیں وہ آپ کو آرام میں رکھتی ہے۔ جوڑ کے ٹھیک ہونے کے ساتھ ساتھ تکلیف آہستہ آہستہ کم ہو جاتی ہے۔
شروع میں آپ کے ہاتھ پر ایک بڑی موٹی پٹی ہوگی، جو تقریباً 10 دن تک لگی رہتی ہے۔ جب ہم آپ کو دیکھتے ہیں، تو ہم اسے بدل دیتے ہیں یا اتار دیتے ہیں اور بھرتی ہوئی جلد کا معائنہ کرتے ہیں۔ اس سرجری کے بعد بحالی Extend Rehabilitation میں Ruby Doolan کے ساتھ ہینڈ تھراپی کے ذریعے ہوتی ہے۔ وہ آپ کی ورزشوں میں رہنمائی کریں گی اور اگر آپ کو ضرورت ہو تو اسپلنٹ بنائیں گی۔ یہ ورزشیں نئے جوڑ کی حفاظت کرتی ہیں جبکہ آپ کی انگلی یا انگوٹھا دوبارہ حرکت حاصل کرتا ہے، اور آپ کو دکھایا جائے گا کہ روزمرہ کے کاموں میں اپنے ہاتھ پر زور ڈالے بغیر اسے کیسے استعمال کریں۔
جیسے جیسے سوجن کم ہوتی ہے، انگلی کو موڑنا اور سیدھا کرنا عام طور پر آسان محسوس ہونے لگتا ہے۔ جب آپ بغیر درد کے گرفت اور چٹکی کی گرفت کر سکیں، تو آپ دیکھیں گے کہ کپڑے پہننا، کھانا اور لکھنا جیسے روزمرہ کے کام زیادہ قدرتی ہو جاتے ہیں۔ بہت سے لوگ محسوس کرتے ہیں کہ سب سے بڑا فائدہ اس درد سے نجات ہے جو انہیں سرجری سے پہلے تھا، اور ساتھ ہی روزمرہ کے کاموں کے لیے ہاتھ کا بہتر استعمال۔
جب تک آپ کا ہاتھ اسپلنٹ میں ہو یا آپ تیز درد کش دوا لے رہے ہوں، آپ کو گاڑی نہیں چلانی چاہیے، اور آپ کو اسٹیئرنگ دونوں ہاتھوں سے پکڑنے اور ہنگامی بریک لگانے کی صورت میں فوری ردِعمل دینے کے قابل ہونا چاہیے۔ بازو اور ہاتھ کی سرجری کے بعد گاڑی چلانے کے بارے میں ہماری الگ رہنمائی میں بتایا گیا ہے کہ گاڑی چلانا دوبارہ کب محفوظ ہے۔
صحت یابی ہر شخص میں مختلف ہوتی ہے، اور آپ کا وقت دوسروں سے مختلف ہو سکتا ہے۔ ہر معائنے پر ہم اور آپ کا ہینڈ تھراپسٹ مل کر آپ کی رہنمائی کریں گے۔
کیا مسائل پیدا ہو سکتے ہیں
زیادہ تر مریض ٹھیک رہتے ہیں، لیکن کبھی کبھار مسائل پیدا ہو سکتے ہیں۔ آپ کا سرجن اور ٹیم کسی بھی مسئلے کو جلد پکڑنے کے لیے آپ کی قریبی نگرانی کرتے ہیں۔
اس قسم کی جوڑ کی تبدیلی کے بعد انفیکشن کم ہوتا ہے۔ اپنے زخم کے آس پاس کی جلد پر نظر رکھیں۔ اگر آپ کو زخم سے باہر کی طرف پھیلتی ہوئی سرخی، گرمی، رطوبت کا رسنا، یا گہرا دھڑکتا ہوا درد نظر آئے جو عام درد کش دواؤں سے کم نہ ہو، تو بلا تاخیر کلینک سے رابطہ کریں۔ اگر آپ کو بخار محسوس ہو یا طبیعت خراب ہو، تو ہسپتال کی ایمرجنسی جائیں۔
نیا جوڑ بعض اوقات اپنی جگہ سے نکل سکتا ہے۔ اسے جوڑ کا اپنی جگہ سے نکل جانا (dislocation) کہتے ہیں۔ آپ کو جوڑ میں اچانک سرکنے کا احساس ہو سکتا ہے، اور انگلی یا انگوٹھا کسی عجیب زاویے پر رہ جاتا ہے اور معمول کے مطابق حرکت نہیں کرتا۔ اگر ایسا ہو تو فوراً کلینک کو فون کریں۔
خود امپلانٹ بھی وقت کے ساتھ گھس سکتا ہے، ڈھیلا ہو سکتا ہے، اس میں دراڑ آ سکتی ہے یا وہ مڑ سکتا ہے۔ اس کی علامات میں وہ درد واپس آ جانا شامل ہے جو ختم ہو چکا تھا، نئی کلک کی آواز یا رگڑ، یا انگلی کا سیدھ سے ہٹنا۔ یہ تبدیلیاں اپنے اگلے معائنے پر بتائیں، یا اگر یہ اچانک ہوں تو اس سے پہلے فون کریں۔
آپریشن کے دوران امپلانٹ کے آس پاس کی ہڈیاں بھی ٹوٹ سکتی ہیں۔ آپ کے آپریشن تھیٹر سے نکلنے سے پہلے آپ کا سرجن اس کی جانچ کرتا ہے، اور یہ عام طور پر اسپلنٹ میں کچھ عرصہ مزید حفاظت سے ٹھیک ہو جاتا ہے۔
اگر کوئی مسئلہ پیدا ہو جائے، تو اسے ٹھیک کرنے کے لیے بعض اوقات مزید سرجری کی ضرورت پڑتی ہے۔ اس کا مطلب امپلانٹ کو دوبارہ بدلنا ہو سکتا ہے، یا اگر دوبارہ بدلنا مناسب نہ ہو، تو اس جوڑ کی ہڈیوں کو آپس میں جوڑ دینا تاکہ وہ ایک ٹھوس ہڈی کی طرح جڑ جائیں۔ یہ دوسرا راستہ درد تو ختم کر دیتا ہے لیکن جوڑ کا مڑنا بند کر دیتا ہے۔ اگر کبھی ایسی نوبت آئی تو آپ کا سرجن آپ کو سمجھائے گا کہ آپ کی صورتحال کے لیے کیا مناسب ہے۔
کچھ لوگوں کو سرجری کے بعد انگلی یا انگوٹھے میں مسلسل اکڑاؤ یا کمزوری محسوس ہوتی ہے۔ ہینڈ تھراپی اس میں مدد دیتی ہے، اس لیے انتظار کرنے کے بجائے اپنے معائنے کی ملاقاتوں میں اس کا ذکر کریں۔
اگر آپ تفصیل جاننا چاہتے ہیں تو اس صفحے پر موجود پیچیدگیوں کی جدول میں عام شرحیں دی گئی ہیں۔
ہمیں کب فون کریں
زیادہ تر مسائل پہلے چند ہفتوں میں سامنے آتے ہیں، اس لیے یہ جاننا فائدہ مند ہے کہ کن باتوں پر نظر رکھنی ہے۔ اگر آپ کو زخم سے پھیلتی ہوئی سرخی، رطوبت کا رسنا، بخار، یا ایسا درد نظر آئے جو بڑھتا ہی جا رہا ہو، تو ہمیں فون کریں۔ اگر آپ کو بخار ہو اور طبیعت خراب محسوس ہو، یا آپ کی پنڈلی کا پچھلا حصہ سوج جائے اور اسے چھونے پر درد ہو، تو ہسپتال کی ایمرجنسی جائیں۔ اچانک سانس پھولنے کی صورت میں بھی ایمرجنسی علاج کی ضرورت ہے۔ اگر آپ کی انگلی یا انگوٹھا اچانک اپنی جگہ سے سرک جائے، کسی عجیب زاویے پر رہ جائے، یا آپ اسے ہلا نہ سکیں، تو فوراً ہمیں فون کریں۔ سُن پن یا جھنجھناہٹ جو ٹھیک نہ ہو، اس کا بھی جلد معائنہ ضروری ہے۔ اگر شک ہو تو ہمیں فون کریں۔
مزید تفصیل
Advanced reading: the deeper science (optional)
یہ حصہ اس سے زیادہ تفصیل میں جاتا ہے جتنی آپ کو اپنے علاج کے فیصلوں کے لیے ضرورت ہے۔ انگلی کے جوڑ کی تبدیلی کے بارے میں یہ اضافی مطالعہ ایک دلچسپ بات کی وجہ سے مفید ہے: آج سب سے زیادہ استعمال ہونے والا امپلانٹ بنیادی طور پر وہی ڈیزائن ہے جو 1960 کی دہائی میں متعارف کرایا گیا تھا، اور یہ ہر اس مواد سے زیادہ دیر تک چلا ہے جو اس کی جگہ لینے کے لیے لایا گیا۔ اس کی وجہ سمجھنے سے یہ واضح ہوتا ہے کہ یہ آپریشن دراصل کس لیے ہے۔
سلیکون کی جگہ کوئی نہیں لے سکا
ریومیٹائیڈ آرتھرائٹس میں انگلی کی جڑ کے جوڑ (metacarpophalangeal joint) کی تبدیلی کے بارے میں 2026 کا ایک جائزہ اس نتیجے پر پہنچتا ہے کہ یہ آپریشن ریومیٹائیڈ آرتھرائٹس سے متاثرہ ہاتھ کے علاج میں مرکزی کردار ادا کرتا رہا ہے، اور یہ کہ امپلانٹ کی ٹیکنالوجی میں ترقی کے باوجود، لچکدار سلیکون امپلانٹ سے جوڑ کی تبدیلی ہاتھ کے کام کاج اور شکل میں قابلِ اعتماد بہتری لاتی ہے، بشرطیکہ مریضوں کا انتخاب مناسب طریقے سے کیا گیا ہو [1]۔
ساٹھ سال کی مواد کی سائنس نے دھات اور پلاسٹک والے اور پائرو کاربن (pyrocarbon) کے متبادل تیار کیے ہیں، اور پھر بھی سلیکون کا درمیانی پرزہ ہی معیاری پیمانہ ہے۔ جوڑوں کی تبدیلی میں یہ غیر معمولی بات ہے، جہاں کولہے اور گھٹنے کے امپلانٹ اسی عرصے میں مسلسل بہتر کیے جاتے رہے ہیں۔
اس کی وجہ یہ ہے کہ یہ امپلانٹ وہ کام نہیں کر رہا جو اس کا نام ظاہر کرتا ہے۔ یہ کسی جوڑ کی سطح کو نیا بنا کر بوجھ اٹھانے والی سطح بحال نہیں کرتا۔ یہ ایک لچکدار درمیانی پرزہ ہے جو ہڈیوں کے درمیان خلا برقرار رکھتا ہے اور اندرونی اسپلنٹ کا کام کرتا ہے، جبکہ اس کے گرد زخم بھرنے سے بننے والا سخت ریشہ (scar tissue) بن کر جوڑ کی ایک نئی جھلی (capsule) بنا دیتا ہے۔ نتیجہ آلے سے نہیں بلکہ زخم کے بھرنے سے حاصل ہوتا ہے، اور اسی لیے بہتر رگڑ والی سطح کبھی بہتر نتیجے میں تبدیل نہیں ہوئی۔
نتائج کا دیانت دارانہ خلاصہ
انگلی اور انگوٹھے کے جوڑوں میں امپلانٹ سے جوڑ کی تبدیلی کا ایک جائزہ اسے اچھی طرح بیان کرتا ہے: امپلانٹ سے جوڑ کی تبدیلی سے توقع کے مطابق درد سے نجات ملتی ہے اور مریض بہت مطمئن ہوتے ہیں، لیکن ماضی میں اس میں پیچیدگیوں کی شرح زیادہ رہی ہے، اور اگرچہ دھات اور پلاسٹک والے اور پائرو کاربن مواد میں ترقی ہوئی ہے، امپلانٹ کا کام کرتے رہنا (survivorship) اور دوبارہ آپریشن کی شرح اب بھی تشویش کا باعث ہیں [2]۔
دونوں حصے اہم ہیں۔ لوگ ان آپریشنوں سے قابلِ اعتماد حد تک خوش ہوتے ہیں، درد ختم ہو جاتا ہے، شکل بہتر ہو جاتی ہے، ہاتھ روزمرہ کے کاموں کے لیے بہتر کام کرتا ہے، اور ساتھ ہی امپلانٹ کی عمر محدود ہوتی ہے اور دوبارہ آپریشن کی ایک حقیقی شرح موجود ہے۔ اطمینان اور پائیداری الگ الگ سوال ہیں، اور یہ آپریشن پہلے سوال پر کہیں بہتر ہے۔
جوڑ کے گھسنے والے آرتھرائٹس کے لیے شواہد کمزور ہیں
زیادہ تر تحقیق ریومیٹائیڈ آرتھرائٹس کے بارے میں ہے، کیونکہ وہیں درست کی جانے والی خرابی سب سے زیادہ نمایاں ہوتی ہے۔ جوڑ کے گھسنے والے آرتھرائٹس (osteoarthritis) میں صورتحال کمزور ہے: دستیاب شواہد ماضی کے ریکارڈ پر مبنی (retrospective) تحقیقات پر مشتمل ہیں جن میں مریضوں کی تعداد کم اور فالو اپ کی مدت نسبتاً مختصر ہے [3]۔
قابلِ ذکر بات یہ ہے کہ جہاں مصنفین جوڑ کے گھسنے والے آرتھرائٹس میں سلیکون کے بجائے پائرو کاربن کو ترجیح دیتے ہیں، وہ بہتر استحکام اور سیدھ کے امکان کی بنیاد پر ہے، اور اعداد و شمار کو ابتدائی قرار دیا گیا ہے [3]۔ یہ ایک معقول موقف ہے، لیکن اسے ثابت شدہ برتری کے بجائے طریقۂ کار کی بنیاد پر کیا گیا استدلال سمجھنا چاہیے۔
پائیداری ایک بڑا سوال بنتی جا رہی ہے
تقریباً دو دہائیاں پہلے اٹھایا گیا ایک خدشہ حل ہونے کے بجائے بڑھ گیا ہے: جیسے جیسے اوسط عمر بڑھ رہی ہے، اور جیسے جیسے یہ آپریشن کم عمر اور زیادہ متحرک مریضوں میں کیے جا رہے ہیں جو ان پر زیادہ عرصے تک بوجھ ڈالیں گے، امپلانٹ کی پائیداری زیادہ اہم ہوتی جا رہی ہے [4]۔ جو امپلانٹ دس سال تک قابلِ قبول کارکردگی دکھائے، وہ 75 سال کی عمر میں ایک الگ معاملہ ہے اور 55 سال کی عمر میں الگ۔
عملی طور پر، یہ اس بات کی وجہ ہے کہ آپ واضح طور پر جانیں کہ آپ اس آپریشن سے کیا حاصل کرنا چاہتے ہیں۔ درد سے نجات، خرابی کی درستی اور ایسے ہاتھ کے بہتر کام کاج کے لیے جس پر زیادہ جسمانی بوجھ نہ پڑتا ہو، یہ ایک ایسا آپریشن ہے جس کی تائید شواہد سے ہوتی ہے اور جس کا طویل ریکارڈ ہے۔ دہائیوں تک بھاری استعمال کے لیے ایک پائیدار مرمت کے طور پر، یہ ایسا نہیں ہے۔
حوالہ جات
[1] Herren DB. Balancing metacarpophalangeal joint arthroplasty in rheumatoid arthritis. J Hand Surg Eur Vol. 2026;51(6):778-84. https://doi.org/10.1177/17531934261430139
[2] Srnec JJ, Wagner ER, Rizzo M. Implant arthroplasty for proximal interphalangeal, metacarpophalangeal, and trapeziometacarpal joint degeneration. J Hand Surg Am. 2017;42(10):817-25. https://doi.org/10.1016/j.jhsa.2017.07.030
[3] Martin AS, Awan HM. Metacarpophalangeal arthroplasty for osteoarthritis. J Hand Surg Am. 2015;40(9):1871-2. https://doi.org/10.1016/j.jhsa.2015.05.019
[4] Goldfarb CA, Dovan TT. Rheumatoid arthritis: silicone metacarpophalangeal joint arthroplasty indications, technique, and outcomes. Hand Clin. 2006;22(2):177-82. https://doi.org/10.1016/j.hcl.2006.02.001
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- MCP joint arthroplasty was performed safely in the setting of acute complex open MCP joint trauma [1].
- Revision MCP arthroplasty is a challenging procedure with one in five patients requiring a revision procedure at 5 years [2].
- Revision MCP arthroplasty has a relatively high rate of postoperative dislocations [2].
- Dorsal capsule interposition arthroplasty provides a viable surgical option for isolated degenerative or traumatic arthritis of the MCPJ at an average follow-up of 2 years [3].
- Treatment of MCP joint arthroplasty dislocation with revision to silicone implant appears to hold the most promise in achieving a stable MCP joint after an acute prosthetic dislocation [4].
- MCP joint arthroplasty is an effective treatment option from a patient-centered perspective, improving appearance, pain, and function [5].
- Silastic interposition arthroplasty of the MCPJ is reliable in terms of pain relief and correction of deformity [6].
- Patient satisfaction with Silastic interposition arthroplasty of the MCPJ is high despite only modest improvements in the objective assessment of hand function [6].
- The nonconstrained implant design for the MCP joint can have good outcomes and excellent arc of motion in OA patients [8].
- Periprosthetic joint infection is uncommon after MCP or PIP arthroplasties [9].
- Patient expectations of MCP joint arthroplasty were uniformly high, with functional improvement being the greatest motivation for surgery [11].
- Joint goal-setting is essential for understanding patients' unique reasons for undergoing MCP arthroplasty and facilitating realistic expectations [14].
- Implant arthroplasty of the PIP, MCP, and TMC joints predictably produces pain relief and high satisfaction [24].
- Implant arthroplasty of the PIP, MCP, and TMC joints has historically suffered from high rates of complications [24].
- The evidence regarding MCP arthroplasty for OA consists of retrospective cohorts with small sample sizes and relatively short evaluations [26].
Anatomy & Pathophysiology
Joint Mechanics and Kinematics
- The metacarpophalangeal joint allows hyperextension up to approximately 20° [17].
- Radial and ulnar deviation at the metacarpophalangeal joint decreases with flexion due to the associated tightening of the collateral ligaments [17].
- Volar and proximal translation of the proximal phalanx is observed on 4-dimensional computed tomography following silicone implant arthroplasty [48].
Bony and Ligamentous Anatomy
- The metacarpophalangeal articulations serve as the keystones of the longitudinal arches of the hand [39].
- The thick anterior glenoid capsules, known as volar plates, prevent hyperextension at the metacarpophalangeal joints [39].
- The volar plates are interconnected by the transverse interglenoid ligament [39].
- The stability of the metacarpophalangeal joints is essential to the support of both the longitudinal arch and the transverse metacarpal arch [39].
- The deep transverse intermetacarpal ligament, also named the interglenoid ligament, ties together the anterior glenoid ligaments of the metacarpophalangeal articulations [39].
- The lateral accessory ligaments, sagittal bands of the extensor apparatus, and the first annular segment of the flexor tendon pulley insert on the volar plate [39].
Muscular Anatomy
- The deep head of each dorsal interosseous muscle forms a lateral tendon, or lateral band, at the level of the metacarpophalangeal joint [36].
- The deep head of the dorsal interosseous muscles flexes and weakly abducts the proximal phalanx while extending the middle and distal phalanges [36].
- Transverse fibers arch dorsally from each lateral band to join over the dorsum of the finger, flexing the proximal phalanx [36].
- Oblique fibers from the lateral bands sweep over the distal third of the proximal phalanx to insert onto the lateral tubercles at the base of the middle phalanx [36].
- The oblique fibers extend the middle phalanx at the proximal interphalangeal joint [36].
- The lateral bands are joined by the lateral slips of the extensor tendon to form the conjoined lateral band [36].
- The two conjoined lateral bands to each finger unite at the distal third of the middle phalanx to form the terminal tendon [36].
- The terminal tendon inserts at the base of the distal phalanx to extend it [36].
- The volar interossei form the ulnar lateral band of the index finger and the radial lateral band of the ring and little fingers [36].
- The flexor digiti quinti brevis forms the ulnar lateral band of the little finger [36].
Pathophysiology
- Rheumatoid arthritis is a chronic, progressive, systemic inflammatory disease that affects multiple organ systems, including the musculoskeletal system [17].
- The inflammatory process in rheumatoid arthritis is triggered and perpetuated by a cascade of mediators that result in synovial proliferation, collagenous destruction of the cartilage and soft tissues, and bone resorption [17].
- The metacarpophalangeal joint is the most common site of involvement in the rheumatoid hand [17].
- The metacarpophalangeal and proximal interphalangeal joints of the hand are typically involved early in rheumatoid arthritis [17].
Classification
- Silicone rubber implants are the most frequently used device for treatment of revised metacarpophalangeal arthroplasty [17].
- The nonconstrained implant design for the MCP joint can have good outcomes and excellent arc of motion in osteoarthritis patients [8].
- Pyrocarbon implants were designed as a resurfacing implant for the MCP joint [28].
- A radiographic classification system was modified to differentiate stable implant migration patterns (grade 2) from unstable patterns (grade 3) based on cortical breach status [28].
- In a radiographic analysis of 37 pyrocarbon arthroplasties, 34 (92%) were determined to be stable at last follow-up [28].
- Three (7%) pyrocarbon implants became unstable from migration, all involving grade 3 implant loosening [28].
- Evidence of implant subsidence greater than 1 mm occurred in 6 (16%) of 37 pyrocarbon implants [28].
- Postoperative ulnar deviation greater than 10° occurred in 8 (22%) fingers following pyrocarbon arthroplasty [28].
- Implant fractures in silicone MCP arthroplasty are determined based on criteria including lucent lines, fragmentation, translation greater than one-half the diameter of the bone, and dislocation defined as proximodistal overlap more than one-half the width of the midportion of the implant [20].
- Coronal plane deviation greater than 45° is an additional criterion for determining implant fracture or instability in silicone MCP arthroplasty [20].
Clinical Presentation
Indications and Etiology
- Metacarpophalangeal joint arthroplasty is most often performed in patients with rheumatoid arthritis, although it is occasionally performed for joints affected by osteoarthritis [17].
- Dorsal capsule interpositional arthroplasty provides a viable surgical option for isolated degenerative or traumatic arthritis of the MCPJ [3].
- Metacarpophalangeal joint arthroplasty continues to play a central role in the management of the rheumatoid hand [15].
Patient Expectations and Motivation
Functional Outcomes and Range of Motion
- Silastic interposition arthroplasty of the MCPJ is reliable in terms of pain relief and correction of deformity, and patient satisfaction is high despite only modest improvements in the objective assessment of hand function [6].
- Pain ratings and MCP arc of motion significantly improved following arthroplasty for noninflammatory arthritis [10].
- Implant arthroplasty of the PIP, MCP, and TMC joints predictably produces pain relief and high satisfaction but has historically suffered from high rates of complications [24].
- This study showed improved range of motion and DASH score, excellent pain relief, and excellent patient satisfaction in patients undergoing MCP arthroplasty for nonrheumatic arthritis [30].
- Swanson arthroplasty frequently results in a range of flexion of the MP joint of the little finger that may be insufficient for its principal functions [19].
Complications and Complications Management
- Revision MCP arthroplasty is a challenging procedure with one in five patients requiring a revision procedure at 5 years and a relatively high rate of postoperative dislocations [2].
- The treatment of MCP joint arthroplasty dislocation with revision to silicone implant appears to hold the most promise in achieving a stable MCP joint after an acute prosthetic dislocation [4].
- Increasing MCP joint flexion range was associated with increased fractures of the implants in silicone metacarpophalangeal joint arthroplasty for patients with rheumatoid arthritis [7].
- If squeaking is associated with pain and swelling, revision MCP joint arthroplasty is recommended to identify and correct the underlying cause, such as implant subsidence or an incongruous joint [53].
- An articulating spacer allows movement of the joint and reduces the chance of immobilisation associated complications such as bone loss, joint stiffness, and soft tissue contracture in the management of infected MCPJ arthroplasties [13].
Investigations
- A careful physical examination is essential to direct care and future testing if indicated [27].
- Diagnostic tests such as imaging and serum laboratory studies are useful in determining pathology but can be expensive, time consuming, and often nonspecific [27].
Treatment
Indications and Patient Expectations
- MCP joint arthroplasty is most often performed in patients with rheumatoid arthritis, though it is occasionally performed for osteoarthritis [17].
- The MCP joint is the most common site of involvement in the rheumatoid hand [17].
- MCP joint arthroplasty continues to play a central role in the management of the rheumatoid hand [15].
- Given improvements in the medical management of rheumatoid disease, the indications for and long-term expectations of silicone metacarpophalangeal arthroplasty must be carefully examined [50].
Implant Types and Outcomes
- Both NeuFlex and Swanson implant groups obtained satisfactory clinical improvement after MCP reconstruction of the hand [12].
- Pain ratings and MCP arc of motion significantly improved following surface replacement arthroplasty in metacarpophalangeal joints affected by noninflammatory arthritis [10].
- Good pain relief, a functional range of motion, and high satisfaction were seen in the majority of patients undergoing pyrocarbon metacarpophalangeal joint arthroplasty for noninflammatory arthritis [31].
- Silicone arthroplasty for nonrheumatic metacarpophalangeal joint arthritis showed improved range of motion and DASH score, excellent pain relief, and excellent patient satisfaction [30].
- Follow-up studies show that MCP arthroplasty improves function and deformity and achieves nearly uniform patient satisfaction [17].
Alternative Techniques
- Limited clinical follow-up in a perichondrium transplant group showed reasonably good, and in some cases excellent, results several decades after the surgery, especially at the MCP level [16].
- Arthrodesis has been the gold standard in treating isolated end-stage MP arthritis, whether inflammatory or post-traumatic arthropathies [32].
- Arthrodesis is able to provide effective pain relief as well as restore stability to the joint, even in the setting of severe arthritis [32].
- The key to why MP fusion in the thumb is so successful lies in the relatively negligible loss of motion that results from MP fusion [32].
- By fusing the MP joint between 20 and 40° of flexion, stress can be relieved from the CMC joint by minimizing the activity required at the CMC for thumb opposition [32].
Complications and Revision
- Metallosis is a potential long-term complication of grommets in silicone MCP joint arthroplasty, and given the lack of documented benefit from grommets, the authors recommend against their use [52].
- Static spacers with consequent immobilisation can lead to bone loss, joint stiffness and soft tissue contracture, often causing significant complications at reimplantation [13].
- An articulating spacer allows movement of the joint and reduces the chance of immobilisation associated complications [13].
- An articulated spacer technique can be considered as an option to maintain motion while treating infected MCPJ arthroplasties and the co-morbidity resulting from immobilisation of the whole hand [13].
Specific Clinical Scenarios
Complications
Dislocation and Instability
- Revision MCP arthroplasty is associated with a relatively high rate of postoperative dislocations [2].
- Treatment of acute MCP joint arthroplasty dislocation with revision to a silicone implant appears to hold the most promise in achieving a stable MCP joint [4].
- In a cohort of 37 cases, acute prosthetic dislocation was managed with revision surgery [4].
Implant Fracture and Failure
- One in five patients undergoing revision MCP arthroplasty required a revision procedure at 5 years [2].
- Increasing MCP joint flexion range was associated with increased fractures of silicone implants in patients with rheumatoid arthritis [7].
- In a longitudinal analysis of 325 cases, implant fractures were determined based on criteria including lucent lines, fragmentation, translation greater than one-half the diameter of the bone, and dislocation defined as proximodistal overlap more than one-half the width of the midportion of the implant [20].
- In a study of 40 silicone implants for MCP osteoarthritis, radiographs demonstrated fractured implants in 5 of 40 (12.5%) implants, although none of these patients had clinical instability, pain, or deterioration in range of motion [33].
- For the Neuflex silicone implant, survivorship at 7 years was 88% when revision was the end point, but dropped to 68% when implant fracture was the end point [56].
- In a study of pyrocarbon arthroplasty for rheumatoid arthritis, complication and overall reoperation rates were high, with 1 in 10 patients undergoing revision within 5 years postoperatively [57].
- Patients with greater hand function preoperatively may be at higher risk of revision surgery after silicone MCP arthroplasty for inflammatory arthritis [18].
Infection
- Periprosthetic joint infection (PJI) is uncommon after MCP or PIP arthroplasties [9].
- Management of infected MCP joint replacements can involve removing the prosthesis and inserting gentamycin-loaded bone cement balls for 3 weeks before a final exchange operation [13].
- Static spacers used in MCPJ infection management can lead to bone loss, joint stiffness, and soft tissue contracture, often causing significant complications at reimplantation [13].
- An articulating spacer allows movement of the joint and reduces the chance of immobilization-associated complications compared to static spacers [13].
Other Complications
- Intraoperative periprosthetic fractures are associated with metacarpophalangeal joint arthroplasty [21].
- Swanson arthroplasty frequently results in a range of flexion of the MCP joint of the little finger that may be insufficient for its principal functions [19].
- In a study of pyrocarbon arthroplasty for osteoarthritis, postoperative ulnar deviation greater than 10° occurred in 8 (22%) fingers [28].
- In a study of pyrocarbon arthroplasty for osteoarthritis, 3 (7%) implants became unstable from migration, all with grade 3 implant loosening [28].
- Evidence of implant subsidence greater than 1 mm occurred in 6 (16%) of 37 pyrocarbon implants, but no implants studied at more than 1 year after surgery demonstrated progressive subsidence resulting in implant instability [28].
- Implant arthroplasty of the MCP joint has historically suffered from high rates of complications [24].
Recovery
Functional Outcomes and Patient Satisfaction
- MCP joint arthroplasty improves appearance, pain, and function from a patient-centered perspective [5].
- Silastic interposition arthroplasty of the MCPJ is reliable for pain relief and correction of deformity [6].
- Patient satisfaction is high following Silastic interposition arthroplasty despite only modest improvements in the objective assessment of hand function [6].
- The HAPY spherical pyrocarbon interposition arthroplasty for the metacarpophalangeal joint demonstrates satisfactory short- to mid-term outcomes with considerable improvements in pain relief and joint mobility [59].
Complications and Revision
Patient Expectations and Indications
Specialized Scenarios
Key Evidence
- [L4] MCP joint arthroplasty was performed safely in the setting of acute complex open MCP joint trauma. [1] (10.1016/j.jhsa.2015.09.012)
- [L4] Revision MCP arthroplasty is a challenging procedure with one in five patients requiring a revision procedure at 5 years and a relatively high rate of postoperative dislocations. [2] (10.5435/jaaos-d-17-00042)
- [L4] This technique of dorsal capsule interposition arthroplasty provides a viable surgical option for isolated degenerative or traumatic arthritis of the MCPJ at an average follow-up of 2 years. [3] (10.1177/1558944720911215)
- [L4] The treatment of MCP joint arthroplasty dislocation with revision to silicone implant appears to hold the most promise in achieving a stable MCP joint after an acute prosthetic dislocation. [4] (10.1016/j.jhsa.2017.10.001)
- [L4] MCP joint arthroplasty is an effective treatment option from a patient-centered perspective, improving appearance, pain, and function. [5] (10.1016/j.hcl.2006.02.001)
- [L4] Silastic interposition arthroplasty of the MCPJ is reliable in terms of pain relief and correction of deformity, and patient satisfaction is high despite only modest improvements in the objective assessment of hand function. [6] (10.1054/jhsb.2000.0402)
- [L4] Increasing MCP joint flexion range was associated with increased fractures of the implants. [7] (10.1016/j.jhsa.2020.09.002)
- [L5] The nonconstrained implant design for the MCP joint can have good outcomes and excellent arc of motion in OA patients. [8] (10.1016/j.jhsa.2012.11.025)
- [L4] PJI is uncommon after MCP or PIP arthroplasties. [9] (10.1016/j.jhsa.2024.12.008)
- [L4] Pain ratings and MCP arc of motion significantly improved following arthroplasty. [10] (10.1177/15589447211028917)
- [L1] Patient expectations of MCP joint arthroplasty were uniformly high, with functional improvement being the greatest motivation for surgery. [11] (10.1016/j.jhsa.2011.02.002)
- [L1] Both implant groups obtained satisfactory clinical improvement after MCP reconstruction of the hand. [12] (10.1016/j.jhsa.2009.09.020)
- [L5] [13] (10.1177/17531934251323067)
- [L4] Joint goal-setting is essential for understanding patients' unique reasons for undergoing MCP arthroplasty and facilitating realistic expectations. [14] (10.1002/msc.1061)
- [L5] Metacarpophalangeal joint arthroplasty continues to play a central role in the management of the rheumatoid hand. [15] (10.1177/17531934261430139)
- [L3] [16] (10.1186/s12891-020-03687-3)
- [L5] [17] (10.5435/00124635-200305000-00005)
- [L3] Patients with greater hand function preoperatively may be at higher risk of revision surgery. [18] (10.1177/1558944719831236)
- [L4] Our experience with this cohort, a review of published literature, and a survey of international experts suggest that Swanson arthroplasty frequently results in a range of flexion of the MP joint of the little finger that may be insufficient for its principal functions. [19] (10.1007/s11552-007-9051-5)
- [L4] [20] (10.1177/1753193418778461)
- [L3] [21] (10.1016/j.jhsa.2014.12.038)
- [L4] Implant arthroplasty of the PIP, MCP, and TMC joints predictably produces pain relief and high satisfaction but has historically suffered from high rates of complications. [24] (10.1016/j.jhsa.2017.07.030)
- [L4] The evidence regarding MCP arthroplasty for OA consists of retrospective cohorts with small sample sizes and relatively short evaluations. [26] (10.1016/j.jhsa.2015.05.019)
- [L4] [28] (10.1016/j.jhsa.2022.08.013)
- [L3] This study showed improved range of motion and DASH score, excellent pain relief, and excellent patient satisfaction in patients undergoing MCP arthroplasty for nonrheumatic arthritis. [30] (10.1016/j.jhsa.2013.09.016)
- [L4] Good pain relief, a functional range of motion, and high satisfaction were seen in the majority of patients. [31] (10.1016/j.jhsa.2015.06.104)
- [L5] [32] (10.1016/j.hcl.2006.02.010)
- [L4] [33] (10.1016/j.jhsa.2017.10.010)
- [L4] Volar and proximal translation of the proximal phalange was observed on 4-dimensional computed tomography. [48] (10.1016/j.jhsa.2021.10.001)
- [L4] Given these findings, the indications for and long-term expectations of silicone metacarpophalangeal arthroplasty must be carefully examined in light of the improvements in the medical management of rheumatoid disease. [50] (10.2106/00004623-200310000-00001)
- [Case_report] Metallosis is a potential long-term complication of grommets in silicone MCP joint arthroplasty, and given the lack of documented benefit from grommets, the authors recommend against their use. [52] (10.1007/s11552-012-9401-9)
- [L5] If squeaking is associated with pain and swelling, revision MCP joint arthroplasty is recommended to identify and correct the underlying cause, such as implant subsidence or an incongruous joint. [53] (10.1016/j.jhsg.2022.10.002)
- [L4] [56] (10.1177/1753193408094437)
- [L4] Complication and overall reoperation rates were high, while 1 in 10 undergo revision within 5 years postoperatively. [57] (10.1177/15589447211063577)
- [L4] The HAPY spherical pyrocarbon interposition arthroplasty for the metacarpophalangeal joint demonstrates satisfactory short- to mid-term outcomes, with considerable improvements in pain relief and joint mobility. [59] (10.1016/j.jhsg.2025.100804)
References
[1] Metacarpophalangeal Joint Arthroplasty in the Setting of Trauma. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.09.012
[2] Revision Metacarpophalangeal Arthroplasty: A Longitudinal Study of 128 Cases. Journal of the American Academy of Orthopaedic Surgeons. 2019. DOI: 10.5435/jaaos-d-17-00042
[3] Dorsal Capsule Interpositional Arthroplasty of the Metacarpophalangeal Joint. HAND. 2020. DOI: 10.1177/1558944720911215
[4] Outcomes Following Acute Metacarpophalangeal Joint Arthroplasty Dislocation: An Analysis of 37 Cases. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2017.10.001
[5] Rheumatoid Arthritis: Silicone Metacarpophalangeal Joint Arthroplasty Indications, Technique, and Outcomes. Hand Clinics. 2006. DOI: 10.1016/j.hcl.2006.02.001
[6] Outcome Measures Following Metacarpophalangeal Joint Replacement. Journal of Hand Surgery. 2000. DOI: 10.1054/jhsb.2000.0402
[7] Risk Factors Contributing to Early Implant Fracture in Silicone Metacarpophalangeal Joint Arthroplasty for Patients With Rheumatoid Arthritis. The Journal of Hand Surgery. 2021. DOI: 10.1016/j.jhsa.2020.09.002
[8] Clinical and Radiographic Outcomes of Metacarpophalangeal Joint Pyrolytic Carbon Arthroplasty for Osteoarthritis. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2012.11.025
[9] Incidence and Presentation of Periprosthetic Joint Infection After Primary Metacarpophalangeal and Proximal Interphalangeal Arthroplasty. The Journal of Hand Surgery. 2025. DOI: 10.1016/j.jhsa.2024.12.008
[10] Outcomes of Surface Replacement Arthroplasty in Metacarpophalangeal Joints Affected by Noninflammatory Arthritis. HAND. 2021. DOI: 10.1177/15589447211028917
[11] Hand Appearance as a Patient Motivation for Surgery and a Determinant of Satisfaction with Metacarpophalangeal Joint Arthroplasty for Rheumatoid Arthritis. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2011.02.002
[12] NeuFlex and Swanson Metacarpophalangeal Implants for Rheumatoid Arthritis: Prospective Randomized, Controlled Clinical Trial. The Journal of Hand Surgery. 2010. DOI: 10.1016/j.jhsa.2009.09.020
[13] Management of an infected metacarpophalangeal joint replacement with a temporary articulated cement spacer. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934251323067
[14] Patients' Expectations, Experiences and the Determinants of Satisfaction related to Metacarpophalangeal Arthroplasty. Musculoskeletal Care. 2013. DOI: 10.1002/msc.1061
[15] Balancing metacarpophalangeal joint arthroplasty in rheumatoid arthritis. Journal of Hand Surgery (European Volume). 2026. DOI: 10.1177/17531934261430139
[16] Two-component surface replacement implants compared with perichondrium transplantation for restoration of Metacarpophalangeal and proximal Interphalangeal joints: a retrospective cohort study with a mean follow-up time of 6 respectively 26 years. BMC Musculoskeletal Disorders. 2020. DOI: 10.1186/s12891-020-03687-3
[17] Metacarpophalangeal Joint Arthroplasty in Rheumatoid Arthritis. Journal of the American Academy of Orthopaedic Surgeons. 2003. DOI: 10.5435/00124635-200305000-00005
[18] Factors Associated With Reoperation After Silicone Metacarpophalangeal Joint Arthroplasty in Patients With Inflammatory Arthritis. HAND. 2019. DOI: 10.1177/1558944719831236
[19] Insufficient Flexion of the Metacarpophalangeal Joint of the Little Finger Following Swanson Silicone Arthroplasty for Rheumatoid Arthritis. HAND. 2007. DOI: 10.1007/s11552-007-9051-5
[20] Long-term outcomes of silicone metacarpophalangeal arthroplasty: a longitudinal analysis of 325 cases. Journal of Hand Surgery (European Volume). 2018. DOI: 10.1177/1753193418778461
[21] Intraoperative Periprosthetic Fractures Associated With Metacarpophalangeal Joint Arthroplasty. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.12.038
[24] Implant Arthroplasty for Proximal Interphalangeal, Metacarpophalangeal, and Trapeziometacarpal Joint Degeneration. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.07.030
[26] Metacarpophalangeal Arthroplasty for Osteoarthritis. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.05.019
[27] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[28] Metacarpophalangeal Joint Pyrocarbon Arthroplasty for Osteoarthritis: An Analysis of 44 Arthroplasties. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2022.08.013
[30] Silicone Arthroplasty for Nonrheumatic Metacarpophalangeal Joint Arthritis. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2013.09.016
[31] Pyrocarbon Metacarpophalangeal Joint Arthroplasty in Noninflammatory Arthritis: Minimum 5-Year Follow-Up. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.06.104
[32] Thumb Metacarpophalangeal Arthritis: Arthroplasty or Fusion?. Hand Clinics. 2006. DOI: 10.1016/j.hcl.2006.02.010
[33] Silicone Metacarpophalangeal Arthroplasty for Osteoarthritis: Long-Term Results. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2017.10.010
[36] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[39] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[48] In Vivo Metacarpophalangeal Joint Kinematics After Silicone Implant Arthroplasty in Patients With Rheumatoid Arthritis. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2021.10.001
[50] METACARPOPHALANGEAL JOINT ARTHROPLASTY IN RHEUMATOID ARTHRITIS. The Journal of Bone and Joint Surgery-American Volume. 2003. DOI: 10.2106/00004623-200310000-00001
[52] Metallosis Following Silicone Metacarpophalangeal Joint Arthroplasties with Grommets: Case Report. HAND. 2012. DOI: 10.1007/s11552-012-9401-9
[53] A Painful, Squeaking Pyrolytic Carbon Metacarpophalangeal Joint Replacement. Journal of Hand Surgery Global Online. 2023. DOI: 10.1016/j.jhsg.2022.10.002
[56] Survivorship of the Neuflex Silicone Implant in MCP Joint Replacement. Journal of Hand Surgery (European Volume). 2009. DOI: 10.1177/1753193408094437
[57] Outcomes of Pyrocarbon Arthroplasty in Metacarpophalangeal Joints Affected by Rheumatoid Arthritis. HAND. 2022. DOI: 10.1177/15589447211063577
[59] Functional Outcomes of Spherical Pyrocarbon HAPY Metacarpophalangeal Interposition Arthroplasty for Long Fingers: A Retrospective Study of 16 Cases. Journal of Hand Surgery Global Online. 2025. DOI: 10.1016/j.jhsg.2025.100804