Patients › Rehabilitation
انگوٹھے کی جڑ کے جوڑ کی تبدیلی (Touch)
آرتھرائٹس سے متاثرہ انگوٹھے کی جڑ کے جوڑ کی ڈوئل موبیلیٹی مکمل تبدیلی (Touch امپلانٹ) کے بعد صحت یابی کا مرحلہ وار منصوبہ: شروع میں انگوٹھے کے اسپلنٹ میں نئے جوڑ کی حفاظت، پھر انگوٹھے کو انگلیوں سے ملانے اور حرکت کی بحالی، اور پھر چٹکی کی گرفت اور گرفت کی طاقت بڑھانا۔

یہ پروٹوکول انگوٹھے کی جڑ کے آرتھرائٹس (جوڑ کی خرابی اور سوزش) کے لیے انگوٹھے کی جڑ کے جوڑ کی تبدیلی (ڈوئل موبیلیٹی مکمل جوڑ کی تبدیلی، یعنی Touch امپلانٹ) کے بعد آپ کی صحت یابی میں رہنمائی کرتا ہے، اور یہ آپریشن ڈاکٹر کیرن ہِرپرا Mater Private Hospital Rockhampton میں کرتے ہیں۔ یہ صفحہ گھر پر کی جانے والی آپ کی ورزشوں کے پروگرام سے شروع ہوتا ہے، اور اس کے بعد وہ منظم طبی پروٹوکول آتا ہے جو آپ کے ہینڈ تھراپسٹ (ہاتھ کی بحالی کے ماہر) کے لیے لکھا گیا ہے؛ تھراپی کے پہلے دورے پر یہ صفحہ یا اس کی پی ڈی ایف ساتھ لے کر جائیں تاکہ آپ کی بحالی کا علاج مربوط رہے۔ آپ کی صحت یابی کس طرح آگے بڑھتی ہے، اس کے مطابق آپ کا ہینڈ تھراپسٹ اس منصوبے میں تبدیلی کر سکتا ہے۔ آپ کی پوری صحت یابی باقاعدہ ہینڈ تھراپی کے ذریعے کروائی جاتی ہے۔
اگر سرجری کے بعد آپ کو اپنے زخم کے بارے میں کوئی تشویش ہو تو کلینک سے رابطہ کریں۔ اکثر یہ مددگار ہوتا ہے کہ زخم کی تصویر لے کر جائزے کے لیے ای میل کر دیں۔
کیا توقع رکھیں
آپ کے انگوٹھے کی جڑ کا جوڑ (ٹریپیزیومیٹاکارپل یا سی ایم سی جوڑ، trapeziometacarpal / CMC joint) وہ جگہ ہے جہاں انگوٹھا کلائی سے ملتا ہے، اور یہ آرتھرائٹس ہونے کی ایک بہت عام جگہ ہے۔ اس آپریشن میں جوڑ کی گھسی ہوئی سطحیں نکال دی جاتی ہیں اور ان کی جگہ ایک چھوٹا مصنوعی جوڑ لگا دیا جاتا ہے: ایک ڈوئل موبیلیٹی امپلانٹ (dual-mobility implant)، یعنی ایک ننھا سا گیند اور پیالے والا جوڑ جس میں حرکت کرنے والی ایک اضافی سطح ہوتی ہے جو اسے مستحکم اور ہموار بناتی ہے۔ ٹریپیزیم ہڈی (trapezium) باقی رکھی جاتی ہے اور آپ کے انگوٹھے کی لمبائی برقرار رہتی ہے، اس لیے صحت یابی عام طور پر ٹریپیزیکٹومی (trapeziectomy) سے زیادہ تیز ہوتی ہے (یہ پرانا آپریشن ہے جس میں ایک ہڈی نکال دی جاتی ہے اور جو کئی مہینوں میں زخم بھرنے سے بننے والے سخت ریشے (scar tissue) کے بننے پر انحصار کرتا ہے)۔
اچھی طرح اپنی جگہ بیٹھا ہوا امپلانٹ (جسم میں لگایا گیا مصنوعی پرزہ) شروع سے ہی مستحکم ہوتا ہے اور بوجھ میں حصہ لے سکتا ہے، اسی لیے انگوٹھے کو ہفتوں تک بالکل بے حرکت رکھنے کے بجائے صرف تھوڑے عرصے کے لیے حفاظت کی ضرورت ہوتی ہے۔ منصوبہ یہ ہے کہ پہلے نرم بافتوں کو سنبھلنے دیا جائے، پھر جلد ہی آپ کے انگوٹھے کو دوبارہ انگلیوں سے ملانے (opposition، یعنی انگلیوں کو چھونا) اور حرکت کرنے کے قابل بنایا جائے، اور پھر طاقت بڑھائی جائے۔
صحت یابی تین مرحلوں میں ہوتی ہے:
- پہلے، حفاظت (تقریباً پہلے 2 سے 3 ہفتے)۔ تقریباً پہلے ہفتے کے لیے ایک نرم، موٹی پٹی، اور پھر نئے جوڑ کو آرام دینے کے لیے انگوٹھے کا اسپلنٹ، جب تک زخم اور نرم بافتیں سنبھل نہ جائیں۔ آپ اپنی انگلیوں، کلائی اور ہاتھ کے باقی حصے کو حرکت دیتے رہتے ہیں۔
- پھر، حرکت (تقریباً 2 سے 3 ہفتوں سے 6 ہفتوں تک)۔ دن کے اسپلنٹ سے باہر آ کر، آپ ہلکی، اپنی طاقت سے حرکت شروع کرتے ہیں (انگوٹھے کو انگلیوں سے ملانا، انگوٹھے کو اوپر اٹھانا، انگوٹھے اور شہادت کی انگلی کے درمیان کی جلد (web space) کو کھولنا اور انگوٹھے کو گول گھمانا) اور ہاتھ کو روزمرہ کے ہلکے کاموں کے لیے استعمال کرتے ہیں۔
- پھر، طاقت بڑھانا (6 ہفتوں کے بعد سے)۔ جب امپلانٹ ہڈی سے جڑ جاتا ہے تو چٹکی کی گرفت اور گرفت کو مضبوط کرنے کی ورزشیں شروع ہوتی ہیں اور آہستہ آہستہ بڑھائی جاتی ہیں۔ اگلے 6 سے 12 ماہ تک طاقت بہتر ہوتی رہتی ہے۔
شروع میں جس ایک بات کا خیال رکھنا ہے وہ یہ ہے کہ اگر ارد گرد کی بافتوں کے بھرنے سے پہلے نئے جوڑ کو زبردستی کسی انتہائی حالت میں لے جایا جائے تو وہ اپنی جگہ سے نکل سکتا ہے (dislocation)۔ ایسا کم ہوتا ہے، اور شروع کا منصوبہ اسی بات پر بنا ہے کہ جب تک انگوٹھا سنبھل نہ جائے اس پر زور نہ ڈالا جائے۔
احتیاطیں اور پابندیاں
- اپنا انگوٹھے کا اسپلنٹ ہدایت کے مطابق پہنیں (پہلے 2 سے 3 ہفتوں کے لیے دن کا اسپلنٹ، پھر 6 ہفتوں تک رات کا اسپلنٹ) اور حفاظت کے لیے اسپلنٹ اس وقت تک پہنے رکھیں جب تک آپ کا ہینڈ تھراپسٹ آپ کو اگلے مرحلے میں نہ لے جائے۔
- انگوٹھے کو زبردستی انتہائی حالتوں میں ہرگز نہ لے جائیں، اور شروع کے ہفتوں میں اچانک یا بے ڈھنگے طریقے سے چیزیں جھپٹنے سے پرہیز کریں؛ اگر نیا جوڑ سنبھلنے سے پہلے بہت زیادہ دبایا جائے تو وہ اپنی جگہ سے نکل سکتا ہے۔ صرف اتنی حرکت کریں جتنی آرام سے ہو سکے۔
- تقریباً 6 ہفتوں تک ہرگز نہ زور سے چٹکی بھریں، نہ زور سے گرفت کریں، نہ مروڑنے والے کام کریں (برتنوں کے ڈھکن، چابیاں، نلکے) اور نہ کوئی چیز اٹھائیں؛ طاقت بڑھانے کی ورزشیں صرف اس وقت شروع ہوتی ہیں جب آپ کا ہینڈ تھراپسٹ انہیں شروع کرائے۔
- شروع سے ہی اپنی انگلیوں، کلائی اور ہاتھ کے باقی حصے کو حرکت دیتے رہیں، اور سوجن کم کرنے کے لیے شروع میں اپنا ہاتھ اونچا رکھیں (دل کی سطح سے اوپر)۔
- تقریباً چار سے چھ ہفتوں تک گاڑی ہرگز نہ چلائیں، یعنی جب تک آپ اسپلنٹ سے باہر نہ آ جائیں اور اسٹیئرنگ کو آرام سے اور بغیر درد کے پکڑ نہ سکیں۔
زخم، سوجن اور زخم کے نشان کی دیکھ بھال کے لیے کلینک کی زخم کی دیکھ بھال سے متعلق رہنمائی دیکھیں۔
آپ کی ورزشیں

Kieran Hirpara 4.0
انگوٹھے کو انگلیوں سے ملانا (کپانجی سیڑھی، Kapandji ladder)
آہستہ سے اپنے انگوٹھے کا سرا شہادت کی انگلی کے پہلو سے لگائیں، پھر باری باری ہر انگلی کے سرے سے، اور پھر اسے چھوٹی انگلی کے ساتھ ساتھ اس کی جڑ کی طرف نیچے لے جائیں — جیسے جیسے انگوٹھا کھلتا جائے، 'سیڑھی' پر تھوڑا اور آگے چڑھیں۔ صرف اتنا حرکت کریں جتنا آرام سے ہو سکے۔ انگوٹھے کی جڑ کی تبدیلی کے بعد بحال کی جانے والی یہ سب سے اہم حرکت ہے، اور یہ دن کے اسپلنٹ سے باہر آنے کے بعد (تقریباً دو سے تین ہفتوں پر) آہستگی سے شروع کی جاتی ہے۔
آرام کی حد کے اندر، دن میں 2 سے 3 مرتبہ، سیڑھی کو 5 سے 10 بار مکمل کریں
Kieran Hirpara 4.0
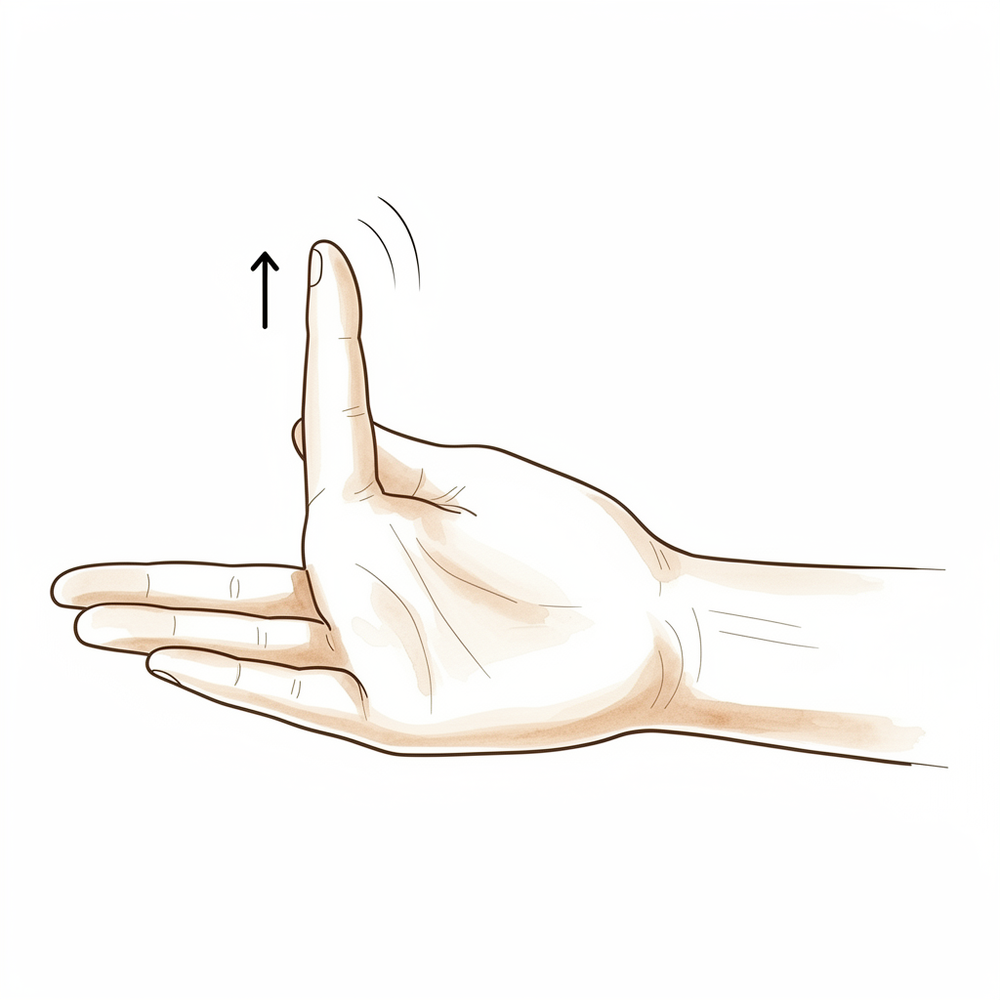
انگوٹھے کو ہتھیلی سے اوپر اٹھانا (palmar abduction)
اپنا ہاتھ ہتھیلی اوپر کر کے چپٹا رکھیں۔ انگوٹھے کو سیدھا رکھتے ہوئے اسے ہتھیلی سے دور چھت کی طرف اٹھائیں، جیسے آپ کوئی ڈبہ (کین) پکڑنے کے لیے ہاتھ کھول رہے ہوں — پھر اسے واپس نیچے لے آئیں۔ اس سے انگوٹھے اور شہادت کی انگلی کے درمیان کی جلد کھلتی ہے اور انگوٹھے کی پہنچ بحال ہوتی ہے۔ اسے ہلکا اور بغیر زور کے رکھیں؛ شروع کے ہفتوں میں حرکت کی آخری حد تک زور نہ لگائیں۔
10 بار، دن میں 2 سے 3 مرتبہ، آرام کی حد کے اندر
Kieran Hirpara 4.0
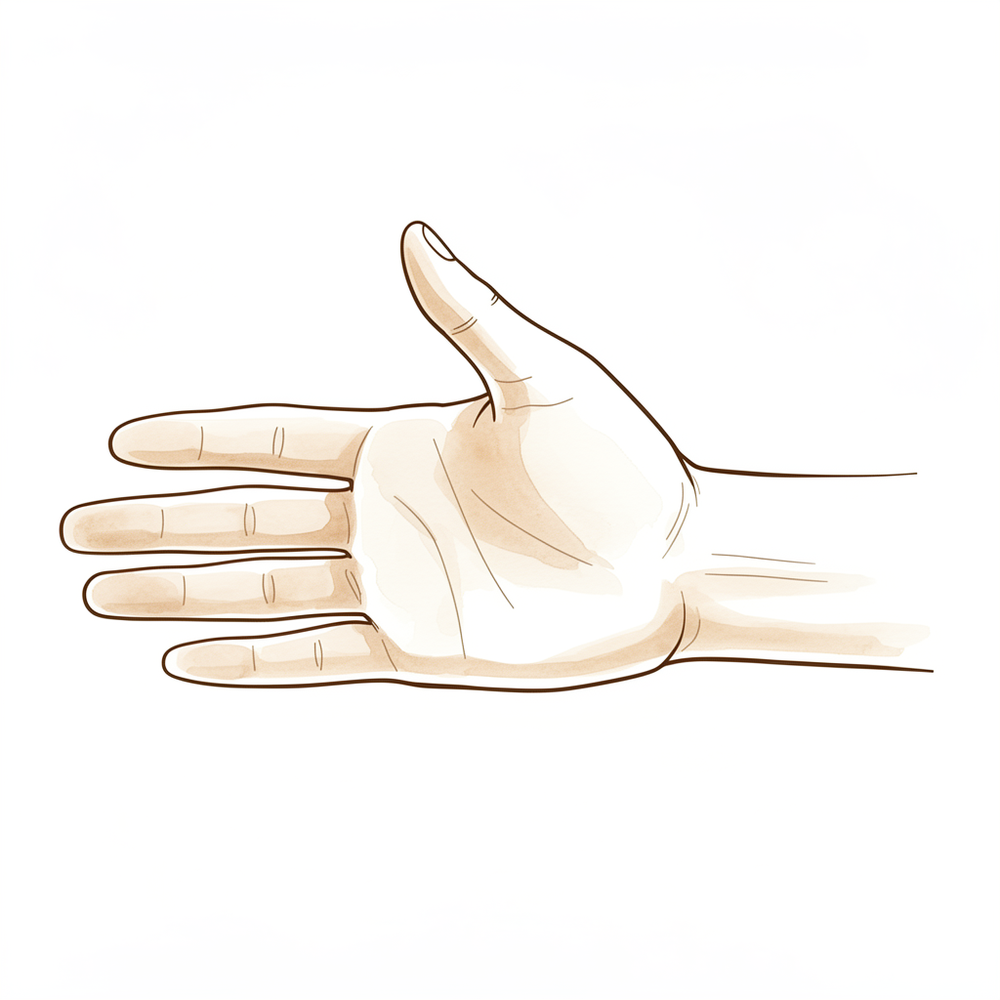
انگوٹھے کو ایک طرف لے جانا (radial abduction)
اپنا ہاتھ ہتھیلی نیچے کر کے چپٹا رکھیں۔ انگوٹھے کو ہتھیلی کی ہی سیدھ میں رکھتے ہوئے اسے شہادت کی انگلی سے دور ایک طرف کھسکائیں — جیسے 'L' کی شکل بنا رہے ہوں — پھر واپس لے آئیں۔ اس سے انگوٹھے کی ایک طرف کی پہنچ بحال ہوتی ہے۔ آہستہ حرکت کریں اور کسی بھی کھنچاؤ سے پہلے رک جائیں۔
10 بار، دن میں 2 سے 3 مرتبہ، آرام کی حد کے اندر
Kieran Hirpara 4.0
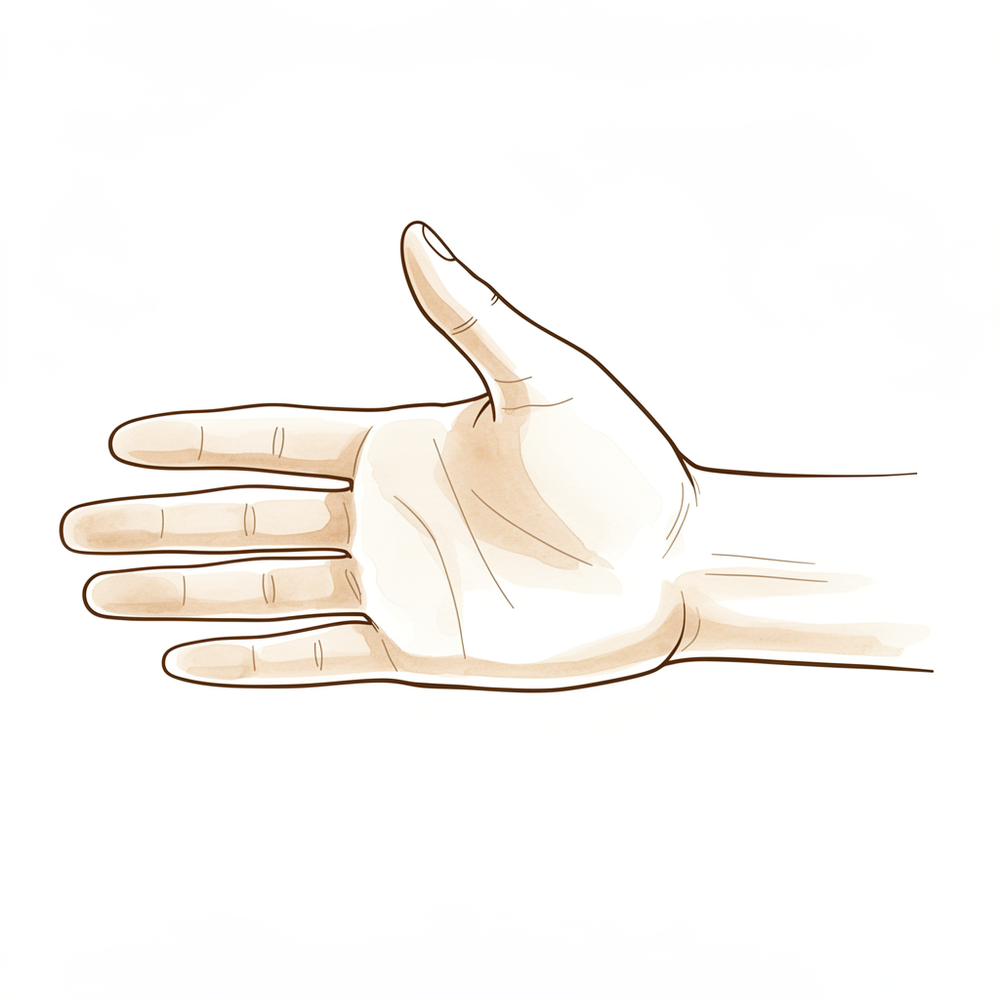
انگوٹھے اور شہادت کی انگلی کے درمیان کی جلد کا اسٹریچ (web-space stretch)
انگوٹھے اور شہادت کی انگلی کے درمیان کی جگہ کو جتنا آرام سے ہو سکے کھولیں، اور اس جلد میں ہلکا سا کھنچاؤ محسوس کریں۔ آپ اپنا ہاتھ میز پر رکھ کر انگوٹھے کو آہستہ سے کھلنے دے سکتے ہیں، یا اسے کسی گول چیز کے گرد رکھ سکتے ہیں۔ کھلی حالت کو تھوڑی دیر رکھیں، پھر ڈھیلا چھوڑ دیں۔ اس سے زخم بھرنے کے دوران یہ جلد سکڑتی نہیں — اسے ہلکا رکھیں، کبھی زبردستی نہ کریں۔
تقریباً 5 سیکنڈ تک رکھیں، 5 سے 10 بار، دن میں 2 سے 3 مرتبہ
Kieran Hirpara 4.0
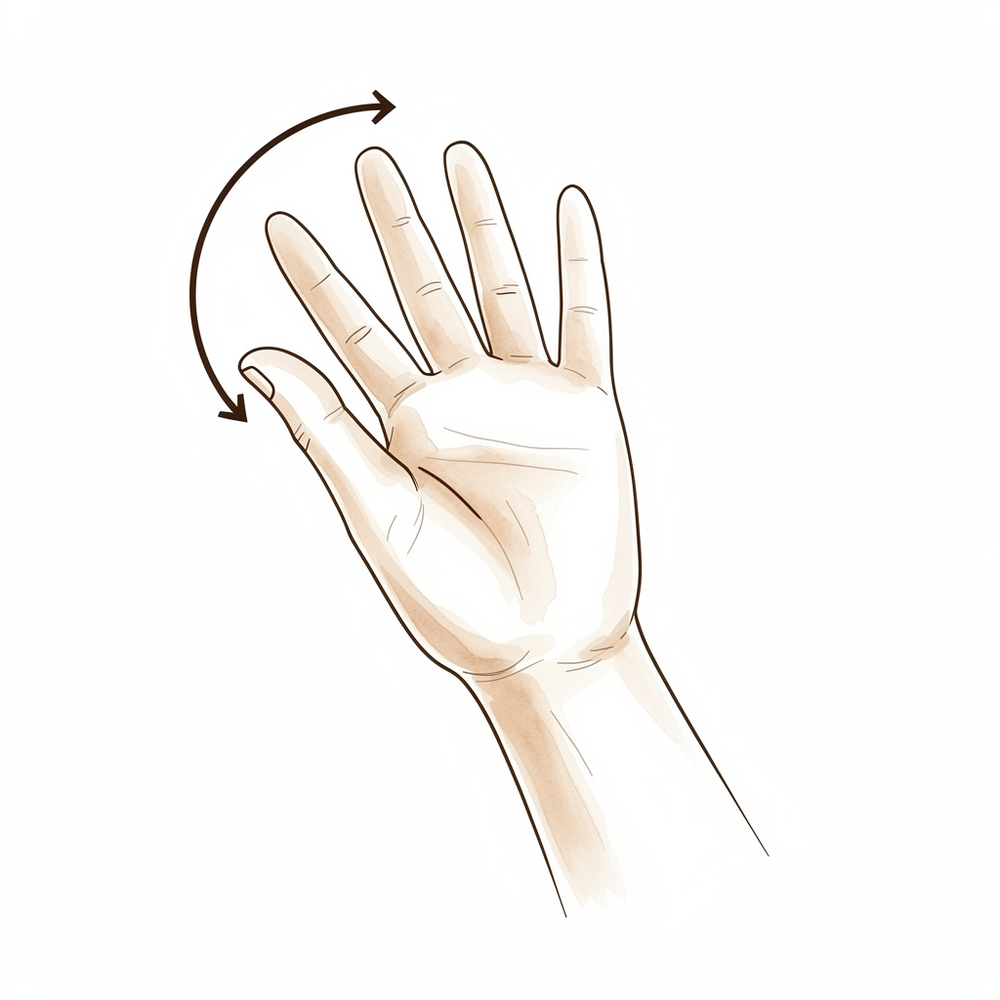
انگوٹھے کو گول گھمانا (circumduction)
ہاتھ کو ڈھیلا رکھ کر، انگوٹھے سے آہستہ اور ہموار دائرے بنائیں، اسے دونوں سمتوں میں اس کی پوری حد میں آہستگی سے گھمائیں — جیسے کسی چھوٹی دیگچی میں چمچ چلا رہے ہوں۔ دائرے آسان اور آرام کی حد کے اندر رکھیں۔ اس سے نئے جوڑ کی ملی جلی، گھومنے والی حرکت بحال ہوتی ہے، اور یہ دن کے اسپلنٹ سے باہر آنے کے بعد آہستگی سے شروع کی جاتی ہے۔
ہر سمت میں 5 سے 10 دائرے، دن میں 2 سے 3 مرتبہ
Kieran Hirpara 4.0
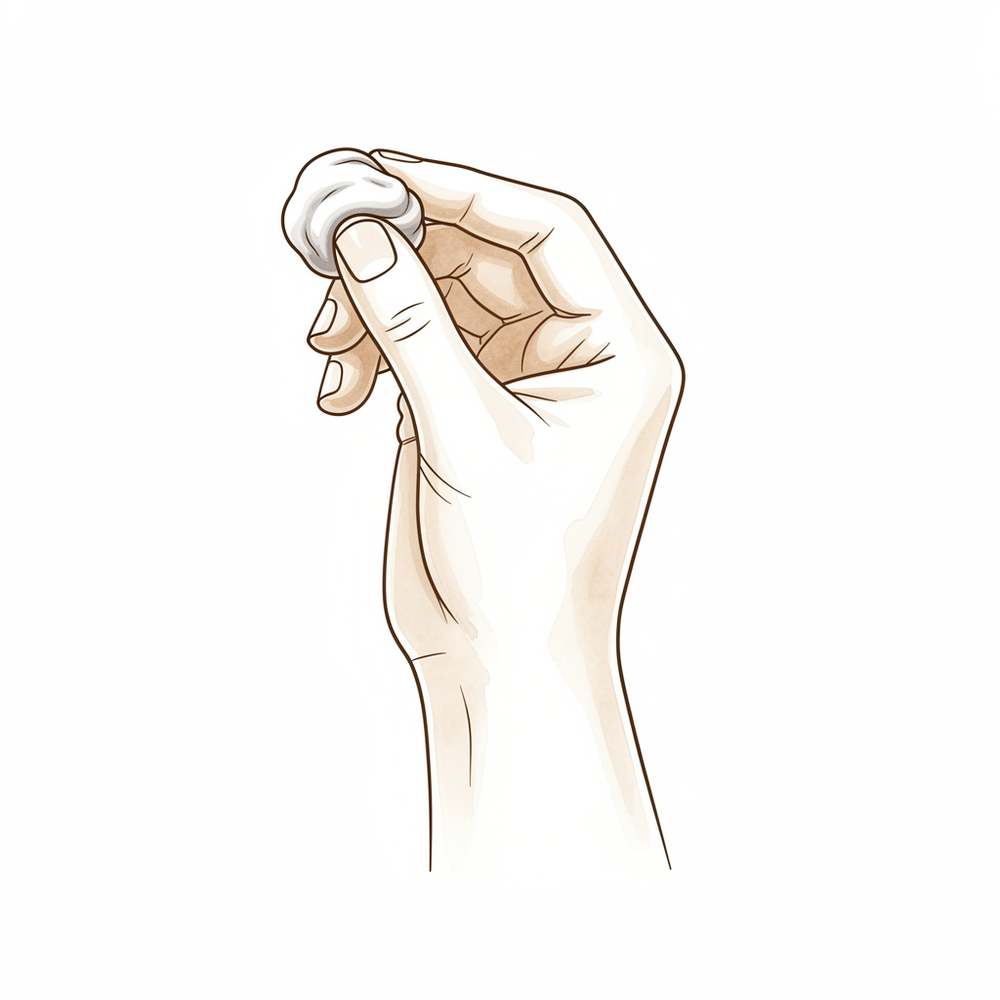
پُٹی / چابی والی چٹکی (ہفتہ 6 سے)
یہ بعد والی ورزش ہے — صرف تقریباً چھ ہفتوں کے بعد، جب آپ کا ہینڈ تھراپسٹ طاقت بڑھانے کی ورزشیں شروع کرائے۔ تھراپی والی پُٹی (therapy putty، ورزش کے لیے نرم لچکدار مادہ) کا ایک ٹکڑا انگوٹھے اور شہادت کی انگلی کے پہلو کے درمیان دبائیں ('چابی' والی چٹکی)، اور انگوٹھے کا سرا انگلیوں کے سروں پر دبائیں ('سرے' والی چٹکی)، اور اگلے ہفتوں اور مہینوں میں زور آہستہ آہستہ بڑھائیں۔ چھ ہفتوں سے پہلے ہرگز نہ زور سے چٹکی بھریں اور نہ زور سے گرفت کریں — نئے جوڑ کو سنبھلنے اور ہڈی سے جڑنے کے لیے اتنا وقت درکار ہے۔
اپنے ہینڈ تھراپسٹ کی رہنمائی کے مطابق (تقریباً 6 ہفتوں سے)، آہستہ آہستہ بڑھائیں
یہ آپ کے ہینڈ آؤٹ کی ورزشیں ہیں۔ انہیں صرف ڈاکٹر ہِرپرا اور اپنے ہینڈ تھراپسٹ کی رہنمائی کے مطابق شروع کریں، اور جو بھی حد اور پابندیاں آپ کو بتائی گئی ہیں ان کے اندر رہیں۔ شروع کی ورزشیں (انگوٹھے کو انگلیوں سے ملانا، انگوٹھے کو اوپر اٹھانا، انگوٹھے کو ایک طرف لے جانا، انگوٹھے اور شہادت کی انگلی کے درمیان کی جلد کا اسٹریچ اور ہلکے گول دائرے) نئے جوڑ پر بوجھ ڈالے بغیر انگوٹھے کی حرکت بحال کرتی ہیں، اور دن کے اسپلنٹ سے باہر آنے کے بعد شروع ہوتی ہیں۔ پُٹی اور چابی والی چٹکی (putty and key pinch) طاقت بڑھانے کی ایک بعد والی ورزش ہے اور اسے تقریباً چھ ہفتوں سے پہلے شروع نہیں کرنا چاہیے، جب آپ کا ہینڈ تھراپسٹ اسے شروع کرائے۔ شروع کے ہفتوں میں ہر حرکت ہلکی اور بغیر زور کے رکھیں، اور جس حرکت سے انگوٹھے کی جڑ میں تیز درد ہو، اسے روک دیں۔
آپ کا طبی پروٹوکول
اس صفحے کا باقی حصہ ڈوئل موبیلیٹی ٹریپیزیومیٹاکارپل (Touch) مکمل جوڑ کی تبدیلی کے بعد بحالی کا مرحلہ وار طبی پروٹوکول ہے۔ یہ حصہ آپ کے ہینڈ تھراپسٹ کو دیا جانا ہے، اور ہر مرحلہ عام فہم زبان میں اس وضاحت سے شروع ہوتا ہے کہ اس دوران کیا ہو رہا ہے۔ ٹریپیزیکٹومی کے برعکس، امپلانٹ فوراً مستحکم ہوتا ہے اور بوجھ میں حصہ لیتا ہے، اس لیے بے حرکت رکھنے کی مدت بہت کم ہوتی ہے اور انگوٹھے کو اپنی طاقت سے انگلیوں سے ملانے کی حرکت جلد بحال کی جاتی ہے؛ اس امپلانٹ سے مخصوص شروع کا خطرہ انتہائی حد تک زبردستی لے جانے پر جوڑ کا اپنی جگہ سے نکل جانا ہے، اس لیے پہلے ہفتوں میں حرکت بحال کرتے ہوئے زبردستی یا حرکت کی آخری حد والی حالتوں سے بچایا جاتا ہے، اور پھر امپلانٹ کے ہڈی سے جڑ جانے (osseointegration) کے بعد بوجھ کے ساتھ طاقت بڑھانے کی طرف بڑھا جاتا ہے۔
علاج سے پہلے مریض کی آپریشن رپورٹ اور پچھلی طبی تاریخ دیکھیں، اور امپلانٹ کے بیٹھنے/استحکام اور آپریشن کے دوران کسی بھی تشویش کے بارے میں علاج کرنے والے سرجن سے رابطہ کریں۔ ڈاکٹر ہِرپرا کا طریقۂ علاج یہ ہے: 7 سے 10 دن تک نرم، موٹی پٹی، پھر 2 سے 3 ہفتوں تک انگوٹھے کا دن کے وقت والا اسپلنٹ (thumb spica DAY splint)، اور اس کے بعد 6 ہفتوں تک رات کا اسپلنٹ (NIGHT splint) جاری رہتا ہے (کلائی سیدھی حالت میں، انگوٹھا ہتھیلی سے درمیانے فاصلے پر (mid palmar abduction)، انگوٹھے کا آئی پی جوڑ آزاد)۔ ٹریپیزیم ہڈی باقی رکھی جاتی ہے اور انگوٹھے کی لمبائی برقرار رہتی ہے۔
مرحلہ I — حفاظت (ہفتہ 0 سے تقریباً 2 سے 3)
پہلے چند ہفتوں میں نرم بافتیں سنبھلتی ہیں اور نئے جوڑ کی حفاظت کی جاتی ہے۔ انگوٹھا ایک نرم، موٹی پٹی میں اور پھر انگوٹھے کے دن والے اسپلنٹ میں آرام کرتا ہے، جبکہ انگلیاں، کلائی اور ہاتھ کا باقی حصہ حرکت کرتے رہتے ہیں۔ انگوٹھے سے مزاحمت کے خلاف کوئی کام نہیں، اور انگوٹھے کی کوئی زبردستی یا انتہائی حالت نہیں (شروع میں جوڑ کا اپنی جگہ سے نکل جانا اس امپلانٹ سے مخصوص خطرہ ہے)۔
آپ کے ہینڈ تھراپسٹ کے لیے:
تعلیم اور احتیاطیں - انگوٹھے کی جڑ کو بے حرکت رکھیں: 7 سے 10 دن نرم، موٹی پٹی، پھر تقریباً 2 سے 3 ہفتوں تک انگوٹھے کا دن کا اسپلنٹ (thumb spica DAY splint) (کلائی سیدھی حالت میں، انگوٹھا ہتھیلی سے درمیانے فاصلے پر، انگوٹھے کا آئی پی جوڑ آزاد) - انگوٹھے کو زبردستی یا انتہائی حالتوں میں لے جانے سے اور اچانک چیزیں پکڑنے سے پرہیز کریں: جوڑ کا اپنی جگہ سے نکل جانا اس امپلانٹ سے مخصوص شروع کا خطرہ ہے - انگوٹھے سے مزاحمت کے خلاف کوئی کام نہیں (نہ چٹکی، نہ گرفت، نہ مروڑنا اور نہ کچھ اٹھانا) - امپلانٹ پر بوجھ نہ ڈالیں؛ ہاتھ کا صرف ہلکا، بغیر بوجھ کے استعمال
علاج کا طریقہ - زخم: ہدایت کے مطابق آپریشن والی پٹیاں؛ انفیکشن پر نظر رکھیں - سوجن (oedema): ہاتھ اونچا رکھنا، ہاتھ کو ہلکے سے پمپ کرنا، ضرورت کے مطابق برف - ورزشیں: انگوٹھے کے آئی پی جوڑ (IP joint)، انگلیوں اور کلائی کی اپنی طاقت سے حرکت کی حد (active ROM)؛ پورے ہاتھ کی حرکت برقرار رکھیں؛ ابھی سی ایم سی جوڑ کی اپنی طاقت سے حرکت یا انگوٹھے کو انگلیوں سے ملانے کی ورزش نہیں، اور کوئی بوجھ نہیں
اگلے مرحلے میں جانے کی شرائط - زخم سنبھل رہا ہو؛ مریض آرام میں ہو؛ تقریباً 2 سے 3 ہفتوں پر اپنی طاقت سے حرکت کے لیے دن کے اسپلنٹ سے باہر
مرحلہ II — رات کے اسپلنٹ کے ساتھ اپنی طاقت سے حرکت (تقریباً ہفتہ 2 سے 3 سے لے کر ہفتہ 6 تک)
تقریباً دو سے تین ہفتوں سے دن کا اسپلنٹ اتر جاتا ہے اور انگوٹھے کی ہلکی، اپنی طاقت سے حرکت شروع ہوتی ہے: انگوٹھے کو انگلیوں سے ملانا (کپانجی (Kapandji) طریقے سے بتدریج)، انگوٹھے کو ہتھیلی سے اوپر اور ایک طرف لے جانا (palmar and radial abduction)، ہلکے گول دائرے (circumduction) اور انگوٹھے اور شہادت کی انگلی کے درمیان کی جلد کو ڈھیلا کرنا۔ رات کا اسپلنٹ چھ ہفتوں تک جاری رہتا ہے۔ روزمرہ کے ہلکے استعمال کی حوصلہ افزائی کی جاتی ہے؛ زور کی گرفت اور چٹکی اب بھی روکی جاتی ہے۔
آپ کے ہینڈ تھراپسٹ کے لیے:
جانچ - انگوٹھے کو اپنی طاقت سے انگلیوں سے ملانا (کپانجی اسکور)، ہتھیلی سے اوپر اور ایک طرف لے جانا، انگوٹھے اور شہادت کی انگلی کے درمیان کے فاصلے کی چوڑائی؛ درد اور سوجن؛ زخم اور زخم کے نشان کا جائزہ
تعلیم اور احتیاطیں - دن کا اسپلنٹ ختم؛ رات کا اسپلنٹ 6 ہفتوں تک جاری رکھیں - انگوٹھے کی صرف اپنی طاقت سے، بغیر مزاحمت کے حرکت: 6 ہفتوں سے پہلے زور کی گرفت یا چٹکی نہیں - حرکت آرام کی حد کے اندر رکھیں؛ حرکت کی آخری حد تک زبردستی لے جانے سے پرہیز کریں
علاج کا طریقہ - ورزشیں: اپنی طاقت سے، بغیر مزاحمت کے انگوٹھے کو انگلیوں سے ملانا (کپانجی طریقے سے بتدریج)، ہتھیلی سے اوپر اور ایک طرف لے جانا، ہلکے گول دائرے، انگوٹھے اور شہادت کی انگلی کے درمیان کی جلد کو ڈھیلا کرنا؛ ہاتھ کا روزمرہ ہلکا استعمال؛ زخم بھرنے کے بعد زخم کے نشان کی مالش شروع کریں
اگلے مرحلے میں جانے کی شرائط - انگوٹھے کو انگلیوں سے ملانے کی اچھی حرکت بحال ہو چکی ہو؛ زخم بھر چکا ہو؛ تقریباً 6 ہفتوں پر بغیر مزاحمت کے حرکت بغیر درد کے ہو
مرحلہ III — بوجھ ڈالنا اور طاقت بڑھانا (ہفتہ 6 اور اس کے بعد)
تقریباً چھ ہفتوں سے امپلانٹ ہڈی سے جڑ چکا ہوتا ہے اور اس پر بوجھ ڈالا جا سکتا ہے۔ چٹکی کی گرفت اور گرفت کو مضبوط کرنے کی ورزشیں شروع ہوتی ہیں (پُٹی کو چٹکی سے دبانا، چابی والی اور سرے والی چٹکی، انگوٹھے کو انگلیوں سے ملانے کی طاقت) اور آہستہ آہستہ بڑھائی جاتی ہیں۔ اگلے 6 سے 12 ماہ تک طاقت پختہ ہوتی رہتی ہے۔
آپ کے ہینڈ تھراپسٹ کے لیے:
جانچ - دوسرے ہاتھ کے مقابلے میں چابی والی اور سرے والی چٹکی اور گرفت کی طاقت؛ انگوٹھے کو انگلیوں سے ملانا؛ بوجھ ڈالنے پر درد اور سوجن کا ردِعمل؛ مناسب ہو تو روزمرہ کاموں اور کام سے متعلق جانچ
تعلیم اور احتیاطیں - 6 ہفتوں سے چٹکی اور گرفت کو بتدریج مضبوط کرنے کی ورزشیں شروع کریں؛ بوجھ آہستہ آہستہ بڑھائیں - توقع رکھیں کہ طاقت 6 سے 12 ماہ میں پختہ ہو گی؛ زیادہ بوجھ کے بارے میں صبر سے کام لینے کا مشورہ دیں
علاج کا طریقہ - ورزشیں: پُٹی کو چٹکی سے دبانا، چابی والی اور سرے والی چٹکی، انگوٹھے کو انگلیوں سے ملانے کی طاقت، بتدریج بڑھتی مزاحمت؛ گرفت کو مضبوط کرنا؛ حرکت اور زخم کے نشان سے متعلق باقی رہ جانے والا کام جاری رکھیں - جب طاقت کام کے قابل ہو جائے اور ہاتھ کا کام مناسب حد تک بحال ہو جائے تو علاج ختم کرنے پر غور کریں - اگر صحت یابی رک جائے یا نتیجہ اچھا نہ ہو تو علاج کرنے والے ڈاکٹر کے پاس واپس بھیجنے (referral) پر غور کریں
علاج ختم کرنے کی شرائط - کام کے قابل، دونوں ہاتھوں میں تقریباً برابر چٹکی اور گرفت؛ روزمرہ اور کام سے متعلق استعمال میں درد نہ ہو
کام اور سرگرمیوں پر واپسی
شروع سے ہی آرام کی حد کے اندر ہاتھ کے روزمرہ ہلکے استعمال (کھانا کھانا، لکھنا، اپنی ہلکی دیکھ بھال) کی حوصلہ افزائی کی جاتی ہے، بشرطیکہ اس میں انگوٹھے پر زور ڈالنا یا زور سے چٹکی بھرنا اور گرفت کرنا شامل نہ ہو۔ چونکہ آپ کو اس وقت تک گاڑی ہرگز نہیں چلانی چاہیے جب تک آپ اسپلنٹ سے باہر نہ آ جائیں اور اسٹیئرنگ کو آرام سے پکڑ نہ سکیں، اس لیے شروع کے ہفتوں میں آنے جانے کے لیے مدد کا انتظام کر لیں۔ گاڑی چلانا عام طور پر تقریباً چار سے چھ ہفتوں پر دوبارہ شروع ہوتا ہے، جب آپ اسٹیئرنگ کو بغیر درد کے پکڑ سکیں اور ڈاکٹر ہِرپرا اس کی تصدیق کر دیں۔
دفتری اور ہلکا کام عام طور پر دو سے چار ہفتوں کے اندر ممکن ہوتا ہے؛ جسمانی مشقت والے اور بھاری کام کے لیے تقریباً چھ ہفتے انتظار کرنا پڑتا ہے اور پھر اسے آہستہ آہستہ بڑھایا جاتا ہے، کیونکہ زور کی چٹکی اور گرفت پر بوجھ صرف چھ ہفتوں پر شروع ہوتا ہے۔ طاقت 6 سے 12 ماہ تک بہتر ہوتی رہتی ہے، اس لیے بھاری اور زیادہ مشکل کاموں پر واپسی ایک ساتھ نہیں بلکہ بتدریج ہوتی ہے، اور اس کا فیصلہ صرف کیلنڈر دیکھ کر نہیں بلکہ اس بنیاد پر ڈاکٹر ہِرپرا اور آپ کا ہینڈ تھراپسٹ آپ کے ساتھ مل کر کرتے ہیں کہ آپ کا انگوٹھا کیسا ردِعمل دے رہا ہے۔
آپ کے پروٹوکول کے بعد
یہ پروٹوکول کلینک کے صحت یابی سے متعلق عمومی مشوروں کے ساتھ مل کر کام کرتا ہے؛ آپریشن کے بعد درد پر قابو پانا، زخم کی دیکھ بھال اور زخم کے نشان کی دیکھ بھال دیکھیں۔ اوپر دیا گیا مرحلہ وار منصوبہ ڈوئل موبیلیٹی والی انگوٹھے کی جڑ کے جوڑ کی تبدیلی کے بعد بحالی سے متعلق شائع شدہ رہنمائی کی عکاسی کرتا ہے، اور آپ کی آگے کی صحت یابی میں ڈاکٹر ہِرپرا اور آپ کا ہینڈ تھراپسٹ آپ کے انگوٹھے کی پیش رفت کے مطابق انفرادی طور پر رہنمائی کرتے ہیں۔
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Thumb Base Joint Replacement (Touch) — Procedure Outcomes & Post-operative Rehabilitation (Dual-mobility TMC/CMC Total Joint Arthroplasty)
Topic scope: post-operative rehabilitation after a dual-mobility total joint replacement of the trapeziometacarpal (thumb base / CMC) joint for advanced thumb base osteoarthritis — the Touch implant. Unlike trapeziectomy, the trapezium is retained and thumb length preserved, and a correctly seated dual-mobility implant is immediately stable and load-sharing. The rehab is therefore a minimal-immobilisation, early-motion pathway: protect briefly against the implant-specific early dislocation risk, restore opposition within the first month, then load.
Defining principle of the rehab here: a trapeziectomy relies on a scar/haematoma "spacer" forming where the bone was removed, which takes roughly 12 months to mature — so rehab is slow by necessity. A dual-mobility thumb base replacement instead provides an immediately stable, load-sharing artificial joint, so immobilisation can be minimal, opposition is restored within the first month, and recovery is faster than trapeziectomy. The dual-mobility cup specifically reduces the early dislocation risk that drove longer immobilisation with older single-mobility implants. The one deliberate early restraint is therefore avoidance of forced/extreme thumb positions (the implant-specific dislocation risk) for the first few weeks, after which loaded pinch/grip strengthening begins. This is a newer implant: the evidence base is short-to-mid-term and low-to-moderate level, and rehab regimens are under-reported and not standardised.
A. PROCEDURE OUTCOMES (dual-mobility Touch TMC arthroplasty)
Dual-mobility total joint replacement of the thumb base is a comparatively new alternative to trapeziectomy for advanced trapeziometacarpal osteoarthritis. Early- to mid-term series report high implant survival and good restoration of pinch and function, with the principal trade-off being a higher complication/revision profile than the well-established trapeziectomy — though the dual-mobility design improves on the dislocation rate of earlier single-mobility implants.
- High short-to-mid-term implant survival and good function. A Touch-specific series reported 96% implant survival at 2 years with high key-pinch strength; the main adverse events were soft-tissue complications (de Quervain-type tenosynovitis, trigger digit) rather than implant failure [Herren 2023]. A 150-patient dual-mobility cohort similarly reports early normalisation of function. Moderate (case series / retrospective cohort).
- Faster recovery than trapeziectomy because the joint is immediately stable. Because the implant is load-sharing from the outset, the thumb is only briefly immobilised, patients return to near-normal activity early, and formal therapy may not always be required — contrasting with the ~12-month maturation of a trapeziectomy spacer [Duerinckx & Verstreken 2022]. Moderate (narrative review / cohort).
- Opposition and pinch/grip recover well. Using the MOOVIS dual-mobility implant, the Kapandji opposition score improved from 7 to 10 with improved pinch and grip [Dreant 2018]. Moderate (cohort).
- The dual-mobility design reduces dislocation. The extra articulation lowers the early dislocation risk that limited older single-mobility prostheses, supporting earlier mobilisation [Tchurukdichian 2019; Martins 2020]. Moderate (cohort / mechanistic).
- Lower reoperation than ball-and-socket designs; persistent revision risk overall. A network meta-analysis found dual-mobility implants had lower reoperation than ball-and-socket designs, with TOUCH reoperation around 1.0% [Burnett 2026 NMA]. Reported outcomes continue to evolve in ongoing reviews [Tosti & Duerinckx 2026]. Moderate (NMA of mostly observational data).
- Registry-level work-absence benchmark. Swedish registry data give a sense of real-world recovery: sick leave of roughly 94 days for men and 109 days for women — a benchmark to set realistic return-to-work expectations rather than a target. Moderate (registry).
B. REHABILITATION / THERAPY EVIDENCE
The central rehab questions are (1) how long to immobilise, and (2) when to start motion and loading. Because the implant is immediately stable, the modern answer is minimal immobilisation with early active opposition — but the literature is explicit that there is no consensus and wide variation between centres, and that rehab protocols are under-reported.
- Minimal immobilisation is justified by immediate stability. A correctly seated dual-mobility implant is stable and load-sharing, so prolonged casting is unnecessary; the thumb is briefly protected, then mobilised early, with opposition typically back within the first month [Duerinckx & Verstreken 2022]. Moderate (review).
- No standardised regimen — wide variation in immobilisation and motion timing. A dedicated review of immobilisation and rehabilitation after thumb-base arthroplasty found reported immobilisation ranging from 2 to 12 weeks and active range-of-motion commencing anywhere from 1 to 6 weeks, with no consensus across studies [Barrett 2022]. This is the key caveat for any protocol: the timings are a defensible, surgeon-confirmed plan, not a trial-derived standard. Moderate (systematic review of heterogeneous protocols).
- Early opposition recovery is achievable and is the functional priority. Improvement of the Kapandji opposition score (7→10) demonstrates that active opposition is the early rehab target and is realistically attainable in the first weeks-to-months [Dreant 2018]. Moderate (cohort).
- The early restraint is dislocation avoidance, not protected healing. The dual-mobility design reduces but does not abolish early dislocation; the practical implication is to avoid forced/extreme thumb positions in the first weeks rather than to immobilise for prolonged periods [Tchurukdichian 2019; Martins 2020]. Moderate / mechanistic.
Recovery trajectory (expected, evidence-anchored)
| Phase | Window | Restraint | Hand use / therapy focus | Strength / load | Notes |
|---|---|---|---|---|---|
| I — Protect | Week 0 to ~2–3 | Soft bulky dressing 7–10 d → thumb spica DAY splint | Keep IP/MCP/digits/wrist moving; oedema control; avoid forced/extreme thumb positions | No resisted thumb work | Early dislocation is the implant-specific risk; minimal immobilisation because the implant is immediately stable |
| II — Active motion | Week ~2–3 to 6 | NIGHT splint to 6 wk | Out of day splint; active unresisted opposition (Kapandji), palmar + radial abduction, gentle circumduction, web-space work; light everyday use; scar massage once healed | Still no heavy grip/pinch | Opposition typically restored within the first month; faster than trapeziectomy |
| III — Load / strengthen | Week 6+ | Restrictions lifted | Progress pinch/grip-specific loading and task use | Pinch + grip strengthening from 6 wk (putty, key/tip pinch); full weight-bearing ~6 wk | Strength matures over 6–12 months; return to heavy/manual work staged across this window |
(Phase windows reflect KH-confirmed parameters and are consistent with the wide ranges reported in the literature; they are typical guides, not trial-derived deadlines — see Barrett 2022.)
C. KEY CONTROVERSIES / EVIDENCE QUALITY
- Replacement vs trapeziectomy. Dual-mobility replacement restores the joint and gives a faster functional return (immediate stability, opposition back within a month) versus the ~12-month maturation of a trapeziectomy spacer, but at the cost of a higher complication and revision rate and a shorter evidence track record. Trapeziectomy remains the well-established, lower-risk benchmark. Moderate; trade-off, not a clear winner.
- How long to immobilise / when to start motion. No consensus — reported immobilisation spans 2–12 weeks and AROM start 1–6 weeks [Barrett 2022]. This page's day-splint-2–3-weeks → night-splint-to-6-weeks → strengthen-from-6-weeks plan is a defensible, surgeon-confirmed regimen within that reported range, not a proven standard. Weak–moderate.
- Dislocation risk. The dual-mobility cup reduces the early dislocation that limited older single-mobility implants, but the risk is not zero in the first weeks — hence the early forced/extreme-position restraint [Tchurukdichian 2019; Martins 2020]. Moderate / mechanistic.
- Complication profile. Soft-tissue complications (de Quervain-type tenosynovitis, trigger digit) are the commonest early issues rather than implant failure [Herren 2023]; reoperation is low for dual-mobility (TOUCH ~1.0%) and lower than ball-and-socket designs [Burnett 2026 NMA]. Moderate.
- Maturity of the evidence. This is a newer implant: outcomes are short-to-mid-term, evidence is low-to-moderate level (case series, retrospective cohorts, registry and NMA of mostly observational data), and rehabilitation is under-reported and not standardised. Tone should be appropriately cautious. Evidence base still maturing.
D. EVIDENCE STRENGTH FLAGS (summary)
- MODERATE (cohort / registry / NMA of observational data): high short-to-mid-term implant survival (96% at 2 yr, Touch) with good key-pinch; Kapandji opposition 7→10; dual-mobility lower reoperation than ball-and-socket (TOUCH ~1.0%); registry sick-leave benchmark (~94 d men / 109 d women); faster functional return than trapeziectomy.
- MODERATE (systematic review of heterogeneous protocols): no consensus on rehab — immobilisation 2–12 weeks, AROM start 1–6 weeks (Barrett 2022).
- WEAK / CONSENSUS: the specific immobilisation-then-early-opposition-then-strengthen phase timings (surgeon-confirmed, within the reported range; not trial-derived); the dislocation-avoidance rationale (mechanistic).
- CAVEAT: newer implant — short-to-mid-term, low-to-moderate-level evidence; higher complication/revision rates than trapeziectomy persist; rehab under-reported.
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Duerinckx J, Verstreken F. Dual mobility prosthesis for trapeziometacarpal joint arthritis. EFORT Open Rev. 2022. DOI: 10.1530/eor-22-0027
- Herren DB, et al. Trapeziometacarpal joint replacement with the Touch prosthesis: two-year results. J Hand Surg (Eur Vol). 2023. DOI: 10.1177/17531934231179581
- Dreant N, et al. Trapeziometacarpal arthroplasty with the dual-mobility MOOVIS prosthesis. Hand (NY). 2018. DOI: 10.1177/1558944718797341
- Tchurukdichian A, et al. Dual-mobility implant reduces the dislocation risk in trapeziometacarpal arthroplasty. Hand (NY). 2019. DOI: 10.1177/1558944719855690
- Martins A, et al. Dual-mobility trapeziometacarpal prosthesis. J Hand Surg (Eur Vol). 2020. DOI: 10.1177/1753193420901435
- Barrett H, et al. Immobilization and rehabilitation after trapeziometacarpal joint arthroplasty: a review. J Hand Surg Glob Online. 2022. DOI: 10.1016/j.jhsg.2022.05.011
- Tosti R, Duerinckx J. Trapeziometacarpal total joint arthroplasty: current concepts. J Hand Surg Am. 2026. DOI: 10.1016/j.jhsa.2026.01.003
- Burnett K, et al. Implant designs for trapeziometacarpal arthroplasty: a network meta-analysis of reoperation. J Hand Surg Am. 2026. DOI: 10.1016/j.jhsa.2025.12.011
Thumb base arthroplasty literature (URLs)
- Herren DB, et al. TOUCH trapeziometacarpal prosthesis — two-year results. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC12098211/
- Dual-mobility trapeziometacarpal arthroplasty — 150-patient cohort. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC12662895/
- TOUCH prosthesis case series. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC8470025/
- KeriMedical — TOUCH thumb base prosthesis patient information. https://www.kerimedical.com/en/patients/