Patients › Rehabilitation
اکڑی ہوئی کہنی کی ریلیز (Arthrolysis)
اکڑی ہوئی کہنی کو کھولنے کے آپریشن کے بعد جلد اور بھرپور حرکت پر مبنی صحت یابی کا منصوبہ — سرجن آپریشن کی میز پر ہی کہنی کا موڑنا اور سیدھا ہونا واپس لے آتے ہیں، اور بحالی کا سارا کام اس حرکت کی حد کو برقرار رکھنا ہے، پہلے دن سے، نہ کسی سلنگ کے ساتھ اور نہ کسی حفاظتی مرحلے کے ساتھ۔
یہ پروٹوکول Mater Private Hospital Rockhampton میں ڈاکٹر کیرن ہِرپرا کے ہاتھوں اکڑی ہوئی کہنی کو کھولنے کے آپریشن (ریلیز، یا آرتھرولائسس (arthrolysis)) کے بعد آپ کی صحت یابی میں رہنمائی کرتا ہے۔ اس کا آغاز آپ کے گھریلو ورزشی پروگرام سے ہوتا ہے، جس کے بعد وہ منظم کلینیکل پروٹوکول آتا ہے جو آپ کے فزیوتھراپسٹ یا ہینڈ تھراپسٹ (ہاتھ کی بحالی کے ماہر) کے لیے لکھا گیا ہے؛ یہ صفحہ یا اس کی پی ڈی ایف تھراپی کی اپنی پہلی ملاقات پر ساتھ لے کر جائیں تاکہ آپ کی بحالی کا علاج مربوط رہے۔ آپ کا تھراپسٹ آپ کی صحت یابی کی رفتار کے مطابق منصوبے میں تبدیلی کر سکتا ہے۔
اگر آپریشن کے بعد آپ کو اپنے زخم کے بارے میں کوئی تشویش ہو تو کلینک سے رابطہ کریں۔ اکثر یہ مددگار ہوتا ہے کہ زخم کی تصویر کھینچ کر جائزے کے لیے ای میل کر دیں۔
کیا توقع رکھیں
کسی پرانی چوٹ یا آپریشن کے بعد کہنی اس لیے اکڑ جاتی ہے کہ جوڑ کی اندرونی جھلی (capsule) موٹی اور سخت ہو جاتی ہے، اور بعض اوقات فالتو ہڈی بن جاتی ہے، جس کی وجہ سے کہنی اپنی پوری قوس (arc، یعنی پورا موڑنے سے پورا سیدھا کرنے تک کی حرکت) میں مڑ اور سیدھی نہیں ہو سکتی۔ ریلیز کے آپریشن کے دوران، جو یا تو دوربین کے ذریعے آپریشن (keyhole، arthroscopic) سے کیا جاتا ہے یا کھلے چیرے کے ذریعے، سرجن اس سخت جھلی کو (اور کسی بھی فالتو ہڈی یا پھنسے ہوئے زخم بھرنے سے بننے والے سخت ریشے (scar tissue) کو) نکال دیتے ہیں تاکہ آپریشن کی میز پر ہی کہنی دوبارہ آزادی سے حرکت کرنے لگے۔
سب سے اہم بات جو سمجھنی ہے وہ یہ ہے کہ یہ صحت یابی مرمت والے آپریشن کے بالکل الٹ ہے۔ ایسی کوئی چیز نہیں جسے ٹانکے لگا کر جوڑا یا ٹھیک کیا گیا ہو اور جسے بھرنے کے لیے ہفتوں آرام کی ضرورت ہو۔ اس کے بجائے، سرجن آپریشن کے دوران تقریباً مکمل حرکت کی حد حاصل کر لیتے ہیں، اور آپ کی بحالی کا سارا کام اس حرکت کو برقرار رکھنا ہے، کیونکہ آپریشن کے بعد کہنی کا قدرتی رجحان دوبارہ اکڑ جانے کا ہوتا ہے۔ اسی لیے نہ کوئی سلنگ ہے اور نہ کوئی حفاظتی مرحلہ: آپ پہلے ہی دن سے کہنی کو حرکت دینا شروع کرتے ہیں، اور اسے مضبوطی سے اور بار بار حرکت دیتے ہیں۔ یہاں اصل دشمن دوبارہ اکڑ جانا ہے، کسی ٹشو کا ٹوٹ جانا نہیں۔
زخم، سوجن اور زخم کے نشان کی دیکھ بھال کے لیے پریکٹس کی زخم کی دیکھ بھال سے متعلق رہنمائی دیکھیں۔ ابتدائی دنوں میں سوجن اور درد ہی وہ اہم چیزیں ہیں جو حرکت کو روکتی ہیں، اس لیے اونچا رکھنے، برف اور اپنی درد کش دوا کے ذریعے ان پر قابو رکھنا اپنی حرکت کی حد برقرار رکھنے کا ایک اہم حصہ ہے۔
آپ کی زیادہ تر بہتری تقریباً 6 ہفتے اور 3 ماہ کے درمیان ہوتی ہے، اور کہنی عموماً تقریباً 4 ماہ پر اپنی بہترین، ٹھہری ہوئی حرکت کی حد تک پہنچ جاتی ہے۔ اپنی حرکت کی حد کو برقرار رکھنے بلکہ اس میں اضافہ کرنے کے لیے، رات کو اور آرام کے اوقات میں اسپلنٹ کا ایک پروگرام استعمال کیا جاتا ہے اور اسے کم از کم 3 ماہ تک جاری رکھا جاتا ہے۔
احتیاطیں اور پابندیاں
- ضرور پہلے دن سے کہنی کو حرکت دینا شروع کریں، اور دن بھر تھوڑا تھوڑا اور بار بار حرکت دیتے رہیں: یہی آپ کی صحت یابی کی بنیاد ہے۔
- ضرور ہر اسٹریچ کے آخری سرے میں ہلکے سے زور لگائیں؛ مرمت والے آپریشن کے برعکس، یہاں کوئی جوڑی گئی چیز نہیں جس کی حفاظت کرنی ہو، اس لیے پوری حد تک پہنچنا ہی مقصد ہے۔
- ضرور اونچا رکھنے، برف اور تجویز کردہ درد کش دوا کے ذریعے سوجن اور درد پر قابو رکھیں: آپ کی حرکت کو یہی محدود کرتے ہیں، خود سرجری نہیں۔
- ضرور سوزش کم کرنے والی کوئی بھی دوا (جیسے انڈومیتھاسن (indomethacin)) بالکل تجویز کے مطابق لیں اگر ڈاکٹر ہِرپرا نے فالتو ہڈی بننے سے روکنے کے لیے اسے شروع کیا ہو۔
- ضرور رات/آرام کا اپنا اسپلنٹ ہدایت کے مطابق، کم از کم 3 ماہ تک، پہنیں تاکہ جو حرکت کی حد آپ حاصل کریں وہ برقرار رہے اور اس میں اضافہ ہو۔
- کہنی کو سنبھلنے دینے کے لیے نہ اسے آرام دیں اور نہ ہی "ہاتھ روک کر" چلیں: اسی طرح اکڑاؤ واپس آتا ہے۔
- گھبرائیں نہیں اگر چھوٹی انگلی اور انگوٹھی والی انگلی (ring finger) میں سوئیاں چبھنے جیسا احساس یا جھنجھناہٹ ہو؛ کہنی کے اندرونی حصے کا عصب (النر عصب (ulnar nerve)) کہنی کے موڑ میں بہتری کے ساتھ زیادہ حساس ہو سکتا ہے، اس لیے ڈاکٹر ہِرپرا یا اپنے تھراپسٹ کو بتائیں تاکہ اس کا معائنہ کیا جا سکے۔
آپ کی ورزشیں
Kieran Hirpara 4.0
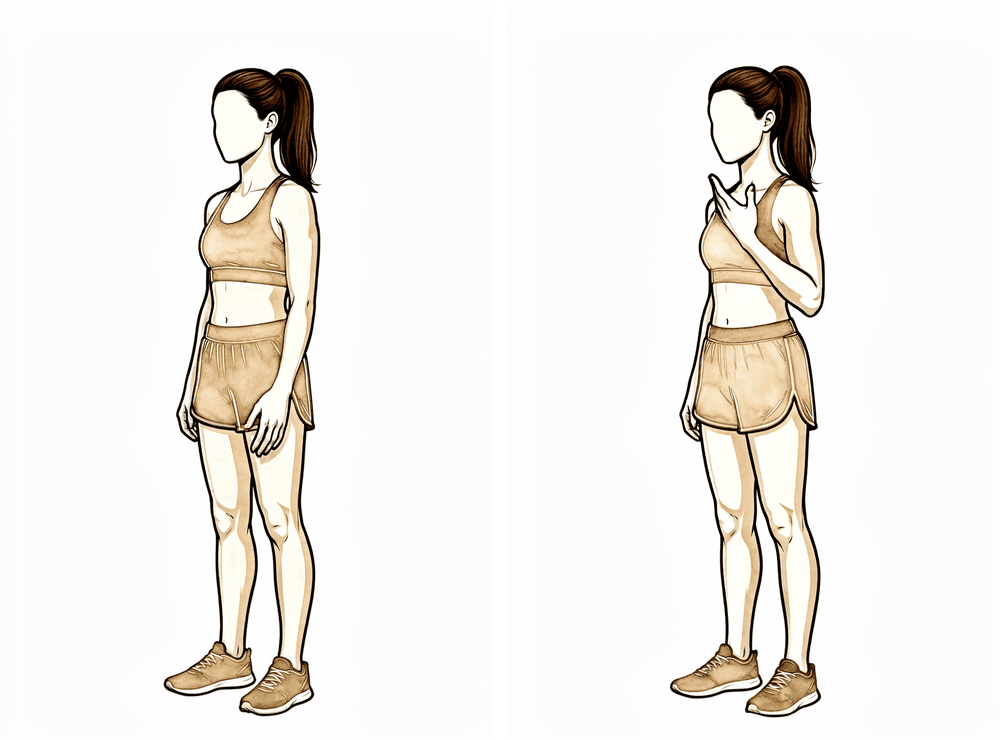
کہنی کو خود موڑنا اور سیدھا کرنا (active elbow bends)
اپنے ہی پٹھوں سے کہنی کو جتنا ہو سکے کندھے کی طرف اوپر موڑیں، پھر اسے جتنا ہو سکے سیدھا کریں۔ حرکت کے ہر سرے پر ہلکے سے زور لگائیں اور وہی حد حاصل کرنے کی کوشش کریں جو سرجن نے آپ کے آپریشن کے دوران حاصل کی تھی۔ یہ سب سے اہم ورزش ہے — کہنی بہت جلد دوبارہ اکڑ جاتی ہے، اس لیے یہ دن بھر تھوڑی تھوڑی اور بار بار کی جاتی ہے۔
ہر سمت میں 10 سے 15 بار، جاگنے کے دوران ہر 1 سے 2 گھنٹے بعد
Kieran Hirpara 4.0
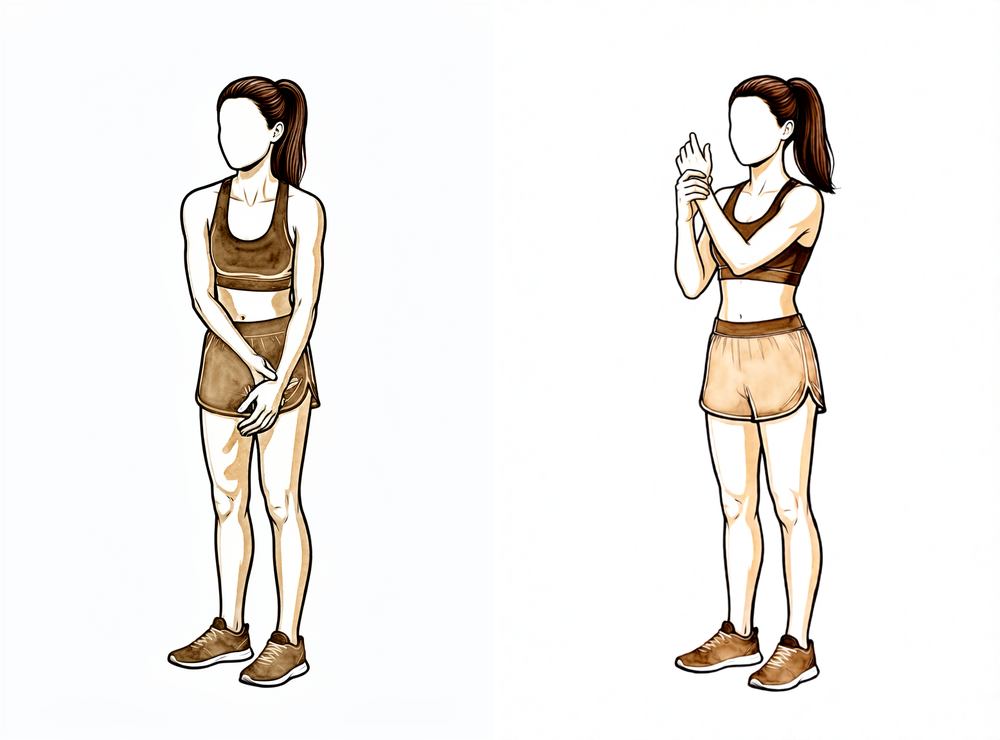
مدد سے (غیر فعال) کہنی موڑنا (passive elbow bend)
آپریشن والے بازو کو پوری طرح ڈھیلا چھوڑ کر، اپنے دوسرے ہاتھ سے کہنی کو ہلکے سے اس سے زیادہ موڑیں جتنا وہ خود مڑتی ہے، اور اس آخری سرے پر روکیں جہاں آپ کو مضبوط کھنچاؤ محسوس ہو۔ حفاظت کے لیے کوئی مرمت نہیں ہے، اس لیے آپ کو ترغیب دی جاتی ہے کہ اسٹریچ میں ہلکے سے زور لگائیں — اسے روکیں، سانس لیں، اور کہنی کو تھوڑا اور آگے جانے دیں۔ تیز درد سے پہلے رک جائیں۔
ہر اسٹریچ 20 سے 30 سیکنڈ روکیں، 3 سے 5 بار، دن میں کئی بار
Kieran Hirpara 4.0
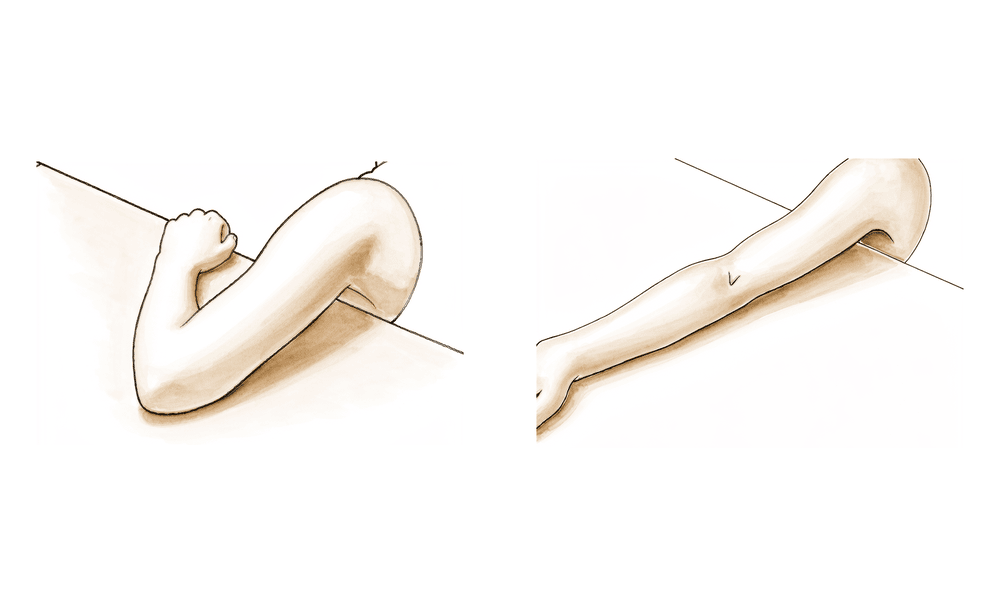
کہنی کو خود سیدھا کرنا (extension)
کہنی کو جتنا ہو سکے سیدھا کرنے پر کام کریں — سیدھا کرنا (extension) وہ حرکت ہے جو سب سے زیادہ ضائع ہوتی ہے، اس لیے اس پر خاص توجہ دی جاتی ہے۔ بازو کے اوپری حصے کی پچھلی طرف کو کسی سخت سطح پر ٹکائیں اور پہلے کشش ثقل کو، پھر اپنے دوسرے ہاتھ کی ہلکی مدد کو، کہنی کو پوری طرح سیدھا ہونے کی طرف لے جانے دیں۔ اسٹریچ کے آخری سرے پر روکیں۔
20 سے 30 سیکنڈ روکیں، 5 بار، دن میں کئی بار
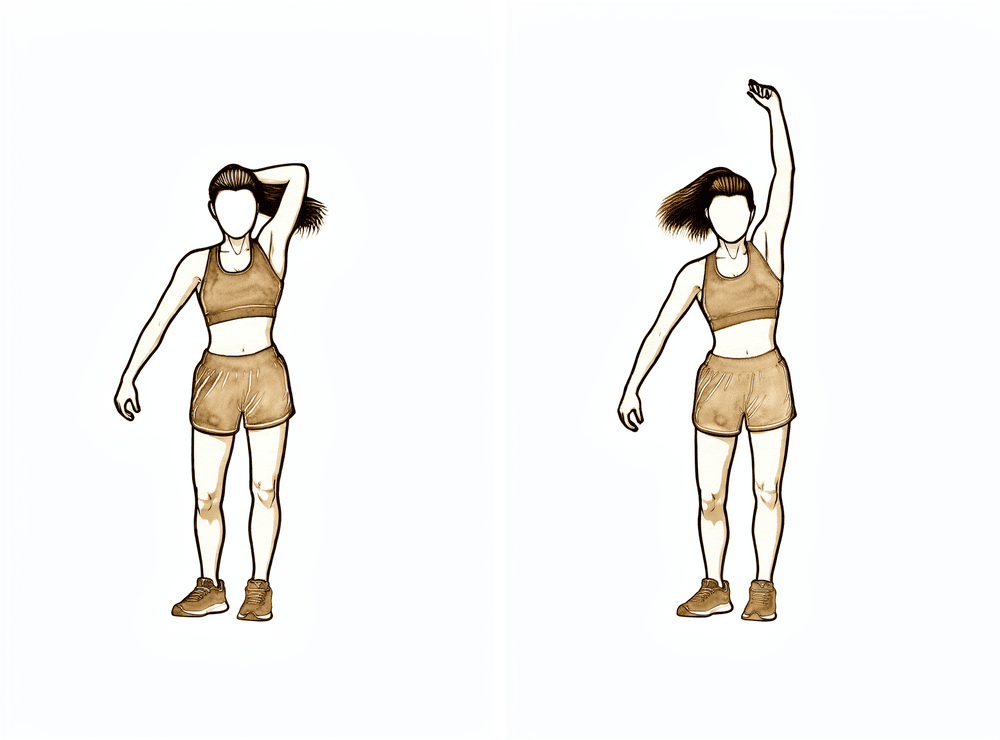
Kieran Hirpara 4.0
سر کے اوپر ٹرائسیپس اسٹریچ (آخری حد تک سیدھا کرنا)
آپریشن والے بازو کو سر کے اوپر اٹھائیں اور اپنے دوسرے ہاتھ سے کہنی کو ہلکے سے پوری طرح سیدھا ہونے کی طرف دھکیلیں، جس سے بازو کے اوپری حصے کی پچھلی طرف کھنچاؤ آئے۔ یہ سیدھا کرنے کی سمت میں آخری حد تک ایک مضبوط اسٹریچ ہے — اسے جھٹکے دینے کے بجائے ٹھہرا کر روکیں۔
20 سے 30 سیکنڈ روکیں، 3 سے 5 بار، دن میں چند بار
Kieran Hirpara 4.0
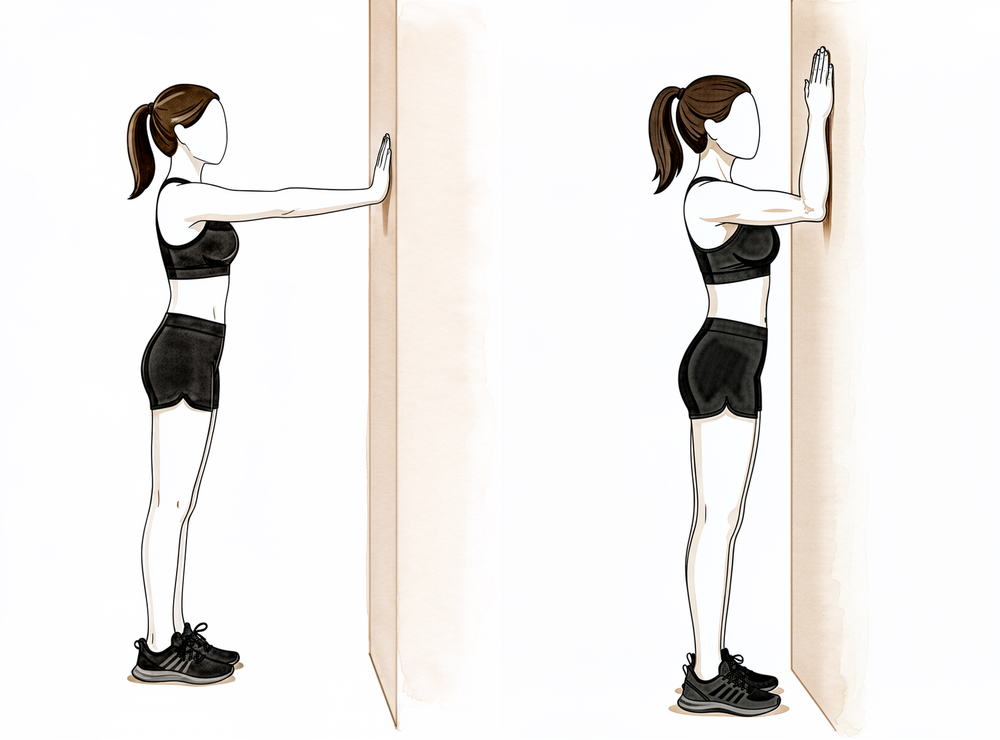
دیوار پر انگلیاں چلا کر کہنی موڑنا (آخری حد تک موڑنا)
دیوار کی طرف منہ کر کے اپنی انگلیوں کو اس پر اوپر چلائیں، اور جیسے جیسے ہاتھ اوپر جائے کہنی کو مزید مڑنے دیں۔ اس وقت تک اوپر جائیں جب تک کہنی کے اندر گہرائی میں مضبوط کھنچاؤ محسوس نہ ہو، روکیں، پھر تھوڑا اور اوپر جائیں۔ اس سے موڑ کا آخری حصہ واپس حاصل کرنے میں مدد ملتی ہے۔
اوپر پہنچ کر 20 سے 30 سیکنڈ روکیں، 5 بار، دن میں چند بار
Kieran Hirpara 4.0
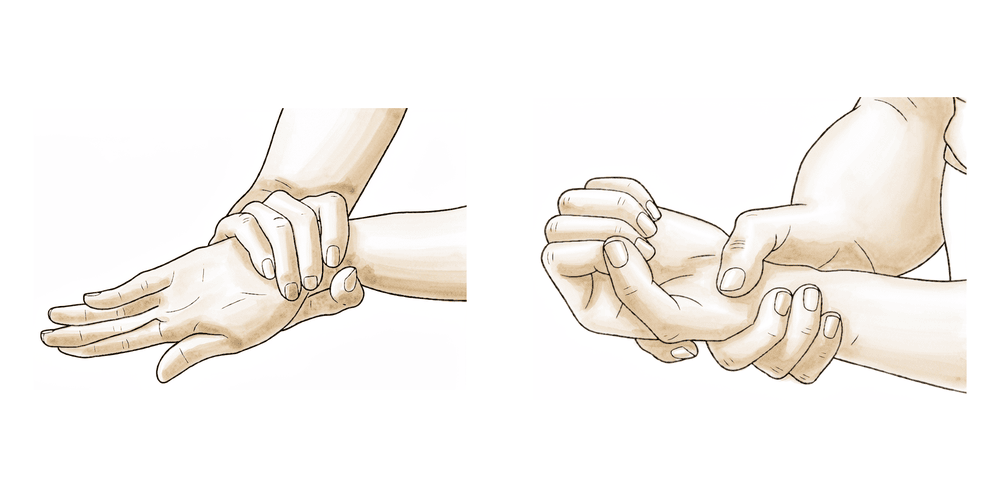
بازو کے نچلے حصے کو گھمانا (ہتھیلی اوپر / ہتھیلی نیچے)
کہنی کو پہلو سے لگا کر اور تقریباً 90 ڈگری پر موڑ کر، ہتھیلی کو اوپر چھت کی طرف گھمائیں، پھر نیچے فرش کی طرف، ہر طرف جتنا ہو سکے۔ ریلیز کا آپریشن اکثر موڑنے کے ساتھ ساتھ گھماؤ کو بھی کھول دیتا ہے، اس لیے موڑنے اور سیدھا کرنے کی ورزش کے ساتھ اسے بھی پوری طرح حرکت میں رکھیں۔ ہر سرے پر تھوڑا اور آگے لے جانے کے لیے آپ اپنے دوسرے ہاتھ سے ہلکا سا دھکیل سکتے ہیں۔
ہر سمت میں 10 سے 15 بار، دن میں کئی بار

Kieran Hirpara 4.0
ٹرائسیپس پٹھے کو کسنا (ہلکی گرفت)
یہ ابتدائی مرحلے میں پٹھے کو فعال کرنے کی ورزش ہے۔ بازو کو سہارا دے کر، بازو کے اوپری حصے کی پچھلی طرف والے پٹھے (ٹرائسیپس (triceps)) کو ہلکے سے کسیں جیسے کہنی کو سیدھا کر رہے ہوں، تاکہ جو سیدھا پن آپ نے حاصل کیا ہے وہ برقرار رہے اور مضبوط ہو۔ اسے ہلکا رکھیں اور اپنے فزیوتھراپسٹ کی رہنمائی کے مطابق کریں۔
تقریباً 5 سیکنڈ روکیں، 5 سے 10 بار، رہنمائی کے مطابق
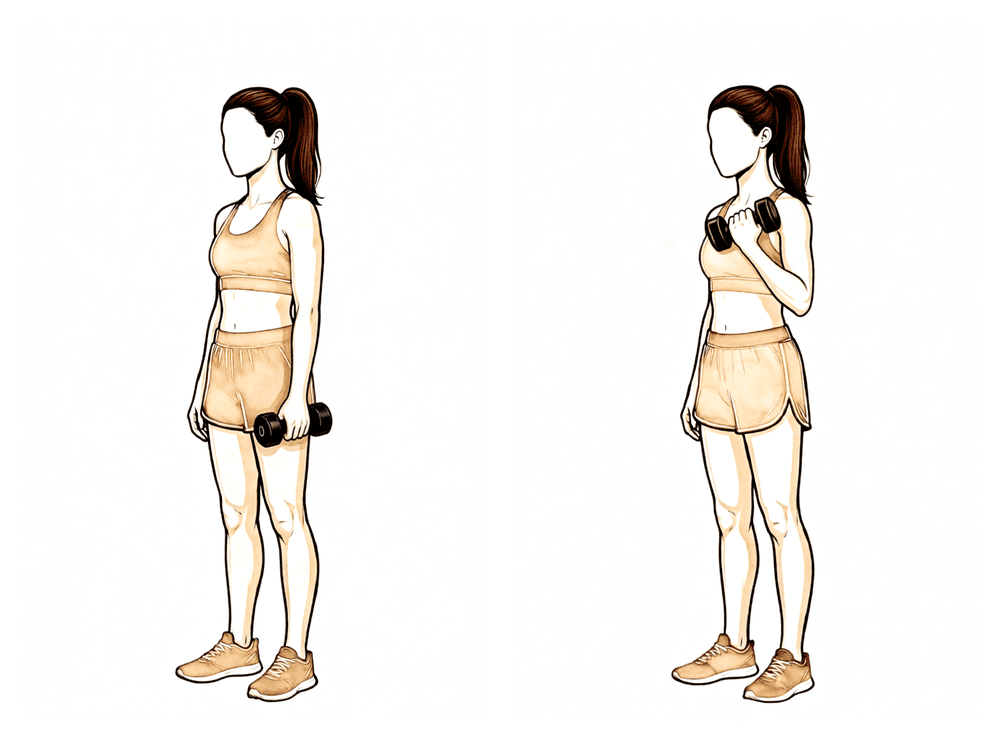
Kieran Hirpara 4.0
بائسیپس کرل (بعد کے مرحلے کی مضبوطی)
یہ بعد کے مرحلے کی ورزش ہے — مضبوطی کی ورزشیں صرف اس وقت شروع ہوتی ہیں جب آپ کی حرکت مستحکم ہو جائے، عموماً تقریباً 6 ہفتے سے۔ ہتھیلی اوپر رکھ کر ہلکا وزن کندھے کی طرف اوپر لائیں، پھر اسے قابو کے ساتھ آہستہ سے نیچے لائیں۔ اپنے فزیوتھراپسٹ کی رہنمائی کے مطابق وزن بتدریج بڑھائیں۔
آپ کے فزیوتھراپسٹ کی رہنمائی کے مطابق (تقریباً ہفتہ 6 سے)
یہ آپ کے ہینڈ آؤٹ میں دی گئی ورزشیں ہیں جو آپ کی کہنی اور بازو کے نچلے حصے کی حرکت دوبارہ حاصل کرنے اور برقرار رکھنے کے لیے ہیں۔ انہیں ڈاکٹر ہِرپرا اور اپنے تھراپسٹ کی رہنمائی کے مطابق شروع کریں؛ اس پروٹوکول میں یہ فوراً شروع ہو جاتی ہیں۔ انہیں مضبوطی سے اور بار بار کیا جاتا ہے، کیونکہ جو حرکت کی حد آپ برقرار رکھتے ہیں وہی ہے جسے آپ ہر روز ان ورزشوں کے ذریعے استعمال کرتے ہیں۔
آپ کا کلینیکل پروٹوکول
اس صفحے کا باقی حصہ اکڑی ہوئی کہنی کی سرجری کے ذریعے ریلیز (آرتھرولائسس) کے بعد بحالی کا کلینیکل پروٹوکول ہے۔ یہ حصہ آپ کے فزیوتھراپسٹ یا ہینڈ تھراپسٹ کو دیا جانا ہے، اور نیچے ہر مرحلہ سادہ زبان میں اس وضاحت سے شروع ہوتا ہے کہ اس دوران کیا ہو رہا ہے۔ سب سے بنیادی اصول یہ ہے کہ سرجن آپریشن کی میز پر تقریباً مکمل قوس حاصل کر لیتے ہیں؛ بحالی کا کام اسے کھونے نہ دینا ہے۔ حفاظت کے لیے کوئی فکسیشن (جوڑی گئی چیز) نہیں ہے اور اس لیے کوئی حفاظتی مرحلہ بھی نہیں: رفتار کو محدود کرنے والی چیزیں درد اور سوجن (oedema) پر قابو ہیں، ٹشو کا بھرنا نہیں۔
آپریشن کے بعد دن 0 سے 2
پہلے ایک دو دن میں کہنی کو تھوڑی دیر آرام دیا جاتا ہے، بازو کو اونچا رکھا جاتا ہے، اور سوجن پر برف اور دباؤ (compression) سے قابو پایا جاتا ہے۔ کہنی کو اکثر پوری طرح سیدھی (extension) پوزیشن میں سہارا دیا جاتا ہے، کیونکہ سیدھا کرنا ہی وہ حرکت ہے جو سب سے زیادہ ضائع ہوتی ہے اور جس کی طرف جھکاؤ رکھنا چاہیے۔ اگر فالتو ہڈی بننے کا خدشہ ہو (مثال کے طور پر فالتو ہڈی نکالنے کے بعد، یا اگر اصل چوٹ بہت زور دار تھی)، تو ڈاکٹر ہِرپرا اسے روکنے کے لیے ابھی سے سوزش کم کرنے والی دوا شروع کر سکتے ہیں۔
آپ کے فزیوتھراپسٹ کے لیے:
علاج سے پہلے مریض کی امیجنگ، آپریشن کی رپورٹ اور سابقہ طبی تاریخ (PMHx) دیکھیں، اور علاج کرنے والے سرجن سے ان باتوں پر رابطہ رکھیں: آپریشن کے دوران حاصل کی گئی قوس، النر عصب پر کیا گیا کوئی عمل، اور یہ کہ آیا غیر معمولی جگہوں پر ہڈی بننے (heterotopic ossification، HO) سے بچاؤ کی دوا شروع کی گئی ہے۔
پوزیشن اور سوجن
- گدی دار اسپلنٹ میں پوری طرح سیدھی (full extension) پوزیشن میں تھوڑی دیر ساکن رکھنا؛ بازو اونچا؛ سوجن کے لیے برف سے ٹھنڈک (cryotherapy)/دباؤ
- ڈرین (زخم سے رطوبت نکالنے والی نلکی) عموماً آپریشن کے بعد پہلے دن (POD1) نکال دیے جاتے ہیں
غیر معمولی ہڈی بننے (HO) سے بچاؤ (اگر ضرورت ہو)
- جہاں ضرورت ہو، خاص طور پر HO نکالنے یا زور دار چوٹ کے بعد، انڈومیتھاسن (مثلاً 25 ملی گرام دن میں تین بار (TID)، یا 75 سے 100 ملی گرام روزانہ) 3 سے 6 ہفتوں تک؛ منتخب زیادہ خطرے والے کیسوں میں اس کے ساتھ یا اس کے بغیر، آپریشن کے قریب شعاعوں سے علاج (radiotherapy) کی ایک خوراک (سرجن کا فیصلہ)
دن 1 اور اس کے بعد — فوری اور بھرپور حرکت کی حد
یہ پروٹوکول کا بنیادی حصہ ہے۔ آپریشن کے بعد پہلے دن اسپلنٹ اتار دیا جاتا ہے اور مضبوط، بار بار حرکت شروع ہو جاتی ہے: معاون فعال (active-assisted) اور غیر فعال (passive) طور پر کہنی کو موڑنا، سیدھا کرنا اور بازو کے نچلے حصے کو گھمانا، اس مقصد کے ساتھ کہ وہ پوری حد واپس حاصل ہو جو سرجن نے آپریشن کی میز پر حاصل کی تھی۔ حرکت کی کوئی بالائی حد نہیں: مقصد آپریشن کے دوران حاصل کی گئی پوری قوس ہے۔
آپ کے فزیوتھراپسٹ کے لیے:
حرکت کی حد (ROM) کی بالائی حد
- کوئی نہیں۔ آپریشن کے دوران حاصل کی گئی پوری قوس بحال کریں۔ آپریشن کے بعد پہلے دن (POD1) اسپلنٹ اتار دیں۔
ورزشیں
- موڑنے (flexion)، سیدھا کرنے (extension)، ہتھیلی نیچے کرنے (pronation) اور ہتھیلی اوپر کرنے (supination) میں معاون فعال اور غیر فعال حرکت کی حد؛ اسٹریچ کا جھکاؤ سب سے سخت سمت کی طرف رکھیں (عموماً سیدھا کرنا)
- اختیاری سی پی ایم (CPM، مشین کے ذریعے جوڑ کو مسلسل غیر فعال حرکت دینا): اگر استعمال کی جائے تو ہسپتال میں آپریشن کے بعد پہلے یا دوسرے دن (POD1–2) پوری دستیاب حد پر شروع کریں (عام طور پر بتائی جانے والی حد 0 سے 145 ڈگری، کہنی کے پیچھے ایک گدی (bolster) رکھ کر) اور فزیوتھراپی (PT) کے علاوہ گھر پر تقریباً 4 ہفتے تک جاری رکھیں۔ سی پی ایم صرف ایک اضافی مدد ہے اور یہ ثابت نہیں ہوا کہ یہ نگرانی میں کی جانے والی فزیوتھراپی سے بہتر ہے؛ اس کا استعمال سرجن کی صوابدید پر ہے۔
- تعداد: آپریشن کے بعد پہلے ہفتے میں روزانہ نگرانی میں فزیوتھراپی، پھر تقریباً 6 ہفتوں تک ہفتے میں 2 سے 3 بار
اگلے مرحلے میں جانے کی شرائط
- آپریشن کی میز پر حاصل کی گئی قوس برقرار ہو؛ سوجن اور درد قابو میں ہوں
ہفتہ 2 سے 6 — قوس کو برقرار رکھنا اور اسپلنٹ کا آغاز
حرکت مضبوطی سے جاری رہتی ہے۔ حرکت کی حد کو برقرار رکھنے اور بڑھانے کے لیے رات کو اور آرام کے اوقات میں اسپلنٹ کا پروگرام شامل کیا جاتا ہے: حرکت کی آخری حد پر کم بوجھ کے ساتھ دیر تک رکھا جانے والا اسٹریچ، باری باری موڑنے اور سیدھا کرنے کی پوزیشن میں۔
آپ کے فزیوتھراپسٹ کے لیے:
ورزشیں اور اسپلنٹ
- بھرپور فعال / معاون فعال / غیر فعال حرکت کی حد جاری رکھیں
- آخری حد پر کم بوجھ کے ساتھ دیر تک اسٹریچ کے لیے اسٹیٹک پروگریسو (static-progressive) اسپلنٹ (یا ڈائنامک / سیریل اسٹیٹک / ٹرن بکل (dynamic / serial-static / turnbuckle) اسپلنٹ) شامل کریں: رات/آرام کا پروگرام جس میں باری باری موڑنے (flexion) اور سیدھا کرنے (extension) کی پوزیشن ہو۔ کہنی کے مڑے رہ جانے والے اکڑاؤ (flexion contracture) کے لیے اسٹیٹک پروگریسو اسپلنٹ (غیر لچکدار، جس میں مریض خود مرحلہ وار قوت بڑھاتا ہے) ترجیحی طریقہ ہے۔
- سوجن اور زخم کے نشان کی دیکھ بھال
اگلے مرحلے میں جانے کی شرائط
- قوس برقرار ہو یا اس سے بڑھ گئی ہو؛ تقریباً ہفتہ 6 تک بوجھ کے لیے تیار
ہفتہ 6 سے 12 — مضبوطی اور اسپلنٹ کا جاری رہنا
جب حرکت مستحکم ہو جائے، عموماً تقریباً 6 ہفتے پر، تو برداشت کے مطابق بتدریج بڑھتی مزاحمت والی ورزشوں کے ساتھ مضبوطی کا آغاز ہوتا ہے۔ اسپلنٹ کا پروگرام جاری رہتا ہے۔
آپ کے فزیوتھراپسٹ کے لیے:
ورزشیں اور اسپلنٹ
- حرکت مستحکم ہونے پر بتدریج بڑھتی مزاحمت والی مضبوطی شروع کریں (عموماً تقریباً 6 ہفتے پر)
- بہترین آخری حرکت کی حد کے لیے آپریشن کے بعد کم از کم تقریباً 3 ماہ تک اسپلنٹ جاری رکھیں
تقریباً 16 ہفتے — بہتری کا ٹھہراؤ
شائع شدہ تحقیقات کے مطابق مریض اوسطاً تقریباً 16 ہفتے پر اپنی حرکت کی زیادہ سے زیادہ قوس تک پہنچتے ہیں، اور زیادہ تر بہتری 6 ہفتے اور 3 ماہ کے درمیان ہوتی ہے۔ یہ توقع آپریشن سے پہلے ہی قائم کر دینی چاہیے۔ موڑنے/سیدھا کرنے اور گھمانے کی قوس میں آخر میں حاصل ہونے والی بہتری عموماً طویل مدت تک برقرار رہتی ہے (بڑے گروپوں میں تقریباً 15 ماہ کی فالو اپ پر)۔
آپ کے فزیوتھراپسٹ کے لیے:
- زیادہ سے زیادہ قوس اوسطاً تقریباً 16 ہفتے پر حاصل ہوتی ہے؛ مریض کو بتائیں کہ آپریشن سے پہلے کی حرکت کی کوئی حد صحت یابی کے راستے کی قابل اعتماد پیش گوئی نہیں کرتی؛ تمام مریضوں پر تقریباً 16 ہفتے کا یکساں شیڈول لاگو کریں
کام اور سرگرمیوں میں واپسی
چونکہ حفاظت کے لیے کوئی فکسیشن نہیں ہے، اس لیے روزمرہ سرگرمیوں میں واپسی کسی چیز کے بھرنے کا انتظار کرنے کے بجائے آپ کے آرام، سوجن اور حرکت کی اس حد کے مطابق ہوتی ہے جو آپ برقرار رکھ رہے ہیں۔ روزمرہ کاموں کے لیے بازو کے ہلکے استعمال کی شروع سے ہی ترغیب دی جاتی ہے؛ درحقیقت، دن بھر کہنی کو معمول کے مطابق استعمال کرنا علاج کا حصہ ہے۔
مضبوطی کی ورزشیں، اور ان کے ساتھ زیادہ بھاری اور مشکل کام، حرکت مستحکم ہونے پر تقریباً 6 ہفتے سے شروع ہوتے ہیں، اور آپ کی طاقت اور حرکت کی حد کے مطابق بتدریج بڑھائے جاتے ہیں۔ زیادہ تر لوگ تقریباً 4 ماہ تک اپنی ٹھہری ہوئی حرکت کی حد اور کام کی صلاحیت تک پہنچ جاتے ہیں، اور حاصل ہونے والی بہتری عموماً طویل مدت تک برقرار رہتی ہے۔ گاڑی چلانے، کام کی ذمہ داریوں اور کھیل میں واپسی کا انحصار اس بات پر ہے کہ اس مخصوص کام کے لیے کافی حرکت، طاقت اور کنٹرول واپس آ گیا ہو؛ اپنی صورتحال کے مطابق وقت کے بارے میں ڈاکٹر ہِرپرا اور اپنے تھراپسٹ سے بات کریں، کیونکہ یہ آپ کے کام اور آپ کی سرجری کی وسعت کے مطابق مختلف ہوتا ہے۔ سب سے اہم پیغام یہ ہے کہ اپنی حرکت کی ورزشیں اور رات/آرام کے اسپلنٹ کا پروگرام پورا عرصہ جاری رکھیں، کیونکہ یہی اس حرکت کی حد کی حفاظت کرتا ہے جسے دوبارہ حاصل کرنے کے لیے آپ نے محنت کی ہے۔
اپنے پروٹوکول کے بعد
یہ پروٹوکول پریکٹس کے عمومی صحت یابی کے مشوروں کے ساتھ مل کر کام کرتا ہے: آپریشن کے بعد درد پر قابو اور زخم کی دیکھ بھال دیکھیں۔ کندھے کے لیے اسی طرح کے آپریشن کے بارے میں، جس میں اکڑے ہوئے کندھے کی اندرونی جھلی کو کھولا جاتا ہے، کیپسولر ریلیز دیکھیں۔ اوپر دیا گیا مرحلہ وار منصوبہ کہنی کے اکڑاؤ کی ریلیز کے بعد بحالی سے متعلق شائع شدہ شواہد کے مطابق ہے، اور آپ کی آگے کی صحت یابی میں آپ کا فزیوتھراپسٹ یا ہینڈ تھراپسٹ آپ کی کہنی کی بہتری کے مطابق انفرادی طور پر رہنمائی کرتا ہے۔
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Stiff Elbow — Arthrolysis / Capsular Release (Open or Arthroscopic) — Rehabilitation Evidence
Topic scope: rehabilitation after surgical release of the post-traumatic / post-surgical stiff elbow — open or arthroscopic arthrolysis, anterior + posterior capsulectomy, ± heterotopic ossification (HO) excision, ± ulnar nerve decompression. The focus here is the post-operative rehabilitation philosophy and timeline, not the indications for or technique of the release itself.
Defining principle: the surgeon establishes a near-full arc of motion on the operating table; rehabilitation's single job is to not lose it. There is no fixation to protect, so — unlike a fracture fixation or a tendon repair — there is no protection phase. Motion starts essentially Day 1 (or even in-hospital CPM from Day 1–2), pushed firmly and often. Pain and oedema control are the rate-limiters, not tissue healing. This is the opposite philosophy to olecranon ORIF or a distal biceps repair. Dr Hirpara's stance: no sling and no immobilisation phase; immediate aggressive active-assisted and passive ROM from POD1; static-progressive (or dynamic) night/rest splinting continued for at least 3 months; HO prophylaxis where indicated; and a frank pre-operative conversation that the elbow reaches its plateau at a mean of ~16 weeks.
Consensus phased timeline (week windows)
| Phase | Window | Immobilisation / "ceiling" | Movement & adjuncts | Strengthening | Criteria to progress |
|---|---|---|---|---|---|
| Immediate | Day 0–2 | Brief splint in full extension; arm elevated, cryotherapy/compression | HO prophylaxis decision made now (see below); drains out POD1 | — | Splint off POD1 |
| Immediate aggressive ROM (core) | Day 1 onward | No ROM ceiling — recover the full intra-operative arc | Active-assisted + passive flexion / extension / pronation / supination; bias toward tightest direction (usually extension). Optional CPM 0–145° with bolster, in-hospital POD1–2, home to ~4 wk. Daily PT first week → 2–3×/wk for ~6 wk | — | On-table arc maintained; oedema/pain controlled |
| Hold the arc + splinting | Weeks 2–6 | None | Continue aggressive A/AAROM/PROM. Add static-progressive (or dynamic / serial-static / turnbuckle) splinting — low-load prolonged end-range stretch, night/rest, alternating flexion/extension | — | Arc maintained or exceeded; ready for loading ~wk 6 |
| Strengthening + continued splinting | Weeks 6–12 | None | Continue splinting | Progressive resistive strengthening once motion stable (~wk 6); continue splinting ≥3 months | Stable, strengthening motion |
| Plateau | ~16 weeks (≈4 months) | None | — | Maintain gains; long-term hold | Maximum arc reached; most recovery occurred 6 wk–3 mo |
Evidence summary by theme
Immediate aggressive motion — the agreed principle (Strong consensus)
Large, consistent retrospective case series and review articles agree that the elbow re-stiffens without immediate motion, and that rehabilitation exists to hold the intra-operative arc. Motion begins POD1; the splint (when used) is removed POD1 and active-assisted + passive ROM is started in all planes, biased toward the tightest direction (usually extension). This is strong consensus across the literature.
Which specific rehab protocol is best (Moderate — genuine equipoise)
The best specific rehab protocol is genuinely unknown. No completed RCT shows superiority of CPM vs PT vs delayed PT — the SET-Study (Stiff Elbow Trial) was designed precisely because this question is unresolved, with three real-world arms (in-hospital CPM + early PT / in-hospital early PT / outpatient PT from POD7–10). CPM is cited in protocols (home use to ~4 weeks) and one arthroscopic- release series reports very good 3-year outcomes with a 4-week CPM rail plus PT, but CPM has never been shown superior to supervised PT alone. So: strong consensus on aggressive early motion; weak/equipoise evidence on which adjunct.
Splinting modality (Moderate — no clear winner)
Static-progressive, dynamic, serial-static and turnbuckle splinting all deliver low-load prolonged end-range stretch. The Lindenhovius RCT found no difference between dynamic orthoses and static-progressive splinting (similar DASH). Static-progressive (inelastic, patient-adjusted incremental torque) is the favoured modality for elbow flexion contractures. Reviews recommend the splinting program run for at least ~3 months post-operatively for optimal final ROM. Bracing alone can rival surgery for non-osseous stiffness with far lower neurovascular risk.
HO prophylaxis (Consensus — extrapolated evidence)
Indomethacin (commonly 25 mg TID, or 75–100 mg/day, for 3–6 weeks) ± single-dose perioperative radiotherapy is widely used after release, especially with HO excision or high-energy trauma. Most HO-prophylaxis RCT evidence is extrapolated from acetabular/hip surgery, not elbow-specific. Recurrent HO / arthrofibrosis responds to repeat excision + release.
Recovery trajectory and plateau (Moderate — cohort data)
Published series report patients reach their maximum arc of motion at a mean of ~16 weeks, with most recovery occurring between 6 weeks and 3 months, and maintained gains at ~15-month follow-up in large cohorts. Growth-mixture modelling found no pre-operative ROM threshold or factor reliably predicted the recovery trajectory — so all patients are counselled on the same ~16-week timeline pre-operatively.
Ulnar nerve (Consensus)
As flexion improves post-release, the ulnar nerve sees increased stress — there should be a low threshold for review, and for concomitant ulnar nerve decompression/transposition at the time of surgery. Tobacco use predicts poorer outcomes and higher complication rates after open arthrolysis.
Evidence strength flags (summary)
- STRONG (consensus across case series/reviews): immediate aggressive active-assisted + passive motion from POD1 to hold the intra-operative arc — no protection phase.
- MODERATE (RCT/cohort, equipoise): which adjunct is best — CPM vs PT vs delayed PT (SET-Study, no completed superiority data); splinting modality (Lindenhovius RCT: no difference dynamic vs static-progressive); ~16-week plateau and maintained gains (growth-mixture-modelling and large open-release cohorts).
- CONSENSUS / EXTRAPOLATED: HO prophylaxis (indomethacin ± single-dose RT; most evidence extrapolated from acetabular/hip surgery); ≥3-month splinting program duration.
Overall topic flag: MODERATE — strong consensus on the principle (aggressive early motion + adjunct splinting + HO prophylaxis), weak/equipoise evidence on the specific adjunct.
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Sun Z, Wang W, Fan C. Tobacco use predicts poorer clinical outcomes and higher post-operative complication rates after open elbow arthrolysis. Arch Orthop Trauma Surg. 2019.
- Open elbow release for post-traumatic stiffness — growth-mixture-modelling cohort: maximum arc of motion at a mean of ~16 weeks, most recovery between 6 weeks and 3 months.
- 103-patient open capsular release series — significant, maintained flexion/extension and supination/pronation arc gains at a mean of 15 months.
- Papatheodorou LK, Sotereanos DG (University of Pittsburgh) — elbow contracture release techniques review.
- Lindenhovius et al. RCT — no difference between dynamic orthoses and static-progressive splinting (cited within a retrieved review).
- Retrieved technique text: indomethacin 25 mg TID for ~6 weeks for HO prophylaxis; CPM continued at home up to 4 weeks, full range 0–145° with a bolster behind the elbow.
- Northwestern series — HO excision + contracture release: ROM gains and complications.
- Arthroscopic release + 4-week CPM rail series — very good ROM, function and quality of life at a mean of 3 years.
Published protocols / reviews (URLs)
- Papadopoulos et al. Elbow contracture release. Annals of Joint (PT from POD1; flexion bias the first 2 weeks then full ROM over 2–3 months; dynamic / static-progressive splinting ≥3 months; CPM optional). https://aoj.amegroups.org/article/view/6083/html
- SET-Study (Stiff Elbow Trial) protocol — CPM vs PT vs delayed PT RCT; documents that the best rehab protocol is unknown. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC5700741/
- Analysis of Long-Term Outcomes Following Surgical Contracture Release of the Elbow — immediate splint in full extension, splint off POD1, AAROM started POD1, OT/PT-guided self-directed program, no CPM. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC8152451/