Patients › Rehabilitation
ٹریگر فنگر ریلیز (Trigger Finger Release)
Post-operative exercises and precautions after trigger finger release, including tendon glides and joint blocking exercises.
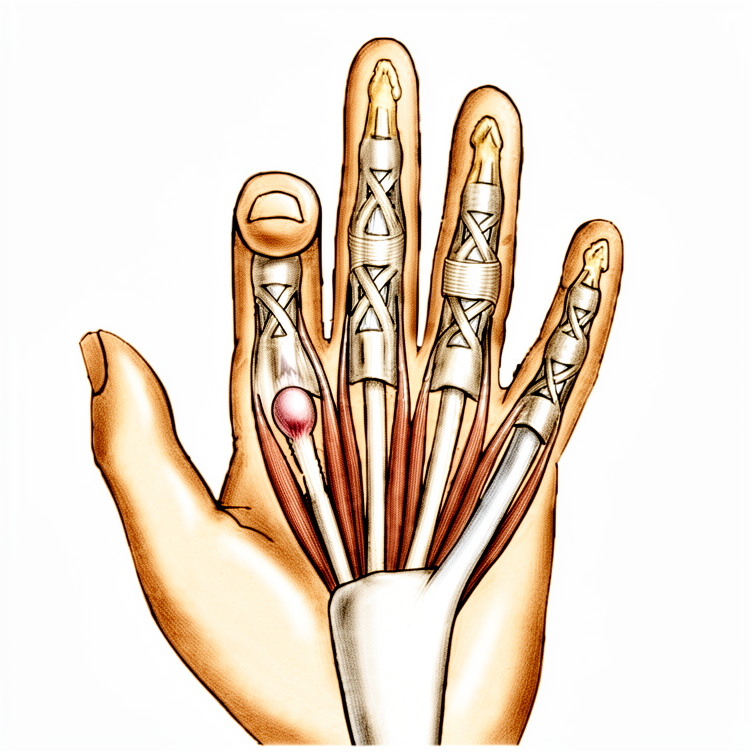
یہ پروٹوکول ٹریگر فنگر ریلیز (trigger finger release، یعنی انگلی کے اٹکنے کو ٹھیک کرنے کے لیے ٹینڈن کے راستے کی تنگی کھولنے کا آپریشن) کے بعد آپ کی صحت یابی میں رہنمائی کرتا ہے، جو ڈاکٹر کیرن ہِرپرا Mater Private Hospital Rockhampton میں کرتے ہیں۔ اس میں بتایا گیا ہے کہ کیا توقع رکھیں، کن احتیاطوں پر عمل کرنا ہے، اور آپریشن کے بعد ورزشوں کا پروگرام کیا ہے: یہ صفحہ یا اس کی پی ڈی ایف اپنے فزیوتھراپسٹ یا ہینڈ تھراپسٹ (ہاتھ کی بحالی کے ماہر) کے پاس لے کر جائیں تاکہ آپ کی بحالی کا علاج مربوط رہے۔
اگر سرجری کے بعد آپ کو اپنے زخم کے بارے میں کوئی تشویش ہو تو کلینک سے رابطہ کریں۔ اکثر یہ مددگار ہوتا ہے کہ زخم کی تصویر لے کر جائزے کے لیے ای میل کر دیں۔
کیا توقع رکھیں
زخم کی دیکھ بھال الگ سے بیان کی گئی ہے: اس پروٹوکول کے آخر میں دیا گیا زخم کی دیکھ بھال والا صفحہ دیکھیں۔
نیچے دی گئی ورزشیں بہت اہم ہیں تاکہ زخم بھرنے کے دوران آپ کے ٹینڈن (tendon)، یعنی وہ مضبوط ڈوری جو پٹھے کو ہڈی سے جوڑتی ہے، آس پاس کے حصوں سے چپک نہ جائیں۔ بعض اوقات اس آپریشن کے بعد آپ کی انگلیوں کے جوڑ اکڑ سکتے ہیں۔ اس اکڑاؤ کو شروع ہی میں روکنا ضروری ہے، اس لیے آپ کو مشورہ دیا جاتا ہے کہ اپنی انگلی کو (اپنے دوسرے ہاتھ کی مدد سے) مضبوطی سے اور دیر تک اسٹریچ کریں، خاص طور پر سیدھا کرنے کی سمت میں۔ دوسرے ہاتھ کی مدد سے اسٹریچ کرنے کا یہ طریقہ (passive stretching) محفوظ ہے اور اس سے آپریشن پر کوئی اثر نہیں پڑے گا: پُلی (pulley)، وہ پٹی جو ٹینڈن کو ہڈی کے قریب رکھتی ہے، پہلے ہی کھولی جا چکی ہے، اس لیے اندر کوئی ایسی چیز نہیں جسے اسٹریچ نقصان پہنچا سکے۔
جب آپ کا زخم بھر جائے تو یہ ورزشیں کرنے سے پہلے 20 منٹ تک اپنے ہاتھ پر گرمائش (ٹکور) دیں۔ ورزشیں مکمل کرنے کے بعد برف لگانا سوزش سے بچنے میں مددگار ہو سکتا ہے۔
بعض اوقات ہاتھ یا زخم زیادہ حساس ہو سکتا ہے۔ یہ معمول کی بات ہے، اور روزانہ حساسیت کم کرنے کی مشق (desensitisation) شروع کر کے اس سے بچا جا سکتا ہے یا اسے کم کیا جا سکتا ہے: زخم کے اوپر (زخم کی پٹی لگی رہنے دیں) ہلکے سے تھپتھپائیں یا سہلائیں، اور یہ سرجری کے فوراً بعد سے شروع کریں۔ اس طرح کا "حسی ردِعمل" (sensory feedback) جلد کو چھونے اور مختلف سطحوں کے احساس کو دوبارہ معمول کے مطابق محسوس کرنے میں مدد دیتا ہے۔
پہلے 48 گھنٹوں میں سوجن کم رکھنے کی کوشش کریں: ہاتھ کو اونچا رکھیں (دل کی سطح سے اوپر)، برف استعمال کریں، اگر آپ کے تھراپسٹ نے دباؤ والی پٹی (compression) دی ہو تو اسے لگائیں، اور انگلیوں کو آہستگی سے "پمپ" کریں (کھولیں اور بند کریں) تاکہ سوجن آگے بڑھ کر کم ہو۔
جیسے ہی درد اجازت دے، ہاتھ کو ہلکے کاموں (کپڑے پہننا، کھانا کھانا اور اسی طرح کے کام) کے لیے استعمال کرنا شروع کریں، اور آہستہ آہستہ اسے بڑھائیں۔ حد سے زیادہ کام نہ کریں: اگر کسی سرگرمی کے بعد آپ کا درد یا سوجن واضح طور پر بڑھ جائے تو ہاتھ کے سنبھلنے تک سرگرمی کم کر دیں، پھر دوبارہ آہستہ آہستہ بڑھائیں۔
جب زخم پوری طرح بھر جائے تو زخم کے نشان کی مالش شروع کریں: چیرے کے اوپر مضبوطی سے گول گول دائرے بنائیں۔ زخم کی دیکھ بھال والے صفحے پر زخم کے نشان کی دیکھ بھال کے بارے میں مزید معلومات موجود ہیں۔
صحت یابی کے بارے میں شواہد کیا کہتے ہیں
کھلے آپریشن کے ذریعے A1 پُلی کو کھولنا ایک اچھی طرح سے آزمودہ آپریشن ہے جس کا شائع شدہ طبی تحقیق میں مضبوط ریکارڈ ہے۔ انگلی کا اٹکنا اور جام ہونا خود آپریشن سے ٹھیک ہو جاتا ہے: جب پُلی کاٹ دی جاتی ہے تو ٹینڈن دوبارہ آزادی سے پھسلنے لگتا ہے، اور عام طور پر انگلی کا اٹکنا واپس نہیں آتا۔ تقریباً 1,600 کھلے آپریشنوں کے ایک سلسلے میں، 1 فیصد سے کم مریضوں کو برقرار رہنے والے یا دوبارہ ہونے والے اٹکنے کی وجہ سے دوسرے آپریشن کی ضرورت پڑی، اور کسی عصب کو نقصان یا گہرا انفیکشن نہیں ہوا [4]۔ تین سال سے زیادہ عرصے تک مریضوں کا جائزہ لینے والی ایک تقابلی تحقیق میں بھی کھلے آپریشن کے بعد یہ مسئلہ دوبارہ نہیں ہوا [5]۔
ہتھیلی کی دکھن پہلے ایک سے دو ہفتوں میں کافی حد تک کم ہو جاتی ہے۔ ایک تقابلی تحقیق میں کھلے آپریشن کے بعد درد میں نمایاں کمی آنے کی درمیانی (median) مدت تقریباً ایک ہفتہ تھی [5]۔ اس کے بعد بھی کئی ہفتوں تک زور سے پکڑنے پر ہتھیلی میں کچھ چھونے پر درد، ہلکی سوجن یا انگلی کا اکڑاؤ رہ سکتا ہے۔ یہ معمول کی بات ہے اور اس بات کی علامت ہے کہ زخم کا نشان پختہ ہو رہا ہے، جس میں تقریباً تین ماہ لگتے ہیں [3]؛ اس پروٹوکول میں حساسیت کم کرنے کی مشق، زخم کے نشان کی مالش اور ورزشوں کا پروگرام بالکل اسی کو سنبھالنے کے لیے بنایا گیا ہے۔ اوپر بیان کیے گئے بڑے سلسلے میں، ہر بیس میں سے تقریباً ایک انگلی میں سرجری کے بعد کوئی مسئلہ درج کیا گیا، جو زیادہ تر عارضی اکڑاؤ یا زخم کے نشان پر چھونے سے درد تھا جو علاج سے ٹھیک ہو گیا؛ ذیابیطس (شوگر) والے افراد میں حرکت کی بحالی عام طور پر زیادہ آہستہ ہوتی ہے، اس لیے اس گروپ میں ورزشوں کا پروگرام اور بھی زیادہ اہم ہے [4]۔
ہینڈ تھراپی کے شائع شدہ پروٹوکول سرجری کے بعد پہلے چند دنوں کے اندر انگلی کی اپنی طاقت سے اور دوسرے ہاتھ کی مدد سے حرکت، اور ٹینڈن کو پھسلانے والی ورزشیں شروع کرتے ہیں، زخم بھرنے کے بعد زخم کے نشان کی دیکھ بھال اور حساسیت کم کرنے کی مشق شامل کرتے ہیں، اور بعد میں گرفت کو مضبوط کرنے کی بتدریج ورزشیں دوبارہ شروع کرتے ہیں [2][3]، اور یہ وہی مرحلہ وار طریقہ ہے جو اس صفحے کے پروگرام میں ہے۔ ورزشیں جلد شروع کرنا ہی وہ چیز ہے جو زخم بھرنے کے دوران ٹینڈن کو پھسلتا اور جوڑوں کو لچکدار رکھتی ہے۔
کام پر واپسی اس بات پر منحصر ہے کہ آپ کے کام میں ہاتھ سے کیا کچھ کرنا پڑتا ہے۔ ایک تقابلی تحقیق میں، آدھے مریض کھلے آپریشن کے تقریباً دو ہفتوں کے اندر کام پر واپس آ گئے تھے [5]؛ ہلکے یا دفتری کام کرنے والے لوگ اکثر اس سے پہلے واپس جا سکتے ہیں، جبکہ جسمانی مشقت والے بھاری کام کے لیے اس وقت تک انتظار کرنا پڑتا ہے جب تک نیچے بیان کی گئی وزن اٹھانے اور گرفت کی پابندی ختم نہ ہو جائے۔
ایک رینڈمائزڈ کنٹرولڈ ٹرائل (randomised controlled trial) میں کھلے آپریشن کے بعد تین ماہ کی نگرانی میں تھراپی کا موازنہ خود سے کیے جانے والے گھریلو ورزشوں کے پروگرام سے کیا گیا: چھ ماہ پر دونوں گروپوں میں مجموعی کارکردگی، حرکت اور درد ملتے جلتے تھے، نگرانی میں تھراپی کے ساتھ گرفت کی طاقت زیادہ بحال ہوئی، اور جن مریضوں کو باقاعدہ تھراپی سے واضح فائدہ ہوا وہ تھے جن میں سرجری سے پہلے بارہ ماہ سے زیادہ عرصے سے انگلی اٹک رہی تھی، اور وہ جو گھر کا کام کاج یا ہلکا کام کرتے تھے [1]۔ عملی طور پر، اچھی طرح کیا گیا گھریلو پروگرام (اس صفحے پر دی گئی ورزشیں) زیادہ تر مریضوں کے لیے کافی ہوتا ہے، اور باقاعدہ ہینڈ تھراپی اس وقت زیادہ فائدہ دیتی ہے جب سرجری سے پہلے انگلی لمبے عرصے تک اکڑی رہی ہو یا بہتری آہستہ ہو رہی ہو۔
احتیاطیں اور پابندیاں
روزمرہ زندگی کے کاموں، جیسے اپنی دیکھ بھال، کھانا کھانا، کپڑے پہننا، لکھنا اور ٹائپ کرنا، کے لیے ہاتھ کے ہلکے استعمال کی حوصلہ افزائی کی جاتی ہے۔ جو حدود اہم ہیں:
- آپریشن کے بعد 4 ہفتے تک وزن اٹھانے، چیزوں کو پکڑنے (گرفت) اور ہاتھ پر وزن ڈالنے، ان سب سے پرہیز کریں۔
- پہلے ہفتے کے دوران گاڑی چلانا محدود ہے؛ جب درد اجازت دے، آپ پوری مٹھی بنا سکیں، اور گاڑی کو محفوظ طریقے سے قابو میں رکھ سکیں، تب دوبارہ شروع کریں۔
آپ کے فزیوتھراپسٹ کے لیے:
علاج کا طریقہ
- نیچے دیے گئے کارڈز کے مطابق گھریلو ورزشوں کا پروگرام: کلائی کو آگے اور پیچھے موڑنے کا اسٹریچ؛ انگلی کے سرے والے جوڑ (DIP، distal interphalangeal) اور درمیانی جوڑ (PIP، proximal interphalangeal) کو الگ الگ موڑنے کی مشق (joint blocking)؛ ٹینڈن کو پھسلانے والی ورزشیں (tendon glides، Series A اور Series B)
- جوڑوں کے اکڑاؤ کو شروع ہی میں روکنے کے لیے انگلی کو دوسرے ہاتھ کی مدد سے مضبوطی سے اور دیر تک اسٹریچ کرنا، خاص طور پر سیدھا کرنے کی سمت میں
- زخم بھرنے کے بعد ورزشوں سے پہلے 20 منٹ تک ہاتھ پر گرمائش؛ سوزش سے بچنے کے لیے ورزشوں کے بعد برف
- روزانہ حساسیت کم کرنے کی مشق (زخم کے اوپر ہلکے سے تھپتھپانا یا سہلانا، زخم کی پٹی لگی رہے) جو آپریشن کے فوراً بعد شروع کی جائے
- پہلے 48 گھنٹوں میں سوجن پر قابو: ہاتھ کو اونچا رکھنا، برف، ضرورت کے مطابق دباؤ والی پٹی، انگلیوں کو آہستگی سے پمپ کرنا
- جتنا درد اجازت دے، ہلکے روزمرہ استعمال کی طرف بتدریج واپسی، اور سرگرمی کے بعد درد یا سوجن کے بڑھ جانے پر نظر رکھنا
- زخم پوری طرح بھر جانے کے بعد زخم کے نشان کی مالش (چیرے کے اوپر مضبوطی سے گول دائرے)
احتیاطیں
- روزمرہ زندگی کے کاموں (اپنی دیکھ بھال، کھانا کھانا، کپڑے پہننا، لکھنا، ٹائپ کرنا) کے لیے صرف ہلکا استعمال
- آپریشن کے بعد 4 ہفتے تک نہ وزن اٹھانا، نہ گرفت کرنا اور نہ ہاتھ پر وزن ڈالنا
- پہلے ہفتے کے دوران گاڑی چلانا محدود؛ جب درد اجازت دے، پوری مٹھی بن سکے اور مریض گاڑی کو محفوظ طریقے سے قابو میں رکھ سکے، تب دوبارہ شروع کریں
متوقع سنگِ میل (شرائط پر مبنی، شائع شدہ پروٹوکولز کی رہنمائی کے مطابق [1][2][3])
- عام درد کش دوا کے ساتھ 1 سے 2 ہفتوں کے اندر درد آرام دہ سطح تک کم ہو جائے [5]
- 2 سے 3 ہفتوں تک زخم بھر جائے، اور زخم کے نشان کی مالش اور حساسیت کم کرنے کی مشق جاری ہو [2][3]
- تقریباً 3 ہفتوں تک انگلی کو اپنی طاقت سے پوری طرح موڑنا اور سیدھا کرنا (پوری مٹھی اور تمام انگلیاں پوری سیدھی)، جو الگ الگ جوڑ موڑنے اور ٹینڈن کو پھسلانے والی ورزشوں کے پروگرام سے بحال اور برقرار رکھا جائے [2]
- گرفت اور چٹکی کی گرفت کو مضبوط کرنے کی بتدریج ورزشیں (مثلاً ورزش والی نرم مٹی، putty) اس وقت شروع کی جائیں جب 4 ہفتے کی وزن اٹھانے اور گرفت کی پابندی ختم ہو جائے، اور پھر ہاتھ کے پورے روزمرہ استعمال تک بڑھایا جائے
- باقاعدہ نگرانی والی ہینڈ تھراپی پر غور کریں اگر آپریشن سے پہلے 12 ماہ سے زیادہ عرصے سے انگلی اٹک رہی تھی، اگر مریض کے کاموں میں ہاتھ کا مسلسل ہلکا یا باریک استعمال شامل ہو، یا اگر حرکت کی حد یا گرفت کی بحالی آہستہ ہو [1]
یہ آپ کے ہینڈ آؤٹ کی ورزشیں ہیں، جو سرجری کے بعد شروع کی جاتی ہیں اور آپ کے فزیوتھراپسٹ یا ہینڈ تھراپسٹ کی رہنمائی کے مطابق گھر پر جاری رکھی جاتی ہیں۔
آپ کی ورزشیں
Kieran Hirpara 4.0
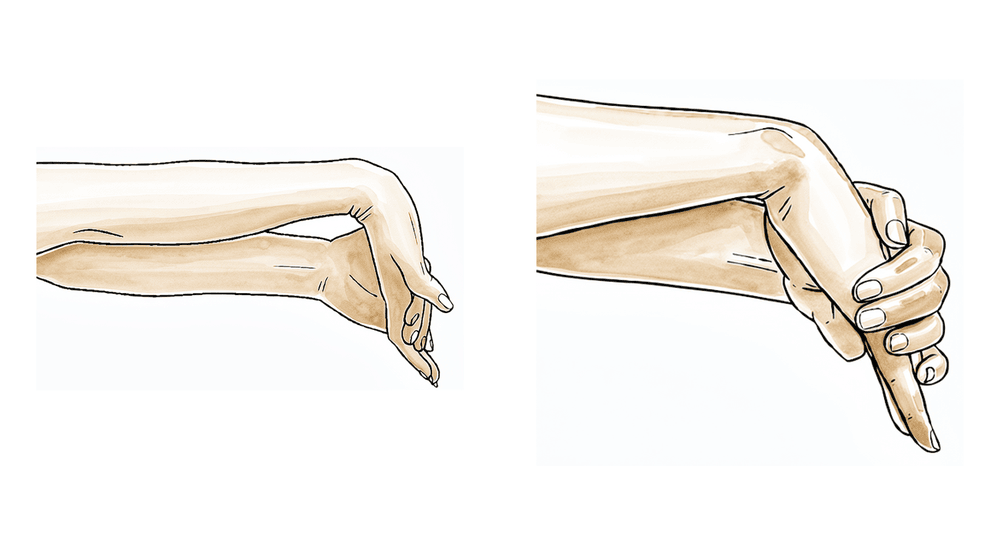
کلائی کو آگے اور پیچھے موڑنے کا اسٹریچ
اپنی کہنی میز پر ٹکائیں (یا بازو کا نچلا حصہ میز یا کرسی کے بازو کے کنارے پر رکھیں) اور اپنی کلائی کو آہستگی سے آگے پیچھے جھلائیں۔ جب یہ کچھ آرام دہ ہو جائے تو دوسرے ہاتھ سے اپنی ہتھیلی کو پکڑیں اور کلائی کو پیچھے کی طرف دبائیں (انگلیاں ڈھیلی، چھت کی طرف) — 15 سیکنڈ تک اسی حالت میں رکھیں؛ پھر دوسری طرف (انگلیاں ڈھیلی، فرش کی طرف) — 15 سیکنڈ تک رکھیں۔ ہر سمت میں 5 بار دہرائیں۔
10 بار، دن میں 4 سے 5 مرتبہ
Kieran Hirpara 4.0
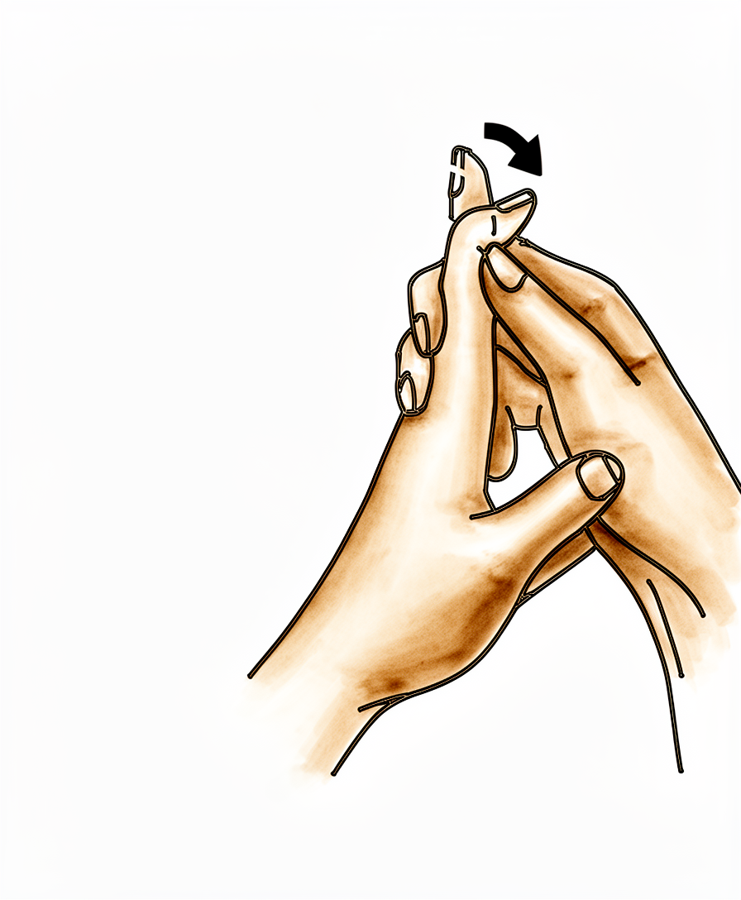
انگلی کے سرے والے جوڑ (DIP) کو الگ سے موڑنا
ڈی آئی پی (DIP، distal interphalangeal) جوڑ آپ کی انگلی کا سب سے آخری (سرے والا) جوڑ ہے۔ ہتھیلی اوپر کی طرف رکھ کر شروع کریں، اور متاثرہ ہاتھ کو دوسرے ہاتھ سے سرے والے جوڑ کے بالکل نیچے سہارا دیں۔ سرے والے جوڑ کو موڑیں اور سیدھا کریں، اور ہر حالت کو 3 سے 5 سیکنڈ تک رکھیں۔ درمیانی جوڑ کو صرف اتنا سہارا دیں کہ وہ نہ مڑے۔ اس ورزش کے دوران اگر دوسری انگلیاں حرکت کریں تو کوئی حرج نہیں۔
10 بار، دن میں 4 مرتبہ، روزانہ

Kieran Hirpara 4.0
انگلی کے درمیانی جوڑ (PIP) کو الگ سے موڑنا
پی آئی پی (PIP، proximal interphalangeal) جوڑ آپ کی انگلی کا درمیانی جوڑ ہے۔ ہتھیلی اوپر کی طرف رکھ کر شروع کریں، اور متاثرہ ہاتھ کو دوسرے ہاتھ سے دوسرے جوڑ کے بالکل نیچے سہارا دیں۔ اپنی انگلی کو درمیانی جوڑ سے موڑیں اور سیدھا کریں، اور ہر حالت کو 3 سے 5 سیکنڈ تک رکھیں۔ اگر دوسری انگلیاں بھی حرکت کریں تو کوئی حرج نہیں۔
10 بار، دن میں 4 مرتبہ، روزانہ
Kieran Hirpara 4.0
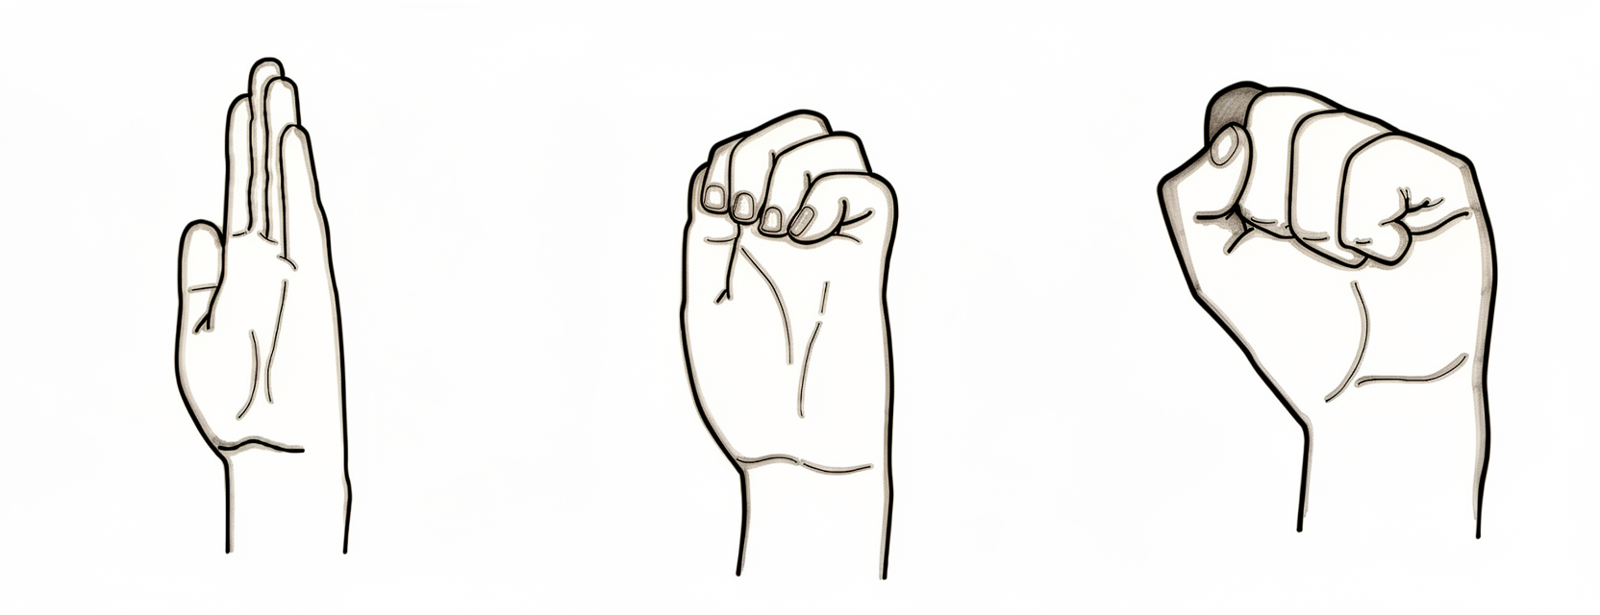
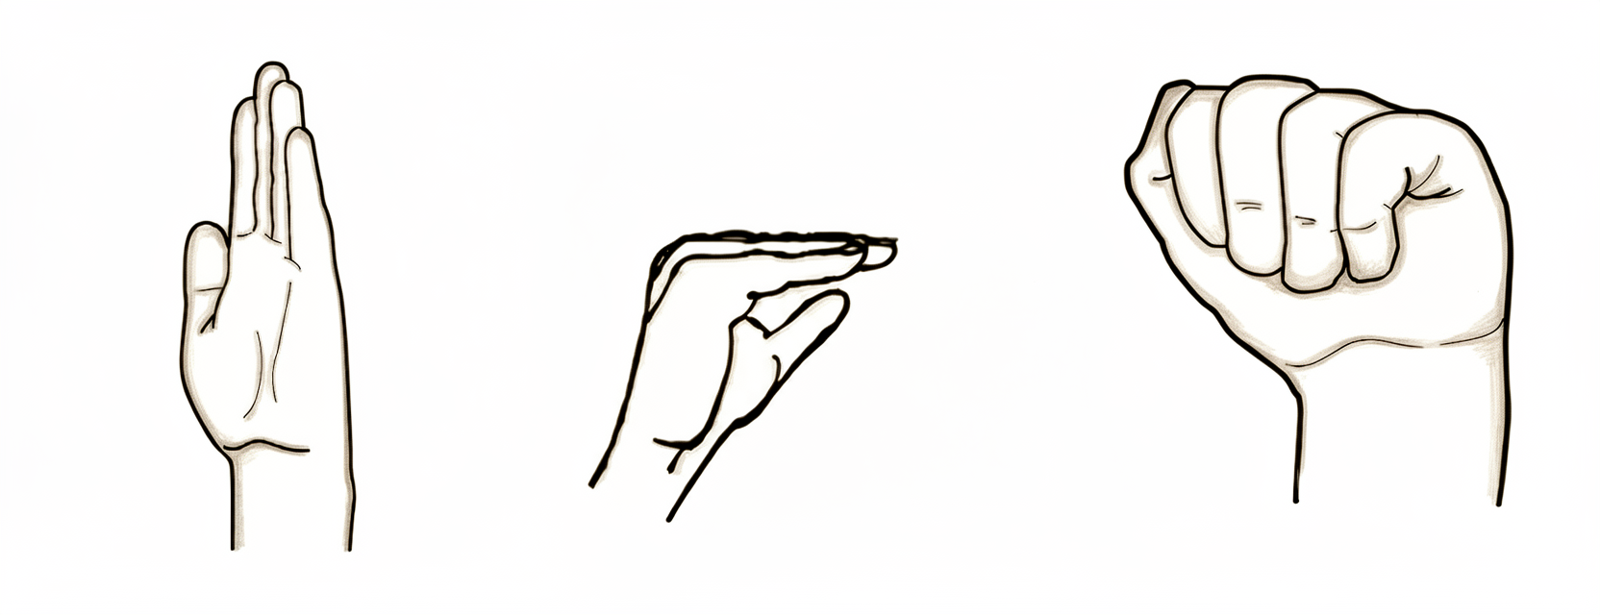
ٹینڈن کو پھسلانے والی ورزشیں (tendon glides) — سلسلہ A
ہاتھ کو اپنے سامنے اور کلائی کو سیدھا رکھ کر، اپنی تمام انگلیوں کو پوری طرح سیدھا کریں — انگلیوں کے پوری طرح سیدھا ہونے کو یقینی بنانے کے لیے آپ اپنا دوسرا ہاتھ استعمال کر سکتے ہیں (حالت 1)۔ انگلیوں کے سروں کو موڑ کر "ہُک" کی حالت میں لائیں، انگلیوں کے جوڑ (knuckles) اوپر کی طرف ہوں (حالت 2)۔ پھر انگوٹھے کو انگلیوں کے اوپر رکھ کر کس کر مٹھی بنائیں (حالت 3)۔
5 سے 10 بار، دن میں 2 سے 3 مرتبہ، روزانہ
Kieran Hirpara 4.0
ٹینڈن کو پھسلانے والی ورزشیں (tendon glides) — سلسلہ B
ہاتھ کو اپنے سامنے اور کلائی کو سیدھا رکھ کر، اپنی تمام انگلیوں کو پوری طرح سیدھا کریں — انگلیوں کے پوری طرح سیدھا ہونے کو یقینی بنانے کے لیے آپ اپنا دوسرا ہاتھ استعمال کر سکتے ہیں (حالت 1)۔ انگلیوں کو صرف جڑ والے جوڑ سے موڑ کر اور انگلیاں سیدھی رکھ کر "میز کی سطح" (tabletop) جیسی شکل بنائیں — دھیان رکھیں کہ آپ کی کلائی آگے کی طرف نہ جھکے (حالت 2)۔ پھر انگلیوں کو درمیانی جوڑ سے موڑیں اور انہیں ہتھیلی سے لگائیں (حالت 3)۔
5 سے 10 بار، دن میں 2 سے 3 مرتبہ، روزانہ
Kieran Hirpara 4.0
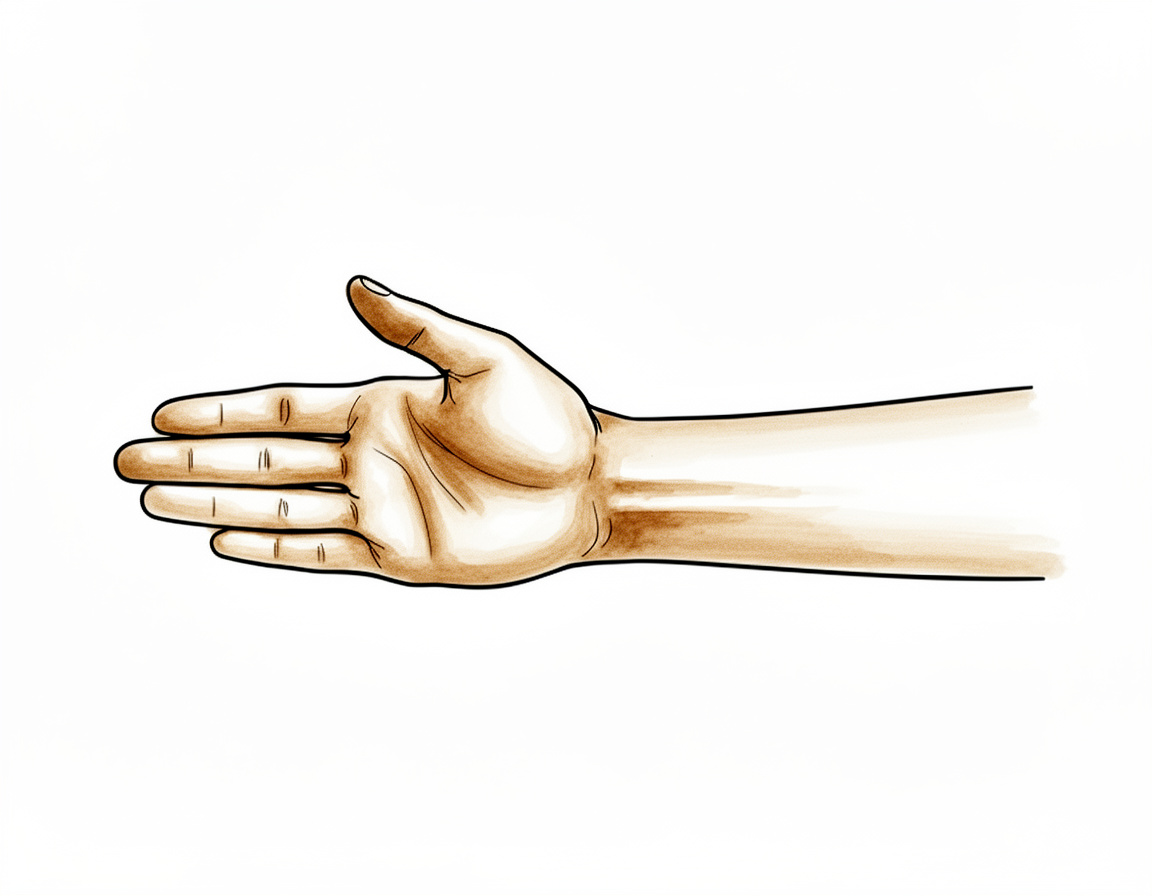
اپنی طاقت سے تمام انگلیاں پوری سیدھی کرنا (active composite extension)
اپنی کہنی میز پر ٹکا کر، انگلیوں کو جتنا ہو سکے سیدھا کریں، پھر دوسرے ہاتھ سے تھوڑا سا اور دبائیں۔ 5 تک گنیں، اور ڈھیلا چھوڑ دیں۔
10 بار، دن میں 3 سے 4 مرتبہ
Kieran Hirpara 4.0
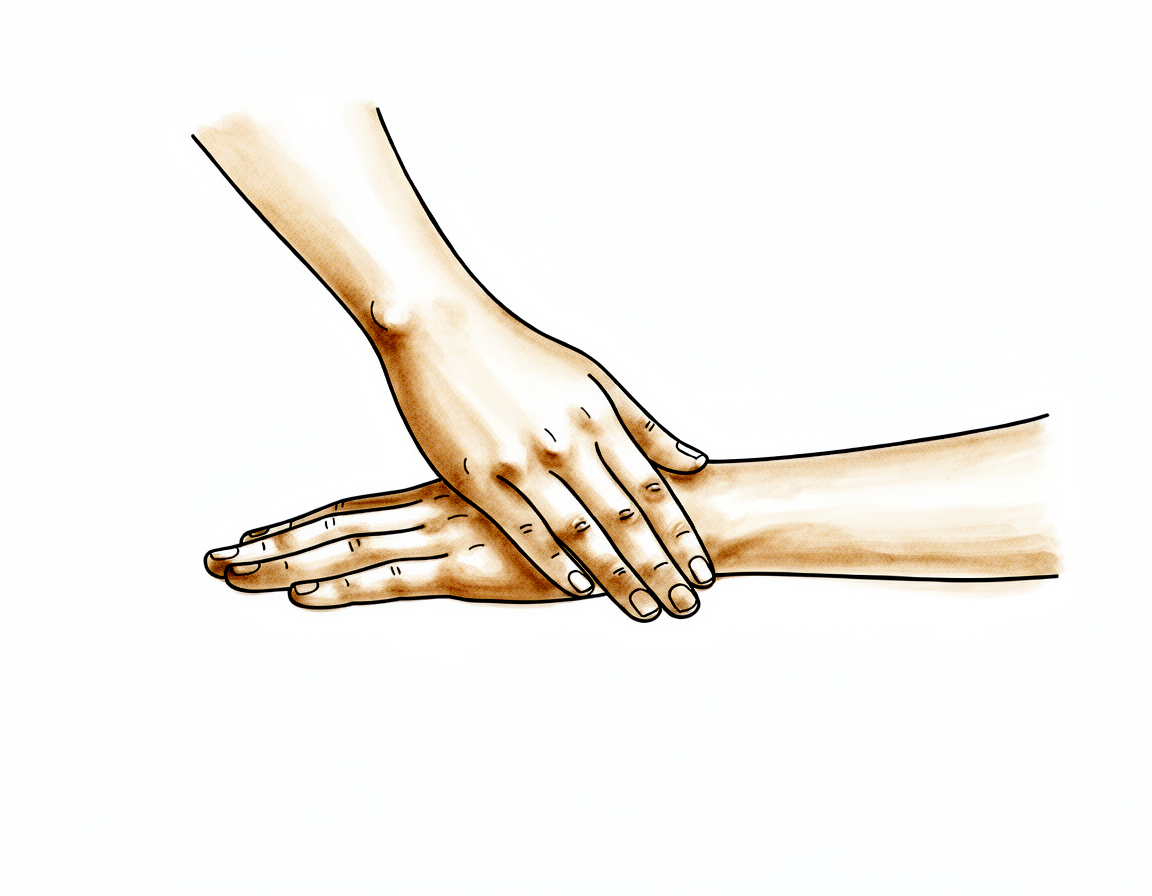
دوسرے ہاتھ کی مدد سے تمام انگلیاں پوری سیدھی کرنا (passive composite extension)
اپنا ہاتھ میز پر چپٹا رکھیں، ہتھیلی نیچے کی طرف۔ دوسرے ہاتھ سے ہاتھ کی پشت پر دباؤ ڈالیں اور اپنے جسم کی طرف 'مالش' کریں۔ 5 تک گنیں، اور ڈھیلا چھوڑ دیں۔
10 بار، دن میں 3 سے 4 مرتبہ
Kieran Hirpara 4.0
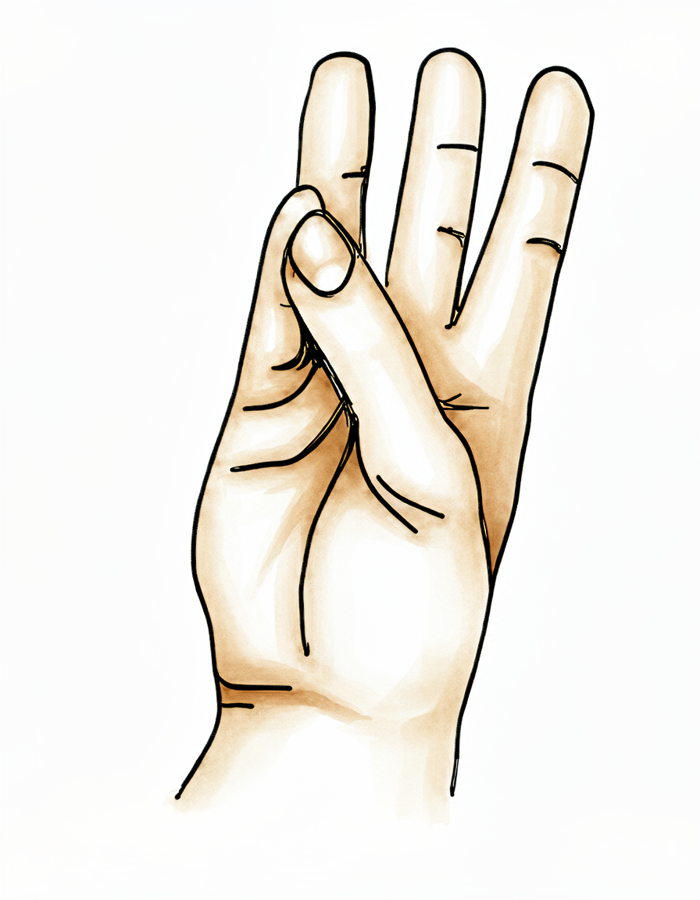
انگوٹھے کو انگلی کے سرے سے ملانا (thumb opposition)
انگلیوں کو سیدھا اور ڈھیلا رکھ کر شروع کریں۔ اپنے انگوٹھے کا سرا شہادت کی انگلی کے سرے سے ملائیں۔ 5 سیکنڈ تک اسی حالت میں رکھیں، پھر شروع والی حالت میں واپس آ جائیں۔
10 بار، دن میں 3 سے 4 مرتبہ
نیچے دی گئی ورزشیں صرف ڈاکٹر ہِرپرا اور اپنے ہینڈ تھراپسٹ کی رہنمائی کے مطابق شروع کریں، اور جو بھی حد اور پابندیاں آپ کو بتائی گئی ہیں ان کے اندر رہیں۔ ٹینڈن کو پھسلانے والی ورزشوں کا سلسلہ اور الگ الگ جوڑ موڑنے کی ورزشیں کھولے گئے ٹینڈن کو اس کے غلاف میں آزادی سے چلتا رکھتی ہیں تاکہ وہ بھرتے ہوئے زخم کے نشان میں چپک نہ جائے — یہی چیز انگلی کے اٹکنے کو اکڑاؤ کی شکل میں واپس آنے سے روکتی ہے۔ اپنی طاقت سے اور دوسرے ہاتھ کی مدد سے تمام انگلیاں پوری سیدھی کرنے کی ورزشیں انگلی کو پوری طرح سیدھا ہوتا رکھتی ہیں، انگوٹھے کو انگلیوں کے سروں سے ملانے کی ورزش چٹکی کی گرفت کو دوبارہ مضبوط کرتی ہے، اور کلائی کا اسٹریچ کلائی کو اس دوران اکڑنے سے روکتا ہے جب ساری توجہ انگلی پر ہوتی ہے۔ ہتھیلی میں زخم کے نشان کے عین اوپر کچھ ہفتوں تک چھونے پر درد متوقع ہے۔ جس ورزش سے تیز درد ہو، اسے روک دیں۔
آپ کے پروٹوکول کے بعد
یہ پروٹوکول Sarah Farrell، BOccThy (Bachelor of Occupational Therapy)، منظور شدہ ہینڈ تھراپسٹ (Accredited Hand Therapist)، کے اشتراک سے لکھا گیا ہے، اور اس میں Extend Rehabilitation کی منظور شدہ ہینڈ تھراپسٹ Ruby Doolan کی طرف سے سرجری کے بعد علاج کی تازہ رہنمائی (اپریل 2025) شامل ہے۔ یہ کلینک کے صحت یابی سے متعلق عمومی مشوروں کے ساتھ مل کر کام کرتا ہے: آپریشن کے بعد درد پر قابو پانا، زخم کی دیکھ بھال اور ہینڈ تھراپی کی بنیادی باتیں دیکھیں۔ خود آپریشن کے بارے میں جاننے کے لیے ٹریگر فنگر ریلیز دیکھیں۔
صحت یابی کا یہ خاکہ اور سنگِ میل مزید اس بنیاد پر بھی ہیں: ٹریگر فنگر ریلیز کے بعد بحالی کے شائع شدہ پروٹوکول، جن میں University of Virginia Hand Center اور Twin Cities Orthopedics کے پروٹوکول شامل ہیں، اور کھلے ٹریگر فنگر ریلیز کے نتائج پر شائع شدہ تحقیقات، جن میں آپریشن کے بعد بحالی کا ایک رینڈمائزڈ کنٹرولڈ ٹرائل (Saito et al., Journal of Clinical Medicine, 2023) اور پیچیدگیوں کا ایک بڑا سلسلہ (Bruijnzeel et al., Journal of Hand Surgery, 2012) شامل ہیں۔
حوالہ جات
[1] Saito T, Nakamichi R, Nakahara R, Nishida K, Ozaki T. The effectiveness of rehabilitation after open surgical release for trigger finger: a prospective, randomized, controlled study. J Clin Med. 2023;12(22):7187. https://pmc.ncbi.nlm.nih.gov/articles/PMC10671987/ [2] University of Virginia Hand Center. Trigger Finger Release Guidelines (post-operative therapy protocol). https://med.virginia.edu/orthopaedic-surgery/wp-content/uploads/sites/242/2015/11/Triggerfingerreleaseprotocol.pdf [3] Meletiou SD, Twin Cities Orthopedics. Post-operative Management of Trigger Release (A1 pulley release). https://tcomn.com/wp-content/uploads/2017/10/Trigger-Release-A1.pdf [4] Bruijnzeel H, Neuhaus V, Fostvedt S, Jupiter JB, Mudgal CS, Ring DC. Adverse events of open A1 pulley release for idiopathic trigger finger. J Hand Surg Am. 2012;37(8):1650–1656. https://pubmed.ncbi.nlm.nih.gov/22763058/ [5] Chanthanapodi P, Aodsup S. Comparative results of percutaneous and open surgery for trigger fingers: a propensity score analysis. Front Surg. 2025;12:1509292. https://pmc.ncbi.nlm.nih.gov/articles/PMC11922895/
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Trigger Finger Release (A1 Pulley Release) — Surgical Outcomes & Post-operative Rehabilitation
Topic scope: (A) the place of surgery in stenosing tenosynovitis (trigger finger/thumb) after failed conservative care (splinting, corticosteroid injection), and (B) post-operative rehabilitation after surgical division of the A1 pulley — open or percutaneous. This is an early-motion pathway: nothing is reconstructed, the catching is mechanically abolished the moment the pulley is divided, and the rehab exists to keep the now-free tendon gliding and the finger joints supple while the wound heals.
Defining principle of the rehab here: A1 pulley release removes the obstruction; it does not create a construct that needs protecting. Once the pulley is divided the flexor tendon glides freely and triggering does not usually recur. So — unlike a tendon repair, and like a carpal-tunnel decompression — the pathway is immediate active motion: full active finger flexion/extension and tendon glides from the first days, oedema and scar care, early light functional use, and a quick return. Most patients need no formal hand therapy at all; supervised therapy is reserved for the minority with pre-existing joint stiffness, long-standing triggering, or slow recovery. The single branch point is whether the finger was already stiff before surgery (long-standing fixed flexion / PIP contracture) — those patients need active therapy to recover motion the release alone cannot restore.
A. WHERE SURGERY SITS IN THE PATHWAY
Trigger finger is usually managed non-operatively first: activity modification, splinting, and corticosteroid injection, which resolves a substantial proportion of digits without surgery. Surgery (A1 pulley release) is reserved for digits that fail injection, recur, or present with a fixed deformity. The corpus contains the comparative evidence underpinning this stepped approach (percutaneous release vs steroid injection; one- vs two-injection regimens; corticosteroid solution choice) — Moderate (RCT). The rehab protocol on the patient page begins after that decision has been made, so this brief concentrates on the surgical and post-surgical evidence.
B. SURGICAL OUTCOMES & RESOLUTION RATES
Open release of the A1 pulley is one of the most reliable operations in hand surgery. The mechanical problem — a thickened tendon catching under a tight pulley — is solved by dividing the pulley, and the result is durable:
- In a series of 1,598 open releases, fewer than 1% required a second operation for persistent or recurrent triggering, with no nerve injuries and no deep infections [Bruijnzeel 2012]. About one digit in twenty had a documented post-operative problem, almost all minor and self-limiting (transient stiffness, scar tenderness). Strong (large cohort).
- Recovery of motion is slower in patients with diabetes, reinforcing the value of the exercise program in that group [Bruijnzeel 2012]. Moderate.
- A propensity-matched comparison with >3 years follow-up found no recurrences after open release, with median time to significant pain reduction of about one week and roughly half of patients back at work within ~2 weeks [Chanthanapodi 2025]. Moderate.
Take-home for rehab: because the operation itself abolishes the triggering, the rehabilitation is not "earning back" a surgical result — it is preventing the two things that can go wrong during healing: tendon adhesion and joint stiffness. Early glide and early extension are the levers.
C. OPEN vs PERCUTANEOUS RELEASE
Both techniques divide the same structure and converge to the same place.
- A Level I meta-analysis of 8 RCTs (548 patients) found no significant difference between open and percutaneous release in revision, complication, or pain rates — both are appropriate options [Casey 2024, J Hand Surg Am]. Strong (meta-analysis of RCTs).
- Larger RCT syntheses show percutaneous release confers faster early functional recovery — better short/mid-term Q-DASH, ~12 days earlier return to work, and shorter analgesic use — while long-term function, grip, motion and complication/revision rates are equivalent. Strong.
- Percutaneous (including ultrasound-guided/sonographically-controlled) technique is supported by multiple corpus series for efficacy and safety, with the main theoretical risks being incomplete release and digital nerve proximity, mitigated by surface landmarks and imaging [corpus percutaneous series]. Moderate.
Rehab implication: the post-operative program is essentially the same for both approaches — early active motion, glides, oedema and scar care. The patient page applies regardless of whether the release was open or percutaneous; percutaneous patients simply tend to be comfortable and back to activity a little sooner.
D. THE ROLE — AND LIMITS — OF POST-OPERATIVE HAND THERAPY
This is the central evidence point for the protocol, and it is one where "more therapy" is not automatically better.
- A prospective RCT compared 3 months of supervised rehabilitation after open
release against a self-directed home exercise program: at six months,
overall function, motion and pain were similar between groups. Supervised
therapy added further grip-strength recovery, and the patients who clearly
benefited from formal therapy were those whose **triggering had been present
12 months pre-operatively and those in housework/lighter-work roles [Saito 2023, J Clin Med]. Moderate (single RCT).
- Published surgeon and hand-therapy protocols (e.g. University of Virginia Hand Center; Twin Cities Orthopedics) start active and passive finger motion and tendon glides within the first days, add scar massage and desensitisation once the wound is healed, and reintroduce graded grip strengthening later — precisely the staged structure of the patient page. Consensus.
Bottom line: a well-performed home program carries most patients through. Formal hand therapy is reserved, not routine — escalate it for long-standing pre-operative triggering, pre-existing joint stiffness/contracture, manual or fine-use occupational demands, or slow motion/grip recovery.
E. COMPLICATIONS
Serious complications are uncommon (roughly <1–4% across series) and most "complications" are minor, self-limiting healing phenomena:
- Digital nerve injury — the most feared complication, particularly relevant to percutaneous technique (blind division near the radial digital nerve of the thumb and index) and to scar/retraction in open release. Rare in experienced hands; transient paraesthesia is more common than true division [corpus complication series]. Moderate.
- Incomplete release / persistent triggering — failure to fully divide the A1 pulley (or an A2/FDS slip contribution); a recognised cause of revision, more often discussed with percutaneous technique. Moderate.
- Recurrent triggering — uncommon after adequate open release (<1% reoperation in the 1,598-digit series) [Bruijnzeel 2012]. Strong.
- Infection — usually superficial; deep infection rare (none in the large open series) [Bruijnzeel 2012]. Strong.
- Bowstringing — a rare complication from excessive proximal pulley loss (A1 plus encroachment on A2); largely avoided by limiting division to A1 [bowstringing case literature]. Weak (case-level).
- Stiffness / flexion contracture / "flare" — the commonest self-limiting problem; transient PIP stiffness, scar tenderness and a post-operative inflammatory flare that settle with the motion, desensitisation and scar program. Recovery is slower in diabetes. Moderate. This is the category the rehabilitation program actively targets.
F. PHASED POST-OP TIMELINE (matches the patient protocol)
| Phase | Window | Protection | Motion / use | Therapy add-ons | Notes |
|---|---|---|---|---|---|
| I — Immediate active motion & oedema control | Day 0–2 | None beyond dressing | Active finger flexion/extension and finger "pumps" from day 1; tendon glides commenced | Elevation, ice, compression if provided; desensitisation (tap/rub over dressed wound) from day 1 | Nothing reconstructed -> motion is the priority; manage swelling actively |
| II — Glide & joint motion | Week 0–2 | None | Tendon glides (Series A/B), DIP & PIP blocking, composite extension; firm passive stretch into extension | Continue desensitisation | Goal: keep tendon gliding, prevent adhesion & stiffness; pain settles substantially (~1 wk) [Chanthanapodi 2025] |
| III — Scar maturation & function | Week 2–4 | Light functional use only | Full active fist + full composite extension by ~3 wk; build light daily-living use | Scar massage (firm circles) once wound healed; heat before / ice after exercises | No lifting/gripping/weight-bearing to ~4 wk; driving limited ~first week (full fist + safe control) |
| IV — Strengthening & return | Week 4+ | None | Graded grip/pinch (e.g. putty) once 4-wk precaution lifts -> full function | Supervised therapy if indicated (long-standing trigger, stiffness, slow recovery, occupational demand) [Saito 2023] | Manual workers return later than desk/light roles |
Timings are criteria-based and drawn from published surgeon/hand-therapy protocols; they are typical, not trial-mandated.
G. KEY CONTROVERSIES / EVIDENCE QUALITY
- Is routine post-op hand therapy necessary? The best available evidence (Saito 2023 RCT) says no for most — home exercise matches supervised therapy on function/pain/motion at six months, with supervised therapy adding grip strength and benefiting a defined subgroup (long-standing trigger, lighter-work roles). The protocol's "therapy reserved, not routine" stance is evidence-aligned. Moderate.
- Open vs percutaneous. Equivalent long-term outcomes and safety (Casey 2024 meta-analysis); percutaneous offers faster early recovery. The rehab is the same either way. The live debate is technique-side (nerve safety, completeness of release), not rehab-side. Strong on equivalence.
- The rehab protocol structure itself is consensus/expert, built from surgeon patient-guidance documents plus one rehabilitation RCT — there is no large trial dictating exact phase timings.
- Diabetes modifies recovery — slower motion recovery and a lower threshold to involve a hand therapist; not a different protocol, a different pace. Moderate.
H. EVIDENCE STRENGTH FLAGS (summary)
- STRONG (meta-analysis / RCTs / large cohort): open vs percutaneous equivalence in revision/complication/pain (Casey 2024, 8 RCTs); percutaneous faster early functional recovery (RCT syntheses); durability of open release (<1% reoperation, no nerve injury/deep infection in 1,598 digits, Bruijnzeel 2012).
- MODERATE (single RCT / cohorts): home exercise ~ supervised therapy at 6 months with grip-strength edge for supervised therapy (Saito 2023); percutaneous efficacy/safety series; slower recovery in diabetes; injection-vs- surgery comparative data.
- WEAK / CONSENSUS: the post-operative rehabilitation protocol structure and exact phase timings (surgeon/hand-therapy patient-guidance documents); bowstringing risk (case-level).
CITATIONS
RAG corpus (180,000+ Orthopaedic articles)
- Open Versus Percutaneous Fixation of Trigger Finger: Meta-Analysis of Clinical Outcomes. J Hand Surg Am. 2024. DOI: 10.1016/j.jhsa.2024.03.010
- Complications of Open Trigger Finger Release. J Hand Surg Am. 2010. DOI: 10.1016/j.jhsa.2009.12.040
- Differential Pulley Release in Trigger Finger: A Prospective, Randomized Clinical Trial. Hand (N Y). 2021. DOI: 10.1177/1558944721994231
- Percutaneous A1 pulley release vs steroid injection for trigger digit. J Hand Surg Eur. 2010. DOI: 10.1177/1753193410381824
- Comparative Study of A1 Pulley Release and Ulnar Superficialis Slip Resection in Trigger Finger. J Hand Surg Am. 2022. DOI: 10.1016/j.jhsa.2022.04.021
- Risk Factors for Requiring Ulnar Superficialis Slip Resection During Trigger Finger Release. J Hand Surg Am. 2024. DOI: 10.1016/j.jhsa.2024.08.013
- Impact of Flexor Tendon Traction Tenolysis on Clinical Outcomes in Open A1 Pulley Release. J Hand Surg Glob Online. 2024. DOI: 10.1016/j.jhsg.2024.09.010
- Ultrasound-Assisted Percutaneous Trigger Finger Release: Is It Safe? Hand (N Y). 2008. DOI: 10.1007/s11552-008-9137-8
- Evaluation of Percutaneous First Annular Pulley Release: Efficacy and Complications. J Hand Surg Am. 2016. DOI: 10.1016/j.jhsa.2016.04.009
- Sonographically controlled minimally-invasive A1 pulley release using a new guide. BMC Musculoskelet Disord. 2023. DOI: 10.1186/s12891-023-06982-x
- Percutaneous A1 pulley with corticosteroid injection for trigger finger release. J Orthop Surg Res. 2025. DOI: 10.1186/s13018-025-05776-2
- A Cost and Efficiency Analysis of the WALANT Technique for the Management of Trigger Finger. Plast Reconstr Surg Glob Open. 2019. DOI: 10.1097/gox.0000000000002509
- Management of Pediatric Trigger Thumb and Trigger Finger. J Am Acad Orthop Surg. 2012. DOI: 10.5435/jaaos-20-04-206
- What's New in Hand Surgery. J Bone Joint Surg Am. 2024. DOI: 10.2106/jbjs.23.01343
Trigger finger surgical & rehabilitation literature (URLs)
- Saito T, et al. The Effectiveness of Rehabilitation after Open Surgical Release for Trigger Finger: A Prospective, Randomized, Controlled Study. J Clin Med. 2023;12(22):7187. https://pmc.ncbi.nlm.nih.gov/articles/PMC10671987/
- Bruijnzeel H, et al. Adverse Events of Open A1 Pulley Release for Idiopathic Trigger Finger. J Hand Surg Am. 2012;37(8):1650-1656. https://pubmed.ncbi.nlm.nih.gov/22763058/
- Casey JC, et al. Open Versus Percutaneous Fixation of Trigger Finger: Meta-Analysis of Clinical Outcomes. J Hand Surg Am. 2024;49(6):570-575. https://pubmed.ncbi.nlm.nih.gov/38727666/
- Chanthanapodi P, Aodsup S. Comparative results of percutaneous and open surgery for trigger fingers: a propensity score analysis. Front Surg. 2025;12:1509292. https://pmc.ncbi.nlm.nih.gov/articles/PMC11922895/
- Complications of Percutaneous Release of the Trigger Finger. PMC. https://pmc.ncbi.nlm.nih.gov/articles/PMC6485534/
- Trigger Finger. StatPearls, NCBI Bookshelf. https://www.ncbi.nlm.nih.gov/books/NBK459310/
- Bowstringing as a complication of trigger finger release. J Hand Surg Am. 1988. https://www.jhandsurg.org/article/S0363-5023(88)80097-2/abstract
- Trigger Finger (patient information). British Society for Surgery of the Hand (BSSH). https://www.bssh.ac.uk/patients/conditions/15/trigger_finger
Published rehab protocols (patient-guidance — basis for the phase structure)
- University of Virginia Hand Center. Trigger Finger Release Guidelines (post-operative therapy protocol). https://med.virginia.edu/orthopaedic-surgery/wp-content/uploads/sites/242/2015/11/Triggerfingerreleaseprotocol.pdf
- Meletiou SD, Twin Cities Orthopedics. Post-operative Management of Trigger Release (A1 pulley release). https://tcomn.com/wp-content/uploads/2017/10/Trigger-Release-A1.pdf
- EmergeOrtho. Trigger Finger Release - Post-operative Instructions. https://emergeortho.com/wp-content/uploads/2022/06/Trigger-Finger-Release.pdf