Patients › Hand
Fracturas de dedos
Phalangeal and metacarpal fractures of the hand — non-operative care and indications for fixation.
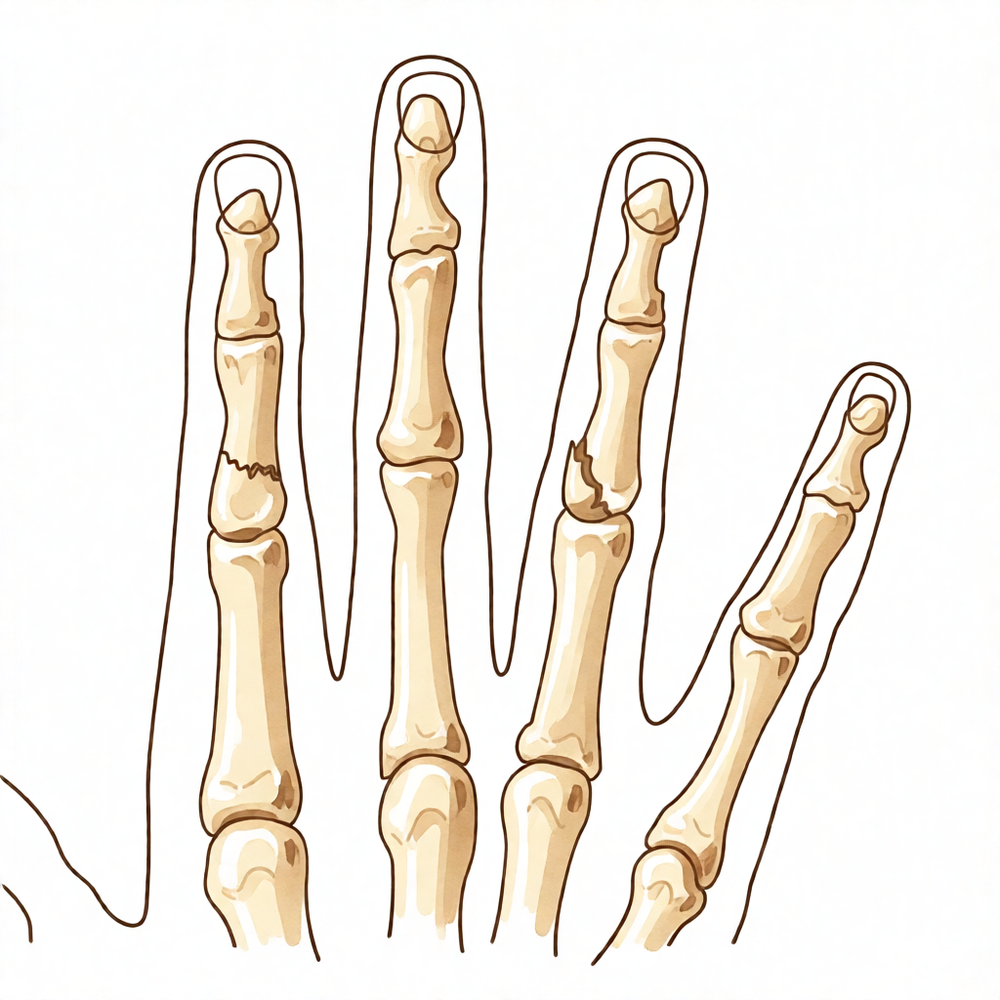
Qué está sintiendo
Un dedo roto suele producirse en un momento concreto. Un balón golpea la punta del dedo, usted cae sobre la mano o un golpe directo alcanza el dedo. Puede oír o sentir un chasquido o un crujido en ese instante. El dolor aparece de inmediato, y el dedo se hincha rápidamente. A menudo aparecen moratones en las horas siguientes.
El dedo lesionado puede verse doblado o torcido, o simplemente puede doler demasiado para moverlo. Puede notar que los dedos ya no quedan alineados entre sí al cerrar el puño. En los niños, la misma lesión suele producirse en la base del dedo, y el meñique y el pulgar son los que se lesionan con más frecuencia. Un aplastamiento de la punta del dedo puede romper la piel, y a veces la uña o la piel que la rodea se desgarran.
En los primeros días, el dolor es más agudo cuando intenta doblar el dedo o agarrar algo. Tareas sencillas como sostener un bolígrafo, abrocharse una camisa o girar el pomo de una puerta pueden doler. Al principio, el dolor a menudo le despierta por la noche. Durante las primeras dos a tres semanas, la hinchazón y el dolor van disminuyendo poco a poco a medida que el hueso empieza a soldarse.
Algunos signos de alarma requieren actuar el mismo día en que aparecen, no en su próxima cita. Acuda al servicio de urgencias ese mismo día si hay una herida en la piel sobre el dedo o la articulación lesionados, si se ve el hueso o si el dedo parece claramente deformado. Lo mismo se aplica si el dedo se pone pálido, frío, blanco o azulado, o si pierde de repente la sensibilidad o el movimiento en él después de la lesión. Si el dedo se pone caliente, rojo, hinchado y doloroso, sobre todo con fiebre, también necesita atención urgente ese mismo día. Para ninguno de estos casos necesita una derivación de su médico de cabecera.
Si el dolor no se calma con el paso de las semanas, empeora o le impide usar la mano o trabajar, acuda a su médico de cabecera o solicite una evaluación especializada.
¿Qué está ocurriendo realmente?
Una fractura de dedo es la rotura de uno de los pequeños huesos del interior del dedo. Cada dedo tiene tres de estos huesos, y el pulgar tiene dos. La fractura suele producirse cuando un golpe directo, una caída o una lesión deportiva doblan el hueso más allá de su límite. A veces se rompe más de un dedo a la vez, y los huesos de la muñeca o de la mano pueden lesionarse en el mismo accidente.
El hueso roto puede permanecer alineado o puede desplazarse de su sitio. Cuando se desplaza, los músculos y los tendones unidos a ese hueso tiran de los fragmentos rotos. Los tendones son los cordones que unen el músculo al hueso, y discurren tan cerca de los huesos del dedo que tiran de los fragmentos en cuanto el hueso cede. Esa tracción es la razón por la que un dedo roto puede verse doblado o más corto, y por la que no puede agarrar ni estirarse con normalidad mientras los fragmentos están desalineados.
El cuerpo empieza a reparar la fractura de inmediato. La sangre se acumula alrededor de la fractura, y el hueso empieza a soldarse de nuevo a través del espacio, de forma parecida a una rama agrietada que se cierra con madera nueva. El inconveniente es que todo lo que está cerca de la fractura también cicatriza. La sangre y la hinchazón se convierten en tejido cicatricial que puede pegar los tendones al hueso. Como los tendones están justo pegados al hueso, casi sin nada entre ellos, esta rigidez puede producirse incluso cuando la propia fractura era leve. Es la razón por la que un dedo que ha soldado bien todavía puede estar rígido y tardar en doblarse.
Si la fractura se extiende hasta la superficie de una articulación del nudillo, la superficie lisa de deslizamiento deja de encajar, lo que añade sus propios problemas. La mayoría de las fracturas de dedos se resuelven sin cirugía, pero algunas fracturas, sobre todo las que están desplazadas o son inestables, necesitan ayuda para mantenerse inmóviles mientras se curan.
Qué podemos hacer al respecto
El Dr. Kieran Hirpara, cirujano de extremidades superiores en el Mater Private Hospital Rockhampton, adapta el tratamiento a su lesión concreta. Algunos dedos rotos se curan sin operación, y otros necesitan cirugía poco después de la lesión, por lo que una evaluación rápida es importante. Por lo general, los pacientes son derivados a nuestra clínica por su médico de cabecera; si un fisioterapeuta le ha sugerido que nos consulte, igualmente necesitará una derivación de su médico de cabecera para poder acceder al reembolso de Medicare. En la clínica tomamos su historia clínica, examinamos su mano y solicitamos radiografías cuando son necesarias. Las radiografías muestran si el hueso sigue alineado, cuánto se ha desplazado y si la fractura se extiende hasta una superficie articular.
La mayoría de las fracturas de dedos pueden tratarse sin cirugía. Si el hueso está estable o solo ligeramente desplazado, lo mantenemos inmóvil con una férula o un yeso mientras se cura. Una férula para un dedo roto a menudo mantiene el nudillo doblado y las articulaciones del dedo rectas, y puede dejar la muñeca libre para moverse. Algunas lesiones se sujetan en cambio con una pequeña tracción constante, que mantiene los fragmentos alineados sin una operación. Sujetar con cinta el dedo lesionado al dedo vecino es otra forma de darle apoyo, y esto funciona bien en muchas fracturas de dedos en niños. Controlamos el dedo con nuevos estudios de imagen cuando es necesario, y lo ponemos en movimiento por etapas en cuanto la fractura puede tolerarlo. Moverlo pronto es importante porque un dedo que se mantiene inmóvil demasiado tiempo se pone rígido, incluso cuando el hueso suelda bien.
La cirugía se recomienda desde el principio cuando el hueso está muy desplazado, cuando no se mantiene en su sitio o cuando la fractura se extiende hasta una articulación del nudillo y las superficies dejan de encajar. Algunos patrones siempre la necesitan, como una articulación que se ha fracturado y luxado a la vez, o una fractura cerca de la uña en un niño con la piel desgarrada por debajo. Sus propias necesidades también cuentan: un trabajador manual que necesita un agarre fuerte puede elegir de forma distinta a alguien cuyo trabajo es ligero. El objetivo de la cirugía es mantener los fragmentos en la posición correcta para que el dedo pueda moverse mientras se cura. Repasaremos las opciones con usted, incluido lo que cada opción supone en cuanto a dolor, rigidez y el aspecto y la fuerza finales de su dedo, y decidiremos juntos.
Sea cual sea la opción, las primeras semanas son parecidas. Los analgésicos le mantienen cómodo mientras disminuye la hinchazón. Usted protege el dedo de golpes y esfuerzos mientras el hueso se suelda. La terapia de mano empieza en el momento adecuado para su lesión, con ejercicios que recuperan la capacidad de doblar y estirar el dedo sin alterar el hueso que se está curando.
Qué esperar
La mayoría de los dedos rotos se curan bien, pero el dedo suele tardar más en sentirse normal que el hueso en soldarse. Muchas fracturas se sueldan en 4 semanas, y la mayoría se curan entre las 5 y las 9 semanas. El tiempo medio de curación es de unas 6 semanas. Durante esas semanas el dedo permanece protegido con una férula o un yeso, y el dolor y la hinchazón disminuyen de forma constante. En cuanto la fractura puede tolerarlo, el movimiento se recupera por etapas.
Cuánta función recupere depende de la propia fractura. Las fracturas de los pequeños huesos de los dedos suelen evolucionar bien, y la mayoría de las personas recuperan una buena función a las nueve semanas. Algunos patrones son más difíciles: las fracturas cerca de las articulaciones de los nudillos, las fracturas en varios fragmentos y las fracturas con la piel de alrededor muy dañada pueden dejar el dedo más rígido o más débil de lo que le gustaría. La rigidez es el contratiempo más frecuente después del tratamiento, y puede producirse incluso cuando el hueso ha soldado perfectamente. Por eso el dedo se mueve pronto siempre que sea seguro hacerlo, y por eso la terapia de mano es tan importante.
Algunas cosas pueden salir mal por el camino. A veces el hueso tarda en soldarse o no llega a soldarse. A veces se suelda en una mala posición, lo que puede limitar cuánto se dobla y se estira el dedo. Si una fractura cerca de una articulación del nudillo se cura desalineada, esa articulación puede perder capacidad para doblarse y estirarse. Estos problemas son la razón por la que su cirujano controla el dedo con radiografías mientras se cura, y por la que es importante seguir las indicaciones sobre la férula o el yeso.
Después de la cirugía, el hueso se mantiene en su sitio con agujas, tornillos o una pequeña placa para que el dedo pueda empezar a moverse antes. La mayoría de las personas recuperan un buen movimiento y una buena fuerza de agarre, y muchas vuelven a su trabajo y actividades habituales a medida que el dedo lo permite. La terapia de mano después de la cirugía se realiza con Ruby Doolan en Extend Rehabilitation. Ruby dirige sus ejercicios y confecciona cualquier férula que necesite a lo largo del proceso.
Si el dolor o la rigidez no se calman con el paso de las semanas, empeoran o le impiden trabajar o usar la mano, acuda a su médico de cabecera o solicite una evaluación especializada.
Cuándo consultar a un especialista
Busque atención urgente si el dedo parece claramente doblado o torcido, si hay una herida en la piel sobre la lesión, si se ve el hueso, si el dedo se pone pálido, frío, blanco o azulado, o si pierde de repente la sensibilidad o el movimiento en él. Un dedo que se pone caliente, rojo, hinchado y doloroso, sobre todo con fiebre, también necesita atención urgente ese mismo día. Para ninguno de estos casos necesita una derivación de su médico de cabecera. Si no puede comunicarse con la clínica, acuda al servicio de urgencias más cercano.
Acuda a su médico de cabecera o solicite una evaluación especializada si el dolor no se calma con el paso de las semanas, si empeora, o si la hinchazón, el movimiento o el agarre no mejoran semana tras semana mientras el hueso se cura. Algunas lesiones de los dedos parecen leves al principio, pero aun así necesitan una evaluación adecuada, por lo que vale la pena revisar cualquier dedo que duela, esté hinchado o no se mueva con normalidad en lugar de esperar a que pase.
En mayor profundidad
Advanced reading: the deeper science (optional)
Esta sección va más allá de lo necesario para que usted tome sus propias decisiones de tratamiento. Vale la pena leer más sobre las fracturas de dedos por dos hallazgos que contradicen la práctica habitual: los antibióticos profilácticos no parecen ser útiles en una fractura abierta de la punta del dedo y, en la difícil fractura articular del nudillo medio, ningún método de fijación ha demostrado ser mejor que los demás.
Los antibióticos en una fractura abierta de la punta del dedo no reducen la infección
A una fractura abierta de la falange distal, con el hueso expuesto a través de una herida, normalmente tras un aplastamiento, se le administran de forma rutinaria antibióticos profilácticos, siguiendo el principio general de que las fracturas abiertas los necesitan.
La evidencia no lo respalda en este caso. En 353 pacientes, los resultados no muestran ningún efecto de los antibióticos profilácticos sobre la tasa de infecciones superficiales tras fracturas abiertas de la falange distal, y los autores concluyen que el foco debe ponerse en la irrigación y el desbridamiento rápidos, en lugar de la administración de antibióticos profilácticos [1].
La diferencia está entre limpiar la herida y medicarla. Eliminar mecánicamente la contaminación es lo que reduce la infección; no se demostró que los antibióticos aportaran algo más en este contexto. Dados los costes del uso innecesario de antibióticos, conviene saber que no administrarlos tras un cuidado minucioso de la herida responde a la evidencia y no a un descuido.
En la fractura-luxación de la articulación media, ninguna técnica es superior
Las fracturas-luxaciones de la articulación interfalángica proximal se encuentran entre las lesiones más difíciles de la mano: una articulación pequeña con una superficie fracturada que debe reducirse y mantenerse reducida mientras se mueve.
En 735 pacientes, la comparación resulta instructiva precisamente porque no logra diferenciar las opciones: la fijación percutánea logró el mayor rango de movimiento postoperatorio, la fijación con agujas con bloqueo de la extensión dio como resultado la mayor fuerza de agarre, y ningún método de tratamiento ni tipo de fractura ofreció resultados sistemáticamente mejores que otro [2].
Cuando está afectada más de la mitad de la superficie articular, una opción reconstructiva es rehacerla con un injerto del hueso ganchoso. En 235 pacientes, la artroplastia con hemiganchoso resultó fiable y eficaz, proporcionando alivio de los síntomas y recuperación funcional [3].
Por qué la rigidez es el verdadero enemigo
La dificultad de estas lesiones no se debe a que el hueso no se cure: las fracturas de dedos consolidan con facilidad. Se debe a que el dedo se vuelve rígido.
Los tendones flexores y extensores discurren justo sobre el hueso, con muy poco tejido blando entre ellos, de modo que la sangre y la hinchazón alrededor de una fractura se organizan en una cicatriz que une los tendones al hueso. Este proceso está muy avanzado en pocas semanas y, una vez establecido, es difícil de revertir.
Por eso las fracturas de dedos se movilizan pronto siempre que la fractura sea lo bastante estable para permitirlo, y por eso la fijación se elige en parte según si permite el movimiento, y no solo según la rigidez con la que sujeta el hueso. También explica la situación aparentemente paradójica de una fractura perfectamente consolidada en la radiografía y un dedo que no se dobla: el hueso nunca fue el problema.
Referencias
[1] Metcalfe D, Aquilina AL, Hedley HM. Antibióticos profilácticos en fracturas abiertas de la falange distal: revisión sistemática y metaanálisis. J Hand Surg Eur Vol. 2015;41(4):423-30. https://doi.org/10.1177/1753193415601055
[2] Demino C, Yates M, Fowler JR. Tratamiento quirúrgico de las fracturas-luxaciones de la articulación interfalángica proximal: revisión sistemática. Hand (N Y). 2019;16(4):453-60. https://doi.org/10.1177/1558944719873152
[3] Faulkner H, Graham DJ, Hile M, Lawson RD, Sivakumar BS. Artroplastia con hemiganchoso para la fractura de la base de la falange media: revisión sistemática. Hand (N Y). 2021;18(2):300-6. https://doi.org/10.1177/15589447211014623
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Recent PIP joint fractures present challenges in both diagnosis and treatment, with final outcomes significantly impacting global finger and hand function [1].
- Most pediatric hand fractures are treated nonoperatively with good results [2].
- A subset of pediatric phalangeal fractures requires prompt recognition and surgical intervention to minimize complications [2].
- The majority of hand fractures can be treated without surgery [3].
- Surgery offers distinct advantages in properly selected cases of hand fractures [3].
- Good or excellent function was achieved in 94% of metacarpal fractures treated with external fixation by nine weeks [4].
- Good or excellent function was achieved in 85% of phalangeal fractures treated with external fixation by nine weeks [4].
- No differences in outcome were observed between dorsal and lateral plate fixation for finger proximal phalangeal fractures [5].
- Approximately one quarter of open finger fractures will likely need more than one surgical procedure [6].
- The need for multiple surgical procedures in open finger fractures is especially common in more severely injured fingers, due to crush or with vascular impairment [6].
- Results from external fixation of closed metacarpal and phalangeal fractures were similar to those obtained in the management of stable and undisplaced fractures [7].
- Indications for surgical treatment of finger fractures are more clearly defined than previously [8].
- Operative techniques and implants for osteosynthesis of finger fractures are continuing to evolve and improve [8].
- Results for finger fracture treatment vary according to fracture type, surgeon experience, and patient compliance [8].
- It is recommended that all finger fractures should be assessed and treated by surgeons with training in the management of hand injuries [9].
- Conservative functional techniques are the optimum treatment for the majority of patients with single metacarpal fractures [10].
- All six fingers in a study of intramedullary fixation through a volar extra-tendon sheath approach obtained satisfactory union of proximal phalangeal fractures [11].
- No patient complained of pain at the final follow-up in a study of intramedullary fixation through a volar extra-tendon sheath approach [11].
- Open finger fractures formed the majority of the workload of open fractures at a specific trauma centre [12].
- Open finger fractures usually required simple treatments only [12].
- Traction splinting has been shown to be successful in the treatment of closed proximal phalangeal fractures [13].
- Injuries sustained in the thumb and index finger were more likely to undergo unplanned reoperation after vascular reconstruction [14].
- The likelihood of unplanned reoperation for thumb and index finger injuries may guide initial treatment decision-making and postoperative follow-up [14].
- Miniature plates and screws are applicable for selected unstable metacarpal and phalangeal fractures of certain configurations [17].
- Miniature plate fixation showed to be safe and effective when used for treatment of extra-articular metacarpal and proximal phalangeal fractures [19].
- Most pediatric phalangeal fractures can be treated nonsurgically [22].
- A small subset of pediatric phalangeal fractures benefits from surgical intervention [22].
- Screw fixation is suggested to achieve patient satisfaction and optimal functional recovery of closed, isolated proximal phalanx fractures of the long fingers [23].
- The Ichi-Fixator system is a definitive treatment option for managing various phalangeal fractures [28].
- Taping finger fractures can be recommended irrespective of the degree of displacement or the need for reduction in children [44].
- Intramedullary fixation approaches have been reviewed for metacarpal fractures, phalangeal fractures, and interphalangeal joint arthrodesis [55].
- Percutaneous compressive bone tie was used to treat two intraarticular proximal phalangeal fractures of the thumb with satisfactory outcomes [68].
- Full range of movements was achieved within 3 weeks in a study using percutaneous compressive bone tie for thumb phalangeal fractures [68].
- No complications were reported in a study using percutaneous compressive bone tie for thumb phalangeal fractures [68].
- No need for implant removal was reported in a study using percutaneous compressive bone tie for thumb phalangeal fractures [68].
Anatomy & Pathophysiology
Bony Anatomy
- All phalanges consist of a proximal base, a central diaphysis, and a distal head [52].
- In contrast with the metacarpals, the bases of all the phalanges and not the heads develop as metaphyses [52].
- The distal portion of the distal phalanx is referred to as the tuft [52].
- Fingers usually follow a typical pattern of relative lengths where the tip of the index finger extends to the base of the nail of the middle finger, the tip of the ring finger to the mid-aspect of the middle finger nail, and the tip of the small finger to a corresponding point [52].
- The length of the metacarpal and the phalanges of the same finger resembles the series of Fibonacci [79].
- In complex flexion, a finger describes an equiangular spiral [79].
- The articulations of the fingers form a triarticular chain that flexes toward the thumb and the palm to allow grasp [79].
- The interphalangeal articulations of the digits function uniquely in flexion–extension and their trochlear-shaped articulations are closely congruent throughout excursion of motion [79].
- The normal finger phalangeal joint surfaces are congruent throughout the arc of motion of the interphalangeal joints [52].
- The third and fourth metacarpal heads help stabilize the metacarpal arch by providing attachments for the transverse metacarpal ligament [18].
- The proximal phalanx of either the middle or the ring finger is important functionally because its absence creates a hole through which small objects can pass and impairs scooping maneuvers [18].
- The small finger plays an important role in palmar grip because of the mobility of its CMC joint and the action of the hypothenar muscles [33].
- The small finger increases the span of the hand for grasp owing to its abduction moment [33].
- The ring finger forms the keystone of the palmar arch and participates in power grip [48].
- The ring finger plays a minimal role in precision pinch [48].
Joint Anatomy & Ligaments
- The articulations of the digits have two firm collateral ligaments and a thick reinforced anterior capsule, the anterior fibrocartilage, also known as the volar plate [79].
- The fibrous dorsal capsule of the digit articulations is thin and lax [79].
- The interphalangeal joint is a stable uniaxial hinge joint [79].
- Flexion of the metacarpophalangeal joint is about 85 degrees [79].
- Flexion of the proximal interphalangeal joint is about 115 degrees [79].
- Flexion of the distal interphalangeal joint is 80 degrees [79].
- The index finger is capable of less flexion than the other fingers because it opposes the thumb [79].
- The normal ulnar inclination of the fingers occurs at the metacarpophalangeal joints [84].
- Ulnar inclination is most marked in the index finger, less in the middle and little fingers, and almost non-existent in the ring finger [84].
- The ulnar inclination is due to anatomical factors including asymmetry of the metacarpal heads and collateral ligaments, tendon crossing on the ulnar side, intrinsic muscle predominance, and forward displacement of the ulnar metacarpals [84].
- The ulnar inclination is normally limited by capsuloligamentous resistance at the MP joints and by the action of the interosseous muscles [84].
- The dislocation of the carpometacarpal joint of the little finger causes rupture of the hamatometacarpal and intermetacarpal ligaments [65].
- The dislocation of the carpometacarpal joint of the little finger leaves intact the deep transverse metacarpal ligament and the extensor and flexor carpi ulnaris tendons [65].
Soft Tissue & Tendon Anatomy
- The extensor tendons pass from the forearm onto the dorsum of the hand through six compartments beneath the extensor retinaculum [83].
- The first compartment contains the extensor pollicis brevis and the abductor pollicis longus [83].
- The second compartment contains the extensors carpi radialis longus and brevis [83].
- The third compartment contains the extensor pollicis longus [83].
- The fourth compartment contains the four tendons of the extensor digitorum communis plus the extensor indicis proprius [83].
- The fifth compartment contains the extensor digiti quinti [83].
- The sixth compartment contains the extensor carpi ulnaris [83].
- The interosseous muscles produce lateral movements of fingers through their insertions on the lateral aspect of the base of the proximal phalanges [89].
- When the metacarpophalangeal joint is in extension, the interosseous muscles extend the distal phalanges [89].
- When the metacarpophalangeal joint is in flexion, the interosseous muscles reinforce flexion of the proximal phalanx and lose their extensor action on the distal phalanges [89].
- The lumbrical muscles are able to extend the two distal phalanges whether the metacarpophalangeal joint is in extension or flexion [89].
- The lumbricals participate in extension of the distal phalanges by pulling distally on the flexor profundus tendon when this muscle is at rest [89].
- The palmar skin is anchored to the underlying fascial planes by a system of fibrous tracts [80].
- The palmar skin adheres closely to the aponeurosis in the mid-palmar area [80].
- In all other areas, the deep aspect of the skin is separated from the superficial palmar fascia by a layer of fatty tissue divided into compartments by fibrous septa [80].
- The metacarpophalangeal pad sits transversely over the base of the fingers from the ulnar to the radial border of the hand [80].
- The pulp has a lobulated palmar pad where fibrous septa join the periosteum of the distal phalanx to the deep aspect of the dermis [80].
- The cutaneous striations that make up fingerprints reflect the arrangement of the papillary ridges of the underlying dermis [80].
- The concentric arrangement of striae at the pulp ensures the presence of a group of striae perpendicular to the force exerted, whatever its direction [80].
- The soft tissue of the fingertips is tightly anchored [81].
- The soft tissue of the fingers between the fingertips and the area of the aponeurosis is mobile and flexible [81].
- The mobile soft tissue of the fingers overlies the fibrous tendon sheaths and extends from the distal phalanges to the metacarpophalangeal joints [81].
- The midlateral finger incision allows the neurovascular bundle to be carried volarward with the volar flap of the incision [47].
- On the radial sides of the index and middle fingers and on the ulnar side of the little finger, the dorsal branch of the digital nerve should be preserved if possible [47].
Pathophysiology & Mechanism of Injury
- Intrinsic and extrinsic tendon insertions act as deforming forces to create typical angulation patterns in phalangeal fractures [52].
- Proximal and middle phalangeal shaft fractures typically collapse into apex volar angulation because of the proximal flexion moment of the intrinsics and distal extensor moment of the extensor mechanism [52].
- Intraarticular fractures that disrupt joint congruency can occur at either the distal (condylar fracture) or proximal (pilon or proximal condylar fracture) articular surface [52].
- Most commonly, intraarticular phalangeal fractures are produced by an axial loading injury [52].
- Fractures of the proximal phalangeal shaft typically exhibit an apex palmar angulation with the fracture gap wider volarly and compressed dorsally [36].
- The intrinsic muscles flex the proximal fragment of a proximal phalangeal shaft fracture, whereas the distal fragment is extended by the attachment of the central slip to the dorsal lip of the middle phalanx [36].
- The axis of rotation of proximal phalangeal fractures lies on the fibro-osseous border of the flexor tendon sheath [36].
- The moment arm from the rotational axis of the fracture site to the extensor tendon is greater than that to the flexor tendon [36].
- Fracture hematoma permeates the zone of injury and incites a proliferative fibroblastic response of the multiple surrounding collagenous structures [36].
- Scar tissue tends to involve all of the structures within the zone of injury, producing adherence between the bone and the adjacent tendons, joint capsule, and ligaments [36].
- Adhesions formed between the extensor mechanism and the fracture may result in loss of extensor glide [36].
- The mallet finger deformity is characterized by a loss of active distal interphalangeal joint extension with full passive ROM evident [61].
- The mallet finger reflects the loss of normal extensor force transmission via the terminal tendon insertion onto the distal phalanx [61].
- The unopposed flexor digitorum profundus pulls the distal joint into flexion in mallet finger [61].
- The usual mechanism of injury for mallet finger involves sudden passive flexion of the actively extended distal interphalangeal joint [61].
- Disruption of the terminal tendon in mallet finger may be entirely confined to the tendon or may involve an avulsed fracture fragment from the dorsal lip of the distal phalanx proximal articular surface [61].
- The forces of the extensor digitorum communis and of the flexor superficialis on the middle phalanx have a component that produces extension of the proximal phalanx [89].
- The intrinsic muscles (lumbrical and interossei) normally oppose the extension force on the proximal phalanx produced by extrinsic tendons [89].
- When intrinsic muscles are paralyzed, no force exists to prevent the proximal phalanx from swinging into hyperextension if the extensor digitorum communis and flexor superficialis are active [89].
- Shortening and closing an injury that leads to proximal migration of the FDP from its insertion at the base of the distal phalanx may result in a lumbrical-plus finger [31].
- In a lumbrical-plus finger, the FDP tendon retracts and creates tension on the extensor mechanism through the lumbrical that originates off the FDP tendon, causing paradoxical IP joint extension with active digit flexion [31].
- The "jammed" finger with a swollen, painful PIP joint usually involves a volar plate injury or small nondisplaced avulsion fracture off the volar base of the middle finger epiphysis [29].
- Salter-Harris II fractures of the digits are an extremely common hand fracture with the little finger proximal phalanx being the most commonly injured [29].
- Salter-Harris II fractures of the digits usually occur because of a jamming or hyperextension injury to the finger resulting in an abduction deformity [29].
- Malrotation in Salter-Harris II fractures does not remodel and can result in problems with grip formation [29].
- Seymour fractures are a Salter-Harris I/II or juxtaphyseal fracture of the distal phalanx with interposed nail bed at the fracture site [29].
- Seymour fractures are open fractures but are often missed [29].
- Missed Seymour fractures have a high rate of complication including infection and nail or physeal growth disturbance [29].
- The key to diagnosis of Seymour fractures is disruption of the nail plate/cuticle as well as a displaced fracture of the distal phalanx on radiographs [29].
- Displaced phalangeal neck fractures require reduction and pin fixation which can usually be achieved through a closed fashion [29].
- Condyle fractures can often also be treated with closed reduction and pinning [29].
- Open procedures for condyle fractures increase a risk for osteonecrosis [29].
- The dislocation of the carpometacarpal joint of the little finger results in fixed supination of the finger, disturbing the normal axis of movement and weakening power grip if treatment is delayed [65].
- This deformity may be obscured by swelling and bruising on the ulnar border of the hand [65].
- Palmar dislocation of the metacarpophalangeal joint is a rare injury where the mechanism is likely hyperextension force applied during strong active flexion [127].
Classification
- Type I phalangeal neck fractures are defined as undisplaced fractures [148].
- Type II phalangeal neck fractures are defined as displaced fractures where the distal fragment maintains some bone-to-bone contact with the proximal fragment [35, 148].
- Type III phalangeal neck fractures are defined as displaced fractures with loss of bone-to-bone contact between the proximal and distal fragments at the fracture site [35].
- A minimally displaced phalangeal neck fracture should be classified as Type II rather than Type I [148].
- Salter-Harris type II fractures of the proximal phalanx are the most frequent phalangeal fractures in children [74].
- Type II D phalangeal neck fractures tend to occur in young children and the majority involve the middle phalanx [146].
Clinical Presentation
Epidemiology and Demographics
- Fractures of the finger phalanges account for about 10% of all fractures seen [42].
- Finger phalangeal fractures are the second most common fracture in males [42].
- The little and ring fingers are the most affected by finger phalangeal fractures [42].
- The prevalence of little finger phalangeal fractures is 32.5% [42].
- The prevalence of ring finger phalangeal fractures is 25.8% [42].
- The prevalence of thumb phalangeal fractures is 18.4% [42].
- The prevalence of middle finger phalangeal fractures is 14.3% [42].
- The prevalence of index finger phalangeal fractures is 9.0% [42].
- Direct blow or assault is the most common mode of injury for finger phalangeal fractures, accounting for 39.1% of cases [42].
- Falls from standing height account for 29.5% of finger phalangeal fractures [42].
- Sports injuries account for 23.8% of finger phalangeal fractures [42].
- Approximately 70% of all phalangeal and metacarpal fractures occur in patients between the ages of 11 and 45 years [52].
- Phalangeal fractures are more common in men than women [52].
- Hand and finger fractures are the second most common fracture presenting to emergency departments in the pediatric population [29].
- Pediatric hand and finger fractures have a bimodal age distribution with peaks at 0 to 2 years of age and 12 to 16 years of age [29].
- The most commonly injured location in pediatric hand fractures is the base of the proximal phalanx, accounting for 67% of cases [29].
- In pediatric hand fractures, the little finger is the most commonly injured border ray at 52.2% [29].
- In pediatric hand fractures, the thumb is the second most commonly injured border ray at 23.5% [29].
- Open fractures of the phalanges are relatively common, with the highest prevalence seen in 36- to 64-year-old males [42].
- The distal phalanges are the most common site for open phalangeal fractures, with 25.3% of fractures at this site being open [42].
- About 55% of patients with multiple phalangeal fractures have other phalangeal fractures as the associated injury [42].
- The average age of patients presenting with multiple phalangeal fractures is 55.4 years [42].
Mechanism and Injury Patterns
- Proximal and middle phalangeal shaft fractures typically collapse into apex volar angulation due to the proximal flexion moment of the intrinsics and distal extensor moment of the extensor mechanism [52].
- Intraarticular phalangeal fractures that disrupt joint congruency are most commonly produced by an axial loading injury [52].
- The classic "jammed" finger with a swollen, painful PIP joint usually involves a volar plate injury or small nondisplaced avulsion fracture off the volar base of the middle finger epiphysis [29].
- Phalangeal neck and condyle fractures have a similar presentation to a simple "jammed" finger and are often missed [29].
- Toddlers and preschool age children usually sustain hand injuries while at home, usually as a crush injury [29].
- Adolescents most often get injured outside the home with sporting activities [29].
- A spiral fracture of the proximal phalanx of the index finger can result from finger wrestling [25].
- Severe mincer injuries carry a potential risk of damaging vital structures if the caught hand is freed by rotating the handle in the reverse direction [27].
- Punch injuries commonly occur in road traffic accidents and are usually associated with other serious injuries of the hand, wrist, and distal forearm [58].
Clinical Examination and Diagnosis
- Appropriate evaluation of hand and finger fractures includes clinical examination and radiographs [29].
- Clinical examination must assess for open injuries and angular and rotational malalignment of the injured ray [29].
- Rotational alignment can be confirmed by ensuring that all fingers point to the scaphoid tubercle when the fingers are flexed [29].
- Radiographs should include PA, lateral, and oblique views of the injured location [29].
- The coronal plane deformity in Salter-Harris II fractures is easy to assess, but extra care must be taken to assess for rotational deformity, which is not as obvious on radiographs [29].
- Prolonged immobilization of simple "jammed" finger injuries can result in significant joint stiffness [29].
- Seymour fractures are open fractures that are often missed [29].
- The key to diagnosing Seymour fractures is disruption of the nail plate/cuticle, which indicates disruption of the nail bed and the likelihood of an open fracture with interposed tissue [29].
- Radiographs for Seymour fractures reveal a displaced fracture of the distal phalanx [29].
- A meticulous examination of the patient’s hand is required for injury diagnosis [52].
- Open finger fractures formed the majority of the workload of open fractures at a trauma centre but usually required simple treatments only [12].
- Injuries sustained in the thumb and index finger were more likely to undergo unplanned reoperation, which may guide initial treatment decision-making and postoperative follow-up [14].
Pediatric Specifics
- Most pediatric phalangeal fractures can be treated nonsurgically, but a small subset benefits from surgical intervention [22].
- Most phalangeal neck fractures in children less than 3 years old obtained satisfactory results [16].
- Articular fractures of the fingers in children often result in sequelae, with a rate as high as 50% when the fracture was displaced initially [21].
- Complications of distal phalanx fractures in children are frequent [100].
- Avascular necrosis following phalangeal neck fractures usually affects the little finger and presents with stiffness [57].
- Further surgery is not often required short term for avascular necrosis following phalangeal neck fractures in children [57].
- Salter-Harris II fractures of the digits are an extremely common hand fracture in children, with the little finger proximal phalanx being the most commonly injured [29].
- Treatment for Seymour fractures involves removal of the nail plate with débridement of the fracture site, extrication of the interposed nail bed, and reduction of the fracture [29].
- If a Seymour fracture is unstable, it may require Kirschner wire placement in addition to immobilization in splint/cast [29].
- Antibiotics are a necessity to prevent infection in Seymour fractures as these are open fractures [29].
- Recommended antibiotic treatment for Seymour fractures includes a dose of IV antibiotic in the emergency department followed by a 7- to 10-day course of oral antibiotic [29].
- A first-generation cephalosporin is the preferred antibiotic for Seymour fractures [29].
- Displaced phalangeal neck fractures in children require reduction and pin fixation which can usually be achieved through a closed fashion [29].
- Condyle fractures in children can often be treated with closed reduction and pinning [29].
- Open procedures for condyle fractures increase a risk for osteonecrosis, so all attempts should be made for early diagnosis and treatment [29].
- In a retrospective review of 105 pediatric patients treated with closed reduction pin fixation of a displaced proximal phalanx fracture, the average age was 11 years [29].
- The complication rate for closed reduction pin fixation of displaced proximal phalanx fractures in children was 4.8%, including infection, pin site complication, and malunion [29].
- Thirty-six of 105 pediatric patients had postoperative stiffness, with 31 requiring therapy [29].
- Phalangeal neck fractures had the highest rate of postoperative stiffness in pediatric patients treated with closed reduction pin fixation [29].
- Thirty-one pediatric patients available for follow-up at 1 year or greater reported return of full motion, no pain, and happiness with function and appearance [29].
- Despite 22% (7 of 31) of pediatric patients having a measurable coronal plane deformity on radiograph, they reported full motion and satisfaction at follow-up [29].
Adult Specifics
- The majority of hand fractures can be treated without surgery, though surgery offers distinct advantages in properly selected cases [3].
- Most hand fractures can be managed successfully without operation, and conservative functional techniques are the optimum treatment for the majority of patients with single metacarpal fractures [10].
- Recent PIP fractures are challenging trauma in terms of diagnosis as well as treatment, with the final outcome having a considerable impact on global finger and hand function [1].
- A quarter of open finger fractures will likely need more than one surgical procedure, especially in more severely injured fingers, due to crush or with vascular impairment [6].
- Phalangeal neck fractures of the proximal phalanx in adults are rare with limited options for unstable fractures [62].
- Fractures of the fingers are better understood, indications for surgical treatment are more clearly defined, and operative techniques and implants for osteosynthesis are continuing to evolve and improve [8].
- Results for finger fractures vary according to fracture type, surgeon experience, and patient compliance [8].
- The primary goals of phalangeal fracture treatment are to restore anatomy and preserve function [54].
- Lost productivity attributed to phalangeal fractures exceeds 2 billion every year, making early return to activities a key goal [54].
- The preferred method of treatment for phalangeal fractures is one that offers limited soft tissue damage and enables mobilization of the injured digit(s) as soon as fracture stability permits [54].
- Operative treatment for phalangeal fractures is reserved for unstable fractures or those creating unacceptable articular incongruity [54].
- Complications such as nonunion, malunion, infection, and stiffness can occur even in the setting of appropriate surgical treatment for phalangeal fractures [54].
- There are two major causes of PIP joint extensor lag following proximal phalangeal fractures: soft tissue adhesions and persistent skeletal deformity [36].
- Fracture hematoma permeates the zone of injury and incites a proliferative fibroblastic response of the multiple surrounding collagenous structures that is proportionate to injury severity [36].
- Simple fractures caused by low-energy injuries occasionally may be complicated by some measure of permanent stiffness as a result of soft tissue adhesion [36].
- When adjacent flexor or extensor tendon injury accompanies a proximal phalangeal fracture, the difficulty of treatment and achieving a favorable outcome may be compounded substantially [36].
- Surgical treatment for proximal phalangeal fractures requires a second "planned injury," superimposing further soft tissue injury and increasing the risk of soft tissue adhesions [36].
- The intrinsic muscles flex the proximal fragment, whereas the distal fragment is extended by the attachment of the central slip to the dorsal lip of the middle phalanx [36].
- Phalangeal fractures tend to deteriorate total active motion (TAM) more than metacarpal fractures [39].
- Pain in the post-operative week predicts pain and hand use twelve weeks after proximal phalangeal fracture fixation [34].
- In a study of proximal phalangeal fractures, 52% of fractures were little fingers, 40% were intra-articular, and 46% were in the dominant hand [34].
- The mean age of patients in a study on post-operative pain after proximal phalangeal fracture fixation was 35 years, with 75% being male [34].
- Extension lags of the PIP joints were found in 67% of all fractured fingers treated with plate fixation for extra-articular proximal phalanx fractures [60].
- At 6 weeks postoperatively, an average TAM of 183° was found in patients treated with plate fixation for extra-articular proximal phalanx fractures [60].
- At final follow-up, an improved average TAM of 213° was found in patients treated with plate fixation for extra-articular proximal phalanx fractures [60].
- In a study of conservative management of proximal phalangeal fractures in an A&E department, 147 of 242 phalangeal fractures (61%) involved the proximal phalanx [49].
- Proximal phalangeal fractures formed 7% of all hand fractures and 0.3% of all attendances in a study of A&E patients [49].
- The results achieved with external fixation for closed metacarpal and phalangeal fractures were similar to those obtained in the management of stable and undisplaced metacarpal and phalangeal fractures [7].
- No differences in the outcome of finger proximal phalangeal fractures treated by dorsal and lateral plate fixation were observed [5].
- All six fingers obtained satisfactory union of the fractures, and no patient complained of pain at the final follow-up in a study of intramedullary fixation of proximal phalangeal fractures through a volar extra-tendon sheath approach [11].
- A mini external fixator constructed from readily available materials is another tool available to the hand surgeon treating fractures of the hand and phalanges [38].
- The Joshi's External Stabilization System (JESS) has had extensive use in the management of hand injuries [63].
- Hand fractures require excellent communication between the surgeon and therapist to progress the patient through the course of therapy [41].
- These findings underscore the importance of careful assessment and management of nail bed injuries and fracture healing when treating distal phalanx fractures [96].
- The patient returned to his previous activity level but demonstrated a residual deficit in thumb IP joint flexion with follow-up radiographic evidence of a healed fracture and a physis that remains open in a case of Salter-Harris Type III fracture of the distal phalanx [24].
Investigations
Imaging and Diagnostic Modalities
- A true lateral radiograph is required for the accurate diagnosis of carpometacarpal fracture-dislocations because swelling can obscure the deformity [108].
- Loss of parallel joint surfaces at the carpometacarpal articulations on a posteroanterior radiograph is indicative of carpometacarpal fracture-dislocation [108].
- Computed tomography scans are beneficial for determining the extent of joint surface involvement in carpometacarpal injuries and guiding appropriate intervention [108].
- Ultrasonography may provide greater accuracy in fracture diagnostics by revealing small avulsed bony fragments missed on radiographs [155].
- Ultrasonography can be beneficial in diagnosing occult fractures, especially in children [155].
- Quantitative 3DCT analysis of fracture fragments provides useful information that could facilitate surgery and analysis of complex fractures of the base of the middle phalanx [156].
Clinical Examination
- The coronal plane deformity of Salter-Harris II fractures is easy to assess, but extra care must be taken to assess for rotational deformity, which is not as obvious on radiographs [29].
- Malrotation does not remodel and can result in problems with grip formation [29].
- The key to diagnosing Seymour fractures is disruption of the nail plate/cuticle as well as a displaced fracture of the distal phalanx on radiographs [29].
- Disruption of the nail bed indicates the likelihood of an open fracture with interposed tissue in Seymour fractures [29].
Treatment
General Principles
- Recent PIP fractures present diagnostic and treatment challenges where final outcome significantly impacts global finger and hand function [1].
- Fractures of the fingers are better understood, indications for surgical treatment are more clearly defined, and operative techniques and implants for osteosynthesis are continuing to evolve and improve, though results vary according to fracture type, surgeon experience, and patient compliance [8].
- The preferred method of treatment is one that offers limited soft tissue damage and enables mobilization of the injured digit(s) as soon as fracture stability permits [54].
- In general, operative treatment is reserved for unstable fractures or those creating unacceptable articular incongruity [54].
- Optimal outcome from surgical treatment demands appropriate surgical plan, atraumatic soft tissue handling, and stable fixation to facilitate early motion; however, complications such as nonunion, malunion, infection, and stiffness can occur even in the setting of appropriate treatment [54].
- A management algorithm proposes that if a fracture is deemed stable, nonoperative management is recommended [116].
- A finger undergoing any type of surgery is likely to be stiffer than one that was treated nonoperatively [116].
- If a fracture is deemed stable yet not quite enough to begin early active range of motion, it is reasonable to delay motion for an additional week or two [116].
- A fracture that did not undergo surgery and progressed more slowly to allow for adequate fracture healing is still better than one that underwent surgery followed by an early range of motion protocol [116].
Non-Operative Management
- The majority of pediatric hand and finger fractures can be treated with closed reduction, appropriate immobilization, and early motion [29].
- Well-reduced, minimally angulated, or nonangulated fractures of the proximal phalanges of the fingers can be effectively treated using functional casts without immobilizing the wrist [122].
- A non-invasive technique using a thermoplastic traction platform is safe and effective in the management of proximal phalangeal fractures [140].
- Traction splinting presents a method for noninvasive management of angulated and rotated phalanx fractures [138].
- Buddy taping is a non-inferior treatment modality for most paediatric finger fractures compared to splint immobilization [105].
- Taping paediatric finger fractures can be recommended irrespective of the degree of displacement or the need for reduction [44].
- Nonsurgical treatment is supported for closed and displaced mallet finger fractures with greater than one-third articular surface involvement [69].
- For a closed extensor tendon rupture from its insertion into the distal phalanx, the treatment usually is nonsurgical [73].
- The distal interphalangeal joint is constantly held in hyperextension on a splint for 6 to 8 weeks and at night only for 2 to 4 additional weeks to allow tendon healing and prevent stretching [73].
- Splint treatment within 2 weeks of injury has been found to be as effective as splinting more than 4 weeks after injury for mallet finger [73].
- This treatment can be successful in some patients 3 months after injury for mallet finger [73].
- High patient satisfaction was reported at an average of 5 years after splint treatment of mallet deformities, with and without fracture [73].
- Osteoarthritic changes were seen in 48% of mallet finger cases treated with splinting, usually associated with fractures [73].
- Mallet finger deformities in children caused by traumatic separation of the epiphysis can be treated with early detection, straightforward reduction with hyperextension of the distal interphalangeal joint, and splinting for 3 to 4 weeks [73].
- Antibiotics are a necessity to prevent infection for Seymour fractures, with recommended treatment including a dose of IV antibiotic in the emergency department followed by a 7- to 10-day course of oral antibiotic [29].
- The classic “jammed” finger involving a volar plate injury or small nondisplaced avulsion fracture off the volar base of the middle finger epiphysis does not require surgical intervention [29].
- Jammed fingers should be splinted in approximately 30° of flexion for a week followed by 3 weeks of buddy tape to allow for healing [29].
- For transverse metacarpal fractures of the shaft and neck, historically patients were left to mobilize freely and healed with some deformity but good function [103].
- Barton (1984) showed the efficacy of plaster or splint support to reduce the angulation of transverse metacarpal shaft fractures [103].
- For metacarpal neck (boxer’s) fractures, acceptable flexion malunion has been variously suggested as 50° to 60°, 30°, and 20° [103].
- For little finger metacarpal shaft fractures, acceptable angulation has been suggested as 30° [103].
- A Cochrane review has shown there is no good evidence that more marked malunion causes reduced hand function or unacceptable deformity for metacarpal fractures [103].
- The outcome of non-operative treatment for metacarpal fractures is typically an excellent functional outcome apart from a mild cosmetic abnormality [103].
- No one technique of non-operative management has been shown to be superior in the published studies for metacarpal fractures [103].
- Treatment for phalangeal fractures in baseball should be immediate, with nonoperative splinting for at least 3 weeks for nondisplaced fractures [129].
- Fingertip injuries without exposed bone are allowed to heal by second intention if less than 1 cm² of the tip or pulp is involved [31].
- Full-thickness skin grafts (FTSGs) are preferred for the fingertip because they provide better durability, less contraction, and superior sensibility than composite or split-thickness skin grafts (STSGs) [31].
- Composite flaps for distal fingertip amputations may be attempted in patients younger than 6 years, but patients’ parents must acknowledge possibility of failure [31].
Operative Management
- Surgery for displaced proximal phalangeal fractures in baseball is indicated [129].
- External fixation of unstable metacarpal and phalangeal fractures achieved good or excellent function in 94% of metacarpal and 85% of phalangeal fractures by nine weeks [4].
- The results achieved with external fixation of closed metacarpal and phalangeal fractures were similar to those obtained in the management of stable and undisplaced metacarpal and phalangeal fractures [7].
- Non-locking plates are appropriate for most metacarpal and phalangeal fractures necessitating plate fixation [132].
- Intramedullary screw fixation for proximal phalangeal fractures finds good functional outcomes and a low complication rate [45].
- Intramedullary fixation of proximal phalangeal fractures through a volar extra-tendon sheath approach resulted in satisfactory union of the fractures in all six fingers, with no patient complaining of pain at the final follow-up [11].
- Screw fixation is suggested to achieve patient satisfaction and optimal functional recovery of closed, isolated proximal phalangeal fractures of the long fingers [23].
- The Ichi-Fixator system (IFS) is a definitive treatment option for managing various phalangeal fractures [28].
- Open reduction and internal fixation (ORIF) of proximal phalangeal fractures achieved excellent outcomes, providing a benchmark for recovery [37].
- Open reduction and interfragmentary screw fixation is an effective treatment modality for symptomatic non-union of distal phalangeal fractures with minimal morbidity, resulting in union and normal function in all patients [104].
- In a retrospective review of 105 patients treated with closed reduction pin fixation of a displaced proximal phalanx fracture, the complication rate was 4.8% including infection, pin site complication, and malunion [29].
- Thirty-six of 105 patients had postoperative stiffness with 31 requiring therapy after closed reduction pin fixation of displaced proximal phalanx fractures [29].
- Phalangeal neck fractures had the highest rate of postoperative stiffness after closed reduction pin fixation [29].
- Thirty-one patients available for follow-up at 1 year or greater all reported return of full motion, no pain, and happiness with function and appearance despite 22% (7 of 31) having a measurable coronal plane deformity on radiograph [29].
- Unstable PIP fracture-dislocations must be managed surgically using ORIF or hemihamate arthroplasty [142].
- Chronic PIP fracture-dislocations are managed using volar plate arthroplasty or hemihamate arthroplasty [142].
- Pilon fractures of the base of the middle phalanx are managed using longitudinal traction (pin and rubber band traction) and immediate motion [142].
- Rotatory subluxation-dislocations of the PIP often require surgical intervention for reduction because of interposed soft tissues [142].
- If a voral PIP dislocation is still unstable after reduction, pinning for 3 weeks is required [142].
- Excising the third metacarpal shaft removes the origin of the adductor pollicis and weakens pinch [18].
- The index ray should not be transposed unless the adductor pollicis can be reattached elsewhere [18].
- Transposition of the index metacarpal after partial middle finger metacarpal amputation is technically challenging and has significant complications [18].
- Union of midshaft metacarpal osteotomies is more difficult, and metaphyseal fixation is recommended in such instances [18].
- Amputation of the index, long, and small fingers requires preservation of the metacarpal base to protect the insertion of the flexor and extensor tendons [33].
- Ray resections without transposition avoid complications such as nonunion and minimize postoperative immobilization [33].
- Ray resections with transposition narrow the resultant open space and avoid complications such as malrotation leading to scissoring [33].
- An acute ray amputation following trauma should be performed sparingly as delayed ray resection can be performed to address functional or esthetic concerns [33].
- Cross-finger flap is indicated for volar oblique fingertip injuries with exposed bone [31].
- The donor site for a cross-finger flap is covered with an STSG and the flap is split during a separate procedure 2 to 3 weeks later [31].
- Thenar flap is indicated for volar oblique injuries to the index or long digits [31].
- Complications of the thenar flap include donor site tenderness and PIP contracture, especially in older patients [31].
- Homodigital island flap is raised on the digital artery of the involved finger and may maintain sensory innervation to the fingertip [31].
- Heterodigital island flap is raised on the ulnar aspect of the long or ring finger and typically tunneled in the palm to provide coverage to the thumb [31].
- V-Y advancement is indicated to preserve length and cover transverse or dorsal oblique fingertip injuries [31].
- Reverse cross-finger flap is indicated for loss of tenosynovium and dorsal exposure of bone [31].
- A lumbrical-plus finger is treated with release of the radial lateral band [31].
- Moberg advancement flap is most useful for amputations distal to the thumb interphalangeal (IP) joint [31].
- Complications of the Moberg advancement flap include flap necrosis and thumb IP joint flexion contracture [31].
- First dorsal metacarpal artery “kite” flap or heterodigital island flap is indicated for thumb tip injury of any size [31].
- The best indication of the reversed digital artery island flap is the coverage of large defects of the dorsal aspects of the middle and third phalanx, not the treatment of fingertip injuries [115].
Complications
General and Pediatric Outcomes
- Recent PIP fractures present challenges in diagnosis and treatment, with final outcomes having a considerable impact on global finger and hand function [1].
- In younger children, residual angulation of 30 degrees or less should remodel without significant disability [139].
- Uncorrected angulation of 25 degrees or more in the adult or older child usually results in loss of both flexion and extension of the proximal interphalangeal joint, aside from any adherence of tendon apparatus adjacent to the fracture site [139].
- Two of six children over age ten with impacted fractures in the proximal third of the proximal phalax had malunion with loss of significant flexion and extension of the proximal interphalangeal joint [139].
- Of seventeen adults with impacted fractures in the proximal third of the proximal phalax, nine had malunion [139].
- Seven adults first seen more than five weeks after injury had angulation of 25 to 70 degrees with significant loss of both flexion and extension at the proximal interphalangeal joint [139].
- The commonest causes of malunion in impacted proximal phalangeal fractures were immobilization of the digit in insufficient flexion at the metacarpophalangeal and proximal interphalangeal joints, permitting loss of reduction [139].
- Acceptance of oblique rather than true lateral roentgenograms for evaluation of angulation in fractures of the proximal phalanx, both before and after reduction, was a common cause of malunion [139].
Operative Complications and Reoperation
- Postoperative finger stiffness occurred in 43% of fractures treated with titanium plates and/or screws for unstable proximal phalangeal fractures [26].
- Injuries sustained in the thumb and index finger were more likely to undergo unplanned reoperation after phalangeal fractures requiring vascular reconstruction [14].
- The risk for postoperative complications and reoperations after closed reduction and percutaneous pinning (CRPP) of closed proximal phalanx fractures is considerable [125].
- Union of midshaft metacarpal osteotomies is more difficult in the context of index ray transposition [18].
- The operation of index ray transposition is contraindicated if the hand is needed for heavy manual labor [18].
- The authors do not agree with the system of freeing the caught hand by rotating the handle in the reverse direction due to the potential risk of damaging vital structures in severe mincer injuries [27].
- Long-term follow-up in patients with pay phone receiver cord injuries to the hand was impossible, and anticipated hand function results are less than optimal [43].
- The patient with a Salter-Harris Type III fracture of the distal phalanx demonstrated a residual deficit in thumb IP joint flexion [24].
- Follow-up radiographic evidence in the patient with a Salter-Harris Type III fracture of the distal phalanx showed a healed fracture and a physis that remains open [24].
Specific Technique Outcomes
- Good or excellent function was achieved in 94% of metacarpal and 85% of phalangeal fractures treated with external fixation by nine weeks [4].
- All six fingers treated with intramedullary fixation through a volar extra-tendon sheath approach obtained satisfactory union of the fractures [11].
- No patient complained of pain at the final follow-up after intramedullary fixation through a volar extra-tendon sheath approach [11].
- Dual antegrade intramedullary headless screw fixation of proximal phalangeal fractures resulted in no complications with follow-up of at least 1 year [67].
- An updated systematic review finds a low complication rate following the use of intramedullary screw (IMS) fixation for proximal phalangeal fractures [45].
- The remaining patients in a series of phalangeal fractures had either suffered an unusual type of injury, or had developed an arthrosis associated with a long delay between injury and operation [76].
Recovery
General Outcomes and Prognosis
- Recent PIP fractures have a final outcome that considerably impacts global finger and hand function [1].
- Fractures of the fingers are better understood, with indications for surgical treatment more clearly defined, though results vary according to fracture type, surgeon experience, and patient compliance [8].
- In a retrospective series of nearly 7,000 hospital admissions for phalangeal fractures, no significant change in incidence was found in any specific age group during the study period [75].
- Patients who suffered an unusual type of injury or developed arthrosis associated with a long delay between injury and operation had less favorable outcomes [76].
Non-Operative Recovery
Operative Recovery and Complications
- Good or excellent function was achieved in 94% of metacarpal and 85% of phalangeal fractures by nine weeks following external fixation [4].
- No differences in the outcome of finger proximal phalangeal fractures were observed between dorsal and lateral plate fixation [5].
- A quarter of open finger fractures will likely need more than one surgical procedure, especially in more severely injured fingers due to crush or vascular impairment [6].
- Open fractures with both palmar and dorsal wounds should be treated with delayed fixation of K-wires otherwise stabilized immediately after injury [163].
- Most fractures healed within 4 weeks following closed reduction and periarticular pinning of base and shaft fractures of the proximal phalanx, with the majority of patients having excellent or good results [157].
- Excellent outcomes were achieved in a prospective longitudinal study of open reduction and internal fixation of proximal phalangeal fractures, providing a benchmark for recovery [37].
- Dual antegrade intramedullary headless screw fixation of proximal phalangeal fractures resulted in excellent postoperative motion, near-normal grip strength, positive self-reported patient outcomes, and no complications with follow-up of at least 1 year [67].
- An updated systematic review found good functional outcomes and a low complication rate following the use of intramedullary screw fixation for proximal phalangeal fractures [45].
- All six fingers obtained satisfactory union of the fractures, and no patient complained of pain at the final follow-up after intramedullary fixation through a volar extra-tendon sheath approach [11].
- The authors suggest using screw fixation to achieve patient satisfaction and optimal functional recovery of closed, isolated proximal phalanx fractures of the long fingers [23].
- Dynamic external fixation is considered an effective tool in the management of a range of complex intraarticular phalangeal fractures [72].
Pediatric and Articular Specifics
- A patient with a Salter-Harris Type III fracture of the distal phalanx returned to his previous activity level but demonstrated a residual deficit in thumb IP joint flexion with follow-up radiographic evidence of a healed fracture and a physis that remains open [24].
Rehabilitation and Long-Term Follow-Up
- Long-term follow-up in a specific transient patient population with pay phone receiver cord injuries was impossible, and anticipated hand function results are less than optimal [43].
- Bone resorption occurred in a digit reconstructed using the circumferential method seven months after surgery, though the true incidence remains unclear as radiographs are not commonly performed after such procedures [78].
- At 6 months, very significant progress was observed with complete and total recovery of active flexion amplitudes of the proximal and distal interphalangeal joints of 4 long fingers following secondary tendon surgery [153].
Key Evidence
- [L5] Recent PIP fractures are challenging trauma in terms of diagnosis as well as treatment, with the final outcome having a considerable impact on global finger and hand function. [1] (10.1016/j.main.2004.08.010)
- [L5] Most pediatric hand fractures are treated nonoperatively with good results, but a subset of phalangeal fractures requires prompt recognition and surgical intervention to minimize complications. [2] (10.1097/01.blo.0000205890.88952.97)
- [L5] The majority of hand fractures can be treated without surgery, though surgery offers distinct advantages in properly selected cases. [3] (10.1016/j.jhsa.2013.02.017)
- [L3] Good or excellent function was achieved in 94% of metacarpal and 85% of phalangeal fractures by nine weeks. [4] (10.1016/0266-7681(92)90077-f)
- [L3] No differences in the outcome of finger proximal phalangeal fractures treated by dorsal and lateral plate fixation were observed. [5] (10.1007/s00402-017-2650-x)
- [L3] A quarter of open finger fractures will likely need more than one surgical procedure, especially in more severely injured fingers, due to crush or with vascular impairment. [6] (10.1177/15589447211043191)
- [L2] The results achieved were similar to those obtained in the management of stable and undisplaced metacarpal and phalangeal fractures. [7] (10.1016/j.jhsb.2005.09.013)
- [L5] Fractures of the fingers are better understood, indications for surgical treatment are more clearly defined, and operative techniques and implants for osteosynthesis are continuing to evolve and improve, though results vary according to fracture type, surgeon experience, and patient compliance. [8] (10.1054/jhsb.2002.0889)
- [L3] It is recommended that all finger fractures should be assessed and treated by surgeons with training in the management of hand injuries. [9] (10.1016/0266-7681(90)90008-r)
- [L5] Most hand fractures can be managed successfully without operation, and conservative functional techniques are the optimum treatment for the majority of patients with single metacarpal fractures. [10] (10.1177/1753193420928820)
- [L4] All six fingers obtained satisfactory union of the fractures, and no patient complained of pain at the final follow-up. [11] (10.1142/s0218810411005230)
- [L3] Open finger fractures formed the majority of the workload of open fractures at our trauma centre but usually required simple treatments only. [12] (10.1142/s2424835516500338)
- [L4] We believe we have shown its success in the treatment of closed proximal phalangeal fractures. [13] (10.1016/s0020-1383(01)00138-3)
- [L3] Injuries sustained in the thumb and index finger were more likely to undergo unplanned reoperation, which may guide initial treatment decision-making and postoperative follow-up. [14] (10.1177/15589447221109635)
- [L4] Most phalangeal neck fractures in children less than 3 years old obtained satisfactory results. [16] (10.1186/s13018-025-05849-2)
- [L4] We conclude that this technique is applicable for selected unstable metacarpal and phalangeal fractures of certain configurations. [17] (10.1016/s0363-5023(86)80072-7)
- [L4] It showed to be safe and effective when used for treatment of extra-articular metacarpal and proximal phalangeal fractures. [19] (10.1177/1558944716660555dq)
- [L4] Articular fractures of the fingers in children often result in sequelae, with a rate as high as 50% when the fracture was displaced initially. [21] (10.1016/s0749-0712(21)00213-4)
- [Paper] Most pediatric phalangeal fractures can be treated nonsurgically, but a small subset benefits from surgical intervention. [22] (10.1016/j.jhsa.2025.08.015)
- [L4] The authors suggest using screw fixation to achieve patient satisfaction and optimal functional recovery of closed, isolated proximal phalanx fractures of the long fingers. [23] (10.1016/j.hansur.2016.08.009)
- [L4] The patient returned to his previous activity level but demonstrated a residual deficit in thumb IP joint flexion with follow-up radiographic evidence of a healed fracture and a physis that remains open. [24] (10.1177/15589447221082165)
- [L4] These two cases present an uncommon mechanism resulting in a spiral fracture of the proximal phalanx of the index finger, which to our knowledge has not been reported previously in the English literature. [25] (10.1016/0020-1383(92)90162-l)
- [L2] Postoperative finger stiffness occurred in 43% of fractures. [26] (10.1016/j.jhsa.2014.06.107)
- [L4] The authors do not agree with the system of freeing the caught hand by rotating the handle in the reverse direction due to the potential risk of damaging vital structures. [27] (10.1016/0266-7681(85)90045-2)
- [L4] The IFS is a definitive treatment option for managing various phalangeal fractures. [28] (10.1016/j.hansur.2019.07.011)
- [L3] [34] (10.1142/s2424835519500607)
- [L4] [35] (10.1177/1753193408091430)
- [Paper] [36] (10.1016/s0894-1130(03)80008-x)
- [L3] Excellent outcomes were achieved, providing a benchmark for recovery after ORIF of proximal phalangeal fractures. [37] (10.1177/1753193416670591)
- [L5] This is another tool available to the hand surgeon treating fractures of the hand and phalanges. [38] (10.1097/bth.0b013e318217615f)
- [L2] The phalangeal fractures tend to deteriorate %TAM than metacarpal fractures. [39] (10.1016/s0363-5023(11)60047-6)
- [L5] Hand fractures, in particular, require excellent communication between the surgeon and therapist to progress the patient through the course of therapy. [41] (10.1016/s0894-1130(03)80006-6)
- [L4] Long-term follow-up in this particular transient patient population was impossible, and anticipated hand function results are less than optimal. [43] (10.1016/s0363-5023(84)80078-7)
- [L1] With the current data, we can conclude that taping these finger fractures can be recommended irrespective of the degree of displacement or the need for reduction. [44] (10.1177/17531934241293338)
- [L4] This updated systematic review finds good functional outcomes and a low complication rate following the use of IMS fixation for proximal phalangeal fractures. [45] (10.1177/15589447251329597)
- [L4] [49] (10.1016/0266-7681(92)90123-j)
- [L5] [52] (10.1016/j.hcl.2012.05.032)
- [L5] [54] (10.1016/j.hcl.2013.08.006)
- [L5] The article reviews the background, biomechanics, applications, techniques, outcomes, and costs of this approach for metacarpal fractures, phalangeal fractures, and interphalangeal joint arthrodesis. [55] (10.1016/j.jhsa.2023.08.011)
- [L4] In contrast, avascular necrosis following phalangeal neck fractures usually affects the little finger and presents with stiffness, and hence, further surgery is not often required short term. [57] (10.1016/j.jhsa.2010.03.038)
- [L5] It commonly occurs in RTAs and is usually associated with other serious injuries of the hand, wrist and distal forearm so adequate imaging should be sought early in all instances. [58] (10.1016/j.jhsb.2007.01.009)
- [L4] [60] (10.1007/s00402-015-2155-4)
- [L4] Phalangeal neck fractures of the proximal phalanx in adults are rare with limited options for unstable fractures. [62] (10.1016/j.injury.2010.06.017)
- [Paper] The system has had extensive use in the management of hand injuries. [63] (10.1016/s0020-1383(97)88363-5)
- [L5] [65] (10.1016/0266-7681(87)90028-3)
- [L4] Dual antegrade IMHS fixation of proximal phalanx fractures resulted in excellent postoperative motion, near-normal grip strength, positive self-reported patient outcomes, and no complications with follow-up of at least 1 year. [67] (10.1177/1558944717750919)
- [L4] The technique was used to treat two intraarticular proximal phalangeal fractures of the thumb with satisfactory outcomes, including full range of movements within 3 weeks, no complications, and no need for implant removal. [68] (10.1177/1753193415615032)
- [L4] This study supports the rationale for nonsurgical treatment of closed and displaced mallet finger fractures with greater than one-third articular surface involvement. [69] (10.1016/j.jhsa.2005.02.010)
- [L4] We consider that this device is an effective tool in the management of a range on complex intraarticular phalangeal fractures. [72] (10.1016/j.jhsb.2003.08.009)
- [L5] Phalangeal fractures are the most common hand fractures in children, with Salter-Harris type II fractures of the proximal phalanx being the most frequent. [74] (10.5435/jaaos-d-16-00199)
- [L4] In this retrospective series of nearly 7,000 hospital admissions for phalangeal fractures we found no significant change in incidence in any specific age group during the study period. [75] (10.1016/0266-7681(94)90157-0)
- [L4] The remaining patients had either suffered an unusual type of injury, or had developed an arthrosis, associated with a long delay between injury and operation. [76] (10.1016/0020-1383(81)90217-5)
- [L4] Bone resorption occurred in the digit reconstructed using the circumferential method seven months after surgery, though the true incidence remains unclear as radiographs are not commonly performed after such procedures. [78] (10.1177/1753193412453413)
- [L3] These findings underscore the importance of careful assessment and management of nail bed injuries and fracture healing when treating distal phalanx fractures. [96] (10.1177/17531934261456220)
- [L4] Complications of distal phalanx fractures in children are frequent. [100] (10.1016/j.jhsa.2017.03.042)
- [L4] [103] (10.1177/1753193414548170)
- [L4] Open reduction and interfragmentary screw fixation is an effective treatment modality for symptomatic non-union of distal phalangeal fractures with minimal morbidity, resulting in union and normal function in all patients. [104] (10.1177/1753193407087866)
- [L1] Buddy taping is a non-inferior treatment modality for most paediatric finger fractures compared to splint immobilization. [105] (10.1177/1753193418822692)
- [L4] The best indication of the reversed digital artery island flap is not the treatment of fingertip injuries, but rather the coverage of large defects of the dorsal aspects of the middle and third phalanx. [115] (10.1016/0363-5023(94)90032-9)
- [L4] [116] (10.1177/1558944717735947)
- [L2] Well-reduced, minimally angulated, or nonangulated fractures of the proximal phalanges of the fingers can be effectively treated using functional casts without immobilizing the wrist. [122] (10.1016/j.jhsa.2012.02.017)
- [L3] The risk for postoperative complications and reoperations after CRPP of closed proximal phalanx fractures is considerable, and surgeons should counsel patients before surgery about these risks. [125] (10.1016/j.jhsg.2023.11.004)
- [L5] Palmar dislocation of the metacarpophalangeal joint is a rare injury where the mechanism is likely hyperextension force applied during strong active flexion. [127] (10.1016/j.jhsb.2003.09.009)
- [L5] Treatment should be immediate, with nonoperative splinting for at least 3 weeks for nondisplaced fractures and surgery for displaced fractures. [129] (10.1016/j.hcl.2012.05.033)
- [L5] Non-locking plates are appropriate for most metacarpal and phalangeal fractures necessitating plate fixation. [132] (10.1016/j.jhsa.2011.09.023)
- [L5] The case study presents a method for noninvasive management of angulated and rotated phalanx fractures. [138] (10.1016/s0894-1130(04)00198-x)
- [L4] [139] (10.2106/00004623-196951070-00006)
- [L4] This non-invasive technique using a thermoplastic traction platform is safe & effective in the management of proximal phalangeal fractures. [140] (10.1016/j.jht.2021.02.001)
- [Paper] Type II D phalangeal neck fractures tend to occur in young children and the majority involve the middle phalanx. [146] (10.1055/s-0040-1703097)
- [L4] [148] (10.1054/jhsb.2000.0506)
- [L5] At 6 months, very significant progress was observed with complete and total recovery of active flexion amplitudes of the proximal and distal interphalangeal joints of 4 long fingers. [153] (10.1016/j.hansur.2018.10.074)
- [L4] Ultrasonography may provide greater accuracy in fracture diagnostics by revealing small avulsed bony fragments missed on radiographs and can be beneficial in diagnosing occult fractures, especially in children. [155] (10.1016/j.jhsa.2015.02.022)
- [L4] Quantitative 3DCT analysis of fracture fragments provides useful information that could facilitate surgery and analysis of complex fractures of the base of the middle phalanx. [156] (10.1007/s11552-014-9665-3)
- [L4] Most fractures healed within 4 weeks, and the majority of patients had excellent or good results. [157] (10.1016/j.jhsa.2014.05.008)
- [L3] Open fractures with both palmar and dorsal wounds should be treated with delayed fixation of K-wires otherwise stabilized immediately after injury. [163] (10.1038/s41598-017-11918-2)
References
[1] Fractures récentes des articulations IPP. Chirurgie de la Main. 2005. DOI: 10.1016/j.main.2004.08.010
[2] Pediatric Phalanx Fractures. Clinical Orthopaedics and Related Research. 2006. DOI: 10.1097/01.blo.0000205890.88952.97
[3] Hand Fractures: A Review of Current Treatment Strategies. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2013.02.017
[4] External Fixation of Unstable Metacarpal and Phalangeal Fractures. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90077-f
[5] Dorsal versus lateral plate fixation of finger proximal phalangeal fractures: a retrospective study. Archives of Orthopaedic and Trauma Surgery. 2017. DOI: 10.1007/s00402-017-2650-x
[6] Reoperation After Operative Treatment of Open Finger Fractures. HAND. 2022. DOI: 10.1177/15589447211043191
[7] External Fixation of Closed Metacarpal and Phalangeal Fractures of Digits. A Prospective Study of One Hundred Consecutive Patients. Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsb.2005.09.013
[8] Treatment of Fractures of the Fingers. What’s New?. Journal of Hand Surgery. 2003. DOI: 10.1054/jhsb.2002.0889
[9] Why all finger fractures should be referred to a hand surgery service: A prospective study of primary management. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1990. DOI: 10.1016/0266-7681(90)90008-r
[10] Current methods, outcomes and challenges for the treatment of hand fractures. Journal of Hand Surgery (European Volume). 2020. DOI: 10.1177/1753193420928820
[11] INTRAMEDULLARY FIXATION OF PROXIMAL PHALANGEAL FRACTURES THROUGH A VOLAR EXTRA-TENDON SHEATH APPROACH. Hand Surgery. 2011. DOI: 10.1142/s0218810411005230
[12] Open Finger Fractures: Incidence, Patterns of Injury and the Influence of Social Deprivation. The Journal of Hand Surgery (Asian-Pacific Volume). 2016. DOI: 10.1142/s2424835516500338
[13] Old principles revisited—traction splinting for closed proximal phalangeal fractures. Injury. 2002. DOI: 10.1016/s0020-1383(01)00138-3
[14] Phalangeal Fractures Requiring Vascular Reconstruction: Epidemiology and Factors Predictive of Reoperation. HAND. 2022. DOI: 10.1177/15589447221109635
[16] Clinical results of phalangeal neck fractures in children aged 3 years or younger: a case series of 37 patients. Journal of Orthopaedic Surgery and Research. 2025. DOI: 10.1186/s13018-025-05849-2
[17] Fixation of metacarpal and phalangeal fractures with miniature plates and screws. The Journal of Hand Surgery. 1986. DOI: 10.1016/s0363-5023(86)80072-7
[18] Campbell S Operative Orthopaedics 4 Volume Set. AMPUTATION THROUGH THE SURGICAL NECK OF THE HUMERUS > MIDDLE OR RING FINGER RAY AMPUTATIONS.
[19] Metacarpal and Proximal Phalangeal Fracture. HAND. 2016. DOI: 10.1177/1558944716660555dq
[21] ARTICULAR FRACTURES OF THE FINGERS IN CHILDREN. Hand Clinics. 2000. DOI: 10.1016/s0749-0712(21)00213-4
[22] Pediatric Finger Fractures: Preventing Big Problems After Small Fractures. The Journal of Hand Surgery. 2026. DOI: 10.1016/j.jhsa.2025.08.015
[23] Surgical management of closed, isolated proximal phalanx fractures in the long fingers: Functional outcomes and complications of 87 fractures. Hand Surgery and Rehabilitation. 2017. DOI: 10.1016/j.hansur.2016.08.009
[24] Salter-Harris Type III Fracture of the Distal Phalanx: A Rare Juxtaphyseal Variant. HAND. 2022. DOI: 10.1177/15589447221082165
[25] Spiral fracture of the proximal phalanx of the index finger by finger wrestling. Injury. 1992. DOI: 10.1016/0020-1383(92)90162-l
[26] Predictors of Postoperative Finger Stiffness After Treatment of Unstable Proximal Phalangeal Fractures With Titanium Plates And/Or Screws. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.06.107
[27] Severe mincer injuries. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1985. DOI: 10.1016/0266-7681(85)90045-2
[28] Treatment of finger phalangeal fractures using the Ichi-Fixator system: A prospective study of 12 cases. Hand Surgery and Rehabilitation. 2019. DOI: 10.1016/j.hansur.2019.07.011
[29] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Pediatric Forearm, Wrist, and Hand Trauma > Hand and Finger Fractures.
[31] Miller S Review Of Orthopaedics. 4. Fingertip injuries with tissue loss.
[33] Green S Operative Hand Surgery. SMALL FINGER RAY AMPUTATION.
[34] Pain in the Post-Operative Week Predicts Pain and Hand Use Twelve Weeks after Proximal Phalangeal Fracture Fixation. The Journal of Hand Surgery (Asian-Pacific Volume). 2019. DOI: 10.1142/s2424835519500607
[35] Phalangeal Neck Fractures with Concurrent Vascular Injury. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193408091430
[36] Rehabilitation for proximal phalangeal fractures. Journal of Hand Therapy. 2003. DOI: 10.1016/s0894-1130(03)80008-x
[37] Pattern of recovery after open reduction and internal fixation of proximal phalangeal fractures in the finger: a prospective longitudinal study. Journal of Hand Surgery (European Volume). 2016. DOI: 10.1177/1753193416670591
[38] A Mini External Fixator for Hand and Finger Fractures Constructed From Readily Available Materials. Techniques in Hand & Upper Extremity Surgery. 2011. DOI: 10.1097/bth.0b013e318217615f
[39] Predictors of the Postoperative Range of Finger Motion for Comminuted Hand and Finger Fractures Treated with a Titanium Plate. The Journal of Hand Surgery. 2011. DOI: 10.1016/s0363-5023(11)60047-6
[41] Rehabilitation approaches for distal and middle phalanx fractures of the hand. Journal of Hand Therapy. 2003. DOI: 10.1016/s0894-1130(03)80006-6
[42] Rockwood And Green S Fractures In Adults. 3: Biologic and Biophysical Technologies for the Enhancement of Fracture Repair > Finger Phalanges.
[43] Pay phone receiver cord injuries to the hand. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80078-7
[44] Buddy taping after reduction of displaced extra-articular phalangeal finger fractures in children: a randomized controlled trial. Journal of Hand Surgery (European Volume). 2024. DOI: 10.1177/17531934241293338
[45] Intramedullary Compression Screw Fixation of Proximal Phalanx Fractures: An Updated Systematic Review. HAND. 2025. DOI: 10.1177/15589447251329597
[47] Campbell S Operative Orthopaedics 4 Volume Set. RESULTS OF SUTURE OF THE SCIATIC NERVE > FINGER INCISIONS.
[48] Green S Operative Hand Surgery. RING FINGER RAY AMPUTATION.
[49] The Conservative Management of Proximal Phalangeal Fractures of the Hand in an Accident and Emergency Department. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90123-j
[52] Phalangeal Fractures. Hand Clinics. 2012. DOI: 10.1016/j.hcl.2012.05.032
[54] Treatment of Phalangeal Fractures. Hand Clinics. 2013. DOI: 10.1016/j.hcl.2013.08.006
[55] Intramedullary Fixation of Hand Fractures and Arthrodeses. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2023.08.011
[57] Nonunion and Avascular Necrosis Following Phalangeal Neck Fractures in Children. The Journal of Hand Surgery. 2010. DOI: 10.1016/j.jhsa.2010.03.038
[58] An Unusual Punch Injury. Journal of Hand Surgery (European Volume). 2007. DOI: 10.1016/j.jhsb.2007.01.009
[60] Plate fixation of extra-articular fractures of the proximal phalanx: do new implants cause less problems?. Archives of Orthopaedic and Trauma Surgery. 2015. DOI: 10.1007/s00402-015-2155-4
[61] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > 3. Mallet Finger.
[62] Phalangeal neck fractures of the proximal phalanx of the fingers in adults. Injury. 2010. DOI: 10.1016/j.injury.2010.06.017
[63] Joshi's External Stabilization System (JESS): a simple mini external fixator for the management of hand trauma and its sequels. Injury. 1997. DOI: 10.1016/s0020-1383(97)88363-5
[65] Dislocation of carpometacarpal joint of the little finger. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90028-3
[67] Dual Antegrade Intramedullary Headless Screw Fixation for Treatment of Unstable Proximal Phalanx Fractures. HAND. 2018. DOI: 10.1177/1558944717750919
[68] Percutaneous compressive bone tie for reduction of condylar phalangeal fractures. Journal of Hand Surgery (European Volume). 2016. DOI: 10.1177/1753193415615032
[69] Nonsurgical Treatment of Closed Mallet Finger Fractures. The Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsa.2005.02.010
[72] Dynamic External Fixation for Complex Intraarticular Phalangeal Fractures. Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsb.2003.08.009
[73] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTION OF FINGER FLEXORS: SINGLE-STAGE TENDON GRAFT > EXTENSOR TENDON REPAIR.
[74] Pediatric Phalanx Fractures. Journal of the American Academy of Orthopaedic Surgeons. 2016. DOI: 10.5435/jaaos-d-16-00199
[75] Phalangeal Fractures of the Hand. Journal of Hand Surgery. 1994. DOI: 10.1016/0266-7681(94)90157-0
[76] Fractures of phalanges. Injury. 1981. DOI: 10.1016/0020-1383(81)90217-5
[78] Bone resorption of the proximal phalanx secondary to pulley reconstruction. Journal of Hand Surgery (European Volume). 2012. DOI: 10.1177/1753193412453413
[79] Exam Of The Hand Wrist 2Ed. Movements of the fingers > Articulations of the fingers.
[80] Exam Of The Hand Wrist 2Ed. Macroscopic appearance of palmar skin > Fingerprints.
[81] Dupuytren S Disease And Related Hyperproliferative Disorders. 2. Palmar Fibromatosis or the Loss of Flexibility of the Palmar Finger Tissue: A New Insight into the Disease Process of Dupuytren Contracture > 2.2 The Skin Anchoring Fibers in the Normal and Diseased Hand > 2.2.1 The External View of the Soft Tissue of the Fingers.
[83] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTION OF FINGER FLEXORS: SINGLE-STAGE TENDON GRAFT > EXTENSOR TENDONS.
[84] Exam Of The Hand Wrist 2Ed. Movements of the fingers > Normal ulnar inclination of the fingers.
[89] Exam Of The Hand Wrist 2Ed. Mechanisms of finger flexion and extension > Actions of the intrinsic muscles.
[96] Risk factors for nail dystrophy following distal phalangeal fractures of the hand. Journal of Hand Surgery (European Volume). 2026. DOI: 10.1177/17531934261456220
[100] Complications of Distal Phalanx Fractures in Children. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.03.042
[103] The non-operative management of hand fractures. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193414548170
[104] OPEN REDUCTION AND INTERFRAGMENTARY SCREW FIXATION FOR SYMPTOMATIC NONUNION OF DISTAL PHALANGEAL FRACTURES. Journal of Hand Surgery (European Volume). 2008. DOI: 10.1177/1753193407087866
[105] Buddy taping versus splint immobilization for paediatric finger fractures: a randomized controlled trial. Journal of Hand Surgery (European Volume). 2019. DOI: 10.1177/1753193418822692
[108] Campbell S Operative Orthopaedics 4 Volume Set. FRACTURES, DISLOCATIONS, AND LIGAMENTOUS INJURIES OF THE HAND AND WRIST > FINGER METACARPALS.
[115] A Reversed Digital Artery Island Flap for the Treatment of Fingertip Injuries. The Journal of Hand Surgery. 1994. DOI: 10.1016/0363-5023(94)90032-9
[116] Proximal Phalanx Fracture Management. HAND. 2017. DOI: 10.1177/1558944717735947
[122] Extra-Articular Fractures of the Proximal Phalanges of the Fingers: A Comparison of 2 Methods of Functional, Conservative Treatment. The Journal of Hand Surgery. 2012. DOI: 10.1016/j.jhsa.2012.02.017
[125] Risks of Reoperation in Surgically Treated Fractures of the Proximal Phalanx. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2023.11.004
[127] Palmar Dislocation of the Metacarpophalangeal Joint of the Finger. Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsb.2003.09.009
[129] Phalangeal Fractures in Baseball: Commentary. Hand Clinics. 2012. DOI: 10.1016/j.hcl.2012.05.033
[132] Non-Locked and Locked Plating Technology for Hand Fractures. The Journal of Hand Surgery. 2011. DOI: 10.1016/j.jhsa.2011.09.023
[138] Traction splinting phalanx fractures: A case study. Journal of Hand Therapy. 2004. DOI: 10.1016/s0894-1130(04)00198-x
[139] Impacted Fractures in the Proximal Portion of the Proximal Phalanx of the Finger. The Journal of Bone & Joint Surgery. 1969. DOI: 10.2106/00004623-196951070-00006
[140] A traction orthosis for the treatment of proximal phalangeal fractures. Journal of Hand Therapy. 2022. DOI: 10.1016/j.jht.2021.02.001
[142] Orthopaedic Knowledge Update Sports Medicine 6. Hand and Wrist Injuries > Hand Injuries > Finger Dislocations.
[146] Type II D Phalangeal Neck Fractures in Children: A Series of 20 Cases Treated According to a Preset Stepwise Algorithm. Journal of Hand and Microsurgery. 2021. DOI: 10.1055/s-0040-1703097
[148] PHALANGEAL NECK FRACTURES IN CHILDREN: CLASSIFICATION AND OUTCOME IN 66 CASES. Journal of Hand Surgery. 2001. DOI: 10.1054/jhsb.2000.0506
[153] Tubulure de perfusion siliconée en lieu et place de tiges de Hunter dans la chirurgie secondaire des tendons fléchisseurs en zone 2 dans un environnement chirurgical à ressources limitées. Hand Surgery and Rehabilitation. 2018. DOI: 10.1016/j.hansur.2018.10.074
[155] Ultrasonography Can Be Used to Assess Phalanx Fractures. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2015.02.022
[156] Quantitative 3-Dimensional CT Analyses of Fractures of the Middle Phalanx Base. HAND. 2014. DOI: 10.1007/s11552-014-9665-3
[157] Outcomes of Closed Reduction and Periarticular Pinning of Base and Shaft Fractures of the Proximal Phalanx. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.05.008
[163] Timing for Surgical Stabilization with K-wires after Open Fractures of Proximal and Middle Phalangeal Shaft. Scientific Reports. 2017. DOI: 10.1038/s41598-017-11918-2