Patients › Rehabilitation
Fijación de la clavícula (reducción abierta y fijación interna, ORIF)
Rehabilitation after plate fixation of a clavicle fracture, gated on radiographic healing at review.
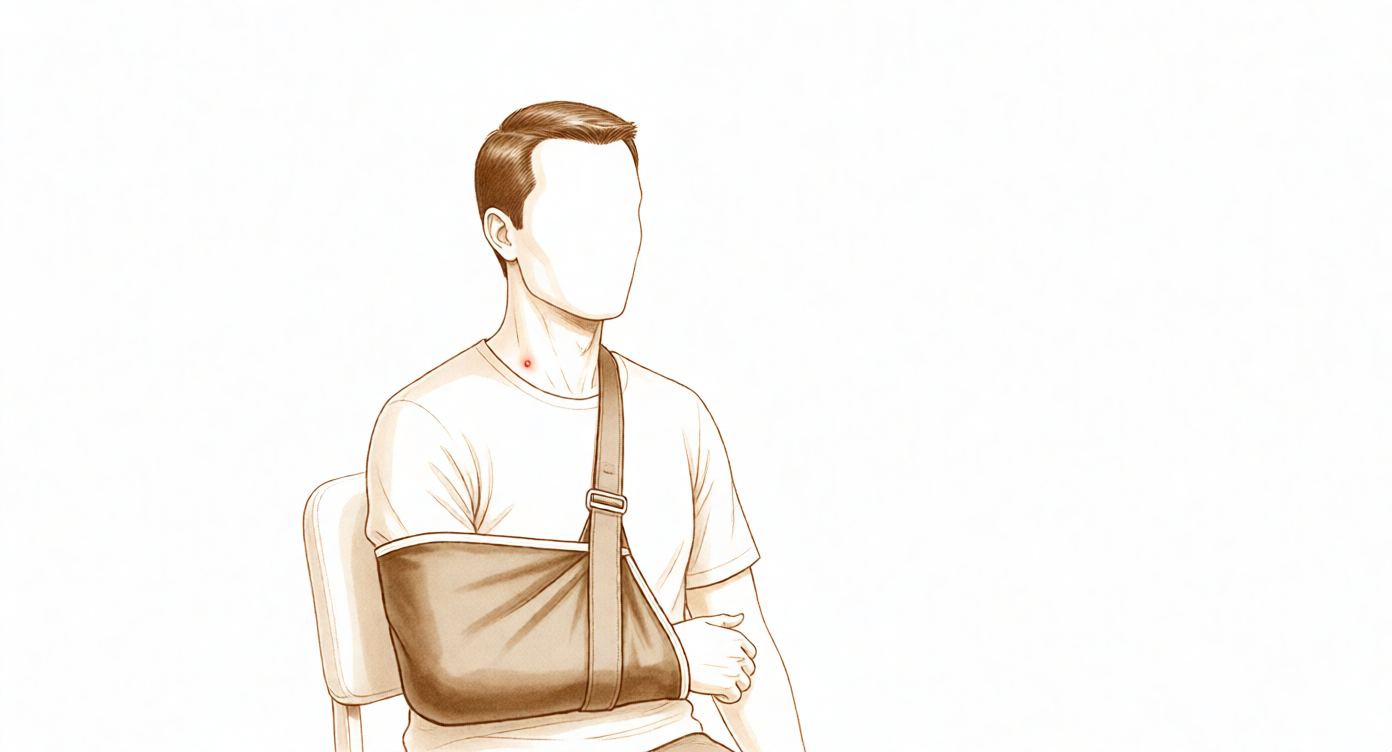
Este protocolo le servirá de guía para su recuperación tras la fijación con placa de una fractura de clavícula, mediante reducción abierta y fijación interna (ORIF), bajo la supervisión del Dr. Kieran Hirpara en el Mater Private Hospital Rockhampton. Cada fase comienza con una explicación sencilla, en lenguaje comprensible, de lo que está ocurriendo y qué aspectos son más importantes; a continuación se detalla el protocolo estructurado destinado a su fisioterapeuta. Lleve esta página o su versión en PDF a su primera sesión de fisioterapia para garantizar una rehabilitación coordinada. Su fisioterapeuta podrá modificar el plan según el progreso de su recuperación.
Si tiene alguna duda respecto a la herida quirúrgica, no dude en contactar con el consultorio. A menudo resulta útil tomar una fotografía de la herida y enviarla por correo electrónico para su evaluación.
Qué esperar
La operación consiste en fijar los extremos rotos de la clavícula con una placa y tornillos para que el hueso pueda sanar. La placa es resistente, pero funciona como un soporte, no como un sustituto del hueso curado: normalmente el hueso tarda entre seis y doce semanas en unirse, y sigue fortaleciéndose (remodelándose) durante varios meses después. La rehabilitación se organiza en función de este proceso biológico: en las primeras semanas se protege la fijación mientras la fractura comienza a soldarse; luego se recupera el movimiento; y por último se permite la carga de peso y la práctica deportiva, una vez que el hueso ya lo soporta.
Al tratarse de una fractura, cada avance importante (elevar el brazo por encima del nivel del hombro, fortalecimiento muscular, levantar cargas más pesadas y volver a hacer deporte) no depende únicamente del tiempo transcurrido, sino de cómo se ve la fractura en las radiografías, según se confirme en su consulta con el Dr. Hirpara. Los intervalos de semanas indicados a continuación son típicos, no fijos.
La curación ósea es más lenta en fumadores y en personas con diabetes; el tabaquismo, en particular, puede retrasar o incluso impedir que la fractura se una. Si usted fuma, las semanas posteriores a la fractura son un momento especialmente adecuado para dejar de fumar.
La clavícula se encuentra justo debajo de la piel, por lo que es común sentir (e incluso ver) la placa una vez que la hinchazón disminuye. En los primeros meses, puede ser sensible bajo el cinturón de seguridad o la correa de una mochila; esto suele mejorar a medida que esa zona se insensibiliza. Si la placa sigue causando molestias después de que la fractura haya sanado por completo, existe la opción de retirarla, tema que podrá discutirse en una consulta posterior; se trata de una decisión independiente y sin prisa, que se toma mucho después de que el hueso ya se haya unido.
Resumen del proceso:
- Fase I — Protección: semanas 0–3
- Fase II — Movilidad temprana: semanas 3–6
- Fase III — Fortalecimiento: semanas 6–12
- Fase IV — Retorno a la actividad plena y al deporte: a partir de la semana 12
Cómo usar el cabestrillo
El cabestrillo sostiene el peso del brazo, alivia las molestias y protege el hueso en proceso de curación durante las primeras semanas. Las reglas son sencillas:
- Úselo especialmente cuando esté fuera de casa, para proteger el brazo y evitar que alguien lo golpee. No es necesario usarlo para dormir.
- Durante las primeras tres semanas, úselo la mayor parte del tiempo. A partir de entonces, se irá retirando gradualmente según su comodidad; la mayoría de las personas dejan de usarlo a las seis semanas.
- Quíteselo para ducharse, para hacer los ejercicios y para realizar tareas tranquilas sentado con el brazo apoyado: comer, escribir, leer.
- Cuando esté en casa descansando, puede quitarse el cabestrillo si actúa con precaución: apoye el brazo en una almohada mientras está sentado y mantenga la mano por debajo del nivel del hombro.
- No debe conducir durante seis semanas (esto aplica a cualquier cirugía de hombro), ni mientras lleve el cabestrillo. Pasado ese tiempo, podrá volver a conducir una vez que pueda controlar el vehículo de forma cómoda y segura, según lo confirmado en su consulta con el Dr. Hirpara.
Sus primeros días después de la cirugía
Si se utilizó un bloqueo nervioso durante la intervención, es posible que el brazo se sienta entumecido y pesado durante algunas horas; manténgalo protegido en el cabestrillo hasta que recupere la sensibilidad normal. A continuación, algunos consejos prácticos para los primeros días:
- Tome los analgésicos antes de realizar los ejercicios y antes de sus sesiones de fisioterapia.
- Aplique hielo sobre la zona afectada para aliviar el dolor y la hinchazón; haga esto durante unos 15–20 minutos cada vez, envolviendo el hielo en un paño húmedo; nunca lo aplique directamente sobre la piel o la herida.
- Al usar el cabestrillo, relaje el hombro y permita que el cabestrillo soporte el peso del brazo.
- Cuide su postura: mantenga las orejas, los hombros y las caderas alineados, evitando que los hombros se hundan hacia adelante; una buena postura protege la posición de la fractura y ayuda a prevenir la rigidez.
- Desde el principio, mueva los dedos, la muñeca, el codo y el cuello.
- Si presenta cualquier problema, comuníquese con el consultorio o informe a su fisioterapeuta.
Fase I — Protección (Semana 0–3)
Kieran Hirpara 4.0
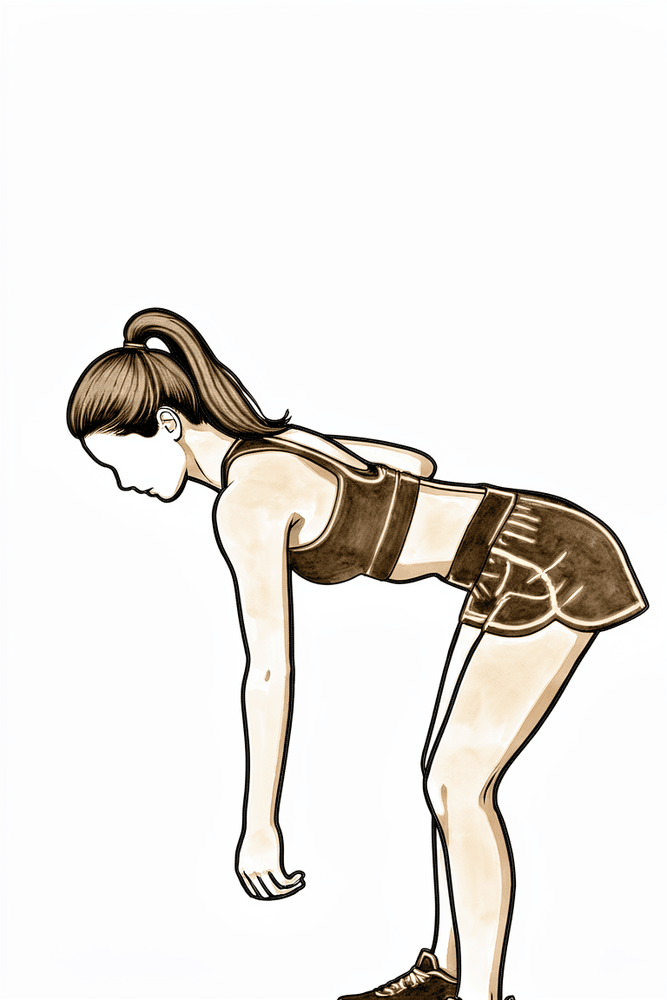
Ejercicios de péndulo
Incline el cuerpo hacia adelante, apoyándose con la otra mano en una mesa, y deje que el brazo operado cuelgue relajado. Realice pequeños círculos: primero en sentido horario y luego en sentido antihorario, balanceando su cuerpo suavemente. El brazo debe permanecer relajado en todo momento; el movimiento debe provenir del cuerpo, no del hombro.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
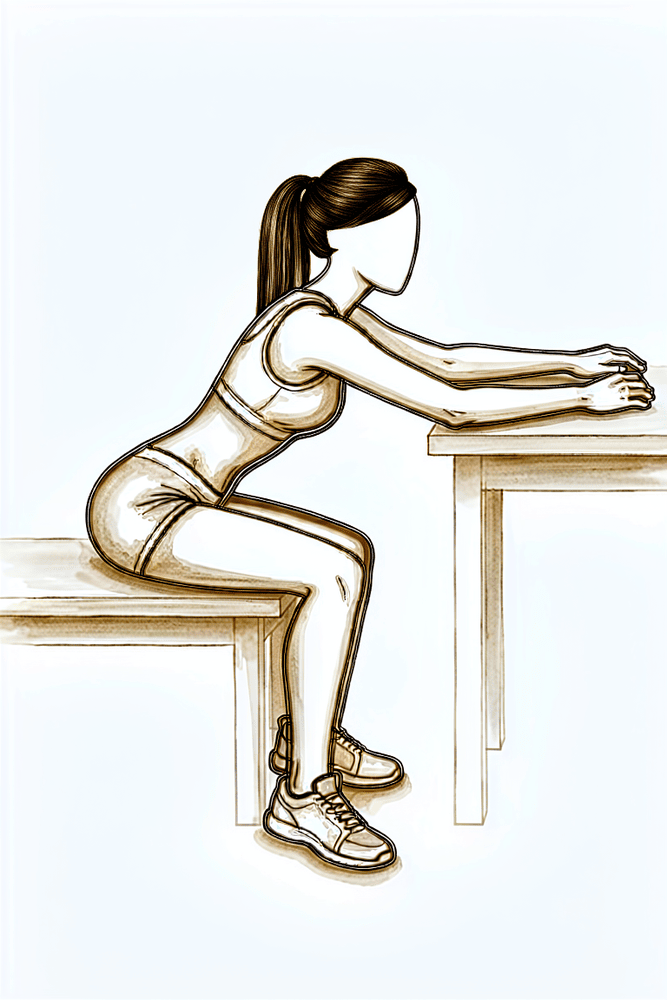
Deslizamientos sobre la mesa
Siéntese en una mesa con el antebrazo apoyado sobre ella. Incline el torso suavemente hacia adelante para que la mano se deslice por la mesa, permitiendo que la mesa soporte el peso del brazo; luego vuelva a sentarse erguido. Manténgase dentro de los límites de la comodidad y mantenga el brazo por debajo de la altura del hombro.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
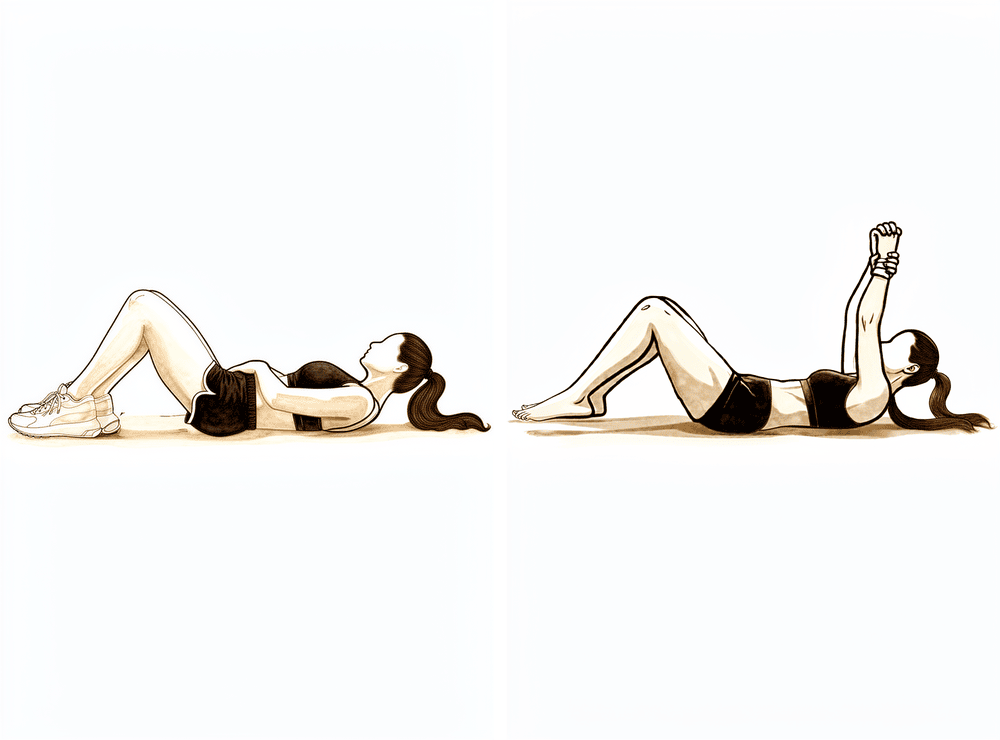
Flexión asistida del hombro (en decúbito)
Acuéstese boca arriba. Con la otra mano, sostenga la muñeca del brazo operado y levántelo suavemente hacia adelante hasta un máximo de 90 grados — apuntando al techo, pero sin superar ese ángulo — y luego bájelo. El brazo operado debe permanecer relajado; es la otra mano la que realiza el movimiento. No supere los 90 grados hasta que el médico lo autorice en su revisión a las seis semanas.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
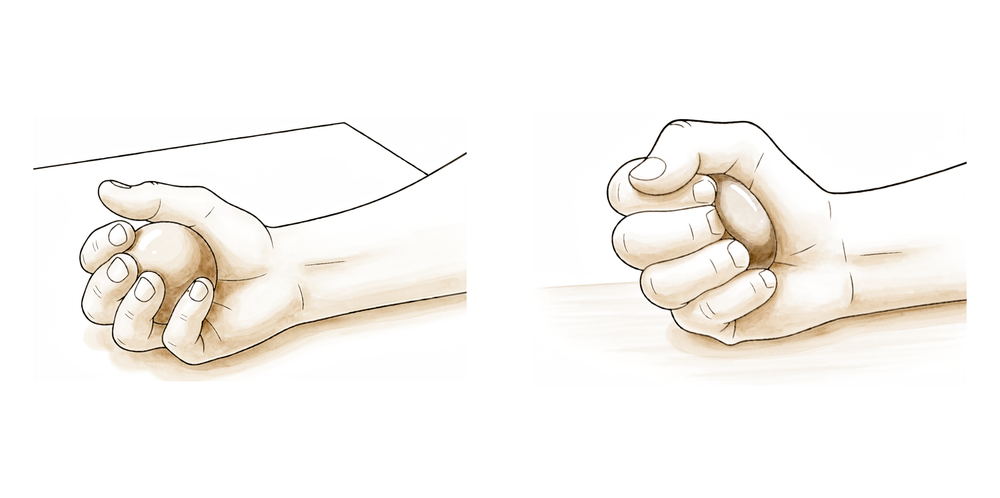
Aprietes de pelota
Con el brazo apoyado, apriete una pelota blanda o haga un puño cerrado, y luego abra la mano por completo. Mantenga los dedos, la muñeca y la mano en movimiento desde el inicio.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
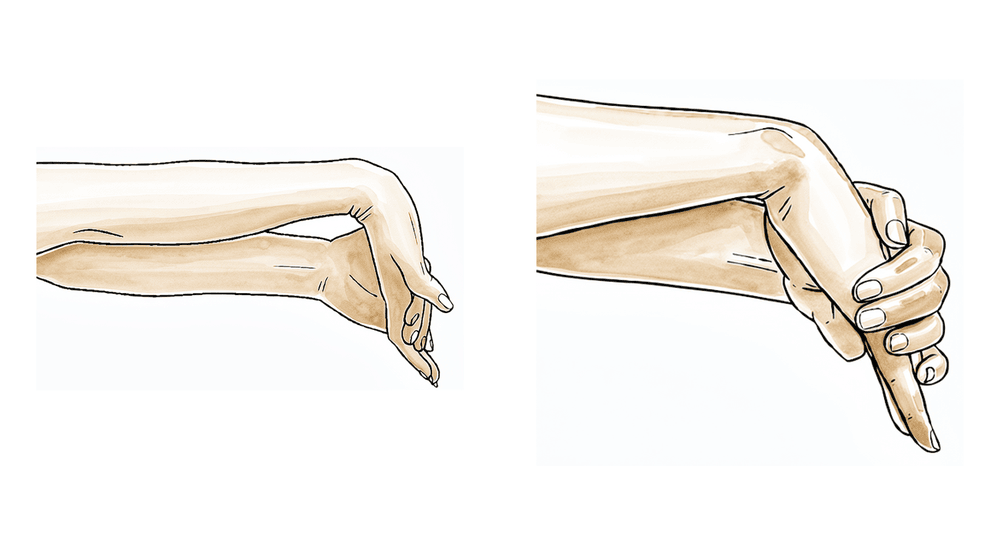
Movimiento de la muñeca
Con el brazo fuera del cabestrillo y bien sostenido, mueva la muñeca doblándola hacia adelante, hacia atrás y de lado a lado. Mantener la movilidad de la muñeca desde el principio evita la rigidez, al tiempo que se protege el hombro.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
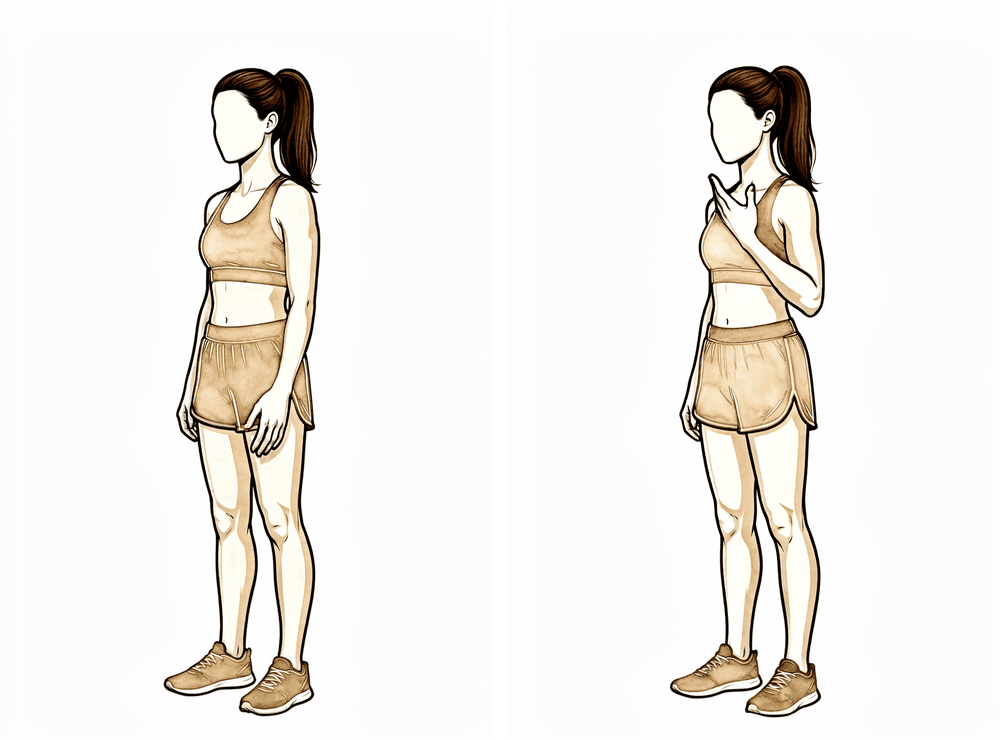
Flexión del codo
Con el brazo apoyado a lo largo del costado, flexione el codo todo lo que le resulte cómodo y luego extiéndalo por completo. Solo debe moverse el codo; mantenga el hombro relajado. De este modo, el codo queda libre mientras se protege la clavícula.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
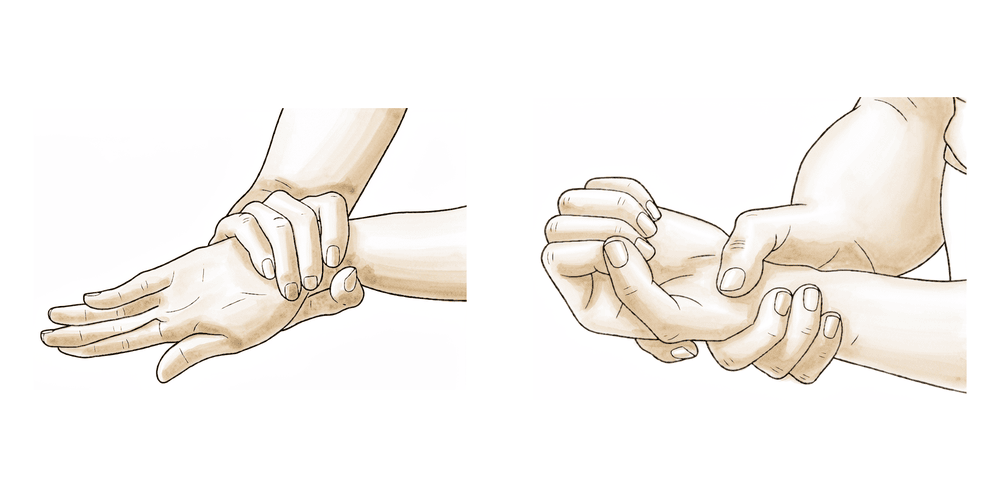
Rotación del antebrazo
Con el codo pegado al costado y doblado en ángulo recto, gire la palma de la mano hacia arriba y luego hacia abajo. Mantenga el brazo inmóvil, de modo que solo el antebrazo gire. A partir de la segunda semana, su fisioterapeuta podría añadir una resistencia suave a este ejercicio.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
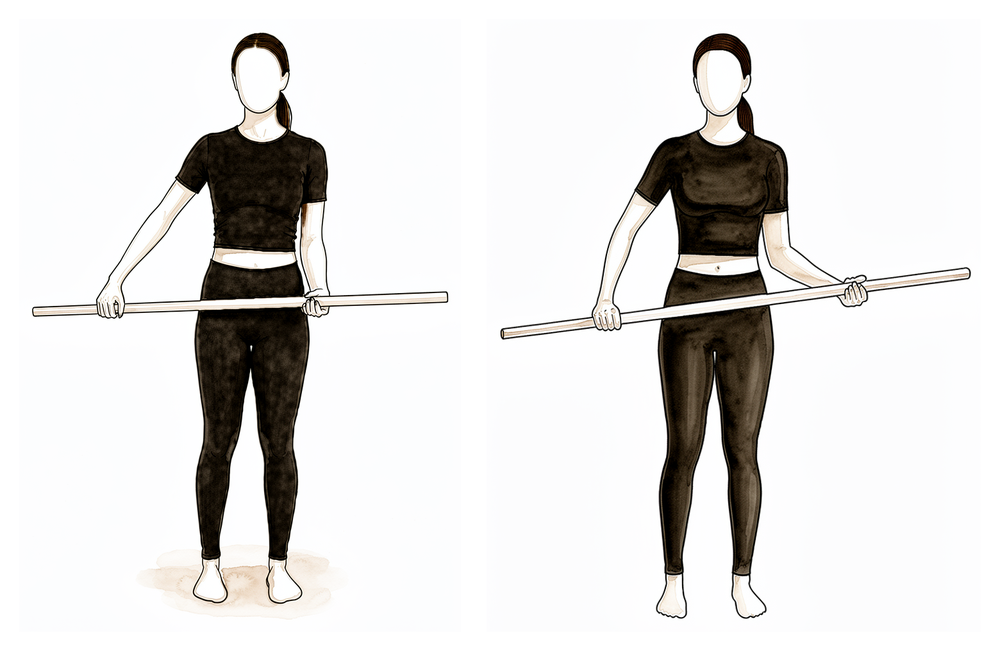
Rotación externa asistida mediante un palo
Acuéstese boca arriba con el codo operado pegado al costado y doblado en ángulo recto. Sostenga un palo con ambas manos y use el brazo sano para girar suavemente la mano operada hacia afuera, rotando el hombro, y luego vuelva a la posición inicial. Mantenga el codo junto al cuerpo; este es un movimiento asistido, no forzado.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
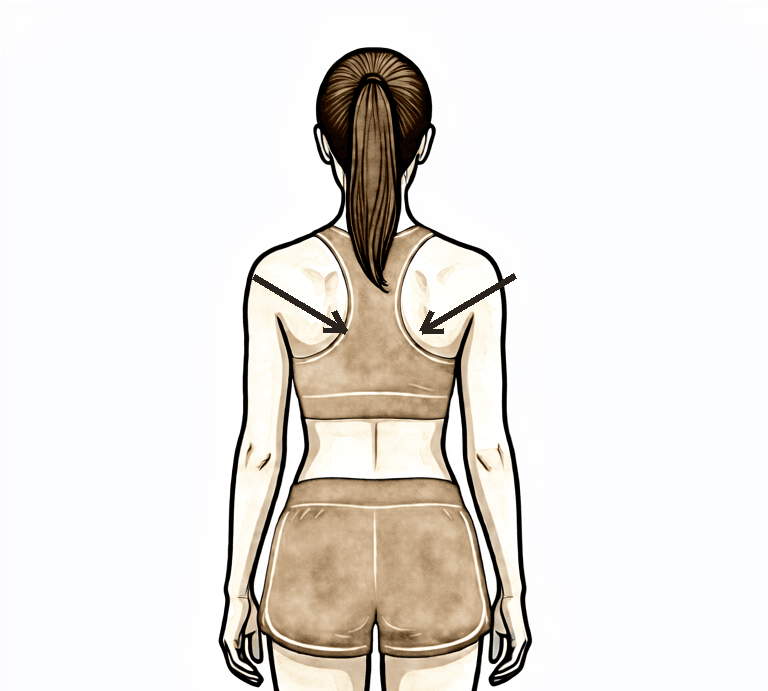
Posicionamiento de la escápula
Ya sea sentado o de pie, acerque suavemente los omóplatos el uno hacia el otro y hacia abajo, alejándolos de las orejas. Mantenga esa posición unos segundos y luego relájese. De esta forma, los músculos de los omóplatos permanecen activos sin mover la clavícula en proceso de curación.
Según las indicaciones de su fisioterapeuta.

Kieran Hirpara 4.0
Caminar con el brazo en cabestrillo
Mantenga una actividad cardiovascular suave, como caminar, con el brazo operado apoyado en el cabestrillo. Esto le ayudará a conservar su condición física general mientras se protege la fractura.
Según las indicaciones de su fisioterapeuta.
Durante las primeras semanas, el objetivo es proteger la fijación ósea mientras la fractura comienza a consolidarse. Deberá usar el cabestrillo, aplicar hielo para controlar la hinchazón y realizar ejercicios suaves que mantengan en movimiento el resto del brazo: la mano, la muñeca, el codo y el cuello; además de movimientos pendulares y movilizaciones asistidas del hombro por debajo de la altura del hombro. Las reglas más importantes: no levantar el codo por encima de la altura del hombro, no levantar ni cargar nada con el brazo operado, no empujar utilizando ese brazo, y no conducir durante seis semanas (esto aplica a cualquier cirugía de hombro) ni mientras lleve puesto el cabestrillo.
Para su fisioterapeuta:
Objetivos
- Proteger la fijación ósea y la cicatrización de huesos y tejidos blandos
- Controlar el dolor y la hinchazón
- Restaurar el rango de movimiento pasivo del hombro por debajo de los 90° de elevación
- Mantener el rango completo de movimiento activo del codo, muñeca, mano y columna cervical
Manejo
- Crioterapia y otras modalidades según sea necesario; analgesia previa a los ejercicios y sesiones
- Verificar el ajuste del cabestrillo; instruir al paciente sobre su uso (protección, especialmente fuera de casa; no es obligatorio usarlo durante la noche según la práctica habitual) y sobre la postura corporal
- Movimientos pendulares y deslizamientos sobre la mesa
- PROM: rotación externa e interna en el plano de la escápula hasta donde el paciente lo tolera; flexión, abducción y elevación hasta un máximo de 90°
- AAROM: rotación externa asistida con un palo en posición neutra; flexión asistida en decúbito supino hasta 90°
- AROM: movimientos activos del codo, muñeca, mano y columna cervical; ejercicios de agarre (apretar pelotas)
- A partir de la semana 2: flexión/extensión de muñeca y rotación de antebrazo con resistencia; ejercicios suaves de retracción y estabilización de la escápula
- Cardio: caminar con el brazo en el cabestrillo; bicicleta estática o recumbente con el brazo en el cabestrillo
Precauciones
- No realizar elevación activa del hombro
- No realizar flexión ni abducción del hombro más allá de los 90°, ni siquiera de forma pasiva
- No levantar ni cargar nada con el brazo operado; no soportar peso mediante ese brazo
- No conducir durante seis semanas (esto aplica a cualquier cirugía de hombro), ni mientras lleve puesto el cabestrillo
Criterios para avanzar
- Flexión/abducción pasiva cómoda hasta 90° y rotación externa de aproximadamente 30°
- Dolor controlado, por debajo de 4/10 en reposo
- Rango completo de movimiento activo del codo, muñeca y mano
- Herida cicatrizada, sin signos de complicaciones
Fase II — Movilización temprana (Semana 3–6)
Kieran Hirpara 4.0
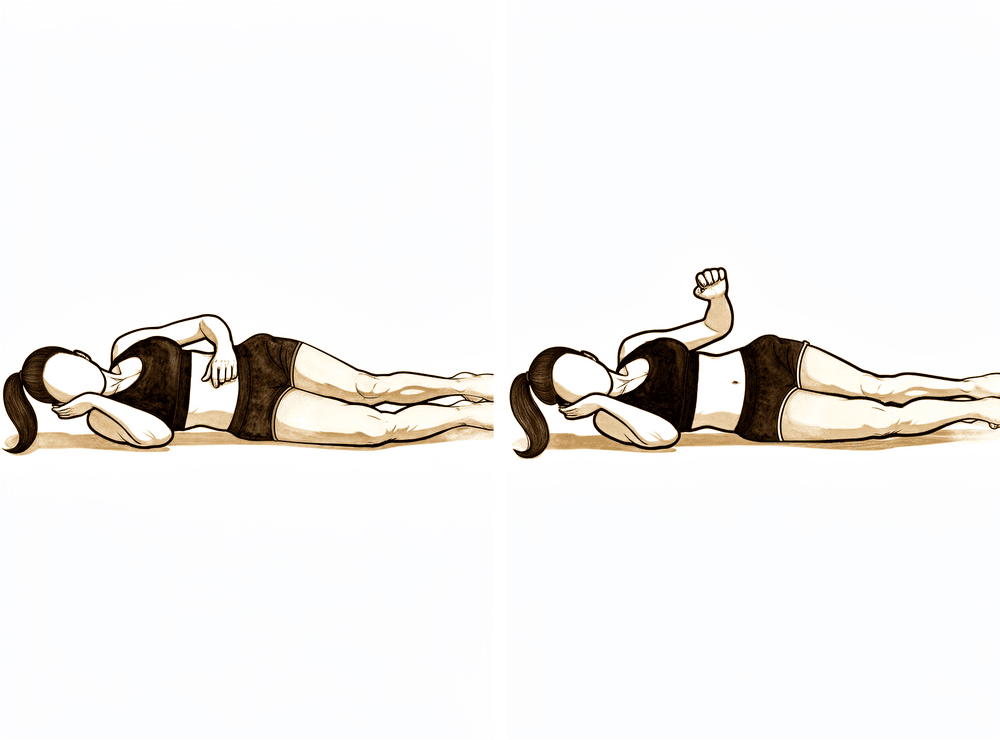
Rotación externa en decúbito lateral
Acuéstese sobre el lado no operado, con el brazo operado encima; doble el codo a 90 grados y acérquelo al cuerpo. Manteniendo el codo en esa posición, gire el antebrazo hacia arriba, alejándolo del abdomen, hasta donde le resulte cómodo; luego bájelo de forma controlada. En esta fase no se deben usar pesas: el brazo debe moverse únicamente por su propia fuerza.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
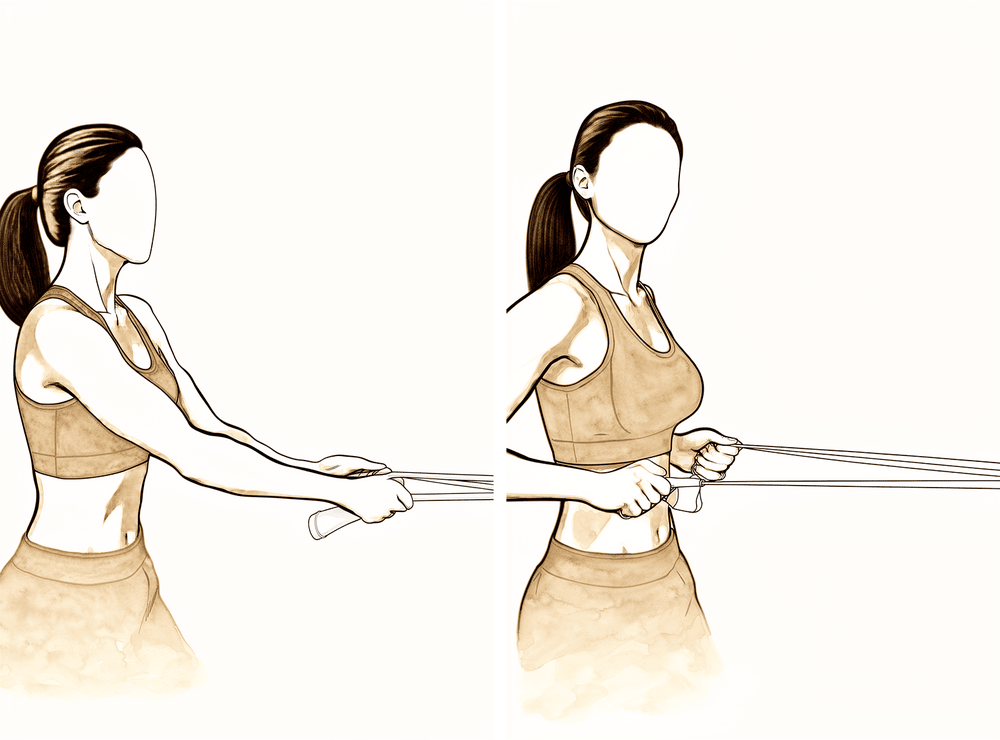
Ejercicio de remo con banda elástica
Fije una banda elástica delante de usted a la altura de la cintura. De pie, tire de la banda hacia sí, llevando suavemente el omóplato hacia abajo y hacia atrás; luego suelte la banda de forma controlada. Mantenga la resistencia en un nivel bajo.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
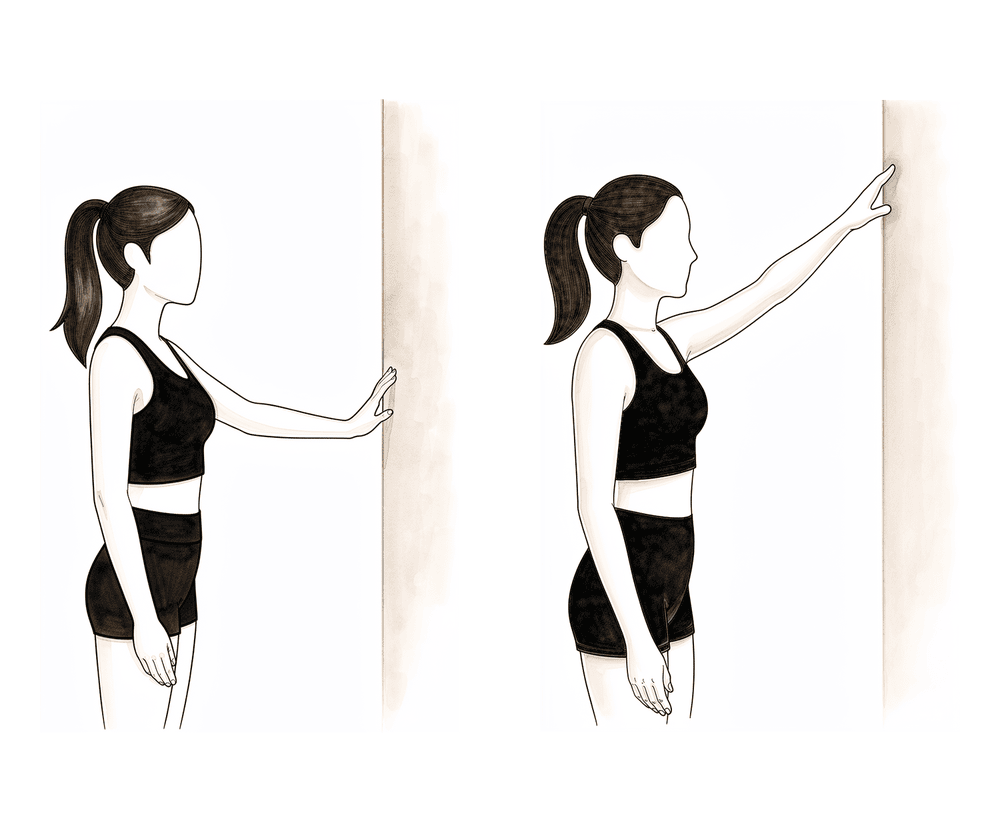
Deslizamientos en la pared (desplazamiento de los dedos)
Párese de cara a una pared y apoye los dedos en ella. Deslice los dedos hacia arriba por la pared para levantar el brazo; deje que la pared soporte parte del peso, y luego deslice los dedos de nuevo hacia abajo. Durante esta fase, mantenga el brazo por debajo de la altura del hombro: como la pared brinda la ayuda necesaria, el movimiento resulta suave y seguro.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
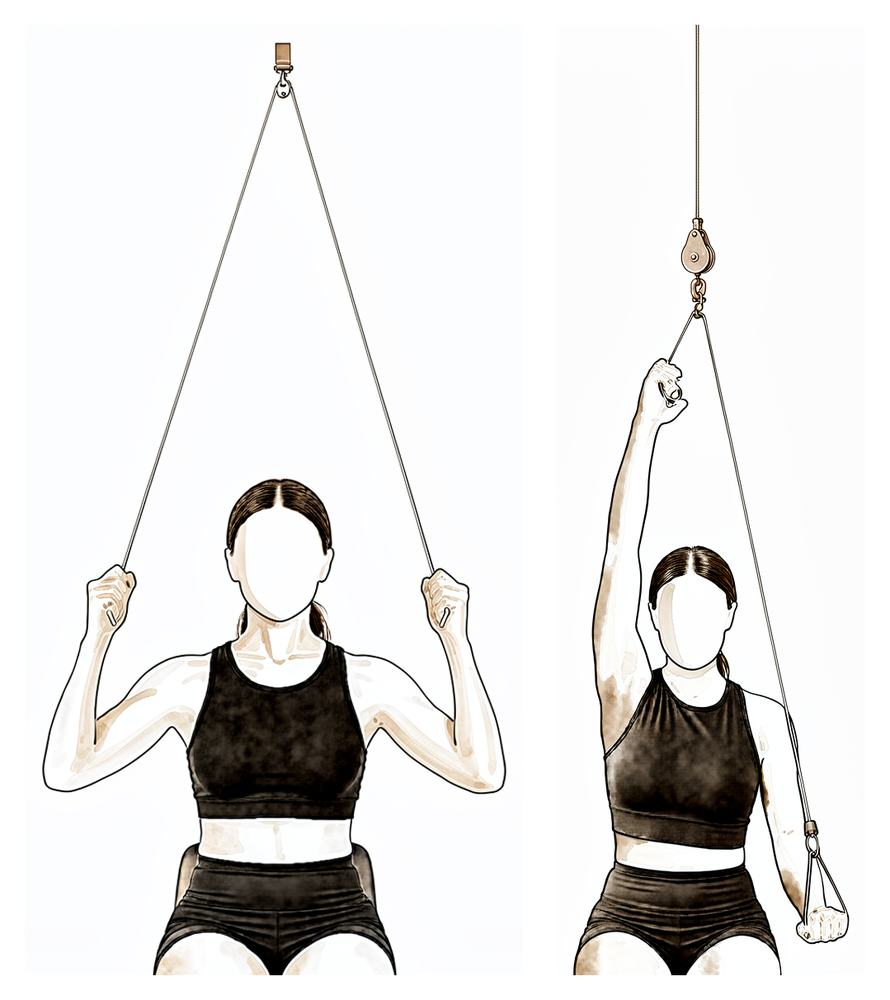
Polea de puerta
Siéntese debajo de una polea de puerta, sujetando un mango en cada mano. Tire hacia abajo con el brazo sano para elevar el brazo operado hasta donde le resulte cómodo; luego bájelo lentamente. Por ahora, mantenga el movimiento dentro de un rango suave y por debajo de la altura del hombro; el brazo sano es el que realiza el esfuerzo.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
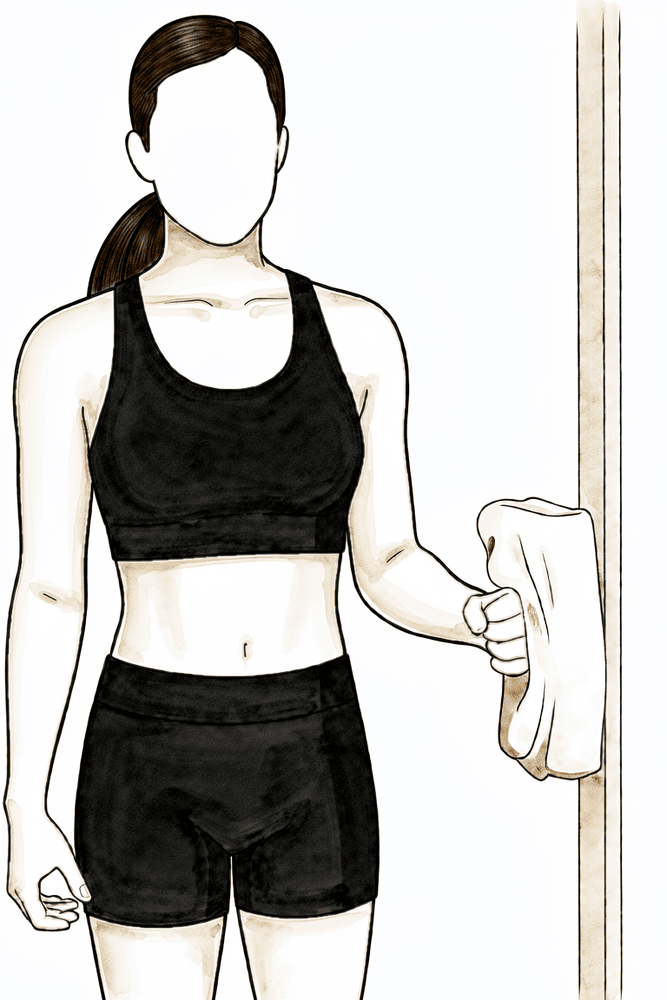
Rotación externa isométrica
Párese con el codo pegado al costado y doblado en ángulo recto, con el dorso de la mano apoyado contra una pared o marco de puerta. Presione suavemente hacia afuera sin mover el brazo, mantenga la posición unos segundos y luego relájese. Esto activa el manguito rotador sin necesidad de mover el hombro.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
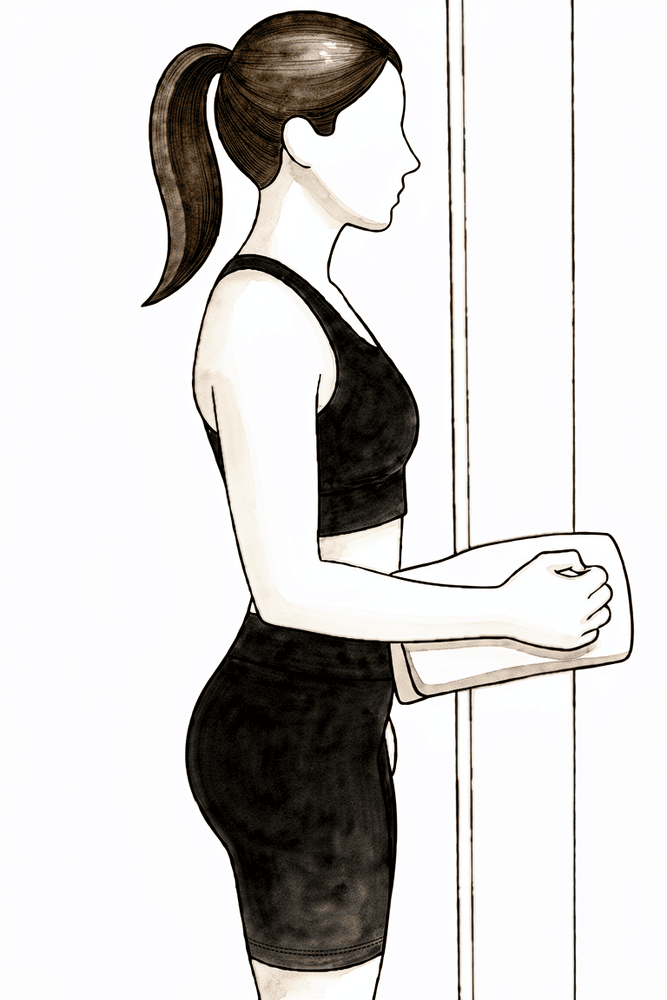
Rotación interna isométrica
Párese con el codo pegado al costado y doblado en ángulo recto; la palma de la mano debe quedar contra una pared o marco de puerta. Presione suavemente hacia adentro sin mover el brazo, mantenga la posición unos segundos y luego relájese. Es una forma suave de empezar a activar el manguito rotador.
Según las indicaciones de su fisioterapeuta.
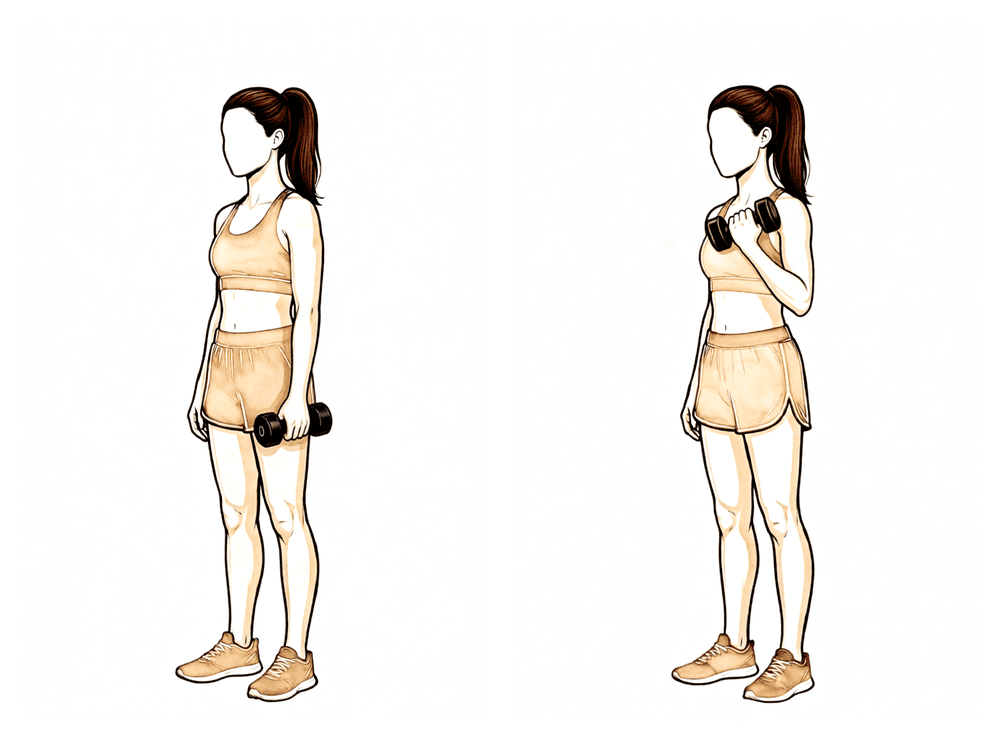
Kieran Hirpara 4.0
Flexión de bíceps
Con el brazo a un lado del cuerpo, doble el codo para levantar un peso ligero hacia el hombro y luego bájelo de forma controlada. Asegúrese de que el peso sea ligero; se trata de un ejercicio suave de tonificación del brazo, no de levantar cargas pesadas.
Según las indicaciones de su fisioterapeuta.
La fractura está empezando a consolidarse, pero aún no está curada: en esta fase se recupera el movimiento, no la fuerza. Se va retirando el cabestrillo según el paciente lo tolera; el rango de movimiento pasivo y asistido avanza hacia la amplitud completa, y el paciente comienza a mover el brazo por sí mismo por debajo de la altura del hombro, realizando además ejercicios suaves de activación muscular (isométricos). El peso de cualquier objeto que se levante o transporte debe ser, como máximo, el de una taza de café; además, se debe evitar cualquier estiramiento brusco. Esta fase concluye con una radiografía y una evaluación con el Dr. Hirpara alrededor de la semana seis; dicha evaluación, y no simplemente el paso del tiempo, permite iniciar el fortalecimiento y el movimiento por encima de la altura del hombro.
Para su fisioterapeuta:
Objetivos
- Retirar progresivamente el cabestrillo (se elimina alrededor de la semana 6)
- Lograr un rango de movimiento pasivo completo en todos los planos
- Establecer un rango de movimiento activo por debajo de los 90°, con buena mecánica articular
- Iniciar ejercicios isométricos suaves y ejercicios para la musculatura periescapular
Manejo
- PROM: avanzar hacia la amplitud completa de movimiento en todos los planos, según tolerancia; sin estiramientos bruscos
- AAROM: flexión en decúbito supino utilizando una varilla, progresando hacia posiciones verticales; deslizamientos contra la pared o barandillas, uso de poleas
- AROM: elevación del brazo por debajo de los 90°, sin dolor; flexión en decúbito supino que se va adaptando a la posición de pie; rotación externa en posición sentada o lateral
- Ejercicios isométricos para el manguito rotador en posición neutra; fortalecimiento leve de la musculatura periescapular (retracción escapular, remo ligero, remo medio); ejercicios suaves para bíceps y tríceps
- Vigilar la aparición de patrones compensatorios (elevación excesiva del hombro, sustitución por movimientos escapulares)
- Actividad cardiovascular: caminar; bicicleta estática
Precauciones
- No levantar ni transportar objetos cuyo peso supere el de una taza de café
- No realizar elevaciones activas por encima de los 90° hasta que la consolidación de la fractura se confirme en la evaluación de la semana seis
- Evitar cualquier estiramiento brusco del hombro o posturas que provoquen dolor
- No soportar peso alguno con el brazo
- No conducir durante seis semanas (esto aplica a cualquier cirugía de hombro), ni mientras se lleva el cabestrillo
Criterios para avanzar a la siguiente fase
- Rango de movimiento pasivo completo o casi completo
- Elevación activa hasta los 90°, con mínima compensación y dolor inferior a 4/10
- Consolidación satisfactoria de la fractura según la radiografía, confirmada en la evaluación con el Dr. Hirpara
Fase III — Fortalecimiento (Semana 6–12)
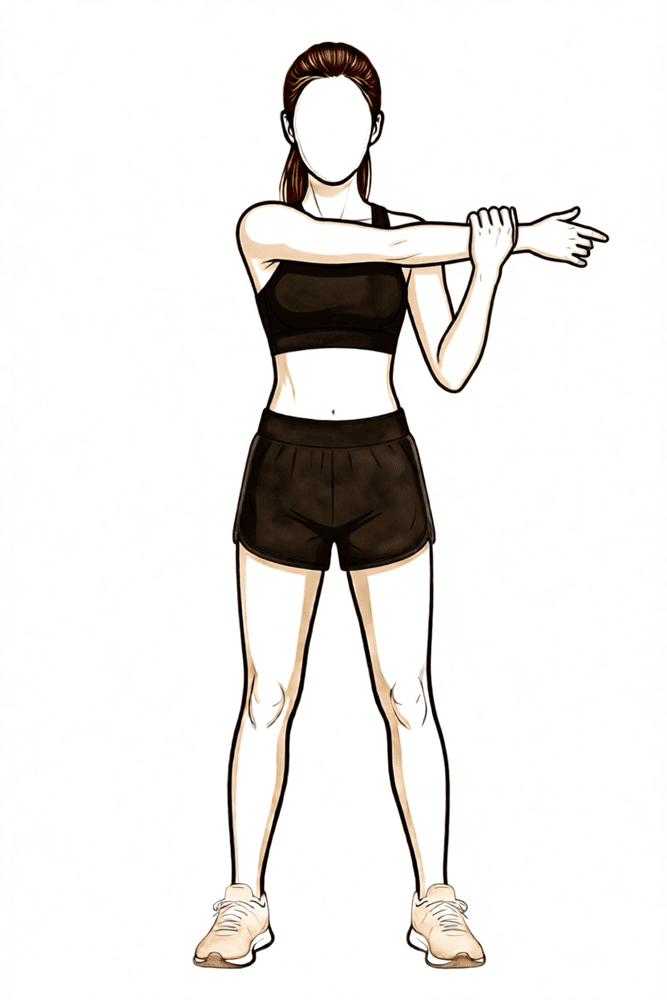
Kieran Hirpara 4.0
Estiramiento cruzado del cuerpo
Utilice la otra mano para llevar el brazo operado hacia el pecho hasta que sienta un estiramiento en la parte posterior del hombro. Mantenga esa posición brevemente y luego relájese. El estiramiento debe generar solo una molestia moderada; nunca debe provocar dolor intenso.
Según las indicaciones de su fisioterapeuta.
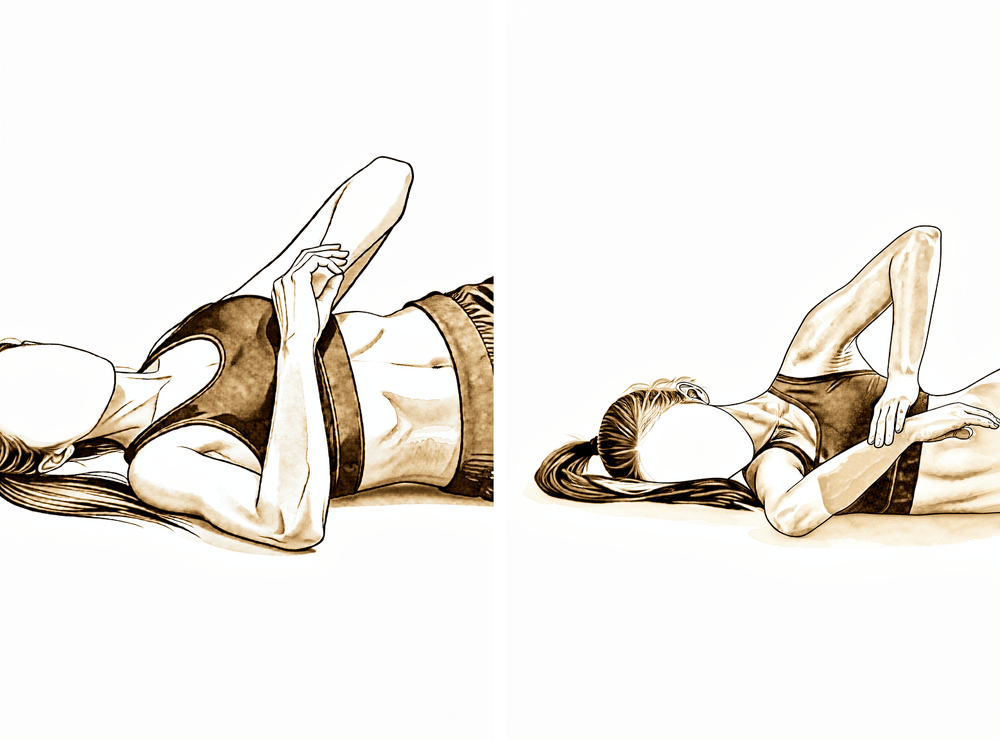
Kieran Hirpara 4.0
Estiramiento de “dormilón”
Acuéstese sobre el lado operado, con el hombro y el codo flexionados a 90 grados. Con la otra mano, presione suavemente el antebrazo hacia la cama hasta sentir un estiramiento en la parte posterior del hombro; luego suelte. Haga el movimiento con suavidad: no debe sentir dolor intenso.
Según las indicaciones de su fisioterapeuta.
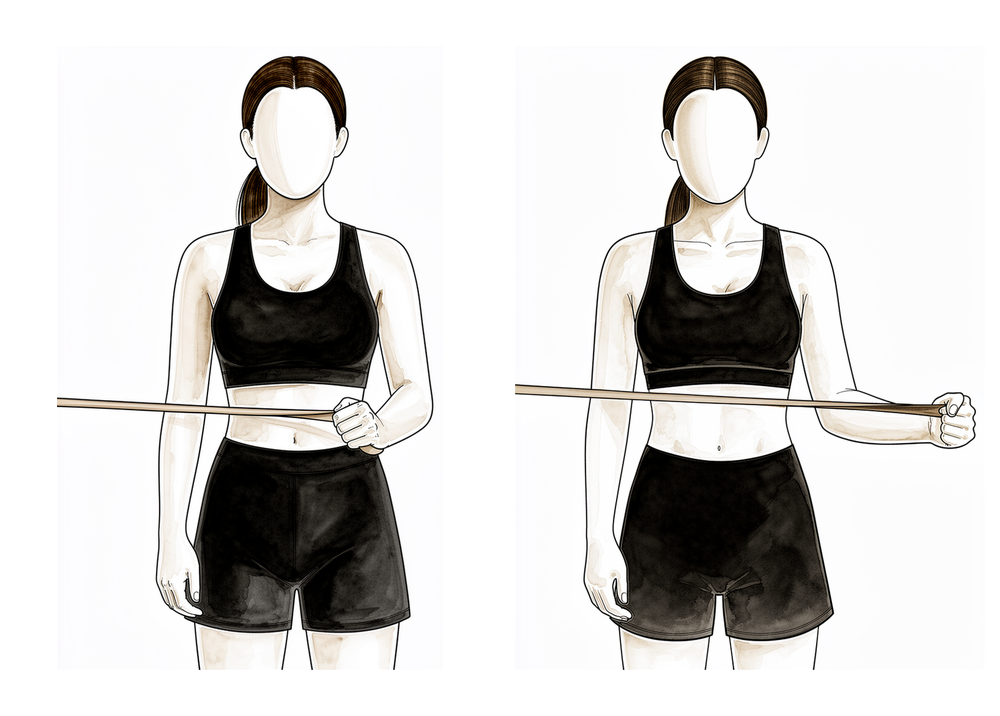
Kieran Hirpara 4.0
Rotación externa con banda elástica
Párese con el codo pegado al costado y doblado en ángulo recto, sosteniendo una banda elástica fijada a la altura de la cintura. Manteniendo el codo junto al cuerpo, gire el antebrazo hacia afuera contra la resistencia de la banda y luego regrese lentamente a la posición inicial. Este ejercicio hace progresar el trabajo del manguito rotador a partir de los ejercicios isométricos previos.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
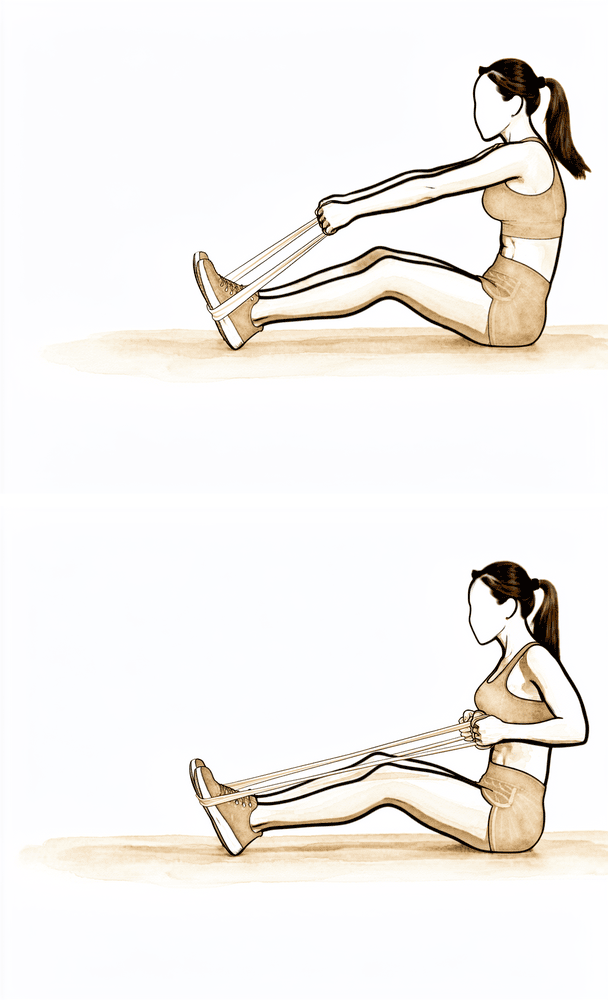
Remo bajo
Sostenga una banda elástica anclada frente a usted, a la altura de la cintura. Manteniendo el brazo bastante recto, tire de él hacia atrás y hacia abajo, en dirección a la cadera, contraiendo la escápula hacia abajo y hacia atrás; luego regrese lentamente a la posición inicial. Este ejercicio fortalece los músculos de la escápula que dan soporte al manguito rotador.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
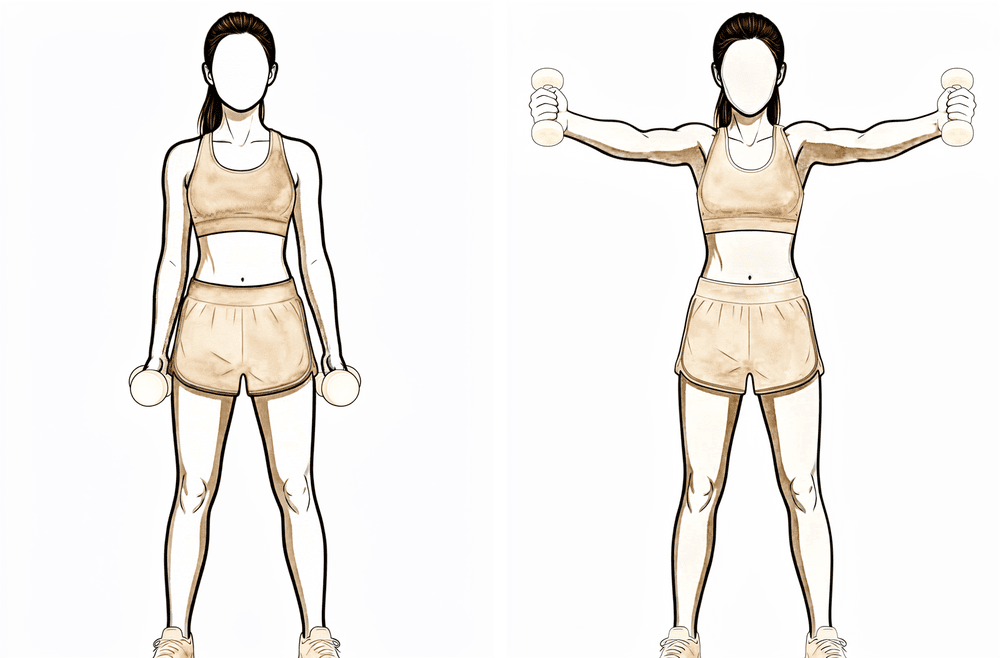
Elevaciones en el plano escapular («lata llena»)
Con los pulgares hacia arriba, levante el brazo hasta unos 45 grados frente a usted — entre la posición recta hacia adelante y la posición extendida hacia el costado — y luego bájelo de forma controlada. Una vez que se le autorice el rango por encima de la altura del hombro, eleve el brazo hasta un rango cómodo por encima de la cabeza. Utilice un peso ligero.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
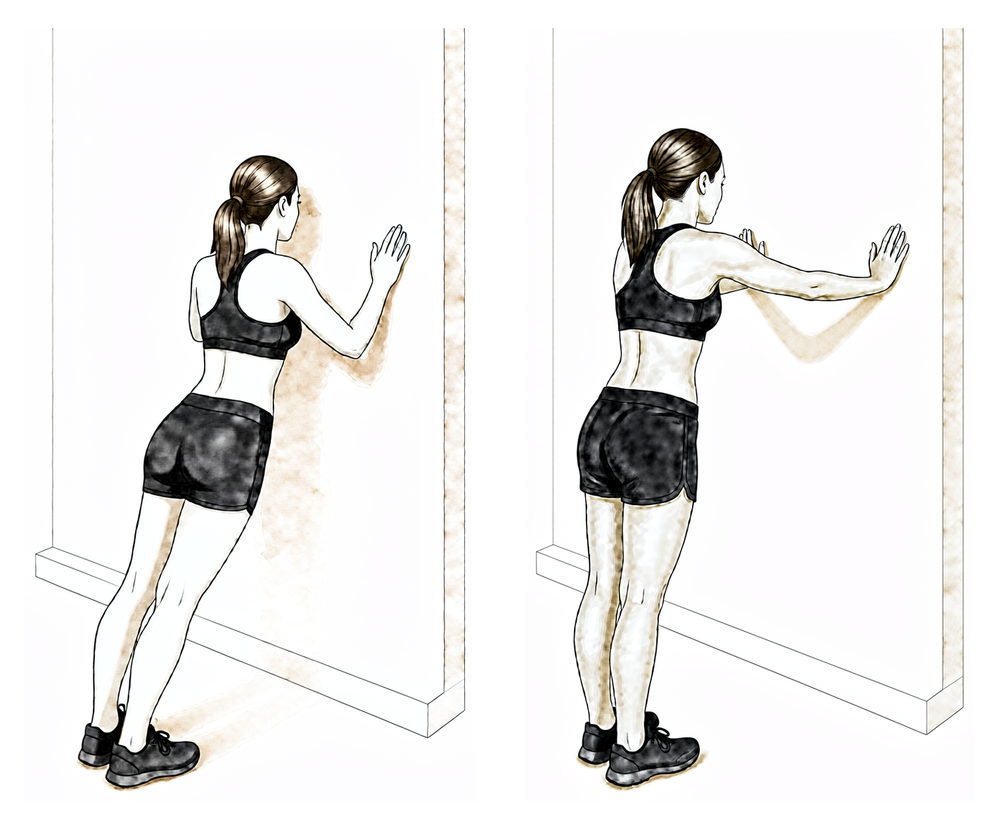
Flexiones contra la pared
Párese de frente a una pared, con las manos extendidas sobre ella a la altura de los hombros. Flexione los codos para inclinarse hacia la pared y luego empuje hacia atrás; al final, haga un empuje suave con las manos para separar los omóplatos. Introduzca este ejercicio únicamente al final de esta fase, siguiendo las indicaciones de su fisioterapeuta.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
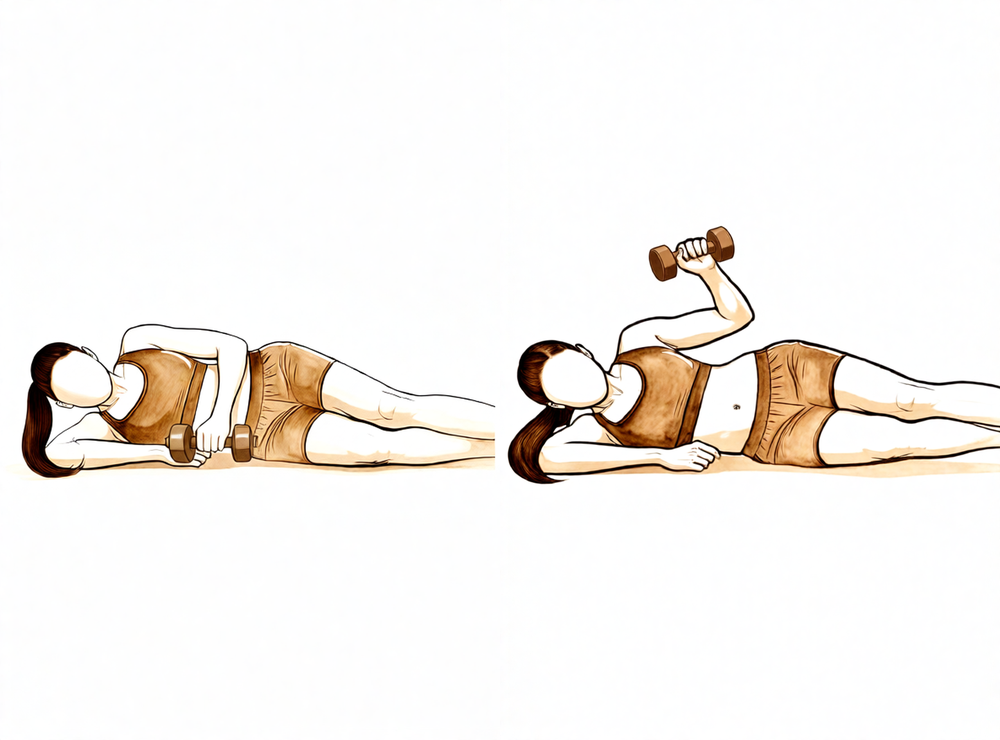
Rotación externa en decúbito lateral con carga
Acuéstese sobre el lado no operado, con el codo superior doblado en ángulo recto y pegado al cuerpo. Sosteniendo un peso ligero, gire el antebrazo hacia el techo y luego bájelo lentamente. Utilice un peso ligero y realice un mayor número de repeticiones.
Según las indicaciones de su fisioterapeuta.
Kieran Hirpara 4.0
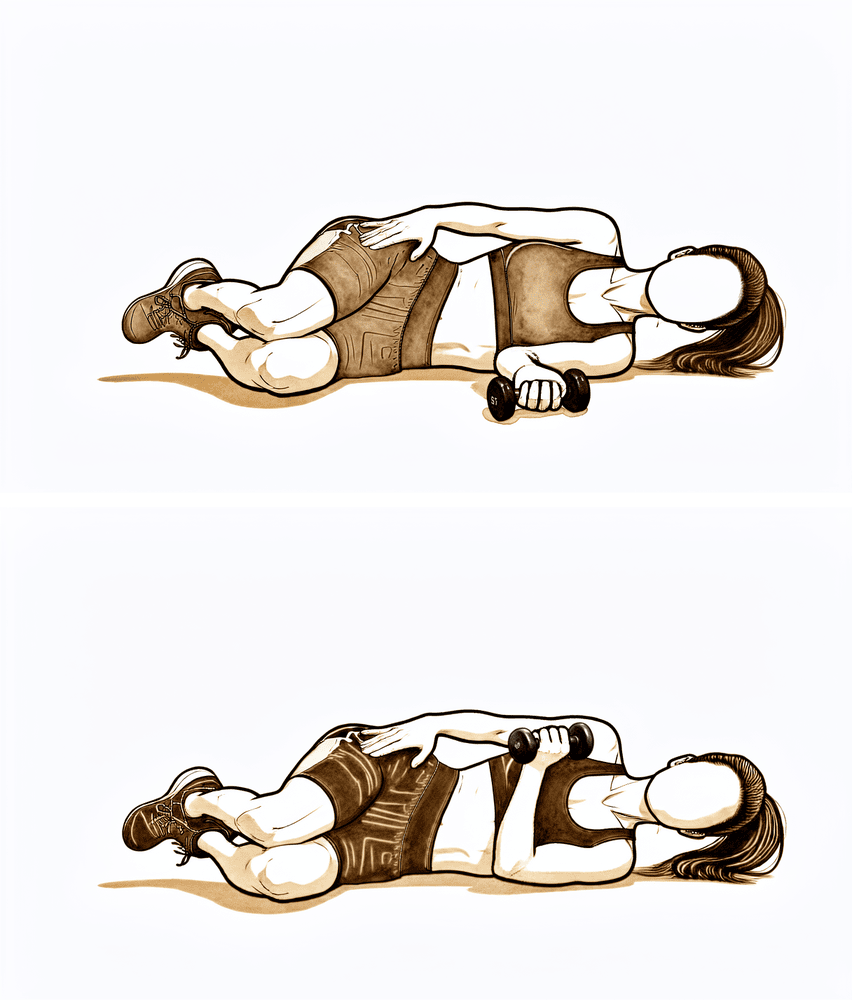
Rotación interna en decúbito lateral con carga
Acuéstese sobre el lado operado, con el codo doblado en ángulo recto y pegado al cuerpo. Sosteniendo un peso ligero, levántelo hacia el abdomen rotando el hombro hacia adentro y luego bájelo lentamente. Utilice un peso ligero y realice más repeticiones.
Según las indicaciones de su fisioterapeuta.
Una vez que la evaluación confirme que la fractura está sanando adecuadamente, se inician los movimientos por encima de la altura del hombro, y se va recuperando progresivamente el rango de movimiento activo durante las siguientes semanas. El fortalecimiento comienza de forma suave: primero se trabaja la activación muscular, luego se usan bandas elásticas y, posteriormente, pesas ligeras para los músculos del manguito rotador y de la escápula. El levantamiento de pesas debe mantenerse ligero (no más de 2 kg aproximadamente) hasta la semana 12; el levantamiento de cargas pesadas o por encima de la cabeza debe posponerse, y en esta fase no se permiten deportes de contacto. La natación y el ciclismo suelen reiniciarse en esta etapa, según las indicaciones de su fisioterapeuta.
Para su fisioterapeuta:
Objetivos
- Alcanzar un rango de movimiento activo completo en todos los planos, con mecánica normal
- Iniciar y progresar el fortalecimiento del manguito rotador y de los músculos periescapulares
- Retornar a las actividades cotidianas normales
Manejo
- Progresar el rango de movimiento activo por encima de 90° en todos los planos, minimizando patrones compensatorios
- Estiramientos según sea necesario: del dorsal ancho, pectorales, cápsula posterior y estiramientos en posición supina
- Fortalecimiento: ejercicios isométricos para el manguito rotador, progresando a ejercicios de rotación externa/interna resistida con bandas, inicialmente por debajo de la altura del hombro; retracción y ejercicios de remo para la escápula; elevaciones laterales, ejercicios para el músculo serrato y flexiones contra la pared hacia el final de la fase
- Uso progresivo de pesas libres ligeras, según tolerancia: carga baja y repeticiones elevadas
- Ejercicio cardiovascular: bicicleta estática y caminata; natación y carrera a partir de la semana 8–10, si así lo autoriza la evaluación médica
Precauciones
- No levantar cargas superiores a 2 kg hasta la semana 12
- Evitar levantar pesas pesadas por encima de la cabeza o lejos del cuerpo hasta la semana 12
- No practicar deportes de contacto; tampoco ejercicios pliométricos ni con impacto hasta finales de la fase (alrededor de la semana 10–12)
- El fortalecimiento debe mantenerse dentro del rango cómodo y no debe provocar dolor persistente
Criterios para avanzar a la siguiente fase
- Rango de movimiento activo equivalente al menos al 90 % del lado no afectado
- Buena activación del manguito rotador y de los músculos periescapulares, con un dolor no superior a 3/10 durante los ejercicios resistidos
- Progresión adecuada de la consolidación ósea según las radiografías, confirmada en la evaluación con el Dr. Hirpara
Fase IV — Retorno a la actividad plena y al deporte (a partir de la semana 12)
Kieran Hirpara 4.0
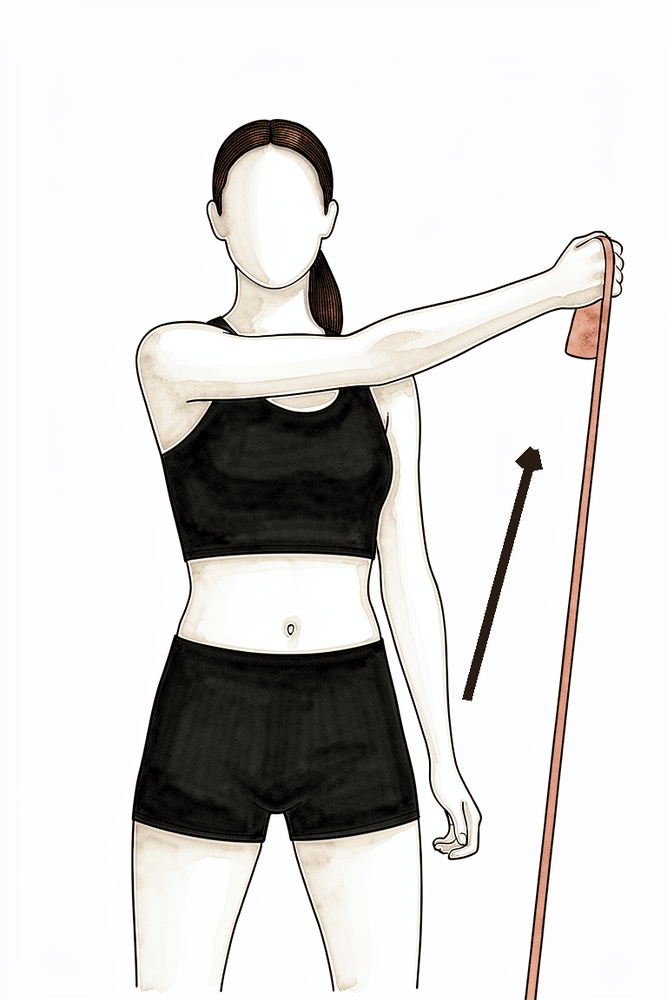
Patrón diagonal con una banda (D1)
Sujete una banda elástica y desplázala en diagonal a través del cuerpo: desde abajo, cruzando una cadera, hacia arriba y hacia el lado opuesto; luego repita el movimiento en sentido inverso con control. Estos patrones diagonales funcionales restablecen la coordinación del movimiento de todo el brazo, tal como se utiliza en el trabajo y el deporte. Realice este ejercicio únicamente una vez que la fractura haya consolidado.
Según las indicaciones de su fisioterapeuta.
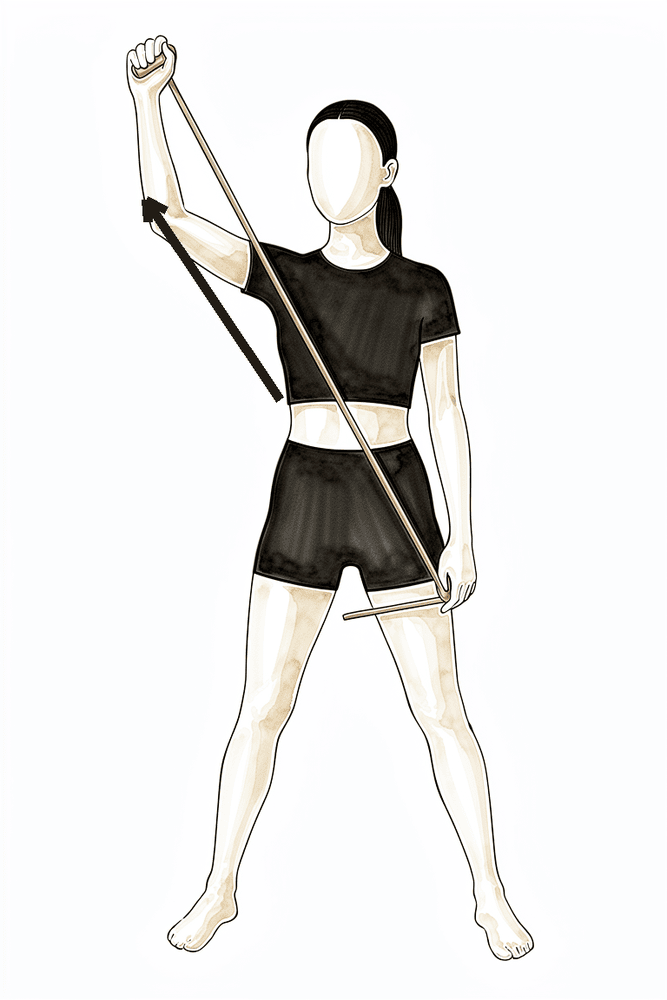
Kieran Hirpara 4.0
Patrón diagonal con una banda (D2)
Sujete una banda elástica y desplácela en diagonal, desde el lado opuesto del cuerpo hacia abajo, luego hacia arriba por encima de la cabeza y hacia afuera; a continuación, repita el movimiento en sentido inverso con control. Esto fortalece los patrones de movimiento por encima de la cabeza y específicos para el deporte en el hombro. Solo debe incorporarse este ejercicio una vez que la fractura haya consolidado y se haya autorizado el trabajo por encima de la cabeza.
Según las indicaciones de su fisioterapeuta.
La fase final consiste en un retorno gradual a levantamientos más pesados, al trabajo manual y al deporte. El entrenamiento de fuerza avanza mediante resistencias mayores, posiciones por encima de la cabeza y, para los atletas, ejercicios pliométricos, de lanzamiento y específicos de cada deporte. Para practicar deportes de contacto o colisión (fútbol, rugby, equitación), se requiere que la fractura haya consolidado según los rayos X, confirmado en la revisión con el Dr. Hirpara; normalmente esto ocurre a partir de los tres a cuatro meses, aunque algunos protocolos recomiendan esperar hasta los seis meses. Regresar antes de que el hueso haya consolidado conlleva riesgo de nueva fractura; por ello, este es un requisito esencial que debe cumplirse.
Para su fisioterapeuta:
Objetivos
- Mantener un rango de movimiento completo y sin dolor
- Alcanzar una fuerza mínima del 90 % del lado no afectado
- Retorno gradual al trabajo manual, a actividades recreativas y al deporte
Manejo
- Entrenamiento de resistencia progresivo, incluyendo cargas excéntricas, posiciones por encima de la cabeza y patrones funcionales según la tolerancia del paciente
- Ejercicios de estabilización rítmica y propiocepción; programas pliométricos e intervalados de lanzamiento o uso de raquetas para atletas que realizan actividades por encima de la cabeza
- Condicionamiento específico para trabajadores manuales; ejercicios deportivos específicos antes de volver a practicar el deporte sin restricciones
- La decisión de retorno al deporte debe ser individualizada (según si el deporte es de contacto o no, y la demanda que requiere de la extremidad superior) y coordinada con el cirujano
Criterios para avanzar
- Rango de movimiento activo completo y sin dolor
- Fuerza mínima del 90 % del lado no afectado según la dinamometría, sin dolor durante las pruebas de fuerza
- Finalización exitosa de un programa gradual de retorno al deporte, sin dolor ni sensación de inseguridad
- Consolidación ósea confirmada mediante radiografía en la revisión con el Dr. Hirpara antes de practicar deportes de contacto o colisión
Después de seguir el protocolo
Las fases descritas anteriormente se han adaptado de protocolos de rehabilitación publicados para la fijación de fracturas de clavícula: el Massachusetts General Brigham Sports Medicine, el Mammoth Orthopedic Institute, la Universidad de Colorado (Dr. Jonathan Bravman) y Midwest Orthopaedics at Rush (Dr. Brian Cole), además de las guías de fisioterapia del NHS procedentes de West Suffolk y United Lincolnshire, así como los datos sobre el retorno al deporte obtenidos de una revisión sistemática de fracturas de clavícula en atletas. Los intervalos de semanas indicados son orientativos y no fijos; su progreso lo guiará su fisioterapeuta y dependerá de la consolidación de la fractura, evaluada en las revisiones con el Dr. Hirpara. Esta página complementa las recomendaciones generales de recuperación de la clínica; consulte control del dolor postoperatorio y cuidado de la herida. Para información sobre la intervención quirúrgica, véase fijación de la clavícula. La base científica de este protocolo (datos de ensayos comparativos entre tratamiento quirúrgico y no quirúrgico, tasas de consolidación y retorno al deporte, así como los protocolos publicados por cirujanos) se resume en la sección de evidencia, disponible en formato PDF en la parte superior de esta página.
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Midshaft Clavicle Fracture — Operative vs Non-operative Management & Post-operative Rehabilitation (Plate ORIF)
Topic scope: (A) the decision between non-operative management and plate fixation for displaced midshaft clavicle fractures (the randomised-trial evidence on union, function and return to sport), and (B) post-operative rehabilitation after open reduction and internal fixation (ORIF) of the clavicle with a plate and screws. Distal-third and proximal-third fractures, which involve different fixation constructs, are noted only where they bear on the rehab principles.
Defining principle of the surgical rehab here: clavicle ORIF is a protect-the-fixation / protect-the-healing-fracture pathway, NOT an early-aggressive-motion pathway. The plate is a splint, not a substitute for healed bone — it neutralises load while the fracture itself unites over roughly 6–12 weeks and remodels for months afterwards. So the rehab is staged around fracture biology: a sling and below-shoulder-height-only motion early to protect the construct, range of motion progressed as the fracture knits (overhead motion deferred until the ~6-week x-ray), and strengthening / loading / collision sport withheld until radiographic union is confirmed. This is the opposite of a debridement or capsular-release pathway, where motion is the goal from day one and there is no fracture to protect. The single most important gate throughout is the x-ray, not the calendar — every major step up depends on how the fracture is healing.
A. THE OPERATIVE-vs-NON-OPERATIVE DECISION
Most clavicle fractures heal without surgery. The debate concerns completely displaced midshaft fractures (typically ≥100% displacement or ≥~2 cm shortening), where historic "all clavicles heal" teaching was overturned by randomised data.
The landmark trial — Canadian Orthopaedic Trauma Society (COTS) 2007
The COTS multicentre RCT randomised 132 patients with displaced midshaft clavicle fractures to plate ORIF vs non-operative sling treatment. Plate fixation produced a markedly lower nonunion rate (~2% vs ~23–24% non-operative), fewer symptomatic malunions, faster time to union, and better Constant and DASH scores at one year. This trial is the basis for offering surgery to active patients with completely displaced fractures — it did not establish that all such fractures require surgery. STRONG (RCT). [COTS 2007]
What later evidence tempered
- Meta-analyses of RCTs confirm operative fixation reduces nonunion and symptomatic malunion but show that much of the early functional advantage converges by 1 year, and comes at the cost of hardware-related reoperation. The decision is therefore shared and patient-specific (activity demands, displacement, comminution, smoking, occupation) rather than automatic. STRONG (SR/MA of RCTs). [Woltz-type meta-analysis; meta-regression, JSES 2020 — DOI 10.1016/j.jse.2020.02.011]
- A modern cohort comparison of dual mini-fragment plating vs non-operative care (mean 3.4-yr follow-up) found fewer union complications with fixation but similar patient-reported outcomes at final follow-up — echoing the "fixation buys reliable union, not necessarily a better long-term shoulder" theme. MODERATE (cohort). [DOI 10.1016/j.jse.2024.10.018]
- Heterogeneity between trials (how nonunion and displacement were defined, statistical handling of time-to-union) explains some of the apparent disagreement across studies — a caution against over-reading any single union statistic. MODERATE. [DOI 10.1016/j.jse.2012.03.015; meta-regression DOI 10.1016/j.jse.2020.02.011]
Construct choice (informs the rehab, not the patient's behaviour)
- Plate vs intramedullary fixation: an RCT comparing locked intramedullary nailing with plating found both achieve union; plates remain the workhorse for comminuted/displaced patterns. MODERATE (RCT). [DOI 10.1016/j.jse.2010.05.002]
- Plate position: superior plating is biomechanically strong but the plate lies directly under thin skin and is frequently symptomatic; anteroinferior plating lowers symptomatic hardware and removal rates. This is why patients commonly feel and see the plate, and why removal is a later, elective conversation. [Hardware-removal cohort, DOI 10.1016/j.jse.2017.03.011]
- Fixation reaches union even when delayed: immediate fixation vs delayed reconstruction of displaced midshaft fractures both restore objective strength and patient-oriented outcomes — reassuring that a fracture initially treated non-operatively can still be fixed successfully if it fails to unite. MODERATE (cohort). [DOI 10.1016/j.jse.2007.01.001]
B. POST-OPERATIVE REHABILITATION (plate ORIF)
The operation holds the fracture ends in position with a plate and screws so the bone can heal. Rehab is the same staged, fracture-protective sequence used across published surgeon and NHS protocols. Key facts that shape it:
- The plate neutralises load but the bone must unite biologically — typically 6–12 weeks to radiographic union, with remodelling for months after. Strengthening and loading that precede union risk implant loosening or re-fracture. Consensus / biomechanical.
- Bone healing is slower in smokers and in diabetics, and smoking can delay or prevent union — a modifiable risk worth addressing in the post-fracture window. Established.
- Overhead motion and strengthening are gated on the x-ray, not a fixed date — published protocols restrict elevation to ≤90° until early healing is confirmed (commonly the ~6-week review).
Consensus phased post-op timeline (plate ORIF)
| Phase | Window | Sling | ROM | Strengthening | Notes |
|---|---|---|---|---|---|
| I — Protection | Week 0–3 | Most of the time; off for showers/exercises/seated tasks; not required overnight | Passive/AAROM below 90° only — flexion/scaption/abduction capped at 90°, ER/IR in scapular plane to comfort; pendulums, table slides; full elbow/wrist/hand/cervical AROM | None at shoulder (grip + wrist only) | Protect fixation; settle pain/swelling; no driving while in sling; no lifting/carrying/weight-bearing through the arm |
| II — Early motion | Week 3–6 | Weaned as comfort allows; discarded by ~6 wk | Progress passive→full all planes (no forceful stretch); active motion below 90°; AAROM lawn-chair/pulley progression | Gentle isometrics + light periscapular work only | Recover movement, not strength. Lift ≤ a coffee cup. Phase ends with x-ray + review that gates overhead motion + strengthening |
| III — Strengthening | Week 6–12 | Off | AROM progresses above 90° once union confirmed; full active range built up | Cuff + scapular strengthening: isometric → bands → light weights; lift ≤ ~2 kg until 12 wk | Swimming/cycling typically return; no contact sport; no overhead/heavy lifting |
| IV — Return to activity & sport | Week 12 + | Off | Full, pain-free, maintained | Progressive heavy/eccentric/overhead loading; sport-specific + plyometric drills | Contact/collision sport needs radiographic union — typically ~3–4 months at the earliest, some protocols stage collision as late as 6 months |
The structure above matches the topic's patient protocol and is drawn from published surgeon ORIF protocols (Massachusetts General Brigham; Mammoth Orthopedic Institute; University of Colorado / Bravman; Midwest Orthopaedics at Rush / Cole) and NHS physiotherapy guidance (West Suffolk; United Lincolnshire). These protocols broadly agree on the sling ~3 weeks, ROM ≤90° early, overhead and strengthening after the ~6-week review, return to sport gated on union sequence; exact week boundaries vary by surgeon. WEAK / CONSENSUS — no rehab RCT defines the optimal regimen.
Return to sport — the evidence
- A systematic review of return to sport after clavicle fractures (Robertson & Wood, Br Med Bull 2016, 23 studies) found ~92% return to sport, at a mean of ~96 days (~3 months). MODERATE (SR of heterogeneous cohorts). [Robertson 2016]
- A more recent systematic review and meta-analysis reported mean return to play ~3.1 months operative vs ~3.9 months non-operative, with similar overall return rates but a higher rate of return to pre-injury level after operative treatment. MODERATE. [RTP SR-MA, JSES Rev 2024]
- In elite athletes specifically (e.g. NFL series), operative management has been used to achieve predictable, timely return — though selection bias makes these cohorts hard to generalise. WEAK (selected cohorts). [DOI 10.1177/0363546510372795]
The consistent signal: most athletes return by ~3 months, operative slightly faster and more reliably to pre-injury level — but union on x-ray, not the average timeline, governs clearance for collision sport.
C. KEY CONTROVERSIES / EVIDENCE QUALITY
- Who actually needs surgery. COTS established that fixation reduces nonunion/malunion in completely displaced midshaft fractures, but the early functional gap narrows by a year and fixation adds hardware reoperations. The modern position is shared decision-making for the active, completely-displaced patient — not routine fixation of all displaced fractures. Strong evidence, nuanced application.
- How big is the nonunion benefit, really? Reported nonunion rates vary with how "nonunion" and "displacement" are defined and how time-to-union is analysed; meta-regression shows this heterogeneity drives much of the between-study disagreement. Treat single headline figures with caution. Moderate.
- Hardware prominence and removal. Because the clavicle is subcutaneous, plates are often felt and sometimes symptomatic; removal rates depend heavily on plate position (anteroinferior < superior) and design (low-profile/dual). Removal is an elective, post-union decision. Moderate (cohorts).
- The rehab protocol itself is consensus. Phase timings come from surgeon patient-guidance documents and NHS leaflets, not a rehab RCT. The ≤90°-until-6-weeks and union-gated-sport principles are widely shared; precise week boundaries are not trial-derived. Weak/consensus.
D. EVIDENCE STRENGTH FLAGS (summary)
- STRONG (RCT / SR-MA of RCTs): plate fixation reduces nonunion and symptomatic malunion in displaced midshaft fractures (COTS 2007 RCT; meta-analyses), with early functional benefit that converges by ~1 year; plate vs IM nail both achieve union (RCT).
- MODERATE (cohorts / SR of cohorts): similar long-term PROs fixation vs non-op despite fewer union complications (dual-plate cohort 2024); return to sport ~92% at ~3 months, operative slightly faster/more reliable to pre-injury level (Robertson 2016 SR; RTP SR-MA 2024); hardware removal rate and its dependence on plate position; delayed fixation still succeeds.
- WEAK / CONSENSUS: the post-operative rehabilitation protocol itself (surgeon + NHS patient-guidance documents; no defining rehab RCT); elite-athlete operative series (selection bias).
CITATIONS
RAG corpus (180,000+ Orthopaedic articles) — clavicle-specific evidence
- Canadian Orthopaedic Trauma Society. Nonoperative treatment compared with plate fixation of displaced midshaft clavicular fractures: a multicenter, randomized clinical trial. J Bone Joint Surg Am. 2007;89(1):1–10. (also corpus-adjacent reanalysis: DOI 10.1016/j.jse.2012.03.015)
- Factors explaining heterogeneity in studies comparing surgical and nonsurgical treatment of midshaft clavicle fractures: a meta-regression analysis of RCTs and high-quality observational studies. J Shoulder Elbow Surg. 2020. DOI: 10.1016/j.jse.2020.02.011
- Dual mini-fragment plate fixation of midshaft clavicle fractures demonstrates fewer union complications but similar patient-reported outcomes compared to nonoperative management: a cohort study (mean 3.4-yr follow-up). J Shoulder Elbow Surg. 2024. DOI: 10.1016/j.jse.2024.10.018
- Locked intramedullary fixation vs plating for displaced and shortened mid-shaft clavicle fractures: a randomized clinical trial. J Shoulder Elbow Surg. 2010. DOI: 10.1016/j.jse.2010.05.002
- Does delay matter? Restoration of objectively measured shoulder strength and patient-oriented outcome after immediate fixation versus delayed reconstruction of displaced midshaft clavicle fractures. J Shoulder Elbow Surg. 2007. DOI: 10.1016/j.jse.2007.01.001
- Functional outcome of surgical treatment of symptomatic nonunion and malunion of midshaft clavicle fractures. J Shoulder Elbow Surg. 2007. DOI: 10.1016/j.jse.2006.12.002
- Plate fixation of midshaft clavicular fractures: patient-reported outcomes and hardware-related complications. J Shoulder Elbow Surg. 2015. DOI: 10.1016/j.jse.2015.09.029
- What is the hardware removal rate after anteroinferior plating of the clavicle? A retrospective cohort study. J Shoulder Elbow Surg. 2017. DOI: 10.1016/j.jse.2017.03.011
- A biomechanical and clinical comparison of midshaft clavicle plate fixation: are 2 screws as good as 3 on each side of the fracture? Orthop J Sports Med. 2017. DOI: 10.1177/2325967117725293
- Evolving management of middle-third clavicle fractures in the National Football League. Am J Sports Med. 2010. DOI: 10.1177/0363546510372795
- Effect of different statistical methods on union or time to union in a published study about clavicular fractures. J Shoulder Elbow Surg. 2012. DOI: 10.1016/j.jse.2012.03.015
- Treatment of clavicle fractures: current concepts review. J Shoulder Elbow Surg. 2011. DOI: 10.1016/j.jse.2011.08.053
Literature (URLs)
- Canadian Orthopaedic Trauma Society. Nonoperative treatment compared with plate fixation of displaced midshaft clavicular fractures: a multicenter RCT. JBJS 2007. https://journals.lww.com/jbjsjournal/fulltext/2007/01000/nonoperative_treatment_compared_with_plate.1.aspx
- Plate fixation versus nonoperative treatment for displaced midshaft clavicular fractures: a meta-analysis of RCTs. PubMed. https://pubmed.ncbi.nlm.nih.gov/28632595/
- Robertson GA, Wood AM. Return to sport following clavicle fractures: a systematic review. Br Med Bull. 2016;119(1):111–128. https://academic.oup.com/bmb/article-abstract/119/1/111/1744610
- Return to play following clavicular fracture — a systematic review and meta-analysis. JSES Rev Rep Tech. 2024. https://www.sciencedirect.com/science/article/pii/S2666639124001500
- Hardware removal after clavicle plating (rates, plate position): retrospective cohort. PubMed. https://pubmed.ncbi.nlm.nih.gov/28478898/
- Have new plate designs reduced hardware removal following midshaft clavicle fixation? J Clin Med. 2025. https://www.mdpi.com/2077-0383/14/18/6351
Published rehab protocols (patient-guidance — basis for the phase structure)
- Massachusetts General Brigham Sports Medicine. Rehabilitation Protocol for Clavicle ORIF. https://www.massgeneral.org/assets/MGH/pdf/orthopaedics/sports-medicine/physical-therapy/rehabilitation-protocol-for-clavicle-ORIF.pdf
- Crall T, Perumal J. Rehabilitation Guidelines for Clavicle Fracture S/P ORIF. Mammoth Orthopedic Institute. 2018. https://www.mammothortho.com/pdf/shoulder-clavicle-fx-orif-protocol.pdf
- Bravman JT. Clavicle ORIF Rehab Protocol. University of Colorado School of Medicine. https://www.sportsandshoulderdoc.com/pt-protocols/clavicle-orif.pdf
- Cole BJ. Clavicle Fracture ORIF Rehabilitation Protocol. Midwest Orthopaedics at Rush. https://www.briancolemd.com/wp-content/themes/ypo-theme/pdf/orif-clavicle-fracture-post-op-ver2.pdf
- West Suffolk NHS Foundation Trust. Clavicle ORIF — physiotherapy advice for patients after surgery. 2023. https://www.wsh.nhs.uk/CMS-Documents/Patient-leaflets/Physiotherapy/6857-1-Clavicle-open-reduction-internal-fixation-ORIF-physiotherapy-advice.pdf
- United Lincolnshire Teaching Hospitals NHS Trust. Clavicle Fracture ORIF — physiotherapy advice for patients after surgery. June 2025. https://www.ulh.nhs.uk/wp-content/uploads/2025/07/Clavicle-fracture.pdf