Patients › Hand
Dedo en martillo
Mallet finger causes fingertip drooping after extensor tendon injury; splinting is key, surgery occasionally needed.
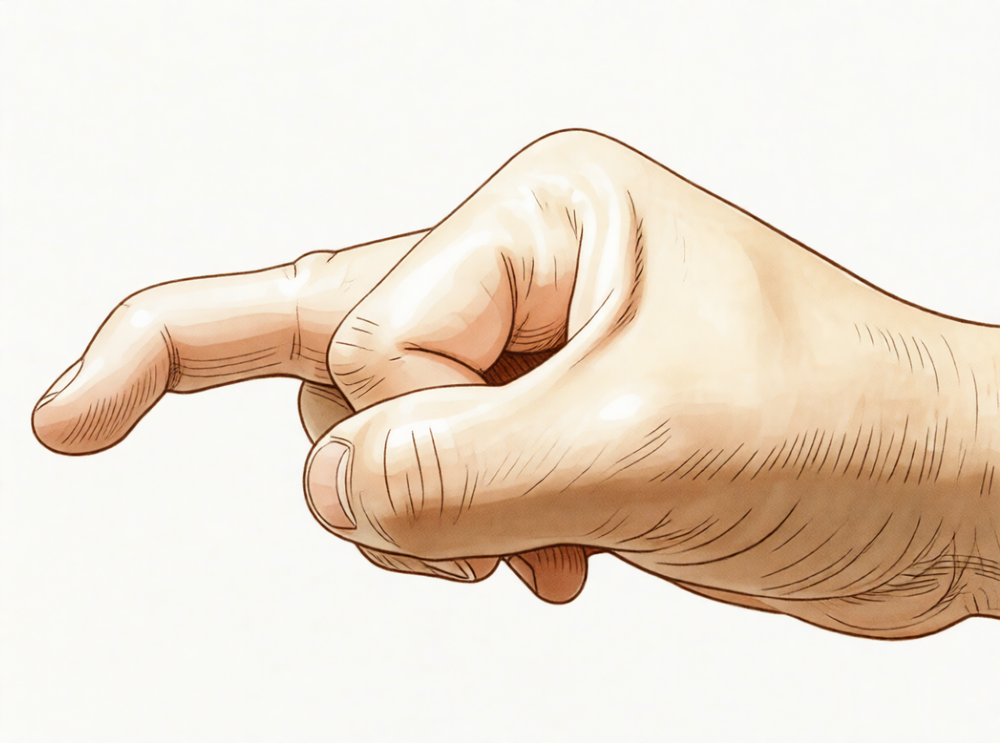
Qué está sintiendo
En el caso de un dedo en martillo, la última articulación del dedo queda caída y no puede enderezar la punta del dedo por sí mismo. Por lo general, el dedo sigue doblándose hacia abajo con normalidad. La lesión se produce cuando el tendón que endereza la punta del dedo se desprende, a veces arrastrando consigo un pequeño fragmento óseo. Suele ocurrir cuando un balón golpea el extremo de un dedo recto, por eso es una lesión frecuente en el fútbol.
El dolor se localiza en la parte dorsal de la última articulación, justo por debajo de la uña. Suele ser más intenso en los primeros días después de la lesión, cuando el dedo está hinchado y sensible al tacto. Doblar la punta del dedo lo empeora. Una vez que el dedo está inmovilizado con una férula y se mantiene recto, el dolor suele calmarse. La caída en sí no duele, pero cambia la forma en que funciona el dedo.
Las tareas diarias que requieren una punta del dedo firme se vuelven difíciles. Recoger monedas pequeñas, enhebrar una aguja, girar una llave pequeña o pulsar botones puede resultar torpe, porque la punta del dedo no consigue apoyarse plana. Escribir o sostener un teléfono también puede sentirse diferente. La articulación media del dedo también puede doblarse hacia atrás más de lo habitual para compensar la punta caída.
Algunas personas notan que el dedo tiene peor aspecto por la mañana, después de que la mano ha estado quieta durante la noche, y que se suelta una vez que empiezan a moverlo.
Algunos signos de alarma requieren actuar con rapidez. Si el dedo se pone caliente, enrojecido, hinchado y doloroso, sobre todo si tiene fiebre, acuda al servicio de urgencias ese mismo día. Si hay piel abierta sobre la articulación lesionada, o el dedo presenta una deformidad evidente, acuda ese mismo día. Si el dedo se pone pálido, frío, blanco o azulado, o pierde de repente la sensibilidad o el movimiento del dedo después de una lesión, acuda ese mismo día. Si los síntomas no mejoran, empeoran a lo largo de las semanas o le impiden trabajar o usar la mano, consulte a su médico de cabecera o pida una valoración por un especialista.
¿Qué está ocurriendo realmente?
Por la parte dorsal de la punta del dedo discurre un delgado cordón de tendón, una cuerda de fibras que une el músculo al hueso. Sus fibras más distales se fijan al último hueso pequeño del dedo, justo por debajo de la uña. Cuando endereza el dedo, ese cordón tira del hueso. En el dedo en martillo, el cordón se ha desprendido de su punto de anclaje. A veces arranca consigo un pequeño fragmento de hueso.
Una vez que el cordón deja de estar fijado, nada sostiene la punta del dedo hacia arriba. El músculo que dobla la punta del dedo hacia abajo sigue funcionando y, como nada tira en sentido contrario, se impone. La punta queda caída y usted no puede enderezarla por sí mismo, aunque todavía puede empujarla hasta dejarla recta con la otra mano. Esto se debe a que el músculo que dobla el dedo está intacto y el cordón que lo endereza no.
La lesión suele producirse cuando una punta del dedo recta se ve forzada a doblarse de repente, por ejemplo al engancharse en un bolsillo o en una sábana al estirar la mano. También puede verse afectada la superficie articular. Si el fragmento óseo desprendido abarca más de un tercio de la superficie articular, o el último hueso se desalinea, por lo general se recomienda la cirugía. Los fragmentos más pequeños suelen tratarse solo con una férula.
Puede quedar cierta caída incluso cuando el tratamiento va bien, y la mayoría de las personas se adaptan a ella sin mucha dificultad. Si la férula no ha funcionado, la cirugía es una opción, aunque no se ha demostrado claramente que la cirugía ofrezca una ventaja.
¿Qué podemos hacer al respecto?
El Dr. Kieran Hirpara, cirujano de extremidades superiores en el Mater Private Hospital Rockhampton, adapta el tratamiento a su lesión específica. Algunos dedos en martillo se curan sin operación y otros necesitan cirugía pronto, por lo que es importante una evaluación sin demora. Por lo general, los pacientes son derivados a nuestra clínica por su médico de cabecera; si un fisioterapeuta le ha recomendado consultarnos, igualmente necesitará una derivación de su médico de cabecera para poder acceder al reembolso de Medicare. En la clínica tomamos su historia clínica, examinamos el dedo y solicitamos una radiografía si es necesaria. La radiografía muestra si se ha desprendido un fragmento óseo junto con el tendón, qué tamaño tiene ese fragmento y si el último hueso del dedo se ha desalineado.
Para la mayoría de las lesiones, el tratamiento comienza con una férula que mantiene recta la punta del dedo. La férula debe llevarse puesta de forma continua durante 6 a 8 semanas, porque incluso unos pocos minutos de flexión, por ejemplo al lavarse las manos, pueden deshacer la cicatrización. Nuestra terapeuta de mano, Ruby Doolan, de Extend Rehabilitation, le coloca la férula y le guía en los ejercicios. Un terapeuta de mano puede tratar estas lesiones tan bien como un cirujano, y la férula causa muy pocos problemas en la piel. Si el dedo sigue caído al retirar la férula, las semanas adicionales de férula forman parte del plan y no son señal de que haya fracasado. Añadir una férula nocturna no aporta nada. Si practica deporte, deberá evitar el deporte que causó la lesión mientras el dedo esté inmovilizado con la férula. Incluso las lesiones que se dejaron sin tratar durante 2 a 4 semanas antes del tratamiento pueden evolucionar bien con la férula.
Por lo general se recomienda la cirugía cuando el fragmento óseo desprendido abarca más de un tercio de la superficie articular, o cuando el último hueso del dedo se ha desalineado hacia la palma. También se ofrece en ocasiones para una caída que persiste después de la férula, o para una lesión antigua que nunca se trató. Si la férula no ha funcionado, la cirugía es una opción, aunque no se ha demostrado claramente que la cirugía ofrezca una ventaja. La operación mantiene el tendón o el fragmento óseo en su sitio para que la punta del dedo pueda volver a enderezarse, y tiene su propia página.
Qué esperar
La mayoría de los dedos en martillo se resuelven con una férula. Aproximadamente la mitad de las lesiones se curan o mejoran claramente solo con la férula. La férula mantiene recta la punta del dedo durante 6 a 8 semanas, y el tendón cicatriza en esa posición. Si el dedo sigue caído al retirar la férula, más semanas de férula forman parte del plan y no son señal de que haya fracasado.
Su evolución depende en gran medida de que use la férula exactamente según las indicaciones. Las personas que siguen las instrucciones de la férula obtienen mejores resultados que las que se la quitan. Incluso unos pocos minutos de flexión pueden deshacer la cicatrización, por eso la férula se lleva puesta de forma continua. Las lesiones tratadas dentro de las dos semanas posteriores a producirse rara vez dejan una discapacidad duradera. Las lesiones que quedaron sin tratar durante 2 a 4 semanas todavía pueden evolucionar bien con la férula, por lo que empezar tarde no es motivo para darse por vencido.
Puede quedar cierta caída incluso cuando el tratamiento va bien. Es posible que la punta del dedo no quede perfectamente recta, y la mayoría de las personas se adaptan a ello sin mucha dificultad. La última articulación aporta poco al trabajo de agarre, por lo que una pequeña caída permanente suele importar menos de lo que parece. Si la férula no ha funcionado, la cirugía es una opción, aunque no se ha demostrado claramente que la cirugía ofrezca una ventaja.
Si se deja completamente sin tratar, el dedo en martillo tiende a mantener la caída. El tendón no vuelve a fijarse por sí solo sin ayuda. Algunas personas conviven con la caída y se manejan bien, mientras que otras encuentran frustrante la torpeza de la punta del dedo a lo largo de los meses. Si sus síntomas no mejoran, empeoran a lo largo de las semanas o le impiden trabajar o usar la mano, consulte a su médico de cabecera o pida una valoración por un especialista.
Cuándo consultar a un especialista
La mayoría de los dedos en martillo se deben a un balón que golpea el extremo de un dedo recto, a menudo en el fútbol. La punta del dedo queda caída y no se endereza por sí sola, lo que suele bastar para motivar una consulta. Algunas fracturas más grandes se comportan de otra manera: la punta del dedo puede seguir recta aunque se haya desprendido un fragmento óseo, por lo que un dedo dolorido que no mejora tras un golpe en la punta sigue mereciendo una radiografía. Las lesiones óseas en martillo suelen producirse cuando el dedo se fuerza hacia atrás, no hacia delante.
Algunos signos requieren actuar con rapidez. Si el dedo se pone caliente, enrojecido, hinchado y doloroso, sobre todo si tiene fiebre, acuda al servicio de urgencias ese mismo día. Si hay piel abierta sobre la articulación lesionada, o el dedo presenta una deformidad evidente, acuda ese mismo día. Si el dedo se pone pálido, frío, blanco o azulado, o pierde de repente la sensibilidad o el movimiento del dedo después de una lesión, acuda ese mismo día. Si los síntomas no mejoran, empeoran a lo largo de las semanas o le impiden trabajar o usar la mano, consulte a su médico de cabecera o pida una valoración por un especialista.
En profundidad
Advanced reading: the deeper science (optional)
Esta sección va más allá de lo necesario para que usted tome decisiones sobre su propio tratamiento. Vale la pena leer más sobre el dedo en maza, ya que las dos situaciones que habitualmente se consideran indicaciones claras para la cirugía —la presencia de un fragmento óseo grande y la persistencia de la flexión anormal del dedo tras el uso de férula— no están tan bien establecidas como se afirma con tanta certeza.
Ambos tratamientos producen buenos resultados, pero nadie sabe dónde está el límite
Una revisión sistemática sobre el tratamiento quirúrgico y no quirúrgico llegó a una conclusión excepcionalmente directa: ambos métodos generan buenos resultados clínicos, y no existen evidencias suficientes para determinar cuándo está indicada la intervención quirúrgica [1].
Esta segunda parte es la más importante. La controversia no radica en si alguno de los tratamientos funciona; el problema es que el umbral para optar por la cirugía —el punto en el que la fractura se considera demasiado extensa o la articulación demasiado subluxada— se basa en convenciones más que en evidencia comparativa.
Cuando un fragmento afecta a más de un tercio de la superficie articular, o cuando la falange distal presenta subluxación, generalmente se indica la cirugía; sin embargo, aún no se ha demostrado claramente ninguna ventaja significativa del tratamiento quirúrgico, incluso en esos casos complejos [2].
El uso de férulas funciona; lo importante es la duración
La evidencia científica sobre el uso de órtesis es más concreta. Dos de cada tres estudios hallaron un gran tamaño del efecto en la intervención con órtesis, que oscila entre 2,17 y 12,12, recomendándose una duración de inmovilización de 6 a 8 semanas, además de otras semanas adicionales si persiste el retraso [3].
Se destacan dos aspectos prácticos. El primero es que la férula debe mantener la punta del dedo recta de forma continua; la posición de la férula basta para mantener las extremidades del tendón juntas, pero unos pocos minutos de flexión durante el lavado reinician el proceso de curación. El segundo es que “las semanas adicionales si persiste el retraso” forman parte del protocolo de tratamiento, no son señal de fracaso terapéutico.
¿Por qué suele ser aceptable una ligera flexión residual?
Después del tratamiento, es frecuente que persista una pequeña limitación para la extensión; esto suele ser compatible con un uso normal de la mano. La articulación distal aporta relativamente poco a la fuerza de agarre, y la mayoría de las personas se adaptan a unos pocos grados de flexión sin notar ninguna alteración funcional.
Esto resulta relevante al valorar la conveniencia de una cirugía cuando el resultado no será perfecto: intervenir en esta articulación no está exento de riesgos; el fragmento óseo es pequeño, la piel es delgada, y la fijación mediante clavos o alambres en una articulación de este tamaño conlleva riesgos de infección, deformidad de las uñas y rigidez articular. Todo ello debe sopesarse frente a la ganancia estética y funcional, que suele ser mínima. Dado que los estudios mencionados no evidencian ventajas de la cirugía, ni siquiera en casos complejos, aceptar una ligera limitación funcional es una decisión acorde con la evidencia científica, en lugar de un simple compromiso.
La deformidad que no es dedo en martillo
El dedo en martillo forma parte de un grupo de lesiones del mecanismo extensor; se distinguen principalmente por el lugar del tendón donde se produce la ruptura: en la punta del dedo en el caso del dedo en martillo, en la articulación media en el caso de la deformidad en botón, y en la banda sagital en la articulación metacarpofalángica [4]. En las primeras fases, cuando la hinchazón dificulta la identificación del patrón clínico, estas lesiones suelen confundirse entre sí; además, cada una requiere una posición específica para la inmovilización mediante férula. Si se coloca una férula para dedo en martillo en una lesión en botón, se inmoviliza la articulación equivocada; por eso es fundamental confirmar el diagnóstico antes de proceder a seis semanas de inmovilización.
Referencias
[1] Lin JS, Samora JB. Manejo quirúrgico y no quirúrgico del dedo en martillo: una revisión sistemática. J Hand Surg Am. 2018;43(2):146-163.e2. https://doi.org/10.1016/j.jhsa.2017.10.004
[2] Lamaris GA, Matthew MK. Diagnóstico y manejo de las lesiones por dedo en martillo. Hand (N Y). 2016;12(3):223-8. https://doi.org/10.1177/1558944716642763
[3] Valdes K, Naughton N, Algar L. Tratamiento conservador del dedo en martillo: una revisión sistemática. J Hand Ther. 2015;28(3):237-46. https://doi.org/10.1016/j.jht.2015.03.001
[4] Lin JD, Strauch RJ. Lesiones cerradas del mecanismo extensor de partes blandas (dedo en martillo, dedo en botón y banda sagital). J Hand Surg Am. 2014;39(5):1005-11. https://doi.org/10.1016/j.jhsa.2013.11.018
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Most mallet finger injuries can be managed non-surgically with splinting [6].
- Surgery is occasionally recommended for acute or chronic mallet finger cases or for salvage of failed prior treatment [6].
- Mallet fingers can be cured or significantly improved in approximately 50% of cases by simple splintage [3, 9].
- After a mallet-finger injury treated within two weeks by either internal or external splintage, few patients have significant persistent disability [8].
- Both surgical and nonsurgical treatments of mallet finger injuries lead to excellent clinical outcomes [7].
- There was insufficient evidence from randomised controlled trials to establish the relative effectiveness of different custom-made or off-the-shelf finger splints used for treating mallet finger injury [15].
- The perforated mallet finger splint can produce consistently good results even in patients who would not tolerate a conventional splint [33, 34].
- Compliant patients have significantly better outcomes than noncompliant patients in the treatment for mallet finger injuries [22].
- Specialist hand therapists could treat mallet finger by themselves, providing that the patients fit the inclusion criteria for non-operative treatment [17].
- The authors propose to treat all cases of mallet finger with a dorsal glued splint except for stage IV mallet finger, which they treat with extra-articular pinning [1].
- Absolute indications for surgical intervention for mallet fingers in the pediatric population remain unclear [2].
- Simple surgery such as Kirschner wire fixation of the DIP joint or tenodermodesis is of benefit in most patients with mallet finger who fail to be cured by simple splintage [11].
- Delayed surgical management of bony mallet fingers demonstrated adequate functional outcome with minimal complications when compared with prior literature [4].
- Complication rates were low, suggesting that large-fragment mallet finger cases can be effectively managed conservatively [5].
- Surgery is generally indicated in the case of mallet fractures involving more than one-third of the articular surface as well as in all patients who develop volar subluxation of the distal phalanx [46].
- A significant advantage of surgical management even in complicated mallet fracture cases has yet to be clearly proven [46].
- The role of surgery for mallet fractures of the thumb remains unclear due to their uncommon nature and favorable radiographic findings [18].
- Primary surgical repair is the preferred treatment for mallet thumb, but conservative treatment should be the first choice if there is no skin wound or the conditions at first consultation are not appropriate for surgery [32].
- Central slip tenotomy is the best choice for mallet finger deformity because of the minimal amount of time required to return to function [14].
- The authors recommend the central slip release as an alternative to reconstruction in certain types of chronic mallet finger deformity [24].
- A safe and simple technique for chronic mallet fingers is proposed if deformity exceeds 30°, for patients untreated after the second month, or when splinting has failed [13].
- Today most authorities splint only the distal joint for mallet finger deformities [10].
Anatomy & Pathophysiology
Anatomy
- The extensor apparatus of the fingers includes the interosseous muscle, extensor digitorum communis tendon, lumbrical muscle, flexor tendon sheath, sagittal bands, transverse metacarpal ligament, interosseous hood, interosseous hood oblique fibers, extensor lateral band, extensor middle band, interosseous middle band, interosseous lateral band, oblique retinacular ligament, central extensor lateral, spiral fibers, transverse retinacular ligament, lateral extensor tendon, triangular lamina, and terminal extensor tendon [27].
- The terminal extensor tendon inserts onto the distal phalanx [27].
- The mallet finger deformity reflects the loss of normal extensor force transmission via the terminal tendon insertion onto the distal phalanx [41].
- The unopposed flexor digitorum profundus pulls the distal joint into flexion in mallet finger deformity [41].
- Displacement of the epiphysis of the distal phalanx can cause the digit to assume a mallet finger posture [27].
- Hyperextension of the phalanx usually affords satisfactory reduction of a displaced epiphysis in mallet finger [27].
Pathophysiology
- Mallet finger involves loss of continuity of the extensor tendon over the distal interphalangeal joint [28].
- Mallet finger results in a flexion deformity of the distal finger joint [28].
- Mallet finger may lead to an imbalance between flexion and extension forces more proximally in the digit [28].
- The mallet finger deformity is characterized by a loss of active distal interphalangeal joint extension with full passive range of motion evident [41].
- The usual mechanism of injury involves sudden passive flexion of the actively extended distal interphalangeal joint [41].
- Disruption of the terminal tendon may be entirely confined to the tendon or may involve an avulsed fracture fragment from the dorsal lip of the distal phalanx proximal articular surface [41].
- Because the avulsed fragment includes the terminal tendon insertion, the clinical appearance of soft tissue and bony mallet fingers is similar [41].
- The distal joint rests in flexion, a posture that cannot be actively changed in mallet finger [41].
- Full passive extension of the distal interphalangeal joint is possible in mallet finger [41].
- Mallet finger is due to a disruption of the extensor mechanism from its insertion at the dorsal base of the distal phalanx [57].
- Closed mallet injuries are usually from a sudden forced flexion of a previously extended distal interphalangeal joint [57].
- Mallet finger most commonly involves a closed rupture of the terminal tendon with or without associated fracture of the distal phalanx [91].
- Snagging the extending finger on a pants cuff, a bedsheet, or other object that suddenly flexes the extending distal interphalangeal joint is a frequent cause of mallet finger [91].
- A forceful hyperextension injury of the distal interphalangeal joint may result in a large fracture of the base of the distal phalanx involving one-third or more of the articular surface [91].
- Elderly patients with osteoarthritis of the distal interphalangeal joint may have mallet deformities that are not related to trauma [91].
- Individuals with hyperlax joints may have multiple pseudomallet swan neck postures that are unrelated to trauma [91].
- Open mallet injuries are uncommon [91].
- The most frequently involved digits in mallet finger are the small, ring, and middle fingers of the dominant hand [91].
- Mallet finger has a male predominance [91].
- Tendinous mallet fingers have been reported to occur from age 11 onward [91].
- In skeletally immature individuals, a transepiphyseal plate fracture may be seen in mallet finger [91].
- There may be a familial predisposition to mallet fingers [91].
- An epidemiologic survey of 24 members of a three-generation family revealed an unusually high incidence of mallet fingers [12].
- Twenty mallet fingers were found in seven family members by clinical examination, suggesting a familial predisposition to develop this deformity [12].
- Multiple mallet fingers occurred in the surveyed family, with a range of two to six per member [12].
- The term "mallet finger" refers to a disruption to the terminal extensor mechanism with a lack of full or active extension through the distal interphalangeal joint [53].
- The term "mallet finger" is a misnomer, as rarely do these digits actually resemble a mallet [53].
- Other descriptions for mallet finger injuries include "baseball finger," "cricket finger," and "drop finger" [53].
- The direction of force on the fingertip that results in a mallet fracture has yet to be determined [115].
- The precise mechanism of injury leading to different sizes of mallet fracture fragments might be difficult to delineate due to multiple variables, including tendon tension at the time of injury and the strain-rate-dependent mechanical properties of the affected bone and soft tissues [115].
- Distal interphalangeal joint subluxation is expected with a mallet fracture fragment involving more than one-half of the joint surface [115].
- The distal interphalangeal joint has a remarkable ability to remodel [115].
Classification
- The Doyle classification system describes four types of mallet finger injuries [119].
- In the Doyle classification, Type IV represents mallet fractures and is further broken into three subtypes according to the size of articular involvement [119].
- The Wehbe and Schneider classification describes DIP joint subluxation and epiphyseal and physeal injuries [119].
- In the Wehbe and Schneider classification, articular injuries are subdivided into type A (less than one-third), type B (between one-third and two-thirds), and type C (larger than two-thirds of the joint) [119].
- The Doyle classification is proposed to be modified to make it more encompassing and less prone to interobserver error [53].
- The modified Mallet classification demonstrated strong to excellent agreement and interrater reliability across face-to-face, live tele-assessment, and video-based conditions [113].
- The modified Mallet classification is suggested to be appropriate for remote medical follow-up [113].
- The interrater reliability of the Kellgren & Lawrence and OARSI classification systems for post-traumatic osteoarthritis in the distal interphalangeal joint after mallet finger fractures is considerably lower than initially assumed [102].
- There is a need for better randomized, prospective studies to separate the various types of mallet injuries and their treatments [31].
Clinical Presentation
- Mallet injuries can be classified into four types based on skin integrity and the presence or absence of bony involvement [28].
- The diagnosis of bony mallet finger is usually straightforward based on the patient’s history, typical findings observed on physical examination (i.e., drop finger deformity and lack of DIPJ extension) and identification of an avulsion fracture on lateral finger radiographs [66].
- Mallet finger is often associated with a dorsal fracture of the base of the terminal phalanx [67].
- In cases of mallet finger with fracture, the avulsed fragment is typically small [67].
- In cases of mallet finger with fracture, there may be hyperextension at the proximal interphalangeal joint [67].
- In some cases of dorsal basal fracture, the fragment is appreciably larger and widely separated but there is no dropping of the fingertip [67].
- In cases with a larger dorsal basal fragment and no dropping of the fingertip, there is no associated hyperextension at the proximal interphalangeal joint [67].
- In cases with a larger dorsal basal fragment and no dropping of the fingertip, there may be volar subluxation of the terminal phalanx [67].
- Bony mallet injuries are typically caused by hyperextension rather than hyperflexion [44].
- Mallet finger injuries are frequent in football [43].
- Mallet deformity accounts for a minority of sporting injuries [36].
- Multiple mallet fingers occurred in the surveyed family, with a range of two to six per individual [12].
Investigations
- A radiograph should be obtained to determine whether a fracture is present [41].
- If a fracture is present, a radiograph should determine whether the dorsal fragment is large and whether the distal phalanx is subluxed palmarward [41].
- The clinical appearance of soft tissue and bony mallet fingers is similar, with the distal joint resting in a flexion posture that cannot be actively changed [41].
- Full passive extension of the distal interphalangeal joint is possible in mallet finger deformities [41].
Treatment
Non-Operative Management
- Splinting of the distal interphalangeal joint for 6 to 8 weeks has yielded good results while minimizing morbidity in the majority of patients [28].
- Non-operative management of mallet fractures, regardless of fracture classification, joint congruence or pre-existing degenerate change in the DIP joint, is safe and yields predictably good outcomes in most patients [30].
- This study supports the rationale for nonsurgical treatment of closed and displaced mallet finger fractures with greater than one-third articular surface involvement [39].
- The author argues that mallet fractures can be treated by nonoperative methods, stating that nonoperative treatment provided good results without the need for manipulation, open or closed, and without the use of pins [99].
- Conservative management of tendinous mallet finger injuries that have been neglected for 2 to 4 weeks can be treated as well as those injuries in patients presenting within the first 2 weeks of injury with low long-term complication rates [38].
- A hand therapist can treat mallet finger injuries of type 1 as effectively as a surgeon, with a method of immobilisation that offers practically no complications regarding skin condition [86].
- A hand therapist can treat type 1 mallet finger injuries as effectively as a surgeon [97].
- The management of uncomplicated mallet fingers by the hand therapy team achieved satisfactory results, indicating that specialist hand therapists could treat mallet finger by themselves, providing that the patients fit the inclusion criteria for non-operative treatment [17].
- Supplemental night splinting does not improve the outcome of mallet finger in terms of extensor lag, disability, or satisfaction with treatment [52].
- There was insufficient evidence from comparisons tested within randomised controlled trials to establish the relative effectiveness of different, either custom-made or off-the-shelf, finger splints used for treating mallet finger injury [15].
- Conservative therapeutic management of acute, closed mallet finger is diverse and varied, with exercises and interventions supplementary to splinting commonly utilised [82].
- Mallet deformity accounts for a minority of sporting injuries, but excellent functional outcome can be achieved with splintage and avoidance of the causative sport while splinted [36].
- Two patients with closed mallet deformities of the thumb were treated conservatively with satisfactory results [19].
- The prevailing opinion of most authors is to treat a closed mallet thumb injury nonsurgically with splinting [111].
- A retrospective study examined the outcomes of acute bony mallet injuries treated with 4 weeks of static immobilization in a splint, followed by graduated mobilization [44].
- The clinical efficacy of the proposed method of elastic taping for the treatment of mallet finger injuries remains to be tested vigorously [76].
- The study recommends a simple splint as an alternative means of treating mallet finger [23].
Operative Management
- Surgery is occasionally recommended for acute or chronic cases or for salvage of failed prior treatment [6].
- It is concluded that simple surgery such as Kirschner wire fixation of the DIP joint or tenodermodesis is of benefit in most patients with mallet finger who fail to be cured by simple splintage [11].
- Although surgery is generally indicated in the case of mallet fractures involving more than one-third of the articular surface as well as in all patients who develop volar subluxation of the distal phalanx, a significant advantage of surgical management even in those complicated cases has yet to be clearly proven [46].
- The indications for surgical treatment of bony mallet injuries include dorsal fracture fragments of more than one-third of the joint surface on the lateral radiograph or volar subluxation of the main remainder of the distal phalanx [109].
- It is a challenging surgery performed in treatment of bony mallet finger [16].
- We propose this safe and simple technique for chronic mallet fingers if deformity exceeds 30°, for patients untreated (after the second month), or when splinting has failed [13].
- The method is a suitable alternative in patients with annoying chronic mallet finger who refuse arthrodesis or further conservative treatment [45].
- The method is simple and very effective for treatment of chronic mallet deformity [50].
- This method seems to be a new reliable alternative in the treatment of chronic mallet finger [55].
- Scar overlapping suture for treating chronic tendinous mallet finger in children is safe and effective [89].
Complications
- The complication rate after operative treatment of mallet fracture was 41% [117].
- The high complication rate after operative treatment of mallet fracture is likely attributable to anatomical factors such as thin extensor tendon and poor blood supply [117].
- Delayed surgical management of bony mallet fingers demonstrated minimal complications when compared with prior literature [4].
- Complication rates were low in large-fragment mallet finger cases managed conservatively [5].
- Conservative management of tendinous mallet finger injuries neglected for 2 to 4 weeks is associated with low long-term complication rates [38].
- A series of acute combined tendon and bone mallet fingers treated with pullout wire fixation and Kirschner wire stabilization reported no complications such as infection, nonunion, or nail deformity [59].
Recovery
Non-Operative Management
- Treatment by splintage produces a cure or improvement in half the patients studied [9].
- Most authorities splint only the distal joint for mallet finger deformities [10].
- The management of uncomplicated mallet fingers by a hand therapy team achieved satisfactory results, indicating that specialist hand therapists could treat mallet finger by themselves provided patients fit inclusion criteria for non-operative treatment [17].
- Conservative management of tendinous mallet finger injuries neglected for 2 to 4 weeks can be treated as well as those presenting within the first 2 weeks of injury with low long-term complication rates [38].
- Nonsurgical treatment is supported for closed and displaced mallet finger fractures with greater than one-third articular surface involvement [39].
- Large-fragment mallet finger cases can be effectively managed conservatively with low complication rates [5].
Operative Management
- The chronic mallet deformity was corrected in each of the 12 cases reported in a series using oblique retinacular ligament reconstruction [25].
- Tenodermodesis is a useful surgical procedure in cases of mallet fingers where conservative treatment has failed [49].
- Mallet finger injuries are frequent in football and difficult to treat during the competitive season, often requiring delayed treatment or internal splinting [43].
Key Evidence
- [L5] The authors propose to treat all cases of mallet finger with a dorsal glued splint except for stage IV mallet finger, which they treat with extra-articular pinning. [1] (10.5999/aps.2016.43.2.134)
- [L4] Absolute indications for surgical intervention for mallet fingers in this population remain unclear. [2] (10.1016/j.jhsa.2018.03.037)
- [L1] Mallet fingers can be cured or significantly improved in approximately 50% of cases by simple splintage. [3] (10.1016/0266-7681(88)90124-6)
- [L4] Delayed surgical management of bony mallet fingers demonstrated adequate functional outcome with minimal complications when compared with prior literature. [4] (10.1177/1558944719840749)
- [L4] Complication rates were low, suggesting that large-fragment mallet finger cases can be effectively managed conservatively. [5] (10.1186/s12891-026-09787-w)
- [L5] Most mallet finger injuries can be managed non-surgically with splinting, although surgery is occasionally recommended for acute or chronic cases or for salvage of failed prior treatment. [6] (10.1007/s11552-014-9609-y)
- [L4] Both surgical and nonsurgical treatments of mallet finger injuries lead to excellent clinical outcomes. [7] (10.1016/j.jhsa.2017.10.004)
- [L1] After a mallet-finger injury treated within two weeks by either method few patients have significant persistent disability. [8] (10.1016/s0072-968x(82)80011-9)
- [L1] Our study shows that treatment by splintage is worthwhile in cases of mallet finger, producing a cure or improvement in half the patients studied. [9] (10.1016/0266-7681_88_90124-6)
- [L5] Today most authorities splint only the distal joint for mallet finger deformities. [10] (10.1016/s0749-0712(21)00059-7)
- [L4] It is concluded that simple surgery such as Kirschner wire fixation of the DIP joint or tenodermodesis is of benefit in most patients with mallet finger who fail to be cured by simple splintage. [11] (10.1016/0266-7681(88)90127-1)
- [L4] [12] (10.1016/s0363-5023(88)80003-0)
- [L4] We propose this safe and simple technique for chronic mallet fingers if deformity exceeds 30°, for patients untreated (after the second month), or when splinting has failed. [13] (10.1016/s1297-3203(02)00008-2)
- [L4] Central slip tenotomy is the best choice for mallet finger deformity because of the minimal amount of time required to return to function. [14] (10.1016/s0363-5023(87)80205-8)
- [L1] There was insufficient evidence from comparisons tested within randomised controlled trials to establish the relative effectiveness of different, either custom-made or off-the-shelf, finger splints used for treating mallet finger injury. [15] (10.1002/14651858.cd004574.pub2)
- [L4] It is a challenging surgery performed in treatment of bony mallet finger. [16] (10.1177/1753193414553139)
- [L3] The management of these uncomplicated mallet fingers by the hand therapy team achieved satisfactory results, indicating that specialist hand therapists could treat mallet finger by themselves, providing that the patients fit the inclusion criteria for non-operative treatment. [17] (10.1016/s0266-7681(03)00220-1)
- [L3] The role of surgery for mallet fractures of the thumb remains unclear due to their uncommon nature and favorable radiographic findings. [18] (10.1177/1558944716672192)
- [L4] Two patients with closed mallet deformities of the thumb were treated conservatively with satisfactory results. [19] (10.1016/s0363-5023(86)80058-2)
- [L4] Compliant patients have significantly better outcomes than noncompliant patients in the treatment for mallet finger injuries. [22] (10.1016/s0894-1130(12)80037-8)
- [L2] The study recommends this splint as an alternative means of treating mallet finger. [23] (10.1136/emj.10.3.244)
- [L4] The authors recommend the central slip release as an alternative to reconstruction in certain types of chronic mallet finger deformity. [24] (10.1016/s0363-5023(78)80042-2)
- [L4] The chronic mallet deformity was corrected in each of the 12 cases reported in this series. [25] (10.1016/s0363-5023(84)80231-2)
- [L5] [28] (10.5435/00124635-200509000-00007)
- [L3] Non-operative management of mallet fractures, regardless of fracture classification, joint congruence or pre-existing degenerate change in the DIP joint, is safe and yields predictably good outcomes in most patients. [30] (10.1177/1753193421992986)
- [L4] Primary surgical repair is the preferred treatment for mallet thumb, but conservative treatment should be the first choice if there is no skin wound or the conditions at first consultation are not appropriate for surgery. [32] (10.1016/s0363-5023(86)80057-0)
- [L1] The perforated mallet finger splint can produce consistently good results even in those patients who would not tolerate a conventional splint. [33] (10.1016/0266-7681(86)90276-7)
- [L1] The perforated mallet finger splint can produce consistently good results even in those patients who would not tolerate a conventional splint. [34] (10.1016/0266-7681_86_90276-7)
- [L4] Mallet deformity accounts for a minority of sporting injuries, but excellent functional outcome can be achieved with splintage and avoidance of the causative sport while splinted. [36] (10.1054/jhsb.2000.0484)
- [L3] Conservative management of tendinous mallet finger injuries that have been neglected for 2 to 4 weeks can be treated as well as those injuries in patients presenting within the first 2 weeks of injury with low long-term complication rates. [38] (10.1016/j.jhsa.2014.06.140)
- [L4] This study supports the rationale for nonsurgical treatment of closed and displaced mallet finger fractures with greater than one-third articular surface involvement. [39] (10.1016/j.jhsa.2005.02.010)
- [L5] Mallet finger injuries are frequent in football and difficult to treat during the competitive season, often requiring delayed treatment or internal splinting. [43] (10.1016/j.hcl.2012.05.043)
- [L4] [44] (10.1177/17531934251382017)
- [L4] The method is a suitable alternative in patients with annoying chronic mallet finger who refuse arthrodesis or further conservative treatment. [45] (10.1016/0266-7681(89)90102-2)
- [L4] Although surgery is generally indicated in the case of mallet fractures involving more than one-third of the articular surface as well as in all patients who develop volar subluxation of the distal phalanx, a significant advantage of surgical management even in those complicated cases has yet to be clearly proven. [46] (10.1177/1558944716642763)
- [L4] Tenodermodesis is a useful surgical procedure in cases of mallet fingers where conservative treatment has failed. [49] (10.1016/s0363-5023(77)80095-6)
- [L5] The method is simple and very effective for treatment of chronic mallet deformity. [50] (10.1097/00130911-200403000-00006)
- [L1] Supplemental night splinting does not improve the outcome of mallet finger in terms of extensor lag, disability, or satisfaction with treatment. [52] (10.1007/s11552-013-9600-z)
- [L4] [53] (10.1016/j.jhsa.2022.10.013)
- [Paper] This method seems to be a new reliable alternative in the treatment of chronic mallet finger. [55] (10.1016/j.injury.2013.01.013)
- [L3] [57] (10.1016/0363-5023(94)90200-3)
- [L4] The study describes a surgical technique for acute combined tendon and bone mallet fingers and reports good to excellent long-term results with no reported complications such as infection, nonunion, or nail deformity in the series. [59] (10.1016/j.jhsa.2014.11.011)
- [L4] [66] (10.1016/j.hansur.2020.08.008)
- [L4] [67] (10.1016/0020-1383(81)90167-4)
- [L4] The clinical efficacy of the proposed method of elastic taping for the treatment of mallet finger injuries remains to be tested vigorously. [76] (10.1016/j.jht.2014.02.005)
- [L4] Conservative therapeutic management of acute, closed mallet finger is diverse and varied, with exercises and interventions supplementary to splinting commonly utilised. [82] (10.1177/1758998316664822)
- [L4] A hand therapist can treat mallet finger injuries of type 1 as effectively as a surgeon, with a method of immobilisation that offers practically no complications regarding skin condition. [86] (10.1177/175899830501000103)
- [L4] Scar overlapping suture for treating chronic tendinous mallet finger in children is safe and effective. [89] (10.1186/s13018-019-1106-0)
- [L4] A hand therapist can treat type 1 mallet finger injuries as effectively as a surgeon. [97] (10.1197/j.jht.2008.04.002)
- [L5] The author argues that mallet fractures can be treated by nonoperative methods, stating that nonoperative treatment provided good results without the need for manipulation, open or closed, and without the use of pins. [99] (10.1016/j.jhsa.2005.01.011)
- [L4] The interrater reliability of the Kellgren & Lawrence and OARSI classification systems for post-traumatic osteoarthritis in the distal interphalangeal joint after mallet finger fractures is considerably lower than initially assumed. [102] (10.1016/j.jhsa.2024.03.012)
- [L3] [109] (10.1177/1753193415581517)
- [L5] [111] (10.1016/j.jhsa.2013.02.001)
- [L3] The modified Mallet classification demonstrated strong to excellent agreement and interrater reliability across face-to-face, live tele-assessment, and video-based conditions, suggesting it is appropriate for remote medical follow-up. [113] (10.1177/17531934231196118)
- [L5] [115] (10.1016/j.jhsa.2008.04.014)
- [L4] The complication rate after operative treatment of mallet fracture was 41%, likely attributable to anatomical factors such as thin extensor tendon and poor blood supply. [117] (10.1054/jhsb.2000.0440)
- [L5] [119] (10.1177/1753193414554772)
References
[1] Review of Acute Traumatic Closed Mallet Finger Injuries in Adults. Archives of Plastic Surgery. 2016. DOI: 10.5999/aps.2016.43.2.134
[2] Outcomes of Splinting in Pediatric Mallet Finger. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2018.03.037
[3] Mallet finger: A trial of two splints. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90124-6
[4] Delayed Extension Block Pinning in 27 Patients With Mallet Fracture. HAND. 2019. DOI: 10.1177/1558944719840749
[5] Surgical versus conservative management of Doyle type 4c mallet finger: a comparative study. BMC Musculoskeletal Disorders. 2026. DOI: 10.1186/s12891-026-09787-w
[6] Current Concepts: Mallet Finger. HAND. 2014. DOI: 10.1007/s11552-014-9609-y
[7] Surgical and Nonsurgical Management of Mallet Finger: A Systematic Review. The Journal of Hand Surgery. 2018. DOI: 10.1016/j.jhsa.2017.10.004
[8] Mallet-Finger Injuries: A Prospective, Controlled Trial of Internal and External Splintage.. Hand. 1982. DOI: 10.1016/s0072-968x(82)80011-9
[9] Mallet Finger: A Trial of Two Splints. Journal of Hand Surgery. 1988. DOI: 10.1016/0266-7681_88_90124-6
[10] EXTENSOR TENDON INJURIES AT THE DISTAL INTERPHALANGEAL JOINT. Hand Clinics. 1995. DOI: 10.1016/s0749-0712(21)00059-7
[11] Mallet finger : Comparison between operative and conservative management in those cases failing to be cured by splintage. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90127-1
[12] Epidemiologie study of the mallet finger deformity. The Journal of Hand Surgery. 1988. DOI: 10.1016/s0363-5023(88)80003-0
[13] Traitement chirurgical du doigt en maillet invétéré par accourcissement–suture du cal tendineux. À propos de 66 cas. Chirurgie de la Main. 2003. DOI: 10.1016/s1297-3203(02)00008-2
[14] Central slip tenotomy for chronic mallet finger deformity. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80205-8
[15] Interventions for treating mallet finger injuries. Cochrane Database of Systematic Reviews. 2004. DOI: 10.1002/14651858.cd004574.pub2
[16] The treatment of bony mallet fingers using a triple K-wire fixation technique. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193414553139
[17] A Model for the Conservative Management of Mallet Finger. Journal of Hand Surgery. 2004. DOI: 10.1016/s0266-7681(03)00220-1
[18] Mallet Fractures of the Thumb Compared With Mallet Fractures of the Fingers. HAND. 2016. DOI: 10.1177/1558944716672192
[19] Conservative treatment of two cases of mallet thumb. The Journal of Hand Surgery. 1986. DOI: 10.1016/s0363-5023(86)80058-2
[22] The Impact of Cormpliance on the Rehabilitation of Patients with Mallet Finger Injuries. Journal of Hand Therapy. 1994. DOI: 10.1016/s0894-1130(12)80037-8
[23] The conservative treatment of mallet finger with a simple splint: a case report.. Emergency Medicine Journal. 1993. DOI: 10.1136/emj.10.3.244
[24] Chronic mallet finger: The use of Fowler's central slip release. The Journal of Hand Surgery. 1978. DOI: 10.1016/s0363-5023(78)80042-2
[25] Oblique retinacular ligament reconstruction for chronic mallet finger deformity. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80231-2
[27] Campbell S Operative Orthopaedics 4 Volume Set. RECONSTRUCTION OF FINGER FLEXORS: SINGLE-STAGE TENDON GRAFT > CHRONIC MALLET FINGER (SECONDARY REPAIR).
[28] Mallet Finger. Journal of the American Academy of Orthopaedic Surgeons. 2005. DOI: 10.5435/00124635-200509000-00007
[30] The non-operative management of bony mallet injuries. Journal of Hand Surgery (European Volume). 2021. DOI: 10.1177/1753193421992986
[31] In_Reply_S0363502310000766. n.d..
[32] Conservative treatment for a ruptured extensor tendon on the dorsum of the proximal phalanges of the thumb (mallet thumb). The Journal of Hand Surgery. 1986. DOI: 10.1016/s0363-5023(86)80057-0
[33] A comparative controlled trial of a new perforated splint and a traditional splint in the treatment of mallet finger. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1986. DOI: 10.1016/0266-7681(86)90276-7
[34] A Comparative Controlled Trial of a New Perforated Splint and a Traditional Splint in the Treatment of Mallet Finger. Journal of Hand Surgery. 1986. DOI: 10.1016/0266-7681_86_90276-7
[36] Mallet Deformity in Sport. Journal of Hand Surgery. 2001. DOI: 10.1054/jhsb.2000.0484
[38] Soft-Tissue Mallet Injuries: A Comparison of Early and Delayed Treatment. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2014.06.140
[39] Nonsurgical Treatment of Closed Mallet Finger Fractures. The Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsa.2005.02.010
[41] A Lange Medical Book Current Diagnosis Treatment In Orthopedics Fifth Edition. 9Hand Surgery > 3. Mallet Finger.
[43] Tendon Ruptures: Mallet, FDP in Football. Hand Clinics. 2012. DOI: 10.1016/j.hcl.2012.05.043
[44] Four-week splint with early mobilization protocol for the management of bony mallet injuries. Journal of Hand Surgery (European Volume). 2025. DOI: 10.1177/17531934251382017
[45] Abbrevatio: A new operation for chronic mallet finger. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1989. DOI: 10.1016/0266-7681(89)90102-2
[46] The Diagnosis and Management of Mallet Finger Injuries. HAND. 2016. DOI: 10.1177/1558944716642763
[49] A simplified technique for treating mallet fingers: Tenodermodesis. The Journal of Hand Surgery. 1977. DOI: 10.1016/s0363-5023(77)80095-6
[50] The Brooks and Graner Procedure for Treatment of Chronic Tendinous Mallet Finger Deformity. Techniques in Hand and Upper Extremity Surgery. 2004. DOI: 10.1097/00130911-200403000-00006
[52] A Prospective Randomized Controlled Trial Comparing Night Splinting with No Splinting after Treatment of Mallet Finger. HAND. 2014. DOI: 10.1007/s11552-013-9600-z
[53] Acute Mallet Finger Injuries—A Review. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2022.10.013
[55] A new surgical treatment for mallet finger deformity: Deepithelialised pedicled skin flap technique. Injury. 2013. DOI: 10.1016/j.injury.2013.01.013
[57] Mallet finger: Results of early versus delayed closed treatment. The Journal of Hand Surgery. 1994. DOI: 10.1016/0363-5023(94)90200-3
[59] Pullout Wire Fixation Together With Distal Interphalangeal Joint Kirschner Wire Stabilization for Acute Combined Tendon and Bone (Double Level) Mallet Finger Injury. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.11.011
[66] Reliability of subluxation and articular involvement measurements during the assessment of bony mallet finger. Hand Surgery and Rehabilitation. 2021. DOI: 10.1016/j.hansur.2020.08.008
[67] Mallet finger and fractures. Injury. 1981. DOI: 10.1016/0020-1383(81)90167-4
[76] A novel way of treating mallet finger injuries. Journal of Hand Therapy. 2014. DOI: 10.1016/j.jht.2014.02.005
[82] How do hand therapists conservatively manage acute, closed mallet finger? A survey of members of the British Association of Hand Therapists. Hand Therapy. 2016. DOI: 10.1177/1758998316664822
[86] Hand Therapist-led Management of Mallet Finger. The British Journal of Hand Therapy. 2005. DOI: 10.1177/175899830501000103
[89] Scar overlapping suture for treating chronic tendinous mallet finger in children. Journal of Orthopaedic Surgery and Research. 2019. DOI: 10.1186/s13018-019-1106-0
[91] Green S Operative Hand Surgery. CASE STUDY 5.2 Unusual Mallet Finger Presentation.
[97] Hand Therapist-led Management of Mallet Finger. Journal of Hand Therapy. 2008. DOI: 10.1197/j.jht.2008.04.002
[99] A Simple Fixation Method for Unstable Bony Mallet Finger. The Journal of Hand Surgery. 2005. DOI: 10.1016/j.jhsa.2005.01.011
[102] Rater Agreement of Post-Traumatic Osteoarthritis of the Distal Interphalangeal Joint 12 Years After a Mallet Finger Fracture. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2024.03.012
[109] Clinical comparison of hook plate fixation versus extension block pinning for bony mallet finger: a retrospective comparison study. Journal of Hand Surgery (European Volume). 2015. DOI: 10.1177/1753193415581517
[111] Mallet Thumb. The Journal of Hand Surgery. 2013. DOI: 10.1016/j.jhsa.2013.02.001
[113] Interrater reliability of face-to-face, tele- and video-based assessments with the modified Mallet classification in brachial plexus birth injuries. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231196118
[115] A Biomechanical Study of Distal Interphalangeal Joint Subluxation After Mallet Fracture Injury. The Journal of Hand Surgery. 2008. DOI: 10.1016/j.jhsa.2008.04.014
[117] Complications of Operative Treatment for Mallet Fractures of the Distal Phalanx. Journal of Hand Surgery. 2001. DOI: 10.1054/jhsb.2000.0440
[119] Mallet fingers with bone avulsion and DIP joint subluxation. Journal of Hand Surgery (European Volume). 2014. DOI: 10.1177/1753193414554772