Patients › General-Health
Ortesis, férulas y soportes
When braces, splints and supports help upper-limb conditions, the main types, how to use them, and what the evidence shows for sprains, tendon problems, arthritis and after surgery.
¿Qué es?
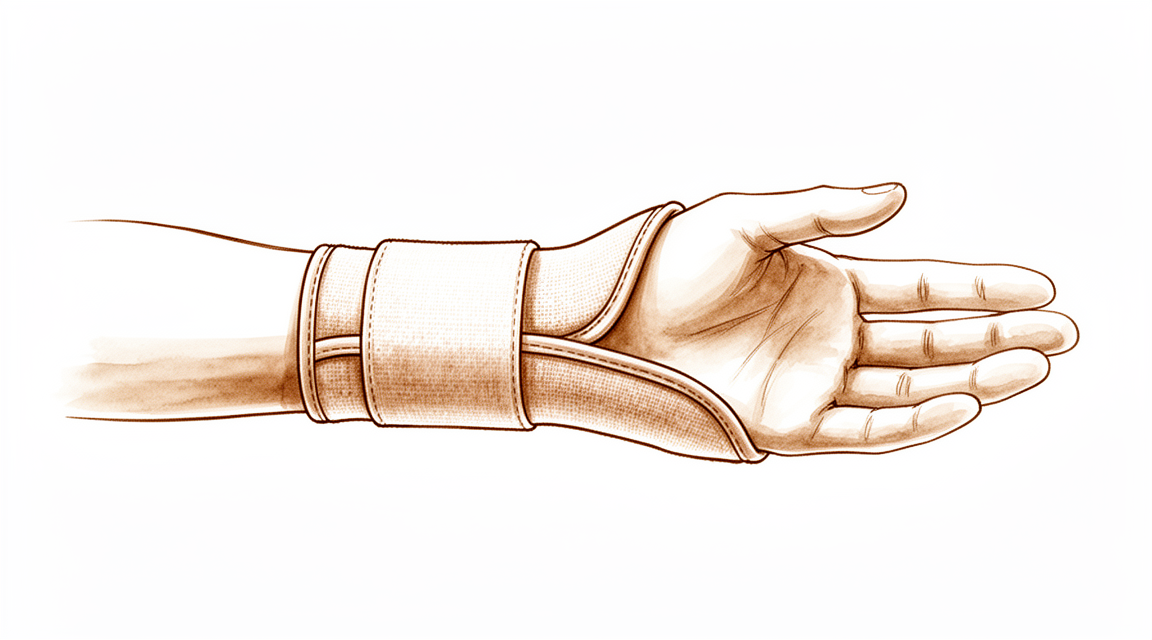
Una ortesis, una férula o un soporte es un dispositivo que mantiene quieta una parte de su cuerpo o guía cómo se mueve. Las férulas suelen ser rígidas y mantienen una articulación en una sola posición. Las ortesis y los soportes a menudo permiten cierto movimiento mientras protegen la zona. Se utilizan para problemas de la mano, la muñeca, el codo y el hombro, y a veces para lesiones de la rodilla como una rotura del LCA, en la que un programa con ortesis es una opción en lugar de la cirugía [1].
Las férulas funcionan manteniendo las articulaciones y los tejidos blandos en una posición estable. Las férulas de yeso lo hacen de forma suave y precisa, lo que ayuda a ir remodelando el tejido rígido con el tiempo [2]. En la fase inicial de una lesión, una ortesis puede sostener los tejidos inflamados sin impedir todo el movimiento, lo que favorece la curación [3]. Algunas férulas son dinámicas, es decir, unos muelles o unas gomas tiran de una articulación hacia un movimiento que usted está trabajando. Otras son estáticas y simplemente la mantienen quieta. Cada diseño tiene sus ventajas y sus inconvenientes [4].
Es posible que le ofrezcan una férula después de una lesión, después de una cirugía, o por rigidez y problemas nerviosos. En algunas afecciones, como los problemas de la mano y de la extremidad superior, el uso de férulas se acepta como práctica habitual en la rehabilitación [5]. Una férula puede llevarse durante el día, por la noche o en ambos momentos. Algunos diseños son sencillos y casi no necesitan mantenimiento [6]. Muchas pueden fabricarse con materiales de bajo coste [7].
Las férulas no siempre son la solución. En un estudio sobre fracturas de la mano, menos personas mantuvieron el tratamiento con una ortesis que con un yeso, y más personas del grupo de la ortesis tuvieron complicaciones [8]. Su médico valorará si una férula, un yeso o la cirugía es lo más adecuado para su lesión.
¿Funciona?
La respuesta sincera es que depende de para qué se utilice la férula. En algunas afecciones hay pruebas sólidas. En otras, todavía hay muy poca investigación de calidad, y su médico se basará en la experiencia y en la práctica habitual.
Algunos resultados son claros. Las personas con artrosis en la base del pulgar que se sintieron mejor con una férula al principio tuvieron una mejoría de entre el 54 % y el 61 % en sus síntomas seis meses después [9]. En las fracturas de los huesos de la mano, una ortesis funcional que permite cierto movimiento mantuvo los huesos más rectos que una férula convencional [10]. Las personas con un tendón roto en el dorso del dedo que usaron un tipo de férula dinámica evolucionaron mejor que las tratadas con otros métodos [11]. Y las personas con una lesión de un tendón en el dorso de la mano volvieron a sus actividades completas ocho semanas antes con una férula que permite el movimiento que con una que lo mantenía quieto [12].
Otros resultados son más dispares. Las férulas para el dedo en gatillo pueden funcionar, y son adecuadas para personas que prefieren no recibir una inyección de cortisona [13]. Pero un estudio sobre ejercicios de los dedos con una férula no pudo demostrar que fueran mejores que otros tratamientos no quirúrgicos [14]. En la contractura de Dupuytren, las férulas y las pautas de uso varían tanto de una clínica a otra que es difícil saber qué funciona mejor [15]. Tampoco se sabe si llevar una férula durante meses después de la cirugía de Dupuytren mantiene el dedo más recto a largo plazo [16, 17].
Hay lagunas reales. En algunas reparaciones de tendones no hay ensayos de calidad que comparen los métodos de ferulización, así que el mejor enfoque no está definido [18]. Algunas férulas también pueden fallar. En un estudio, unas pocas personas con una fractura grave de una articulación del dedo necesitaron cirugía porque su férula no mantuvo la articulación en su sitio [19].
Su médico le explicará lo que dicen las pruebas sobre su afección concreta, y lo que no dicen.
¿Cuáles son los riesgos?
La mayoría de los problemas con las ortesis y las férulas son locales, es decir, afectan a la piel y a los tejidos que quedan debajo del dispositivo. Una férula que roza o aprieta demasiado puede causar molestias, y algunos diseños son sencillamente más cómodos que otros. Se observó que un nuevo tipo de férula para el dedo era mucho más cómodo que un yeso, aunque a las personas que lo llevaban les seguía resultando molesto [20]. Si una férula le resulta incómoda, dígaselo a su fisioterapeuta o a su médico, porque pequeños cambios en el ajuste suelen ayudar.
Las férulas también pueden no cumplir su función. En un estudio, tres personas con una fractura grave de una articulación del dedo acabaron necesitando cirugía porque su férula no mantuvo los huesos rotos en su sitio, y sus resultados fueron peores por ello [19]. Por eso se le pedirá que vuelva a las revisiones, para que el equipo pueda confirmar que la férula sigue manteniendo todo donde debe estar.
Mantener el plan también es importante. En un estudio sobre fracturas de la mano, solo el 41 % de las personas a las que se les dio una ortesis completaron el tratamiento, frente al 81 % de las que llevaban un yeso, y las complicaciones explicaron el 60 % de los abandonos en el grupo de la ortesis [8]. Los niños pueden quitarse las férulas, y una clínica observó que un diseño modificado de férula para el pulgar ayudaba a evitarlo [21].
También hay lagunas reconocidas en lo que se sabe. En algunas reparaciones de tendones no hay ensayos de calidad que comparen los métodos de ferulización, así que los riesgos de cada enfoque no están del todo definidos [18]. En la contractura de Dupuytren, no se sabe si llevar una férula durante meses después de la cirugía mantiene el dedo más recto, ni si provoca alguna pérdida de la capacidad de doblarlo [16, 17]. Su médico le explicará cuáles de estos riesgos se aplican a su lesión y qué señales de alarma debe vigilar.
¿Es adecuado para usted?
Una férula o una ortesis puede ser adecuada para usted si su problema es de los que responden a un soporte estable en lugar de a una operación. Eso incluye algunas lesiones de la mano y la muñeca, la rigidez de una articulación de un dedo, la artrosis en la base del pulgar y algunos problemas nerviosos. El uso de férulas se acepta como práctica habitual en muchas afecciones de la mano y de la extremidad superior [5]. Algunas personas también eligen una férula para retrasar o evitar la cirugía. En la artrosis del pulgar, una férula pequeña que sujeta el pulgar y deja libres para moverse las articulaciones cercanas es una opción para las personas que deciden no operarse [22].
Una férula no es adecuada para todas las lesiones ni para todas las personas. Algunos diseños mantienen una articulación en una posición que no convendría a su lesión. Por ejemplo, una férula dinámica para el dedo no debe usarse cuando una articulación cercana necesita mantenerse completamente recta [23]. Algunas férulas tampoco consiguen mantener los huesos rotos en su sitio, y unas pocas personas de un estudio acabaron necesitando cirugía por este motivo [19]. Su médico comparará una férula con un yeso o con la cirugía en función de su lesión, su trabajo y la probabilidad de que usted siga la pauta de uso.
La comodidad y el ajuste importan más de lo que podría pensar. Una férula que le resulta fácil de llevar es una férula que realmente seguirá llevando, y los diseños que le permiten usar la mano favorecen un mejor cumplimiento [24]. Si una férula no le sienta bien, dígalo. Pequeños cambios suelen resolver el problema.
Esta debe ser una decisión compartida con su médico. La sección de riesgos anterior explica lo que puede salir mal, y su médico le explicará cuáles de esos riesgos se aplican a su caso.
Conclusión
Vale la pena considerar una ortesis o una férula para muchos problemas de la mano, la muñeca y el codo, sobre todo si quiere evitar o aplazar la cirugía. Algunos diseños son sencillos, cómodos y le permiten seguir usando las articulaciones cercanas [22, 25]. Las pruebas son más sólidas en unas afecciones que en otras, así que pregunte qué se sabe sobre la suya. Lo más importante de todo es el ajuste y la constancia: una férula que le sienta bien es una férula que realmente llevará, y llevarla según las indicaciones es lo que da resultados.
Referencias
[1] Short-term Outcomes of the Cross Brace Protocol for ACL Rupture Management: A Prospective Cohort Study. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/2325967126s00013
[2] Plaster of Paris: The forgotten hand splinting material. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.015014
[3] REHABILITATION CONCEPTS AND SUPPORTIVE DEVICES FOR OVERUSE INJURIES OF THE UPPER EXTREMITIES. Clinics in Sports Medicine. 2001. DOI: 10.1016/s0278-5919(05)70273-8
[4] Force analysis of the belly gutter and capener splints. Journal of Hand Therapy. 1999. DOI: 10.1016/s0894-1130(99)80074-x
[5] The influence of splinting on healing tissues. Journal of Hand Therapy. 1998. DOI: 10.1016/s0894-1130(98)80014-8
[6] A modification of the kleinert splint for mobilisation of digital flexor tendons. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90007-6
[7] Examples of simply fabricated, custom-made splints for the hand. The Journal of Hand Surgery. 1981. DOI: 10.1016/s0363-5023(81)80008-1
[8] Functional Fracture Bracing in Metacarpal Fractures: The Galveston Metacarpal Brace versus a Plaster-of-Paris Bandage in a Prospective Study. Journal of Hand Therapy. 1993. DOI: 10.1016/s0894-1130(12)80327-9
[9] Splinting in the treatment of arthritis of the first carpometacarpal joint. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.jhsu24a0086
[10] Functional bracing of fractures of the second through fifth metacarpals. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80179-x
[11] The pipflex splint for treatment of mallet finger. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90126-x
[12] Results of acute zone III extensor tendon injuries treated with dynamic extension splinting. The Journal of Hand Surgery. 1991. DOI: 10.1016/s0363-5023(10)80082-6
[13] Trigger fingers and thumb: When to splint, inject, or operate. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90124-8
[14] Effectiveness of Proximal Interphalangeal Joint Orthosis and Therapeutic Exercise in the Management of Trigger Finger: A Prospective Case Series. Journal of Hand Surgery Global Online. 2026. DOI: 10.1016/j.jhsg.2026.101038
[15] A Review of Attitudes to Splintage in Dupuytren's Contracture. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90208-j
[16] A review of attitudes to splintage in Dupuytren's contracture. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90182-3
[17] A Review of Attitudes to Splintage in Dupuytren’s Contracture. Journal of Hand Surgery. 1987. DOI: 10.1016/0266-7681_87_90182-3
[18] Splints, with or without wrist immobilization, following surgical repair of flexor tendon lesions of the hand: A systematic review. Hand Surgery and Rehabilitation. 2019. DOI: 10.1016/j.hansur.2019.05.004
[19] Dorsal Fracture Subluxation of the Proximal Interphalangeal Joints Treated by Extension Block Splintage. Journal of Hand Surgery. 1992. DOI: 10.1016/s0266-7681(05)80249-9
[20] A new method of extension-block splinting for the proximal interphalangeal joint—Preliminary report. The Journal of Hand Surgery. 1980. DOI: 10.1016/s0363-5023(80)80118-3
[21] Modification to a pediatric thumb splint. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2004.04.014
[22] The biomechanics of a thumb carpometacarpal immobilization splint: Design and fitting. Journal of Hand Therapy. 2000. DOI: 10.1016/s0894-1130(00)80006-x
[23] Dynamic flexion splint for the distal interphalangeal joint. Journal of Hand Therapy. 2003. DOI: 10.1016/s0894-1130(03)00041-3
[24] Low Profile Extension Splint for Active Extensor Lag of the Proximal Interphalangeal Joint. Journal of Hand Therapy. 2007. DOI: 10.1197/j.jht.2007.04.008
[25] Design of an orthosis with straight spring for extension mobilization of flexion contracture of the proximal interphalangeal joint. Journal of Hand Therapy. 2021. DOI: 10.1016/j.jht.2020.01.005
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
- Splint design plays a more significant role in dynamic extensor splinting than previously expected [1].
- The Swing Design Dynamic Traction Splint offers similar benefits to previously reported splints and is simple and compact in design [2].
- Topics selected for a special issue on splinting are intended to advance the artistry of splinting toward an evidence-based practice approach [3].
- The application of splints for treating hand and upper extremity problems is accepted as definitive standard practice in this rehabilitation arena [4].
- The clamshell splint with otoform lining has proven equally effective for other conditions requiring immobilization [5].
- In a single-subject experiment on radial nerve palsy, only splint 3 met the criteria of improving function and being worn by the patient [6].
- To the authors' knowledge, the optimal orthosis for the complete median and radial nerve-injured war casualty has not been previously described [7].
- The conclusion that sling immobilization is 'not inferior' to brace immobilization after arthroscopic rotator cuff repair cannot be attributed solely to the type of immobilization [8].
- A modification of the Kleinert splint for mobilisation of digital flexor tendons is easy to make and requires virtually no maintenance due to its simplicity [9].
- Many splints can be constructed with material that is inexpensive, available, and often discarded [10].
- The modified Kleinert splint appears to be producing improved results and to be gaining more widespread acceptance [11].
- The patient for whom the adjustable first webspace splint was initially developed has recovered a very satisfying webspace thanks to the splint [12].
- The types of splint and programmes for using them in Dupuytren's contracture varied widely [19].
- Force analysis of the belly gutter and capener splints clearly indicates theoretical advantages and disadvantages of the dynamic and static splint designs [22].
- In a prospective study of metacarpal fractures, only 41% of patients from the metacarpal-brace group completed the treatment, compared to 81% in the plaster-cast group [24].
- In a prospective study of metacarpal fractures, 60% of exclusions in the brace group were due to complications [24].
- Dynamic flexion splinting for the distal interphalangeal joint is contraindicated in situations that require the PIP to be held in full extension [33].
- The concept of a straight spring for an orthosis for extension mobilization of flexion contracture of the proximal interphalangeal joint was effective for tissue deformation, easy to make and finish, cost-effective, low profile, and easy to handle by the patient [34].
- The only drawback to Plaster of Paris splints was that if changes were needed, a whole new splint had to be fabricated [39].
- To date, selection of the proper splint for managing joint stiffness has been empirical [41].
- A volar splint has clear limitations regarding immobilization, which is of relevance in clinical practice [63].
- An ulnar boost splint for midcarpal instability follows recommendations to support the pisotriquetral area [64].
How It Works
- The application of splints for treating hand and upper extremity problems is accepted as definitive standard practice in rehabilitation [4].
- The optimal orthosis for the complete median and radial nerve-injured war casualty has not been previously described to the authors' knowledge [7].
- The modified Kleinert splint for mobilisation of digital flexor tendons is easy to make and requires virtually no maintenance due to its simplicity [9].
- Many hand splints can be constructed with material that is inexpensive, available, and often discarded [10].
- The modified Kleinert splint appears to be producing improved results and is gaining more widespread acceptance [11].
- The adjustable first webspace splint allowed the patient for whom it was initially developed to recover a very satisfying webspace [12].
- Therapeutic hand splint texts focus on mechanics, physics, and biological considerations rather than providing specific splint patterns or fabrication instructions [13].
- A silicone splint has value as both a protective splint following injury and prophylactically for diving injuries of the thumb [14].
- Limited results from an underpowered study suggest splinting may not be required postoperatively for isolated digital nerve injuries in the hand [15].
- Studies involving smaller numbers of subjects can contribute greatly to substantiating the effectiveness of splinting if performed with the highest level of study design and use standardized outcome measures [16].
- James traction splinting interventions for PIP fractures have been highlighted in two case studies at military treatment facilities [17].
- Three patients with dorsal fracture subluxation of the proximal interphalangeal joints initially managed with splintage proceeded to surgery because the splint failed to hold the joint in reduction, and these patients had a less favourable outcome [18].
- A static gutter splint may be worn at night to maintain gains achieved in the day for distal interphalangeal joint flexion contractures [20].
- Braces during the early phase of overuse injuries of the upper extremities provide support to inflamed tissues without complete immobilization, facilitating healing [21].
- Force analysis clearly indicates theoretical advantages and disadvantages of dynamic and static splint designs for belly gutter and capener splints [22].
- Low-profile dynamic splints assist therapists in the prescription of splints for certain patients and enable them to monitor progress closely [23].
- Only 41% of patients from the metacarpal-brace group completed treatment compared to 81% in the plaster-cast group, with 60% of exclusions in the brace group due to complications [24].
- A newly developed buddy splint corrects the mechanical and kinesiologic disadvantages of current buddy strapping systems [25].
- The sustained positioning of joints and soft tissue with plaster of Paris provides a gentler and more precise means of tissue remodeling than dynamic or static progressive splinting [26].
- The objective of providing reduction and stability to the thumb metacarpophalangeal joint and improving function was achieved with a three-point static splint for chronic volar subluxation [27].
- The objective of providing reduction and stability to the MP joint and improving function was achieved with the Ambulatory Arm Elevator Sling (Hands Up) [28].
- It is necessary to determine whether patients treated with static splintage for several months after operation for Dupuytren's contracture achieve better extension at 12 to 18 months and if there is any loss of flexion in this group [30, 31].
- The modified Kleinert controlled mobilization splint has theoretical advantages over the usual Kleinert splint and may be of clinical use [42].
- Creation of splint designs should be based on mechanical fact rather than on mode-of-the-day bias [43].
- A better position for splintage of mallet finger deformities is slight flexion, as hyperextension provided by a splint is likely to cause the subluxation to appear [44].
- Surgery and the postoperative regimen of rigid night splints and web-retaining gloves for day wear has allowed arrest or minimal progression of contractures in compliant patients with recessive dystrophic epidermolysis bullosa in short-term follow-up of an average of 17 months [46].
- The Cross Brace Protocol provides an additional non-operative option for ACL injuries and may be associated with satisfactory anatomical and functional healing for certain patient groups [47].
What the Evidence Shows
General Principles and Materials
- Splint design plays a more significant role than previously expected [1].
- Woodcast splints are used in clinical practice with good results and high patient acceptability [38].
- The sustained positioning of joints and soft tissue with plaster of Paris provides a gentler and more precise means of tissue remodeling than does dynamic or static progressive splinting [26].
- Studies involving smaller numbers of subjects can contribute greatly to the evidence base so long as they are performed with the highest level of study design and use standardized outcome measures that are valid for answering the designated research questions [16].
- The lack of high-quality evidence means that randomized clinical trials need to be performed to guide rehabilitation choices for splints with or without wrist immobilization following surgical repair of flexor tendon lesions [65].
Fractures and Dislocations
- Functional bracing of fractures of the second through fifth metacarpals resulted in a final angulation averaging 15° in the brace group compared to 31° in the splint group [49].
- The objective of providing reduction and stability to the MP joint and improving function was achieved with an ambulatory arm elevator sling [28].
Tendon Injuries
- A new dynamic splint for postoperative treatment of flexor tendon injury produced results that were significantly better than after treatment in the traditional splint [52].
- Patients with acute zone III extensor tendon injuries treated with dynamic extension splinting returned to full activities with good-to-excellent results 8 weeks earlier instead of at 16 to 18 weeks compared to static splinting [60].
- A modification of the Kleinert splint for mobilisation of digital flexor tendons is easy to make and requires virtually no maintenance [9].
Nerve Injuries and Palsy
- In a single-subject experiment on splinting for radial nerve palsy, only splint 3 met the criteria of improving function and being worn by the patient [6].
- Although an underpowered study on postoperative splinting for isolated digital nerve injuries in the hand suggests splinting may not be required postoperatively, these limited results are based on a small sample [15].
Contractures and Stiffness
- The functional arc of motion or very close to it was achieved using patient-adjusted static elbow splints after failure of conservative treatment for elbow contractures [62].
- In Dupuytren's contracture, the types of splint and programmes for using them varied widely [19].
- It is necessary to determine whether patients treated with static splintage for several months after Dupuytren's contracture operation achieve better extension at 12 to 18 months and if there is any loss of flexion in this group [30, 31].
Trigger Finger
- Splinting offers an alternative for patients who have a strong objection to cortisone injection for trigger fingers and thumb [37].
- A low-profile ring splint for trigger finger is easily fabricated and functional, and the treatment protocol requires minimal therapy visits [58].
- A prospective case series on proximal interphalangeal joint orthosis and therapeutic exercise for trigger finger demonstrates feasibility and short-term clinical improvement but cannot establish superiority over other conservative treatments due to the absence of a control group [50].
Arthritis and Overuse
- All patients with arthritis of the first carpometacarpal joint who had initial improvement in their symptoms with splinting had between 54% and 61% average improvement in symptom severity 6 months after splinting [55].
Specific Splint Designs and Applications
- The Swing Design Dynamic Traction Splint for intra-articular fractures of the digits offers similar benefits to splints reported previously in the literature and is simple and compact in design [2].
- An adjustable first webspace splint was developed for a patient who recovered a very satisfying webspace thanks to the splint [12].
- A supination splint worn distal to the elbow is clinically effective in increasing supination passive range of motion [53].
- The results of treatment with the pipflex splint for mallet finger in 25 patients are superior to those resulting from other methods of splintage [61].
- The significantly superior results of the double-T splint for maintaining the safe position in a palmar splint are worth the additional 50 g weight [59].
- A modification to a pediatric thumb splint has aided in preventing children in the clinic from removing their splints [35].
- A new power source in dynamic splinting with lower force-extension ratios has helped to improve range of motion within the splint, although further controlled trials are needed to confirm this [40].
- Relative motion orthoses may improve outcomes in a variety of hand conditions, however, high-quality studies that contribute to the evidence base for its use are needed [29].
Practical Considerations
Design and Biomechanics
- The text focuses on mechanics, physics, and biological considerations rather than providing specific splint patterns or fabrication instructions [13].
- A straight spring concept for an orthosis was effective for tissue deformation, easy to make and finish, cost-effective, low profile, and easy to handle by the patient [34].
- Lower force-extension ratios in dynamic splinting have helped to improve range of motion within the splint, although further controlled trials are needed to confirm this [40].
- Low-profile dynamic splints assist therapists in the prescription of splints for certain patients and enable them to monitor their progress closely [23].
Materials and Fabrication
- The Reston foam splint is a very comfortable, safe, versatile, and simple splint that is much cheaper and more readily available than conventional manufactured splints [56].
- Further studies are suggested for comparing time and cost effectiveness between commercially available splinting materials [32].
- A modified Kleinert splint is easy to make and, because of its simplicity, requires virtually no maintenance [9].
- A static progressive wrist extension splint is easy to fabricate, cost-effective, and relatively comfortable [48].
Clinical Application and Outcomes
- Only splint 3 met the criteria of improving function and being worn by the patient in a single-subject experiment for radial nerve palsy [6].
- A modified Kleinert splint appears to be producing improved results and to be gaining more widespread acceptance [11].
- The patient for whom an adjustable first webspace splint was initially developed has recovered a very satisfying webspace thanks to the splint [12].
- Studies involving smaller numbers of subjects can contribute greatly to substantiating the effectiveness of splinting, so long as they are performed with the highest level of study design and use standardized outcome measures that are valid for answering the designated research questions [16].
- Three patients initially managed with extension block splintage for dorsal fracture subluxation of the proximal interphalangeal joints proceeded to surgery because the splint failed to hold the joint in reduction, and these patients had a less favourable outcome [18].
- A static gutter splint may be worn at night to maintain gains achieved in the day for distal interphalangeal joint flexion contracture [20].
- A dynamic flexion splint for the distal interphalangeal joint is contraindicated in situations that require the proximal interphalangeal joint to be held in full extension [33].
- A splint modification has aided in preventing children in a clinic from removing their pediatric thumb splints [35].
- If patients with minimally displaced distal radial fractures can be treated safely using a removable splint, this will save them time and inconvenience in terms of additional visits to the hospital, and save the healthcare system money [45].
- An alternative flexion splinting protocol requires only the flexion splint as opposed to the traditional extension splint followed by flexion splinting; therefore, the cost of splint fabrication is reduced and the instructions to patients for following their splinting programs are simplified [51].
- A thumb carpometacrotacarpal immobilization splint allows unrestricted use of adjacent joints and is a cost-effective, efficient treatment option for those patients who elect to postpone or exclude surgical reconstruction for thumb CMC joint pain [54].
- Although the authors found an extension-block splint for the proximal interphalangeal joint annoying, it was much more comfortable than an extension-block cast [57].
Key Evidence
- [Paper] This shows that splint design plays a more significant role than previously expected. [1] (10.1016/0363-5023(92)90404-d)
- [L4] It offers similar benefits to splints reported previously in the literature, and is simple and compact in design. [2] (10.1197/j.jht.2005.11.001)
- [L5] The topics selected for inclusion in this special issue are intended to advance the artistry of splinting toward an evidence-based practice approach. [3] (10.1053/hanthe.2002.v15.015009)
- [L5] Currently, the application of splints for treating hand and upper extremity problems is accepted as definitive standard practice in this rehabilitation arena. [4] (10.1016/s0894-1130(98)80014-8)
- [L5] The splint has proven equally effective for other conditions requiring immobilization. [5] (10.1016/s0894-1130(97)80046-4)
- [L5] Only splint 3 met the criteria of improving function and being worn by the patient. [6] (10.1016/s0894-1130(01)80053-3)
- [L5] To the authors' knowledge the optimal orthosis for this situation has not been previously described. [7] (10.1016/s0894-1130(12)80275-4)
- [L5] They argue that the conclusion that sling immobilization is 'not inferior' to brace immobilization cannot be attributed solely to the type of immobilization. [8] (10.1002/arj.70326)
- [L4] The splint is easy to make and, because of its simplicity, requires virtually no maintenance. [9] (10.1016/0266-7681(87)90007-6)
- [L5] The examples given show that many splints can be constructed with material that is inexpensive, available, and often discarded. [10] (10.1016/s0363-5023(81)80008-1)
- [L5] The modified splint appears to be producing improved results and to be gaining more widespread acceptance. [11] (10.1016/s0363-5023(88)80070-4)
- [L5] The patient for whom the splint was initially developed has recovered a very satisfying webspace thanks to the splint. [12] (10.1016/s0894-1130(96)80091-3)
- [Paper] The text focuses on mechanics, physics, and biological considerations rather than providing specific splint patterns or fabrication instructions. [13] (10.1016/s0894-1130(02)70027-6)
- [L5] Our clinical opinion is that it has value as both a protective splint following injury and as well as prophylacticly. [14] (10.1197/j.jht.2006.07.029)
- [L1] Although this study is underpowered, these limited results suggest splinting may not be required postoperatively. [15] (10.1197/j.jht.2007.04.010)
- [Paper] While studies that include large numbers of subjects are needed to substantiate the effectiveness of splinting, studies involving smaller numbers of subjects can contribute greatly as well, so long as they are performed with the highest level of study design and use standardized outcome measures that are valid for answering the designated research questions. [16] (10.1053/hanthe.2002.v15.0150131)
- [L4] The authors present two case studies highlighting James traction splinting interventions and corresponding outcomes at military treatment facilities. [17] (10.1197/j.jht.2007.08.019)
- [L3] Three patients initially managed with splintage proceeded to surgery because the splint failed to hold the joint in reduction, and these patients had a less favourable outcome. [18] (10.1016/s0266-7681(05)80249-9)
- [L5] The types of splint and programmes for using them varied widely. [19] (10.1016/0266-7681(92)90208-j)
- [L5] A static gutter splint may be worn at night to maintain gains achieved in the day. [20] (10.1016/s0894-1130(01)80009-0)
- [L5] Braces during the early phase provide support to inflamed tissues without complete immobilization, facilitating healing. [21] (10.1016/s0278-5919(05)70273-8)
- [L3] It clearly indicates theoretical advantages and disadvantages of the dynamic and static splint designs. [22] (10.1016/s0894-1130(99)80074-x)
- [Paper] This will assist therapists in the prescription of splints for certain patients and enable them to monitor their progress closely. [23] (10.1016/s0894-1130(12)80332-2)
- [L1] Only 41% of the patients from the metacarpal-brace group completed the treatment, compared to 81% in the plaster-cast group, with 60% of exclusions in the brace group due to complications. [24] (10.1016/s0894-1130(12)80327-9)
- [Paper] This newly developed buddy splint corrects the mechanical and kinesiologic disadvantages of current buddy strapping systems. [25] (10.1016/s0894-1130(12)80041-x)
- [L5] The sustained positioning of joints and soft tissue with plaster of Paris provides a gentler and more precise means of tissue remodeling than does dynamic or static progressive splinting. [26] (10.1053/hanthe.2002.v15.015014)
- [L5] The objective of providing reduction and stability to the MP joint and improving function was achieved with this splint. [27] (10.1016/s0894-1130(12)80062-7)
- [Paper] The objective of providing reduction and stability to the MP joint and improving function was achieved with this splint. [28] (10.1016/s0894-1130(12)80064-0)
- [Paper] RM orthoses may improve outcomes in a variety of hand conditions; however, high-quality studies that contribute to the evidence base for its use are needed. [29] (10.1016/j.jht.2016.07.001)
- [L5] In particular, we need to know whether patients treated with static splintage for several months after operation achieve better extension at 12 to 18 months and, if so, is there any loss of flexion in this group? [30] (10.1016/0266-7681(87)90182-3)
- [L5] In particular, we need to know whether patients treated with static splintage for several months after operation achieve better extension at 12 to 18 months and, if so, is there any loss of flexion in this group? [31] (10.1016/0266-7681_87_90182-3)
- [L4] Further studies are suggested for comparing time and cost effectiveness between commercially available splinting materials. [32] (10.1016/s0894-1130(98)80060-4)
- [L5] This splinting tack is contraindicated in situations that require the PIP to be held in full extension. [33] (10.1016/s0894-1130(03)00041-3)
- [Paper] The concept of a straight spring for this orthosis was effective for tissue deformation, easy to make and finish, cost-effective, low profile, and easy to handle by the patient. [34] (10.1016/j.jht.2020.01.005)
- [L5] This splint modification has aided in preventing children in our clinic from removing their splints. [35] (10.1197/j.jht.2004.04.014)
- [L4] Splinting offers an alternative for patients who have a strong objection to cortisone injection. [37] (10.1016/0363-5023(92)90124-8)
- [L5] Woodcast splints are used in clinical practice with good results and high patient acceptability. [38] (10.1097/bth.0000000000000210)
- [Paper] The only drawback to these splints was that if changes were needed, a whole new splint had to be fabricated. [39] (10.1016/s0894-1130(12)80157-8)
- [L4] It is their initial impression that the lower force-extension ratios have helped to improve range of motion within the splint, although further controlled trials are needed to confirm this. [40] (10.1016/s0894-1130(89)80022-5)
- [L5] To date, selection of the proper splint for managing joint stiffness has been empirical. [41] (10.1053/hanthe.2002.v15.015015)
- [L5] The modified splint has theoretical advantages over the usual Kleinert splint and it may be of clinical use—further trials are in progress. [42] (10.1016/s0266-7681(84)80039-x)
- [Paper] Creation of splint designs should be based on mechanical fact rather than on mode-of-the-day bias. [43] (10.1016/s0894-1130(12)80309-7)
- [L5] The author suggests that a better position for splintage is slight flexion, as hyperextension provided by a splint is likely to cause the subluxation to appear. [44] (10.1016/s0363-5023(85)80277-x)
- [L2] If patients can be treated safely using a removable splint, this will save them time and inconvenience in terms of additional visits to the hospital, and save the healthcare system money. [45] (10.1302/0301-620x.107b1.bjj-2024-0634.r1)
- [L4] Surgery and the postoperative regimen of rigid night splints and web-retaining gloves for day wear has allowed arrest or minimal progression of contractures in compliant patients in short-term follow-up study of an average of 17 months. [46] (10.1016/s0363-5023(96)80210-3)
- [L2] The Cross Brace Protocol provides an additional non-operative option for ACL injuries and may be associated with satisfactory anatomical and functional healing for certain patient groups. [47] (10.1177/2325967126s00013)
- [L5] Based on clinical experience, the authors have found this splint is easy to fabricate, cost-effective, and relatively comfortable. [48] (10.1016/s0894-1130(02)80009-6)
- [L2] Final angulation averaged 15° in the brace group compared to 31° in the splint group. [49] (10.1016/s0363-5023(87)80179-x)
- [L4] Because of the absence of a control group, these findings demonstrate feasibility and short-term clinical improvement but cannot establish superiority over other conservative treatments. [50] (10.1016/j.jhsg.2026.101038)
- [L4] This protocol requires only the flexion splint as opposed to the traditional extension splint followed by flexion splinting; therefore, the cost of splint fabrication is reduced and the instructions to patients for following their splinting programs are simplified. [51] (10.1016/s0894-1130(96)80022-6)
- [L4] Results were significantly better than after treatment in the traditional splint. [52] (10.1016/s0363-5023(89)80025-5)
- [L4] Results indicate the supination splint is clinically effective in increasing supination PROM. [53] (10.1016/s0894-1130(03)00034-6)
- [L5] This small splint allows unrestricted use of adjacent joints and is a cost-effective, efficient treatment option for those patients who elect to postpone or exclude surgical reconstruction for thumb CMC joint pain. [54] (10.1016/s0894-1130(00)80006-x)
- [L4] All patients who had initial improvement in their symptoms with splinting had between 54% and 61% average improvement in symptom severity 6 months after splinting. [55] (10.1053/jhsu.1999.jhsu24a0086)
- [L5] The Reston foam splint is a very comfortable, safe, versatile, and simple splint that is much cheaper and more readily available than conventional manufactured splints. [56] (10.1016/s0363-5023(89)80029-2)
- [L4] Although the authors found the splint annoying, it was much more comfortable than an extension-block cast. [57] (10.1016/s0363-5023(80)80118-3)
- [L4] This low-profile ring splint is easily fabricated and functional and the treatment protocol requires minimal therapy visits. [58] (10.1197/j.jht.2008.05.001)
- [L2] The significantly superior results of the double-T splint are worth this additional 50 g. [59] (10.1016/s0266-7681(05)80214-1)
- [L2] When results were compared with the results of our method of static splinting used prior to this prospective study, patients returned to full activities with good-to-excellent results 8 weeks earlier instead of at 16 to 18 weeks. [60] (10.1016/s0363-5023(10)80082-6)
- [L4] The results of treatment in 25 patients are superior in our hands to those resulting from other methods of splintage. [61] (10.1016/0266-7681(88)90126-x)
- [L4] The functional arc of motion or very close to it was achieved using patient-adjusted static splints after failure of conservative treatment. [62] (10.1016/s1058-2746(95)80215-0)
- [L4] A volar splint has clear limitations regarding immobilization, which is of relevance in clinical practice. [63] (10.1177/1753193416686039)
- [L5] The splint follows recommendations to support the pisotriquetral area. [64] (10.1197/j.jht.2004.04.013)
- [L5] The lack of high-quality evidence means that randomized clinical trials need to be performed to guide rehabilitation choices. [65] (10.1016/j.hansur.2019.05.004)
References
[1] Electrophysiologic basis of dynamic extensor splinting. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90404-d
[2] Swing Design Dynamic Traction Splinting for the Treatment of Intra-articular Fractures of the Digits. Journal of Hand Therapy. 2006. DOI: 10.1197/j.jht.2005.11.001
[3] The splinting issue. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.015009
[4] The influence of splinting on healing tissues. Journal of Hand Therapy. 1998. DOI: 10.1016/s0894-1130(98)80014-8
[5] The clamshell splint with otoform lining. Journal of Hand Therapy. 1997. DOI: 10.1016/s0894-1130(97)80046-4
[6] Splinting and radial nerve palsy: A single-subject experiment. Journal of Hand Therapy. 2001. DOI: 10.1016/s0894-1130(01)80053-3
[7] Orthosis for the Complete Median and Radial Nerve-injured War Casualty. Journal of Hand Therapy. 1992. DOI: 10.1016/s0894-1130(12)80275-4
[8] Regarding “Sling Is Not Inferior to Brace Immobilization After Arthroscopic Rotator Cuff Repair: A Randomized Controlled Trial”. Arthroscopy. 2026. DOI: 10.1002/arj.70326
[9] A modification of the kleinert splint for mobilisation of digital flexor tendons. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90007-6
[10] Examples of simply fabricated, custom-made splints for the hand. The Journal of Hand Surgery. 1981. DOI: 10.1016/s0363-5023(81)80008-1
[11] Kleinert splint. The Journal of Hand Surgery. 1988. DOI: 10.1016/s0363-5023(88)80070-4
[12] Adjustable First Webspace Splint. Journal of Hand Therapy. 1996. DOI: 10.1016/s0894-1130(96)80091-3
[13] Therapeutic Hand Splints: A Rational Approach. Volume 1: Mechanical and Biomechanical Considerations. Journal of Hand Therapy. 2002. DOI: 10.1016/s0894-1130(02)70027-6
[14] A Silicone Splint to Prevent Diving Injuries of the Thumb. Journal of Hand Therapy. 2006. DOI: 10.1197/j.jht.2006.07.029
[15] Postoperative Splinting for Isolated Digital Nerve Injuries in the Hand. Journal of Hand Therapy. 2007. DOI: 10.1197/j.jht.2007.04.010
[16] Outcomes, treatment effectiveness, efficacy, and evidence-based practice: Examples from the world of splinting. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.0150131
[17] James Traction Splinting for PIP Fractures. Journal of Hand Therapy. 2008. DOI: 10.1197/j.jht.2007.08.019
[18] Dorsal Fracture Subluxation of the Proximal Interphalangeal Joints Treated by Extension Block Splintage. Journal of Hand Surgery. 1992. DOI: 10.1016/s0266-7681(05)80249-9
[19] A Review of Attitudes to Splintage in Dupuytren's Contracture. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90208-j
[20] A flexion contracture splint for the distal interphalangeal joint. Journal of Hand Therapy. 2001. DOI: 10.1016/s0894-1130(01)80009-0
[21] REHABILITATION CONCEPTS AND SUPPORTIVE DEVICES FOR OVERUSE INJURIES OF THE UPPER EXTREMITIES. Clinics in Sports Medicine. 2001. DOI: 10.1016/s0278-5919(05)70273-8
[22] Force analysis of the belly gutter and capener splints. Journal of Hand Therapy. 1999. DOI: 10.1016/s0894-1130(99)80074-x
[23] Low-profile Dynamic Splints: A Solution to the Friction Problem. Journal of Hand Therapy. 1993. DOI: 10.1016/s0894-1130(12)80332-2
[24] Functional Fracture Bracing in Metacarpal Fractures: The Galveston Metacarpal Brace versus a Plaster-of-Paris Bandage in a Prospective Study. Journal of Hand Therapy. 1993. DOI: 10.1016/s0894-1130(12)80327-9
[25] Buddy Splint. Journal of Hand Therapy. 1994. DOI: 10.1016/s0894-1130(12)80041-x
[26] Plaster of Paris: The forgotten hand splinting material. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.015014
[27] Three-Point Static Splint for Chronic Volar Subluxation of the Thumb Metacarpophalangeal Joint. Journal of Hand Therapy. 1994. DOI: 10.1016/s0894-1130(12)80062-7
[28] Ambulatory Arm Elevator Sling (Hands Up). Journal of Hand Therapy. 1994. DOI: 10.1016/s0894-1130(12)80064-0
[29] Relative motion orthoses in the management of various hand conditions: A scoping review. Journal of Hand Therapy. 2016. DOI: 10.1016/j.jht.2016.07.001
[30] A review of attitudes to splintage in Dupuytren's contracture. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1987. DOI: 10.1016/0266-7681(87)90182-3
[31] A Review of Attitudes to Splintage in Dupuytren’s Contracture. Journal of Hand Surgery. 1987. DOI: 10.1016/0266-7681_87_90182-3
[32] Comparison study of quickcast versus a traditional thermoplastic in the fabrication of a resting hand splint. Journal of Hand Therapy. 1998. DOI: 10.1016/s0894-1130(98)80060-4
[33] Dynamic flexion splint for the distal interphalangeal joint. Journal of Hand Therapy. 2003. DOI: 10.1016/s0894-1130(03)00041-3
[34] Design of an orthosis with straight spring for extension mobilization of flexion contracture of the proximal interphalangeal joint. Journal of Hand Therapy. 2021. DOI: 10.1016/j.jht.2020.01.005
[35] Modification to a pediatric thumb splint. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2004.04.014
[37] Trigger fingers and thumb: When to splint, inject, or operate. The Journal of Hand Surgery. 1992. DOI: 10.1016/0363-5023(92)90124-8
[38] An Eco-conscious Alternative Material for Splinting in Hand Surgery. Techniques in Hand & Upper Extremity Surgery. 2018. DOI: 10.1097/bth.0000000000000210
[39] Plaster of Paris Splints. Journal of Hand Therapy. 1995. DOI: 10.1016/s0894-1130(12)80157-8
[40] A new power source in dynamic splinting: Clinical experience and results. Journal of Hand Therapy. 1989. DOI: 10.1016/s0894-1130(89)80022-5
[41] A proposed decision hierarchy for splinting the stiff joint, with an emphasis on force application parameters. Journal of Hand Therapy. 2002. DOI: 10.1053/hanthe.2002.v15.015015
[42] A Modified Kleinert Controlled Mobilization Splint Following Flexor Tendon Repair. Journal of Hand Surgery. 1984. DOI: 10.1016/s0266-7681(84)80039-x
[43] Splints: Mechanics versus Convention. Journal of Hand Therapy. 1995. DOI: 10.1016/s0894-1130(12)80309-7
[44] Molded polythene splint for mallet finger deformities. The Journal of Hand Surgery. 1985. DOI: 10.1016/s0363-5023(85)80277-x
[45] Do patients with minimally displaced distal radial fractures need a plaster cast?. The Bone & Joint Journal. 2025. DOI: 10.1302/0301-620x.107b1.bjj-2024-0634.r1
[46] Surgical treatment and postoperative splinting of recessive dystrophic epidermolysis bullosa. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80210-3
[47] Short-term Outcomes of the Cross Brace Protocol for ACL Rupture Management: A Prospective Cohort Study. Orthopaedic Journal of Sports Medicine. 2025. DOI: 10.1177/2325967126s00013
[48] Static progressive wrist extension splint. Journal of Hand Therapy. 2002. DOI: 10.1016/s0894-1130(02)80009-6
[49] Functional bracing of fractures of the second through fifth metacarpals. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80179-x
[50] Effectiveness of Proximal Interphalangeal Joint Orthosis and Therapeutic Exercise in the Management of Trigger Finger: A Prospective Case Series. Journal of Hand Surgery Global Online. 2026. DOI: 10.1016/j.jhsg.2026.101038
[51] Effect of an alternative flexion splinting protocol on mid-joint rom. Journal of Hand Therapy. 1996. DOI: 10.1016/s0894-1130(96)80022-6
[52] A new dynamic splint for postoperative treatment of flexor tendon injury. The Journal of Hand Surgery. 1989. DOI: 10.1016/s0363-5023(89)80025-5
[53] A Supination Splint Worn Distal to the Elbow:. Journal of Hand Therapy. 2003. DOI: 10.1016/s0894-1130(03)00034-6
[54] The biomechanics of a thumb carpometacarpal immobilization splint: Design and fitting. Journal of Hand Therapy. 2000. DOI: 10.1016/s0894-1130(00)80006-x
[55] Splinting in the treatment of arthritis of the first carpometacarpal joint. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.jhsu24a0086
[56] A simple, comfortable, conforming, and adaptable splint. The Journal of Hand Surgery. 1989. DOI: 10.1016/s0363-5023(89)80029-2
[57] A new method of extension-block splinting for the proximal interphalangeal joint—Preliminary report. The Journal of Hand Surgery. 1980. DOI: 10.1016/s0363-5023(80)80118-3
[58] Effectiveness of Splinting for the Treatment of Trigger Finger. Journal of Hand Therapy. 2008. DOI: 10.1197/j.jht.2008.05.001
[59] Maintaining the Safe Position in a Palmar Splint. Journal of Hand Surgery. 1996. DOI: 10.1016/s0266-7681(05)80214-1
[60] Results of acute zone III extensor tendon injuries treated with dynamic extension splinting. The Journal of Hand Surgery. 1991. DOI: 10.1016/s0363-5023(10)80082-6
[61] The pipflex splint for treatment of mallet finger. The Journal of Hand Surgery: Journal of the British Society for Surgery of the Hand. 1988. DOI: 10.1016/0266-7681(88)90126-x
[62] Patient-adjusted static elbow splints for elbow contractures: A preliminary report. Journal of Shoulder and Elbow Surgery. 1995. DOI: 10.1016/s1058-2746(95)80215-0
[63] Helicoidal splinting after wrist surgery: a laboratory study. Journal of Hand Surgery (European Volume). 2017. DOI: 10.1177/1753193416686039
[64] An ulnar boost splint for midcarpal instability. Journal of Hand Therapy. 2004. DOI: 10.1197/j.jht.2004.04.013
[65] Splints, with or without wrist immobilization, following surgical repair of flexor tendon lesions of the hand: A systematic review. Hand Surgery and Rehabilitation. 2019. DOI: 10.1016/j.hansur.2019.05.004