Patients › Wrist
Tenosinovitis de De Quervain
Patient-facing topic on De Quervain's tenosynovitis (first dorsal compartment) — diagnosis, conservative management, and indications for de Quervain's release.
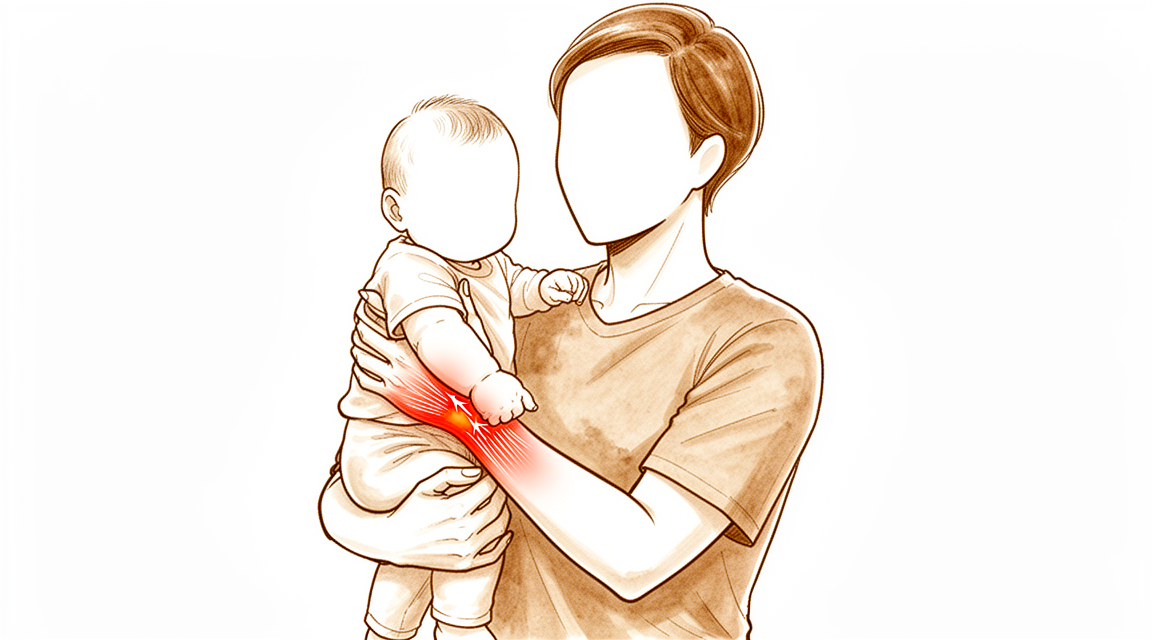
Qué está sintiendo
La tenosinovitis de De Quervain es un problema de dos tendones situados en el lado del pulgar de la muñeca. El túnel por el que pasan se hincha y se estrecha, por lo que a los tendones les duele deslizarse a través de él. Siente dolor y sensibilidad al tacto en el lado del pulgar de la muñeca, cerca del bulto óseo de la base del pulgar. A menudo hay hinchazón sobre esa misma zona.
Ciertos movimientos empeoran el dolor. Doblar la muñeca hacia el meñique, agarrar algo con fuerza mientras dobla la muñeca hacia el lado del pulgar, o juntar en pinza el pulgar y el índice pueden provocarlo. Las tareas cotidianas que requieren estos movimientos se vuelven difíciles: levantar una tetera, girar un picaporte, cargar a un niño pequeño, escurrir un paño o usar tijeras. Algunas personas notan un leve roce o crujido bajo la piel al presionar sobre la zona dolorida.
La mayoría de las personas notan que el dolor se intensifica con el uso y se calma con el reposo. Puede empeorar después de un día de mucho uso de la mano. Algunas personas lo notan a primera hora de la mañana o durante la noche.
Un pequeño número de personas (alrededor de 1 de cada 100) notan que, además del dolor, el pulgar se engancha o se bloquea. Conviene mencionarlo, porque puede cambiar qué tratamientos funcionan bien.
Cuándo buscar ayuda
Consulte a su médico de cabecera o solicite una evaluación especializada si el dolor no mejora, empeora a lo largo de las semanas, le despierta por la noche o le impide trabajar o usar la mano.
Acuda al servicio de urgencias ese mismo día si la mano o el brazo se pone caliente, rojo, hinchado y doloroso, sobre todo si tiene fiebre. Podría tratarse de una infección que requiere atención el mismo día, y no necesita una derivación de su médico de cabecera. Acuda también ese mismo día si los dedos o la mano se ponen pálidos, fríos, blancos o azulados, o si pierde de repente la sensibilidad o el movimiento después de una lesión.
Si no puede contactar con la clínica, por ejemplo fuera del horario de atención o durante el fin de semana, acuda al servicio de urgencias más cercano.
¿Qué está ocurriendo realmente?
Dos tendones separan el pulgar de la mano y lo estiran. Pasan uno junto al otro por un túnel estrecho en el lado del pulgar de la muñeca. El túnel tiene un techo firme que mantiene los tendones pegados al hueso, como una anilla guía que sujeta dos cuerdas en su sitio.
El problema es que los tendones y su túnel se inflaman. El revestimiento hinchado ocupa espacio dentro de un hueco que ya es estrecho, de modo que los tendones rozan al deslizarse. Esa fricción provoca más hinchazón y más dolor, y el propio túnel puede estrecharse con el tiempo. El riego sanguíneo a través de este paso estrecho es escaso, lo que dificulta que la irritación se calme por sí sola.
Algunas personas tienen de forma natural una pared adicional dentro del túnel, que lo divide en dos pasos separados. Esto es importante porque ambos tendones necesitan espacio para deslizarse. Si uno de los tendones queda en su propio paso cerrado, ese paso puede seguir estrecho aunque se trate el túnel principal.
Esto explica lo que siente. La zona dolorida en el lado del pulgar de la muñeca es el propio túnel. El dolor al agarrar, pellizcar y levantar objetos se debe a que los tendones tiran a través del espacio estrechado. La fuerza de pinza y del pulgar puede disminuir porque los tendones no pueden deslizarse libremente. El roce o crujido que notan algunas personas es la superficie áspera del tendón moviéndose bajo la piel.
Cuando el pulgar se engancha o se bloquea además de doler, el estrechamiento se ha vuelto lo bastante intenso como para atrapar el tendón momentáneamente. Se trata de una forma más avanzada del mismo problema, y conviene señalarlo pronto porque cambia qué tratamientos funcionan bien.
El dolor en esta zona también puede venir de estructuras vecinas al túnel y no del propio túnel: la artrosis de la base del pulgar, tendones irritados más arriba en el antebrazo o un nervio superficial que cruza esta parte de la muñeca. Estos problemas necesitan tratamientos distintos, y por eso importa saber exactamente de dónde viene el dolor.
Qué podemos hacer al respecto
El Dr. Kieran Hirpara, cirujano de extremidades superiores en el Mater Private Hospital Rockhampton, comienza con las opciones menos invasivas que se adapten a su condición. Por lo general empezamos con cambios en la forma en que usa la mano y con terapia de la mano para calmar la irritación y reducir la carga sobre los tendones. Una férula que mantiene inmóviles el pulgar y la muñeca puede dar descanso a los tendones y reducir la fricción que causa el dolor. Dé a estas medidas una oportunidad real antes de pasar a otra cosa, y avísenos si no mejora.
El tratamiento con la evidencia más sólida para esta afección es una inyección de cortisona. La cortisona es un medicamento antiinflamatorio que reduce la hinchazón dentro del túnel. Una sola inyección alivia los síntomas en el 82% de las personas, y más de la mitad de ellas permanecen sin síntomas durante al menos 12 meses. Guiar la inyección con ecografía puede mejorar el resultado, y además nos ayuda a confirmar exactamente qué estamos tratando. Combinar la inyección con una férula que mantiene inmóvil la muñeca funciona mejor que la inyección sola. Si los síntomas reaparecen, una segunda inyección sigue siendo una opción razonable y no una señal de que las inyecciones hayan fracasado. Si usted padece diabetes, una sola inyección tiene menos probabilidades de ser eficaz que en otras personas, pero cada inyección adicional sigue funcionando tan bien como la anterior.
La mayoría de las personas no necesitarán cirugía. La consideramos cuando el tratamiento no quirúrgico no ha producido una mejoría suficiente, o cuando el pulgar se engancha y se bloquea además de doler, algo que no suele calmarse por sí solo. La operación libera el techo estrecho del túnel para que los tendones vuelvan a deslizarse libremente. Es una operación pequeña y tiene su propia página en la que se describe en qué consiste.
Qué esperar
En la mayoría de las personas, esta afección no desaparece por sí sola rápidamente. La mayoría de quienes la padecen siguen teniendo síntomas un año después si no se hace nada, y el dolor tiende a reagudizarse con el uso en lugar de ir desapareciendo poco a poco. Un pequeño número de personas (alrededor de una de cada tres) acabará necesitando cirugía en un plazo de dos años, y la mayoría de quienes la necesitan llegan a ese punto durante el primer año.
Con el tratamiento, el pronóstico es bueno, dicho con sinceridad. Una sola inyección de cortisona resuelve por completo los síntomas en el 70% de las personas, y una segunda inyección cura a un 10% adicional. En conjunto, las inyecciones tienen éxito el 73.4% de las veces con un máximo de dos inyecciones. Cuando se necesita cirugía, funciona bien: el 88% de las personas están totalmente satisfechas después, y la operación cura el problema en el 91% de los casos.
Cómo se vive la recuperación depende del camino que elija. Después de una inyección, el dolor suele aliviarse en cuestión de días o semanas a medida que se reduce la hinchazón dentro del túnel. Después de la cirugía, los tendones vuelven a deslizarse libremente, y la mejoría suele llegar antes con el método mínimamente invasivo (endoscópico) que con el método abierto. La terapia de la mano después de la cirugía se realiza con Ruby Doolan en Extend Rehabilitation. Ruby es terapeuta especializada en mano: dirige su terapia y confecciona cualquier férula que necesite.
Conviene saber algunas cosas desde el principio. Si padece diabetes o síndrome metabólico (un conjunto de problemas de salud que incluye la presión arterial alta y el exceso de peso alrededor de la cintura), las inyecciones tienen menos probabilidades de ser eficaces en su caso que en otras personas. La forma en que usted percibe la afección también influye: las personas que esperan lo peor tienden a referir más dolor y menos función, por lo que ayuda tener expectativas realistas en lugar de temores sobre lo que significa esta afección.
Si sus síntomas no mejoran, empeoran a lo largo de las semanas, le despiertan por la noche o le impiden trabajar o usar la mano, consulte a su médico de cabecera o solicite una evaluación especializada.
¿Cuándo consultar a un especialista?
La mayoría de las señales de alarma de esta afección ya se describen en la primera sección: un dolor que no mejora, que empeora a lo largo de las semanas, que le despierta por la noche o que le impide trabajar o usar la mano. Si alguna de ellas se aplica a usted, consulte a su médico de cabecera o solicite una evaluación especializada.
Hay una señal que merece mencionarse de nuevo aquí. Si el pulgar se engancha o se bloquea además de doler, dígaselo a quien le atienda. Esta forma del problema no suele calmarse solo con reposo o con una férula, y cambia qué tratamientos funcionan bien, por lo que conviene señalarla pronto en lugar de esperar a ver si desaparece.
El mismo consejo se aplica si el dolor se sitúa un poco lejos de la zona habitual, por ejemplo más arriba en el antebrazo o sobre la base del pulgar. Varias otras afecciones pueden parecerse a esta y responden a tratamientos distintos. Una exploración cuidadosa permite saber cuál de ellas tiene.
Acuda al servicio de urgencias ese mismo día si la mano o el brazo se pone caliente, rojo, hinchado y doloroso, sobre todo si tiene fiebre, o si los dedos se ponen pálidos, fríos, blancos o azulados.
En mayor profundidad
Advanced reading: the deeper science (optional)
Esta sección profundiza más de lo necesario para que usted tome sus propias decisiones terapéuticas. La tenosinovitis de De Quervain merece esta lectura adicional debido a una pequeña variante anatómica que explica gran parte de la insatisfacción postoperatoria, a pesar de que el procedimiento en sí es bastante fiable; además, el mejor resultado sin intervención quirúrgica se logra combinando dos tratamientos en lugar de optar por uno solo.
La combinación de ambos tratamientos es más eficaz que cualquiera por separado
El primer compartimento dorsal contiene dos tendones dentro de un túnel situado en el lado del pulgar de la muñeca. El objetivo del tratamiento es reducir la inflamación en dicho túnel y disminuir la carga que soporta.
Un metaanálisis de red realizado con 823 pacientes concluyó que la inyección de corticoides junto con un período breve de inmovilización sigue siendo el tratamiento principal y eficaz, siendo la terapia con ondas de choque extracorpóreas una opción secundaria [1]. Al analizar cada componente por separado, los enfoques que combinan el uso de órtesis e inyección de corticoides resultan más eficaces que cualquiera de las intervenciones por sí solas [2].
Esto constituye una indicación más precisa que el consejo genérico de “probar primero con una férula y, si no funciona, aplicar una inyección”. La evidencia científica respalda la aplicación conjunta de ambas medidas, utilizando la férula durante un breve período tras la inyección.
Vale la pena aplicar una segunda inyección
Cuando los síntomas reaparecen, lo lógico es pensar que las inyecciones han fracasado y optar por la cirugía. Sin embargo, los datos obtenidos de un gran grupo de pacientes indican lo contrario: aunque la tasa de éxito disminuye con múltiples inyecciones, las inyecciones repetidas siguen teniendo una alta tasa de éxito y constituyen una opción clínica viable [3].
Es normal que el éxito disminuya con el uso repetido de inyecciones. No obstante, una tasa de éxito menor no equivale a ineficacia; por ello, aplicar una segunda inyección sigue siendo una medida razonable, y no una mera táctica para retrasar el tratamiento.
La variante que explica la mayoría de las decepciones quirúrgicas
La liberación del primer compartimento dorsal es eficaz; cuando no da resultados satisfactorios, suele haber una razón específica. La insatisfacción puede deberse a una liberación incompleta, a la subluxación de los tendones, a lesiones nerviosas o simplemente a la duración de la recuperación. Además, la existencia de una vaina del extensor pollicis brevis no identificada ni liberada constituye una causa concreta de insatisfacción [4].
Esto merece ser analizado en profundidad, pues es el dato más relevante de esta sección. En una proporción considerable de pacientes, el compartimento no es un único túnel, sino dos; el tendón del extensor pollicis brevis discurre en su propia vaina, separada de las demás. Una liberación que abra únicamente el compartimento principal deja intacta esa segunda vaina, de modo que el tendón permanece comprimido. Se abre la muñeca, se completa la intervención según lo descrito, pero los síntomas persisten.
Esta es también la razón por la que las otras dos causas mencionadas son importantes: una liberación excesiva permite que los tendones se subluxen fuera de su canal al mover la muñeca, provocando un chasquido doloroso; además, la rama superficial del nervio radial discurre justo sobre el campo operatorio. Por ello, el compartimento debe abrirse por completo, pero sin excesos, teniendo en cuenta la presencia del nervio; esto explica por qué una intervención aparentemente menor requiere el mismo cuidado que una más compleja.
No todo el dolor en la zona radial de la muñeca se debe al síndrome de De Quervain
El dolor en esta zona presenta varias posibles causas que vale la pena conocer, ya que los tratamientos difieren: la artritis en la base del pulgar, el síndrome de intersección a unos pocos centímetros más arriba en el antebrazo, y la irritación del nervio radial pueden provocar dolor en zonas similares. Una sensibilidad localizada exactamente sobre dicha zona, junto con dolor que se reproduce al desviar la muñeca hacia el lado cubital con el pulgar metido en la palma, son indicadores de que el problema radica en la vaina tendinosa y no en otras estructuras cercanas.
Referencias
[1] Chong HH, Pradhan A, Dhingra M, Liong W, Hau MY, Shah R. Avances en el tratamiento de la tenosinovitis de De Quervain: un metaanálisis de red integral de ensayos controlados aleatorizados. J Hand Surg Am. 2024;49(6):557-69. https://doi.org/10.1016/j.jhsa.2024.03.003
[2] Cavaleri R, Schabrun SM, Te M, Chipchase LS. Terapia de la mano frente a inyecciones de corticoides en el tratamiento de la enfermedad de De Quervain: una revisión sistemática y metaanálisis. J Hand Ther. 2016;29(1):3-11. https://doi.org/10.1016/j.jht.2015.10.004
[3] Hassan K, Sohn A, Shi L, Lee M, Wolf JM. Tenosinovitis de De Quervain: evaluación de la epidemiología y utilidad de múltiples inyecciones mediante una base de datos nacional. J Hand Surg Am. 2022;47(3):284.e1-284.e6. https://doi.org/10.1016/j.jhsa.2021.04.018
[4] Rogozinski B, Lourie GM. Insatisfacción tras la liberación del compartimento dorsal primario por tendinopatía de De Quervain. J Hand Surg Am. 2016;41(1):117-9. https://doi.org/10.1016/j.jhsa.2015.09.003
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Overview
Anatomy and Diagnosis
- Anatomical variations in the first extensor compartment are clinically relevant to the pathophysiology and treatment of De Quervain's tenosynovitis [1].
- Wrist radiography does not influence the management of patients presenting with de Quervain tendinopathy [6].
- The tethered thumb sign is a clinical maneuver that supports the diagnosis of de Quervain tenosynovitis and assists in determining an effective treatment algorithm [12].
- Ultrasound can be used as a diagnostic tool in the management of de Quervain’s disease [18].
Non-Operative Treatment
- Corticosteroid injection is the only available nonsurgical treatment that can potentially modify the course of de Quervain's tenosynovitis and is the preferred initial treatment [2].
- Corticosteroid injection with a short duration of immobilization remains the primary and effective treatment for de Quervain tenosynovitis [28].
- Corticosteroid injections lead to treatment success 73.4% of the time within 2 injections [22].
- Although the success rate for the treatment of De Quervain's tenosynovitis decreases with multiple injections, repeat injections have a high rate of success and are a viable clinical option [46].
- Corticosteroid injection for De Quervain tenosynovitis is not as effective in patients with metabolic syndrome compared with age- and sex-matched controls in terms of functional outcomes and treatment failure [5].
- Patients with diabetes mellitus have a decreased probability of success following a single corticosteroid injection for de Quervain tenosynovitis in comparison to nondiabetic patients [40].
- The effectiveness of each additional corticosteroid injection does not appear to diminish in patients with diabetes mellitus [40].
- Ultrasound-guided triamcinolone injection should be considered to improve the treatment outcome for de Quervain's disease [18].
Operative Treatment
- Surgical release of De Quervain's tenosynovitis remains the gold standard treatment [10].
- Surgical intervention is effective as definitive therapy for de Quervain's tenosynovitis, with a cure rate of 91% and 88% of patients indicating full satisfaction [11].
- The release of the first extensor compartment for refractory de Quervain's disease results in good clinical outcomes with minimal morbidity [24].
- Longitudinal incision offers the advantage of easy identification of the compartment, more complete releases of tendon sheath and peritendinous adhesions, and less risk of palmar subluxation of tendons [10].
- The longitudinal incision for release of the first extensor compartment is a safe and effective technique that provides good exposure, protects vital structures, prevents possible tendon subluxation in the postoperative period, and is cosmetically acceptable [17].
- Endoscopic release for de Quervain's tenosynovitis seems to provide earlier improvement after surgery, with fewer superficial radial nerve complications and greater scar satisfaction, when compared with open release [33].
- One portal endoscopic assisted release of the extensor compartment is an effective and safe minimal invasive procedure with similar complication rates reported previously in open and endoscopic procedures [31].
- Endoscopic release of the extensor compartment is an effective and safe procedure in patients with de Quervain's disease who are unresponsive to nonoperative treatments, despite a little increase in operation time [41].
- Pulley reconstruction should be considered part of the surgical treatment for de Quervain tenosynovitis and gives satisfactory medium-term results [4].
Prognosis and Patient Factors
- Patients presenting with de Quervain's tenosynovitis may favor initial nonsurgical management [7].
- Patients who scored lower than 40 for physical function or higher than 60 for pain interference had significantly increased odds of eventually undergoing surgical release for de Quervain tenosynovitis [34].
- The failure of an operation in De Quervain tenosynovitis is due to anatomical variations, the involvement of the radial superficial nerve, and the ignoring of another syndrome in the proximity [13].
- Addressing misconceptions about de Quervain's tenosynovitis regarding consequences for patients and symptom duration allows patients to make informed decisions about treatment [9].
Anatomy & Pathophysiology
Anatomical Variations
- The first dorsal compartment of the wrist exhibits immense anatomical variation, including commonly found supernumerary tendons or tendon slips [107].
- Variation in tendon insertion is present in the population of the first dorsal compartment [107].
- Septa or aberrant compartments are present in the first dorsal compartment [107].
- Bilateral variations are present in the population regarding the anatomy of the first dorsal compartment [107].
- The superficial branch of the radial nerve is expected to be encountered in more than 50% of patients undergoing surgery for De Quervain's tenosynovitis [94].
Pathophysiology
- De Quervain's syndrome is defined as a condition where the abductor pollicis longus and extensor pollicis brevis tendons in the first dorsal compartment become inflamed through friction within a tight osteoligamentous tunnel [3].
- Compromised blood flow and nutrition in the first dorsal compartment lead to the development of adhesions and tendon stenosis [3].
- De Quervain's syndrome may involve myxoid degeneration, defined as a degenerative process where connective tissues are replaced by a gelatinous or mucoid substance [3].
- The pathophysiology of De Quervain's disease does not involve inflammation, with histopathological examination showing predominant degenerative changes such as myxoid degeneration and fibrocartilagenous metaplasia [38].
- De Quervain's tenosynovitis is caused by impaired gliding of the abductor pollicis longus and extensor pollicis brevis tendons [38].
- Impaired gliding in De Quervain's tenosynovitis is most probably caused by thickening of the extensor retinaculum of the wrist [38].
- De Quervain's syndrome may not be an isolated pathology and may be associated with trauma, extensor carpi ulnaris involvement, ligament instability, or repetitive strain [3].
- Operative treatment for distal radius fractures confers a slightly greater risk of developing De Quervain tenosynovitis within 1 year of injury or surgery [105].
Clinical Presentation & Assessment
- De Quervain's tenosynovitis is characterized by pain, tenderness, and swelling over the thumb side of the wrist at the radial styloid process [38].
- The condition is especially associated with sideward movements of the wrist and often leads to impairment of thumb function [38].
- The tethered thumb sign is a clinical maneuver that can support the diagnosis of De Quervain tenosynovitis and assist in determining an effective treatment algorithm [12].
- Subjects with stenosing tenosynovitis demonstrate a significant decrease in maximum velocity in slow fist tasks [81].
- In vivo extensor pollicis brevis tendon excursion measures have been quantified, and wrist position has been found to have an influence on excursion [73].
- The proportion of wrists with a positive extensor pollicis brevis entrapment test was significantly higher among those with two compartments (18 of 22) than among those with one compartment (0 of 4) [97].
Etiology & Risk Factors
- Women are more affected by De Quervain tenosynovitis than men, potentially due to manual work such as housekeeping activities and child rearing influencing first compartment dynamics [72].
- Training intensity is a major factor in determining De Quervain disease in volleyball players, with patients in the higher intensity group showing a mean training time quotient of 155 compared to 74 in the lower intensity group [72].
- The close association of work and repetitive trauma with De Quervain’s disease has been observed, although the exact relationship is controversial [21].
- Recent studies have disputed the view that repetitive work is causative of De Quervain’s disease, with one review of 100 patients finding no increased incidence in the dominant hand [21].
- A study of workers in a car plant reported 544 cases of tenosynovitis but only 2 cases of De Quervain’s disease [21].
- Repetitive work is less contentious as a factor in aggravating symptoms, as tendon movement within a stenosed sheath during activity logically causes pain [21].
- The process of tendon movement within a stenosed sheath may cause tendon damage through wear and tear, potentially leading to tendon rupture [21].
Complications & Associated Pathology
- Rupture of the abductor pollicis longus tendon in association with De Quervain’s disease has never been reported in the literature prior to the 2006 case report [21].
- Volar subluxation of the tendons of the first dorsal compartment can occur after surgery for De Quervain's stenosing tenosynovitis [48].
- Volar tendon subluxation after De Quervain's release can be treated with a distally based flap of the brachioradialis tendon to prevent tendon prolapse [48].
- Symptomatic palmar tendon subluxation after surgical release for De Quervain's disease can be avoided by leaving a palmarly based flap of extensor retinaculum [15].
- Dorsal tendon dislocation after De Quervain's release can occur if the patient overstresses the wrist through forceful extension [80].
- Repeat provocative testing for volar tendon subluxation following De Quervain’s release revealed volar tendon translation with wrist flexion, with no pain reported [85].
- Osteoid osteoma of the radial styloid can mimic stenosing tenosynovitis, with correct diagnosis often requiring histological examination when clinical presentation and X-rays are not typical [45].
Classification
Anatomical Variations and Subcompartmentalization
- The prevalence of a septated first dorsal compartment is considerably higher than previously reported, most notably in patients with De Quervain tenosynovitis [52].
- In a prospective study of 87 wrists, 22 of 30 patients (73%) who failed non-operative treatment and underwent operative release were found to have a separate compartment for the extensor pollicis brevis [55].
- The prevalence of a separate compartment for the extensor pollicis brevis in patients failing non-operative treatment is significantly higher than that in the general population, as shown in anatomical studies of cadavers [55].
- The persistence of an intracompartmental septum between the abductor pollicis longus and extensor pollicis brevis tendons has been described in a mean 43% of wrists in cadaveric studies, with a wide variation ranging from 20 to 75% [39].
- When the extensor pollicis brevis tendon resides in a subcompartment, it is likely to do so particularly in patients with de Quervain's disease [53].
- Ultrasound is a useful imaging technique for diagnosing de Quervain's disease and provides important information about anatomic variations within the first extensor compartment [50].
- The presence of an intracompartmental septum detected by ultrasound is associated with the failure of ultrasound-guided steroid injection in de Quervain’s syndrome [39].
Diagnostic Mimics and Associated Pathologies
- Extensor pollicis longus tenosynovitis caused by the extensor pollicis longus's unusual course through the first extensor compartment is a very rare condition that mimics de Quervain’s disease [30].
- An osteoid osteoma of the radial styloid can mimic stenosing tenosynovitis, with correct diagnosis often requiring histological examination when clinical presentation and X-rays are not typical [45].
- A hemangioma of the extensor pollicis brevis in the first dorsal compartment is an unusual cause of bilateral de Quervain's disease [14].
- De Quervain’s syndrome may not be an isolated pathology, with potential associations to trauma, extensor carpi ulnaris involvement, ligament instability, and repetitive strain [3].
- Failure of surgical treatment in De Quervain tenosynovitis can be attributed to anatomical variations, the involvement of the radial superficial nerve, and the ignorance of another syndrome in the proximity [13].
- The complexities of de Quervain's tendinitis and the diagnosis and treatment of associated diseases and complications are described to help prevent surgical failures and prolonged disabilities in working women [8].
Clinical Presentation and Physical Examination
- Triggering or locking in extension is an uncommon symptom in de Quervain’s stenosing tenosynovitis, with a prevalence of 1.3% based on a review of 827 consecutive patients [20].
- A new test for evaluating the first extensor compartment is a useful clinical tool in the diagnosis of De Quervain's tenosynovitis [36].
- Ultrasound can be used as a diagnostic tool in the management of de Quervain’s disease, in addition to improving treatment outcomes [18].
Epidemiology and Risk Factors
- In a young, active population, the unadjusted incidence rate of de Quervain’s tenosynovitis was 0.94 per 1000 person-years [54].
- The adjusted incidence rate ratio for females compared to male patients was 4.45 (95% CI 4.28, 4.62) when controlling for race, age, service, and rank [54].
- The highest incidence rate of de Quervain’s tenosynovitis was seen in the ≥40-year-old group, with an incidence rate of 1.37 per 1000 person-years [54].
- The adjusted incidence rate ratio for the ≥40-year-old group compared to the <20-year-old group was 3.65 (95% CI 3.26, 4.09) [54].
- Non-white race is a risk factor for de Quervain’s tenosynovitis, with an adjusted incidence rate ratio of 1.31 (95% CI 1.21, 1.42) for black race and 1.17 (95% CI 1.05, 1.25) for others compared to white race [54].
- De Quervain’s syndrome affects around 1.3% of women and 0.5% of men in a population of adults of working age [39].
Pathophysiology
- De Quervain’s syndrome is defined as a condition where the abductor pollicis longus and extensor pollicis brevis tendons in the first dorsal compartment become inflamed through friction, leading to compromised blood flow, nutrition, adhesions, and tendon stenosis [3].
- De Quervain’s syndrome may represent a myxoid degeneration, defined as a degenerative process in which connective tissues are replaced by a gelatinous or mucoid substance [3].
- The role of repetitive work in the causation of de Quervain’s disease is controversial, with some studies disputing it as a primary cause while acknowledging it may aggravate symptoms [21].
- Rupture of the abductor pollicis longus tendon in association with De Quervain’s disease has never been reported in the literature prior to the 2006 report [21].
Clinical Presentation
Symptoms and Signs
- Patients typically complain of soreness and tenderness on the radial side of the distal radius that is exacerbated by ulnar deviation of the thumb [59].
- Symptoms are also exacerbated by a strong grasp combined with flexion and radial deviation of the wrist or by a firm pinching together of the index finger and thumb [59].
- Physical examination reveals tenderness and swelling directly over the first dorsal compartment [59].
Diagnostic Testing
- De Quervain disease is diagnosed clinically and no imaging studies are required [64].
- Wrist radiography does not influence management of patients presenting with de Quervain tendinopathy [6].
- In a study of 200 patients, no radiographic findings altered the course of treatment in patients with isolated de Quervain's tenosynovitis [62].
- Wrist imaging is required only in the presence of associated processes that may need to be evaluated, such as previous distal radius or scaphoid fracture, arthritis of the thumb, and instability of the wrist [64].
- Ultrasound can be useful as a diagnostic tool in the management of de Quervain’s disease [18].
- Ultrasound is a worthwhile preoperative investigation in case of de Quervain's disease [51].
- The wrist hyperflexion and abduction of the thumb (WHAT) test is a more specific and sensitive test to diagnose de Quervain tenosynovitis than the Eichhoff’s Test [59].
- Finkelstein's test is superior to Eichhoff's test in the investigation of de Quervain's disease [63].
- A new clinical maneuver, the tethered thumb sign, can support the diagnosis of de Quervain tenosynovitis and assist in determining an effective treatment algorithm [12].
Differential Diagnosis and Mimics
- Extensor pollicis longus tenosynovitis caused by the EPL's unusual course through the first extensor compartment is a very rare condition that mimics de Quervain’s disease [30].
- Congenital synostosis between the scaphoid and the trapezium can cause tenosynovitis simulating de Quervain's disease [43].
- The failure of surgical treatment in De Quervain tenosynovitis can be due to anatomical variations, the involvement of the radial superficial nerve, and the ignoring of another syndrome in the proximity [13].
- In cases with symptoms of de Quervain's syndrome where the constriction involves only the extensor pollicis brevis in a separate compartment, exploration of both compartments is advised [27].
Patient Factors and Perception
- Providers should remain cognizant that patients presenting with de Quervain's tenosynovitis may favor initial nonsurgical management [7].
- Most informed patients initially elect symptomatic treatment for de Quervain's disease, and most experience symptom resolution within one year [32].
- More negative perceptions of the consequences of de Quervain's tenosynovitis and worse pain catastrophizing are associated with worse pain and reduced function at baseline in patients awaiting surgical decompression [25].
- Addressing misconceptions about de Quervain's tenosynovitis in terms of the consequences for patients and how long their symptoms will last should allow patients to make informed decisions about the treatment that best matches their values [9].
Investigations
Clinical Examination
- Finkelstein's test is described as a descriptive error that can produce a false positive [16].
- A staged description of the Finkelstein test has been proposed to address diagnostic accuracy issues [16].
- A new clinical test for evaluating the first extensor compartment is a useful tool in the diagnosis of De Quervain's tenosynovitis [36].
- In cases where symptoms suggest de Quervain's syndrome but constriction involves only the extensor pollicis brevis in a separate compartment, exploration of both compartments is advised [27].
Imaging
- Deferring routine wrist radiography does not affect the management of de Quervain tendinopathy patients [6].
- Ultrasound is a useful imaging technique for diagnosing de Quervain's disease and provides information about anatomic variations within the first extensor compartment [50].
- Ultrasound is a worthwhile preoperative investigation in cases of de Quervain's disease [51].
- Radial styloid abnormalities do not affect the outcome of management for de Quervain's disease [19].
- An osteoid osteoma of the radial styloid can mimic stenosing tenosynovitis, and correct diagnosis may require histological examination when clinical presentation and X-rays are atypical [45].
- Congenital synostosis between the scaphoid and the trapezium can cause tenosynovitis that simulates de Quervain's disease [43].
- Extensor pollicis longus tenosynovitis caused by an unusual course through the first extensor compartment is a rare condition that mimics de Quervain’s disease [30].
Anatomical Variations
- Anatomical variations in the first extensor compartment are clinically relevant in the pathophysiology and treatment of De Quervain's tenosynovitis [1].
- The presence of an intracompartmental septum does not significantly affect clinical outcomes or complications following endoscopic release for de Quervain's syndrome [42].
- When the extensor pollicis brevis tendon is associated with thumb interphalangeal joint extension, it is likely to reside in a subcompartment of the first dorsal compartment, particularly in patients with de Quervain's disease [53].
- De Quervain's disease may be secondary to extensor pollicis brevis entrapment [29].
Patient Factors and Perception
- Addressing misconceptions about the consequences of de Quervain's tenosynovitis and symptom duration allows patients to make informed decisions about treatment [9].
- Growth hormone abuse is associated with a more recalcitrant form of de Quervain tenosynovitis that does not respond well to nonsurgical treatment, increasing the likelihood of surgical decompression [79].
Treatment
Non-Operative Management
- One or two local injections of 1 ml triamcinolone acetonide 10 mg/ml provided by general practitioners leads to short-term improvement in participants with de Quervain's tenosynovitis compared to placebo [26].
- Corticosteroid injections are a useful treatment for de Quervain's tenosynovitis, leading to treatment success 73.4% of the time within 2 injections [22].
- A single cortisone injection was effective in alleviating symptoms of de Quervain tendinopathy in 82% of patients, with over half remaining symptom-free for at least 12 months [67].
- The combined technique of corticosteroid injection and thumb spica casting was better than injection alone in the treatment of de Quervain tenosynovitis in terms of treatment success and functional outcomes [68].
- Patients with diabetes mellitus have a decreased probability of success following a single corticosteroid injection for de Quervain tenosynovitis in comparison to nondiabetic patients, but the effectiveness of each additional injection does not appear to diminish [40].
- Ultrasound should be considered to improve the treatment outcome of corticosteroid injections and can also be useful as a diagnostic tool in the management of de Quervain’s disease [18].
- Pain and clinical outcomes significantly improved after corticosteroid injection in de Quervain's disease [49].
- Preliminary results indicate that betamethasone is a superior treatment for De Quervain's tenosynovitis compared to ketorolac injection [70].
- Splinting has not been shown to provide long-lasting relief beyond allowing the joints to rest in an immobilized position [65].
- Iontophoresis with dexamethasone may improve functional outcomes, while therapeutic pulsed ultrasound may be effective in decreasing pain in patients with de Quervain's tenosynovitis [69].
Operative Management
- The release of the first extensor compartment for refractory de Quervain's disease resulted in good clinical outcomes with minimal morbidity [24].
- An oblique incision coursing along the extensor brevis tendon is preferred for surgical release, though transverse, oblique, or longitudinal incisions are also satisfactory [35].
- The longitudinal incision for release of the first extensor compartment offers the advantage of easy identification of the compartment, more complete releases of tendon sheath and peritendinous adhesions, and less risk of palmar subluxation of tendons [10].
- The first dorsal compartment should be opened on its dorsoulnar side during surgical release [35].
- A volarly based retinacular flap must remain over the released tendons to prevent volar tendon subluxation [35].
- Symptomatic palmar tendon subluxation after surgical release can be avoided by leaving a palmarly based flap of extensor retinaculum to prevent palmar subluxation of the tendons with wrist flexion [15].
- Volar subluxation of the tendons of the first dorsal compartment after surgery can be treated with a distally based flap of the brachioradialis tendon [48].
- One portal endoscopic assisted release of the extensor compartment is an effective and safe minimal invasive procedure with similar complication rates reported previously in open and endoscopic procedures in patients with de Quervain's disease who are unresponsive to non-operative treatments [31].
- Endoscopic release of the extensor compartment seems to be an effective and safe procedure in patients with de Quervain's disease who are unresponsive to nonoperative treatments, despite a little increase in operation time [41].
- Pulley reconstruction should be considered part of the surgical treatment for de Quervain tenosynovitis as it gives satisfactory medium-term results [4].
- The failure of an operation in De Quervain tenosynovitis is due to anatomical variations, the involvement of the radial superficial nerve, and the ignorance of another syndrome in the proximity [13].
- Anatomical variations are clinically relevant in the pathophysiology and treatment of De Quervain's tenosynovitis [1].
- Anatomic variations are frequently encountered in recalcitrant cases of de Quervain tenosynovitis, including multiple slips of APL and EPB in its own separate compartment [83].
- First dorsal compartment release during volar approach for distal radius fracture fixation reduces symptoms in patients with pre-existing De Quervain disease compared with no release [75].
Complications
Surgical Complications
- Surgical failure in De Quervain tenosynovitis is attributed to anatomical variations, involvement of the radial superficial nerve, and the failure to diagnose another syndrome in the proximity [13].
- Symptomatic palmar tendon subluxation is a complication of surgical release that can be avoided by leaving a palmarly based flap of extensor retinaculum [15].
- The longitudinal incision for release of the first extensor compartment prevents possible tendon subluxation in the postoperative period [17].
- Endoscopic release for de Quervain's tenosynovitis is associated with fewer superficial radial nerve complications compared with open release [33].
- The longitudinal incision offers a less risk of palmar subluxation of tendons compared to other approaches [10].
Tendon and Structural Complications
- Rupture of the abductor pollicis longus tendon in association with De Quervain’s disease has been reported, with pathogenesis potentially linked to ongoing tendon damage from wear and tear within the stenosed sheath [21].
- Longitudinal split tears of the extensor pollicis brevis tendon have been reported in cases of de Quervain's tenosynovitis [16].
Diagnostic and Associated Pathology
- De Quervain's syndrome may be associated with trauma, extensor carpi ulnaris involvement, ligament instability, or repetitive strain, indicating it may not be an isolated pathology [3].
- Extensor pollicis longus tenosynovitis caused by the EPL's unusual course through the first extensor compartment is a rare condition that mimics de Quervain’s disease [30].
- In cases where constriction involves only the extensor pollicis brevis in a separate compartment, exploration of both compartments is advised to avoid diagnostic error [27].
- The complexities of de Quervain's tendinitis and associated diseases and complications are described to help prevent surgical failures and prolonged disabilities in working women [8].
Recovery
Non-Operative Management
- A single injection of steroid gives complete and lasting relief in 70% of patients with de Quervain's disease, and a further 10% will be cured by a second injection [91].
Operative Management
- Only 34.9% of patients with new stenosing tenosynovitis required surgery within a 2-year follow-up period, with most progressing to surgery within 1 year of presentation [93].
Surgical Technique and Complications
- Pulley reconstruction as part of the surgical treatment for de Quervain tenosynovitis gives satisfactory medium-term results and should be considered part of the surgical treatment [4].
Patient Factors and Prognosis
- More negative perceptions of the consequences of de Quervain's tenosynovitis and worse pain catastrophizing are associated with worse pain and reduced function at baseline in patients awaiting surgical decompression of de Quervain's tenosynovitis [25].
Key Evidence
- [L4] These variations are clinically relevant in the pathophysiology and treatment of De Quervain's tenosynovitis. [1] (10.1016/j.bjps.2016.08.020)
- [L4] According to the limited evidence available, injection of corticosteroids is the only available nonsurgical treatment that can potentially modify the course of de Quervain's tenosynovitis and is therefore the preferred initial treatment. [2] (10.1016/j.jhsa.2008.12.030)
- [L4] [3] (10.1177/1758998315599796)
- [L4] The authors believe the technique gives satisfactory medium-term results and should be considered part of the surgical treatment for de Quervain tenosynovitis. [4] (10.1055/s-0035-1556862)
- [L3] Although considerable improvements in symptom severity and hand function will likely occur in patients with metabolic syndrome, corticosteroid injection for De Quervain tenosynovitis is not as effective in these patients compared with age- and sex-matched controls in terms of functional outcomes and treatment failure. [5] (10.1177/1753193417694112)
- [L3] Wrist radiography does not influence management of patients presenting with de Quervain tendinopathy. [6] (10.1055/s-0037-1606124)
- [L4] Providers should remain cognizant that patients presenting with de Quervain's tenosynovitis may favor initial nonsurgical management. [7] (10.1016/j.jhsg.2024.01.009)
- [L4] The complexities of de Quervain's tendinitis and the diagnosis and treatment of associated diseases and complications are described to help prevent surgical failures and prolonged disabilities in these groups of working women. [8] (10.1016/s0363-5023(87)80204-6)
- [L3] Addressing misconceptions about de Quervain's tenosynovitis in terms of the consequences for patients and how long their symptoms will last should allow patients to make informed decisions about the treatment that best matches their values. [9] (10.1097/corr.0000000000001577)
- [L4] Surgical release of De Quervain's tenosynovitis remains the gold standard treatment, and longitudinal incision offers advantage of easy identification of compartment, more complete releases of tendon sheath and peritendinous adhesions and less risk of palmar subluxation of tendons. [10] (10.1007/s12306-018-0585-1)
- [L4] Surgical intervention is effective as definitive therapy for de Quervain's tenosynovitis, with a cure rate of 91% and 88% of patients indicating full satisfaction. [11] (10.1053/jhsu.1999.1071)
- [L4] We can conclude that the failure of an operation in the De Quervain tenosynovitis is due to anatomical variations, the involvement of the radial superficial nerve, and the ignoration of another syndrome in the proximity. [13] (10.1177/1558944716660555gr)
- [L5] [14] (10.1016/s0363-5023(96)80112-2)
- [L5] This complication can be avoided by leaving a palmarly based flap of extensor retinaculum to prevent palmar subluxation of the tendons with wrist flexion. [15] (10.1016/s0363-5023(84)80017-9)
- [L4] [16] (10.1016/j.jhsa.2014.09.024)
- [L4] In our experience, the longitudinal incision for release of the first extensor compartment for de Quervain tenosynovitis is a safe and effective technique that provides good exposure, protects vital structures, prevents possible tendon subluxation in the postoperative period, and is cosmetically acceptable. [17] (10.1097/01.bth.0000181105.24124.c0)
- [L4] Therefore, ultrasound should not only be considered to improve the treatment outcome, but can also be useful as a diagnostic tool in the management of de Quervain’s disease. [18] (10.1016/j.main.2013.09.002)
- [L4] Though considered as a manifestation of de Quervain's disease by some authors, styloid abnormalities do not affect the outcome of management as proved in this study. [19] (10.1007/s11552-010-9258-8)
- [L4] Triggering or locking in extension is an uncommon symptom in de Quervain’s stenosing tenosynovitis, with a prevalence of 1.3% based on a review of 827 consecutive patients. [20] (10.1053/jhsu.1999.1311)
- [L4] [21] (10.1016/j.jhsb.2005.09.020)
- [L3] This study indicates that corticosteroid injections are a useful treatment for de Quervain's tenosynovitis, leading to treatment success 73.4% of the time within 2 injections. [22] (10.1177/1558944716681976)
- [L4] The release of the first extensor compartment for refractory de Quervain's disease resulted in good clinical outcomes with minimal morbidity. [24] (10.4055/cios.2014.6.4.405)
- [L3] More negative perceptions of the consequences of de Quervain's tenosynovitis and worse pain catastrophizing are associated with worse pain and reduced function at baseline in patients awaiting surgical decompression of de Quervain's tenosynovitis. [25] (10.1097/corr.0000000000000992)
- [L1] One or two local injections of 1 ml triamcinolonacetonide 10 mg/ml provided by general practitioners leads to improvement in the short term in participants with de Quervain's tenosynovitis when compared to placebo. [26] (10.1186/1471-2474-10-131)
- [L4] In cases with symptoms of de Quervain's syndrome where the constriction involves only the extensor pollicis brevis in a separate compartment, exploration of both compartments is advised. [27] (10.2106/00004623-194931040-00019)
- [L1] Corticosteroid injection with a short duration of immobilization remains the primary and effective treatment for de Quervain tenosynovitis. [28] (10.1016/j.jhsa.2024.03.003)
- [L4] We conclude that de Quervain's disease is secondary to EPB entrapment. [29] (10.1016/s0363-5023(98)80160-3)
- [L5] Extensor pollicis longus tenosynovitis caused by the EPL's unusual course through the first extensor compartment is a very rare condition that mimics de Quervain’s disease. [30] (10.1016/j.jhsa.2003.11.012)
- [L4] One portal endoscopic assisted release of the extensor compartment is an effective and safe minimal invasive procedure with similar complication rates reported previously in open and endoscopic procedures in patients with de Quervain's disease who are unresponsive to non-operative treatments. [31] (10.1016/j.aott.2018.10.004)
- [L4] Most informed patients initially elect symptomatic treatment for de Quervain's disease, and most experience symptom resolution within one year. [32] (10.1007/s12593-009-0018-3)
- [L1] Endoscopic release for de Quervain's tenosynovitis seems to provide earlier improvement after surgery, with fewer superficial radial nerve complications and greater scar satisfaction, when compared with open release. [33] (10.1302/0301-620x.95b7.31486)
- [L4] Patients who scored lower than 40 for physical function or higher than 60 for pain interference had significantly increased odds of eventually undergoing surgical release for de Quervain tenosynovitis. [34] (10.1016/j.jhsa.2023.07.005)
- [L3] The new test is a useful clinical tool in the diagnosis of De Quervain's tenosynovitis. [36] (10.1016/j.main.2011.10.017)
- [L1] [38] (10.1002/14651858.cd005616.pub2)
- [L3] [39] (10.1177/1753193415611414)
- [L4] Patients with diabetes mellitus have a decreased probability of success following a single corticosteroid injection for de Quervain tenosynovitis in comparison to nondiabetic patients, but the effectiveness of each additional injection does not appear to diminish. [40] (10.1016/j.jhsa.2022.02.018)
- [L4] Endoscopic release of the extensor compartment seems to be an effective and safe procedure in patients with de Quervain's disease who are unresponsive to nonoperative treatments, despite a little increase in operation time. [41] (10.1016/j.bjps.2011.05.015)
- [L4] The presence of a septum does not significantly affect clinical outcomes or complications following endoscopic release for de Quervain's syndrome. [42] (10.1177/17531934231214137)
- [L5] We describe a case of nonsyndromic congenital fusion of the scaphoid and the trapezium as a cause of tendinitis simulating de Quervain's stenosing tenosynovitis, an association not previously reported. [43] (10.1016/s1297-3203(00)73478-0)
- [L5] As the clinical presentation and X-rays of the wrist were not typical of an osteoid osteoma, only the histological examination led to the correct diagnosis. [45] (10.1016/0266-7681(92)90100-g)
- [L2] Although the success rate for the treatment of De Quervain's tenosynovitis decreases with multiple injections, repeat injections have a high rate of success and are a viable clinical option. [46] (10.1016/j.jhsa.2021.04.018)
- [L4] [48] (10.1016/s0363-5023(10)80007-3)
- [L1] Pain and clinical outcomes significantly improved after corticosteroid injection in de Quervain's disease. [49] (10.1016/j.otsr.2019.11.015)
- [L5] Ultrasound is a useful imaging technique for diagnosing de Quervain's disease and provides important information about anatomic variations within the first extensor compartment. [50] (10.1136/bcr-2021-242173)
- [L4] Ultrasound is a worthwhile preoperative investigation in case of de Quervain's disease. [51] (10.1007/s12593-009-0001-z)
- [L3] The prevalence of a septated first dorsal compartment is considerably higher than previously reported, most notably in patients with De Quervain tenosynovitis. [52] (10.1177/1558944718810864)
- [L4] When it does, particularly in patients with de Quervain's disease, it is likely to reside in a subcompartment of the first dorsal compartment. [53] (10.1016/j.jhsa.2008.12.015)
- [L2] [54] (10.1016/j.jhsa.2008.08.020)
- [L2] [59] (10.1177/1753193412475043)
- [L4] [62] (10.1055/s-0040-1716522)
- [L3] [63] (10.1055/s-0038-1626690)
- [L5] [64] (10.5435/00124635-200712000-00009)
- [L4] [65] (10.1007/s11552-014-9649-3)
- [L4] A single cortisone injection was effective in alleviating symptoms of de Quervain tendinopathy in 82% of patients, with over half remaining symptom-free for at least 12 months. [67] (10.1016/j.jhsa.2014.12.027)
- [L2] The combined technique of corticosteroid injection and thumb spica casting was better than injection alone in the treatment of de Quervain tenosynovitis in terms of treatment success and functional outcomes. [68] (10.1016/j.jhsa.2013.10.013)
- [L4] This study demonstrated that iontophoresis with dexamethasone may improve functional outcomes, while therapeutic pulsed ultrasound may be effective in decreasing pain in patients with de Quervain's tenosynovitis. [69] (10.1016/j.jht.2014.08.032)
- [L1] Preliminary results indicate that betamethasone is a superior treatment for De Quervain's tenosynovitis. [70] (10.1016/j.jhsa.2017.06.086)
- [L4] [72] (10.1177/0363546504268134)
- [L4] In vivo EPB tendon excursion measures have been quantified, and wrist position has been found to have an influence on excursion. [73] (10.1016/j.jht.2017.12.004)
- [L1] The current results demonstrated a significantly greater reduction in de Quervain disease symptoms in the release group compared with the no release group during the short-term follow-up. [75] (10.1016/j.jhsg.2024.03.009)
- [L3] Our results suggest that growth hormone abuse is associated with a more recalcitrant form of de Quervain tenosynovitis that does not respond well to nonsurgical treatment, thus leading to increased likelihood of surgical decompression. [79] (10.1177/0363546509337993)
- [L5] The patient overstressed his wrist through forceful extension during over-zealous weightlifting. [80] (10.1177/1753193419871862)
- [L3] Those subjects demonstrate a significant decrease in maximum velocity in slow fist tasks, highlighting the need for comprehensive assessment to ascertain the full extent of functional limitations that can occur in the setting of hand pathology. [81] (10.1177/1558944717729218)
- [L4] Repeat provocative testing revealed volar tendon translation with wrist flexion, with no pain reported. [85] (10.1097/bth.0000000000000054)
- [L4] A single injection of steroid gives complete and lasting relief in 70% of patients with de Quervain's disease, and a further 10% will be cured by a second injection. [91] (10.1016/s0363-5023(09)91110-8)
- [L2] Only 34.9% of patients with new stenosing tenosynovitis required surgery within a 2-year follow-up period, with most progressing to surgery within 1 year of presentation. [93] (10.1016/j.jhsa.2017.06.088)
- [L2] The anatomical findings are consistent with previous studies, with an expectation to encounter the superficial branch of the radial nerve in more than 50% of patients. [94] (10.1055/s-0039-1688700)
- [L3] The proportion of wrists with a positive EPB entrapment test was significantly higher among those with 2 compartments (18 of 22) than among those with 1 compartment (0 of 4). [97] (10.1053/jhsu.2002.35309)
- [Paper] Operative treatment for distal radius fractures confers a slightly greater risk of developing DeQuervain tenosynovitis within 1 year of injury or surgery. [105] (10.1177/15589447251366456)
- [Paper] There is immense anatomical variation present in the first dorsal compartment of the wrist, supernumerary tendons/tendon slips are commonly found, there is variation of insertion present in the population, septum/aberrant compartment is also present, and bilateral variations are present in the population. [107] (10.1007/s12593-012-0073-z)
References
[1] Surgical anatomy of the first extensor compartment: A systematic review and comparison of normal cadavers vs. De Quervain syndrome patients. Journal of Plastic, Reconstructive & Aesthetic Surgery. 2017. DOI: 10.1016/j.bjps.2016.08.020
[2] Nonsurgical Treatment for de Quervain's Tenosynovitis. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2008.12.030
[3] De Quervain’s syndrome: It may not be an isolated pathology. Hand Therapy. 2015. DOI: 10.1177/1758998315599796
[4] Pulley Reconstruction As Part of the Surgical Treatment for de Quervain Disease: Surgical Technique with Medium-Term Results. Journal of Wrist Surgery. 2015. DOI: 10.1055/s-0035-1556862
[5] RETRACTED: Effects of metabolic syndrome on the functional outcomes of corticosteroid injection for De Quervain tenosynovitis. Journal of Hand Surgery (European Volume). 2017. DOI: 10.1177/1753193417694112
[6] Deferring Routine Wrist Radiography Does Not Affect Management of de Quervain Tendinopathy Patients. Journal of Wrist Surgery. 2017. DOI: 10.1055/s-0037-1606124
[7] De Quervain’s Tenosynovitis: As Seen from the Perspective of the Patient. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2024.01.009
[8] de Quervain's release in working women: A report of failures, complications, and associated diagnoses. The Journal of Hand Surgery. 1987. DOI: 10.1016/s0363-5023(87)80204-6
[9] Are Patient Expectations and Illness Perception Associated with Patient-reported Outcomes from Surgical Decompression in de Quervain’s Tenosynovitis?. Clinical Orthopaedics & Related Research. 2020. DOI: 10.1097/corr.0000000000001577
[10] Functional outcome of De Quervain’s tenosynovitis with longitudinal incision in surgically treated patients. MUSCULOSKELETAL SURGERY. 2019. DOI: 10.1007/s12306-018-0585-1
[11] Patient satisfaction and outcomes of surgery for de Quervain's tenosynovitis. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.1071
[12] Tethered_Thumb_Sign_A_Unique_Observation_in_the_Physical_Examination_of_de_Querv_S0363502313005340. n.d..
[13] Failure of Surgical Treatment in the De Quervain Tenosynovitis. HAND. 2016. DOI: 10.1177/1558944716660555gr
[14] Hemangioma of the extensor pollicis brevis in the first dorsal compartment: An unusual cause of bilateral de Quervain's disease. The Journal of Hand Surgery. 1996. DOI: 10.1016/s0363-5023(96)80112-2
[15] Symptomatic palmar tendon subluxation after surgical release for de Quervain's disease: A case report. The Journal of Hand Surgery. 1984. DOI: 10.1016/s0363-5023(84)80017-9
[16] Longitudinal Split Tear of the Extensor Pollicis Brevis Tendon: Report of 2 Cases. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.09.024
[17] Longitudinal Incision in Surgical Release of De Quervain Disease. Techniques in Hand & Upper Extremity Surgery. 2005. DOI: 10.1097/01.bth.0000181105.24124.c0
[18] The role of ultrasound-guided triamcinolone injection in the treatment of De Quervain's disease: Treatment and a diagnostic tool?. Chirurgie de la Main. 2013. DOI: 10.1016/j.main.2013.09.002
[19] Does Radial Styloid Abnormality in de Quervain's Disease Affect the Outcome of Management?. HAND. 2010. DOI: 10.1007/s11552-010-9258-8
[20] Extensor triggering in de Quervain's stenosing tenosynovitis. The Journal of Hand Surgery. 1999. DOI: 10.1053/jhsu.1999.1311
[21] Abductor Pollicis Longus Tendon Rupture in De Quervain’s Disease. Journal of Hand Surgery. 2006. DOI: 10.1016/j.jhsb.2005.09.020
[22] Effectiveness of Corticosteroid Injections for Treatment of de Quervain’s Tenosynovitis. HAND. 2016. DOI: 10.1177/1558944716681976
[24] Surgical Release of the First Extensor Compartment for Refractory de Quervain's Tenosynovitis: Surgical Findings and Functional Evaluation Using DASH Scores. Clinics in Orthopedic Surgery. 2014. DOI: 10.4055/cios.2014.6.4.405
[25] Which Psychological Variables Are Associated With Pain and Function Before Surgery for de Quervain’s Tenosynovitis? A Cross-sectional Study. Clinical Orthopaedics & Related Research. 2019. DOI: 10.1097/corr.0000000000000992
[26] Randomised controlled trial of local corticosteroid injections for de Quervain's tenosynovitis in general practice. BMC Musculoskeletal Disorders. 2009. DOI: 10.1186/1471-2474-10-131
[27] AN UNUSUAL FORM OF DE QUERVAINʼS SYNDROME. The Journal of Bone & Joint Surgery. 1949. DOI: 10.2106/00004623-194931040-00019
[28] Advancements in de Quervain Tenosynovitis Management: A Comprehensive Network Meta-Analysis. The Journal of Hand Surgery. 2024. DOI: 10.1016/j.jhsa.2024.03.003
[29] Limited surgical treatment of de quervain's disease: Decompression of only the extensor pollicis brevis subcompartment. The Journal of Hand Surgery. 1998. DOI: 10.1016/s0363-5023(98)80160-3
[30] Extensor pollicis longus tenosynovitis mimicking de quervain’s disease because of its course through the first extensor compartment: a report of 2 cases. The Journal of Hand Surgery. 2004. DOI: 10.1016/j.jhsa.2003.11.012
[31] One portal endoscopic release of the first extensor compartment in de Quervain's disease. Acta Orthopaedica et Traumatologica Turcica. 2020. DOI: 10.1016/j.aott.2018.10.004
[32] Patient-centered care of de Quervain’s disease. Journal of Hand and Microsurgery. 2009. DOI: 10.1007/s12593-009-0018-3
[33] Endoscopicversusopen release in patients with de Quervain’s tenosynovitis. The Bone & Joint Journal. 2013. DOI: 10.1302/0301-620x.95b7.31486
[34] Association of Patient-Reported Outcomes Measurement Information System Measures With Injection and Surgical Treatment Response in Patients With De Quervain Tenosynovitis. The Journal of Hand Surgery. 2023. DOI: 10.1016/j.jhsa.2023.07.005
[35] Campbell S Operative Orthopaedics 4 Volume Set. EXCISION OF NECROTIC MUSCLES COMBINED WITH NEUROLYSIS OF MEDIAN AND ULNAR NERVES FOR SEVERE CONTRACTURE > SURGICAL TREATMENT OF DE QUERVAIN DISEASE.
[36] Évaluation de la première loge des extenseurs à fin diagnostique : un nouveau test dans le diagnostic de la ténosynovite de De Quervain. Chirurgie de la Main. 2011. DOI: 10.1016/j.main.2011.10.017
[38] Corticosteroid injection for de Quervain's tenosynovitis. Cochrane Database of Systematic Reviews. 2009. DOI: 10.1002/14651858.cd005616.pub2
[39] Presence of an intracompartmental septum detected by ultrasound is associated with the failure of ultrasound-guided steroid injection in de Quervain’s syndrome. Journal of Hand Surgery (European Volume). 2015. DOI: 10.1177/1753193415611414
[40] Effectiveness of Corticosteroid Injections in Diabetic Patients With De Quervain Tenosynovitis. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2022.02.018
[41] Does endoscopic release of the first extensor compartment have benefits over open release in de Quervain’s disease?. Journal of Plastic, Reconstructive & Aesthetic Surgery. 2011. DOI: 10.1016/j.bjps.2011.05.015
[42] Prediction of an intracompartmental septum and its effect on outcomes of endoscopic release for de Quervain’s syndrome. Journal of Hand Surgery (European Volume). 2023. DOI: 10.1177/17531934231214137
[43] Congenital synostosis between the scaphoid and the trapezium as a cause of tenosynovitis simulating de Quervain's disease. Chirurgie de la Main. 2000. DOI: 10.1016/s1297-3203(00)73478-0
[45] Osteoid Osteoma of the Radial Styloid Mimicking Stenosing Tenosynovitis. Journal of Hand Surgery. 1992. DOI: 10.1016/0266-7681(92)90100-g
[46] De Quervain Tenosynovitis: An Evaluation of the Epidemiology and Utility of Multiple Injections Using a National Database. The Journal of Hand Surgery. 2022. DOI: 10.1016/j.jhsa.2021.04.018
[48] Tendon subluxation after de Quervain's release: Treatment by brachioradialis tendon flap. The Journal of Hand Surgery. 1991. DOI: 10.1016/s0363-5023(10)80007-3
[49] Prospective randomized comparison of ultrasonography-guided and blind corticosteroid injection for de Quervain's disease. Orthopaedics & Traumatology: Surgery & Research. 2020. DOI: 10.1016/j.otsr.2019.11.015
[50] Type II de Quervain’s disease: depicting subcompartmentalisation with ultrasound. BMJ Case Reports. 2021. DOI: 10.1136/bcr-2021-242173
[51] Preoperative ultrasound in de Quervain’s disease: an investigation worth doing. Journal of Hand and Microsurgery. 2009. DOI: 10.1007/s12593-009-0001-z
[52] Prevalence of a Septated First Dorsal Compartment Among Patients With and Without De Quervain Tenosynovitis: An In Vivo Anatomical Study. HAND. 2018. DOI: 10.1177/1558944718810864
[53] Thumb Interphalangeal Joint Extension By the Extensor Pollicis Brevis: Association With a Subcompartment and de Quervain's Disease. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2008.12.015
[54] Incidence of de Quervain's Tenosynovitis in a Young, Active Population. The Journal of Hand Surgery. 2009. DOI: 10.1016/j.jhsa.2008.08.020
[55] Treatment of de Quervain tenosynovitis. A prospective study of the results of injection of steroids and immobilization in a splint.. The Journal of bone and joint surgery. American volume. 1991.
[59] The wrist hyperflexion and abduction of the thumb (WHAT) test: a more specific and sensitive test to diagnose de Quervain tenosynovitis than the Eichhoff’s Test. Journal of Hand Surgery (European Volume). 2013. DOI: 10.1177/1753193412475043
[62] Are Plain X-Rays Necessary in the Diagnosis of De Quervain's Tenosynovitis?. Journal of Wrist Surgery. 2020. DOI: 10.1055/s-0040-1716522
[63] Finkelstein's Test Is Superior to Eichhoff's Test in the Investigation of de Quervain's Disease. Journal of Hand and Microsurgery. 2018. DOI: 10.1055/s-0038-1626690
[64] de Quervain Tenosynovitis of the Wrist. Journal of the American Academy of Orthopaedic Surgeons. 2007. DOI: 10.5435/00124635-200712000-00009
[65] De Quervain's Tenosynovitis: A Review of the Rehabilitative Options. HAND. 2014. DOI: 10.1007/s11552-014-9649-3
[67] de Quervain Tendinopathy: Survivorship and Prognostic Indicators of Recurrence Following A Single Corticosteroid Injection. The Journal of Hand Surgery. 2015. DOI: 10.1016/j.jhsa.2014.12.027
[68] Corticosteroid Injection With or Without Thumb Spica Cast for de Quervain Tenosynovitis. The Journal of Hand Surgery. 2014. DOI: 10.1016/j.jhsa.2013.10.013
[69] Effective Conservative Treatments for De Quervain's Tenosynovitis: A Retrospective Study. Journal of Hand Therapy. 2016. DOI: 10.1016/j.jht.2014.08.032
[70] Betamethasone Versus Ketorolac Injection for the Treatment of De Quervain's Tenosynovitis: A Double-Blind Randomized Clinical Trial. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.06.086
[72] De Quervain Disease in Volleyball Players. The American Journal of Sports Medicine. 2005. DOI: 10.1177/0363546504268134
[73] Ultrasound assessment of extensor pollicis brevis tendon excursion in different wrist positions in healthy people. Journal of Hand Therapy. 2019. DOI: 10.1016/j.jht.2017.12.004
[75] First Dorsal Compartment Release During Volar Approach for Distal Radius Fracture Fixation Reduces Symptoms in Patients With Pre-Existing De Quervain Disease. Journal of Hand Surgery Global Online. 2024. DOI: 10.1016/j.jhsg.2024.03.009
[79] Abuse of Growth Hormone Increases the Risk of Persistent de Quervain Tenosynovitis. The American Journal of Sports Medicine. 2009. DOI: 10.1177/0363546509337993
[80] Dorsal tendon dislocation after de Quervain's release and its surgical management: a case report. Journal of Hand Surgery (European Volume). 2019. DOI: 10.1177/1753193419871862
[81] Dynamic Functional Assessment of Hand Motion Using an Animation Glove: The Effect of Stenosing Tenosynovitis. HAND. 2017. DOI: 10.1177/1558944717729218
[83] Miller S Review Of Orthopaedics. 2. Flexor tendon injury > 5. de Quervain tenosynovitis (Fig. 7.35).
[85] Radial Ridge Excision for Symptomatic Volar Tendon Subluxation Following de Quervain’s Release. Techniques in Hand & Upper Extremity Surgery. 2014. DOI: 10.1097/bth.0000000000000054
[91] De Quervain's disease: Surgical or nonsurgical treatment. The Journal of Hand Surgery. 1990. DOI: 10.1016/s0363-5023(09)91110-8
[93] A Prospective Study of Risk Modeling for Stenosing Tenosynovitis. The Journal of Hand Surgery. 2017. DOI: 10.1016/j.jhsa.2017.06.088
[94] A Prospective Evaluation of the Anatomy of the First Dorsal Compartment in Patients Requiring Surgery for De Quervain's Tenosynovitis. Journal of Wrist Surgery. 2019. DOI: 10.1055/s-0039-1688700
[97] The extensor pollicis brevis entrapment test in the treatment of de Quervain's disease. The Journal of Hand Surgery. 2002. DOI: 10.1053/jhsu.2002.35309
[105] Incidence of DeQuervain Tenosynovitis After Distal Radius Fractures. HAND. 2025. DOI: 10.1177/15589447251366456
[107] A Cadaveric Study of the First Dorsal Compartment of the Wrist and Its Content Tendons: Anatomical Variations in the Indian Population. Journal of Hand and Microsurgery. 2012. DOI: 10.1007/s12593-012-0073-z