यह ऑपरेशन क्यों सुझाया गया है
डॉ. कीरन हिरपरा, माटर प्राइवेट हॉस्पिटल, रॉकहैम्पटन में ऊपरी अंग (कंधे से हाथ तक) के सर्जन हैं, और वे इलाज को आपकी ख़ास चोट के अनुसार तय करते हैं। मरीज़ों को आमतौर पर उनके जीपी (आपके फैमिली डॉक्टर) हमारे क्लिनिक में रेफ़र करते हैं; अगर किसी फिजियोथेरेपिस्ट ने आपको हमसे मिलने की सलाह दी है, तब भी मेडिकेयर रिबेट (मेडिकेयर से मिलने वाली राशि) पाने के लिए आपको अपने जीपी से रेफ़रल लेना होगा। आपके अपॉइंटमेंट पर हम आपकी पूरी जानकारी लेते हैं, आपके हाथ की जांच करते हैं, और यह समझने के लिए कि क्या हुआ है, ज़रूरत हो तो स्कैन या एक्स-रे करवाते हैं।
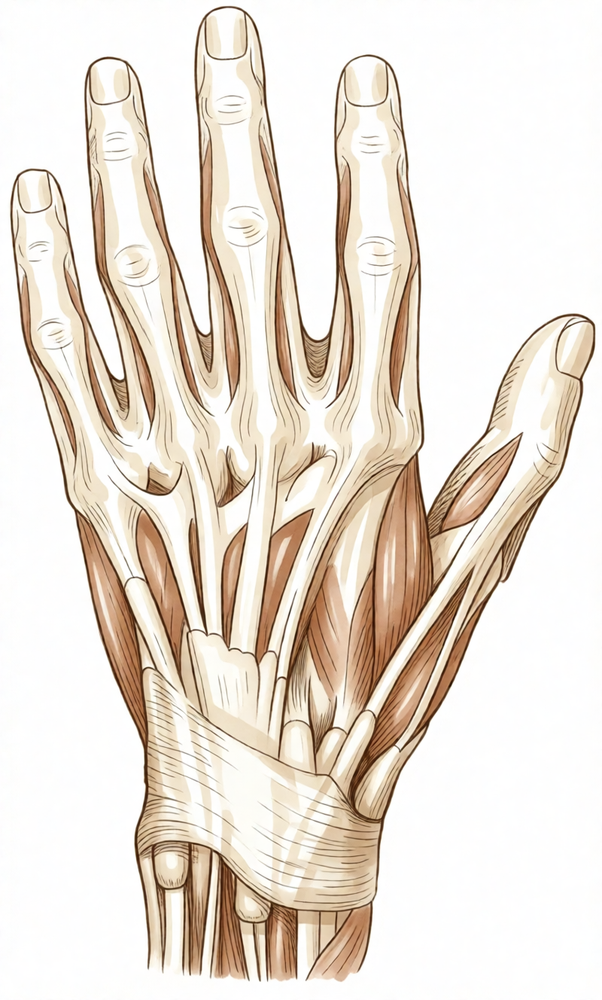
एक्सटेंसर टेंडन (कंडरा) आपके हाथ और उंगलियों के पिछले हिस्से पर मौजूद वे डोरियां हैं जो उन्हें सीधा करती हैं। ये किसी कट से कट सकते हैं, कुचलने वाली चोट या खेल की चोट से फट सकते हैं, या किसी फ्रैक्चर के बाद पूरी तरह फट (रप्चर) सकते हैं। इनमें से कई चोटों, जैसे मैलेट फिंगर, का इलाज बिना सर्जरी के स्प्लिंट से किया जाता है। दूसरी चोटों में रिपेयर (टेंडन को वापस जोड़ना) की ज़रूरत होती है, ख़ासकर खुले कट, लंबे समय से चले आ रहे फटाव, या ऐसी चोटें जिनमें टेंडन को बहुत ज़्यादा नुकसान पहुंचा हो। हम सर्जरी पर तब विचार करते हैं जब स्प्लिंट से पर्याप्त सुधार न हुआ हो, या तुरंत तब करते हैं जब चोट ताज़ा हो और टेंडन अपने आप नहीं जुड़ेगा। उद्देश्य है टेंडन की लंबाई और ताकत वापस लाना, ताकि आपकी उंगली या अंगूठा फिर से सीधा हो सके और आपका हाथ बिना दर्द के काम कर सके।
ऑपरेशन से पहले
जब आपका ऑपरेशन तय हो जाएगा, तो हम आपको आने से पहले के दिनों में पालन करने के लिए साफ़ निर्देश देंगे। आपको सर्जरी से सात घंटे पहले खाना और पीना बंद करना होगा। हम सात घंटे इसलिए कहते हैं ताकि अगर ऑपरेशन थिएटर की सूची जल्दी चल रही हो तो आपकी बारी पहले आ सके। आपके सर्जन बताएंगे कि आपकी सामान्य दवाओं में से कौन-सी बंद करनी हैं और कौन-सी लेते रहनी हैं, इसलिए आप जो कुछ भी लेते हैं उसकी लिखी हुई सूची साथ लाएं, जिसमें खून पतला करने वाली कोई भी दवा शामिल हो। ऑपरेशन के बाद आपको घर ले जाने के लिए किसी गाड़ी चलाने वाले का इंतज़ाम कर लें, क्योंकि आप ख़ुद गाड़ी नहीं चला पाएंगे। ढीले, आरामदायक कपड़े पहनें जिनकी आस्तीनें आसानी से उतर सकें। ज़्यादातर लोगों को और कोई तैयारी नहीं करनी होती। अगर आपको दूसरी बीमारियां हैं, तो आपको खून की जांच या एनेस्थेटिस्ट (बेहोशी के डॉक्टर), यानी वह डॉक्टर जो एनेस्थीसिया देते हैं, से जांच की ज़रूरत पड़ सकती है।
ऑपरेशन के दिन
आप अस्पताल की सर्जिकल एडमिशन यूनिट में आएंगे, जहां आपका नाम दर्ज किया जाता है और आपको ऑपरेशन थिएटर के लिए तैयार किया जाता है। वहां आप एनेस्थेटिस्ट से मिलेंगे। यह ऑपरेशन जनरल एनेस्थीसिया (जिसमें आप पूरी तरह बेहोश रहते हैं) में किया जाता है। ऑपरेशन के बाद दर्द से राहत के लिए कभी-कभी रीजनल नर्व ब्लॉक (हाथ या बांह को सुन्न करने का इंजेक्शन) भी दिया जाता है; एनेस्थेटिस्ट उसी दिन आपसे इस पर बात करेंगे। इसके बाद आपको ऑपरेशन थिएटर में ले जाया जाता है, जहां ऑपरेशन किया जाता है। बाद में आप रिकवरी एरिया में जागेंगे, जहां एनेस्थीसिया का असर खत्म होने तक नर्सें आप पर नज़र रखती हैं। जब आपकी हालत स्थिर हो जाएगी, तो ऑपरेशन के प्रकार और आपकी रिकवरी के अनुसार आप या तो वार्ड में जाएंगे या घर जाएंगे।
ऑपरेशन में क्या किया जाता है
सही-सही कदम इस पर निर्भर करते हैं कि टेंडन कहां और कितना फटा है। एक्सटेंसर टेंडन हाथ और उंगलियों के पिछले हिस्से पर त्वचा के ठीक नीचे चलते हैं, इसलिए आपके सर्जन आमतौर पर प्रभावित उंगली या हाथ के पिछले हिस्से पर एक चीरे से चोट तक पहुंच सकते हैं। अगर त्वचा को भी चोट लगी थी, तो पहले खराब हुए ऊतक को साफ़ करके हटाया जाता है, और उस हिस्से को ढकने के लिए स्वस्थ त्वचा लाई जा सकती है।
टेंडन के सिरे मिल जाने पर आपके सर्जन उन्हें सिलकर वापस जोड़ते हैं। रिपेयर को इतना मज़बूत बनाया जाता है कि वह बाद में आपके हाथ से की जाने वाली शुरुआती हरकतों को सह सके। अगर टेंडन का कोई हिस्सा गायब हो या सिलने के लिए बहुत ज़्यादा खराब हो, तो इसके बजाय उस खाली जगह को जोड़ा जा सकता है। यह ऐसी उंगली से लिए गए टेंडन के टुकड़े से किया जा सकता है जिसे बचाया नहीं जा सकता, ग्राफ्ट (शरीर के दूसरे हिस्से से लिया गया ऊतक) से, या पास के किसी टेंडन को खिसकाकर फटे हुए टेंडन का काम उसे सौंपकर। आपके सर्जन टेंडन की प्राकृतिक लंबाई वापस लाने का प्रयास करते हैं, क्योंकि बहुत ढीला या बहुत कसा हुआ छोड़ा गया टेंडन उंगली को ठीक से सीधा नहीं करेगा।
चीरे को टांकों से बंद किया जाता है और ड्रेसिंग (घाव की पट्टी) से ढका जाता है। आप अपने हाथ की देखभाल के लिखे हुए निर्देशों के साथ घर जाएंगे।
इसके बाद जो होता है, वह रिपेयर जितना ही ज़रूरी है। कुछ रिपेयर में ऐसे स्प्लिंट की ज़रूरत होती है जो उंगली को स्थिर रखे, जबकि दूसरों में पहले कुछ सप्ताह के भीतर ही शुरुआती, सुरक्षित हिलाना-डुलाना शुरू कर दिया जाता है। एक तरीके में पहले दो सप्ताह में 30 डिग्री तक ख़ुद से हिलाने की अनुमति होती है, जो तीसरे सप्ताह में बढ़कर 40 डिग्री और चौथे सप्ताह में 50 डिग्री हो जाती है। आपके सर्जन योजना को आपकी चोट के अनुसार तय करेंगे और आपको साफ़-साफ़ बताएंगे कि आप क्या कर सकते हैं और क्या नहीं।
ऑपरेशन के बाद
आप रिकवरी एरिया में जागेंगे, जहां एनेस्थीसिया का असर खत्म होने तक नर्सें आप पर नज़र रखती हैं। आपके हाथ पर ड्रेसिंग होगी और आपकी चोट के अनुसार वह स्प्लिंट में रखा हो सकता है। ऑपरेशन थिएटर से निकलने से पहले ही दर्द से राहत की योजना बना ली जाती है, और किसी भी समय दर्द हो तो आप नर्सों को बता सकते हैं। पहले 24 घंटे किसी को आपके साथ रहना चाहिए। ज़्यादातर लोग जागने के कुछ ही समय बाद सामान्य रूप से चलने-फिरने लगते हैं; ऑपरेशन आपके हाथ का हुआ है, पैरों का नहीं। आपकी टीम बताएगी कि आप उसी दिन घर जाएंगे या एक रात अस्पताल में रुकेंगे। हम ड्रेसिंग को लगभग 10 दिन तक लगी रहने देते हैं; जब तक हम न कहें, कृपया उससे पहले इसे न हटाएं। जब हम आपसे मिलते हैं तब हम इसे बदलते या हटाते हैं।
ठीक होने की प्रक्रिया
पहले कुछ दिनों और सप्ताहों तक आपके हाथ में दर्द और सूजन रहेगी। यह सामान्य है। हाथ को तकियों पर ऊपर रखने से, सोते समय भी, सूजन कम होने में मदद मिलती है। आपकी टीम के बताए अनुसार साधारण दर्द निवारक दवा आमतौर पर तकलीफ़ कम कर देती है।
आपकी ड्रेसिंग लगभग 10 दिन तक लगी रहती है। आपकी चोट के अनुसार, आप ऐसा स्प्लिंट पहन सकते हैं जो उंगली को स्थिर रखे, या आपको शुरुआती सुरक्षित हिलाना-डुलाना शुरू कराया जा सकता है। अगर शुरुआती हिलाना-डुलाना आपकी योजना का हिस्सा है, तो आपको साफ़-साफ़ दिखाया जाएगा कि उंगली को कितना मोड़ना और सीधा करना है और कितनी बार। शुरुआत में हरकतें छोटी होती हैं और जैसे-जैसे रिपेयर मज़बूत होता है, वे बढ़ती जाती हैं। रिहैबिलिटेशन एक्सटेंड रिहैबिलिटेशन की हैंड थेरेपिस्ट (हाथ की विशेषज्ञ थेरेपिस्ट) रूबी डूलन के साथ होता है। वे आपकी एक्सरसाइज़ में मार्गदर्शन करेंगी और आपको जिस भी स्प्लिंट की ज़रूरत हो, उसे बनाएंगी।
घर पर आप रोज़ के ज़्यादातर ऐसे काम कर सकते हैं जिनसे हाथ पर ज़ोर न पड़े। जब तक आपके थेरेपिस्ट अनुमति न दें, तब तक आपको भारी चीज़ उठाने, कसकर पकड़ने और ऐसी किसी भी चीज़ से बचना होगा जिससे रिपेयर पर चोट लग सकती हो। जब तक हम घाव की जांच न कर लें, हाथ को साफ़ और सूखा रखें। जैसे-जैसे सूजन कम होती है और हिलना-डुलना वापस आता है, एक्सरसाइज़ आसान होती जाती हैं और उंगली ज़्यादा आसानी से सीधी होने लगती है।
ठीक होने का समय हर व्यक्ति में अलग होता है। आपका समय अलग हो सकता है, और हर फॉलो-अप जांच में आपके सर्जन और हैंड थेरेपिस्ट आपका मार्गदर्शन करेंगे।
क्या समस्याएं हो सकती हैं
ज़्यादातर मरीज़ अच्छी तरह ठीक होते हैं, लेकिन कभी-कभी समस्याएं हो सकती हैं। आपके सर्जन और टीम आप पर बारीकी से नज़र रखते हैं, ताकि किसी भी समस्या का जल्दी पता चल सके।
इस सर्जरी के बाद सबसे आम समस्या जकड़न है। हो सकता है उंगली पूरी तरह सीधी न हो या पूरी मुट्ठी बनाने जितनी न मुड़े, और पकड़ की ताकत पहले से कमज़ोर रह सकती है। ऐसा तब होता है जब हाथ को स्थिर रखे जाने के दौरान टेंडन अपने आसपास के ऊतक से निशान वाले ऊतक के ज़रिये चिपक जाता है। आपके थेरेपिस्ट हर मुलाकात में इस पर नज़र रखेंगे और आपकी एक्सरसाइज़ में बदलाव करेंगे। अगर हिलना-डुलना बढ़ना रुक जाए या उंगली लगातार ज़्यादा कसी हुई महसूस हो, तो इंतज़ार करने के बजाय अपनी अगली फॉलो-अप जांच में इसके बारे में बताएं।
कभी-कभी बाकी सब ठीक होने पर भी उंगली को सीधा करने की थोड़ी ताकत कम हो जाती है। आप देख सकते हैं कि उंगली सीधी करने की कोशिश करने पर वह अपनी पड़ोसी उंगलियों से थोड़ी नीचे रहती है, या हथेली तक पूरी तरह नहीं मुड़ती। इसे एक्सटेंसर लैग कहते हैं। यह जानना अच्छा है कि ऐसा हो सकता है, ख़ासकर अगर इलाज से पहले चोट पुरानी हो चुकी थी। फॉलो-अप जांच में इसके बारे में बताएं, ताकि आपके थेरेपिस्ट इस पर काम कर सकें।
रिपेयर ख़ुद भी नाकाम हो सकता है। अगर आपको अचानक 'पॉप' जैसा झटका महसूस हो, या जो उंगली अच्छी तरह सीधी हो रही थी वह अचानक फिर से नीचे लटक जाए, तो तुरंत क्लिनिक से संपर्क करें। अगले अपॉइंटमेंट का इंतज़ार न करें।
संक्रमण असामान्य है, लेकिन इस पर जल्दी ध्यान देना ज़रूरी है। ऐसे दर्द पर नज़र रखें जो कम होने के बजाय लगातार बढ़ता जाए, घाव से बाहर की ओर फैलती लाली, कम होने के बजाय बढ़ती सूजन, या टांकों से रिसता कोई भी तरल। दर्द वाले हाथ के साथ बुखार भी चेतावनी का संकेत है। अगर आपको इनमें से कुछ भी दिखे, तो उसी दिन क्लिनिक को फ़ोन करें, या अगर क्लिनिक का समय खत्म हो चुका हो तो इमरजेंसी विभाग जाएं।
अगर बाद में निशान में फंसे टेंडन को छुड़ाने के लिए सर्जरी की ज़रूरत पड़े, तो इसे टेनोलाइसिस कहते हैं। यह मूल योजना का हिस्सा नहीं है, लेकिन अगर थेरेपी से जकड़न में सुधार न हो तो यह एक विकल्प है। आपके सर्जन इस पर आपसे तभी बात करेंगे जब आपका हिलना-डुलना एक स्तर पर आकर रुक जाए।
अगर आप विस्तार से जानना चाहते हैं, तो इस पेज पर जटिलताओं की तालिका में आम दरें दी गई हैं।
हमें कब फ़ोन करें
समस्याओं का जल्दी पता चल जाए तो उन्हें ठीक करना आसान होता है। अगर आपका दर्द कम होने के बजाय लगातार बढ़ रहा हो, या घाव के आसपास की त्वचा ज़्यादा लाल, ज़्यादा गर्म हो जाए या उससे तरल रिसने लगे, तो हमें फ़ोन करें। अगर आपको बुखार जैसा महसूस हो, आपकी उंगलियां या हाथ सुन्न हो जाएं, या आप उंगली को बिल्कुल भी न हिला पाएं, तो हमें फ़ोन करें। अगर आपको अपनी पिंडली में अचानक सूजन और दर्द दिखे, या आपकी सांस फूलने लगे, तो इमरजेंसी विभाग जाएं। अगर जो उंगली अच्छी तरह सीधी हो रही थी वह अचानक नीचे लटक जाए, या आपको 'पॉप' जैसा झटका महसूस हो, तो तुरंत हमें फ़ोन करें।
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Anatomy & Pathophysiology
General Hand Architecture
- The hand is composed of 19 bones, 17 articulations, and 19 muscles situated entirely within the hand [2].
- Approximately the same number of tendons activated by forearm muscles are present in the hand [2].
- The hand functions efficiently only if the proximal joints of the limb are stable and yet mobile [2].
- The dorsal aspect of the hand is convex, while the anterior, palmar, or volar aspect is concave [2].
- The palmar surface is the functional surface of the hand, while the dorsal surface is usually visible and aesthetically important [2].
- The thumb has a more proximal and lateral position than the four fingers, allowing movement inward and outward from the palm [2].
- When fingers are extended and separated, their tips lie on the circumference of a circle whose center is the head of the third metacarpal [2].
Metacarpal and Longitudinal Arch Anatomy
- The metacarpal arch possesses adaptability due to the mobility of the peripheral metacarpals [7].
- The index metacarpal is the most firmly fixed of the metacarpals [7].
- The ring metacarpal has approximately 10 degrees of mobility in flexion and extension [7].
- The fifth metacarpal has a range of flexion–extension of approximately 20 degrees [7].
- The second to fifth metacarpals are bound together by the deep transverse intermetacarpal ligament, also known as the interglenoid ligament [7].
- The interglenoid ligament ties together the anterior glenoid ligaments of the metacarpophalangeal articulations, known as volar plates [7].
- The metacarpophalangeal joints serve as the keystones of the longitudinal arches of the hand [7].
- The volar plates prevent hyperextension at the metacarpophalangeal joints [7].
- The sagittal bands of the extensor apparatus insert onto the volar plate [7].
- The first annular segment of the pulley of the flexor tendons inserts onto the volar plate [7].
Extensor Tendon and Intrinsic Muscle Anatomy
- There are seven interosseous muscles in the hand, consisting of four dorsal and three volar muscles [4].
- The dorsal interossei are abductors, while the volar interossei are adductors [4].
- The middle finger has two dorsal interossei and no volar interossei because the central axis of the hand lies within it [4].
- Each dorsal interosseous muscle, with the exception of the third, has two muscle heads: a superficial head and a deep head [4].
- The superficial head of the dorsal interosseous muscles abducts and weakly flexes the proximal phalanx [4].
- The deep head of the dorsal interosseous muscles forms the lateral band at the level of the metacarpophalangeal joint [4].
- The deep head of the dorsal interosseous muscles flexes and weakly abducts the proximal phalanx while extending the middle and distal phalanges [4].
- Transverse fibers arch dorsally from each lateral band to join over the dorsum of the finger, flexing the proximal phalanx [4].
- Oblique or spiral fibers from the lateral bands insert onto the lateral tubercles at the base of the middle phalanx to extend the middle phalanx [4].
- The lateral bands are joined by the lateral slips of the extensor tendon to form the conjoined lateral band [4].
- The two conjoined lateral bands unite at the distal third of the middle phalanx to form the terminal tendon [4].
- The terminal tendon inserts at the base of the distal phalanx to extend it [4].
- The volar interossei have only one muscle head and do not insert onto the proximal phalanx [4].
- The flexor digiti quinti brevis forms the ulnar lateral band of the little finger [4].
Cutaneous and Vascular Anatomy
- The dorsal cutaneous unit extends from the wrist to the proximal interphalangeal joints of the fingers and the interphalangeal joint of the thumb [3].
- The dorsal covering of the interphalangeal articulations forms a unique cutaneous unit characterized by considerable excess of skin when digits are in extension [3].
- The palmar integument is subdivided into two zones by the oppositional crease of the thumb [3].
- The skin of the radial portion of the palm covers the thenar eminence and is relatively well vascularized and mobile [3].
- The skin of the ulnar and distal portion of the palm covers the hypothenar eminence and has poor mobility [3].
- The central triangular part of the palm has fixed, poorly vascularized skin that covers the superficial palmar aponeurosis [3].
- Incisions made along the sides of the diamond-shaped cutaneous contact zones in flexed digits present a minimal chance of retraction [3].
- The princeps pollicis artery is the terminal branch of the radial artery that crosses the first intermetacarpal space [8].
- The princeps pollicis artery runs along the ulnar side of the first metacarpal bone and along the volar surface of the adductor muscle [8].
- The princeps pollicis artery divides into two terminal rami, the collateral palmar arteries of the thumb, at the level of the metacarpophalangeal joint flexion crease [8].
- Only 15% of anatomical dissections of the palmar arteries of the thumb fall into the classical "typical" category [8].
- In the second segment of the thumb, the ulnar collateral artery is often easier to dissect than the radial collateral artery [8].
- A subtendinous anastomosis at the level of the neck of the first phalanx acts as a moderator between the two collateral arteries [8].
- The dorsal arteries of the thumb originate from palmar arteries at the level of the first metacarpal and head distally on the side of the two distal phalanges [8].
Investigations
- Clinical evaluation of the injured or dysfunctional hand and wrist requires combining patient history with a careful physical examination to pinpoint or narrow the scope of possible pathologic processes [1].
- Diagnostic tests such as imaging and serum laboratory studies are useful in determining pathology but can be expensive, time consuming, and often nonspecific [1].
- A careful physical examination is essential to direct care and future testing if indicated [1].
- A systematic method to approaching the physical examination of the hand and wrist is essential due to the number of structures in a small space [1].
- An 8-MHz Doppler tone assessment may be used to identify superficially displaced neurovascular bundles when Dupuytren cords lie beneath soft fleshy prominences [11].
- False-negatives are possible with 8-MHz Doppler tone assessment for identifying neurovascular bundles [11].
- Doppler imaging is a promising improvement for identifying structures, but higher resolution imaging technology is needed [11].
- MR assessment of Dupuytren’s disease is hindered by the resolution of current equipment, orientation issues due to multiplanar deformities of the fingers, and lack of intraoperative availability [11].
- MRI is probably most useful in identifying additional pathology such as flexor tendon bowstringing [11].
- MRI may be helpful in providing a quantitative noninvasive measure of cellularity of affected areas, which is an index of biologic activity [11].
- The potential staging tool of MRI for measuring cellularity has not been investigated yet on a large scale [11].
References
[1] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Evaluation, Clinical Examination, and Imaging > Evaluation and Clinical Examination: Current Concepts.
[2] Exam Of The Hand Wrist 2Ed. INTRODUCTION.
[3] Exam Of The Hand Wrist 2Ed. Functional cutaneous units.
[4] Green S Operative Hand Surgery. Interosseous and Hypothenar Muscles.
[7] Exam Of The Hand Wrist 2Ed. The arches of the hand > The metacarpal arch.
[8] Exam Of The Hand Wrist 2Ed. Techniques of investigation of the arterial supply by J P Melki > Vascularization of the thumb > Palmar aspect.
[11] Dupuytren S Disease And Related Hyperproliferative Disorders. 54. The Future of Dupuytren’s Research and Treatment > 54.4 Mechanical Measurements and Procedures > 54.4.4 Imaging.