Patients › Elbow
गोल्फ़र्स एल्बो रिलीज़ (टेंडन के क्षतिग्रस्त जुड़ाव को रिलीज़ करने का ऑपरेशन)
यह ऑपरेशन क्यों सुझाया गया है
डॉ. कीरन हिरपरा, जो माटर प्राइवेट हॉस्पिटल, रॉकहैम्पटन में ऊपरी अंग (कंधे से हाथ तक) के सर्जन हैं, सबसे कम चीर-फाड़ वाले उन विकल्पों से शुरुआत करते हैं जो आपकी समस्या के लिए सही हों। मरीज़ों को आमतौर पर उनके जीपी (आपके फैमिली डॉक्टर) हमारे क्लिनिक में रेफ़र करते हैं; अगर किसी फिजियोथेरेपिस्ट ने आपको हमसे मिलने का सुझाव दिया है, तब भी मेडिकेयर रिबेट पाने के योग्य होने के लिए आपको अपने जीपी से रेफ़रल की ज़रूरत होगी। अपॉइंटमेंट पर हम आपकी बीमारी का इतिहास (हिस्ट्री) लेते हैं, आपकी कोहनी की जांच करते हैं, और निदान पक्का करने के लिए ज़रूरत हो तो इमेजिंग (एक्स-रे या स्कैन) करवाते हैं।
गोल्फ़र्स एल्बो उस जगह का घिसाव और इरिटेशन (टेंडन का परेशान हो जाना) है जहां आपकी कलाई को मोड़ने और पकड़ने वाले टेंडन (कंडरा) आपकी कोहनी के भीतरी हिस्से में हड्डी से जुड़ते हैं। यह अक्सर धीरे-धीरे शुरू होता है, और आराम करने पर भी दर्द बना रह सकता है। हम आमतौर पर बिना ऑपरेशन वाले इलाज से शुरुआत करते हैं, जैसे कामों में बदलाव, फिजियोथेरेपी या हैंड थेरेपी, और स्प्लिंट लगाना। सर्जरी पर तब विचार किया जाता है जब लंबे समय में उससे पर्याप्त सुधार न हुआ हो।
यह ऑपरेशन टेंडन के क्षतिग्रस्त जुड़ाव को हड्डी से रिलीज़ करता है, ताकि हर बार पकड़ने या उठाने पर दर्द वाली जगह खिंचे नहीं। यह उन लोगों को सुझाया जाता है जिनका दर्द इन दूसरे इलाजों से शांत नहीं हुआ है। इस तरह इलाज की गई ज़्यादातर कोहनियों में सुधार होता है, और 72% से 94% मामलों में सफलता बताई गई है। लक्ष्य दर्द से लंबे समय तक राहत और रोज़मर्रा की ज़िंदगी व खेल में आपकी कोहनी का बेहतर इस्तेमाल है।
ऑपरेशन से पहले
सर्जरी से पहले आपको कुछ इमेजिंग करवानी होगी ताकि ऑपरेशन की योजना बनाई जा सके। इसमें एक्स-रे, अल्ट्रासाउंड, या एमआरआई स्कैन शामिल हो सकता है, जो चुंबकों की मदद से आपकी कोहनी के आसपास के नरम ऊतकों को दिखाता है। ज़्यादातर लोगों को किसी और जांच की ज़रूरत नहीं होती। अगर आपको दूसरी बीमारियां हैं, तो आपको खून की जांच या एनेस्थेटिस्ट (बेहोशी के डॉक्टर, जो आपको एनेस्थीसिया देते हैं) से जांच की ज़रूरत पड़ सकती है।
ऑपरेशन के दिन, अपने ऑपरेशन के समय से सात घंटे पहले खाना-पीना बंद कर दें। हम छह के बजाय सात घंटे इसलिए कहते हैं ताकि अगर ऑपरेशन थिएटर की सूची जल्दी चले तो आपकी सर्जरी पहले की जा सके। आपके सर्जन आपको बताएंगे कि आपकी रोज़ की दवाओं में से कौन-सी लेनी हैं और कौन-सी रोकनी हैं। आप जो कुछ भी लेते हैं, उसकी एक सूची साथ लाएं। बाद में आपको गाड़ी से घर ले जाने के लिए किसी का इंतज़ाम करें, और ढीले, आरामदायक कपड़े पहनें।
ऑपरेशन के दिन
आप अस्पताल की सर्जिकल एडमिशन यूनिट में पहुंचते हैं, जहां आपकी भर्ती की जाती है और आपको ऑपरेशन थिएटर के लिए तैयार किया जाता है। फिर आप एनेस्थेटिस्ट से मिलते हैं, जो आपको एनेस्थीसिया देने वाले डॉक्टर हैं। यह ऑपरेशन जनरल एनेस्थीसिया (जिसमें आप पूरी तरह बेहोश रहते हैं) में किया जाता है। ऑपरेशन के बाद दर्द से राहत के लिए कभी-कभी एक रीजनल नर्व ब्लॉक (हाथ या बांह को सुन्न करने का इंजेक्शन) भी जोड़ा जाता है; एनेस्थेटिस्ट उसी दिन आपसे इस पर बात करेंगे। फिर आपको ऑपरेशन थिएटर में ले जाया जाता है, जहां ऑपरेशन किया जाता है।
आप रिकवरी एरिया में जागते हैं, जहां एनेस्थीसिया का असर खत्म होने तक नर्सें आप पर नज़र रखती हैं। स्थिर होने के बाद, प्रक्रिया और आपके ठीक होने के हिसाब से, आप या तो वार्ड में जाते हैं या घर। यह ऑपरेशन करवाने वाले बहुत से लोग उसी दिन घर चले जाते हैं। आपके जाने से पहले, हम आपको समझाएंगे कि अपनी कोहनी की देखभाल कैसे करें और आपका फॉलो-अप अपॉइंटमेंट कब होगा।
ऑपरेशन में क्या किया जाता है
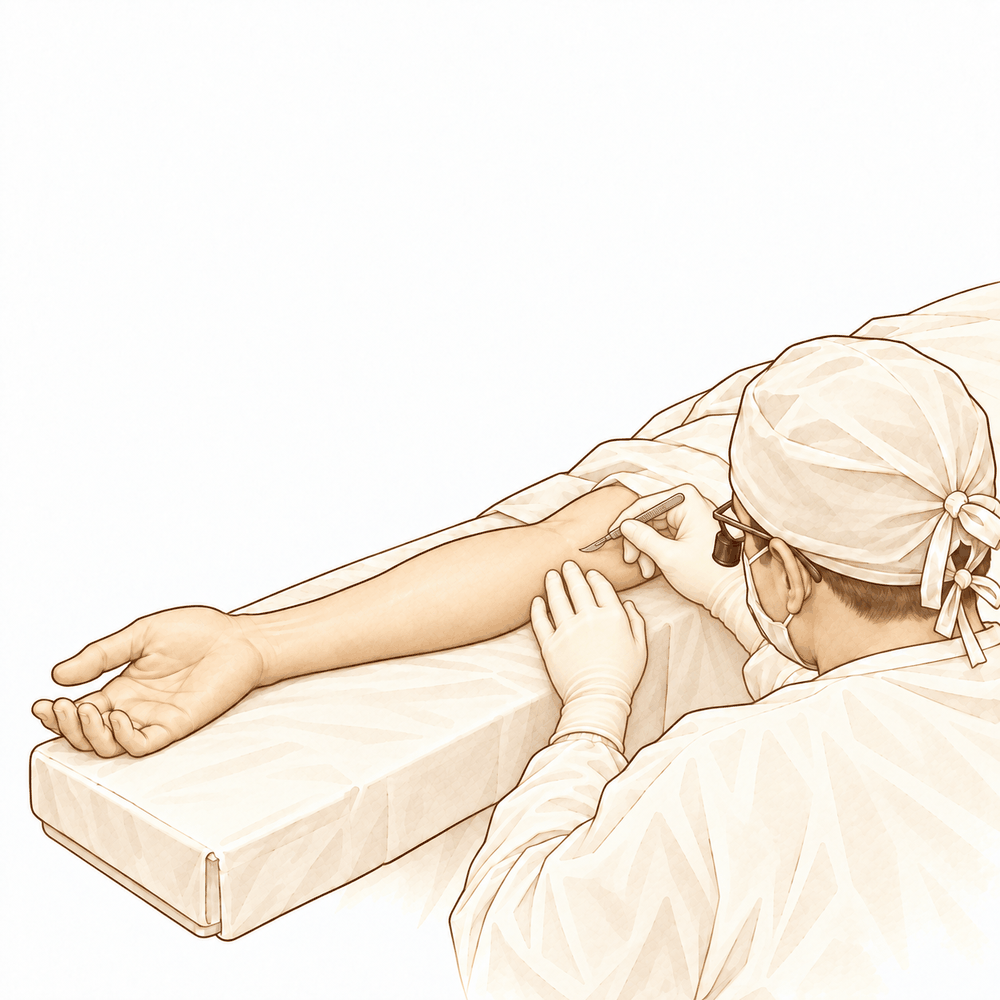
ऑपरेशन आपकी कोहनी के भीतरी हिस्से की उस जगह पर किया जाता है जहां दर्द वाले टेंडन हड्डी से जुड़ते हैं। आपके सर्जन हड्डी के उस उभार के ऊपर एक छोटा चीरा लगाते हैं और टेंडन के क्षतिग्रस्त जुड़ाव को रिलीज़ करते हैं, ताकि हर बार पकड़ने या उठाने पर वह खिंचे नहीं। टेंडन के अंदर का अस्वस्थ, कड़ा रेशेदार ऊतक साफ़ कर दिया जाता है, और स्वस्थ टेंडन को हड्डी पर वापस बैठने और ठीक होने के लिए जगह दी जाती है।
कुछ कोहनियों में थोड़ा अलग तरीक़ा अपनाना पड़ता है। अगर आपकी कोहनी के भीतरी हिस्से से गुज़रने वाली नर्व (तंत्रिका) भी परेशान (इरिटेट) है, तो आपके सर्जन उसे ऊतक की उस सुरंग से रिलीज़ कर सकते हैं (उस पर से दबाव हटा सकते हैं) जिसमें से वह फिसलती है, या हड्डी के उस छोटे टुकड़े को उसकी जगह से हटा सकते हैं जो उस पर दबाव डाल रहा है। अगर जोड़ ख़ुद जकड़ा हुआ है या उसके अंदर ऊतक के ढीले टुकड़े अटक रहे हैं, तो ऑपरेशन इसके बजाय दो या तीन छोटे चीरों से, एक पतले कैमरे से कोहनी के अंदर देखते हुए किया जा सकता है (दूरबीन से ऑपरेशन, यानी आर्थ्रोस्कोपी)।
चीरे को टांकों से बंद किया जाता है और ड्रेसिंग (घाव की पट्टी) से ढक दिया जाता है। पूरा ऑपरेशन आमतौर पर एक घंटे से काफ़ी कम समय में हो जाता है, और ज़्यादातर लोग उसी दिन घर चले जाते हैं।
ऑपरेशन के बाद
आप रिकवरी एरिया में जागते हैं, जहां एनेस्थीसिया का असर खत्म होने तक नर्सें आप पर नज़र रखती हैं। आपकी कोहनी पर ड्रेसिंग लगी होगी, और आराम के लिए आपकी बांह स्लिंग (बांह को सहारा देने वाली पट्टी) में रखी जा सकती है। जागने के कुछ ही देर बाद आप चल-फिर सकते हैं, और आपको जिस भी चीज़ की ज़रूरत हो, नर्सें उसमें आपकी मदद करेंगी। आपके जाने से पहले दर्द से राहत की योजना बना ली जाती है, और टीम आपको समझाएगी कि घर पर किसी भी दर्द को कैसे संभालें। पहले 24 घंटे किसी को आपके साथ रहना चाहिए। आपकी टीम आपको बताएगी कि आप उसी दिन घर जाएंगे या एक रात अस्पताल में रुकेंगे। हम ड्रेसिंग को लगभग 10 दिन तक लगी रहने देते हैं; कृपया उससे पहले इसे न हटाएं, जब तक हम आपसे ऐसा करने को न कहें। जब हम आपको देखते हैं, तब हम इसे बदलते या हटाते हैं।
ठीक होने की प्रक्रिया
पहले कुछ दिनों तक आपकी कोहनी में दर्द रहेगा और सूजन हो सकती है। आराम करना, जब हो सके अपने हाथ को ऊपर उठाकर रखना, और हमारी तय की हुई दर्द निवारक दवा इसे कम करेंगे। जैसे-जैसे ठीक हो रहा ऊतक शांत होता है, दर्द धीरे-धीरे कम हो जाता है।
आप जल्दी ही हल्की हरकत शुरू करेंगे। आपकी हैंड थेरेपिस्ट (हाथ की विशेषज्ञ थेरेपिस्ट), एक्सटेंड रिहैबिलिटेशन की रूबी डूलन, आपके व्यायाम में आपका मार्गदर्शन करेंगी और आपको जिस भी स्प्लिंट की ज़रूरत हो, उसे बनाएंगी। शुरुआती चरणों का लक्ष्य आपकी कोहनी को फिर से पूरी तरह मोड़ना और सीधा करना है। इसके बाद आपकी पकड़ और बांह की ताक़त बढ़ाई जाती है, और यह आपके सामान्य कामों पर लौटने का एक बड़ा हिस्सा है।
घर पर आप जितना आराम से कर सकें, उतना अपनी बांह का इस्तेमाल हल्के कामों के लिए कर सकते हैं। जब तक हम आपको अनुमति न दें, भारी वज़न उठाने से बचें, क्योंकि ठीक हो रहे टेंडन को हड्डी पर वापस बैठने के लिए समय चाहिए। अगर किसी हरकत से तेज़ दर्द हो, तो उसे कम करें और अपने थेरेपिस्ट को बताएं।
ठीक होना हर व्यक्ति में अलग होता है। आपकी समय-सीमा अलग हो सकती है, और हर फॉलो-अप जांच में हम आपके थेरेपिस्ट के साथ मिलकर आपका मार्गदर्शन करेंगे।
क्या समस्याएं हो सकती हैं
ज़्यादातर मरीज़ अच्छी तरह ठीक हो जाते हैं, लेकिन कभी-कभार समस्याएं हो सकती हैं। आपके सर्जन और टीम किसी भी समस्या को जल्दी पकड़ने के लिए आप पर क़रीबी नज़र रखते हैं।
आपकी कोहनी के भीतरी हिस्से से गुज़रने वाली नर्व ऑपरेशन की जगह के पास होती है। अगर सर्जरी के बाद यह परेशान (इरिटेट) हो जाए, तो आपको छोटी उंगली और अनामिका में झुनझुनी, सुई चुभने जैसा एहसास, या सुन्नपन महसूस हो सकता है। अगर ऐसा हो तो अपनी अगली फॉलो-अप जांच में हमें बताएं, या अगर यह गंभीर हो तो उससे पहले ही क्लिनिक को फ़ोन करें।
सर्जरी के बाद कुछ कोहनियां जकड़ जाती हैं। आपको अपनी बांह को पूरी तरह सीधा करने में मुश्किल हो सकती है, या मोड़ते समय कोहनी तंग महसूस हो सकती है। अपने हैंड थेरेपिस्ट के साथ हल्के व्यायाम आमतौर पर मदद करते हैं। अगर कोहनी जकड़ी ही रहे, तो हम फॉलो-अप जांच में हरकत वापस पाने के दूसरे तरीक़ों पर बात कर सकते हैं।
आपकी कलाई को मोड़ने और पकड़ने वाले टेंडन उसी जगह के पास जुड़ते हैं। पकड़ने या उठाने में कमज़ोरी असामान्य है, लेकिन अगर आपको लगे कि आपकी पकड़ अलग महसूस हो रही है, तो अपने अगले अपॉइंटमेंट में यह बात उठाएं।
किसी भी ऑपरेशन में संक्रमण (इन्फेक्शन) का जोखिम होता है। ऐसे गहरे, धड़कते हुए दर्द पर ध्यान दें जो साधारण दर्द निवारक दवाओं से कम न हो, घाव से बाहर की ओर फैलती लाली पर, या ड्रेसिंग से तरल के रिसाव पर। अगर आपको इनमें से कुछ भी दिखे, तो अपनी फॉलो-अप जांच का इंतज़ार करने के बजाय तुरंत क्लिनिक को फ़ोन करें।
कोहनी के पास किसी शिरा (वेन) में खून का थक्का बनना दुर्लभ है, लेकिन इसका जल्दी इलाज ज़रूरी है। बांह में, या किसी पिंडली में, अचानक सूजन और छूने पर दर्द हो, तो इसकी तुरंत जांच होनी चाहिए। अगर ऐसा हो तो इमरजेंसी विभाग जाएं।
कभी-कभार कोहनी फिर से अपनी जगह से खिसक सकती है, या किसी चोट के बाद जोड़ के अंदर हड्डी की सख़्त गांठें बन सकती हैं। कट-कट की आवाज़ या रगड़ (ग्राइंडिंग) जैसा एहसास, या हरकत का अचानक कम हो जाना, हमें बताया जाना चाहिए।
कुछ लोगों को महीनों बाद भी ऑपरेशन की जगह पर हल्का दर्द महसूस होता है। अगर आपका दर्द उस तरह कम नहीं हो रहा जैसा हमने बताया था, तो अपनी फॉलो-अप जांच में यह बात उठाएं ताकि हम इसकी जांच कर सकें।
अगर आप विस्तृत जानकारी चाहते हैं, तो इस पेज पर दी गई जटिलताओं की तालिका में सामान्य दरें दी गई हैं।
हमें कब फ़ोन करें
अगर आपको बुखार हो, या अगर घाव ज़्यादा लाल या सूजा हुआ हो जाए, या उससे तरल रिस रहा हो, तो तुरंत क्लिनिक को फ़ोन करें। अगर आपको अचानक बहुत तेज़ दर्द हो, बांह या पिंडली में अचानक सूजन या छूने पर दर्द हो, या सांस फूल रही हो, तो इमरजेंसी विभाग जाएं। ये खून के थक्के के संकेत हो सकते हैं। अगर आपको अपने हाथ में कुछ महसूस न हो, या आप अपनी बांह बिल्कुल भी न हिला पाएं, तब भी इमरजेंसी विभाग जाएं। अगर छोटी उंगली और अनामिका में हल्की झुनझुनी या सुन्नपन हो, तो हमें फ़ोन करें या अपनी अगली फॉलो-अप जांच में यह बात उठाएं।
Evidence & references
This is the clinical evidence summary written for health professionals. It is technical, and it lists the research this page was built from. You do not need to read it to understand your treatment or to make a decision about it.
Anatomy & Pathophysiology
Bony Anatomy
- The elbow is a trocho-ginglymoid joint consisting of medial and lateral articulations that provide bony stability [3].
- The medial articulation involves the trochlea and the ulna within the greater sigmoid notch, forming the ulnohumeral hinged portion [3].
- The ulnohumeral joint exhibits highly congruent anatomy through almost 180° of articular contact, with the exception of a bare area on the greater sigmoid notch devoid of cartilage [3].
- The coronoid process possesses medial and lateral facets that buttress the trochlea anteriorly [3].
- The sublime tubercle is located just distal and medial to the coronoid and serves as the attachment site for the anterior bundle of the medial ulnar collateral ligament [3].
- The medial epicondyle serves as the attachment site for the origins of the flexor pronator mass and is larger and more posteriorly oriented than the lateral epicondyle [3].
- The lateral articulation involves the capitellum and radial head, forming the radiocapitellar joint [3].
- The radius is held in close approximation to the ulna at the proximal radioulnar joint by the annular ligament [3].
- The area of the ulna that articulates with the margin of the radial head at the proximal radioulnar joint is known as the lesser sigmoid notch [3].
- The radial head is a concave elliptical structure covered with articular cartilage along the radiocapitellar joint and approximately 270° of the articular margin [3].
- The radial head articulates with both the capitellum and the lesser sigmoid notch [3].
- The lateral epicondyle is the origin of the lateral extensor musculature [3].
- The origin of the lateral ulnar collateral ligamentous complex is located just distal to the lateral epicondyle at the geometric center of the radiocapitellar articulation [3].
- The distal humeral articulation is angled 30° from the longitudinal axis [3].
- The anterior humeral line should pass through the center of the axis of rotation [3].
- The axis of rotation is angulated 5° to 7° in the coronal plane relative to the epicondylar axis, with the medial side more distal than the lateral side [3].
- The angulation of the distal humeral articulation accounts for the change from a valgus carrying angle to a more varus position as the elbow is flexed [3].
- There is a high correlation between the size of the radius and capitellum on the left and right sides within the same individual [3].
- The olecranon provides a broad attachment site for the triceps [3].
- The ulna bends approximately 8° medially at 8 cm from the tip of the olecranon [3].
- The articulation to the tip of the coronoid is approximately 30° from the long axis of the ulna in the sagittal plane [3].
Ligaments & Stability
- Elbow stability is determined by primary and secondary stabilizers [1].
- The three primary stabilizers of the elbow are the ulnohumeral articulation, the medial ulnar collateral ligament, and the lateral ulnar collateral ligament complex [1].
- Secondary stabilizers include the radiocapitellar articulation, the common flexor tendon, the common extensor tendon, and the joint capsule [1].
- The medial ulnar collateral ligament is the primary valgus stabilizer of the elbow [4].
- The anterior bundle of the medial ulnar collateral ligament is the most important component for stability [4].
- The posterior bundle of the medial ulnar collateral ligament exhibits the greatest change in length and becomes taut at flexion beyond 120 degrees [4].
- The lateral ulnar collateral ligament acts as a posterolateral stabilizer [4].
- Osborne’s ligament stabilizes the ulnar nerve in the cubital tunnel [4].
- The ligament of Struthers is a variant anatomy arising from the supracondylar process to attach to the medial epicondyle and is a potential site of median nerve compression [4].
- Tensile forces are present at the medial elbow, while compressive forces are present at the lateral elbow [4].
- The joint capsule allows maximum distension at approximately 70 to 80 degrees of flexion [4].
- The anterior capsule attaches at a point approximately 6 mm distal to the tip of the coronoid [4].
- The coronoid tip is an intraarticular structure that is visualized during elbow arthroscopy [4].
Muscles & Tendons
- The brachialis is the strongest elbow flexor and attaches to the coronoid 11 mm distal to the tip [4].
- The biceps brachii inserts at the ulnar margin of the radial tuberosity, with the long head inserting proximally and the short head distally [4].
- The biceps brachii is a powerful supinator of the forearm [4].
- The triceps is the primary elbow extensor and inserts on the olecranon process [4].
- The mobile wad consists of the brachioradialis, extensor carpi radialis longus, and extensor carpi radialis brevis [4].
- The flexor-pronator mass consists of the pronator teres, flexor carpi radialis, palmaris longus, flexor carpi ulnaris, and flexor digitorum superficialis [4].
- The common origin of the extensor muscles is attached to the lateral condylar fragment [6].
- The common origin of the extensor muscles can be separated from the lateral epicondyle with a thin flake of bone or divided just distal to the lateral epicondyle [6].
Biomechanics & Motion
- The normal elbow has a range of motion from 0° to 140° from extension to flexion [1].
- The normal elbow has a range of motion of 75° in pronation and 85° in supination [1].
- A functional arc for the elbow is 100° for flexion and extension [1].
- A functional arc for the elbow is 100° for forearm rotation [1].
Investigations
History and Physical Examination
- The physical examination of the elbow is directed by the history and the location of the patient's pain in the anterior, posterior, medial, or lateral aspect of the elbow [1].
- The normal elbow has a range of motion of 75° and 85° in pronation and supination, respectively [1].
- A functional arc for the elbow is 100° for flexion and extension and forearm rotation [1].
- Elbow stability is determined by primary stabilizers, which include the ulnohumeral articulation, the medial ulnar collateral ligament (MUCL), and the lateral ulnar collateral ligament (LUCL) complex [1].
- Secondary stabilizers of the elbow include the radiocapitellar articulation, the common flexor tendon, the common extensor tendon, and the joint capsule [1].
- The ulnar nerve is of utmost importance in the physical examination due to its anatomic proximity to the elbow [9].
- The posterior bundle of the medial collateral ligament (MCL) forms the floor of the cubital tunnel along the course of the ulnar nerve [9].
- Electromyography and nerve conduction velocity studies should be performed if there is any question about neurologic dysfunction [9].
- An assessment for ulnar nerve subluxation should be performed during the physical examination [9].
- Subluxation of the ulnar nerve is a relative contraindication for an arthroscopic procedure secondary to possible iatrogenic nerve injury [9].
- If the elbow has less than 90° to 100° of flexion, the posterior bundle of the medial collateral ligament (MCL) is contracted and must be released to restore flexion [9].
- Pain during the mid-arc of range of motion is more common with intrinsic disease and may not improve with contracture release alone [9].
Imaging
- Plain radiographs remain the hallmark and the best screening test for elbow evaluation [1].
- Standard radiographic views for the elbow include AP, lateral, and oblique views [9].
- Serial radiography is used as follow-up when heterotopic ossification is present [9].
- Primary bony landmarks identified on radiographs include the ulnohumeral joint, coronoid process, radial head, capitellum, radiocapitellar joint, olecranon tip, coronoid/olecranon fossae, and trochlear ridge [9].
- CT is helpful when assessing for malunion architecture and the location and pattern of osteophytes and/or loose bodies [9].
- Three-dimensional CT is used to check for heterotopic ossification [9].
- CT is not necessary when the stiffness is entirely soft-tissue related [9].
- CT is beneficial if any joint incongruity or abnormal bony anatomy is present [9].
- MRI can be used to evaluate ligaments and tendons, but it is rarely indicated for elbow stiffness [9].
- AP, lateral, oblique, and axillary views of the elbow may reveal posteromedial olecranon osteophytes and/or loose bodies in valgus extension overload syndrome [11].
- CT with two-dimensional reconstruction and three-dimensional surface rendering best visualizes the pathology of valgus extension overload syndrome [11].
- MRI may be most helpful in evaluating associated injuries including partial or complete tears of the medial collateral ligament (MCL) in valgus extension overload syndrome [11].
- Radiographic evaluations are essential when diagnosing an osteochondritis dissecans (OCD) lesion of the elbow [12].
- Important aspects of OCD lesions may be better seen with MRI [12].
- Standard AP and lateral radiographs should be obtained for the evaluation of elbow osteoarthritis [13].
- Radiographs for elbow osteoarthritis typically show osteophyte formation at the coronoid process, coronoid fossa, radial fossa, radial head, olecranon tip, and olecranon fossa [13].
- Joint spaces at the ulnohumeral joint are usually preserved in elbow osteoarthritis [13].
- Joint spaces at the radiocapitellar joint are mildly narrowed in elbow osteoarthritis [13].
- Loose bodies may be evident on radiographs, which typically underestimate the number present [13].
- CT may be useful for surgical planning of elbow osteoarthritis, allowing a detailed assessment of osteophytes and the presence of loose bodies [13].
References
[1] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Biomechanics, Physical Examination, and Imaging of the Elbow > Summary and Conclusions.
[3] Orthopaedic Knowledge Update 13 Ebook Without Multimedia. Anatomy, Biomechanics, Physical Examination, and Imaging of the Elbow > Anatomy > Bony Anatomy.
[4] Miller S Review Of Orthopaedics. SECTION 16 PATELLAR TRACKING IN TOTAL KNEE ARTHROPLASTY > TABLE 2.3 Shoulder Spaces.
[6] Campbell S Operative Orthopaedics 4 Volume Set. LATERAL APPROACHES.
[9] Aaos Comprehensive Orthopaedic Review 3. Elbow Stiffness* > IV. Evaluation.
[11] Aaos Comprehensive Orthopaedic Review 3. Elbow Injuries in the Athlete* > III. Valgus Extension Overload Syndrome and Posterior Impingement.
[12] Orthopaedic Knowledge Update. Osteochondritis Dissecans of the Knee and Elbow* > Summary.
[13] Aaos Comprehensive Orthopaedic Review 3. Arthritis and Arthroplasty of the Elbow > I. Osteoarthritis.